Benfotiamine for Diabetic Neuropathy
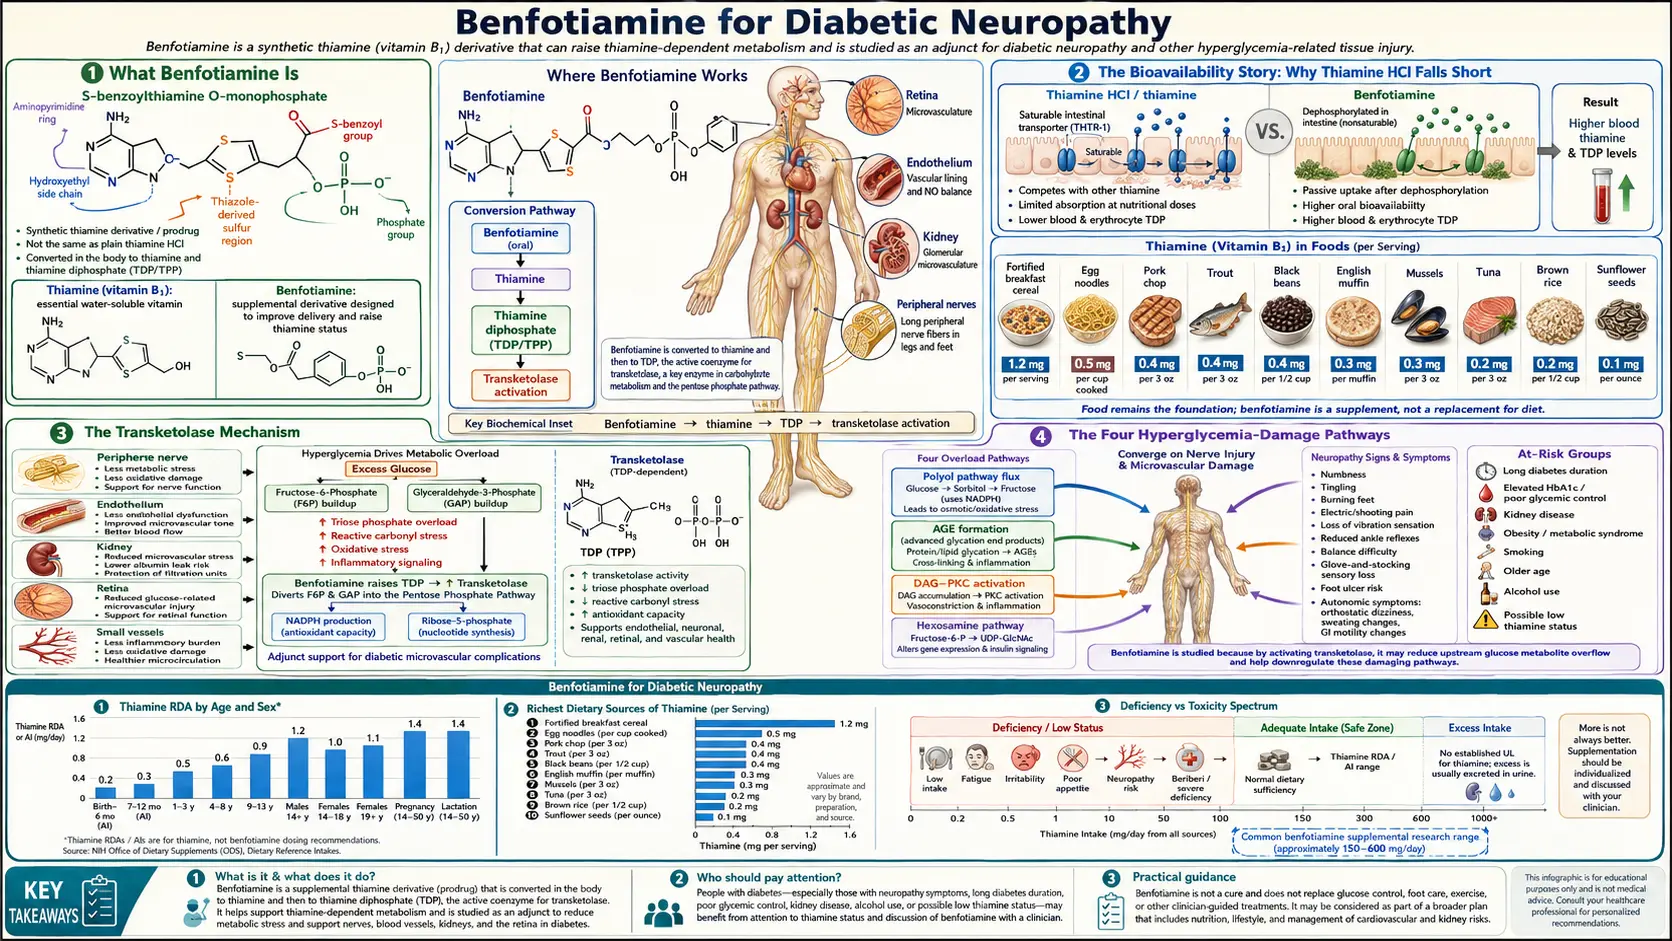
Benfotiamine is the fat-soluble S-acyl derivative of thiamine with significantly higher oral bioavailability than water-soluble thiamine salts in a 1991 study of healthy men, because as a fat-soluble compound it crosses the gut lining by passive diffusion. By driving up intracellular thiamine pyrophosphate (TPP), it activates transketolase, which in a 2003 rat study diverted glycolysis intermediates away from three major hyperglycemia-damage pathways (AGE formation, DAG–PKC and hexosamine). The human evidence is mixed: the 6-week BENDIP trial (Stracke 2008) found a better Neuropathy Symptom Score on benfotiamine in its per-protocol analysis, just short of significance in its intention-to-treat analysis, while the two longest trials so far (24 months in type 1 diabetes and 12 months in type 2 diabetes) found no difference from placebo in nerve function. The 2010 Pan paper on memory often cited alongside them is a study in mice. Benfotiamine + alpha lipoic acid 600 mg is the most-studied non-pharmaceutical nerve-support stack, with complementary mechanisms covered in a mechanism-comparison table below.
Table of Contents
- What Benfotiamine Is
- The Bioavailability Story: Benfotiamine and Thiamine HCl
- The Transketolase Mechanism
- The Four Hyperglycemia-Damage Pathways
- The BENDIP Trial
- Longer Trials: Stracke 1996, Fraser 2012 and BOND
- Hammes 2003 Nature Medicine: Retinopathy
- Benfotiamine vs Alpha Lipoic Acid: A Mechanism Comparison
- Why the Combination Is Widely Used
- Dosing and Practical Use
- Other Applications: Retinopathy, Nephropathy, Cognitive
- Cautions
- Key Research Papers
- Connections
- Featured Videos
What Benfotiamine Is
Benfotiamine is S-benzoylthiamine O-monophosphate, a fat-soluble derivative of thiamine in which the thiazole ring is opened and an S-benzoyl group is attached to the sulfur atom. The compound was developed in Japan in the 1950s as part of a broader effort to create thiamine derivatives that could overcome the absorption limitation of thiamine HCl. It is structurally distinct from the closely-related fat-soluble thiamine derivatives allithiamine (TTFD) and sulbutiamine, and the three have different tissue distribution profiles.
Once absorbed, benfotiamine is rapidly dephosphorylated by serum alkaline phosphatases to S-benzoylthiamine, which crosses cell membranes by passive diffusion. Inside the cell, esterases cleave the S-benzoyl group to release free thiamine, which is then phosphorylated to TPP by thiamine pyrophosphokinase. The end result: a much larger intracellular pool of TPP than achievable with equivalent doses of thiamine HCl.
Benfotiamine has been approved for clinical use in Germany, Austria, Switzerland, Italy, and several Asian countries for decades for the indication of "thiamine deficiency states including diabetic and alcoholic polyneuropathy." It is sold over-the-counter in the United States as a dietary supplement. In Germany it is sold both on its own and as a benfotiamine with vitamins B6 and B12 combination. Manufacturing is now widespread and generic.
The Bioavailability Story: Benfotiamine and Thiamine HCl
The reason benfotiamine matters — the reason it produces clinical effects that oral thiamine HCl does not — is the bioavailability gap. Thiamine HCl is taken up in the small intestine partly by the SLC19A2 and SLC19A3 active transporters, which can be saturated. But ordinary thiamine HCl is not limited to that route. In a 2012 randomized, double-blind crossover study (Smithline and colleagues), healthy people took single doses of 100 mg, 500 mg and 1500 mg thiamine HCl. Blood levels (peak and area under the curve) kept rising across that whole range, though less than in proportion to the dose, with the steepest rise at the lowest doses. The authors concluded that high blood levels of thiamine can be reached rapidly with oral thiamine HCl, because thiamine is absorbed by both an active process and a non-saturable passive process.
Benfotiamine bypasses this transport limitation entirely. As a lipophilic compound, it crosses the intestinal mucosa by passive diffusion. What the 1991 bioavailability study (Bitsch and colleagues) measured:
- In 10 healthy young men, benfotiamine gave significantly higher thiamine levels in blood plasma and in red blood cells (both the peak and the area under the curve) than water-soluble thiamine mononitrate, even though the benfotiamine dose was only 40% as large
- Benfotiamine also raised the activity of the thiamine-dependent enzyme transketolase in red blood cells over the short term, which the authors took as a sign of better effect inside cells
- Time to peak is roughly the same (1.5-2.5 hours) for both forms
The clinical rationale: in chronic conditions where the goal is to drive intracellular TPP above baseline (diabetic neuropathy, retinopathy, nephropathy, cognitive aging), benfotiamine is expected to do more than thiamine HCl; the trials below test that idea, with mixed results. Acute conditions where rapid massive doses are needed (Wernicke encephalopathy, shoshin beriberi) still require parenteral thiamine — even benfotiamine's improved absorption cannot match the brain TPP repletion achievable with intravenous (IV) thiamine.
The other fat-soluble thiamine derivatives (allithiamine/TTFD, sulbutiamine) have similar bioavailability advantages over thiamine HCl, with different tissue-distribution preferences. Benfotiamine accumulates preferentially in nerve, kidney, and liver; allithiamine crosses the blood-brain barrier more readily (and is preferred for cognitive and autonomic indications); sulbutiamine has the best brain penetration and is sometimes used for fatigue and asthenia.
The Transketolase Mechanism
Transketolase is the bridging enzyme of the pentose phosphate pathway (PPP). It transfers two-carbon units between sugar phosphates, allowing fructose-6-phosphate and glyceraldehyde-3-phosphate (the intermediates of glycolysis) to be shunted into the PPP for reduced nicotinamide adenine dinucleotide phosphate (NADPH) and ribose-5-phosphate generation. Transketolase requires TPP as its cofactor.
The breakthrough insight (Hammes et al., Nature Medicine, 2003, in diabetic rats) was that activating transketolase with benfotiamine diverts glucose intermediates away from three major pathways of hyperglycemic damage, and also blocks hyperglycemia-linked NF-kappaB activation. Transketolase converts the glycolysis intermediates glyceraldehyde-3-phosphate and fructose-6-phosphate into pentose sugars, starving these pathways of their raw material:
- Advanced glycation end-product (AGE) formation — from methylglyoxal generated by triose phosphate accumulation
- Protein kinase C (PKC) activation — from accumulated diacylglycerol
- The hexosamine pathway — from accumulated fructose-6-phosphate
A fourth damage pathway often discussed in diabetes — the polyol pathway, in which aldose reductase converts excess glucose to sorbitol — was not one of the three the Hammes study reported. When transketolase activity is high (driven by high intracellular TPP), it pulls fructose-6-phosphate and glyceraldehyde-3-phosphate into the PPP and out of the damage pathways. The downstream consequence in the rat work: reduced AGE formation, reduced PKC activation and reduced hexosamine flux; any effect on polyol pathway flux would be indirect and theoretical. Less biochemical damage to the small blood vessels supplying the nerves, retina, and kidneys means less diabetic complication.
This is mechanistically distinct from how alpha lipoic acid (ALA) works in the same indication. Alpha-lipoic acid addresses the downstream consequences of the damage pathways — mitochondrial superoxide, oxidative stress, antioxidant depletion. Benfotiamine addresses the upstream source — the metabolic flux through the damage pathways themselves. The two approaches are complementary, which is the rationale for combining them (see the mechanism comparison table below).
The Four Hyperglycemia-Damage Pathways
Brownlee's unifying hypothesis (2001) proposed that all the damage pathways in diabetic complications are downstream of a single root cause: mitochondrial superoxide overproduction driven by excess glucose flux through the electron transport chain. The four damage pathways (polyol, AGE, PKC, hexosamine) all increase when mitochondrial superoxide rises, because superoxide inhibits glyceraldehyde-3-phosphate dehydrogenase (GAPDH), causing upstream glycolysis intermediates to back up into the damage pathways.
This is where transketolase activation becomes powerful: it provides an alternative drain for the backed-up glycolysis intermediates. When TPP is high, transketolase pulls fructose-6-phosphate and glyceraldehyde-3-phosphate into the PPP, relieving the upstream pressure that would otherwise feed the damage pathways. Hammes's experimental work showed that benfotiamine reduced retinal capillary cell apoptosis, acellular capillaries, and pericyte loss in diabetic rats — the histologic hallmarks of diabetic retinopathy — and attributed this to transketolase activation blocking three of these pathways (hexosamine, AGE and DAG–PKC) plus NF-kappaB activation.
The clinical relevance: benfotiamine is theoretically capable of addressing all four damage pathways simultaneously through this one upstream intervention. The empirical evidence supports the theory most strongly for neuropathy (the BENDIP trial and the 1996 Stracke combination trial, though the two longest neuropathy trials found no benefit) and retinopathy (the Hammes preclinical work plus several human pilot trials); for nephropathy, a 12-week randomized trial found no fall in urine albumin (see Other Applications).
The BENDIP Trial
The BENDIP trial (Benfotiamine in Diabetic Polyneuropathy — Stracke et al., 2008) was a placebo-controlled, double-blind, randomized trial of 165 patients with diabetic polyneuropathy randomized to one of three arms for 6 weeks:
- Benfotiamine 600 mg/day
- Benfotiamine 300 mg/day
- Placebo
Of 181 people screened, 165 were randomized and 133 were analysed in the intention-to-treat analysis (124 per protocol): 47 on 600 mg, 45 on 300 mg and 41 on placebo. The primary outcome was change in the Neuropathy Symptom Score (NSS, a validated bedside symptom measure).
Results:
- After 6 weeks, the NSS differed significantly between the three groups in the per-protocol analysis (p=0.033); in the intention-to-treat analysis the improvement was just short of significance (p=0.055)
- The Total Symptom Score (TSS) showed no significant difference between groups after 6 weeks; within it, the best results were for pain
- The improvement was more pronounced at the higher (600 mg) dose and grew with treatment duration
- Treatment was well tolerated in all groups
The authors concluded that benfotiamine may extend the treatment options for diabetic polyneuropathy and that further studies should confirm the positive experiences. In clinical practice, 300 mg twice daily (total 600 mg/day) is the most commonly used regimen.
Longer Trials: Stracke 1996, Fraser 2012 and BOND
An earlier double-blind, randomized, controlled trial by Stracke and colleagues (1996) tested a combination of benfotiamine with vitamins B6 and B12 for 12 weeks in 24 people with diabetic polyneuropathy. Nerve conduction velocity in the peroneal nerve (in the leg) improved significantly (p = 0.006), and there was a trend toward better vibration sensing. Nine people on the combination were followed for 9 months, which the authors say supported the results, and no treatment-specific side effects were seen. Because it was a combination, the result cannot be credited to benfotiamine alone.
The two longest benfotiamine trials so far were negative:
- Fraser 2012 (type 1 diabetes, 24 months). 67 people with type 1 diabetes were randomized to benfotiamine 300 mg a day or placebo for 24 months; 59 finished. Blood thiamine and thiamine diphosphate rose markedly on benfotiamine (both p < 0.001 versus placebo), but there was no significant difference between the groups in peripheral nerve function or in blood markers of inflammation.
- BOND (Ziegler 2026, type 2 diabetes, 12 months). 57 people with type 2 diabetes and mild-to-moderate symptomatic neuropathy took benfotiamine 300 mg twice a day or placebo for 12 months. The main measure — the length of nerve fibres in the cornea of the eye, seen with a special microscope — did not differ between groups, and neither did skin-biopsy nerve counts, nerve conduction, sensory testing, heart and sweat-nerve tests, symptom and sign scores, or quality of life. Only the Neuropathy Symptom Score leaned toward benefit (p = 0.098, not significant). All six thiamine measures in the blood rose on benfotiamine, and side-effect rates did not differ from placebo. The authors conclude that 12 months of benfotiamine was well tolerated but had no significant effect on neuropathy.
The evidence base for benfotiamine in diabetic neuropathy is smaller than the alpha-lipoic acid evidence base (ALADIN, SYDNEY, NATHAN trials with ~2000 total patients), and its results are mixed: short-term symptom benefit in BENDIP, no nerve-function benefit in the two longest trials. The combination of benfotiamine and alpha-lipoic acid — addressing different mechanisms — is widely used in integrative-medicine approaches to diabetic neuropathy.
Hammes 2003 Nature Medicine: Retinopathy
Hammes and colleagues' Nature Medicine paper (2003) is the foundational mechanistic paper for benfotiamine in diabetic complications. Using a streptozotocin-induced diabetic rat model of retinopathy, they showed:
- Benfotiamine increased transketolase activity in retinal tissue by 250-400%
- The activation diverted methylglyoxal precursors away from AGE formation
- Hexosamine pathway flux was reduced
- PKC activation was reduced
- The classical histologic markers of diabetic retinopathy (acellular capillaries, pericyte ghosts) were substantially reduced
- The mechanism was specifically attributed to transketolase activation, confirmed by genetic and pharmacologic transketolase blockade
This paper established the modern mechanistic rationale for benfotiamine in diabetic complications and was the impetus for the subsequent human trials. The clinical translation to humans has been most successful in peripheral neuropathy (BENDIP, Stracke 1996), although the longest neuropathy trials were negative, and less successful in retinopathy (where human trials have been smaller and harder to interpret) — but the unified mechanistic framework applies across complications.
Benfotiamine vs Alpha Lipoic Acid: A Mechanism Comparison
Both benfotiamine and alpha lipoic acid (ALA) have robust evidence in diabetic peripheral neuropathy, but their mechanisms are largely complementary rather than overlapping:
| Aspect | Benfotiamine | Alpha Lipoic Acid (ALA) |
|---|---|---|
| Primary mechanism | Transketolase activation diverts glucose intermediates away from damage pathways (upstream) | Mitochondrial superoxide scavenging + antioxidant network regeneration + aldose reductase inhibition (downstream) |
| Polyol pathway | Indirect (reduces upstream substrate) | Direct aldose reductase inhibition |
| AGE formation | Strong upstream block (transketolase diverts methylglyoxal precursors) | Modest direct block via thiol structure |
| PKC activation | Indirect (reduces diacylglycerol substrate) | Indirect via redox restoration |
| Mitochondrial superoxide | Minimal direct effect | Strong direct scavenging |
| Intraneural blood flow | Minimal data | Strong endothelial / NO-mediated improvement |
| Onset of symptom relief | 3-6 weeks | 4-8 weeks (oral) / 1-2 weeks (intravenous) |
| Largest evidence base | BENDIP (Stracke 2008); Hammes Nature Medicine 2003 (rat study) | ALADIN I/II/III, SYDNEY 1/2, NATHAN 1 (4-year) |
| Standard dose | 300 mg twice daily (600 mg/day total) | 600 mg/day racemic or 300 mg/day R-ALA |
| Hypoglycemia risk | Minimal | Meaningful — can lower glucose, monitor closely with insulin / sulfonylureas |
| Cost (US, monthly) | ~$20-30 | ~$15-40 (racemic) / $35-70 (R-ALA) |
The biochemistry makes clear why combining the two is rational: benfotiamine reduces the upstream metabolic flow that drives damage, while alpha-lipoic acid neutralizes the downstream oxidative consequences that have already begun. Hitting both ends of the pathological cascade simultaneously is a more comprehensive intervention than either alone.
Why the Combination Is Widely Used
The benfotiamine 300 mg + alpha lipoic acid 600 mg daily combination is a widely used non-pharmaceutical nerve-support stack for diabetic peripheral neuropathy in integrative medicine and is described as common in parts of European clinical practice. The rationale rests on:
- Mechanistic complementarity — benfotiamine acts upstream on metabolic flux; alpha-lipoic acid acts downstream on oxidative damage. The two together cover the cascade more comprehensively than either alone.
- Largely non-overlapping side effect profiles — benfotiamine was well tolerated in the trials above, with side-effect rates similar to placebo. Alpha-lipoic acid can cause gastrointestinal (GI) upset and hypoglycemia at high doses. The two combine without compounding adverse effects.
- Different tissue distribution — benfotiamine accumulates in nerve, kidney, and liver; alpha-lipoic acid crosses the blood-brain barrier and accumulates in mitochondria everywhere. Together they cover a broader tissue range.
- Clinical evidence for combination — several smaller trials have explicitly tested the combination and found additive or synergistic effects beyond either alone. The combination appears in many integrative-medicine texts.
- Cost is reasonable — the combination costs $35-70/month, comparable to a single brand-name pharmaceutical co-pay.
A protocol described in integrative practice: benfotiamine 300 mg twice daily plus alpha-lipoic acid 600 mg once daily (alpha-lipoic acid usually on an empty stomach), continued for at least 3-6 months to judge response and then long term if benefit is seen. Practitioners add biotin 300 mcg/day because long-term alpha-lipoic acid is thought to deplete biotin. Because alpha-lipoic acid can lower blood sugar, the same practice descriptions include closer glucose monitoring for people on insulin or sulfonylureas, with anticipated dose reductions of 10-25%.
For patients with severe baseline symptoms or treatment-refractory neuropathy, intravenous alpha-lipoic acid induction (600 mg daily for 14-21 days at a nutrient infusion clinic) is sometimes added before transitioning to the long-term oral combination — this produces faster initial symptom relief but does not change the long-term endpoint.
Dosing and Practical Use
- Standard dose — benfotiamine 300 mg twice daily (total 600 mg/day) is the most-studied and most commonly used regimen for diabetic neuropathy.
- Lower dose — benfotiamine 150-300 mg/day is used for maintenance after symptom resolution, or for patients with mild baseline disease, or as part of a broader B-complex maintenance regimen.
- Higher dose — up to 1200 mg/day has been used in severe disease; no clear safety signal at this level but limited evidence for additional benefit over 600 mg/day.
- Timing — with or without food (benfotiamine absorption is not meaningfully affected by food, unlike thiamine HCl).
- Onset of effect — 3-6 weeks for symptom improvement; 3-6 months for objective nerve conduction improvement; sustained improvement requires sustained dosing.
- Duration — practitioners describe it, like alpha-lipoic acid, as long-term use for established diabetic neuropathy; symptoms may regress on discontinuation.
- Combination products — a benfotiamine with vitamins B6 and B12 combination sold in Germany contains benfotiamine 50 mg + vitamin B6 100 mg + vitamin B12 1000 mcg per tablet; the dose is often 3-4 tablets/day. This addresses the fact that many diabetic neuropathy patients also have low B6 and B12 status.
- Magnesium 200-400 mg/day — often taken alongside, because magnesium is required for thiamine phosphorylation to TPP; practitioners describe most diabetic patients as subclinically magnesium-deficient.
- B-complex — a comprehensive B-complex is often taken alongside benfotiamine to address coexisting deficiencies (B6, B12 in particular).
Other Applications: Retinopathy, Nephropathy, Cognitive
Beyond peripheral neuropathy, benfotiamine has been investigated in:
- Diabetic retinopathy — the Hammes 2003 preclinical data is striking, and several small human trials suggest benefit, but no large definitive randomized trial has been completed. The American Diabetes Association does not currently recommend benfotiamine for retinopathy but several integrative practitioners include it in the management plan for early non-proliferative disease.
- Diabetic nephropathy — the mechanism (reduced AGE deposition in glomerular tissue) is biologically plausible, but a 12-week double-blind randomized trial (Alkhalaf 2010) in 82 people with type 2 diabetes and kidney damage, who were already on ACE inhibitor or angiotensin receptor blocker medicines, found that benfotiamine 900 mg a day improved thiamine status but did not reduce urine albumin or the kidney-injury marker KIM-1. Evidence is weaker than for neuropathy.
- Cognitive function in mild Alzheimer's disease — Gibson 2020 conducted a 1-year benfotiamine pilot trial in mild AD that showed promising signals on cognitive outcomes (see the dedicated cognitive function deep-dive). The larger follow-up is BenfoTeam, a randomized, double-blind, placebo-controlled phase 2A–2B trial in early Alzheimer's disease whose protocol was published in 2024: 406 participants treated for 72 weeks, with a first phase choosing between 600 mg and 1200 mg a day.
- Alcohol-related neurocognitive impairment — benfotiamine is sometimes used as part of long-term maintenance after acute Wernicke encephalopathy treatment, taking advantage of its higher oral bioavailability than thiamine HCl.
- Painful peripheral neuropathy of other etiologies — alcoholic neuropathy, chemotherapy-induced peripheral neuropathy (CIPN), and idiopathic small-fiber neuropathy have been investigated in small studies with promising signals.
- Cardiovascular complications of diabetes — small trials suggest benfotiamine reduces endothelial dysfunction and platelet activation, which would predict cardiovascular benefit. Long-term cardiovascular outcome trials have not been done.
Cautions
- Hypersensitivity — rare allergic reactions to benfotiamine have been reported, similar in mechanism to the rare intravenous thiamine anaphylaxis; a rash or whole-body reaction is the sign of such an allergy.
- Drug interactions — minimal. Benfotiamine does not significantly affect cytochrome P450 enzymes or alter the pharmacokinetics of other medications.
- Pregnancy and breastfeeding — benfotiamine is considered safe at standard doses; thiamine itself is required for fetal development. Combination products containing high-dose B6 carry a theoretical risk of B6 nerve damage at very high cumulative doses, a concern raised for pregnancy.
- Renal function — benfotiamine is renally cleared but no dose adjustment is generally needed in chronic kidney disease at standard doses.
- Hypoglycemia — benfotiamine does not significantly affect blood glucose (unlike alpha-lipoic acid). No glucose monitoring intensification is required.
- Not a substitute for glycemic control — benfotiamine works on the metabolic consequences of hyperglycemia but does not lower glucose itself. Standard diabetes management (diet, exercise, metformin or other glucose-lowering medications, insulin if needed) remains the primary intervention.
- Not adequate for acute Wernicke encephalopathy — although benfotiamine has higher bioavailability than thiamine HCl, even benfotiamine cannot deliver enough TPP to the brain fast enough in acute Wernicke. Parenteral thiamine remains the standard of care for that emergency.
- Magnesium status — thiamine phosphorylation requires magnesium. Apparent failure of benfotiamine to produce expected benefit may reflect coexisting magnesium deficiency.
Key Research Papers
- Stracke H et al. (2008). Benfotiamine in diabetic polyneuropathy (BENDIP): results of a randomised, double blind, placebo-controlled clinical study. Exp Clin Endocrinol Diabetes. — PubMed PMID: 18473286
- Stracke H et al. (1996). A benfotiamine-vitamin B combination in treatment of diabetic polyneuropathy. Exp Clin Endocrinol Diabetes. — PubMed PMID: 8886748
- Hammes HP et al. (2003). Benfotiamine blocks three major pathways of hyperglycemic damage and prevents experimental diabetic retinopathy. Nature Medicine. — PubMed PMID: 12592403
- Haupt E et al. (2005). Benfotiamine in the treatment of diabetic polyneuropathy: a three-week randomized, controlled pilot study (BEDIP study). Int J Clin Pharmacol Ther. — PubMed PMID: 15726875
- Winkler G et al. (1999). Effectiveness of different benfotiamine dosage regimens in the treatment of painful diabetic neuropathy. Arzneimittelforschung. — PubMed PMID: 10219465
- Bitsch R et al. (1991). Bioavailability assessment of the lipophilic benfotiamine as compared to a water-soluble thiamine derivative. Ann Nutr Metab. — PubMed PMID: 1776825
- Loew D (1996). Pharmacokinetics of thiamine derivatives especially of benfotiamine. Int J Clin Pharmacol Ther. — PubMed PMID: 8929745
- Stirban A et al. (2006). Benfotiamine prevents macro- and microvascular endothelial dysfunction and oxidative stress following a meal rich in advanced glycation end products in individuals with type 2 diabetes. Diabetes Care. — PubMed PMID: 16936154
- Pan X et al. (2010). Powerful beneficial effects of benfotiamine on cognitive impairment and beta-amyloid deposition in amyloid precursor protein/presenilin-1 transgenic mice. Brain;133(Pt 5):1342-51. — PubMed PMID: 20385653
- Alkhalaf A et al. (2012). Effect of benfotiamine on advanced glycation endproducts and markers of endothelial dysfunction and inflammation in diabetic nephropathy. PLoS One;7(7):e40427. — PubMed PMID: 22792314
- Alkhalaf A et al. (2010). A double-blind, randomized, placebo-controlled clinical trial on benfotiamine treatment in patients with diabetic nephropathy. Diabetes Care;33(7):1598-601. — PubMed PMID: 20413516
- Beltramo E, Nizheradze K, Berrone E, Tarallo S, Porta M (2009). Thiamine and benfotiamine prevent apoptosis induced by high glucose-conditioned extracellular matrix in human retinal pericytes. Diabetes Metab Res Rev;25(7):647-56. — PubMed PMID: 19768736
- Brownlee M (2001). Biochemistry and molecular cell biology of diabetic complications. Nature. — PubMed PMID: 11742414
- Smithline HA, Donnino M, Greenblatt DJ (2012). Pharmacokinetics of high-dose oral thiamine hydrochloride in healthy subjects. BMC Clin Pharmacol;12:4. — PubMed PMID: 22305197
- Fraser DA, Diep LM, Hovden IA, Nilsen KB, Sveen KA, Seljeflot I, Hanssen KF (2012). The effects of long-term oral benfotiamine supplementation on peripheral nerve function and inflammatory markers in patients with type 1 diabetes: a 24-month, double-blind, randomized, placebo-controlled trial. Diabetes Care;35(5):1095-7. — PubMed PMID: 22446172
- Ziegler D, Sipola G, Strom A, et al. (2026). Effects of benfotiamine treatment over 12 months on morphometric, neurophysiological and clinical measures in type 2 diabetes patients with symptomatic polyneuropathy: a randomized, placebo-controlled, double-blind clinical trial (BOND study). BMJ Open Diabetes Res Care;14(1):e005773. — PubMed PMID: 41571333
- Gibson GE, Luchsinger JA, Cirio R, et al. (2020). Benfotiamine and Cognitive Decline in Alzheimer's Disease: Results of a Randomized Placebo-Controlled Phase IIa Clinical Trial. J Alzheimers Dis;78(3):989-1010. — PubMed PMID: 33074237
- Feldman HH, Luchsinger JA, Léger GC, et al.; ADCS BenfoTeam Study Group (2024). Protocol for a seamless phase 2A-phase 2B randomized double-blind placebo-controlled trial to evaluate the safety and efficacy of benfotiamine in patients with early Alzheimer's disease (BenfoTeam). PLoS One;19(5):e0302998. — PubMed PMID: 38809849
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B1 Overview
- B1 Benefits Hub
- B1 for Wernicke-Korsakoff
- B1 for Beriberi & Cardiac
- B1 for Cognition & Alzheimer's
- Alpha Lipoic Acid Overview
- Alpha-Lipoic Acid Benefits Hub
- Alpha-Lipoic Acid for Diabetic Neuropathy
- Alpha-Lipoic Acid for Blood Sugar
- Peripheral Neuropathy
- Diabetes
- Diabetic Complications
- Numbness & Tingling
- Magnesium
- Vitamin B6
- Vitamin B12
- Blood Sugar
- Hemoglobin A1c
- Deficiency
- Toxicity
- History
- Sources