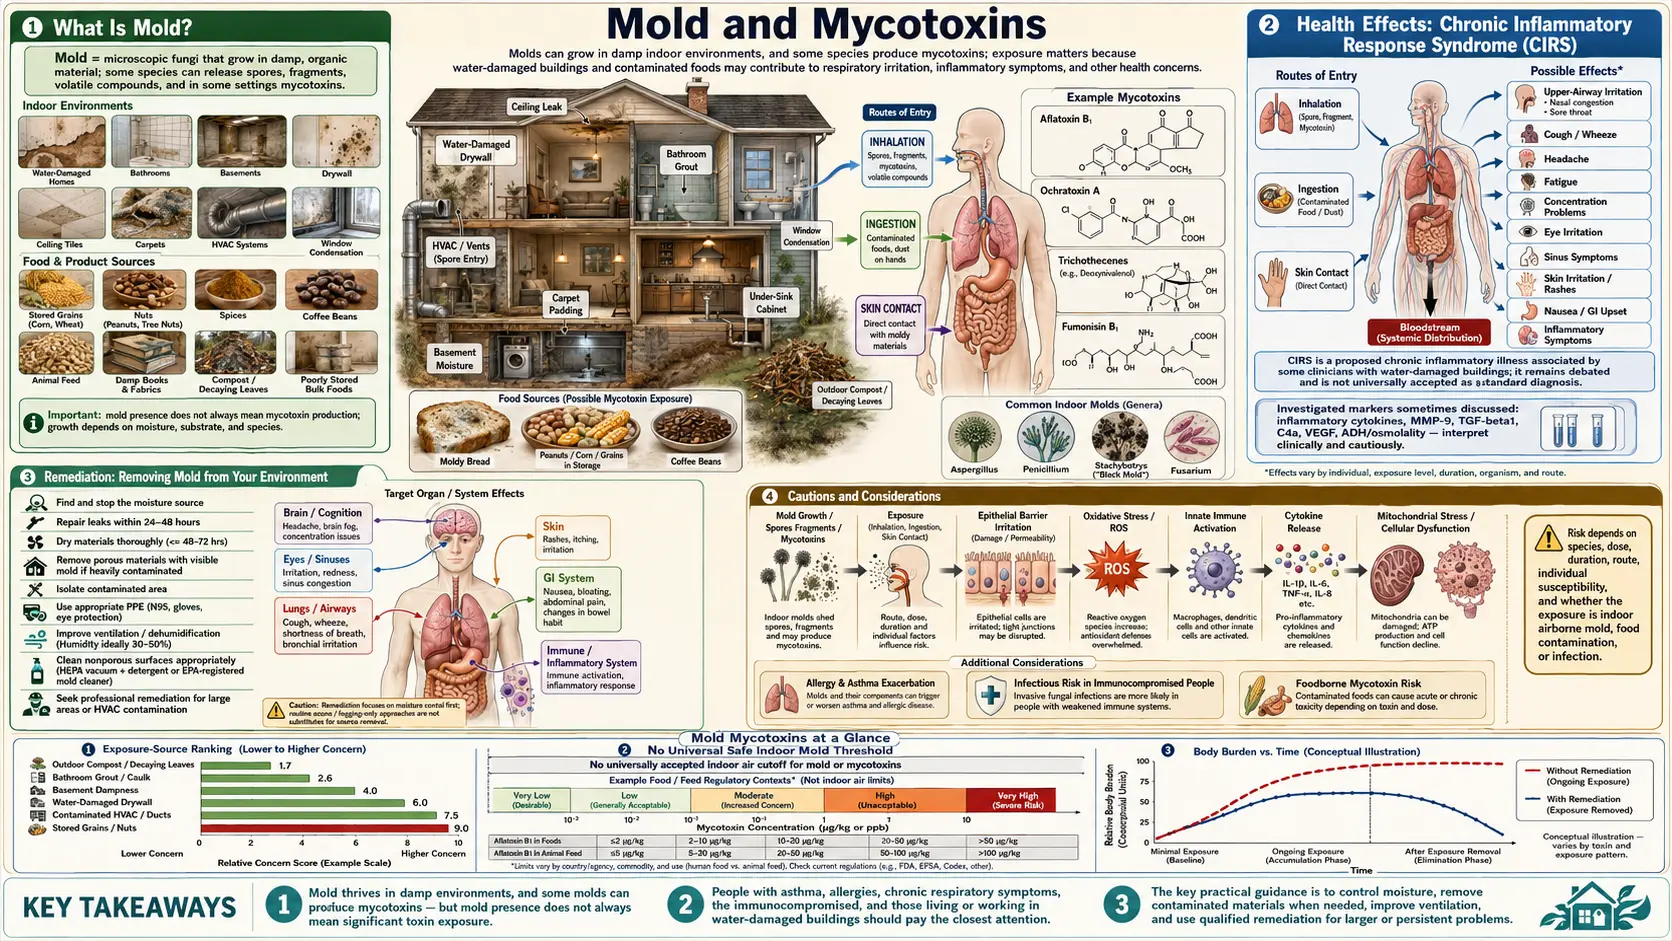
Mold and Mycotoxins

Table of Contents
- What Is Mold?
- What Major Reviews Found
- Common Indoor and Food Molds
- What Are Mycotoxins?
- How Exposure Occurs
- The Cleveland Infant Cluster
- Sick Building Syndrome
- CIRS: A Proposed Diagnosis
- Symptoms: Established and Claimed
- The HLA-DR Susceptibility Claim
- Testing and Its Limits
- Remediation in Agency Guidance
- Detoxification Claims and the Evidence
- Mycotoxins in Food and Their Limits
- Prevention in Agency Guidance
- Known Hazards and Open Questions
- Key Research Papers
- Connections
- Featured Videos
What Is Mold?
Mold is a type of fungus that grows in multicellular filaments called hyphae. Molds are found throughout the natural environment, where they decompose organic matter, and mold spores are present in all indoor environments. Molds grow and multiply indoors only where there is enough moisture, so indoor mold growth points to a water problem: a leak, flooding, condensation or persistently high humidity (Hardin 2003; EPA).
Indoor dampness is common. The World Health Organization's 2009 guidelines estimate that it affects 10–50% of indoor environments in Europe, North America, Australia, India and Japan, and that it is highest in deprived neighbourhoods. A 2011 review notes that the Institute of Medicine (IOM) estimated at least 20% of buildings had dampness problems, and that one estimate put the prevalence of dampness or fungi in U.S. houses at 50% (Mendell 2011).
Some molds can produce toxic compounds called mycotoxins. How much mold-related illness exists beyond allergy and asthma is disputed. Practitioners of naturopathic and functional medicine describe chronic mold illness as under-recognised and underdiagnosed, and often mistaken for chronic fatigue syndrome (Dooley 2024). The major allergy and occupational-medicine bodies describe many proposed mold illnesses as unproven (Bush 2006; Hardin 2003). Both positions are set out below, with their sources.
What Major Reviews Found: Damp Buildings and Health
Two expert reviews are the reference points for indoor mold and health. The IOM report Damp Indoor Spaces and Health (2004) found sufficient evidence of an association between damp indoor environments and upper respiratory tract symptoms, cough, wheeze and asthma symptoms in sensitized people. For the presence of mold or other agents in damp indoor environments it found the same four outcomes plus hypersensitivity pneumonitis in susceptible people. It found limited or suggestive evidence for dyspnoea, asthma development and lower respiratory illness in otherwise healthy children, and inadequate or insufficient evidence for all other health effects it considered. It found no outcome with sufficient evidence of a causal relationship (IOM 2004, as tabulated in WHO 2009).
The WHO guidelines (2009) found sufficient epidemiological evidence that occupants of damp or mouldy buildings are at increased risk of respiratory symptoms, respiratory infections and exacerbation of asthma, and listed associations with asthma development, current asthma, respiratory infections, upper respiratory tract symptoms, cough, wheeze and dyspnoea. WHO also cited clinical evidence that mould and other dampness-related agents increase the risk of rare conditions such as hypersensitivity pneumonitis, allergic alveolitis, chronic rhinosinusitis and allergic fungal sinusitis. A meta-analysis of the studies reviewed by the IOM found that building dampness and mold were associated with roughly 30–50% increases in a variety of respiratory and asthma-related outcomes (Fisk 2007).
The evidence tiers for damp buildings, from the IOM review (2004, as reproduced in the WHO guidelines) and the WHO guidelines (2009), with the claims that neither review established.
The 2003 evidence-based statement of the American College of Occupational and Environmental Medicine (ACOEM) found that, for almost all allergic people, mold reactions are limited to rhinitis or asthma, and that indoor mold is not a source of fungal infection except for people with severely impaired immune systems. It concluded that "current scientific evidence does not support the proposition that human health has been adversely affected by inhaled mycotoxins in home, school, or office environments" (Hardin 2003). The American Academy of Allergy, Asthma & Immunology (AAAAI) 2006 position paper describes the well-defined mold diseases (asthma, allergic rhinitis, allergic bronchopulmonary aspergillosis, sinusitis, hypersensitivity pneumonitis) and states that many newer hypothesised mold-related illnesses "remain largely or completely unproved" (Bush 2006). The paper drew a number of published letters and authors' replies in 2006 and 2008.
Common Indoor and Food Molds
Thousands of mold species exist. These genera are the ones most often discussed for indoor environments and food.
Stachybotrys chartarum ("Black Mold")
- Appearance and habitat: A greenish-black mold that grows on material with a high cellulose content, such as fiberboard, gypsum board and paper (CDC)
- Mycotoxins: Isolates collected from Cleveland homes produced a number of highly toxic compounds in laboratory culture (Jarvis 1998); the main ones discussed are macrocyclic trichothecenes such as the satratoxins
- What is established: The CDC states that no test exists that proves an association between Stachybotrys chartarum and particular health symptoms, and that a possible association with acute idiopathic pulmonary hemorrhage among infants has not been proven (see the Cleveland cluster). The ACOEM statement found that years of study had failed to establish exposure in homes, schools or offices as a cause of adverse human health effects (Hardin 2003)
- Growth conditions: It needs sustained wetness of cellulose-rich material, so it is a marker of chronic water damage
Aspergillus
- Prevalence: A common genus indoors and outdoors. Species often discussed include A. fumigatus, A. flavus, A. niger and A. ochraceus
- Mycotoxins: Aflatoxins (A. flavus, A. parasiticus), ochratoxin A (A. ochraceus and others) and gliotoxin (A. fumigatus)
- Disease: Allergic bronchopulmonary aspergillosis and sinusitis are among the well-defined mold diseases (Bush 2006); invasive fungal infection is largely limited to people with severely impaired immune systems (Hardin 2003)
- Food: A. flavus is a major producer of aflatoxins in stored crops such as peanuts, tree nuts and maize
Penicillium
- Prevalence: Common indoors on damp materials and on spoiling food
- Mycotoxins: Some species produce ochratoxin A (for example P. verrucosum), citrinin or patulin
- Health significance: An allergen in sensitized people and a source of mycotoxins in food
Chaetomium
- Habitat: Water-damaged drywall, wallpaper and other cellulose-rich materials, often alongside Stachybotrys
- Mycotoxins: Chaetoglobosins, among others
Fusarium
- Prevalence: Found in soil and on crops, and a major field contaminant of maize, wheat, barley and other cereal grains
- Mycotoxins: Trichothecenes (including deoxynivalenol, also called vomitoxin, and T-2 toxin), zearalenone (an estrogenic mycotoxin) and fumonisins. Fumonisins and their cancer classification are covered on the corn mycotoxins page
Cladosporium
- Prevalence: One of the most common molds outdoors and indoors, on decaying plant material, damp surfaces and window frames
- Health significance: Not a major mycotoxin producer; an allergen that can trigger allergic rhinitis and asthma in sensitized people. The ACOEM statement notes that outdoor molds, rather than indoor ones, are the most important mold allergens (Hardin 2003)
What Are Mycotoxins?
Mycotoxins are secondary metabolites produced by some molds that are toxic to humans and animals. The best-documented harm comes from eating contaminated food, which has been recognised for centuries (Hardin 2003). Many mycotoxins are chemically stable and survive ordinary food processing, though not all heat equally: roasting temperatures above 180°C, as used for coffee, destroy 70% to more than 90% of ochratoxin A (EFSA 2020, ochratoxin A opinion).
Aflatoxins
- Produced by: Aspergillus flavus and Aspergillus parasiticus
- Classification: The International Agency for Research on Cancer (IARC) classifies naturally occurring mixtures of aflatoxins as carcinogenic to humans (Group 1; IARC Monograph Volume 56, 1993)
- Health effects: Aflatoxins are genotoxic and aflatoxin B1 can cause hepatocellular carcinoma (liver cancer) in humans (EFSA 2020, aflatoxins opinion)
- Food sources: Peanuts, tree nuts, maize, dried fruit and some spices; in Europe, grains and grain-based products made the largest contribution to mean dietary exposure to aflatoxin B1 (EFSA 2020). More detail is on the peanut aflatoxin page
Ochratoxin A (OTA)
- Produced by: Aspergillus and Penicillium species, including A. ochraceus, A. carbonarius and P. verrucosum
- Classification and toxicity: IARC classifies OTA as possibly carcinogenic to humans (Group 2B; IARC Monograph Volume 56, 1993). It causes kidney toxicity in different animal species and kidney tumours in rodents (EFSA 2020)
- Balkan endemic nephropathy: OTA was long suspected as a cause of this kidney disease. EFSA's 2020 opinion states that it is now generally agreed that the disease is associated with toxins other than OTA, namely aristolochic acid from Aristolochia plants (Grollman 2007; EFSA 2020)
- Persistence: In one human volunteer given labelled OTA, the calculated plasma half-life was about 35 days, roughly eight times longer than in rats (Studer-Rohr 2000)
Trichothecenes
- Produced by: Fusarium, Stachybotrys, Myrothecium and other genera
- Mechanism: They inhibit protein synthesis at the ribosome
- Weapons research: T-2 toxin and deoxynivalenol are among the mycotoxins a 2005 threat assessment listed as possible bioterrorism agents (Stark 2005)
Gliotoxin
- Produced by: Aspergillus fumigatus, the most common cause of invasive aspergillosis in people with impaired immunity
- Significance: Studied in laboratory work as an immunosuppressive factor that may help the fungus during infection
Citrinin
- Produced by: Some Penicillium and Aspergillus species, and Monascus purpureus, the fungus used to make red yeast rice
- Toxicity: A kidney toxin in animal studies; it often occurs alongside ochratoxin A
- Red yeast rice: Because Monascus purpureus can produce citrinin, the European Union limits citrinin in red yeast rice food supplements to 100 µg/kg (Vanhee 2024)
How Exposure Occurs
Mycotoxin exposure can occur through ingestion, inhalation and skin contact. For most people, food is the main measured source of mycotoxin exposure (EFSA 2020). Indoors, mold exposure is mostly by inhalation; how much mycotoxin is inhaled is the central point of dispute.
Water-Damaged Buildings
- How common: WHO estimates indoor dampness at 10–50% of indoor environments in the countries it reviewed (WHO 2009)
- Hidden growth: Mold can grow behind walls, above ceiling tiles, beneath flooring and in ductwork without visible signs
- What becomes airborne: Mold releases spores, hyphal fragments and volatile organic compounds. In a laboratory chamber, fungal fragments were released from contaminated surfaces in higher numbers than spores, up to 320 times higher, and shared antigens with the spores (Górny 2002)
- The inhaled-dose question: The ACOEM statement concluded that levels of exposure in the indoor environment, animal dose-response data and dose-rate considerations make delivery of a toxic dose of mycotoxins by inhalation "highly unlikely at best" (Hardin 2003). Proponents of mold-illness models argue that the mixture in damp buildings (fungi, mycotoxins, bacteria, endotoxins and volatile compounds) acts together (Shoemaker 2006)
- Common causes of water intrusion: Roof leaks, plumbing failures, flooding, condensation and poor ventilation
Contaminated Food
- Grains and cereals: Wheat, maize, barley, oats and rye can carry Fusarium mycotoxins (trichothecenes, fumonisins, zearalenone) and aflatoxins
- Nuts: Peanuts, pistachios, Brazil nuts and almonds are among the foods for which aflatoxin limits are set
- Ochratoxin A sources: In EFSA's 2020 assessment, the most important contributors to chronic dietary OTA exposure in Europe were preserved meat, cheese, and grains and grain-based products; dried and fresh fruits such as grapes, figs and dates contributed in some groups of children
- Coffee, wine and beer: OTA is also found in coffee, wine, beer, cocoa and grape juice, which were among the categories in EFSA's earlier 2006 assessment
- Spices: Paprika powder, chilli powder, allspice and cayenne pepper, along with liquorice, were among the 15 food groups with the highest mean OTA levels in EFSA's 2020 dataset
The Cleveland Infant Pulmonary Hemorrhage Cluster
The claim that "black mold" kills infants comes from one investigation. In 1993 and 1994 a cluster of acute pulmonary hemorrhage (bleeding in the lungs) was reported among infants aged 1 to 8 months in Cleveland, Ohio. A case-control study identified major home water damage as a risk factor, and Stachybotrys chartarum isolates collected from the homes produced highly toxic compounds in culture (Jarvis 1998). WHO's account describes the original cluster as 10 infants, reported by the CDC in 1994 and 1997 (WHO 2009).
In 2000 the CDC published the results of internal and external reviews, which found "shortcomings in the implementation and reporting of the investigation" and led the CDC to conclude that a possible association between acute pulmonary hemorrhage/hemosiderosis in infants and Stachybotrys chartarum "was not proven" (CDC 2000). The IOM later concluded that the case-report information was "inadequate or insufficient" to determine whether an association exists (IOM 2004, quoted in WHO 2009). The CDC's current Stachybotrys page repeats that the association "has not been proven".
Sick Building Syndrome
Sick building syndrome describes non-specific symptoms that occupants link to time spent in a particular building, usually without a specific identified cause. A 1997 Lancet review found that objective physiological abnormalities are not generally found and that permanent after-effects are rare, but that symptoms can be uncomfortable or disabling and can make whole workplaces non-functional. It separates sick building syndrome from specific building-related illnesses, which it says should be ruled out first, and describes assessment of both the patient and the building, with ventilation improvements and reduction of contamination sources even when no specific agent has been identified (Redlich 1997).
In a study by the National Institute for Occupational Safety and Health (NIOSH), employees at an extensively water-damaged school (95 people) reported more work-related rashes and nasal, lower respiratory and constitutional symptoms than employees at a comparison school without water damage (110 people) (Thomas 2012).
Chronic Inflammatory Response Syndrome (CIRS): A Proposed Diagnosis
Chronic inflammatory response syndrome (CIRS) is a diagnosis proposed by Maryland physician Ritchie Shoemaker and colleagues for a multi-system illness they attribute to "biotoxins", most often from water-damaged buildings. It is not a diagnosis recognised by the major allergy or occupational-medicine bodies: the AAAAI position paper places such newly hypothesised mold illnesses among those that "remain largely or completely unproved" (Bush 2006), and the ACOEM statement found no support for illness from inhaled indoor mycotoxins (Hardin 2003). The account below is the proponents' model, reported as theirs.
The Proponents' Model
- Mechanism as proposed: In genetically susceptible people, exposure to the mixture of agents in water-damaged buildings is said to trigger a persistent innate-immune inflammatory response. Shoemaker's 2006 model links inflammation with tissue hypoxia (signalled, in his account, by abnormal VEGF levels) and disruption of the hypothalamic proopiomelanocortin pathway (signalled by abnormal leptin and MSH levels), and presents these as testable hypotheses (Shoemaker 2006)
- Markers used: Proponents use a panel including TGF-beta 1, C4a, MMP-9, MSH, VIP, VEGF, ADH and osmolality. These markers are not specific to mold exposure, and their use to diagnose CIRS has not been adopted by the bodies above
- The proponents' protocol: The Shoemaker protocol is described by its proponents as a fixed sequence: removal from exposure, a bile-acid-binding drug (cholestyramine), then a series of steps aimed at nasal staphylococcal colonization (MARCoNS) and at hormone and inflammatory-marker abnormalities. It is reported here as the proponents' method, not as a treatment plan
- How common, according to proponents: A 2024 review written by CIRS practitioners describes CIRS as able to affect up to 25% of the population, and found the Shoemaker protocol described in 11 of the 13 articles it identified on CIRS treatment (Dooley 2024). The authors disclose that two of them give expert-witness testimony in CIRS cases
The Main Clinical Study
The most cited study is a 2006 case series with an embedded blinded trial (Shoemaker 2006). Of 28 patients enrolled, 26 completed all five time points. After 2 weeks of cholestyramine the group mean fell from 23 of 37 symptoms to 4, and visual contrast sensitivity improved; after the participants spent 3 days back in the buildings without the drug, all reported relapse. In the double-blind part, 7 participants given cholestyramine improved over 2 weeks while 6 given placebo did not, until they too received cholestyramine. The trial was small and run by the protocol's developer; it has not been replicated by an independent group in the sources reviewed here. The page on binders, charcoal and chlorella covers cholestyramine's label and the binder evidence in more detail.
Symptoms: What Is Established and What Is Claimed
The two groups of symptoms below rest on very different evidence.
Respiratory and Allergic Symptoms (Associated with Damp Buildings)
- Upper respiratory symptoms: Nasal congestion, sneezing and throat irritation (IOM 2004; WHO 2009)
- Lower respiratory symptoms: Cough and wheeze; worsening of asthma in sensitized people; shortness of breath (dyspnoea), which WHO moved to the sufficient-evidence tier
- Respiratory infections: Associated with damp or mouldy buildings in the WHO review
- Rare immune lung disease: Hypersensitivity pneumonitis in susceptible people, documented by clinical evidence
- Sinus disease: WHO cites clinical evidence for chronic rhinosinusitis and allergic fungal sinusitis
Symptoms Attributed by Mold-Illness Proponents
Practitioners who diagnose CIRS or "mold toxicity" describe a multi-symptom, multi-system illness (Dooley 2024) and attribute a much wider list of symptoms to mold, including fatigue, brain fog and memory problems, headaches, dizziness, joint and muscle pain, abdominal symptoms, skin rashes, mood changes, excessive thirst and frequent urination, and hormone disturbances. In Shoemaker's 2006 series, participants reported a group mean of 23 of the 37 symptoms evaluated (Shoemaker 2006). The IOM placed "all other health effects considered", beyond the respiratory outcomes above, in its inadequate-or-insufficient-evidence tier (IOM 2004). A 2025 systematic review by two CIRS practitioners, one of whom discloses an equity stake in mold-related businesses, analysed six articles (five cross-sectional) and concluded that fatigue is associated with indoor mold and dampness (Dooley 2025); the IOM and WHO reviews do not list fatigue among established effects. Because these symptoms are common and non-specific, many conditions can produce them; the chronic fatigue syndrome page covers one of the main alternatives.
The HLA-DR Susceptibility Claim
CIRS proponents hold that particular HLA-DR genotypes explain why some people in a damp building become ill while others do not.
- What HLA genes are: Human leukocyte antigen (HLA) genes code for proteins that present foreign substances to the immune system. Certain HLA types are well established as risk factors for some autoimmune diseases
- The proponents' claim: Proponents state that a sizeable minority of the population carries "mold-susceptible" HLA-DR haplotypes that impair clearance of biotoxins, and that people with "multi-susceptible" genotypes have the most severe illness. These figures and categories come from the proponents' own clinical work
- Status: HLA-DR typing is an ordinary laboratory test, but its use to diagnose CIRS or predict mold illness is not part of the positions of the AAAAI or ACOEM (Bush 2006; Hardin 2003), and the sources reviewed here include no independent validation of the susceptibility categories
- Family clustering: Proponents cite illness in several members of one household as support for inherited susceptibility; shared exposure in the same building is an alternative explanation
Testing for Mold Exposure: Homes, Bodies and Their Limits
Agency guidance and the mold-illness literature differ most sharply on testing.
What the Agencies Say About Testing Homes
- CDC: "CDC does not recommend mold testing", because health effects vary between people and "there are no set standards for what is and what is not an acceptable quantity of different kinds of mold in a home." The CDC adds that it is not necessary to determine what type of mold is growing
- EPA: "In most cases, if visible mold growth is present, sampling is unnecessary"
- Research reviews: A 2011 review of the epidemiologic evidence found that measured microbiologic agents in dust had only limited, partly contradictory associations with health, and that "current evidence does not support measuring specific indoor microbiologic factors to guide health-protective actions" (Mendell 2011)
ERMI and HERTSMI-2
- ERMI (Environmental Relative Moldiness Index): Developed by EPA researchers from dust samples taken in a nationally representative 1096 U.S. homes, using quantitative PCR for 36 indicator mold species. Its developers concluded that the scale "may be useful for home mold-burden estimates in epidemiological studies" (Vesper 2007); it was built as a research tool
- HERTSMI-2: A shorter score derived by CIRS proponents from a subset of ERMI species, with thresholds they set for whether a building is suitable for a person with CIRS. It has not been adopted by the agencies above
Urine Mycotoxin Testing
- What it is: Commercial urine tests report mycotoxins such as aflatoxins, ochratoxin A and trichothecenes in urine, often after a "provocation" step (glutathione, sauna or exercise) that some practitioners use before collection; the sources reviewed here include no validation of that step
- The supporting studies: A 2009 paper, written partly by staff of a testing laboratory, reported trichothecenes, aflatoxins and ochratoxins in urine, sputum and tissue from mold-exposed patients and none in negative controls (Hooper 2009). A 2013 study found at least one mycotoxin in the urine of 104 of 112 patients (93%) with chronic fatigue syndrome, compared with no positives among 55 controls tested earlier by the same laboratory (Brewer 2013)
- The criticism: An environmental epidemiologist who co-authored the 2009 WHO guidelines argued that the 2013 study's control group made the comparison invalid: controls were chosen for having no reported mold exposure, rather than from the same population as the patients (Mendell 2016). Ochratoxin A from ordinary food is also found in human plasma (Studer-Rohr 2000), and EFSA notes that blood, urine and breast-milk methods for OTA have been used extensively in population biomonitoring studies (EFSA 2020)
- Agency position: None of the agency or professional-society sources reviewed here endorses urine mycotoxin tests for diagnosing mold-related illness
Visual Contrast Sensitivity (VCS) Test
- What it measures: The ability to detect differences in contrast. Proponents use it as a screening test for biotoxin illness (Shoemaker 2006)
- Independent evaluation: In the NIOSH school study, VCS values were lower among employees of the water-damaged school, but the investigators wrote: "we do not recommend using it in evaluation of people exposed to mold" (Thomas 2012)
Blood Markers Used in CIRS Practice
- The panel: TGF-beta 1, MMP-9, MSH, C4a, VEGF, VIP, ADH and osmolality, as described in the CIRS model above. At the first time point of Shoemaker's 2006 series, MSH was abnormal in 25 participants, MMP-9 in 22, VEGF in 14 and leptin in 13 (Shoemaker 2006)
- Limits: These are general markers of inflammation or hormone status; none is specific to mold, and none is part of the agency or AAAAI guidance on mold
Remediation: What Agency Guidance Describes
Agency guidance and the ACOEM statement agree that the moisture source comes first: where mold grows indoors there is an inappropriate source of water that must be corrected before remediation can succeed (Hardin 2003).
- Drying: EPA: "It is important to dry water-damaged areas and items within 24-48 hours to prevent mold growth." The CDC gives the same 24–48 hours after flooding
- Small versus large jobs: EPA: "If the moldy area is less than about 10 square feet (less than roughly a 3 ft. by 3 ft. patch), in most cases, you can handle the job yourself." For more than 10 square feet of mold or a lot of water damage, EPA points to its guide for schools and commercial buildings; for damage caused by sewage or other contaminated water, EPA's guidance is to "call in a professional"
- Porous materials: EPA: "Absorbent or porous materials, such as ceiling tiles and carpet, may have to be thrown away if they become moldy"
- Hard surfaces: The CDC states that mold can be removed from hard surfaces with household products, soap and water, or a dilute bleach solution
- Protection during cleanup: EPA's guide notes that an N-95 respirator may be worn, and that it must fit properly
- Belongings: Some mold-illness practitioners describe discarding porous belongings such as upholstered furniture and mattresses; this goes beyond the agency guidance cited here
Detoxification Claims and the Evidence
Mold-illness practitioners describe "detoxification" regimens after exposure ends. A 2013 practitioner review covers glutathione, antioxidants, antifungals, sequestering agents (cholestyramine, charcoal, clay, chlorella), probiotics and induced sweating (Hope 2013). The evidence behind each part differs; no doses are given here.
Binding Agents
- Cholestyramine: A prescription bile-acid-binding resin, central to the Shoemaker protocol. Its human evidence for mold illness is the small 2006 study described above (Shoemaker 2006)
- Colesevelam: Another prescription bile-acid sequestrant, which some practitioners use as an alternative; no trial in mold illness was found in the sources reviewed here
- Clay: In a 3-month randomised trial in Ghanaians with high dietary aflatoxin exposure, capsules of a calcium montmorillonite clay reduced blood and urine aflatoxin biomarkers, with up to a 58% decrease in median urinary aflatoxin M1 in the higher-dose group (Wang 2008). This concerns dietary aflatoxin, not mold illness. See bentonite clay
- Chlorophyllin: In a randomised, placebo-controlled trial in 180 adults in Qidong, China, a region with high dietary aflatoxin exposure, chlorophyllin taken with meals reduced a urinary aflatoxin-DNA adduct biomarker by 55% compared with placebo (Egner 2001). This too concerns dietary aflatoxin; chlorella itself was not tested
- Activated charcoal: A non-specific adsorbent; the binder page linked above summarises its evidence. No controlled trial in mold illness was found in the sources reviewed here
Glutathione, NAC and Antioxidants
- The claim: Practitioners state that mycotoxin exposure depletes glutathione and use glutathione, N-acetyl cysteine, vitamin C or alpha-lipoic acid to support it (Hope 2013)
- The evidence: The sources reviewed here include no randomised trials of these supplements in people with mold-related illness; the support offered is mechanistic and from laboratory and animal studies
Sweating and Sauna
- The claim: Some practitioners use sauna or exercise-induced sweating on the theory that mycotoxins leave the body in sweat (Hope 2013). An uncontrolled case series of 100 mold-exposed patients reported improvement with regimens that included antigen injections, sauna, oxygen therapy and nutrients (Rea 2018)
- The evidence: Case series have no comparison group, so improvement cannot be attributed to the treatment. The sources reviewed here include no controlled trial of sauna for mold illness
Mycotoxins in the Food Supply and Their Limits
Unlike indoor mold, dietary mycotoxins are regulated with numeric limits, because their harm at high intake is well documented.
- U.S. FDA: The FDA's action level for aflatoxins is 20 parts per billion (ppb) in foods, including peanuts and peanut products, Brazil nuts and pistachio nuts, and 0.5 ppb for aflatoxin M1 in milk
- European Union: The EU sets maximum levels for aflatoxin B1 and for total aflatoxins in tree nuts, peanuts and other oilseeds, dried fruit, cereals and some spices, with separate aflatoxin B1 limits for baby foods (EFSA 2020). EFSA has assessed the public-health effect of a proposed increase in the EU limit for total aflatoxins in peanuts for direct consumption from 4 to 10 µg/kg. The EU has also set maximum levels for ochratoxin A in a range of foods since 2006, though not for meat (Vlachou 2022)
- Codex Alimentarius: International limits are negotiated in the Codex Committee on Contaminants in Food; at its 2018 session, discussions on a limit for total aflatoxins in ready-to-eat peanuts were suspended because of divergent views (EFSA 2020)
- EFSA's risk conclusions: For aflatoxin B1, EFSA's 2020 margins of exposure raised a health concern. For ochratoxin A, margins for non-cancer kidney effects indicated low concern for most consumers but a possible concern for high consumers in younger age groups, with high uncertainty (EFSA 2020)
- Cheese: Cheese was one of the three largest contributors to dietary ochratoxin A in EFSA's assessment
Prevention in Agency Guidance
WHO's guidelines state: "The most important means for avoiding adverse health effects is the prevention (or minimization) of persistent dampness and microbial growth on interior surfaces and in building structures" (WHO 2009). A review of the epidemiology reached a similar conclusion: prevention and remediation of indoor dampness and mold are likely to reduce health risks (Mendell 2011).
Home and Building Measures in Agency Guidance
- Humidity: EPA: "Keep indoor humidity below 60 percent (ideally between 30 and 50 percent) relative humidity." CDC: humidity "no higher than 50%"
- Leaks and drying: Agency guidance centres on fixing leaks and drying wet materials within 24–48 hours (EPA; CDC)
- Ventilation: EPA's guide describes venting moisture-producing appliances such as clothes dryers and stoves to the outside where possible, and running the bathroom fan or opening the window when showering
- Materials: Carpet and other porous materials in persistently damp areas are harder to dry and may need replacing if they become moldy (EPA)
Dietary Exposure
- How exposure is controlled: Regulators control dietary mycotoxins mainly through maximum levels and monitoring (see above)
- Diet pattern: Because different foods carry different mycotoxins, total exposure depends on the overall diet; EFSA's assessments estimate exposure across whole diets rather than single foods
Known Hazards and Open Questions
- Disturbing mold releases particles: Fungal fragments and spores are released from contaminated surfaces when disturbed (Górny 2002); EPA's guidance distinguishes small cleanups from larger jobs
- Cholestyramine is a prescription drug: Its label lists constipation as the most common adverse reaction and warns that long-term use can impair absorption of fat-soluble vitamins (A, D, E and K); see the binders page
- Binders bind medicines: Cholestyramine, charcoal and clay can reduce absorption of other medicines and nutrients taken at the same time
- Testing limits: No agency standard defines a safe or unsafe indoor mold level (CDC); urine mycotoxin results lack an appropriate reference population in the published studies (Mendell 2016); provocation protocols are not standardised
- Overlapping symptoms: Symptoms attributed to mold illness are common and overlap with many other conditions, which is why the bodies above stress the difference between established respiratory effects and proposed syndromes
- Who is most affected: The research raises the clearest concern for people with asthma, allergies to mold, chronic lung disease or severely impaired immune systems (CDC; Hardin 2003)
- Psychological impact: Patients and practitioners describe disbelief from others as a common experience for people who attribute their illness to their home
- Clinical decisions: Decisions about testing, medicines and supplements belong with a clinician
Key Research Papers
- World Health Organization Regional Office for Europe (2009). WHO guidelines for indoor air quality: dampness and mould. ISBN 978 92 890 4168 3 — WHO publication page
- Institute of Medicine, Committee on Damp Indoor Spaces and Health (2004). Damp Indoor Spaces and Health. National Academies Press — doi:10.17226/11011
- Mendell MJ, Mirer AG, Cheung K, Tong M, Douwes J (2011). Respiratory and allergic health effects of dampness, mold, and dampness-related agents: a review of the epidemiologic evidence. Environmental Health Perspectives 119(6):748-56 — PubMed PMID: 21269928
- Fisk WJ, Lei-Gomez Q, Mendell MJ (2007). Meta-analyses of the associations of respiratory health effects with dampness and mold in homes. Indoor Air 17(4):284-96 — PubMed PMID: 17661925
- Bush RK, Portnoy JM, Saxon A, Terr AI, Wood RA (2006). The medical effects of mold exposure. Journal of Allergy and Clinical Immunology 117(2):326-33 (AAAAI position paper; errata published) — PubMed PMID: 16514772
- Hardin BD, Kelman BJ, Saxon A (2003). Adverse human health effects associated with molds in the indoor environment. Journal of Occupational and Environmental Medicine 45(5):470-8 (ACOEM evidence-based statement) — PubMed PMID: 12762072
- Centers for Disease Control and Prevention (2000). Update: Pulmonary hemorrhage/hemosiderosis among infants—Cleveland, Ohio, 1993-1996. MMWR Morbidity and Mortality Weekly Report 49(9):180-4 — PubMed PMID: 11795499
- Jarvis BB, Sorenson WG, Hintikka EL, Nikulin M, Zhou Y, Jiang J, Wang S, Hinkley S, Etzel RA, Dearborn D (1998). Study of toxin production by isolates of Stachybotrys chartarum and Memnoniella echinata isolated during a study of pulmonary hemosiderosis in infants. Applied and Environmental Microbiology 64(10):3620-5 — PubMed PMID: 9758776
- Shoemaker RC, House DE (2006). Sick building syndrome (SBS) and exposure to water-damaged buildings: time series study, clinical trial and mechanisms. Neurotoxicology and Teratology 28(5):573-88 — PubMed PMID: 17010568
- Dooley M, Vukelic A, Jim L (2024). Chronic inflammatory response syndrome: a review of the evidence of clinical efficacy of treatment. Annals of Medicine and Surgery 86(12):7248-7254 — PubMed PMID: 39649915
- Dooley M, McMahon SW (2025). Fatigue and exposure to mold and/or dampness: a systematic review of the literature from 2011-2018. Environmental Analysis Health and Toxicology 40(3):e2025018 — PubMed PMID: 41265402
- Thomas G, Burton NC, Mueller C, Page E, Vesper S (2012). Comparison of work-related symptoms and visual contrast sensitivity between employees at a severely water-damaged school and a school without significant water damage. American Journal of Industrial Medicine 55(9):844-54 — PubMed PMID: 22566108
- Hooper DG, Bolton VE, Guilford FT, Straus DC (2009). Mycotoxin detection in human samples from patients exposed to environmental molds. International Journal of Molecular Sciences 10(4):1465-75 — PubMed PMID: 19468319
- Brewer JH, Thrasher JD, Straus DC, Madison RA, Hooper D (2013). Detection of mycotoxins in patients with chronic fatigue syndrome. Toxins 5(4):605-17 — PubMed PMID: 23580077
- Mendell MJ (2016). Comment on Detection of Mycotoxins in Patients with Chronic Fatigue Syndrome. Toxins 2013, 5, 605-617. Toxins 8(11):324 — PubMed PMID: 27827984
- Vesper S, McKinstry C, Haugland R, Wymer L, Bradham K, Ashley P, Cox D, Dewalt G, Friedman W (2007). Development of an Environmental Relative Moldiness index for US homes. Journal of Occupational and Environmental Medicine 49(8):829-33 — PubMed PMID: 17693779
- Górny RL, Reponen T, Willeke K, Schmechel D, Robine E, Boissier M, Grinshpun SA (2002). Fungal fragments as indoor air biocontaminants. Applied and Environmental Microbiology 68(7):3522-31 — PubMed PMID: 12089037
- Redlich CA, Sparer J, Cullen MR (1997). Sick-building syndrome. Lancet 349(9057):1013-6 — PubMed PMID: 9100639
- EFSA Panel on Contaminants in the Food Chain (CONTAM), Schrenk D, Bignami M, Bodin L, et al. (2020). Risk assessment of aflatoxins in food. EFSA Journal 18(3):e06040 — PubMed PMID: 32874256
- EFSA Panel on Contaminants in the Food Chain (CONTAM), Schrenk D, Bodin L, Chipman JK, et al. (2020). Risk assessment of ochratoxin A in food. EFSA Journal 18(5):e06113 — PubMed PMID: 37649524
- Studer-Rohr I, Schlatter J, Dietrich DR (2000). Kinetic parameters and intraindividual fluctuations of ochratoxin A plasma levels in humans. Archives of Toxicology 74(9):499-510 — PubMed PMID: 11131029
- Grollman AP, Shibutani S, Moriya M, et al. (2007). Aristolochic acid and the etiology of endemic (Balkan) nephropathy. Proceedings of the National Academy of Sciences of the USA 104(29):12129-34 — PubMed PMID: 17620607
- Vlachou M, Pexara A, Solomakos N, Govaris A (2022). Ochratoxin A in slaughtered pigs and pork products. Toxins 14(2):67 — PubMed PMID: 35202095
- Vanhee C, Jacobs B, Canfyn M, Malysheva SV, Willocx M, Masquelier J, Van Hoorde K (2024). Quality control and safety assessment of online-purchased food supplements containing red yeast rice (RYR). Foods 13(12):1919 — PubMed PMID: 38928859
- Stark AA (2005). Threat assessment of mycotoxins as weapons: molecular mechanisms of acute toxicity. Journal of Food Protection 68(6):1285-93 — PubMed PMID: 15954722
- Egner PA, Wang JB, Zhu YR, et al. (2001). Chlorophyllin intervention reduces aflatoxin-DNA adducts in individuals at high risk for liver cancer. Proceedings of the National Academy of Sciences of the USA 98(25):14601-6 — PubMed PMID: 11724948
- Wang P, Afriyie-Gyawu E, Tang Y, et al. (2008). NovaSil clay intervention in Ghanaians at high risk for aflatoxicosis: II. Reduction in biomarkers of aflatoxin exposure in blood and urine. Food Additives and Contaminants Part A 25(5):622-34 — PubMed PMID: 18478481
- Hope J (2013). A review of the mechanism of injury and treatment approaches for illness resulting from exposure to water-damaged buildings, mold, and mycotoxins. ScientificWorldJournal 2013:767482 — PubMed PMID: 23710148
- Rea WJ (2018). A large case-series of successful treatment of patients exposed to mold and mycotoxin. Clinical Therapeutics 40(6):889-893 — PubMed PMID: 29861191
- International Agency for Research on Cancer (1993). Some Naturally Occurring Substances: Food Items and Constituents, Heterocyclic Aromatic Amines and Mycotoxins. IARC Monographs Volume 56 — IARC publication page
- Centers for Disease Control and Prevention. About Mold and Facts About Stachybotrys chartarum — CDC mold page
- U.S. Environmental Protection Agency. A Brief Guide to Mold, Moisture and Your Home — EPA guide
- U.S. Food and Drug Administration. Guidance for Industry: Action Levels for Poisonous or Deleterious Substances in Human Food and Animal Feed — FDA guidance
PubMed Topic Searches
Connections
- All Toxins
- Bentonite Clay — the aflatoxin-binding evidence behind the binder protocols
- NAC and Glutathione
- NAC
- Vitamin C
- Detoxification
- Sinusitis
- Asthma
- Fatigue
- Brain Fog
- Chronic Cough
- Shortness of Breath
- Chronic Fatigue Syndrome
- Adrenal Fatigue
- Heavy Metals
- Oxidative Stress
- Chlorella
- Leaky Gut
- Inflammatory Markers
- Turmeric
- Household Chemicals
- EMF Exposure
- Dioxins
- Detox Protocols
Featured Videos