⚠ Evidence warning: Clinical trials or other evidence do not support the claim that methylselenol gives selenium chemopreventive properties in people. This page keeps it as a report of what people, websites or other media say.
Selenium — Benefits Deep Dive
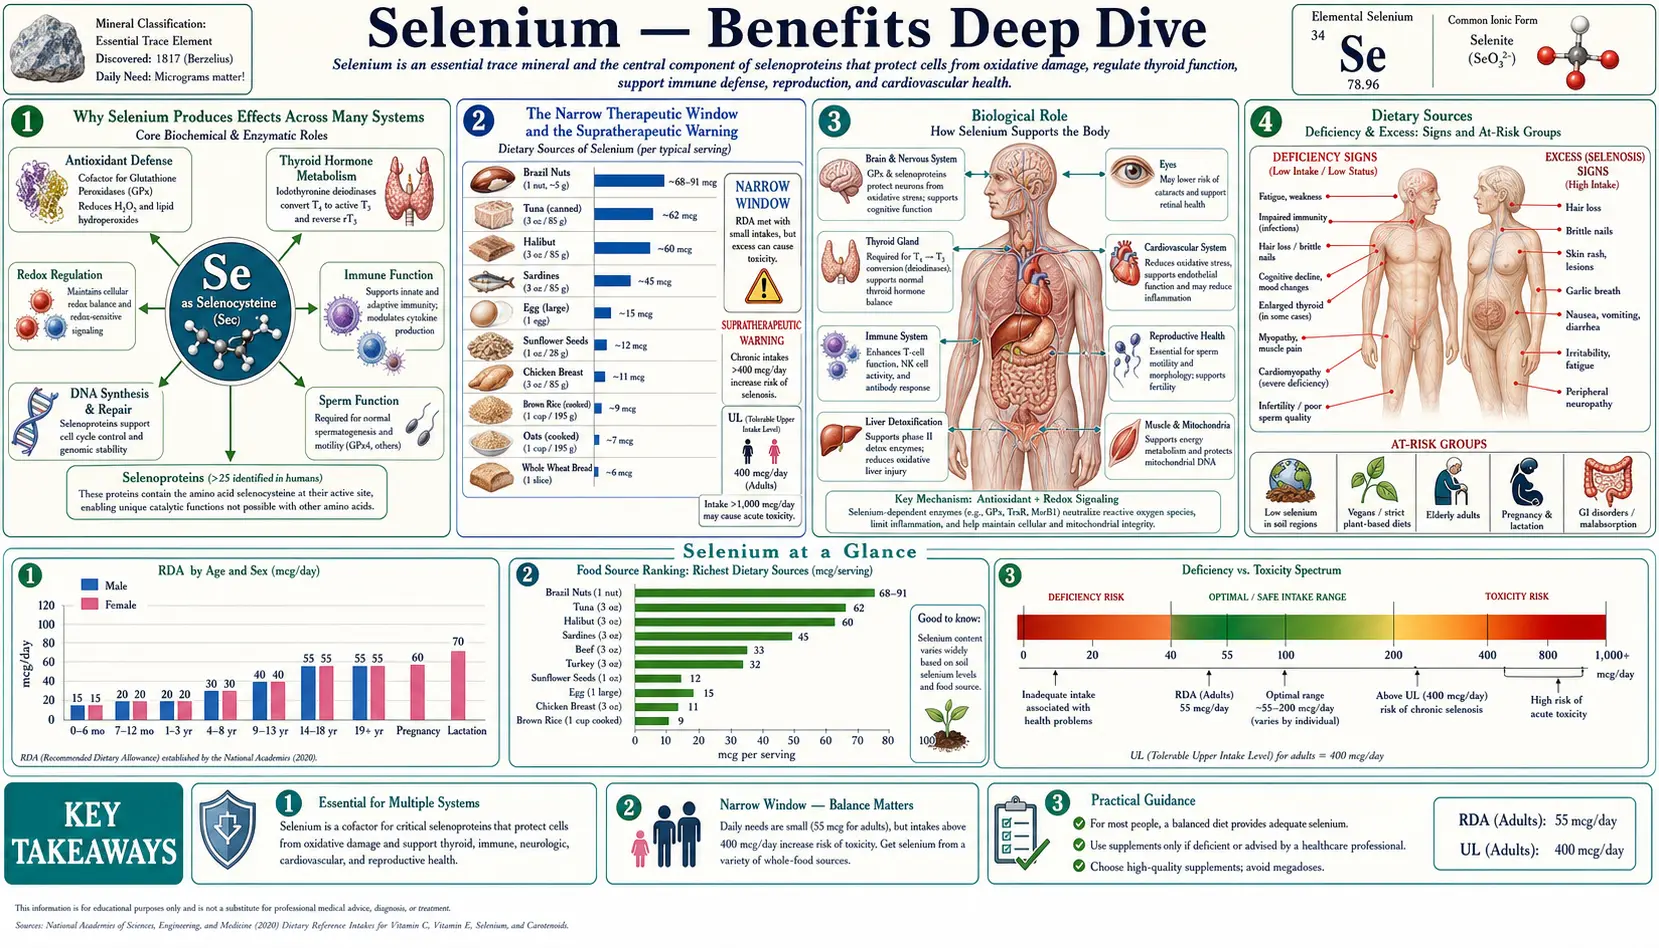
Selenium is a trace element with one of the narrower therapeutic windows among the essential nutrients. The adult Recommended Dietary Allowance (RDA) is just 55 micrograms per day; the tolerable upper intake level is 400 micrograms per day. That is a seven-fold gap between requirement and upper limit. For comparison, in the same US tables vitamin C runs from 90 mg (men) or 75 mg (women) up to 2,000 mg, a far wider gap; zinc runs from 11 mg (men) or 8 mg (women) up to 40 mg, a narrower gap than selenium's; and magnesium's 350 mg upper limit applies only to supplements, so no food-based comparison exists. A single Brazil nut harvested from selenium-rich Brazilian soil can contain anywhere from 5 to 100+ micrograms — eating 6 to 10 per day for months is described as a way to reach selenosis (selenium poisoning), and the European Food Safety Authority says regular Brazil nut eaters may go over its upper limit. Within that narrow window, however, selenium is indispensable. It is the only trace element with its own dedicated amino acid (selenocysteine, the 21st amino acid) and its own dedicated co-translational insertion machinery. The four deep-dive pages below explore the four clinical territories where selenium produces the largest, best-characterized effects — cellular antioxidant defense via the selenoprotein family, autoimmune and synthetic regulation of thyroid hormone, the unusual immune effects that include preventing viral mutation and the prostate-cancer signal from the Selenium and Vitamin E Cancer Prevention Trial (SELECT), and the prostate-cancer-prevention story whose early enthusiasm from the Nutritional Prevention of Cancer (NPC) trial was substantially tempered by that later trial.
Deep-Dive Articles
Antioxidant Defense
The eight glutathione peroxidase isoforms (GPx1–8; GPx1–4 and GPx6 contain selenium, GPx5, GPx7 and GPx8 do not) each guarding a different cellular compartment, the three thioredoxin reductases (TrxR1–3), methionine sulfoxide reductase B1, selenoprotein P as the brain-and-testis selenium transport vehicle, the strange UGA-codon read-through translational machinery that makes selenocysteine the 21st amino acid, the dietary selenoamino acids (selenomethionine, selenocysteine, methylselenocysteine), Brazil-nut soil variability that drives selenosis, and the marine selenoneine that concentrates in tuna mitochondria.
Read the deep dive →Immune Function
The Keshan disease / Coxsackievirus B3 story — how selenium deficiency in the host selects for more virulent viral variants, the six nucleotide changes that turned a benign cloned Coxsackievirus B3 into a heart-damaging strain after it passed through selenium-deficient mice, T-cell proliferation and Th1/Th2 balance, macrophage M1/M2 polarization, natural killer (NK) cell cytotoxicity, the HIV CD4 / selenium relationship, influenza severity, the controversial SISPCT high-dose intravenous (IV) selenium sepsis trial, and the SELECT high-grade prostate cancer signal that has reframed adult selenium supplementation.
Read the deep dive →Thyroid Function
The thyroid contains more selenium per gram of tissue than any other organ. Iodothyronine deiodinases (DIO1, DIO2, DIO3) activate and inactivate thyroid hormone; glutathione peroxidases (especially GPx3 in the follicular lumen) quench the H2O2 generated during thyroid hormone synthesis; selenium repletion lowers anti-TPO antibodies by 20–40% in Hashimoto's, is listed, for selenium-deficient areas, among the measures usually sufficient in mild and active Graves' orbitopathy by the 2021 European Group on Graves' Orbitopathy (EUGOGO) guideline, and reduces postpartum thyroiditis in anti-TPO-positive women.
Read the deep dive →Cancer Prevention
Antioxidant protection of DNA from oxidative mutagenesis, p53 / BRCA1 / Gadd45 modulation, selective apoptosis induction in transformed cells by methylselenol and selenodiglutathione, natural killer and cytotoxic T lymphocyte surveillance enhancement, the Nutritional Prevention of Cancer trial (first reported in 1996) and its secondary finding of fewer prostate cancers, a 63% reduction in data to 1993, with significant reductions by the end of treatment only in men with lower baseline plasma selenium, and the SELECT trial null result with high-grade prostate cancer signal that reframed the field around a U-shaped dose-response curve.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why Selenium Produces Effects Across Many Systems
- The Narrow Therapeutic Window and the Supratherapeutic Warning
- Research Papers: Antioxidant Defense and Selenoproteins
- Research Papers: Thyroid Function
- Research Papers: Immune Function and Viral Mutation
- Research Papers: Cancer Prevention (NPC, SELECT)
- Research Papers: Cross-Cutting (Status, Toxicity, Form)
- External Authoritative Resources
- Connections
- Featured Videos
Why Selenium Produces Effects Across Many Systems
Most trace elements act through one principal class of enzymes (zinc through its hundreds of metalloenzymes; iron through hemoproteins and iron-sulfur clusters; copper through its handful of cuproenzymes). Selenium is different because it acts almost exclusively through one structural strategy — the incorporation of selenocysteine at the active site of 25 human selenoproteins — but the resulting enzymes serve three fundamentally different cellular jobs, each of which produces a distinct category of clinical effect.
- Redox defense (the GPx and TrxR families) — The selenocysteine selenol group is a far more efficient peroxide-reducing catalyst than the cysteine thiol because of its lower pKa, larger atomic radius, and more reversible oxidation states. The selenium-containing glutathione peroxidases (GPx1-4 and GPx6; GPx5, GPx7 and GPx8 carry no selenium) and thioredoxin reductases (TrxR1-3) are the cell's most efficient redox-buffering enzymes, and they are the cellular antioxidant defenses that operate at the catalytic-enzyme level rather than the sacrificial-small-molecule level (vitamins C, E, glutathione). When the GPx/TrxR network is compromised, downstream consequences include lipid peroxidation in membranes (ferroptosis, the master regulator of which is GPx4), accumulation of mutagenic 8-oxoguanine in DNA, oxidative inactivation of redox-sensitive transcription factors, and elevated viral mutation rates in infected cells — the foundation of the Antioxidant Defense page.
- Thyroid hormone metabolism (the deiodinase family DIO1, DIO2, DIO3) — The iodothyronine deiodinases use selenocysteine at the active site to catalyze the regiospecific removal of iodine atoms from thyroxine, either activating it to triiodothyronine (T3) or inactivating it to reverse T3. Selenium is therefore the rate-limiting input for thyroid hormone activation in peripheral tissues. The thyroid gland itself contains more selenium per gram than any other organ, both because of the deiodinases and because GPx3 in the follicular lumen quenches the hydrogen peroxide generated during thyroid hormone synthesis. The full clinical picture is on the Thyroid Function page.
- Selective metabolite-mediated effects (methylselenol, selenodiglutathione) — A subset of dietary selenium compounds (specifically methylselenocysteine from selenium-enriched garlic and broccoli) is metabolized to methylselenol, a small lipophilic selenium species that selectively induces apoptosis in transformed cells, inhibits angiogenesis, and modulates the tumor microenvironment. This is a fundamentally different mechanism from the selenoenzyme-mediated effects above, and it is the mechanistic basis for the chemopreventive properties explored on the Cancer Prevention page.
The three mechanisms together explain why selenium deficiency produces such heterogeneous syndromes — Keshan cardiomyopathy from compromised cardiac GPx and TrxR activity, Hashimoto's and Graves' orbitopathy from compromised thyroidal GPx3 and immune dysregulation. A loss of selective methylselenol-driven apoptosis of transformed cells in the prostate has also been proposed as a route to high-grade prostate cancer, but in the 2014 analysis of the Selenium and Vitamin E Cancer Prevention Trial, toenail selenium without supplementation was not associated with prostate cancer risk, and the rise in high-grade disease came from supplementing men with higher selenium status. The same heterogeneity explains why supratherapeutic selenium is also problematic: pushing already-replete cells beyond saturation does not improve selenoenzyme activity (which is already at maximum) and may produce off-target effects through non-specific incorporation of selenomethionine into the methionine pool.
The thyroid trials show how much the answer depends on the condition. A 2024 review of 35 randomized trials in Hashimoto thyroiditis found that selenium lowered thyroid stimulating hormone in people not on thyroid hormone and lowered thyroid peroxidase antibodies with or without thyroid hormone treatment, with side effects similar to controls; thyroid hormone levels and thyroid volume did not change. The Graves' selenium supplementation (GRASS) trial gave 200 micrograms of selenium or placebo for 24 to 30 months to 430 people newly diagnosed with Graves' hyperthyroidism, on top of standard antithyroid drugs. The disease failed to go into remission in 54.6% on selenium and 53.3% on placebo, with no gain in quality of life. That question is separate from the eye-disease (Graves' orbitopathy) trial listed below.
The Narrow Therapeutic Window and the Supratherapeutic Warning
This hub page deviates from the standard structure to spend a paragraph on a warning that applies across all four deep-dive topics: selenium has one of the narrower therapeutic windows among the essential nutrients, and the evidence that more is better evaporates rapidly once baseline selenium status is adequate.
- The Nutritional Prevention of Cancer (NPC) trial, first reported in 1996, tested 200 mcg/day selenized yeast against skin cancers and found no effect on them. Prostate cancer was a secondary endpoint: a 63% reduction in data to 1993 (13 cases versus 35, relative risk 0.37), then a relative risk of 0.51 at the end of blinded treatment in 1996, with significant reductions only in men in the lower two thirds of baseline plasma selenium (below 123.2 ng/mL). That single secondary-endpoint finding launched a decade of enthusiastic selenium supplementation.
- The 2008 Selenium and Vitamin E Cancer Prevention Trial (SELECT), 35,533 men, found no overall prostate cancer benefit from 200 mcg/day selenomethionine and was stopped early. A 2014 analysis found that men with higher baseline selenium status (at or above the 60th percentile of toenail selenium) experienced a 91% increase in high-grade prostate cancer with supplementation, while men with lower status saw no effect.
- The long-term follow-up of Nutritional Prevention of Cancer trial participants found type 2 diabetes in 58 people on 200 mcg/day against 39 on placebo (hazard ratio 1.55, 95% confidence interval 1.03 to 2.33), and a hazard ratio of 2.70 in the third of participants with the highest baseline plasma selenium.
- Reviews describe a U-shaped link between selenium status and health, and a "sweet spot" of roughly 90 to 140 ng/mL plasma selenium is often quoted, with below ~70 ng/mL described as deficient and above ~140 to 150 ng/mL as supratherapeutic and likely net-harmful. In one US cohort of 13,887 adults, mortality from all causes and from cancer fell as serum selenium rose to 130 ng/mL, with a modest increase above 150 ng/mL; there was no association with cardiovascular mortality.
- In the Danish PRECISE trial, 491 people aged 60 to 74 took 100, 200 or 300 micrograms of selenium a day or placebo for 5 years. At 300 micrograms the hazard ratio for death was 1.59 (1.02 to 2.46) over the whole follow-up, which ran 10 years past treatment. The 100 and 200 microgram doses showed non-significant decreases in deaths during treatment that disappeared after it stopped. The trial was not first designed to study deaths, and its size was limited.
- A 2018 Cochrane review (10 randomized trials, 27,232 people) put the risk ratio for any cancer at 1.01 (0.93 to 1.10) in the trials at low risk of bias, and for cancer death at 1.02 (0.80 to 1.30).
- A single Brazil nut from selenium-rich Brazilian soil can contain anywhere from 5 to 100+ mcg of selenium, with content driven almost entirely by the soil where the tree grew. Eating 6 to 10 Brazil nuts per day is described as a common way for an American adult to accidentally cross into selenosis territory. In a New Zealand trial of 59 adults, 2 nuts a day supplied 53 micrograms on average (possible range 20 to 84) and raised plasma selenium 64.2% in 12 weeks, about the same as 100 micrograms of selenomethionine.
- In 2023 the European Food Safety Authority set the adult upper limit at 255 micrograms a day, below the 400 micrograms given above from the US, using hair loss as the earliest harm. It said adults are unlikely to go over it except regular users of high-dose supplements or regular Brazil nut eaters.
Baseline selenium status shapes most of these findings. Plasma selenium is the usual screening test, and 90 to 140 ng/mL is the range usually quoted. Another marker, useful in people with relatively low intakes, is plasma selenoprotein P (SELENOP): in a UK trial of 119 adults it averaged 4.99 micrograms per mL at baseline and rose to between 5.72 and 6.73 micrograms per mL on selenium, and a later trial report puts its plateau at a plasma selenium of about 125 micrograms per liter. The 200 mcg/day doses used in the Hashimoto's, Graves' orbitopathy, and (in deficient populations) cancer-prevention trials have mostly been studied in low-baseline adults for limited periods, and the research raises a concern for indefinite "wellness" use in adults whose status is already adequate. The same daily amount, 200 micrograms, lowered anti-thyroid peroxidase antibodies as sodium selenite over 3 months in a 2002 trial of women with autoimmune thyroiditis, and as L-selenomethionine it was followed by more high-grade prostate cancer in the men with higher selenium status in the Selenium and Vitamin E Cancer Prevention Trial. These trials tested specific uses in specific populations; none of them tested selenium for general antioxidant support.
Research Papers: Antioxidant Defense and Selenoproteins
- Labunskyy VM, Hatfield DL, Gladyshev VN (2014). Selenoproteins: molecular pathways and physiological roles. Physiological Reviews 94(3):739-777. — PubMed PMID: 24987004
- Brigelius-Flohé R, Maiorino M (2013). Glutathione peroxidases. Biochimica et Biophysica Acta 1830(5):3289-3303. — PubMed PMID: 23201771
- Conrad M, Pratt DA (2019). The chemical basis of ferroptosis. Nature Chemical Biology 15(12):1137-1147. — PubMed PMID: 31740834
- Burk RF, Hill KE (2015). Regulation of Selenium Metabolism and Transport. Annual Review of Nutrition 35:109-134. — PubMed PMID: 25974694
- Berry MJ, Banu L, Chen YY, et al. (1991). Recognition of UGA as a selenocysteine codon in type I deiodinase requires sequences in the 3' untranslated region. Nature 353(6341):273-276. — PubMed PMID: 1832744
- Schomburg L, Schweizer U (2009). Hierarchical regulation of selenoprotein expression and sex-specific effects of selenium. Biochimica et Biophysica Acta 1790(11):1453-1462. — PubMed PMID: 19328222
- Yant LJ, Ran Q, Rao L, et al. (2003). The selenoprotein GPX4 is essential for mouse development and protects from radiation and oxidative damage insults. Free Radical Biology & Medicine 34(4):496-502. — PubMed PMID: 12566075
- Yamashita Y, Yamashita M (2010). Identification of a novel selenium-containing compound, selenoneine, as the predominant chemical form of organic selenium in the blood of bluefin tuna. Journal of Biological Chemistry 285(24):18134-18138. — PubMed PMID: 20388714
- Ip C, Lisk DJ (1994). Bioactivity of selenium from Brazil nut for cancer prevention and selenoenzyme maintenance. Nutrition and Cancer 21(3):203-212. — PubMed PMID: 8072875
- MacFarquhar JK, Broussard DL, Melstrom P, et al. (2010). Acute selenium toxicity associated with a dietary supplement. Archives of Internal Medicine 170(3):256-261. — PubMed PMID: 20142570
Research Papers: Thyroid Function
- Köhrle J (2013). Selenium and the thyroid. Current Opinion in Endocrinology, Diabetes and Obesity 20(5):441-448. — PubMed PMID: 23974773
- Gärtner R, Gasnier BC, Dietrich JW, Krebs B, Angstwurm MW (2002). Selenium supplementation in patients with autoimmune thyroiditis decreases thyroid peroxidase antibodies concentrations. Journal of Clinical Endocrinology and Metabolism 87(4):1687-1691. — PubMed PMID: 11932302
- Marcocci C, Kahaly GJ, Krassas GE, et al. (2011). Selenium and the course of mild Graves' orbitopathy. New England Journal of Medicine 364(20):1920-1931. — PubMed PMID: 21591944
- Negro R, Greco G, Mangieri T, Pezzarossa A, Dazzi D, Hassan H (2007). The influence of selenium supplementation on postpartum thyroid status in pregnant women with thyroid peroxidase autoantibodies. Journal of Clinical Endocrinology and Metabolism 92(4):1263-1268. — PubMed PMID: 17284630
- van Zuuren EJ, Albusta AY, Fedorowicz Z, Carter B, Pijl H (2013). Selenium supplementation for Hashimoto's thyroiditis. Cochrane Database of Systematic Reviews 2013(6):CD010223. — PubMed PMID: 23744563
- Wichman J, Winther KH, Bonnema SJ, Hegedüs L (2016). Selenium Supplementation Significantly Reduces Thyroid Autoantibody Levels in Patients with Chronic Autoimmune Thyroiditis: A Systematic Review and Meta-Analysis. Thyroid 26(12):1681-1692. — PubMed PMID: 27702392
- Duntas LH, Benvenga S (2015). Selenium: an element for life. Endocrine 48(3):756-775. — PubMed PMID: 25519493
- Schomburg L (2016). Dietary Selenium and Human Health. Nutrients 9(1):22. — PubMed PMID: 28042811
- Larsen PR, Davies TF (2003). Hypothyroidism and thyroiditis. Williams Textbook. — PubMed: Hypothyroidism reference
- Bianco AC, Salvatore D, Gereben B, Berry MJ, Larsen PR (2002). Biochemistry, cellular and molecular biology, and physiological roles of the iodothyronine selenodeiodinases. Endocrine Reviews 23(1):38-89. — PubMed PMID: 11844744
- Bartalena L, Kahaly GJ, Baldeschi L, et al. (2021). The 2021 European Group on Graves' orbitopathy (EUGOGO) clinical practice guidelines for the medical management of Graves' orbitopathy. European Journal of Endocrinology 185(4):G43-G67. — PubMed PMID: 34297684
- Huwiler VV, Maissen-Abgottspon S, Stanga Z, et al. (2024). Selenium Supplementation in Patients with Hashimoto Thyroiditis: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Thyroid 34(3):295-313. — PubMed PMID: 38243784
- Cramon PK, Winther KH, Boesen VB, et al. (2026). Selenium supplementation in individuals with newly diagnosed Graves' hyperthyroidism: a double-blind, multi-centre RCT. European Thyroid Journal 15(1):ETJ250264. — PubMed PMID: 41384622
Research Papers: Immune Function and Viral Mutation
- Beck MA, Shi Q, Morris VC, Levander OA (1995). Rapid genomic evolution of a non-virulent coxsackievirus B3 in selenium-deficient mice results in selection of identical virulent isolates. Nature Medicine 1(5):433-436. — PubMed PMID: 7585090
- Beck MA, Nelson HK, Shi Q, et al. (2001). Selenium deficiency increases the pathology of an influenza virus infection. FASEB Journal 15(8):1481-1483. — PubMed PMID: 11387264
- Levander OA, Beck MA (1997). Interacting nutritional and infectious etiologies of Keshan disease. Insights from coxsackie virus B-induced myocarditis in mice deficient in selenium or vitamin E. Biological Trace Element Research 56(1):5-21. — PubMed PMID: 9152508
- Hurwitz BE, Klaus JR, Llabre MM, et al. (2007). Suppression of human immunodeficiency virus type 1 viral load with selenium supplementation: a randomized controlled trial. Archives of Internal Medicine 167(2):148-154. — PubMed PMID: 17242315
- Baum MK, Shor-Posner G, Lai S, et al. (1997). High risk of HIV-related mortality is associated with selenium deficiency. Journal of Acquired Immune Deficiency Syndromes and Human Retrovirology 15(5):370-374. — PubMed PMID: 9342257
- Broome CS, McArdle F, Kyle JA, et al. (2004). An increase in selenium intake improves immune function and poliovirus handling in adults with marginal selenium status. American Journal of Clinical Nutrition 80(1):154-162. — PubMed PMID: 15213043
- Angstwurm MW, Engelmann L, Zimmermann T, et al. (2007). Selenium in Intensive Care (SIC): results of a prospective randomized, placebo-controlled, multiple-center study in patients with severe systemic inflammatory response syndrome, sepsis, and septic shock. Critical Care Medicine 35(1):118-126. — PubMed PMID: 17095947
- Bloos F, Trips E, Nierhaus A, et al. (2016). Effect of Sodium Selenite Administration and Procalcitonin-Guided Therapy on Mortality in Patients With Severe Sepsis or Septic Shock: A Randomized Clinical Trial. JAMA Internal Medicine 176(9):1266-1276. — PubMed PMID: 27428731
- Hoffmann PR, Berry MJ (2008). The influence of selenium on immune responses. Molecular Nutrition & Food Research 52(11):1273-1280. — PubMed PMID: 18384097
- Avery JC, Hoffmann PR (2018). Selenium, Selenoproteins, and Immunity. Nutrients 10(9):1203. — PubMed PMID: 30200430
Research Papers: Cancer Prevention (NPC, SELECT)
- Clark LC, Combs GF Jr, Turnbull BW, et al. (1996). Effects of selenium supplementation for cancer prevention in patients with carcinoma of the skin. A randomized controlled trial. Nutritional Prevention of Cancer Study Group. JAMA 276(24):1957-1963. — PubMed PMID: 8971064
- Lippman SM, Klein EA, Goodman PJ, et al. (2009). Effect of selenium and vitamin E on risk of prostate cancer and other cancers: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 301(1):39-51. — PubMed PMID: 19066370
- Klein EA, Thompson IM Jr, Tangen CM, et al. (2011). Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 306(14):1549-1556. — PubMed PMID: 21990298
- Kristal AR, Darke AK, Morris JS, et al. (2014). Baseline selenium status and effects of selenium and vitamin e supplementation on prostate cancer risk. Journal of the National Cancer Institute 106(3):djt456. — PubMed PMID: 24563519
- Stranges S, Marshall JR, Natarajan R, et al. (2007). Effects of long-term selenium supplementation on the incidence of type 2 diabetes: a randomized trial. Annals of Internal Medicine 147(4):217-223. — PubMed PMID: 17620655
- Vinceti M, Filippini T, Del Giovane C, et al. (2018). Selenium for preventing cancer. Cochrane Database of Systematic Reviews 1(1):CD005195. — PubMed PMID: 29376219
- Hatfield DL, Tsuji PA, Carlson BA, Gladyshev VN (2014). Selenium and selenocysteine: roles in cancer, health, and development. Trends in Biochemical Sciences 39(3):112-120. — PubMed PMID: 24485058
- Steinbrenner H, Speckmann B, Sies H (2013). Toward understanding success and failures in the use of selenium for cancer prevention. Antioxidants & Redox Signaling 19(2):181-191. — PubMed PMID: 23421468
- Cai X, Wang C, Yu W, et al. (2016). Selenium Exposure and Cancer Risk: an Updated Meta-analysis and Meta-regression. Scientific Reports 6:19213. — PubMed PMID: 26786590
- Ip C, Hayes C, Budnick RM, Ganther HE (1991). Chemical form of selenium, critical metabolites, and cancer prevention. Cancer Research 51(2):595-600. — PubMed PMID: 1824684
- Clark LC, Dalkin B, Krongrad A, et al. (1998). Decreased incidence of prostate cancer with selenium supplementation: results of a double-blind cancer prevention trial. British Journal of Urology 81(5):730-734. — PubMed PMID: 9634050
- Duffield-Lillico AJ, Reid ME, Turnbull BW, et al. (2002). Baseline characteristics and the effect of selenium supplementation on cancer incidence in a randomized clinical trial: a summary report of the Nutritional Prevention of Cancer Trial. Cancer Epidemiology, Biomarkers & Prevention 11(7):630-639. — PubMed PMID: 12101110
- Duffield-Lillico AJ, Dalkin BL, Reid ME, et al. (2003). Selenium supplementation, baseline plasma selenium status and incidence of prostate cancer: an analysis of the complete treatment period of the Nutritional Prevention of Cancer Trial. BJU International 91(7):608-612. — PubMed PMID: 12699469
Research Papers: Cross-Cutting (Status, Toxicity, Form)
- Rayman MP (2012). Selenium and human health. The Lancet 379(9822):1256-1268. — PubMed PMID: 22381456
- Combs GF Jr (2015). Biomarkers of selenium status. Nutrients 7(4):2209-2236. — PubMed PMID: 25835046
- Schomburg L, Schweizer U, Holtmann B, Flohé L, Sendtner M, Köhrle J (2003). Gene disruption discloses role of selenoprotein P in selenium delivery to target tissues. Biochemical Journal 370(Pt 2):397-402. — PubMed PMID: 12521380
- Combs GF Jr, Watts JC, Jackson MI, et al. (2011). Determinants of selenium status in healthy adults. Nutrition Journal 10:75. — PubMed PMID: 21767397
- Behne D, Kyriakopoulos A (2001). Mammalian selenium-containing proteins. Annual Review of Nutrition 21:453-473. — PubMed PMID: 11375445
- Bleys J, Navas-Acien A, Guallar E (2008). Serum selenium levels and all-cause, cancer, and cardiovascular mortality among US adults. Archives of Internal Medicine 168(4):404-410. — PubMed PMID: 18299496
- Combs GF Jr (2001). Selenium in global food systems. British Journal of Nutrition 85(5):517-547. — PubMed PMID: 11348568
- Burk RF (2002). Selenium, an antioxidant nutrient. Nutrition in Clinical Care 5(2):75-79. — PubMed PMID: 12134713
- Schomburg L (2011). Selenium, selenoproteins and the thyroid gland: interactions in health and disease. Nature Reviews Endocrinology 8(3):160-171. — PubMed PMID: 22009156
- Yang G, Yin S, Zhou R, et al. (1989). Studies of safe maximal daily dietary Se-intake in a seleniferous area in China. Part II: Relation between Se-intake and the manifestation of clinical signs and certain biochemical alterations in blood and urine. Journal of Trace Elements and Electrolytes in Health and Disease 3(3):123-130. — PubMed PMID: 2535331
- Hurst R, Armah CN, Dainty JR, et al. (2010). Establishing optimal selenium status: results of a randomized, double-blind, placebo-controlled trial. American Journal of Clinical Nutrition 91(4):923-931. — PubMed PMID: 20181815
- Rayman MP, Winther KH, Pastor-Barriuso R, et al. (2018). Effect of long-term selenium supplementation on mortality: Results from a multiple-dose, randomised controlled trial. Free Radical Biology & Medicine 127:46-54. — PubMed PMID: 29454039
- Turck D, Bohn T, Castenmiller J, et al. (2023). Scientific opinion on the tolerable upper intake level for selenium. EFSA Journal 21(1):e07704. — PubMed PMID: 36698500
- Thomson CD, Chisholm A, McLachlan SK, Campbell JM (2008). Brazil nuts: an effective way to improve selenium status. American Journal of Clinical Nutrition 87(2):379-384. — PubMed PMID: 18258628
External Authoritative Resources
- Linus Pauling Institute — Selenium Micronutrient Information Center — the most comprehensive evidence-based summary of selenium biology, regularly updated
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Selenium Fact Sheet for Health Professionals
- WHO — Selenium reference values and global status
- MedlinePlus — Selenium
- PubMed — All research on selenium / selenocysteine / selenoprotein
Connections
- All Minerals
- Selenium (Main Page)
- Selenium for Antioxidant Defense
- Selenium for Cancer Prevention
- Selenium for Immune Function
- Selenium and Thyroid Function
- Selenium and Cancer Prevention — selenoprotein biology, the NPC and SELECT trials, evidence across prostate/colorectal/lung cancers, and the U-shaped dose-response curve.
- Iodine
- Zinc
- Iron
- Vitamin E
- Vitamin C
- Vitamin D3
- Glutathione
- Oxidative Stress
- Immune Boosting
- Methionine
- Cysteine
- Hashimoto's Thyroiditis
- Graves' Disease
- Cancer
- Prostate Conditions
- Cardiomyopathy (Keshan)
- Organ Meats
- Tuna
- Eggs
- Garlic
- Deficiency
- Toxicity
- History
- Sources