Magnesium — Benefits Deep Dive
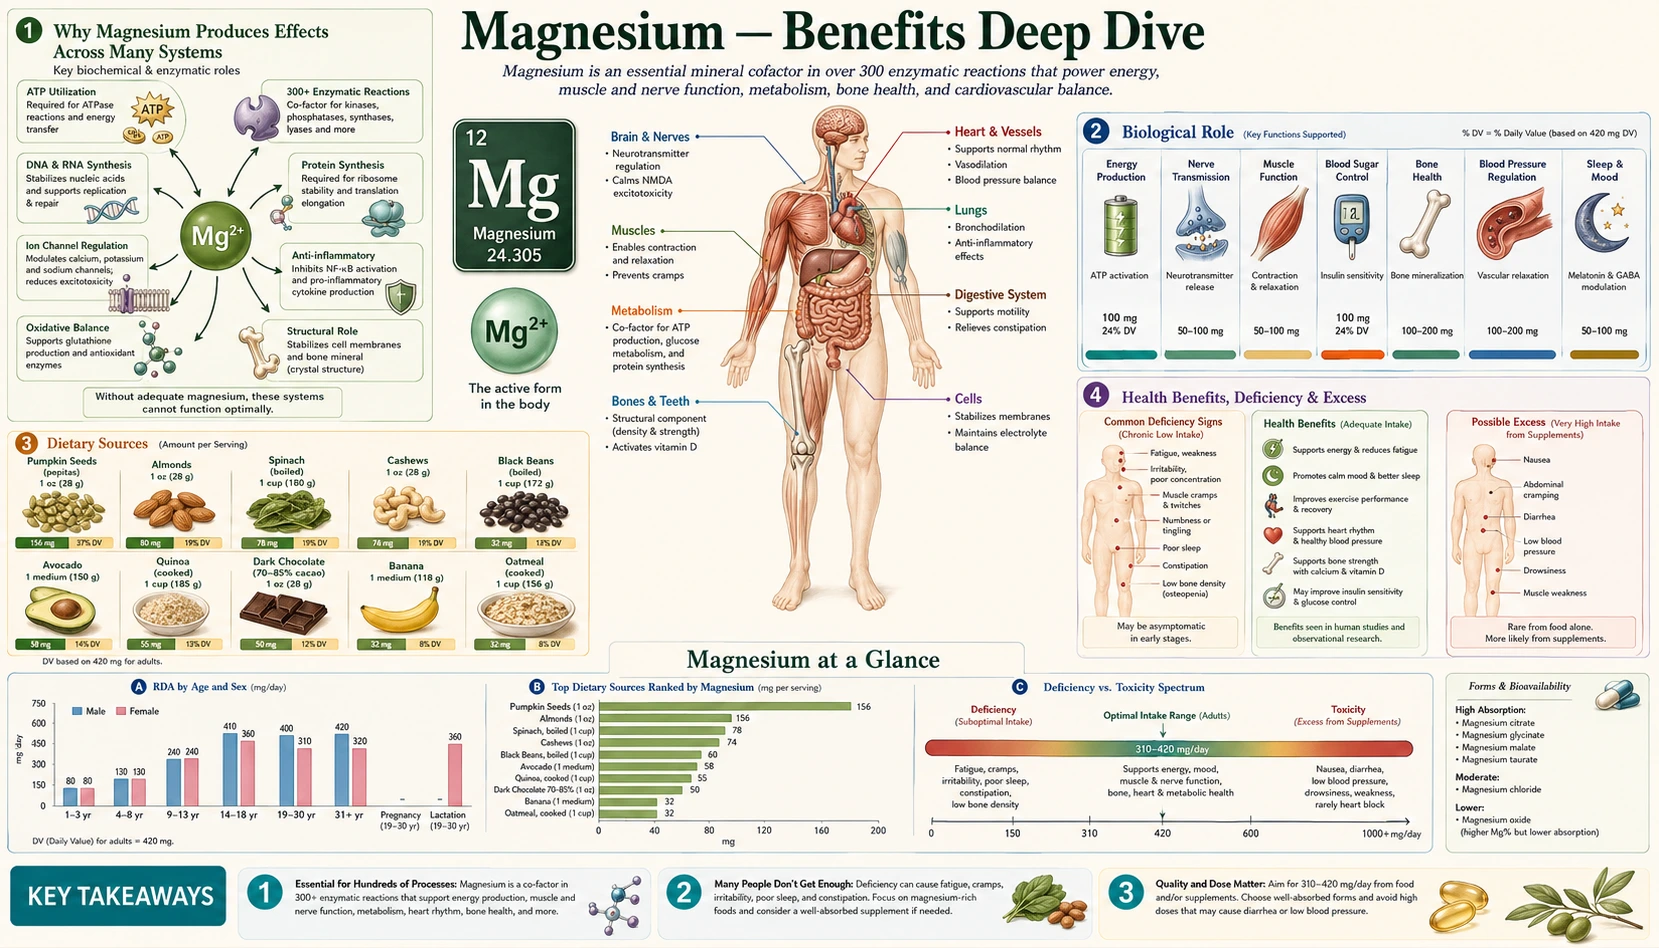
Magnesium is the fourth most abundant mineral in the human body and the second most abundant intracellular cation (after potassium). It is the obligate cofactor for more than 600 enzyme reactions and a modulator for another 200 — spanning energy production (every kinase that touches adenosine triphosphate (ATP) requires Mg-ATP), DNA replication, neurotransmission, muscle contraction-relaxation, cardiovascular tone, bone mineralization, and immune function. Despite this centrality, a 2012 review by Rosanoff and colleagues reported that almost half (48%) of the US population took in less than the required amount of magnesium from food in 2005–2006, and subclinical deficiency is now recognized as a driver of hypertension, atrial fibrillation, insomnia, migraine, leg cramps, restless legs, anxiety, type 2 diabetes, and osteoporosis. Four benefit pages below explore the conditions where magnesium produces the largest clinical effect — cardiovascular disease, sleep disturbance, neuromuscular dysfunction, and migraine prophylaxis.
Deep-Dive Articles
Heart Health
Blood pressure reduction (2.0/1.78 mmHg meta-analysis of 34 randomized controlled trials, RCTs), atrial fibrillation prevention (30-40% postoperative atrial fibrillation (AF) reduction after cardiac surgery), torsades de pointes as first-line intravenous (IV) magnesium emergency therapy, 77% lower sudden cardiac death risk in the Nurses' Health Study highest plasma magnesium quartile, the natural calcium-channel-blocker mechanism, vascular calcification inhibition, and the 8% stroke risk reduction per 100 mg/day dietary increment.
Read the deep dive →Sleep
Gamma-aminobutyric acid-A receptor potentiation, voltage-dependent N-methyl-D-aspartate (NMDA) receptor blockade, support of the tryptophan→serotonin→melatonin pathway, hypothalamic-pituitary-adrenal-axis cortisol dampening, parasympathetic activation. The Abbasi 2012 elderly insomnia trial (500 mg/day for 8 weeks): shorter sleep onset, longer sleep time on the sleep log (total sleep time did not differ significantly), higher sleep efficiency, lower cortisol, higher melatonin. Glycinate vs threonate for sleep; combining with B6, glycine, L-theanine.
Read the deep dive →Muscle Function
Magnesium as the body's endogenous calcium antagonist at the neuromuscular junction. The SERCA-pump-failure model of cramps. Nocturnal leg cramps in pregnancy and aging, restless legs (Hornyak 1998), eyelid twitches (orbicularis myokymia), generalized fasciculations, exercise-induced muscle cramps in athletes (Schwellnus, Miller pickle-juice trial), bronchospasm, smooth muscle. Glycinate vs malate vs threonate vs taurate — the muscle-specific form-selection guide.
Read the deep dive →Migraines
Mauskop's body of work on serum and intracellular magnesium deficiency in migraine. The American Academy of Neurology / American Headache Society Level B (probably effective) rating for 600 mg/day oral magnesium. Intravenous magnesium sulfate for acute migraine in the ED, with the Bigal aura-subgroup specificity. Pediatric migraine (Wang 2003), menstrual migraine and the luteal magnesium drop (Facchinetti), the cortical spreading depression mechanism, CGRP modulation.
Read the deep dive →Interactive Visualization Magnesium — the mineral that makes adenosine triphosphate work Bare adenosine triphosphate is useless and enzymes reject it. Watch magnesium clamp the phosphates and switch it on, plug the N-methyl-D-aspartate channel, and let a cramping muscle finally let go. Launch →
Table of Contents
- Deep-Dive Articles
- Why Magnesium Produces Effects Across Many Systems
- Research Papers: Heart Health
- Research Papers: Sleep
- Research Papers: Muscle Function
- Research Papers: Migraine
- Research Papers: Cross-Cutting (Mechanism, Status, Safety)
- External Authoritative Resources
- Connections
- Featured Videos
Why Magnesium Produces Effects Across Many Systems
Most minerals act through one or two principal mechanisms — iron carries oxygen on hemoglobin and serves as a redox cofactor in a handful of enzymes; iodine is incorporated into thyroid hormone; selenium is the catalytic atom in glutathione peroxidase. Magnesium is unusual because it operates through four fundamentally different mechanisms, each of which maps to a distinct category of clinical effect. The breadth of magnesium's clinical reach is not because magnesium is "good for everything" in some vague nutritional sense — it's because magnesium sits at four distinct nodes in cellular biochemistry, any one of which can become rate-limiting under common modern conditions.
- Mg-ATP is the active form of cellular energy currency — Every kinase reaction in the cell (and there are hundreds) uses Mg-ATP, not free adenosine triphosphate, as substrate. The magnesium ion neutralizes the negative charge on the adenosine triphosphate group, positions the gamma-phosphate for transfer, and stabilizes the transition state of the catalysis. Without magnesium, adenosine triphosphate is biologically inert. This puts magnesium at the catalytic core of glycolysis, the Krebs cycle, oxidative phosphorylation, fatty acid synthesis, protein synthesis, nucleotide synthesis, and signal transduction. The clinical translation is the diffuse fatigue and energy-failure pattern seen in moderate magnesium deficiency, and the specific energy-failure pattern documented by phosphorus MR spectroscopy in migraine cortex.
- Magnesium is the body's endogenous voltage-dependent N-methyl-D-aspartate receptor blocker — At resting membrane potential, magnesium ions physically occupy the N-methyl-D-aspartate glutamate receptor channel, preventing calcium influx. Only when a neuron is already strongly depolarized does the magnesium ion leave the pore, allowing N-methyl-D-aspartate activation. This makes magnesium the central nervous system's gatekeeper of excitatory glutamatergic tone. The same mechanism underlies the sleep-onset effect, the cortical-spreading-depression suppression in migraine, the anxiety-reducing effect, and a substantial fraction of the neuroprotective effect documented in stroke and traumatic brain injury research.
- Magnesium is the body's endogenous calcium antagonist — Calcium triggers contraction in cardiac, vascular smooth, and skeletal muscle; magnesium opposes that trigger and supports the relaxation phase. At the cardiomyocyte, this controls heart rhythm and is why magnesium is first-line intravenous therapy for torsades de pointes (see Heart Health). At vascular smooth muscle, it controls blood pressure (the 2 mmHg systolic reduction from 368 mg/day in 34 randomized controlled trials). At skeletal muscle, it controls cramps, twitches, restless legs, and exercise cramping (see Muscle Function). At smooth muscle in the airways, gut, and uterus, it controls bronchospasm, constipation, and uterine tone — the basis of intravenous magnesium use in severe asthma and preeclampsia.
- Magnesium is a hormone-signaling cofactor — Activation of vitamin D to its bioactive 1,25-dihydroxy form requires magnesium-dependent enzymes; insulin receptor tyrosine kinase activity requires magnesium-ATP; parathyroid hormone (PTH) secretion is modulated by magnesium; and the 2022 Cell paper from Lötscher and colleagues showed that extracellular magnesium is required for the active conformation of LFA-1 on cytotoxic T cells, directly linking magnesium status to antiviral and antitumor immunity. The hormone and immune-signaling mechanism gives magnesium a major role in calcium metabolism, glucose homeostasis (the type 2 diabetes risk reduction), bone health (osteoporosis), and adaptive immunity that cannot be predicted from the energy, N-methyl-D-aspartate, or calcium-antagonism mechanisms alone.
Because magnesium is rate-limiting at all four nodes simultaneously, deficiency does not produce one neat clinical syndrome — it produces a constellation. The constellation can include fatigue (mechanism 1), insomnia and migraine (mechanism 2), cramps and arrhythmia (mechanism 3), insulin resistance and bone loss (mechanism 4). Patients often present with three or four of these simultaneously and don't realize they share a single underlying nutritional deficit. The diagnostic clue is the constellation, not any single symptom — and practitioners describe a 4-8 week trial of magnesium as a cheap test, often reporting improvement across several complaints at once. The trials on this page used 250 mg (Schuster 2025) to 500 mg (Abbasi 2012) of elemental magnesium a day. The Institute of Medicine's 1997 Dietary Reference Intakes report set the tolerable upper intake level for magnesium from supplements and medicines (not food) at 350 mg/day for adolescents and adults, with mild diarrhoea as the first sign of too much; people with poor kidney function are at greater risk of magnesium toxicity.
Recent trials and reviews give the size of these effects and their limits:
- Sleep (older adults): a 2021 meta-analysis of 3 trials in 151 older adults found people fell asleep 17.4 minutes faster on magnesium than on placebo; total sleep rose by 16 minutes, but that change was not statistically significant, and all three trials were at moderate-to-high risk of bias (Mah and Pitre 2021).
- Sleep (adults): a 2026 systematic review of 12 randomized trials of magnesium taken alone found inconsistent results and low to very low certainty evidence; the authors concluded that current evidence does not support oral magnesium as a routine treatment for insomnia, though it may give modest benefits on some self-rated outcomes in some adults (Lopresti 2026).
- Poor sleep, 2025 trial: in a randomized placebo-controlled trial of 155 adults reporting poor sleep, 250 mg elemental magnesium (as bisglycinate) daily lowered the Insomnia Severity Index by 3.9 points at 4 weeks versus 2.3 points on placebo (p = 0.049); the authors rated the effect small (Cohen's d 0.2), with greater gains in people who ate little magnesium (Schuster 2025).
- Leg cramps: the 2020 Cochrane review (11 trials, 735 people) found it unlikely that magnesium gives clinically meaningful protection from cramps in older adults; the evidence in pregnancy is conflicting, and no randomized trials exist for exercise-associated cramps. Oral magnesium was linked mostly to stomach and bowel side effects such as diarrhoea, in 11% to 37% of users (10% to 14% on placebo) (Garrison 2020).
- Severe asthma attacks: a 2014 Cochrane review of 14 trials (2,313 people) found that a single 1.2 g or 2 g intravenous magnesium sulfate infusion in the emergency department reduced hospital admissions (7 fewer per 100 adults treated) and improved lung function in adults not helped enough by oxygen, inhalers and intravenous steroids (Kew 2014).
Research Papers: Heart Health
- Zhang X et al. (2016). Effects of magnesium supplementation on blood pressure: a meta-analysis of randomized double-blind placebo-controlled trials. Hypertension. PubMed PMID: 27402922
- Del Gobbo LC et al. (2013). Circulating and dietary magnesium and risk of cardiovascular disease: a systematic review and meta-analysis of prospective studies. Am J Clin Nutr. PubMed: Del Gobbo 2013
- Chiuve SE et al. (2011). Plasma and dietary magnesium and risk of sudden cardiac death in women. Am J Clin Nutr. (Nurses' Health Study, 77% SCD reduction in highest quartile) PubMed PMID: 21106914
- Woods KL, Fletcher S (1994). Long-term outcome after intravenous magnesium sulphate in suspected acute myocardial infarction: LIMIT-2 trial. Lancet. PubMed PMID: 7908076
- Liao F, Folsom AR, Brancati FL (1998). ARIC Study: low magnesium and coronary heart disease risk. Am Heart J. PubMed PMID: 9736141
- Larsson SC, Orsini N, Wolk A (2012). Dietary magnesium intake and risk of stroke: a meta-analysis of prospective studies. Am J Clin Nutr. PubMed PMID: 22205313
- DiNicolantonio JJ, O'Keefe JH, Wilson W (2018). Subclinical magnesium deficiency: a principal driver of cardiovascular disease and a public health crisis. Open Heart. PubMed: DiNicolantonio 2018
- Fang X et al. (2016). Dietary magnesium intake and the risk of cardiovascular disease, type 2 diabetes, and all-cause mortality: dose-response meta-analysis. BMC Med. PubMed: Fang dose-response
- Gu WJ, Wu ZJ, Wang PF, Aung LH, Yin RX (2012). Intravenous magnesium prevents atrial fibrillation after coronary artery bypass grafting: a meta-analysis of 7 double-blind, placebo-controlled, randomized clinical trials. Trials. 13:41. (1,028 participants; postoperative atrial fibrillation 36% lower, RR 0.64) PubMed PMID: 22520937
Research Papers: Sleep
- Abbasi B et al. (2012). The effect of magnesium supplementation on primary insomnia in elderly: a double-blind placebo-controlled clinical trial. J Res Med Sci. — Abbasi 2012. — PubMed PMID: 23853635
- Rondanelli M et al. (2011). Effect of melatonin, magnesium, and zinc on primary insomnia in long-term care residents: double-blind placebo-controlled trial. J Am Geriatr Soc. PubMed: Rondanelli 2011
- Hornyak M et al. (1998). Magnesium therapy for periodic leg movements-related insomnia and restless legs syndrome: open pilot study. Sleep. PubMed: Hornyak 1998
- Boyle NB, Lawton C, Dye L (2017). The effects of magnesium supplementation on subjective anxiety and stress — a systematic review. Nutrients. PubMed: Boyle anxiety review
- Mah J, Pitre T (2021). Oral magnesium supplementation for insomnia in older adults: a systematic review and meta-analysis. BMC Complement Med Ther. PubMed PMID: 33865376
- Slutsky I et al. (2010). Enhancement of learning and memory by elevating brain magnesium (magnesium L-threonate). Neuron. PubMed: Slutsky threonate
- Bannai M, Kawai N (2012). New therapeutic strategy for amino acid medicine: glycine improves the quality of sleep. J Pharmacol Sci. PubMed: Bannai glycine sleep
- Tarleton EK et al. (2017). Role of magnesium supplementation in the treatment of depression: a randomized clinical trial. PLOS ONE. PubMed: Tarleton depression
- Held K et al. (2002). Oral magnesium supplementation reverses age-related neuroendocrine and sleep EEG changes. Pharmacopsychiatry. PubMed: Held EEG study
- Nielsen FH, Johnson LK, Zeng H (2010). Magnesium supplementation improves indicators of low magnesium status and inflammatory stress. Magnes Res. PubMed: Nielsen 2010
- Schuster J, Cycelskij I, Lopresti A, Hahn A (2025). Magnesium bisglycinate supplementation in healthy adults reporting poor sleep: a randomized, placebo-controlled trial. Nat Sci Sleep. 17:2027-2040. PubMed PMID: 40918053
- Lopresti AL, Smith SJ, Drummond PD (2026). Magnesium supplementation for sleep in adults: a systematic review of randomized controlled trials. J Diet Suppl. 23(5):553-581. PubMed PMID: 42661485
Research Papers: Muscle Function
- Sebo P, Cerutti B, Haller DM (2014). Effect of magnesium therapy on nocturnal leg cramps: systematic review and meta-analysis. Family Practice. PubMed: Sebo 2014
- Garrison SR et al. (2012). Magnesium for skeletal muscle cramps. Cochrane Database Syst Rev. PubMed PMID: 22972143
- Garrison SR, Korownyk CS, Kolber MR, Allan GM, Musini VM, Sekhon RK, Dugré N (2020). Magnesium for skeletal muscle cramps (update of the 2012 review). Cochrane Database Syst Rev. 9:CD009402. PubMed PMID: 32956536
- Dahle LO et al. (1995). The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol. PubMed: Dahle pregnancy
- Miller KC et al. (2010). Reflex inhibition of electrically induced muscle cramps in hypohydrated humans (pickle juice). Med Sci Sports Exerc. PubMed: Miller pickle juice
- Schwellnus MP (2009). Cause of exercise associated muscle cramps (EAMC) — altered neuromuscular control. Br J Sports Med. PubMed: Schwellnus EAMC
- Russell IJ et al. (1995). Treatment of fibromyalgia syndrome with Super Malic (magnesium malate). J Rheumatol. PubMed: Russell Super Malic
- Lukaski HC (2004). Vitamin and mineral status: effects on physical performance. Nutrition. PubMed: Lukaski performance
- Hornyak M et al. (1998). Magnesium and PLMS — the seminal RLS trial. Sleep. PubMed: Hornyak RLS
- Allen RP et al. (2014). Restless legs syndrome/Willis-Ekbom disease diagnostic criteria. Sleep Med. PubMed: IRLSSG criteria
- Kew KM, Kirtchuk L, Michell CI (2014). Intravenous magnesium sulfate for treating adults with acute asthma in the emergency department. Cochrane Database Syst Rev. 2014(5):CD010909. PubMed PMID: 24865567
Research Papers: Migraine
- Mauskop A, Varughese J (2012). Why all migraine patients should be treated with magnesium. J Neural Transm. PubMed: Mauskop 2012
- Peikert A, Wilimzig C, Köhne-Volland R (1996). Prophylaxis of migraine with oral magnesium: prospective multicenter double-blind RCT. Cephalalgia. PubMed: Peikert 1996
- Bigal ME et al. (2002). Intravenous magnesium sulphate in acute treatment of migraine without aura and migraine with aura. Cephalalgia. PubMed: Bigal IV magnesium
- Chiu HY et al. (2016). Effects of intravenous and oral magnesium on reducing migraine: meta-analysis of RCTs. Pain Physician. — Search PubMed
- Wang F et al. (2003). Oral magnesium oxide prophylaxis of frequent migrainous headache in children. Headache. PubMed: Wang pediatric
- Facchinetti F et al. (1991). Magnesium prophylaxis of menstrual migraine: effects on intracellular magnesium. Headache. PubMed: Facchinetti menstrual
- Holland S et al. (2012). AAN/AHS evidence-based guideline update: NSAIDs and other complementary treatments for episodic migraine prevention. Neurology. (Level B for magnesium) PubMed PMID: 22529203
- Köseoglu E et al. (2008). The effects of magnesium prophylaxis in migraine without aura. Magnes Res. PubMed: Köseoglu
- Lodi R et al. (2001). Deficient energy metabolism is associated with low free magnesium in the brains of patients with migraine and cluster headache. Brain Res Bull. PubMed: Lodi MR spectroscopy
- Welch KMA, Ramadan NM (1995). Mitochondria, magnesium and migraine. J Neurol Sci. PubMed: Welch Ramadan
Research Papers: Cross-Cutting (Mechanism, Status, Safety)
- de Baaij JH, Hoenderop JG, Bindels RJ (2015). Magnesium in man: implications for health and disease. Physiological Reviews. PubMed PMID: 25540137
- Rosanoff A, Weaver CM, Rude RK (2012). Suboptimal magnesium status in the United States. Nutrition Reviews. PubMed PMID: 22364157
- Gröber U, Schmidt J, Kisters K (2015). Magnesium in prevention and therapy. Nutrients. PubMed: Gröber review
- Fang X et al. (2016). Dose-response: dietary magnesium and type 2 diabetes risk. Nutrients. PubMed: Fang T2DM
- Veronese N et al. (2016). Effect of magnesium supplementation on glucose metabolism: meta-analysis. Eur J Clin Nutr. PubMed: Veronese glucose
- Lötscher J et al. (2022). Magnesium sensing via LFA-1 regulates CD8+ T cell effector function. Cell. PubMed PMID: 35051368
- Altman D et al. (2002). Magpie Trial: Magnesium sulphate for women with pre-eclampsia. Lancet. PubMed: Magpie Trial
- Doyle LW et al. (2009). Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev. PubMed: Doyle Cochrane
- Orchard TS et al. (2014). Magnesium intake, bone mineral density, and fractures: Women's Health Initiative. Am J Clin Nutr. PubMed: Orchard WHI
- Workinger JL, Doyle RP, Bortz J (2018). Challenges in the diagnosis of magnesium status. Nutrients. PubMed: Workinger diagnosis
- Institute of Medicine (1997). Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Chapter 6: Magnesium (tolerable upper intake level 350 mg/day of supplementary magnesium for adolescents and adults). Washington, DC: National Academies Press. doi:10.17226/5776
External Authoritative Resources
- Linus Pauling Institute — Magnesium Micronutrient Information Center — the single most authoritative scientific summary of magnesium biology, regularly updated
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Magnesium Fact Sheet (Health Professionals)
- Harvard T.H. Chan School of Public Health — The Nutrition Source: Magnesium
- Sleep Foundation — Magnesium and Sleep
- MedlinePlus — Magnesium
- PubMed — All research on magnesium (~200,000+ papers)
Connections
- All Minerals
- Magnesium: The Mineral That Makes Adenosine Triphosphate Work — interactive animation
- Magnesium (Main Page)
- Magnesium for Heart Health
- Magnesium for Sleep
- Magnesium for Muscle Function
- Magnesium for Migraines
- Magnesium Glycinate
- Calcium
- Potassium
- Zinc
- Vitamin D3
- Vitamin K2
- Vitamin B6
- Glycine
- Taurine
- Hypertension
- Atrial Fibrillation
- Migraine
- Insomnia
- Anxiety
- Restless Legs Syndrome
- Insulin Resistance
- Osteoporosis
- Magnesium Replenishment
- Sleep Hygiene
- Stress Management
- Cramp Prevention
- Magnesium Test
- Deficiency
- Toxicity
- History
- Sources