⚠ Evidence warning: Clinical trials or other evidence do not support the claims that vitamin A supplements reduce respiratory deaths in children, that the mortality reduction is among the largest of any nutritional intervention, and that a dose after childbirth protects infants from gastrointestinal infection through breast milk. This page keeps it as a report of what people, websites or other media say.
Vitamin A for Immune Function
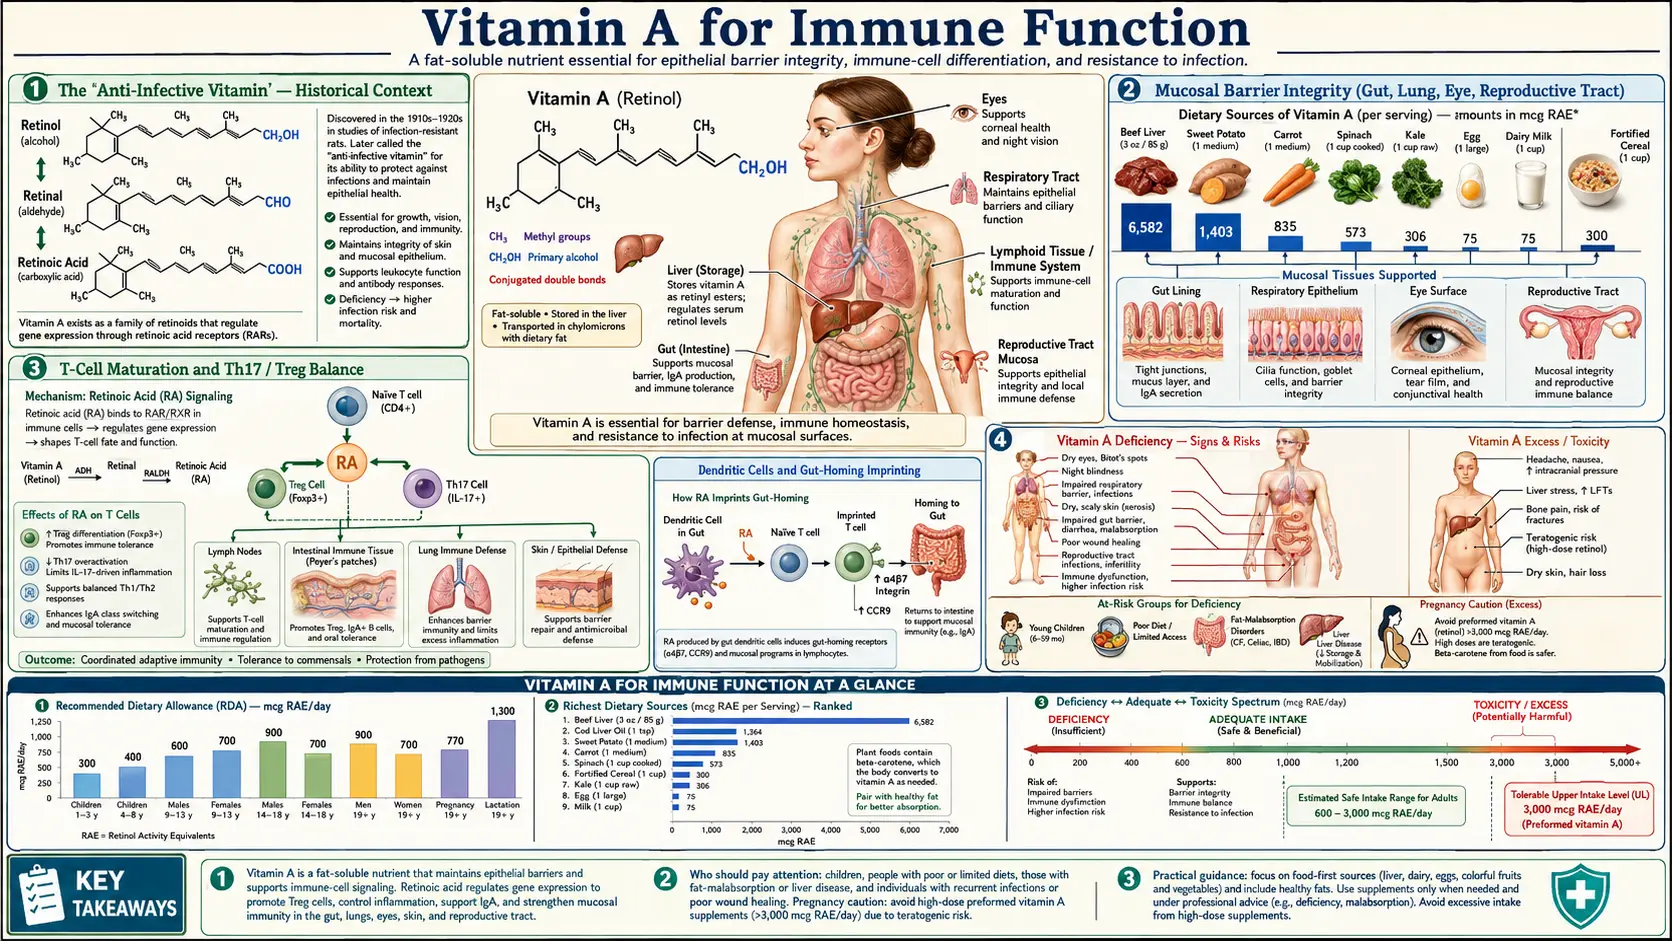
Vitamin A was originally called an "anti-infective agent" by Harry Green and Edward Mellanby in their joint 1928 paper, before its mechanism was understood, simply because deficient animals died of infection at strikingly higher rates than replete animals. A century later, the mechanism is well-mapped: retinoic acid is a master regulator of T-cell differentiation (Th17/Treg balance), B-cell class switching to mucosal immunoglobulin A (IgA), dendritic cell gut-homing imprinting, and natural killer cell function. The clinical translation has been one of global health's most successful interventions — in children under two with measles, the World Health Organization (WHO) treatment of two 200,000 international units (IU) doses on consecutive days was linked to much lower death rates in the Cochrane review of measles treatment, and biannual supplementation programs in 80 countries prevent an estimated 600,000 deaths per year. This deep-dive walks through each immune mechanism, the pivotal clinical trials, and the practical implications for adult patients facing immune-related conditions.
Table of Contents
- The "Anti-Infective Vitamin" — Historical Context
- Mucosal Barrier Integrity (Gut, Lung, Eye, Reproductive Tract)
- T-Cell Maturation and Th17 / Treg Balance
- Dendritic Cells and Gut-Homing Imprinting
- B-Cell Class Switching to Mucosal Immunoglobulin A
- The World Health Organization Measles Protocol (2×200,000 International Units)
- Respiratory Infections and Pneumonia
- Diarrheal Disease and Gut Barrier
- Adult Immune Applications
- Cautions (Including the Negative Tuberculosis Signal)
- Key Research Papers
- Connections
- Featured Videos
The "Anti-Infective Vitamin" — Historical Context
The idea of Vitamin A as an "anti-infective agent" comes from the joint 1928 British Medical Journal paper of Harry Green and Edward Mellanby, which described the dramatic protective effect of Vitamin A against infection in laboratory animals. Their rats fed Vitamin-A-deficient diets developed not only the expected xerophthalmia but also pneumonia, otitis media, urinary tract infections, and severe diarrhea — all of which resolved when Vitamin A was added back to the diet. This was decades before any modern understanding of T cells, cytokines, or nuclear receptor signaling.
The clinical translation in humans came in fits and starts. Early work suggested supplementation reduced respiratory mortality in children. The seminal modern work was done by Alfred Sommer at Johns Hopkins through field epidemiology in Indonesia in the 1970s and 1980s. Sommer's 1986 Lancet paper reported a randomised community trial in 450 villages in northern Sumatra (25,939 preschool children): capsules of 200,000 IU Vitamin A were given twice, about six months apart, and among children aged 12–71 months, deaths were 7.3 per 1,000 in control villages against 4.9 per 1,000 where supplements were given. The authors concluded that supplements given to deficient populations may decrease mortality by as much as 34% — far more than could be explained by eye disease alone. The reduction was driven primarily by deaths from measles, pneumonia, and diarrhea, confirming the broader immune-protective effect.
The Cochrane review of Vitamin A supplementation for children aged six months to five years (Imdad et al., updated in 2022 with the same conclusions as the 2017 version) pooled 47 studies with about 1,223,856 children. It found a 12% reduction in deaths from all causes (risk ratio (RR) 0.88; 19 trials; high-certainty evidence) and a 12% reduction in deaths from diarrhea (RR 0.88; 9 trials; high-certainty evidence). It found no clear difference in deaths from measles (RR 0.88) or respiratory disease (RR 0.98). The reduction in all-cause deaths from supplementation is one of the largest documented mortality reductions for any nutritional intervention in any setting.
The same review found that supplements reduced how often children got diarrhea (RR 0.85), measles (RR 0.45), Bitot's spots (RR 0.42), night blindness (RR 0.32) and Vitamin A deficiency itself (RR 0.71), but did not change how often they got respiratory disease (RR 0.99) or how often they were admitted to hospital for diarrhea or pneumonia. Vomiting in the first 48 hours after a dose was about twice as common (RR 1.97). The authors concluded that supplementation is associated with a clinically meaningful reduction in illness and death in children, and that studies comparing different doses and ways of giving it are still needed.
Mucosal Barrier Integrity (Gut, Lung, Eye, Reproductive Tract)
The first line of immune defense is not the immune system in the conventional sense — it is the epithelial barrier that physically separates the body's interior from the outside world. The gut, the respiratory tract, the conjunctiva, and the genitourinary tract are all lined with specialized epithelium that secretes mucus, antimicrobial peptides, and secretory immunoglobulin A. The integrity of these epithelial barriers depends critically on retinoic acid signaling through the RAR/RXR nuclear receptor complex.
Without adequate Vitamin A, the epithelium undergoes squamous metaplasia — mucus-producing columnar epithelium converts to dry, keratinized squamous epithelium. The conjunctival version of this is visible as Bitot's spots and xerophthalmia. The same process occurs less visibly in the respiratory tree, the gut, and the urinary tract, where it:
- Reduces mucus secretion that traps pathogens and irritants
- Eliminates the cilia that sweep trapped material out of the airways
- Reduces antimicrobial peptide production (defensins, lysozyme)
- Disrupts the tight junctions between epithelial cells, allowing pathogen translocation
- Eliminates the goblet cells that produce the protective mucin layer
The net effect is that pathogens that would normally be cleared by mechanical and chemical defenses now establish infection. The deficient child becomes a near-universal target for any opportunistic respiratory or enteric pathogen circulating in the community — which is why diarrhea and pneumonia are the leading killers of deficient children worldwide, far more than the iconic blindness.
T-Cell Maturation and Th17 / Treg Balance
Beyond the mucosal barrier, retinoic acid plays a direct role in adaptive immunity through its effects on T-cell differentiation. Naive CD4+ T cells encountering antigen can differentiate down several distinct paths: Th1 (cellular immunity, intracellular pathogens), Th2 (humoral immunity, parasites), Th17 (mucosal defense, extracellular bacteria, fungi), or Treg (regulatory T cells that suppress inflammation and prevent autoimmunity).
The balance between Th17 and Treg is particularly sensitive to retinoic acid concentration. In the presence of adequate retinoic acid, naive T cells encountering antigen in mucosal lymphoid tissue tend toward the Treg phenotype, producing interleukin-10 (IL-10) and TGF-beta to maintain mucosal tolerance to commensal bacteria and food antigens. Without retinoic acid, the same encounter pushes toward the Th17 phenotype, producing IL-17 and IL-22, which is appropriate for fighting fungal and extracellular bacterial infection but pathological when chronic and untargeted — the Th17 axis drives several autoimmune conditions including psoriasis, ankylosing spondylitis, and inflammatory bowel disease.
This Th17/Treg balance has therapeutic implications. Retinoic acid analogs are being explored as adjuncts in inflammatory bowel disease, multiple sclerosis (some animal-model evidence), and graft-versus-host disease. Conversely, Vitamin A deficiency disrupts mucosal tolerance and is associated with increased allergic sensitization, food allergy, and atopic disease in observational studies. The mechanism is the same Th17/Treg disequilibrium, just expressed in different organ systems.
For the related immune-modulating effects of Vitamin D, which works through a separate but parallel nuclear receptor pathway, see our Vitamin D3 page. The two fat-soluble vitamins are often discussed together because both signal through the RXR retinoid X receptor partner and produce complementary effects on adaptive immunity.
Dendritic Cells and Gut-Homing Imprinting
A particularly elegant aspect of retinoic acid immunology is the role of dendritic cells in "imprinting" T cells with gut-homing receptors. CD103+ dendritic cells in mesenteric lymph nodes constitutively express retinaldehyde dehydrogenase (RALDH), the enzyme that converts dietary retinal to active retinoic acid. When these dendritic cells present antigen to a naive T cell, the locally produced retinoic acid induces expression of two surface receptors on the T cell: CCR9 (a chemokine receptor that recognizes thymus-expressed chemokine TECK/CCL25 produced by small intestinal epithelium) and integrin alpha4-beta7 (which binds MAdCAM-1 expressed on mucosal vessel endothelium).
The dual expression of CCR9 and alpha4-beta7 functionally addresses the T cell to the gut. After clonal expansion in the mesenteric lymph node, the activated T cell exits via the thoracic duct, enters circulation, and is recruited preferentially back to the small intestinal lamina propria where the initial antigen encounter occurred — precisely where its effector function is needed.
Without adequate retinoic acid in the dendritic cell's local environment, the gut-homing imprinting fails. T cells activated against gut pathogens do not return to the gut to fight them. This is a beautiful concrete molecular mechanism behind the older epidemiologic observation that Vitamin A deficient children get more diarrheal disease — their adaptive immune cells literally lose the address tags that would send them to the gut.
B-Cell Class Switching to Mucosal Immunoglobulin A
Retinoic acid also drives B-cell class switching toward the immunoglobulin A isotype — the dominant antibody class secreted into mucosal surfaces. Secretory immunoglobulin A dimers are secreted across the gut, airway, lacrimal, salivary, and mammary epithelium and provide the antigen-specific arm of mucosal immunity, complementing the non-specific epithelial barrier and antimicrobial peptides.
The class-switch recombination event that converts a B cell from producing immunoglobulin M (IgM) to producing immunoglobulin A requires both TGF-beta and retinoic acid co-signals. Without adequate Vitamin A, mucosal immunoglobulin A production drops — deficient children have measurably lower secretory immunoglobulin A in saliva, breast milk, and intestinal washings, even when they have otherwise intact humoral immunity for systemic immunoglobulin G (IgG) responses.
The clinical relevance: breastfeeding mothers in deficient populations transmit fewer protective antibodies to their nursing infants. A single large Vitamin A dose for mothers after childbirth, which the World Health Organization recommended in areas of deficiency at the time of the 2006 ZVITAMBO trial report, was meant to address this: it raises maternal Vitamin A status enough to support normal breast-milk immunoglobulin A content, transferring measurable protection against gastrointestinal infection to the infant. The 2016 Cochrane review of postpartum Vitamin A (14 trials, 25,758 mother–infant pairs) found that it raised breast-milk retinol by 0.20 µmol/L, but that this did not translate into health benefits for mothers or infants: there was no evidence of fewer infant deaths (RR 1.08), and the effect on infant gastroenteritis was uncertain (very low-quality evidence).
The World Health Organization Measles Protocol (2×200,000 International Units)
Measles is the most dramatic clinical demonstration of the Vitamin A immune connection. Measles infection itself depletes Vitamin A stores rapidly (the virus accelerates retinol turnover and the febrile illness causes anorexia and reduced intake). A child who was marginally deficient at the start of a measles infection can become severely deficient within days, and that deficiency in turn dramatically increases the risk of dying from measles complications — bacterial pneumonia superinfection, severe diarrhea with dehydration, encephalitis, or measles-associated keratomalacia and permanent blindness.
The Hussey and Klein 1990 NEJM trial established the modern World Health Organization protocol. 189 South African children hospitalized with severe measles were randomized to two doses of 200,000 international units oral Vitamin A on consecutive days, or placebo. Results:
- Of the 12 children who died, 10 had received placebo and 2 Vitamin A (P = 0.05); the risk of death or a major complication during the hospital stay was half that of the placebo group (relative risk 0.51)
- Faster recovery from pneumonia (6.3 vs 12.4 days on average) and diarrhea (5.6 vs 8.5 days), and less croup (13 vs 27 cases)
- Shorter hospital stay (10.6 vs 14.8 days on average)
- Safety profile was excellent — no acute hypervitaminosis A despite the high dose
The World Health Organization formally adopted the 2×200,000 international units protocol for measles management in all measles-endemic areas. The World Health Organization recommends an oral dose (200,000 IU, or 100,000 IU in infants) each day for two days to children with measles who live in areas where Vitamin A deficiency may be present. Cost is approximately 5 US cents per dose. This is one of the most cost-effective single interventions in global pediatric infectious disease.
The Cochrane review of Vitamin A for treating measles (Huiming et al. 2005) adds what is and is not known. When all the trials were pooled, there was no significant reduction in deaths (RR 0.70). Two doses of 200,000 IU on consecutive days were linked to a much lower risk of death in children under two years old (RR 0.18) and to fewer deaths from pneumonia (RR 0.33), and to less croup (RR 0.53), but not to fewer cases of pneumonia or diarrhea. A single dose was not linked to fewer deaths. No trial has directly compared a single dose with two doses.
The relevance to other viral infections has been studied less extensively. There is suggestive evidence for benefit in severe respiratory syncytial virus (RSV) infection in deficient children. For human immunodeficiency virus (HIV) mother-to-child transmission, the trials described under Cautions below found no reduction in transmission, and Vitamin A is no longer a primary intervention in that setting.
Respiratory Infections and Pneumonia
Pneumonia is the leading cause of death in children under five worldwide, killing approximately 700,000 children per year. A substantial fraction of this mortality is concentrated in populations with significant Vitamin A deficiency.
The Cochrane review of Vitamin A supplementation for preventing illness and death in children (Imdad et al., 2017, updated 2022) found no evidence of a difference in deaths from respiratory disease (RR 0.98; 9 studies, 1,098,538 children), in how often respiratory disease occurred (RR 0.99), or in hospital admissions for pneumonia. Treatment of children who already have measles is different: there, two doses were linked to fewer pneumonia deaths (RR 0.33) in the measles-treatment review described above.
For adults in the developed world, the question of Vitamin A and respiratory infection is more nuanced. Adults with frankly low serum retinol (less than 0.7 µmol/L) clearly benefit from repletion in terms of reduced infection susceptibility. Adults with adequate baseline Vitamin A status do not appear to benefit from supraphysiologic dosing for infection prevention — the relationship is more like a step-function than a dose-response. Repletion of deficiency helps; pushing already-adequate intake higher does not.
The exception is patients with documented malabsorption (cystic fibrosis, advanced Crohn's disease, post-bariatric surgery), who often have subclinical Vitamin A deficiency despite normal dietary intake and may benefit from targeted supplementation as part of management of their increased infection susceptibility. For more on respiratory infection management, see our Pneumonia page.
Diarrheal Disease and Gut Barrier
Diarrhea is the second leading cause of childhood mortality globally (after pneumonia). Vitamin A's gut-barrier and mucosal-IgA effects translate to a meaningful reduction in diarrhea mortality in supplementation trials — the Imdad Cochrane review found a 12% reduction in deaths from diarrhea (RR 0.88; high-certainty evidence) and fewer cases of diarrhea (RR 0.85) with Vitamin A supplementation.
The gut-barrier mechanism is twofold:
- Structural integrity — retinoic acid maintains the goblet cells that produce the protective mucin layer (Muc2 is the dominant gel-forming mucin in the colon, Muc5AC in the small intestine), maintains tight junction proteins (claudins, occludin, ZO-1) that prevent paracellular translocation, and supports the antimicrobial peptide-producing Paneth cells in small-intestinal crypts
- Adaptive immunity addressed to the gut — the CCR9 / alpha4-beta7 imprinting of T cells and the immunoglobulin A class switching of B cells both depend on retinoic acid as discussed above. Even when a Vitamin A deficient child mounts an immune response to a gut pathogen, that response is poorly directed to the gut tissue.
For adults, conditions associated with chronic diarrhea (inflammatory bowel disease, small intestinal bacterial overgrowth (SIBO), post-infectious irritable bowel) can lower the status of the fat-soluble vitamins, including Vitamin A, so a secondary deficiency can remain even when the gut condition itself is treated.
Adult Immune Applications
For adult patients in the developed world, the Vitamin-A-and-immunity story plays out differently than in the deficient pediatric population. Most adults are not Vitamin A deficient, and supraphysiologic supplementation does not provide additive immune benefit. The relevant applications are concentrated in specific clinical contexts:
- Inflammatory bowel disease (Crohn's, ulcerative colitis) — both fat malabsorption and intestinal inflammation produce Vitamin A deficiency in 20-30% of patients. Repletion to normal serum retinol restores mucosal integrity and may reduce flare frequency. Typical regimen: 5,000-10,000 international units/day retinyl palmitate or 1 tsp cod liver oil daily, monitored with serum retinol every 6-12 months.
- Cystic fibrosis — routine Vitamin A supplementation is part of standard CF care due to pancreatic insufficiency-driven fat malabsorption. Liquid water-soluble Vitamin A preparations are typically used. Dosing follows CF Foundation guidelines based on age.
- Bariatric surgery — gastric bypass and duodenal switch procedures dramatically reduce fat-soluble vitamin absorption. Lifelong Vitamin A supplementation with periodic monitoring is part of standard aftercare.
- Chronic kidney disease — counterintuitively, advanced chronic kidney disease (CKD) patients can have elevated serum retinol due to impaired renal clearance of retinol-binding protein. In advanced chronic kidney disease, added Vitamin A can therefore raise an already-high level further.
- Recurrent respiratory infection in adults — serum retinol, zinc and vitamin D levels and fat malabsorption are the factors usually looked at. Repletion if deficient produces clinical benefit; supraphysiologic dosing in adequate adults does not.
Cautions (Including the Negative Tuberculosis Signal)
- Teratogenicity in pregnancy — the most consequential warning, repeated across every Vitamin A page. Preformed retinol above 3,000 mcg RAE/day in pregnancy is associated with fetal malformations of the central nervous system, face, ears, and heart. High-dose retinol supplements and beef liver (one of the richest food sources of preformed retinol) can each supply intakes above that level, and isotretinoin and other oral retinoid drugs are contraindicated in pregnancy on their labels because they cause birth defects.
- Tuberculosis — the negative supplementation signal — a notable exception to the "more Vitamin A reduces infection" pattern. Trials of Vitamin A in pulmonary tuberculosis (TB) have shown no benefit. In South African children with pulmonary tuberculosis, high-dose Vitamin A therapy had no effect on disease outcome (Hanekom 1997). In a randomized trial of 154 adults in Cape Town, a single 200,000 IU dose of Vitamin A plus zinc for 8 weeks made no difference to the time until sputum smears or cultures turned negative, to weight gain, or to chest X-ray healing (Visser 2011). The proposed mechanism for a negative signal is that Mycobacterium tuberculosis requires intracellular cholesterol metabolism, and retinoic acid may inadvertently support pathogen lipid metabolism in addition to host immunity.
- Human immunodeficiency virus infection — early enthusiasm for Vitamin A as part of human immunodeficiency virus management has cooled. The ZVITAMBO trial in Zimbabwe (14,110 mother–infant pairs; 4,495 infants of human immunodeficiency virus-positive mothers analysed) found that neither a single large dose to the mother after childbirth nor a dose to the newborn changed mother-to-child transmission after birth or overall deaths up to 24 months. However, in infants who were still uninfected at 6 weeks, all three Vitamin A schemes were associated with about twice the death rate, and the authors raised concern about universal maternal or newborn supplementation where HIV is common. The Durban trial (Coutsoudis 1999; 728 pregnant women with HIV) found no difference in infant infection by 3 months (20.3% with Vitamin A vs 22.3% with placebo). Current World Health Organization guidance does not recommend Vitamin A as a primary human immunodeficiency virus intervention.
- Chronic high-dose toxicity — sustained intake >10,000 international units/day of preformed retinol can produce hepatotoxicity, alopecia, bone loss, and increased fracture risk. Beta-carotene does not carry this risk because of feedback regulation of conversion.
- Beta-carotene in smokers — high-dose isolated beta-carotene (20-30 mg/day) increases lung cancer risk in current and former heavy smokers per the ATBC and CARET trials. Food-source beta-carotene is safe; the trial findings concern isolated high-dose supplements in this population.
- Drug interactions — orlistat, cholestyramine, mineral oil, and other fat-malabsorption drugs reduce Vitamin A absorption. Anticonvulsants (phenytoin, phenobarbital) accelerate Vitamin A catabolism and can deplete stores with chronic use.
Key Research Papers
- Green HN, Mellanby E (1928). Vitamin A as an anti-infective agent. British Medical Journal. — PubMed PMID: 20774205
- Sommer A et al. (1986). Impact of vitamin A supplementation on childhood mortality. A randomised controlled community trial. The Lancet. — PubMed PMID: 2871418
- Hussey GD, Klein M (1990). A randomized, controlled trial of vitamin A in children with severe measles. NEJM. — PubMed PMID: 2194128
- Huiming Y, Chaomin W, Meng M (2005). Vitamin A for treating measles in children. Cochrane Database Syst Rev 2005(4):CD001479. — PubMed PMID: 16235283
- Imdad A, Mayo-Wilson E, Haykal MR, Regan A, Sidhu J, Smith A, Bhutta ZA (2022). Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev 3:CD008524. — PubMed PMID: 35294044
- Oliveira JM, Allert R, East CE (2016). Vitamin A supplementation for postpartum women. Cochrane Database Syst Rev 3:CD005944. — PubMed PMID: 27012320
- Mucida D et al. (2007). Reciprocal TH17 and regulatory T cell differentiation mediated by retinoic acid. Science. — PubMed PMID: 17569825
- Iwata M et al. (2004). Retinoic acid imprints gut-homing specificity on T cells. Immunity. — PubMed PMID: 15485630
- Mora JR et al. (2006). Generation of gut-homing IgA-secreting B cells by intestinal dendritic cells. Science 314(5802):1157-60. — PubMed PMID: 17110582
- WHO (2011). Guideline: Vitamin A supplementation in infants and children 6-59 months of age. — PubMed
- Coutsoudis A et al. (1999). Randomized trial testing the effect of vitamin A supplementation on pregnancy outcomes and early mother-to-child HIV transmission in Durban, South Africa. AIDS. — PubMed PMID: 10465076
- Humphrey JH, Iliff PJ, Marinda ET, Mutasa K, et al.; ZVITAMBO Study Group (2006). Effects of a single large dose of vitamin A, given during the postpartum period to HIV-positive women and their infants, on child HIV infection, HIV-free survival, and mortality. Journal of Infectious Diseases 193(6):860-71. — PubMed PMID: 16479521
- Hanekom WA et al. (1997). Vitamin A status and therapy in childhood pulmonary tuberculosis. Journal of Pediatrics. — PubMed PMID: 9427903
- Visser ME, Grewal HM, Swart EC, Dhansay MA, et al. (2011). The effect of vitamin A and zinc supplementation on treatment outcomes in pulmonary tuberculosis: a randomized controlled trial. American Journal of Clinical Nutrition 93(1):93-100. — PubMed PMID: 21068353
- Stephensen CB (2001). Vitamin A, infection, and immune function. Annual Review of Nutrition 21:167-92. — PubMed PMID: 11375434
- Ross AC (2012). Vitamin A and retinoic acid in T cell-related immunity. American Journal of Clinical Nutrition. — PubMed PMID: 23053562
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin A Overview
- Vitamin A Benefits Hub
- Vitamin A for Vision
- Vitamin A for Skin
- Beta-Carotene vs Preformed
- Immune Boosting
- Vitamin D3 (RXR Partner)
- Vitamin C
- Zinc (RBP Synthesis)
- Measles
- Pneumonia
- Crohn's Disease
- Celiac Disease
- Organ Meats (Beef Liver)
- Omega-3 Fatty Acids
- Deficiency
- Toxicity
- History
- Sources