Chanca Piedra for Kidney Stones
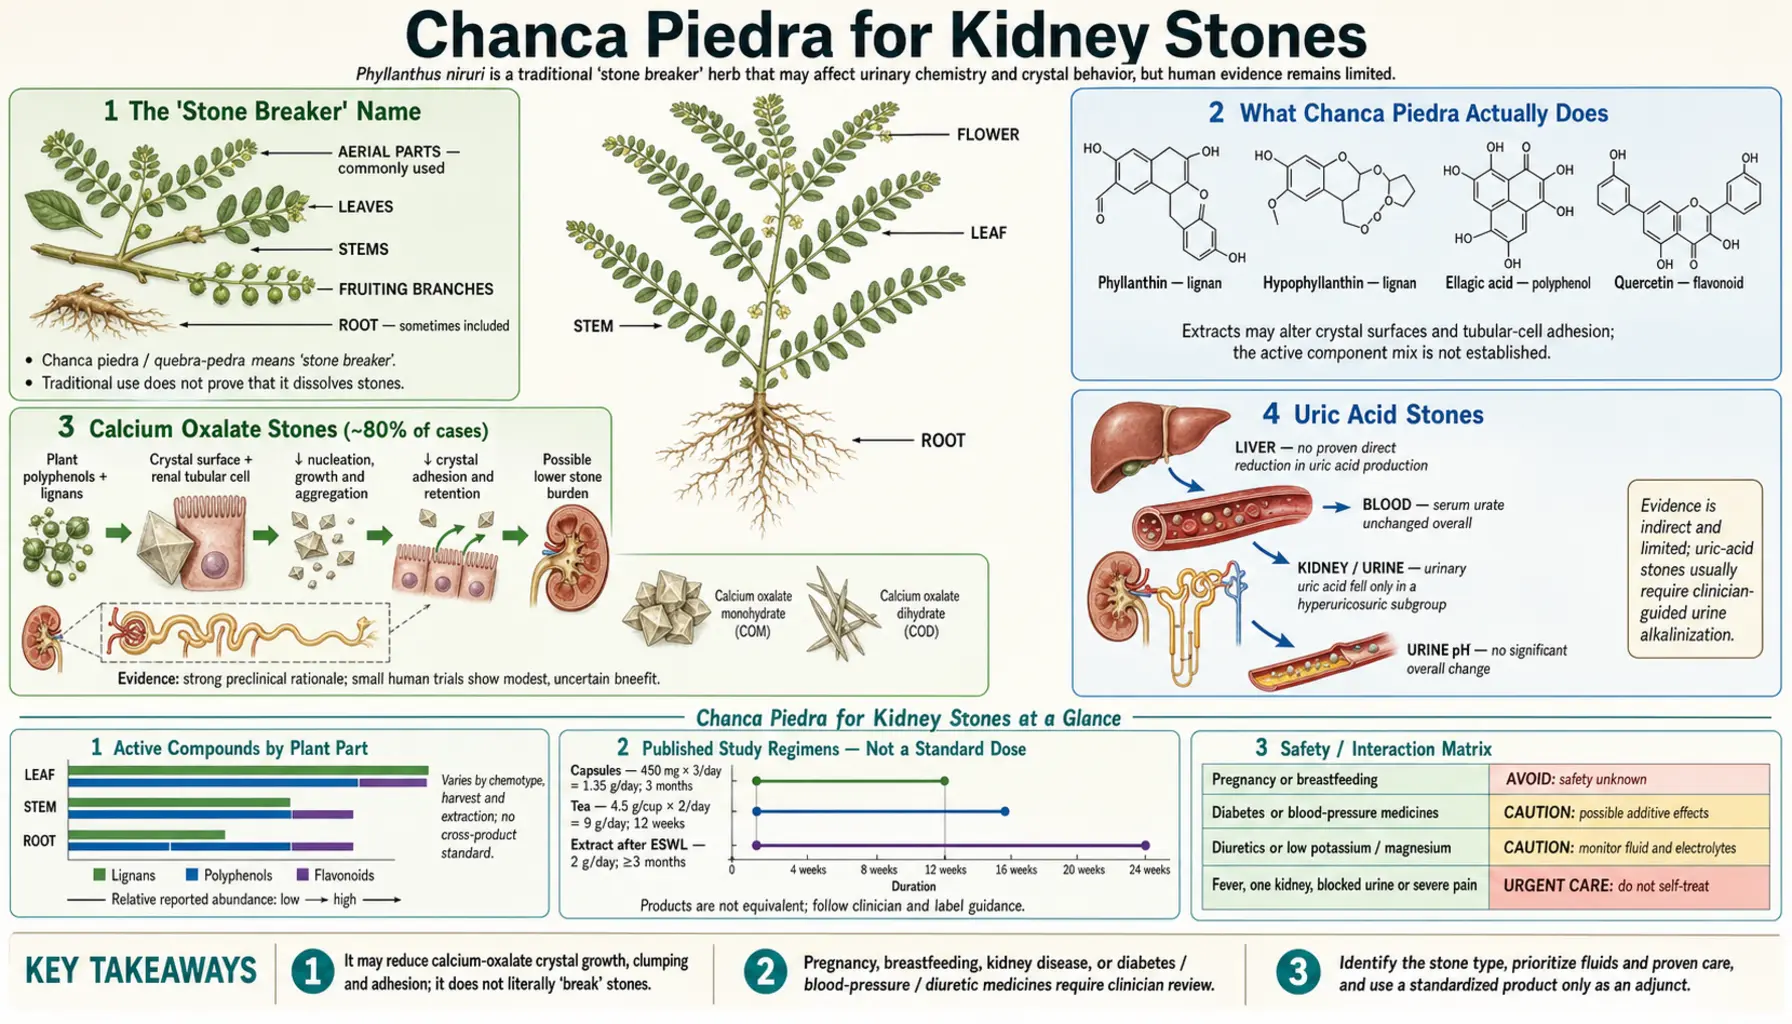
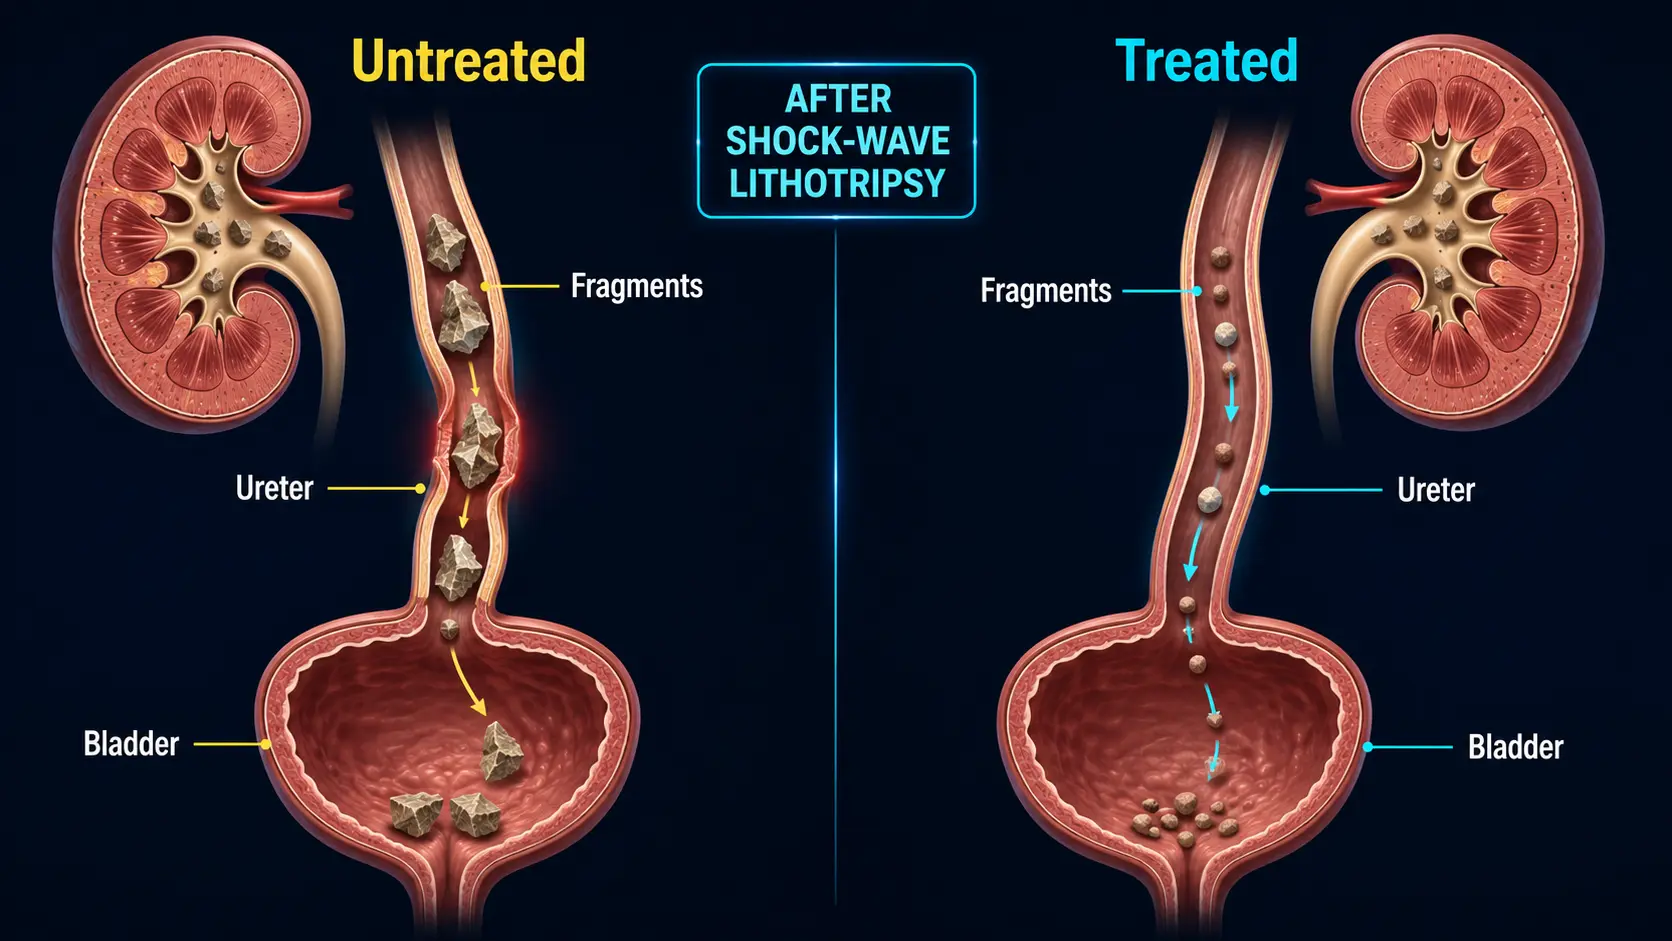
Chanca Piedra's English name is a literal translation of the Spanish — "stone breaker." Centuries of Amazonian and Andean folk use anticipated what modern pharmacology has refined: the herb does not literally dissolve mature stones, but in laboratory studies it reduces crystal growth and clumping and changes crystal shape, and in one trial it helped fragments clear from the lower part of the kidney after shock-wave lithotripsy (SWL). This page covers the patient-facing protocol — the evidence, the dosing, when it works, and where it doesn't.
Table of Contents
- The "Stone Breaker" Name
- What Chanca Piedra Actually Does
- Calcium Oxalate Stones (~80% of cases)
- Uric Acid Stones
- Cystine and Struvite Stones
- The Nishiura 2004 Trial
- Micali 2006: Post-SWL Fragment Passage
- Urinary Chemistry Effects
- Dosing Protocols
- Chanca Piedra vs Standard Prevention
- Evidence Quality
- Key Research Papers
- Connections
- Featured Videos
The "Stone Breaker" Name
Two languages, same translation. Quebra pedra in Portuguese (Brazilian Amazon) and chanca piedra in Spanish (Andean and Peruvian) both literally mean "stone breaker." The name is centuries old in indigenous Amazonian and Andean traditional medicine, where Phyllanthus niruri was prepared as a tea or decoction for "kidney pain" and the passage of stones in the urine. Modern pharmacological investigation began in the 1980s and 1990s at the nephrology division of the Federal University of São Paulo (UNIFESP), where N. Schor (senior author of the papers below), with M. E. Barros, I. P. Heilberg and colleagues, built the experimental framework for studying how the folk remedy might work.
What Chanca Piedra Actually Does
The traditional name oversells the mechanism. Chanca Piedra is not literally a stone-dissolving solvent. The substantiated effects are subtler and arguably more useful as a long-term strategy:
- Anti-crystallization — in laboratory urine, keeps calcium oxalate crystals small (it did not reduce their number)
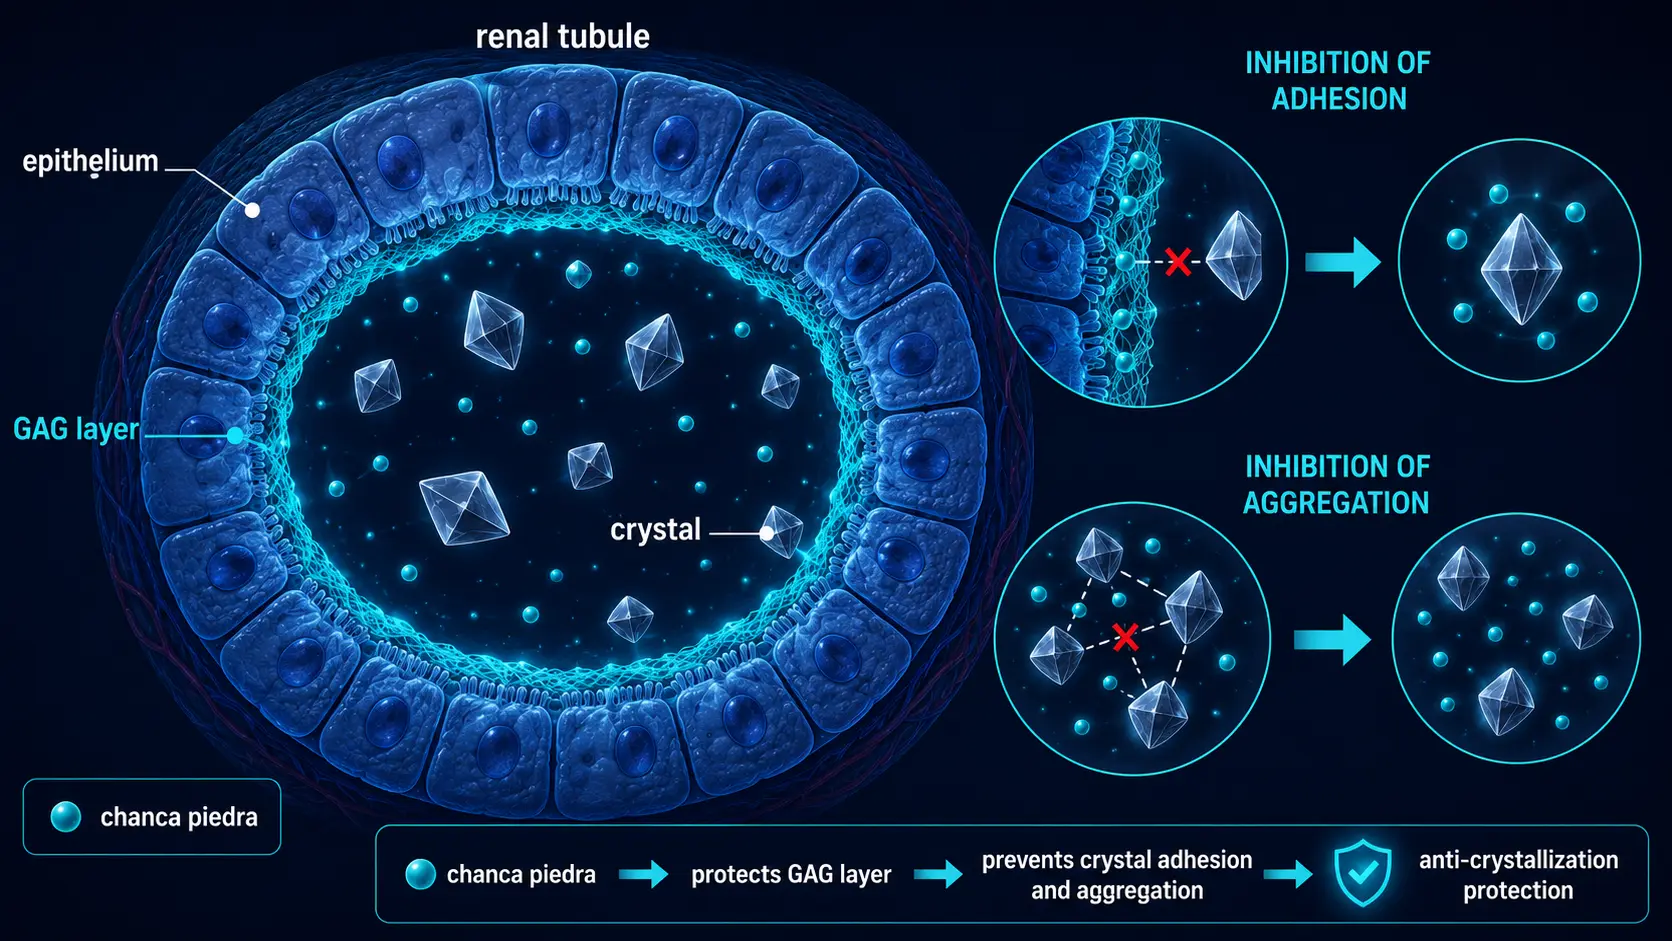
- Anti-aggregation — prevents small crystals from sticking together into larger, harder-to-pass stones
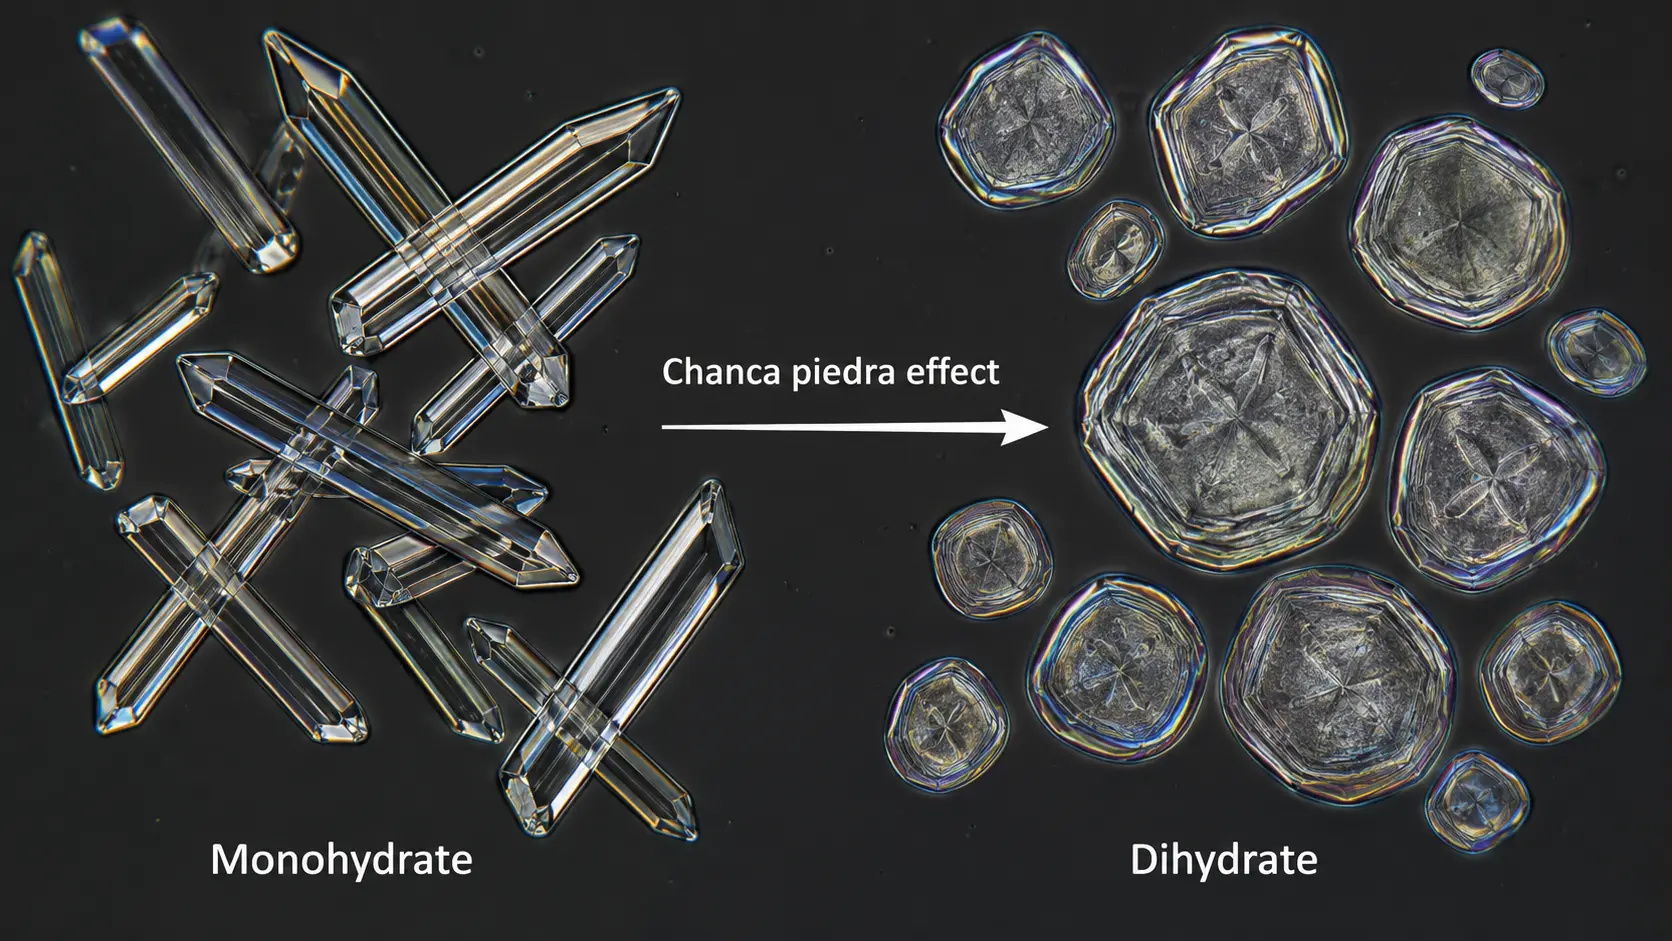
- Crystal-shape modification — shifts the crystal habit from sharp-edged calcium oxalate monohydrate (COM) toward rounder calcium oxalate dihydrate (COD), which slides through the ureter more easily
- Reduced epithelial adhesion — disrupts the glycosaminoglycan binding that lets crystals stick to renal tubular cells (the first step in stone growth)
- Reduced internal calcification — existing stones become more friable (less dense, more crumble-prone), improving fragment passage after SWL
These mechanisms come from laboratory work at UNIFESP. In kidney tubular cells grown in a dish, the extract strongly blocked the cells' uptake of calcium oxalate crystals (Campos & Schor 1999). In a 2003 dish experiment with rat and human urine, the extract did not stop calcium oxalate crystals forming — there were even more of them — but they were significantly smaller, and they clumped together less (Barros 2003). In rats with an implanted calcium oxalate seed, the extract strongly slowed stone growth (Freitas 2002). These are laboratory and animal findings, not results in people.
Calcium Oxalate Stones (~80% of cases)
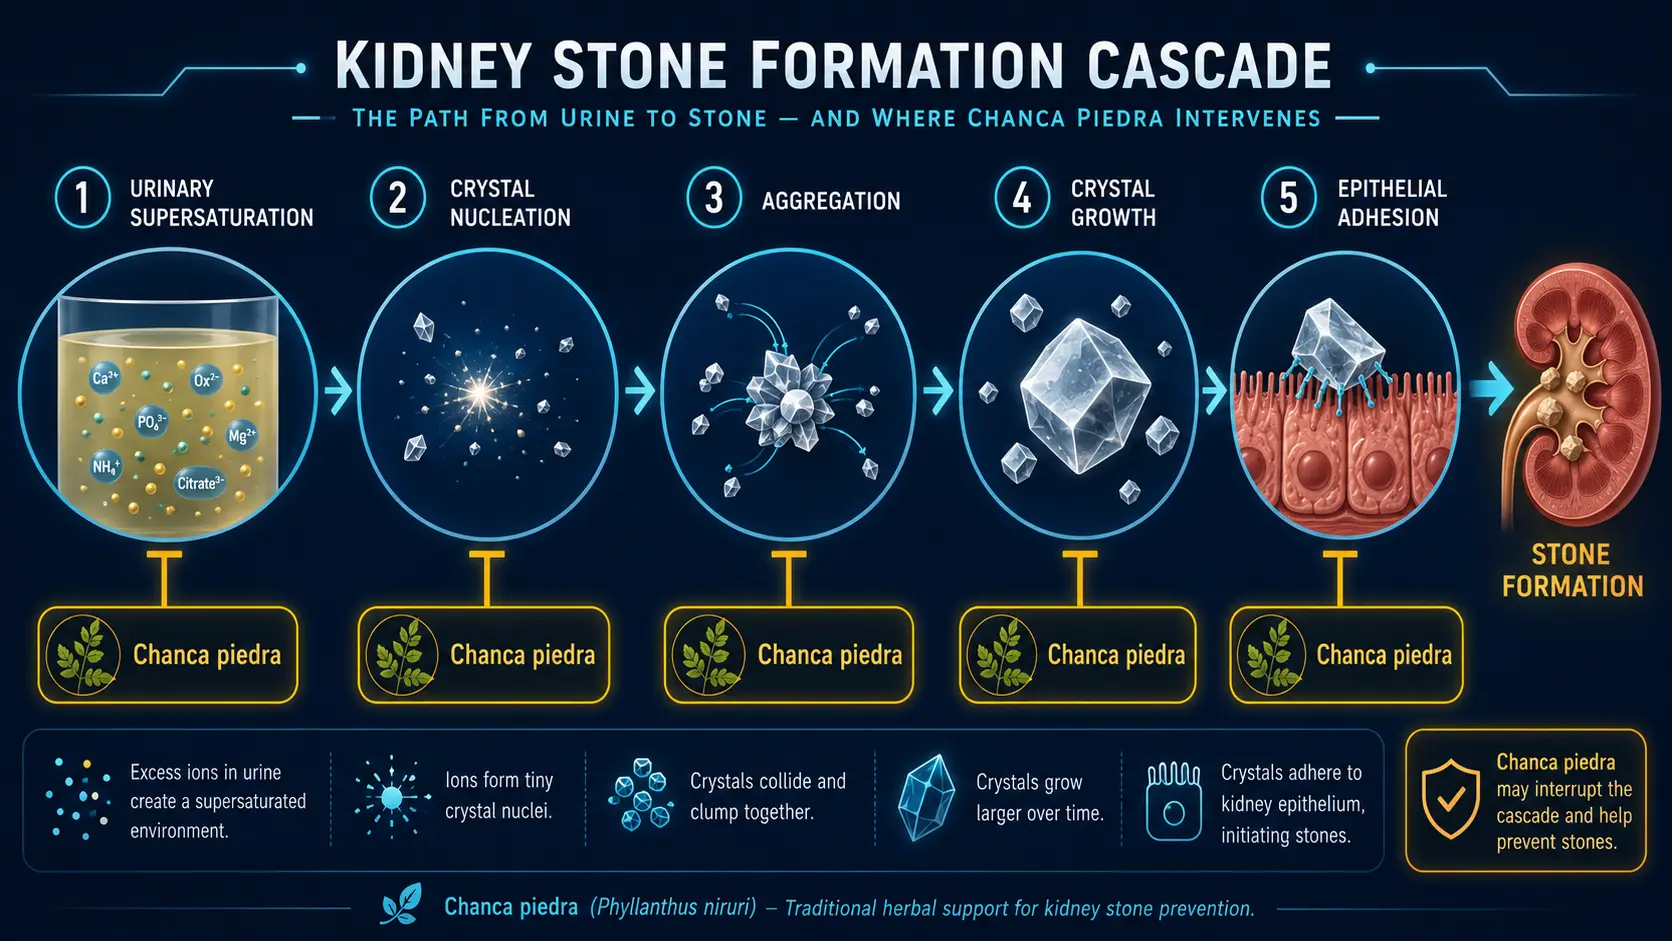
Calcium oxalate stones are by far the most common — about 80% of all kidney stones in the US. They form when urine becomes supersaturated with calcium and oxalate, when crystals nucleate in the renal collecting system, when those crystals stick to the tubular epithelium, and when more crystals layer onto the seed.
Chanca Piedra interrupts this cascade at multiple points. The Nishiura 2004 trial randomized 69 calcium stone formers to 450 mg Phyllanthus niruri capsules three times daily (33 patients) or placebo (36 patients) for three months. The hypercalciuric subgroup (those whose urine carried excess calcium) showed a significant reduction in urinary calcium — the principal driver of new stone formation. Across the whole group, the urine measurements did not change significantly, apart from a slight fall in urinary magnesium that stayed within the normal range, and stone passage and pain relief did not differ from placebo.
Practitioners describe Chanca Piedra for calcium oxalate stone-formers as an add-on to mainstream prevention (high fluid intake, dietary moderation of oxalate-rich foods like spinach and almonds, dietary calcium kept normal rather than restricted, salt and animal-protein moderation) for slowing or preventing new stone growth, not as a replacement for these foundations.
Uric Acid Stones
Uric acid stones account for about 10% of all kidney stones and are particularly common in patients with gout, metabolic syndrome, persistent low urine pH, or chronic diarrhea (which can produce acidic urine through bicarbonate loss). Uric acid is much more soluble at urinary pH above 6.5; below pH 5.5 it crystallizes.
Animal data and small human studies suggest Chanca Piedra has modest uricosuric (urate-excreting) and alkalinizing effects, lowering serum uric acid while raising urinary pH toward the soluble range. The mechanism is less well-characterized than the calcium oxalate effects, but is consistent with the xanthine oxidase inhibition documented in pharmacology studies (see Uric Acid & Gout).
For uric acid stone formers, Chanca Piedra is used as an add-on to potassium citrate or sodium bicarbonate, which remain the primary alkalinizing therapies, and to allopurinol or febuxostat, which directly lower serum urate.
Cystine and Struvite Stones
The honest answer for these less-common stone types: there is essentially no high-quality human data supporting Chanca Piedra. A few in-vitro studies suggest reduced struvite crystal nucleation in urinary-tract-infection models (struvite stones form in alkaline urine in the presence of urease-producing bacteria like Proteus). Cystinuria response to Chanca Piedra is anecdotal and absent from any randomized trial literature.
For cystine or struvite stones, the standard treatments are tiopronin or D-penicillamine for cystine, plus aggressive hydration and pH control, and antibiotics plus surgical clearance for struvite. No study shows Chanca Piedra standing in for them; at most it is used alongside them.
The Nishiura 2004 Trial
The single most-cited human study. Nishiura et al. (UNIFESP, São Paulo), published in Urological Research:
- Design: Randomized, placebo-controlled; 69 calcium stone formers (33 on Phyllanthus niruri, 36 on placebo)
- Intervention: 450 mg Phyllanthus niruri capsules, three times daily, for three months
- Outcomes: 24-hour urine calcium, uric acid, citrate, magnesium, oxalate, sodium and potassium; stone passage and pain relief
- Findings: In the hypercalciuric subset, urinary calcium fell significantly, from 4.8 to 3.4 mg per kg of body weight per 24 hours (about 29% lower). Across the whole group, urine measurements did not change significantly, apart from a slight fall in magnesium within the normal range. Stone passage and pain relief did not differ from placebo. No adverse effects reported.
Nishiura is the cleanest human study of Chanca Piedra for stone prevention. Its limits: the calcium effect came from a subset analysis, the sample was modest (69 patients), it ran at a single center, and it lasted only three months; the authors called for larger trials to confirm the finding. The mechanism it points to (hypercalciuria reduction) is biologically plausible and fits the laboratory work from the same UNIFESP group.
Micali 2006: Post-SWL Fragment Passage
The main trial of Chanca Piedra for stone passage after shock-wave treatment. Micali et al. (Italy), published in The Journal of Urology:
- Design: Randomized; 150 patients with calcium oxalate kidney stones up to 25 mm, in all parts of the kidney (56 of them with stones in the lower calyx), treated with extracorporeal shock-wave lithotripsy (ESWL)
- Intervention: 2 g/day Phyllanthus niruri extract for at least three months after ESWL (78 patients) vs no adjuvant (72 patients)
- Outcomes: Stone-free rates checked at 30, 60, 90 and 180 days, with the end point at 180 days
- Findings: Overall stone-free rate 93.5% vs 83.3%, a difference that was not statistically significant (p = 0.48). In the lower calyx (the part of the kidney where fragments often get stuck because of unfavorable anatomy) the stone-free rate was 93.7% vs 70.8% (p = 0.01). Re-treatment was needed in 39.7% vs 43.3% (p = 0.2). No side effects were recorded.
In this trial, the benefit of Chanca Piedra at 2 g/day for at least three months after shock-wave treatment was clear only for stones in the lower calyx (93.7% vs 70.8% stone-free); across all stone locations, the difference (93.5% vs 83.3%) was not statistically significant.
Pucci 2018 (International Brazilian Journal of Urology) was a different kind of study, not about lithotripsy: 56 patients with kidney stones under 10 mm drank Phyllanthus niruri infusion for 12 weeks, with no comparison group. Urinary oxalate fell in the patients with high oxalate and urinary uric acid in those with high uric acid, and the number of stones per patient fell from 3.2 to 2.0.
Urinary Chemistry Effects
From the Nishiura trial and supporting studies, the documented urinary chemistry effects:
- Calcium: reduced in hypercalciuric patients (significant); no change in normocalciuric patients
- Oxalate: no consistent change
- Citrate: variable; some studies show modest increase, which is favorable for stone prevention
- Magnesium: minimal change
- pH: mild alkalinization in some cohorts — favorable for uric acid stone prevention, neutral or mildly favorable for calcium oxalate
None of these are dramatic. Chanca Piedra is a tilt-the-scales intervention, not a transformation. For perspective: a thiazide diuretic typically reduces 24-hour urinary calcium by 25–50%; in the hypercalciuric subset of Nishiura, Chanca Piedra lowered urinary calcium from 4.8 to 3.4 mg per kg per 24 hours (about 29%), while in the whole group urinary calcium did not change significantly.
Dosing Protocols
Three dosing patterns: the first two are the doses used in the trials above; the third is what practitioners describe, and no trial has tested it.
Post-SWL fragment-passage adjuvant
- Dose: 2 g/day of Phyllanthus niruri extract (the Micali trial dose)
- Duration: at least 3 months after the procedure in the trial
- Usually combined with: high fluid intake (2.5+ L/day), follow-up imaging, urology follow-up
Hypercalciuria prevention
- Dose: 450 mg three times daily of standardized extract (the Nishiura protocol)
- Duration: 3 months in the trial, with 24-hour urine calcium measured before and after
- Usually combined with: dietary salt moderation, animal-protein moderation, normal-not-low dietary calcium, high fluid intake
General "stone history" maintenance
- Dose described by practitioners: 1–2 g/day of standardized extract (some practitioners use a 4-week-on / 1-week-off cycle); no trial has tested this
- Duration: ongoing as part of long-term prevention
- Usually combined with: 2.5–3 L/day fluid (the single most important intervention), dietary moderation, periodic urology follow-up
For details on standardization, extract types, and quality criteria, see Forms, Dosing & Standardization.
Chanca Piedra vs Standard Prevention
Standard medical stone prevention has decades of Level-1 randomized-trial evidence:
- Potassium citrate 10–20 mEq three times daily — the most-studied prevention drug, particularly effective in hypocitraturic and uric acid stone formers
- Thiazide diuretics — hydrochlorothiazide 25–50 mg/day or chlorthalidone 25–50 mg/day; reduce hypercalciuria by 25–50%
- Allopurinol — for uric acid stones and hyperuricosuric calcium oxalate stones
- Hydration — 2.5+ L/day urine output is the single most effective non-pharmacologic intervention
Chanca Piedra is used as a complement to these, not a replacement. Situations in which people describe adding it:
- People already on potassium citrate who want additional anti-crystallization support
- People who cannot tolerate potassium citrate's gastrointestinal (GI) effects (stomach upset, diarrhea, hyperkalemia in chronic kidney disease, CKD)
- People who cannot tolerate a thiazide's metabolic effects (hyperuricemia, hyperglycemia, hypokalemia)
- People who have just had SWL and hope to improve fragment clearance (in the Micali trial the clear benefit was for lower-calyx stones)
- People who have had multiple episodes and want a long-term anti-crystallization adjunct
The research does not support it as a substitute for evidence-based therapy in people with significant stone disease, recurrent stones, or genetic stone-formation syndromes (cystinuria, primary hyperoxaluria).
Evidence Quality
Well-supported:
- Anti-crystallization mechanism in vitro and in animal models
- Post-SWL fragment passage from the lower calyx (Micali 2006; across all stone locations the difference was not significant)
- Reduction of hypercalciuria in the hypercalciuric subset of calcium stone formers (Nishiura 2004)
- Excellent short-to-medium-term safety profile at studied doses
Plausible but preliminary:
- Uric acid stone prevention via mild alkalinization and uricosuric effects
- Citrate-promoting and pH-modifying effects
- Long-term recurrence reduction (most trials only ran 3 months)
Unsupported by evidence:
- Literal dissolution of mature kidney stones (despite the name)
- Cystine or struvite stone treatment as a primary or sole therapy
- Replacement of potassium citrate, thiazides, or allopurinol in indicated patients
- Treatment of acute renal colic (Chanca Piedra is for prevention/passage, not pain control)
Key Research Papers
- Nishiura JL, Campos AH, Boim MA, Heilberg IP, Schor N. Phyllanthus niruri normalizes elevated urinary calcium levels in calcium stone forming (CSF) patients. Urological Research, 2004 Oct;32(5):362-6. — PubMed PMID: 15221244
- Micali S, Sighinolfi MC, Celia A, et al. Can Phyllanthus niruri affect the efficacy of extracorporeal shock wave lithotripsy for renal stones? A randomized, prospective, long-term study. The Journal of Urology, 2006 Sep;176(3):1020-2. — PubMed PMID: 16890682
- Barros ME, Schor N, Boim MA. Effects of an aqueous extract from Phyllantus niruri on calcium oxalate crystallization in vitro. Urological Research, 2003 Feb;30(6):374-9. — PubMed PMID: 12599017
- Pucci ND, Marchini GS, Mazzucchi E, et al. Effect of Phyllanthus niruri on metabolic parameters of patients with kidney stone: a perspective for disease prevention. International Brazilian Journal of Urology, 2018. — PubMed PMID: 29617079
- Freitas AM et al. The effect of Phyllanthus niruri on urinary inhibitors of calcium oxalate crystallization. BJU International. — PubMed PMID: 12010223
- Campos AH, Schor N. Phyllanthus niruri inhibits calcium oxalate endocytosis by renal tubular cells. Nephron. — PubMed PMID: 10095174
PubMed Topic Searches
Connections
- All Herbs
- Chanca Piedra Benefits Hub
- Chanca Piedra Overview
- Liver Protection
- Uric Acid and Gout
- Blood Sugar
- Forms, Dosing and Standardization
- Active Compounds
- Safety and Drug Interactions
- Phyllanthus Species Comparison
- Kidney Stones
- Kidney Function
- Urinalysis
- Comprehensive Metabolic Panel
- Uric Acid
- Magnesium
- Potassium
- Calcium
- Gout
- History