Betel Leaf for Wound Care and Skin
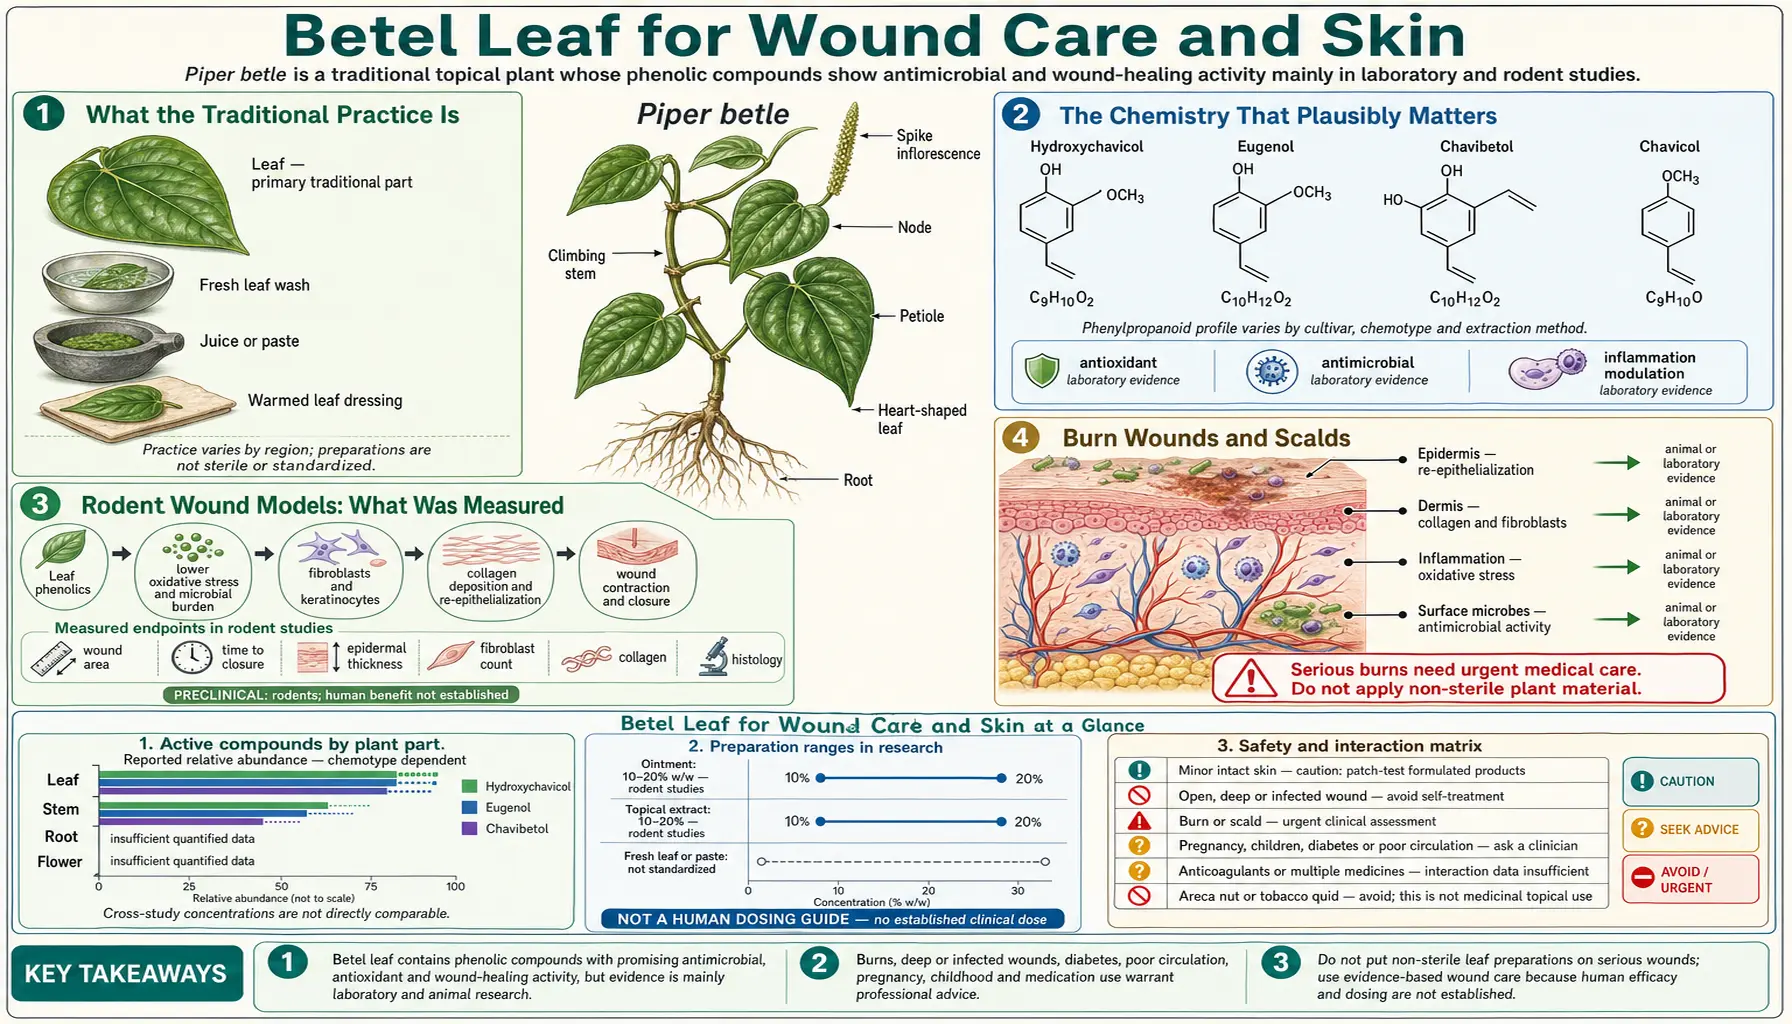
Of betel leaf's traditional uses, external application to wounds and skin complaints is the one where the modern laboratory evidence lines up most neatly with the folk practice. A crushed or warmed leaf laid on a cut delivers antibacterial phenols and polyphenol antioxidants directly to the site, which is a coherent thing to be doing. It is also the use where the honest caveats are easiest to state, because a wound dressing has to be judged on infection risk as much as on chemistry — and a leaf picked from a vine is not sterile.
This is a page about the leaf alone, applied to skin. It has nothing to do with chewing. If you or someone in your household chews betel quid, paan, gutka or any areca-containing product, the article that matters is Betel Leaf vs Betel Quid: Areca Nut and Cancer Risk — the quid is classified by International Agency for Research on Cancer (IARC) as a Group 1 human carcinogen.
Table of Contents
- What the Traditional Practice Is
- The Chemistry That Plausibly Matters
- Rodent Wound Models: What Was Measured
- Burn Wounds and Scalds
- Skin Pathogens Inhibited in Vitro
- Fungal Skin Infection: Tinea and Candida
- Antioxidant and Anti-Inflammatory Chemistry
- Modern Reformulations: Gels, Films and Nanofibres
- Itch, Eczema and Other Traditional Skin Uses
- Irritation, Contact Allergy and Infection Risk
- "Used for Centuries" Is Not "Sterile and Safe"
- When a Wound Needs a Clinician
- Key Research Papers
- Connections
- Featured Videos
What the Traditional Practice Is
Evidence tier: traditional use only.
The documented practices are specific, and worth recording accurately before assessing them.
- Fresh leaf as a dressing. A leaf is bruised or crushed and bound over a cut, graze, boil or small abscess. In some traditions the leaf is briefly warmed over a flame first, or smeared with a little coconut or mustard oil, which makes it pliable and helps it stay in contact.
- Leaf decoction as a wash. Leaves simmered in water and the cooled liquid used to bathe a wound, an infected nail fold, a fungal patch, or inflamed skin.
- Poultice for swelling and pain. Warmed leaves applied over a boil to bring it to a head, over an engorged or mastitic breast, or over a joint. Application to the breast in the postpartum period is a widespread Southeast Asian practice.
- Steam and vapour. Leaves added to hot water for inhalation or for a sitz bath, particularly in Malay and Indonesian tradition.
- Cosmetic and hygiene use. Leaf decoctions as a body wash or intimate wash for odour, which is an antimicrobial claim in cosmetic clothing.
What is notable is the consistency across unrelated traditions — Ayurvedic, Siddha, Malay, Javanese, Thai, Vietnamese and Filipino practice all describe roughly the same external uses. That consistency is a reason to take the plant seriously as a research subject. It is not by itself evidence of efficacy, because widely shared practices can be widely shared errors, and pre-antibiotic wound care was not a success story.
The Chemistry That Plausibly Matters
Evidence tier: preliminary, with well-characterised chemistry.
A wound is a good target for a topical plant phenol, because the barriers that defeat oral herbal medicine — poor absorption, first-pass metabolism, dilution in the whole body — do not apply. What you put on the wound is what the wound gets, at roughly the concentration you applied it.
- Hydroxychavicol (4-allylpyrocatechol) is the leaf's signature catechol and its main antibacterial. Catechols auto-oxidise and shed reactive oxygen species, which is a plausible antimicrobial mechanism and a plausible mechanism for tissue irritation at higher concentrations. Both follow from the same structure.
- Eugenol and chavibetol are lipophilic phenols that partition into microbial membranes and disrupt them. Eugenol is also mildly locally anaesthetic, which may explain the reported pain relief from a leaf poultice better than any anti-inflammatory mechanism does.
- Tannins precipitate surface proteins, producing the astringent, drawn-together feeling of a tannin-rich wash. Astringency has a genuine role in exudate control on a weeping wound, and it is probably underrated in explanations of traditional herbal wound care.
- Polyphenols and flavonoids scavenge free radicals. Whether that speeds healing is a much weaker inference than the antimicrobial argument — some reactive oxygen signalling is required for normal wound repair, and a wound that has been chemically flooded with antioxidants is not obviously better off.
- Caryophyllene and other terpenes contribute aroma and have their own reported anti-inflammatory activity in cell models.
Composition varies substantially by cultivar, region, leaf maturity and season, which is why nominally identical extract concentrations behave differently between studies. See GC-MS characterisation of Piper betle essential oil across cultivars.
Rodent Wound Models: What Was Measured
Evidence tier: preliminary (animal).
The wound-healing literature on Piper betle is almost entirely rodent work using three standard models, and it is worth understanding what each actually measures, because the phrase "accelerated wound healing" hides a lot.
- Excision wound model. A full-thickness circle of skin is removed and the open area is traced at intervals. The endpoint is percentage wound contraction and time to complete epithelialisation. Extracts of Piper betle have been reported to increase contraction rate and shorten epithelialisation time relative to untreated controls. The caveat is that rodent skin is loose and heals largely by contraction, whereas human skin is tethered and heals more by granulation and epithelialisation — so a contraction advantage in a rat does not straightforwardly transfer.
- Incision wound model. A sutured linear incision, with tensile strength measured after some days. This measures collagen deposition and cross-linking rather than closure speed, and reports of increased breaking strength are the more interesting finding of the two, since tensile strength is what determines whether a healed wound holds.
- Dead-space or granuloma model. An implant is placed subcutaneously and the granulation tissue that forms around it is analysed for hydroxyproline content, a proxy for collagen. Increased hydroxyproline is the standard biochemical claim for a pro-healing agent.
Reported mechanisms across these studies cluster on increased collagen deposition, faster re-epithelialisation, reduced local bacterial load, and reduced markers of oxidative stress in wound tissue. Read the primary reports rather than review summaries, because effect sizes and vehicle controls vary a great deal: wound-healing studies of Piper betle in rodent excision and incision models and collagen and hydroxyproline findings in granulation tissue.
Two published examples show what such studies measure. In a 2010 Malaysian study in diabetic rats, a betel extract applied to skin excision wounds for 10 days gave a wound contraction rate of 35.03, compared with 18.40 in untreated diabetic rats (p = 0.014), along with a higher total protein content in the wound. In a 2015 Vietnamese study in mice, a methanol extract of the leaf promoted healing of both burn and excision wounds, and it increased the growth of mouse fibroblast cells (the NIH3T3 cell line) in culture. Both are animal or cell results.
What does not exist is a decent randomized controlled trial of a Piper betle preparation on human wounds — not on surgical wounds, not on diabetic foot ulcers, not on venous leg ulcers, not on burns. That is the gap, and it is the whole gap.
The nearest thing to human data concerns skin around a surgical stoma (an opening of the bowel onto the belly), not a wound. At Chittagong Medical College and Hospital in Bangladesh, from June 1998 to December 2005, 495 children had their stoma cared for with betel leaves laid over zinc oxide paste and 128 with ostomy bags. Skin soreness (excoriation) occurred in 13 of the 495 leaf-group children (2.6%) and in 52 of the 128 bag-group children (40.65%); no allergic reactions were seen with the leaves, while 24 children (18.75%) reacted to the bag adhesive. The leaves cost about 15 cents a month, the bags about US$24. This was the hospital's report of its own practice, not a randomised trial.
Burn Wounds and Scalds
Evidence tier: preliminary (animal).
There is rodent burn-wound work, generally reporting faster closure and lower bacterial colonisation with betel-leaf preparations than with untreated controls, sometimes benchmarked against silver sulfadiazine. Burn models are a reasonable place to test an antibacterial dressing, because infection is what turns a survivable burn into a life-threatening one, and Pseudomonas aeruginosa in particular is a classic burn-wound coloniser.
These rodent results do not carry over to treating a burn at home. Burn care is one of the areas where folk remedies do the most measurable damage: applying oils, pastes, butter, toothpaste or crushed leaves to a fresh burn traps heat, contaminates the wound and obscures the assessment of depth that determines treatment. Standard burn first aid is cool running water for twenty minutes, removal of rings and tight clothing, a clean non-adherent covering, and medical assessment for anything deeper than superficial, anything larger than a few centimetres, and any burn to the face, hands, feet, genitals or across a joint. See burn-model studies of Piper betle and Pseudomonas aeruginosa.
Skin Pathogens Inhibited in Vitro
Evidence tier: preliminary (in vitro).
In-vitro screening reports activity of Piper betle extracts against several organisms of dermatological interest, with the usual pattern for plant phenols — better against Gram-positives than Gram-negatives.
- Staphylococcus aureus, the dominant cause of impetigo, folliculitis, boils, cellulitis and infected wounds, with reports extending to methicillin-resistant isolates. See Staphylococcus aureus.
- Streptococcus pyogenes, the other classic skin and soft-tissue pathogen, responsible for erysipelas and much cellulitis. See Streptococcus pyogenes.
- Pseudomonas aeruginosa, less reliably inhibited, as is typical for a Gram-negative with a formidable outer membrane and efflux capacity.
- Cutaneous Candida and dermatophytes, discussed in the next section.
The reasoning gap to name here is the one that gets skipped most often: in-vitro inhibition of methicillin-resistant Staphylococcus aureus (MRSA) is not treatment of a methicillin-resistant Staphylococcus aureus infection. A minimum inhibitory concentration in broth says nothing about whether the compound reaches viable concentrations in infected tissue, whether it survives contact with wound exudate and protein, or whether it can do anything about an organism inside a biofilm or an abscess cavity. Spreading redness, fever, or a wound that is getting worse rather than better are signs of spreading infection that is usually treated with antibiotics by mouth or drip. See the Piper betle and S. aureus in-vitro literature.
Fungal Skin Infection: Tinea and Candida
Evidence tier: preliminary (in vitro), with a small amount of clinical work.
The antifungal findings are among the more consistent in the whole Piper betle literature. Extracts and the essential oil inhibit Candida albicans and dermatophytes including Trichophyton and Microsporum species — the organisms responsible for tinea pedis, tinea corporis and tinea cruris. Reported mechanisms include membrane disruption and interference with fungal adherence and hyphal formation.
The small amount of clinical work is one Indian outpatient series (Bhadauria and Kumar, 2012). Ointments made from Piper betle flavonoids were tested on outpatients aged 3 months to 58 years with ringworm of the body, scalp, hands or feet (tinea corporis, tinea capitis, tinea manum or tinea pedis), all with a positive potassium hydroxide (KOH) test for fungus at the start. At the end of treatment, 64% of patients were reported cured completely, 24% showed significant improvement and 12% showed little improvement, with the ointments taking 1–5 weeks. The abstract describes no placebo group and no randomisation, so the series cannot show that the ointment did better than standard antifungal creams.
Superficial fungal infection is also, on paper, a good target for a topical botanical: the infection is in the stratum corneum, accessible to anything you rub on, and the standard treatments are themselves topical. But the comparison that matters is against the existing options, and topical terbinafine and the azoles have large, replicated trial bases with cure rates that a leaf decoction has never been shown to approach. No randomised trial has compared betel-leaf preparations with terbinafine or the azoles. See antifungal activity against dermatophytes, activity against Candida albicans, and Athlete's Foot. Compare Tea Tree — Benefits, where the human antifungal trial evidence is better developed.
Antioxidant and Anti-Inflammatory Chemistry
Evidence tier: preliminary (in vitro and animal).
Betel leaf performs strongly in the standard antioxidant assays — radical scavenging, reducing power, lipid-peroxidation inhibition — and hydroxychavicol is usually the largest contributor. Separately, in-vitro work in stimulated macrophage models reports suppression of nitric-oxide production and of pro-inflammatory cytokine release, and rodent studies report anti-inflammatory and analgesic effects in standard paw-oedema and pain models.
Two things keep this honest. First, performing well in a test-tube antioxidant assay is a chemical property, not a clinical one; most polyphenol-rich plants do it, and the assays were designed to characterise chemistry rather than predict outcomes. Second, hydroxychavicol is a catechol and therefore a pro-oxidant as readily as an antioxidant — the same compound generates reactive oxygen species under other conditions, which is precisely why it damages DNA in cell culture at higher concentrations. An extract described as a powerful antioxidant is, on a wound, also an agent with the capacity to injure cells. That is not a reason to dismiss it; it is a reason to be sceptical of anyone marketing it as gentle. See the antioxidant literature, the anti-inflammatory in-vitro work, and the genotoxicity and cytotoxicity findings.
Modern Reformulations: Gels, Films and Nanofibres
Evidence tier: preliminary (laboratory and animal), and this is where the field is actually moving.
The more interesting recent work is not on crushed leaves at all. Groups in India, Malaysia and Indonesia have incorporated Piper betle extract or its essential oil into engineered dressing materials: hydrogels, chitosan and alginate films, electrospun nanofibre mats, and nanoemulsions. The rationale is sound and addresses the real weaknesses of a poultice — a manufactured dressing is sterile, delivers a known quantity of extract, releases it in a controlled way over hours rather than all at once, maintains a moist wound environment, and can be removed without disturbing new tissue.
This is the most plausible route by which betel leaf could end up in real wound care, and it is also honestly at the stage of characterisation studies and small animal experiments. For example, a 2024 Vietnamese study loaded a betel-leaf extract into a chitosan and polyvinyl alcohol film containing montmorillonite clay; the authors measured the film's strength and how much wound fluid it absorbed, a release of extract lasting up to 24 hours, and activity against E. coli and S. aureus in laboratory tests. See work on Piper betle in engineered wound dressings, hydrogels and nanofibre mats.
Itch, Eczema and Other Traditional Skin Uses
Evidence tier: traditional use only.
Leaf washes and decoctions are traditionally used for itch, prickly heat, scabies, "ringworm" in the loose folk sense, body odour and various rashes. There is essentially no controlled human evidence for any of these, and one specific caution applies to inflammatory skin disease.
Eczema and psoriasis are barrier and immune disorders, not infections. The skin barrier in eczema is already compromised, which makes it more permeable and more reactive to applied substances, and pungent phenol-rich plant extracts are a recognised source of irritant and allergic contact dermatitis. Applying a strong botanical extract to eczematous skin can plausibly make it worse, and a flare that gets blamed on the underlying condition may be a contact reaction to the treatment. See Eczema and Psoriasis, and if the aim is a botanical with a better-characterised profile on inflamed skin, see Calendula for Skin and Wound Healing or Aloe Vera — Benefits. Relevant background: topical Piper betle and skin conditions.
Irritation, Contact Allergy and Infection Risk
- Contact dermatitis. Eugenol is a well-recognised fragrance allergen and appears in standard patch-test series. Anyone sensitised to eugenol or to clove, cinnamon or balsam of Peru may react to betel leaf. A 24-hour test on a small patch of intact skin is a common way to check for a reaction before a preparation goes on a wound.
- Irritation. Concentrated preparations and undiluted essential oil can burn skin and mucosa.
- Skin colour changes (contact leukomelanosis). In Taiwan, a 1999 dermatology survey described 15 people, seen in 1997, who had used steamed betel leaves as facial dressings. All had a temporary redness in the first few days of use (9 also had stinging), and a bleaching effect became noticeable about 1 week to 1 month later; 8 reported darker patches and confetti-like pale spots after too much sun. In India, a 2020 report described 10 children aged 4 to 9 with the same light-and-dark patches (leukomelanosis) on the chest or forehead after betel leaves were applied as a home remedy for a cough or cold.
- Contamination. A leaf picked from a vine carries environmental bacteria and fungal spores, and possibly pesticide residue. Fresh produce has been implicated in foodborne outbreaks precisely because leafy surfaces hold organisms well. Applying an unsterile leaf to an open wound introduces organisms into tissue that has lost its barrier — the antibacterial phenols in the leaf do not make the leaf's own surface sterile.
- Delay. The most common real harm from home wound care is not the remedy, it is the days lost before someone with spreading cellulitis, a deep abscess, an infected diabetic foot ulcer or a tetanus-prone wound seeks care.
- Tetanus. Any puncture, any wound contaminated with soil, and any deep or dirty wound raises the question of tetanus immunisation status. A leaf does nothing about Clostridium tetani. See Clostridium tetani.
- Bleeding. Betel-leaf constituents have shown antiplatelet activity in laboratory work — preliminary, but worth knowing before applying a preparation liberally to a bleeding wound or before surgery.
- Pregnancy and breastfeeding. There is no good safety data on the essential oil or concentrated extracts in pregnancy or breastfeeding. The traditional practice of applying warmed leaves to an engorged breast is topical and low-exposure, but anything applied to a breast can be swallowed by the infant unless it is washed off before feeding.
"Used for Centuries" Is Not "Sterile and Safe"
The longevity argument deserves a direct answer, because it appears in every discussion of traditional wound care.
Long use tells you a practice was tolerated, available and culturally embedded. It does not tell you the practice worked, because pre-antibiotic wound care operated in a world where wound infection, sepsis and amputation were ordinary events and where nobody was counting outcomes. Most cuts heal regardless of what is put on them, which is exactly the condition under which an ineffective remedy accumulates centuries of testimonials. The traditions themselves are often more careful than their modern advocates: classical texts warn against excess and specify conditions in which a preparation should not be used.
The consistency of external betel use across unrelated cultures is a genuine reason to fund research on the plant — and researchers have, which is why there is a rodent literature and a nanofibre literature to write about. It is not evidence that a leaf works as well as a sterile dressing.
When a Wound Needs a Clinician
These signs are ones clinics treat as needing care, whatever has been put on the wound:
- Spreading redness, warmth or swelling around a wound, red streaks tracking away from it, fever or feeling unwell — these suggest cellulitis or a deeper infection.
- Increasing pain, particularly pain out of proportion to the wound's appearance.
- Pus, a foul smell, or a wound that is getting worse rather than better after 48 hours.
- A wound that will not stop bleeding, gapes open, or is deep enough to need closure.
- Any bite — animal or human — and any puncture wound, including standing on a nail.
- Any wound with soil, glass, grit or other material in it, or where tetanus cover is uncertain.
- Any burn deeper than superficial, larger than a few centimetres, or on the face, hands, feet, genitals or over a joint.
- Any wound at all in a person with diabetes, peripheral arterial disease, peripheral neuropathy, or a suppressed immune system — especially on the foot. A foot ulcer in diabetes is a limb-threatening problem. See Type 2 Diabetes.
- A sore, ulcer or lesion that has not healed in a few weeks. Non-healing has causes, including malignancy, that clinics examine for.
Key Research Papers
- Keat EC, Razak SS, Fadil NM, et al. (2010). The effect of Piper betel extract on the wound healing process in experimentally induced diabetic rats. La Clinica Terapeutica — PubMed PMID: 20499023
- Lien LT, Tho NT, Ha DM, et al. (2015). Influence of phytochemicals in piper betle linn leaf extract on wound healing. Burns & Trauma — PubMed PMID: 27574669
- Banu T, Talukder R, Chowdhury TK, Hoque M (2007). Betel leaf in stoma care. Journal of Pediatric Surgery — PubMed PMID: 17618892
- Bhadauria S, Kumar P (2012). Broad spectrum antidermatophytic drug for the control of tinea infection in human beings. Mycoses — PubMed PMID: 21929713
- Liao YL, Chiang YC, Tsai TF, et al. (1999). Contact leukomelanosis induced by the leaves of Piper betle L. (Piperaceae): a clinical and histopathologic survey. Journal of the American Academy of Dermatology — PubMed PMID: 10188678
- Karthikeyan K, Gopinath H, Kaleeswaran V, Vimal M (2020). Leaves that leave their mark: A case series of pediatric Piper Betle-induced leukomelanosis. Pediatric Dermatology — PubMed PMID: 32621618
- Tran TNT, Le NH, Tran QM (2024). Effects of montmorillonite on the loading and release of Piper betle L. extract applied for wound dressing based on chitosan/polyvinyl alcohol. International Journal of Biological Macromolecules — PubMed PMID: 38777011
- Tran TNT, Tran QM, Le NH (2025). Optimization of Piper betle L. extraction under ultrasound and its effects on chitosan/polyvinyl alcohol film properties for wound dressing. International Journal of Biological Macromolecules — PubMed PMID: 39675616
PubMed Topic Searches
- Wound-healing activity of Piper betle leaf extract in rodent excision and incision models — the core preclinical basis for the traditional poultice. — Search PubMed
- Collagen deposition and hydroxyproline content in granulation tissue — the biochemical endpoint behind "accelerated healing". — Search PubMed
- Burn-wound models of Piper betle preparations.
- Piper betle incorporated into hydrogels, films and electrospun nanofibre dressings — the most plausible translational route. — Search PubMed
- In-vitro activity against Staphylococcus aureus, including MRSA isolates. — Search PubMed
- Antibacterial screening of the leaf and its phenolic constituents. — Search PubMed
- Antifungal activity against dermatophytes.
- Antifungal activity against Candida albicans.
- Antioxidant and radical-scavenging activity of the leaf and hydroxychavicol. — Search PubMed
- Anti-inflammatory activity in macrophage and cytokine models.
- Genotoxicity and cytotoxicity of Piper betle extract at higher concentrations — the pro-oxidant counterweight. — Search PubMed
- Eugenol as a fragrance allergen in patch-test series — the basis of the contact-allergy caution.
- Essential-oil composition by GC-MS across cultivars — why extract potency is not standardised.
- Topical Piper betle and inflammatory skin conditions — a thin literature relative to the traditional claim.
Connections
- All Herbs
- Betel Leaf — Benefits Deep Dive — the hub, with the chemistry and evidence-tier overview.
- Betel Leaf for Oral Health and Antibacterial Action — the same phenols, applied in the mouth.
- Betel Quid, Areca Nut and Cancer Risk — the risk article, and the one that matters most if anyone in the household chews.
- Betel Leaf (Piper betle) — the main topic page.
- Betel Nut (Areca catechu) — the other plant entirely.
- Dermatology — the skin section.
- Eczema — a barrier disorder, where botanical extracts can worsen things.
- Psoriasis — immune-driven, not infectious.
- Acne — another common target for antibacterial botanicals.
- Athlete's Foot — the fungal infection the antifungal data is most relevant to.
- Staphylococcus aureus — the dominant skin and wound pathogen.
- Streptococcus pyogenes — cellulitis and erysipelas.
- Pseudomonas aeruginosa — the classic burn-wound coloniser.
- Clostridium tetani — why a dirty wound is a vaccination question.
- Type 2 Diabetes — why no foot wound in diabetes is a candidate for a home remedy.
- Calendula for Skin and Wound Healing — the classic Western wound botanical.
- Gotu Kola — Benefits — the botanical with the best collagen and wound-healing evidence.
- Aloe Vera — Benefits — burns and soothing, with real if mixed trial data.
- Tea Tree — Benefits — the better-evidenced topical antimicrobial essential oil.
- Neem — Benefits — the other South Asian antibacterial applied to skin.
- Turmeric — Benefits — traditionally paired with betel leaf in Indian wound practice.
Educational information only, not medical advice. There is no controlled human trial evidence that Piper betle heals wounds, and nearly everything on this page is rodent or cell-culture work. Standard burn first aid does not include crushed leaves, oils or pastes, and wounds in diabetes, peripheral arterial disease, neuropathy or immunosuppression carry a high risk of serious infection. Undiluted essential oil can burn broken skin, eugenol is a recognised contact allergen, and betel-leaf dressings have been reported to cause skin colour changes. The warning signs listed above, and any wound that has not healed in a few weeks, are ones clinics treat as needing care.