⚠ Evidence warning: Clinical trials or other evidence do not support the claims that enhanced curcumin forms raise exposure 7 to 30 fold, that curcumin extracts match ibuprofen and diclofenac for knee osteoarthritis pain with fewer gastrointestinal side effects, and that turmeric-consuming populations in India have markedly lower Alzheimer's prevalence. This page keeps it as a report of what people, websites or other media say.
Turmeric — Benefits Deep Dive
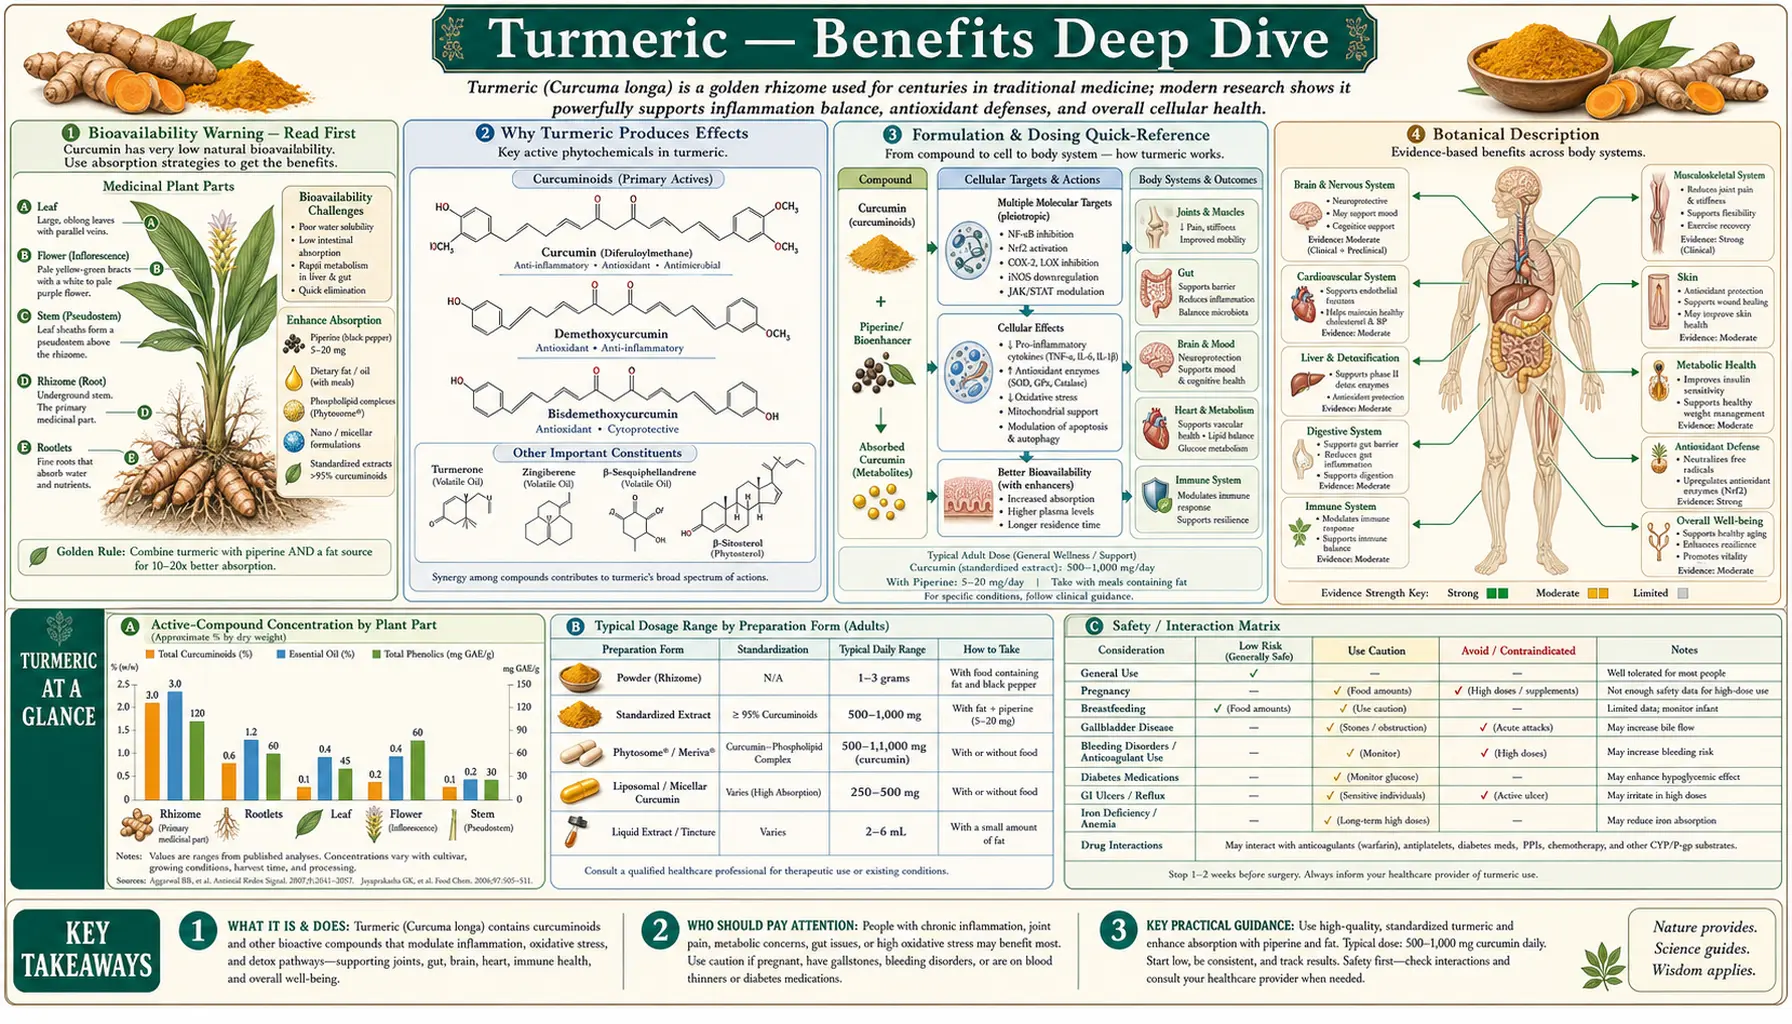
Turmeric (Curcuma longa) is the dried, ground rhizome of a tropical Asian plant in the ginger family. Its principal bioactive is curcumin, the bright-yellow polyphenolic curcuminoid that comprises only 2–7% of the dried root by weight. Curcumin is among the most-researched single herbal compounds in modern medicine — more than 10,000 indexed peer-reviewed papers and several hundred completed human clinical trials — yet the central practical issue for anyone using turmeric is not whether it works but whether it gets absorbed. Free curcumin has less than 1% oral bioavailability. Pure turmeric powder taken without an absorption enhancer is largely excreted in the stool unchanged. In the Shoba 1998 study, 20 mg of piperine (the active compound in black pepper) taken with 2 g of curcumin raised curcumin absorption in human volunteers by about 2000%. Curcumin-phospholipid complexes, colloidal submicron-particle curcumin, solid lipid curcumin particles (SLCP), and micellar curcumin increase systemic exposure over standard curcumin by amounts that differ from formulation to formulation and study to study (see the quick-reference below). Phospholipid complexes, submicron emulsions, solid lipid particles, and liquid micelle formulations increase systemic exposure 7–30 fold over standard curcumin. Turmeric powder in tea or curry produces minimal systemic curcumin levels — the four deep-dive pages below walk through the anti-inflammatory, hepatoprotective, and cognitive evidence base, and the fourth is dedicated entirely to the bioavailability question that determines whether any of the other three apply to you.
Deep-Dive Articles
Anti-Inflammatory & Joint Health
The strongest curcumin evidence base. The Daily 2016 randomized controlled trial (RCT) meta-analysis of arthritis trials (8 trials, n=606, mostly knee osteoarthritis plus rheumatoid arthritis) found turmeric/curcumin lowered pain compared with placebo, and pain relief was not significantly different from pain medicines such as ibuprofen and diclofenac; the pain-medicine groups showed similar side effects, including gastrointestinal symptoms, and the authors judged the evidence not sufficient to draw definitive conclusions. The Henrotin 2013 review covers the same question. Curcumin extracts are roughly comparable to ibuprofen and diclofenac for knee osteoarthritis pain, with fewer gastrointestinal side effects — a finding that has changed orthopedic practice in some settings. Multi-target mechanism: cyclooxygenase-2 (COX-2) inhibition, NF-kB blockade, suppression of tumor necrosis factor-alpha and interleukin-6 (IL-6), and downregulation of MMP-3 and MMP-13 cartilage-degrading enzymes. Practical dosing with curcumin-phospholipid complexes (phytosome) and standardized 95% curcuminoid extracts.
Read the deep dive →Liver Health & Detox
Curcumin is a potent Nrf2 activator, inducing Phase II detoxification enzymes (glutathione S-transferase, nicotinamide adenine dinucleotide (NAD)(P)H quinone dehydrogenase 1, heme oxygenase 1) that conjugate and clear xenobiotics, environmental toxins, and reactive metabolites. The Rahmani 2016 non-alcoholic fatty liver disease (NAFLD) trial showed measurable alanine aminotransferase (ALT)/aspartate aminotransferase (AST) reductions and liver fat clearance. Hepatoprotection in chemotherapy-induced and acetaminophen-induced liver injury (animal-model). Classical cholagogue effect on bile flow. Important caveat: rare cases of drug-induced liver injury (DILI) reported with high-dose bioavailability-enhanced curcumin products.
Read the deep dive →Brain Health & Cognition
The Small 2018 UCLA 18-month randomized trial of a colloidal submicron-particle curcumin (90 mg twice daily) in 40 non-demented adults aged 51–84 showed improvements on both verbal and visual memory testing compared with placebo. On FDDNP-PET imaging (a scan whose signal reflects amyloid and tau together), the signal fell in the amygdala with curcumin; in the hypothalamus it did not change with curcumin but rose with placebo. Indian dementia epidemiology has long shown markedly lower Alzheimer's prevalence in turmeric-consuming populations. A 2001 study of a rural community in India (the Indo-US study) reported some of the lowest Alzheimer's incidence rates ever recorded (4.7 per 1,000 person-years, against 17.5 in a US comparison community); the study did not measure turmeric intake, and its authors cautioned that cultural factors and other confounders limit how the finding can be read. Mechanism: brain-derived neurotrophic factor (BDNF) upregulation, neuroinflammation suppression (tumor necrosis factor-alpha, IL-1beta, microglial activation), and amyloid disaggregation. Curcumin crosses the blood-brain barrier — one of the few polyphenols that does so meaningfully.
Read the deep dive →Bioavailability & Forms (CRITICAL)
The single most important page for anyone buying turmeric or curcumin. Free curcumin has <1% oral bioavailability. Piperine, an inhibitor of hepatic and intestinal glucuronidation, raised absorption ~2000% at 20 mg in one human study. A curcumin-phosphatidylcholine complex (phytosome) achieves ~29x bioavailability. Colloidal submicron-particle curcumin ~27x. Solid lipid curcumin particles (SLCP) gave detectable plasma curcumin where the same amount of unformulated extract gave none. Micellar curcumin ~185x in reported comparisons. Standard turmeric tea produces minimal systemic effect. Detailed formulation comparison and dosing equivalence table.
Read the deep dive →Table of Contents
Bioavailability Warning — Read First
Critical practical issue: Most published clinical trials of turmeric/curcumin use one of four bioavailability-enhanced formulations — a curcumin-phosphatidylcholine phytosome, a colloidal submicron curcumin suspension, solid lipid curcumin particles (SLCP), or a liquid micellar curcumin. Standard turmeric powder — whether in food, tea, or unenhanced capsules — has <1% oral bioavailability and produces effectively zero systemic curcumin levels. The clinical effects described on the four sub-articles below come from trials of concentrated forms, not from a teaspoon of turmeric in milk or a curry. Those trials used either (1) a bioavailability-enhanced commercial extract, (2) standard turmeric paired with piperine (from black pepper or a piperine extract; in the Shoba 1998 study, 20 mg of piperine with 2 g of curcumin raised absorption ~2000%), or (3) very high doses of pure 95%-curcuminoid extract (which still absorb poorly but reach therapeutic blood levels at gram-scale daily intake). Turmeric powder is not curcumin supplement. Full details on the Bioavailability and Forms page.
Why Turmeric Produces Effects
Turmeric is unusual among medicinal plants in that one chemical compound — curcumin — accounts for the great majority of its documented biological activity. (Minor curcuminoids demethoxycurcumin and bisdemethoxycurcumin contribute, and the essential oil fraction containing turmerones has some independent activity, but standardized 95%-curcuminoid extracts produce most of what turmeric-the-spice does.) What is unusual about curcumin is that it is a pleiotropic multi-target compound — it modulates dozens of distinct molecular targets rather than acting through one specific receptor or enzyme.
The principal mechanism pathways, each of which contributes to one or more of the deep-dive topics below:
- NF-kB transcription factor inhibition — NF-kB is the master regulator of inflammatory gene transcription. Curcumin inhibits NF-kB nuclear translocation, blocking transcription of tumor necrosis factor-alpha, IL-1beta, interleukin-6, cyclooxygenase-2, iNOS, and dozens of other inflammatory genes. This single mechanism explains a large fraction of the anti-inflammatory and joint effects.
- Cyclooxygenase-2 and LOX (lipoxygenase) inhibition — direct enzyme inhibition reduces production of prostaglandin and leukotriene mediators of pain and inflammation. Mechanistically similar to nonsteroidal anti-inflammatory drugs (NSAIDs) but without the gastric mucosal toxicity (curcumin actually protects gastric mucosa in animal models).
- Nrf2 / ARE pathway activation — curcumin is a potent activator of nuclear factor erythroid 2-related factor 2 (Nrf2), which translocates to the nucleus and binds antioxidant response elements (ARE) to induce Phase II detoxification enzymes — glutathione S-transferase, nicotinamide adenine dinucleotide(P)H quinone dehydrogenase 1, heme oxygenase 1, and gamma-glutamylcysteine ligase.
- STAT3 inhibition — signal transducer and activator of transcription 3 is constitutively activated in many cancers and in chronic inflammation. Curcumin inhibition is one of the mechanistic bases for the extensive oncology literature.
- Brain-derived neurotrophic factor upregulation — brain-derived neurotrophic factor supports neuronal survival and synaptic plasticity. Curcumin's brain-derived neurotrophic factor effect contributes to the cognitive and mood applications.
- Amyloid-beta disaggregation — curcumin binds amyloid-beta peptide and inhibits both aggregation and fibril formation in vitro and in animal models of Alzheimer's disease.
- Direct antioxidant scavenging — the conjugated double-bond system in the curcumin molecule directly scavenges reactive oxygen species, though plasma concentrations achievable in vivo limit how much this contributes versus the gene-induction mechanisms above.
This multi-target pleiotropic action is also what frustrates pharmaceutical development — curcumin is a "promiscuous" drug-discovery target that does too many things at once for tidy single-mechanism trials. The pragmatic clinical observation, validated across hundreds of human studies, is that the multi-target action produces real if modest effects on multiple inflammatory conditions in real patients, with an unusually favorable safety profile.
Formulation & Dosing Quick-Reference
The four most-studied bioavailability-enhanced curcumin formulations, with typical clinical-trial doses and relative bioavailability versus unformulated 95% curcuminoid extract:
- Curcumin-phosphatidylcholine phytosome — approximately 29x bioavailability. Typical trial dose: 500 mg twice daily (delivering ~100 mg curcuminoids). Used in most of the osteoarthritis literature including the Belcaro 2010 and 2014 long-term studies.
- Colloidal submicron-particle curcumin suspension — approximately 27x bioavailability. Typical dose: 90 mg curcumin twice daily. Used in the Small 2018 UCLA cognitive trial.
- Solid lipid curcumin particles (SLCP) — in the Gota 2010 study, 650 mg gave a mean peak plasma curcumin of 22.43 ng/mL, while the same amount of unformulated 95% curcuminoid extract gave no detectable curcumin, with high person-to-person variability. Typical dose: 400–1000 mg/day. Free unconjugated curcumin in plasma.
- Liquid micellar curcumin — approximately 185x bioavailability in reported comparisons. Typical dose: 80–200 mg/day. Liquid formulation in soft-gel capsules.
- Standard 95%-curcuminoid extract + 5–20 mg piperine — the Shoba 1998 trial found that 20 mg of piperine with a single 2 g dose of curcumin raised absorption ~2000% in human volunteers (154% in rats); lower piperine doses were not tested. Typical dose: 500–1000 mg curcuminoids with 5–20 mg piperine, two to three times daily.
- Plain turmeric powder — for culinary use, immune support tradition, and gentle digestive stimulation. Negligible systemic curcumin. This form does not produce anti-inflammatory blood levels of curcumin.
Choice of formulation depends on cost, label transparency about formulation, and personal response. For most clinical applications discussed in the four sub-articles, the curcumin-phosphatidylcholine phytosome and colloidal submicron-particle curcumin have the most published human trial data. Solid lipid curcumin particles are often chosen for cognitive applications because of reported higher free-curcumin brain penetration. See the Bioavailability and Forms page for a detailed formulation comparison.
Key Research Papers
- Aggarwal BB, Harikumar KB (2009). Potential therapeutic effects of curcumin, the anti-inflammatory agent, against neurodegenerative, cardiovascular, pulmonary, metabolic, autoimmune and neoplastic diseases. International Journal of Biochemistry & Cell Biology. — PubMed PMID: 18662800
- Hewlings SJ, Kalman DS (2017). Curcumin: A review of its effects on human health. Foods. — PubMed PMID: 29065496
- Shoba G et al. (1998). Influence of piperine on the pharmacokinetics of curcumin in animals and human volunteers. Planta Medica. — PubMed PMID: 9619120
- Daily JW et al. (2016). Efficacy of turmeric extracts and curcumin for alleviating the symptoms of joint arthritis: A systematic review and meta-analysis of randomized clinical trials. Journal of Medicinal Food. — PubMed PMID: 27533649
- Small GW et al. (2018). Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. American Journal of Geriatric Psychiatry. — PubMed PMID: 29246725
External Authoritative Resources
- Linus Pauling Institute — Curcumin Micronutrient Information Center — the most authoritative scientific summary of curcumin biology and bioavailability
- U.S. National Center for Complementary and Integrative Health (NCCIH) (National Center for Complementary and Integrative Health) — Turmeric Fact Sheet
- LiverTox (U.S. National Institutes of Health, NIH) — Turmeric
- Drugs.com — Turmeric / Curcumin Monograph
- PubMed — All research on curcumin / turmeric (~10,000+ papers)
Connections
- All Herbs
- Turmeric (Main Page)
- Turmeric for Joint Health
- Turmeric for Liver Health
- Turmeric for Brain Health
- Bioavailability & Forms
- Ginger
- Boswellia
- Black Pepper (Piperine)
- Milk Thistle (Liver)
- Arthritis
- Rheumatoid Arthritis
- Non-Alcoholic Fatty Liver Disease (Fatty Liver)
- Alzheimer's Disease
- Anti-Inflammatory Diet
- History