Turmeric for Brain Health and Cognition
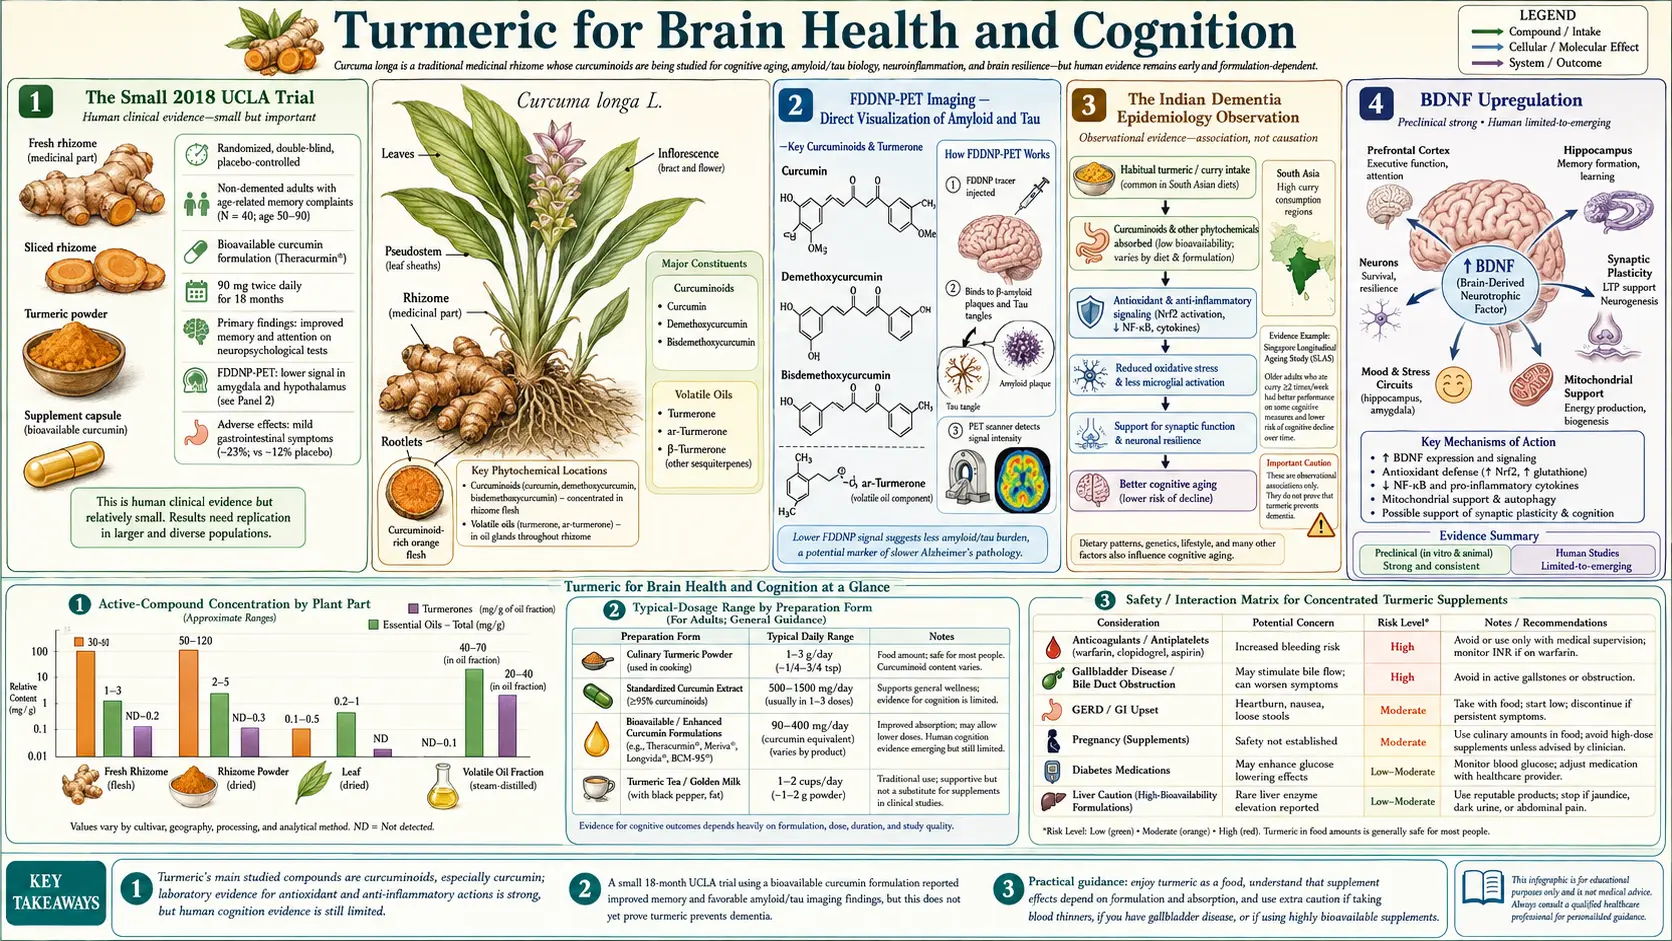
The most compelling human cognitive trial of curcumin is the Small GW et al. 2018 UCLA study published in the American Journal of Geriatric Psychiatry. Forty adults aged 51–84 without dementia were randomized to a colloidal submicron-particle curcumin (90 mg of curcumin twice daily) or placebo for 18 months, with serial neuropsychological testing and FDDNP-PET brain imaging. The curcumin group showed improvements in verbal memory (Buschke Selective Reminding Test, SRT) and visual memory (Brief Visual Memory Test-Revised, BVMT-R); for long-term verbal recall the difference from placebo was borderline (p = 0.05). In an exploratory brain scan (positron emission tomography, PET) of 30 of the participants, the amyloid-and-tau tracer signal in the amygdala fell within the curcumin group, but the difference from placebo was not statistically significant (p = 0.07); in the hypothalamus the signal did not change with curcumin and rose with placebo. The authors suggested that the memory benefits are associated with less amyloid and tau build-up. This sits on top of a long-standing epidemiologic observation: 1990s village surveys in rural northern India found some of the lowest dementia rates reported, and turmeric-rich diet is one of several hypothesized contributors — although the first nationwide survey (2018–2020) estimated that 7.4% of Indians aged 60 and over have dementia. Mechanistically, curcumin upregulates brain-derived neurotrophic factor (BDNF), suppresses microglial neuroinflammation, disaggregates amyloid-beta fibrils in vitro, and — uniquely among most polyphenols — crosses the blood-brain barrier in measurable quantities, especially in the solid-lipid curcumin particle formulations.
Table of Contents
- The Small 2018 UCLA Trial
- FDDNP-PET Imaging — Direct Visualization of Amyloid and Tau
- The Indian Dementia Epidemiology Observation
- Brain-Derived Neurotrophic Factor Upregulation
- Neuroinflammation and Microglial Activation
- Amyloid-Beta Binding and Disaggregation
- Blood-Brain Barrier Crossing
- Depression and Mood
- Vascular Cognitive Impairment and Stroke
- Parkinson's and Other Neurodegenerative Conditions
- Doses Used in Brain and Mood Trials
- Key Research Papers
- Connections
- Featured Videos
The Small 2018 UCLA Trial
Gary Small and colleagues at the UCLA Longevity Center designed the Small 2018 trial to address a specific gap in the curcumin cognitive literature: most prior trials had been short (8–12 weeks) and used cognitive endpoints alone. Small added two critical elements — long duration (18 months) and direct brain imaging of Alzheimer's pathology (FDDNP-PET) — that turned a typical supplement trial into a more rigorous test of disease modification.
Study design:
- Participants: 40 non-demented adults aged 51–84 (21 curcumin, 19 placebo); the trial registration (NCT01383161) admitted people with mild cognitive impairment (MCI) or age-related memory decline, but not dementia
- Intervention: a colloidal submicron-particle curcumin preparation containing 90 mg of curcumin twice daily, totaling 180 mg/day. This form was chosen specifically for its documented high bioavailability and free-curcumin pharmacokinetics.
- Comparator: Matched placebo
- Duration: 18 months — long enough to detect modification of the slowly-progressive Alzheimer's neuropathology
- Primary endpoints: SRT (Buschke Selective Reminding Test) for verbal memory and BVMT-R (Brief Visual Memory Test-Revised) for visual memory; attention (Trail Making A) was a secondary endpoint, and FDDNP-PET for amyloid and tau brain accumulation was an exploratory measure in 30 participants (15 per group)
Results at 18 months:
- SRT Consistent Long-Term Retrieval improved in the curcumin group (effect size 0.63, p = 0.002) but not with placebo; the difference between the groups was borderline (effect size 0.68, p = 0.05). SRT Total also improved with curcumin (effect size 0.53, p = 0.002)
- BVMT-R visual memory scores also improved in the curcumin group (Recall p = 0.01; Delay p = 0.006)
- Attention scores improved on Trails A testing (between-group effect size 0.67, p = 0.04)
- FDDNP-PET binding in the amygdala fell within the curcumin group (effect size −0.41, p = 0.04), but the difference from placebo was not statistically significant (p = 0.07). In the hypothalamus the signal did not change with curcumin (p = 0.2) but rose with placebo (between-group p = 0.02). The authors read these findings as a sign of reduced amyloid and tau accumulation in regions involved in mood and memory
- Mood improved on the Beck Depression Inventory in the curcumin group
- No serious adverse events attributable to curcumin
The trial was small and a single-center study, and FDDNP is no longer the dominant amyloid-PET tracer (florbetapir, florbetaben, and flutemetamol have replaced it for clinical Alzheimer's imaging). The combination of memory improvement and an exploratory PET imaging signal — in a population without dementia, over 18 months, with a bioavailability-enhanced curcumin formulation — is what led the authors to suggest that curcumin may engage genuine Alzheimer's pathology mechanisms.
What is not known: this was one small single-centre trial of 40 people; the amygdala PET difference between the groups was not statistically significant; and the long-term verbal recall difference was borderline (p = 0.05). A 2025 review that pooled 10 human trials (531 people) found that curcumin had no significant effect on overall thinking ability compared with placebo (standardized mean difference 0.14, 95% confidence interval −0.78 to 1.07). In subgroup analyses working memory (standardized mean difference 1.01) and processing speed (0.37) improved. Side effects were reported more often with curcumin than with placebo, and the authors called the human findings inconsistent (Yu L et al. 2025).
FDDNP-PET Imaging — Direct Visualization of Amyloid and Tau
FDDNP (2-(1-{6-[(2-[18F]fluoroethyl)(methyl)amino]-2-naphthyl}ethylidene)malononitrile) is a small-molecule radiotracer developed at UCLA in the early 2000s that binds both amyloid-beta plaques and tau neurofibrillary tangles in vivo. It was the first positron emission tomography tracer to visualize Alzheimer's-disease pathology in living humans, predating the later amyloid-specific tracers florbetapir and Pittsburgh Compound B.
FDDNP has both an advantage and a limitation versus the modern amyloid-specific tracers. The advantage is that it picks up both amyloid and tau, the two hallmark Alzheimer's lesions; the limitation is that it cannot distinguish them. In the Small 2018 trial, the FDDNP signal reduction in the amygdala within the curcumin group could reflect amyloid reduction, tau reduction, or both — the imaging modality cannot tell.
What the imaging adds is an exploratory biological signal alongside the memory results: the amygdala signal fell within the curcumin group (p = 0.04) without a significant difference from placebo (p = 0.07), and the hypothalamus difference between the groups (p = 0.02) came from a rise in the placebo group. This is unusual for supplement trials, which typically report cognitive endpoints alone without any biomarker. The Small trial is therefore one of the few studies of a dietary intervention — not just curcumin — to look for changes in Alzheimer's-relevant brain biomarkers in non-demented older adults.
Subsequent imaging research has continued to investigate curcumin's amyloid-binding properties in vivo. Curcumin itself has been investigated as a potential amyloid-PET tracer because of its high binding affinity to beta-sheet amyloid structures, though its physical chemistry has not made it suitable for clinical positron emission tomography use compared to the established F-18 labeled tracers.
The Indian Dementia Epidemiology Observation
The cross-cultural epidemiology of Alzheimer's disease and other dementias has long included a puzzling observation: 1990s community surveys in rural India found some of the lowest dementia rates ever reported. The Ballabgarh survey of 5,126 villagers aged 55 and over in northern India (Chandra V et al. 1998) found an Alzheimer's prevalence of 0.62% (all dementias 0.84%); the authors listed low life expectancy, short survival with the disease, and low age-specific incidence as possible explanations. A 2001 follow-up of the same community (Chandra V et al. 2001) found an Alzheimer's incidence of 4.7 new cases per 1,000 person-years at age 65 and over, against 17.5 in a comparison community in Pennsylvania, USA (the Monongahela Valley), while cautioning about short follow-up and cultural factors. Several other Indian rural cohort studies have reported similar findings.
The first nationwide dementia survey of India (the Longitudinal Aging Study in India–Diagnostic Assessment of Dementia, LASI-DAD, 2018–2020; Lee J et al. 2023) changes this picture. It estimated that 7.4% of adults aged 60 and over have dementia, about 8.8 million people. Dementia was more common in women than in men and in rural than in urban areas, and it varied widely between states. The authors noted that earlier estimates came from selected communities that did not represent the national population.
The Indian dementia low-prevalence observation is part of the original motivation for the modern curcumin neurology research program. The hypothesis advanced by Frautschy, Cole, and others at UCLA in the early 2000s was that the high turmeric content of traditional Indian cuisine (curry powders, sambar, dal preparations) contributed to the reduced dementia rate. Turmeric is not the only candidate explanation — differences in education, life expectancy, dementia diagnostic capture, cardiovascular risk burden, social and family support structures, and other diet-pattern factors all confound the comparison — but the curcumin hypothesis is biologically plausible and has now been substantially developed through both animal and human studies.
The Cole lab at UCLA (Lim GP et al. 2001) tested dietary curcumin in an Alzheimer's transgenic mouse (Tg2576, also called APPSw): a low dose (160 ppm) lowered insoluble and soluble amyloid-beta and plaque burden by 43–50%, while a high dose (5000 ppm) did not. The mechanism in the mouse models proved to involve all of the pathways discussed below: brain-derived neurotrophic factor upregulation, microglial polarization to the anti-inflammatory M2 phenotype, direct amyloid-beta binding and disaggregation, and reduced tau hyperphosphorylation.
An important practical caveat: the dietary turmeric exposure of Indian populations comes primarily from food-based curcumin, not bioavailability-enhanced supplements, and at modest daily milligram quantities. The protection (if real) develops over decades of cumulative exposure starting in childhood, not over months of supplement use in adulthood. The animal-model and human-trial doses required to demonstrate measurable effects on dementia biomarkers in adults are substantially higher than what is achievable through diet alone.
Brain-Derived Neurotrophic Factor Upregulation
Brain-derived neurotrophic factor (BDNF) is a 14-kDa protein in the neurotrophin family that supports the survival, growth, and synaptic plasticity of neurons throughout the central and peripheral nervous system. Brain-derived neurotrophic factor signals through the tropomyosin receptor kinase B (TrkB) receptor, activating the PI3K/Akt and MAPK pathways that promote dendritic arborization, long-term potentiation (the cellular basis of learning), and adult neurogenesis in the hippocampal dentate gyrus.
Brain-derived neurotrophic factor levels decline with age and are reduced in major depressive disorder, schizophrenia, Alzheimer's disease, and several other neurological and psychiatric conditions. Restoration of brain-derived neurotrophic factor signaling is one of the principal hypothesized mechanisms of action of selective serotonin reuptake inhibitor (SSRI) antidepressants, exercise, intermittent fasting, and ketogenic diet on mood and cognition. Animal studies consistently show that curcumin increases hippocampal and cortical brain-derived neurotrophic factor mRNA and protein expression, with effect sizes comparable to those seen with antidepressant treatment.
The Sanmukhani 2014 randomized controlled trial in Phytotherapy Research compared curcumin 1000 mg/day vs fluoxetine 20 mg/day in 60 patients with major depressive disorder over 6 weeks. The mean change on the Hamilton Depression Rating Scale was comparable in all three groups (curcumin, fluoxetine, and the combination; P = 0.77); the combination had the highest responder rate (77.8% vs 64.7% and 62.5%), but the difference was not statistically significant (P = 0.58). The trial was observer-masked and had no placebo group. While the trial did not measure brain-derived neurotrophic factor directly in humans, the parallel between curcumin and selective serotonin reuptake inhibitor efficacy is consistent with the brain-derived neurotrophic factor-mediated mechanism.
For the broader picture on brain-derived neurotrophic factor in cognitive and mood applications, see our Brain Aging page.
Neuroinflammation and Microglial Activation
Microglia are the resident macrophages of the central nervous system, surveillant cells that detect tissue injury, misfolded protein aggregates, and infection. Activated microglia secrete cytokines (tumor necrosis factor-alpha, IL-1beta, interleukin-6, IL-6), reactive oxygen species, and complement proteins, and they phagocytose dying neurons and protein aggregates. In acute settings this is protective; in chronic settings of slowly-accumulating amyloid plaques or tau tangles, persistent microglial activation produces a low-grade neuroinflammatory state that damages neighboring neurons and accelerates neurodegeneration.
The Alzheimer's field has increasingly recognized microglial dysregulation as a central pathogenic mechanism. Genetic risk loci identified by genome-wide association studies (TREM2, CR1, CD33, ABCA7) cluster around microglial function. The amyloid cascade hypothesis has been refined to include the role of microglial response to amyloid as a major determinant of whether amyloid accumulation translates to clinical dementia.
Curcumin's effects on microglia have been studied extensively in vitro and in animal models. It promotes the polarization of microglia from the pro-inflammatory M1 phenotype (tumor necrosis factor-alpha, IL-1beta, iNOS, MHC-II) toward the anti-inflammatory and tissue-repair M2 phenotype (interleukin-10, TGF-beta, arginase, insulin-like growth factor 1, IGF-1). Curcumin also inhibits NLRP3 inflammasome activation in microglia, reducing IL-1beta and IL-18 production. The net effect is reduced chronic neuroinflammation around amyloid plaques and reduced bystander injury to neighboring neurons.
The neuroinflammation effect overlaps mechanistically with the joint-inflammation effect — the same NF-kB inhibition that calms synovial macrophages also calms microglia. This is why a single curcumin intervention can plausibly produce effects on arthritis, non-alcoholic fatty liver disease (NAFLD), and dementia risk simultaneously.
Amyloid-Beta Binding and Disaggregation
Beyond its anti-inflammatory effects, curcumin has direct biophysical effects on amyloid-beta peptide aggregation. The curcumin molecule has a conjugated planar structure that binds preferentially to the beta-sheet fibrillar form of amyloid-beta, the structure that accumulates in senile plaques. In vitro, curcumin both inhibits the polymerization of amyloid-beta monomers into fibrils and disaggregates pre-formed amyloid fibrils back to smaller species.
The seminal work was by Yang F et al. 2005 in the Journal of Biological Chemistry, demonstrating both effects with purified amyloid-beta peptide. Subsequent work showed that orally-administered curcumin reduces amyloid plaque burden in transgenic Alzheimer's mouse models (TgAPPsw, Tg2576, APP/PS1) by 30–50% over months of dietary administration. The combination of direct anti-amyloid action and the anti-neuroinflammatory effect distinguishes curcumin from purely symptomatic cognitive interventions.
Whether the same anti-amyloid effect operates in humans at achievable supplement doses is the central uncertainty. The Small 2018 FDDNP-PET data are suggestive but limited to a small sample in two specific brain regions. Larger trials with the modern amyloid-PET tracers (florbetapir, florbetaben) and longer follow-up will be needed to firmly establish whether human chronic curcumin supplementation reduces brain amyloid burden over years to decades.
Blood-Brain Barrier Crossing
The blood-brain barrier (BBB) is a major obstacle to any therapy aimed at the central nervous system. Tight junctions between brain capillary endothelial cells, the basal lamina, astrocytic end-feet, and efflux transporters (P-glycoprotein, BCRP) limit which molecules can enter the brain parenchyma. Most polyphenols, including most flavonoids and most resveratrol metabolites, have minimal BBB penetration — the molecules either fail to enter the brain or are actively pumped back out by efflux transporters.
Curcumin is one of the few dietary polyphenols with documented measurable BBB penetration. Its modest molecular weight (368 Da), high lipophilicity (logP around 3.3), and lack of strong P-glycoprotein substrate behavior allow it to cross into brain tissue. The Begum AN et al. 2008 paper measured curcumin in mouse brain tissue after oral dosing, confirming BBB penetration — albeit at very low concentrations compared to plasma.
The brain-penetration question is particularly important for choice of curcumin formulation. The solid lipid curcumin particle (SLCP) formulation was specifically engineered for free unconjugated curcumin in plasma rather than the glucuronide-conjugated form — because free curcumin has substantially better BBB penetration than glucuronide-curcumin. This is the rationale for the solid-lipid form being the most-favored formulation in cognitive research, despite the curcumin-phospholipid complex and colloidal submicron-particle curcumin having stronger trial data in joint and liver applications.
The solid-lipid form was tested in the Cox KH et al. 2015 randomized, double-blind, placebo-controlled trial in 60 healthy adults aged 60–85 (400 mg). One hour after a dose, sustained attention and working memory were better than with placebo. After 4 weeks of daily use, working memory and mood measures (general fatigue, and calmness, contentedness and fatigue under psychological stress) were better. Total and LDL cholesterol fell, and blood safety tests did not change.
For the detailed comparison of curcumin formulations, see the Bioavailability and Forms page.
Depression and Mood
Major depressive disorder shares several pathogenic features with cognitive aging: reduced brain-derived neurotrophic factor, increased neuroinflammation, microglial dysregulation, and hypothalamic-pituitary-adrenal (HPA) axis dysregulation. The same curcumin mechanisms that support cognitive function therefore also have antidepressant effects.
Clinical evidence:
- Sanmukhani 2014 — randomized 60 patients with major depressive disorder (MDD) to curcumin 1000 mg/day vs fluoxetine 20 mg/day vs combination for 6 weeks (observer-masked, no placebo group). Mean change on the 17-item Hamilton Depression Rating Scale (HAM-D17) was comparable in all three groups (P = 0.77); responder rates were 77.8% (combination), 64.7% (fluoxetine) and 62.5% (curcumin), a difference that was not statistically significant (P = 0.58).
- Lopresti 2014 — randomized 56 MDD patients to a curcumin extract 500 mg twice daily (1000 mg/day) vs placebo for 8 weeks. Both groups improved over the first 4 weeks; from weeks 4 to 8 curcumin improved the IDS-SR30 (Inventory of Depressive Symptomatology) depression score more than placebo (p = .045), while the STAI (State-Trait Anxiety Inventory) showed only a non-significant trend (p = .097). The 12-week study by the same group is a separate 2017 trial (below).
- Lopresti 2017 — a 12-week randomized, double-blind, placebo-controlled trial in 123 people with major depressive disorder compared low-dose curcumin extract (250 mg twice daily), high-dose curcumin extract (500 mg twice daily), and low-dose curcumin plus saffron (15 mg twice daily) with placebo. Taken together, the active treatments improved depression scores (p = .031) and anxiety scores (STAI-state p < .001, STAI-trait p = .001) more than placebo. Response was higher in people with atypical depression (65% vs 35%). The doses and the saffron combination did not differ from each other.
- Yu 2015 — randomized 108 men aged 31–59 with major depressive disorder to curcumin 1000 mg/day or placebo as adjunct to existing antidepressant for 6 weeks. Curcumin group had significantly better HAM-D improvement.
- Ng 2017 meta-analysis — pooled six trials with 377 patients comparing curcumin with placebo; curcumin lowered depression scores more than placebo (pooled standardized mean difference −0.344, 95% confidence interval −0.558 to −0.129, P = .002). The trials lasted only 4 to 8 weeks.
These trials tested curcumin alone, against fluoxetine, or added to existing antidepressants, for 4 to 12 weeks; none tested it as a replacement for antidepressants in moderate-to-severe major depression, and long-term data are lacking. In the Ng 2017 meta-analysis no adverse events were reported in any of the six trials, whereas selective serotonin reuptake inhibitors are known for sexual dysfunction, gastrointestinal (GI) upset, weight gain, and discontinuation symptoms — which is why curcumin draws interest from people who tolerate antidepressants poorly.
Vascular Cognitive Impairment and Stroke
A substantial fraction of dementia in aging populations is vascular rather than Alzheimer's — small-vessel ischemic disease, lacunar infarcts, and the cumulative impact of chronic hypertension and atherosclerosis on cerebral perfusion. The Akazawa N et al. 2012 trial in Nutrition Research studied curcumin's effect on endothelial function in postmenopausal women, showing significant improvement in flow-mediated dilation (a measure of vascular endothelial health) after 8 weeks of curcumin 150 mg/day.
The mechanism for cerebrovascular benefit overlaps with curcumin's general cardiovascular effects: improved endothelial function via increased nitric oxide bioavailability, reduced oxidized low-density lipoprotein (LDL), anti-inflammatory effects on the vascular endothelium, and modest reductions in blood pressure and lipids. The cumulative effect of these is reduced small-vessel ischemic burden in the brain, which translates to reduced vascular cognitive impairment in observational studies.
In acute ischemic stroke, animal models show that curcumin pre-treatment reduces infarct volume and improves neurological outcomes through reduction of post-ischemic neuroinflammation. Human stroke prevention or treatment trials with curcumin are not yet conclusive, but the mechanistic basis is reasonable and the cardiovascular risk-factor improvements documented in metabolic trials translate plausibly to reduced stroke risk.
Parkinson's and Other Neurodegenerative Conditions
Parkinson's disease involves accumulation of misfolded alpha-synuclein protein in Lewy bodies, with selective neurodegeneration of dopaminergic neurons in the substantia nigra. Curcumin has been shown in vitro and in animal models to inhibit alpha-synuclein aggregation (analogous to its anti-amyloid effect) and to protect dopaminergic neurons from MPTP-induced and rotenone-induced injury. Human clinical trials of curcumin in established Parkinson's disease are limited, and curcumin is not currently considered a disease-modifying therapy — though integrative-medicine practitioners discuss it as possible add-on neuroprotection in Parkinson's.
Other neurological applications with mechanistic support but limited human trial data include:
- Multiple sclerosis — animal models of experimental autoimmune encephalomyelitis show curcumin reduces disease severity through Th17/Treg shift, similar to the mechanism discussed in the immune section
- Traumatic brain injury — animal models show curcumin reduces secondary neuroinflammation after traumatic brain injury (TBI)
- Chemotherapy-induced cognitive impairment — "chemo brain" — suggestive small studies
- Epilepsy — animal models show anticonvulsant effect through glutamate modulation; human data are lacking
Doses Used in Brain and Mood Trials
The brain and mood studies on this page used different curcumin forms and doses; cognitive research has favored the forms with the best blood-brain barrier penetration:
- Solid lipid curcumin particles, 400 mg — the dose in the Cox 2015 trial in healthy older adults; the form with the highest free-curcumin pharmacokinetics, favored in cognitive research based on BBB penetration data.
- Colloidal submicron-particle curcumin, 90 mg twice daily — the dose in the Small 2018 UCLA trial, the most direct evidence for cognitive outcomes.
- Curcumin extract (curcumin + turmeric essential oil), 500 mg twice daily — the dose in the Lopresti 2014 depression trial; the 2017 trial used 250 or 500 mg twice daily.
- Curcumin-phospholipid complex, 1000 mg/day — well documented for joint and liver applications, with less BBB-penetration data.
Cognitive effects were measured over long periods — the Small UCLA trial ran 18 months — while in the Lopresti 2014 depression trial curcumin separated from placebo between weeks 4 and 8. Other approaches often discussed alongside curcumin for brain health: omega-3 fatty acids (docosahexaenoic acid, DHA) for membrane structural support and SPM precursors; vitamin D for neuroprotective signaling; B12 and folate for homocysteine reduction; regular aerobic exercise for the most-evidence-supported brain-derived neurotrophic factor stimulus.
Key Research Papers
- Small GW et al. (2018). Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. American Journal of Geriatric Psychiatry. — PubMed PMID: 29246725
- Chandra V et al. (1998). Prevalence of Alzheimer's disease and other dementias in rural India: The Indo-US study. Neurology. — PubMed PMID: 9781520
- Chandra V et al. (2001). Incidence of Alzheimer's disease in a rural community in India: The Indo-US study. Neurology. — PubMed PMID: 11571321
- Lee J et al. (2023). Prevalence of dementia in India: National and state estimates from a nationwide study. Alzheimer's & Dementia. — PubMed PMID: 36637034
- Yang F et al. (2005). Curcumin inhibits formation of amyloid beta oligomers and fibrils, binds plaques, and reduces amyloid in vivo. Journal of Biological Chemistry. — PubMed PMID: 15590663
- Begum AN et al. (2008). Curcumin structure-function, bioavailability, and efficacy in models of neuroinflammation and Alzheimer's disease. Journal of Pharmacology and Experimental Therapeutics. — PubMed PMID: 18417733
- Lim GP et al. (2001). The curry spice curcumin reduces oxidative damage and amyloid pathology in an Alzheimer transgenic mouse. Journal of Neuroscience. — PubMed PMID: 11606625
- Sanmukhani J et al. (2014). Efficacy and safety of curcumin in major depressive disorder: A randomized controlled trial. Phytotherapy Research. — PubMed PMID: 23832433
- Lopresti AL et al. (2014). Curcumin for the treatment of major depression: A randomised, double-blind, placebo controlled study. Journal of Affective Disorders. — PubMed PMID: 25046624
- Lopresti AL, Drummond PD (2017). Efficacy of curcumin, and a saffron/curcumin combination for the treatment of major depression: A randomised, double-blind, placebo-controlled study. Journal of Affective Disorders. — PubMed PMID: 27723543
- Yu JJ et al. (2015). Chronic supplementation of curcumin enhances the efficacy of antidepressants in major depressive disorder: A randomized, double-blind, placebo-controlled pilot study. Journal of Clinical Psychopharmacology. — PubMed PMID: 26066335
- Ng QX et al. (2017). Clinical use of curcumin in depression: A meta-analysis. Journal of the American Medical Directors Association. — PubMed PMID: 28236605
- Cox KH et al. (2015). Investigation of the effects of solid lipid curcumin on cognition and mood in a healthy older population. Journal of Psychopharmacology. — PubMed PMID: 25277322
- Akazawa N et al. (2012). Curcumin ingestion and exercise training improve vascular endothelial function in postmenopausal women. Nutrition Research. — PubMed PMID: 23146777
- Voulgaropoulou SD et al. (2019). The effect of curcumin on cognition in Alzheimer's disease and healthy aging: A systematic review of pre-clinical and clinical studies. Brain Research. — PubMed PMID: 31560864
- Frautschy SA, Cole GM (2010). Why pleiotropic interventions are needed for Alzheimer's disease. Molecular Neurobiology. — PubMed PMID: 20437209
- Yu L et al. (2025). Targeting cognitive aging with curcumin supplementation: A systematic review and meta-analysis. Journal of Prevention of Alzheimer's Disease. — PubMed PMID: 40579315
PubMed Topic Searches
Connections
- All Herbs
- Turmeric Benefits Hub
- Turmeric Overview
- Turmeric for Joint Health
- Turmeric for Liver Health
- Bioavailability & Forms
- Bacopa Monnieri
- Lion's Mane Mushroom
- Ashwagandha
- Omega-3 Fatty Acids (Docosahexaenoic Acid)
- Vitamin D3
- Vitamin B12
- Alzheimer's Disease
- Parkinson's Disease
- Depression
- Brain Aging
- Dementia — the broader cognitive-decline syndrome whose low prevalence in India first motivated curcumin neurology research.
- History