Turmeric / Curcumin Bioavailability and Forms
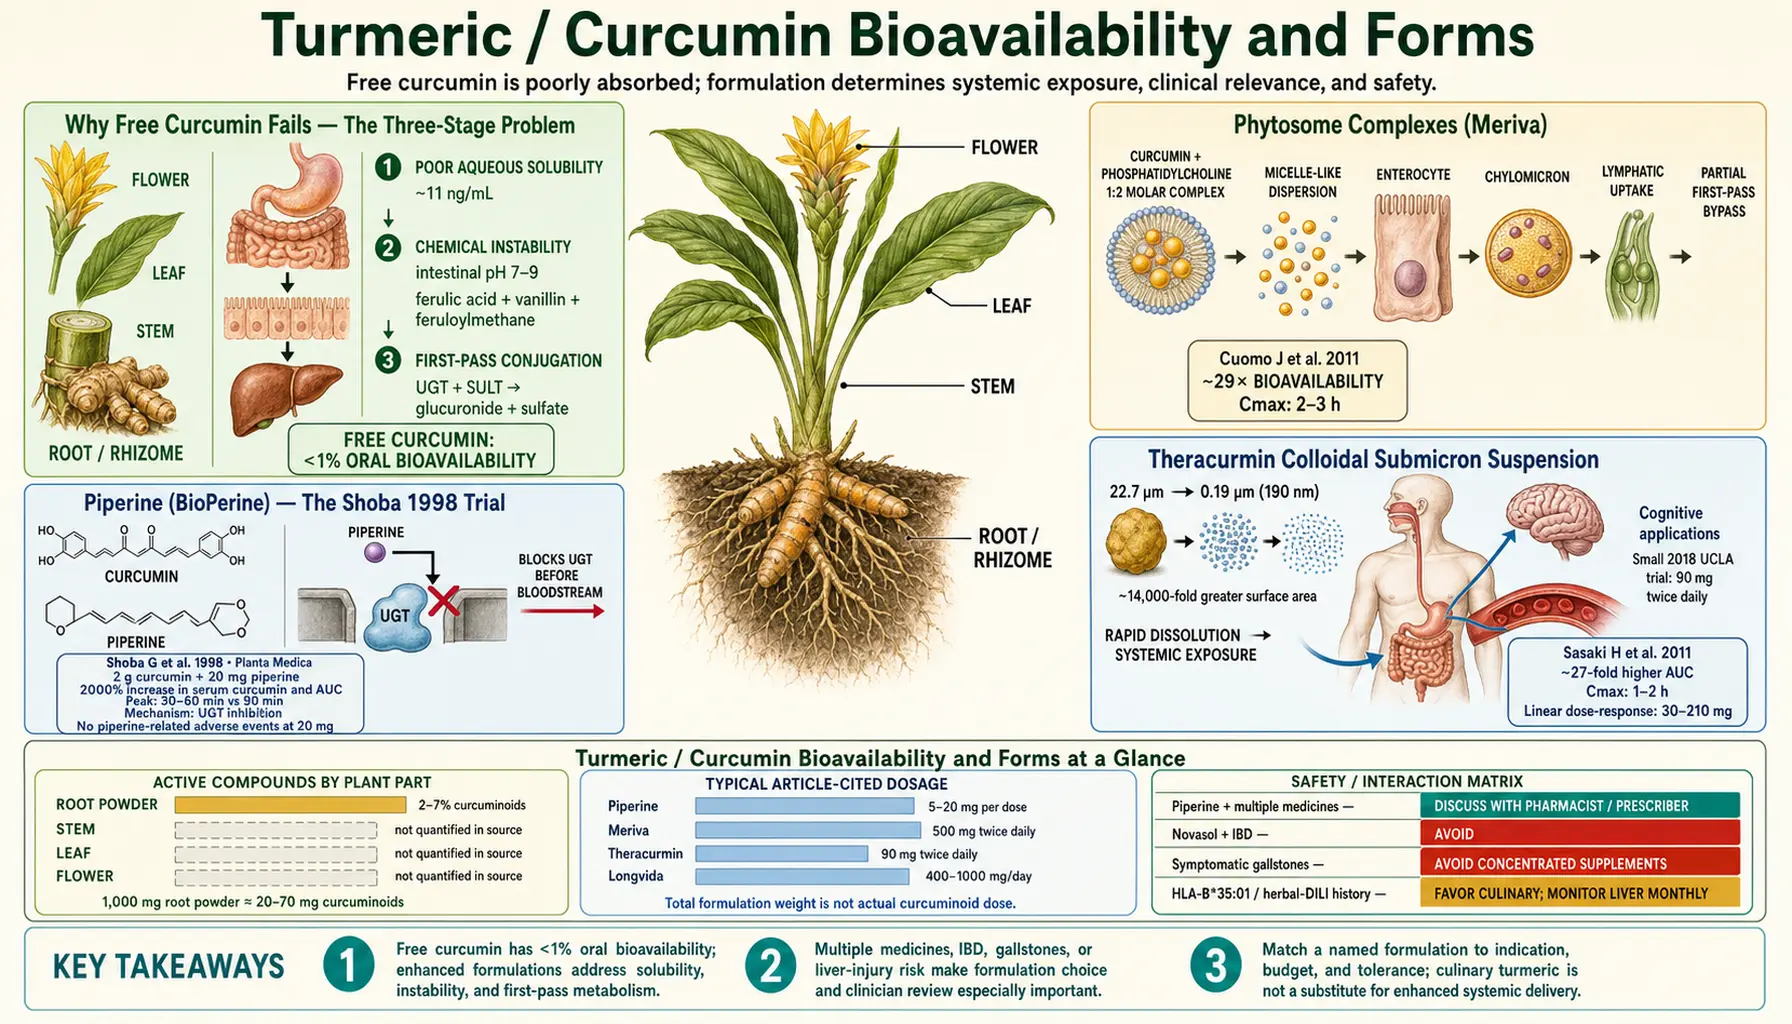
This page describes how much curcumin actually reaches the blood from turmeric and from the different curcumin supplement formulations. Free curcumin has less than 1% oral bioavailability. A teaspoon of turmeric powder in milk, a curry meal, or an unenhanced 500 mg curcumin capsule produces blood curcumin concentrations far too low to drive any of the anti-inflammatory, hepatic, or cognitive effects documented in clinical trials. The bioavailability problem has been the central practical issue in curcumin therapeutics since the 1970s, and the formulations developed in the past two decades underlie most of the modern clinical-trial evidence base. The main approaches: (1) piperine co-administration (the active compound in black pepper) blocks hepatic and intestinal glucuronidation and raised curcumin bioavailability by 2000% in the Shoba 1998 study; (2) phytosome complexes combine curcumin with phosphatidylcholine in a 1:2 molecular complex, with about 29-fold higher absorption of total curcuminoids; (3) colloidal submicron-particle suspensions reduce particle size from a typical 22.7 micrometers to 0.19 micrometers, with about 27-fold higher absorption; (4) solid lipid curcumin particles (SLCP) produce free unconjugated curcumin in plasma rather than only glucuronide-conjugated metabolites — free curcumin was detected after the particles but not after the same amount of unformulated extract — and are described as crossing the blood–brain barrier better; (5) liquid micelle formulations reached about 185-fold higher bioavailability through self-assembling micelle delivery.
Table of Contents
- Why Free Curcumin Fails — The Three-Stage Problem
- Piperine (Black Pepper Extract) — The Shoba 1998 Study
- Phytosome Complexes (Curcumin With Phosphatidylcholine)
- Colloidal Submicron-Particle Curcumin
- Solid Lipid Curcumin Particle (SLCP)
- Micellar Curcumin (Liquid Micelles)
- Curcumin With Turmeric Essential Oil
- Cyclodextrin-Complexed Curcumin
- Nanocurcumin and Polymeric Nanoparticles
- Side-by-Side Comparison Table
- Why Standard Turmeric Tea Has Minimal Systemic Effect
- Formulations and Doses Used in the Clinical Trials
- What Curcumin Supplement Labels Show
- Key Research Papers
- Connections
- Featured Videos
Why Free Curcumin Fails — The Three-Stage Problem
Free curcumin is a hydrophobic polyphenol with terrible drug-like properties from a pharmacokinetics standpoint. There are three sequential barriers between an ingested curcumin molecule and the bloodstream:
- Poor aqueous solubility — curcumin is essentially insoluble in water at physiologic pH (solubility roughly 11 ng/mL). The crystalline curcumin in a typical supplement capsule does not dissolve well in gastric or intestinal fluid, so most of it passes through the gut unabsorbed. The maximum theoretical absorption from a 1000 mg dose of crystalline curcumin is limited by solubility to perhaps 1–3 mg actually entering the enterocyte.
- Chemical instability at intestinal pH — the curcumin that does dissolve undergoes pH-dependent degradation. At neutral-to-alkaline intestinal pH (7–9), curcumin breaks down to ferulic acid, vanillin, and feruloylmethane within minutes. So the fraction that reaches the absorptive enterocytes is further reduced.
- Aggressive Phase II conjugation in the gut and liver (first-pass metabolism) — the small amount of curcumin that crosses the enterocyte membrane is immediately conjugated to glucuronide (by UGT1A6, UGT1A8, UGT1A9, UGT1A10 in enterocytes) and sulfate (by SULT1A1 and SULT1A3). The conjugated metabolites enter the portal vein, pass through the liver where additional UGT/SULT conjugation occurs, and arrive in systemic circulation almost entirely as curcumin-glucuronide and curcumin-sulfate rather than free curcumin.
The net result: oral administration of 4–8 grams of unformulated 95% curcuminoid extract to healthy volunteers produces peak plasma total curcuminoid concentrations of perhaps 0.5–2 micromolar, with free unconjugated curcumin at maybe 1% of that — nanomolar concentrations that are below the in vitro IC50 for most of curcumin's documented molecular targets. This is why historical pure-extract trials produced inconsistent results: the dose was high but the systemic exposure was inadequate.
Every bioavailability-enhancing strategy addresses one or more of these three barriers. Piperine inhibits the UGT enzymes (barrier 3). Phytosomes improve aqueous dispersion and protect against acid degradation (barriers 1 and 2). Submicron particles improve dissolution rate (barrier 1). Solid lipid particles deliver curcumin in a non-conjugatable form past first-pass metabolism (barrier 3). Liquid micelles solve both dissolution and partition into intestinal lipid micelles (barriers 1 and 2).
Piperine (Black Pepper Extract) — The Shoba 1998 Study
The Shoba G et al. 1998 study in Planta Medica is the foundational reference for curcumin-plus-piperine pharmacokinetics. The investigators gave 2 grams of curcumin to healthy human volunteers, alone or with 20 mg of piperine (the active alkaloid in Piper nigrum, black pepper, and Piper longum, long pepper), and measured serum curcumin over the following hours.
Findings:
- With 2 g of curcumin alone, serum curcumin levels were either undetectable or very low
- Curcumin plus 20 mg piperine produced much higher serum concentrations from 15 minutes to 1 hour after the dose, and a 2000% increase in bioavailability
- The authors reported no adverse effects at the doses used
The mechanism is inhibition of hepatic and intestinal UDP-glucuronosyltransferase (UGT) enzymes by piperine. With UGT inhibited, less of the absorbed curcumin is glucuronidated during first-pass metabolism, and more reaches systemic circulation as free curcumin. Piperine also has some inhibitory effect on intestinal P-glycoprotein efflux and on cytochrome P450 3A4 (CYP3A4) oxidative metabolism, both of which contribute marginally to the absorption-enhancing effect.
Standardized 95% piperine extracts from black pepper are the usual form of piperine in curcumin combination products, at 5–20 mg piperine per dose. Higher piperine doses bring more gastrointestinal (GI) upset and more interference with the metabolism of other drugs.
The major caveat: piperine's cytochrome P450 3A4 and UGT inhibition is not specific to curcumin. Piperine elevates blood levels of many co-administered medications including some statins, calcium channel blockers, beta-blockers, anticonvulsants, and immunosuppressants, so the drug-interaction profile of a curcumin-with-piperine product is broader than that of the curcumin itself.
Phytosome Complexes (Curcumin With Phosphatidylcholine)
The curcumin-phosphatidylcholine complex (phytosome) is the formulation that has come to dominate the European clinical-trial literature. It is a 1:2 molar complex of curcumin with phosphatidylcholine (the principal phospholipid in cell membranes and lecithin), produced by a proprietary process that creates non-covalent hydrogen bonds between curcumin and the phospholipid's polar head group.
The phospholipid solves two problems simultaneously. First, it dramatically improves aqueous dispersibility — the phytosome forms micelle-like structures in water rather than crystallizing out. Second, the phospholipid envelope protects curcumin from rapid degradation in the alkaline duodenum and ileum. The phytosome dissociates progressively in the enterocyte and the absorbed curcumin enters the lymphatic system in chylomicrons rather than going directly to the portal vein, partially bypassing first-pass hepatic glucuronidation.
Pharmacokinetics from the Cuomo J et al. 2011 head-to-head comparison published in the Journal of Natural Products:
- The phytosome produced approximately 29-fold higher curcuminoid bioavailability than unformulated 95% curcuminoid extract
- The increase was particularly pronounced for the minor curcuminoids demethoxycurcumin and bisdemethoxycurcumin
- Maximum plasma concentration (Cmax) was reached at 2–3 hours
The phytosome is the formulation in many of the European studies cited on the joint-health and liver-health pages. The Belcaro 2010 osteoarthritis studies were a product-evaluation registry (50 patients, doses corresponding to 200 mg curcumin a day for three months) and an eight-month extended-administration study in 100 patients; the Belcaro 2014 knee osteoarthritis study was an observational study. None of them was a randomized trial. The Panahi 2017 trial was a randomized controlled trial in non-alcoholic fatty liver disease (NAFLD), giving 1,000 mg of phytosomal curcumin a day in two divided doses for 8 weeks. (The Rahmani 2016 NAFLD trial used a different formulation — see the trial-dose section below.) A common clinical-trial dose is 500 mg twice daily of the complex, delivering approximately 100 mg of actual curcuminoids per dose (the complex is roughly 20% curcuminoid by weight; the rest is phosphatidylcholine and microcrystalline cellulose carrier).
Colloidal Submicron-Particle Curcumin
Colloidal submicron-particle curcumin, developed in Japan, takes a different physical-chemistry approach: rather than complex curcumin with a phospholipid, it physically reduces particle size from the typical 22.7 micrometers of crude curcumin powder to approximately 0.19 micrometers (190 nanometers) using a wet-milling process with gum ghatti as a stabilizing colloid.
The bioavailability improvement comes from the Noyes-Whitney dissolution equation: dissolution rate is proportional to particle surface area, and reducing particle diameter from 22.7 to 0.19 micrometers increases surface area by approximately 14,000-fold. The submicron particles dissolve almost instantaneously in gastrointestinal fluid rather than passing through the gut as undissolved solids.
Pharmacokinetics from the Sasaki H et al. 2011 paper in Biological & Pharmaceutical Bulletin and a 2012 follow-up:
- After a single 30 mg dose in healthy volunteers, the submicron particles produced a 27-fold higher AUC (area under the blood concentration curve) than curcumin powder (Sasaki 2011)
- In the Kanai 2012 dose-escalation study (single doses of 150 mg and 210 mg in six healthy volunteers), plasma curcumin rose with the dose at least up to 210 mg without saturating absorption
- Maximum plasma concentration achieved at 1–2 hours
The submicron-particle formulation was used in the Small 2018 UCLA trial discussed on the brain-health page: 40 non-demented adults aged 51–84 took 90 mg of curcumin twice daily or placebo for 18 months. It is sold either as a liquid suspension or as a capsule containing the dried submicron-particle powder.
Solid Lipid Curcumin Particle (SLCP)
The solid lipid curcumin particle is engineered for a specific pharmacokinetic goal: producing free unconjugated curcumin in systemic circulation rather than curcumin-glucuronide or curcumin-sulfate metabolites. This matters because most of curcumin's in vitro molecular activity is from the free unconjugated form, and because free curcumin has substantially better blood–brain barrier penetration than the conjugated metabolites.
The formulation embeds curcumin in a solid lipid matrix using a proprietary process developed by R.K. Sharma at UCLA. The lipid particles protect curcumin from gastric degradation, deliver it to the small intestine for absorption, and — critically — the absorbed curcumin enters the lymphatic system via the chylomicron pathway rather than the portal vein. This routing partially bypasses the heavy first-pass glucuronidation that converts most absorbed curcumin to inactive metabolites.
The Gota VS et al. 2010 paper in the Journal of Agricultural and Food Chemistry compared the solid lipid particle with unformulated curcumin in healthy human volunteers and tested 2, 3 and 4 g doses in 11 patients with osteosarcoma:
- In healthy volunteers, 650 mg of the solid lipid particle gave a mean peak free curcumin concentration of 22.43 ng/mL; free curcumin from the same amount of unformulated 95% curcuminoid extract was not detected (the assay detected down to 1 ng/mL)
- The authors observed high variability between individuals and a nonlinear relationship between dose and blood level
- The formulation was well tolerated in both groups
Because of this free-curcumin profile, the solid lipid particle has been studied for brain-related uses. The Cox 2015 trial gave 400 mg of the solid lipid particle a day to 60 healthy adults aged 60–85 and found better working memory and mood than with placebo after 4 weeks.
Micellar Curcumin (Liquid Micelles)
Micellar curcumin, developed in Germany, uses a self-assembling micelle delivery system based on the emulsifier polysorbate-80. The curcumin is dissolved in the liquid micelle matrix, which spontaneously forms nanoscale micelles when diluted in gastrointestinal fluid. The micelles partition curcumin into the same intestinal mixed-micelle phase that carries dietary fats, vitamins A, D, E, K, and other lipophilic compounds across the enterocyte brush border.
The Schiborr C et al. 2014 pharmacokinetic comparison in Molecular Nutrition & Food Research gave 23 healthy adults (13 women, 10 men) a single oral dose of 500 mg curcuminoids as native powder, micronized powder, or liquid micelles:
- Micellar curcumin produced approximately 185-fold higher total curcuminoid bioavailability than native curcumin powder in all subjects — 277-fold in women and 114-fold in men
- Micronized powder was 9-fold better than native powder in the same study
- The formulation is a liquid concentrate, typically delivered in soft-gel capsules
Micellar curcumin is widely used in European studies of curcumin in metabolic, cardiovascular, and cognitive applications. Its emulsifier, polysorbate-80, has been shown in some animal studies to alter gut microbiota composition with chronic high-dose exposure — a concern that has been raised for other polysorbate-80-containing pharmaceutical formulations, and one that matters most for people with established gut dysbiosis or inflammatory bowel disease. At typical supplement doses the emulsifier exposure is small. The phytosome, submicron-particle and solid lipid particle formulations do not use polysorbate-80.
Curcumin With Turmeric Essential Oil
Curcumin with turmeric essential oil, a formulation made in India, combines curcuminoids with the natural turmeric essential oil fraction containing ar-turmerone and other sesquiterpene ketones. The turmeric oil acts as a natural self-emulsifying agent that improves curcumin dissolution and absorption, and the ar-turmerone itself has independent anti-inflammatory and neuroactive properties.
The Antony B et al. 2008 crossover study found a relative bioavailability about 6.93-fold that of normal curcumin, and about 6.3-fold that of a curcumin-lecithin-piperine formula — lower than the figures reported for the phytosome or the solid lipid particle, from a “whole turmeric extract” rather than an engineered delivery system. This formulation is the one used in the Sanmukhani 2014 and Lopresti 2014 depression trials and the Chandran 2012 rheumatoid arthritis trial. The Madhu 2013 knee osteoarthritis trial tested a different Curcuma longa extract (coded NR-INF-02, 500 mg twice daily for 42 days).
Cyclodextrin-Complexed Curcumin
Cyclodextrin-complexed curcumin uses gamma-cyclodextrin as a complexing agent. Cyclodextrins are cyclic oligosaccharides with a hydrophobic interior cavity and hydrophilic exterior. Curcumin sits inside the cavity, where it is shielded from acid degradation, while the cyclodextrin exterior provides aqueous solubility. The complex dissociates in the intestinal fluid, releasing curcumin in a dissolved form for absorption.
In the Purpura M et al. 2018 double-blind crossover study in 12 healthy volunteers, the gamma-cyclodextrin formulation gave a 39-fold higher relative bioavailability of total curcuminoids over 12 hours than unformulated curcumin extract. Hydroxypropyl-beta-cyclodextrin is another cyclodextrin platform sometimes used.
Nanocurcumin and Polymeric Nanoparticles
A research-grade family of curcumin delivery systems uses polymeric nanoparticles — PLGA (poly-lactic-co-glycolic acid), chitosan, dendrimers, and various synthetic polymer matrices — to encapsulate curcumin in 50–200 nanometer particles. These can produce extraordinary bioavailability improvements (some reports of 100x to 1000x) in animal pharmacokinetic studies, and they have been investigated for targeted delivery to tumors, atherosclerotic plaques, and the brain.
For consumer supplements, most of the "nanocurcumin" products on the market are not true polymeric nanoparticles but are submicron-particle suspensions or micellar systems like those described above, repackaged with "nano" marketing language. True polymeric nanoparticle curcumin remains primarily a research and clinical-trial tool. A label that claims "nanocurcumin" without naming the underlying delivery system (cyclodextrin, micelle, phytosome, or polymer) does not tell the reader which of these it contains.
Side-by-Side Comparison Table
Comparison of the major curcumin formulations:
| Formulation | Mechanism | Relative Bioavailability | Where It Has Been Studied or Used |
|---|---|---|---|
| Plain turmeric powder | None | 1x (baseline, ~<1% absorbed) | Culinary use |
| 95% curcuminoid extract | Higher dose of free curcumin | ~3–5x (still poor) | Often combined with piperine |
| Curcumin + 5-20 mg piperine | UGT inhibition | 2000% increase (Shoba 1998, 20 mg piperine) | Widely sold combination products |
| Curcumin with turmeric essential oil | Turmeric oil self-emulsification | ~7x (Antony 2008) | Depression and rheumatoid arthritis trials |
| Curcumin-phosphatidylcholine complex (phytosome) | Curcumin-phosphatidylcholine complex; lymphatic uptake | ~29x (Cuomo 2011) | Joint and liver studies |
| Colloidal submicron-particle curcumin | Submicron particle suspension | ~27x (Sasaki 2011, 30 mg dose) | Memory trial (Small 2018) |
| Cyclodextrin-complexed curcumin | Gamma-cyclodextrin inclusion | ~39x total curcuminoids (Purpura 2018) | Pharmacokinetic study in healthy volunteers |
| Micellar curcumin | Polysorbate-80 liquid micelle | ~185x (Schiborr 2014) | High systemic exposure; the emulsifier is a concern raised for inflammatory bowel disease (IBD) |
| Solid lipid curcumin particle (SLCP) | Solid lipid particle; lymphatic delivery; free curcumin | Free curcumin detected (22.43 ng/mL peak from 650 mg); none detected from unformulated extract (Gota 2010) | Memory and mood trial (Cox 2015) |
Note that "relative bioavailability" numbers are not directly comparable across studies — different research groups use different analytical methods, different reference comparators, and different ways of integrating the plasma concentration curve. The numbers are order-of-magnitude indicators rather than precise rankings. What is consistent is that all of the enhanced formulations are dramatically better absorbed than plain curcumin.
Why Standard Turmeric Tea Has Minimal Systemic Effect
"Golden milk" — a traditional Indian and Ayurvedic preparation of turmeric powder simmered in milk with black pepper and warming spices — has been promoted online as a daily anti-inflammatory tonic. The traditional preparation has cultural and culinary value and may have local gut-soothing effects from the warm fat-soluble vehicle, but it does not produce the systemic curcumin blood levels that drive the clinical effects described on the other deep-dive pages.
The arithmetic: one teaspoon of dried turmeric powder weighs approximately 3 grams. At 2–7% curcuminoid content (typical for culinary turmeric, with some high-curcumin varieties reaching higher), that delivers 60–210 mg of curcuminoids per teaspoon. Without the bioavailability enhancement of piperine or phytosome formulation, less than 1% of that is absorbed and most of what is absorbed is rapidly glucuronidated. The systemic free curcumin from a cup of golden milk is in the low-nanomolar range — orders of magnitude below the IC50 for the molecular targets discussed on the other deep-dive pages.
The traditional preparation does include black pepper, which has piperine. A typical pinch of black pepper provides perhaps 0.5–1 mg of piperine, less than the 5–20 mg used in commercial formulations but enough to produce some bioavailability enhancement. Even with the piperine boost, the systemic curcumin from a daily cup of golden milk remains modest compared with the 1,000 mg/day phytosome dose used in the Panahi 2017 trial.
This does not mean turmeric tea is useless. Local effects on the gastric and intestinal mucosa, the cholagogue effect on bile flow, the warming and comforting psychological effect of the ritual, and the modest cumulative exposure over decades all have value. The joint, liver and memory trials described on this page used bioavailability-enhanced formulations, not turmeric tea, and none of them measured turmeric tea alone.
Formulations and Doses Used in the Clinical Trials
What the trials and studies described on this page and its sister pages used:
- Knee osteoarthritis — the Belcaro 2010 registry used the phytosome at doses corresponding to 200 mg curcumin a day for three months (50 patients), and the Belcaro 2010 extended study ran eight months (100 patients); the Belcaro 2014 observational study combined the phytosome with glucosamine for four months (124 patients). The Madhu 2013 randomized trial used a different turmeric extract, 500 mg twice daily for 42 days (120 patients).
- Rheumatoid arthritis — the Chandran 2012 randomized trial in 45 patients with active rheumatoid arthritis compared curcumin 500 mg (the turmeric-oil formulation), the painkiller diclofenac sodium 50 mg, and the two together.
- Non-alcoholic fatty liver disease (NAFLD) — the Panahi 2017 trial gave 1,000 mg of phytosomal curcumin a day in two divided doses for 8 weeks; the Rahmani 2016 trial gave an amorphous dispersion curcumin formulation at 500 mg once a day (equivalent to 70 mg curcumin) for 8 weeks. Both trials measured liver enzymes, which fell in the curcumin groups.
- Depression — the Lopresti 2014 trial gave curcumin 500 mg twice daily for 8 weeks to 56 people with major depressive disorder; the Sanmukhani 2014 trial compared curcumin 1,000 mg a day with the antidepressant fluoxetine 20 mg, and the two together, over six weeks.
- Memory and thinking — the Small 2018 trial gave 90 mg of curcumin twice daily as submicron particles for 18 months; the Cox 2015 trial gave 400 mg a day of the solid lipid particle for 4 weeks.
- Sensitive gastrointestinal tract or inflammatory bowel disease — the polysorbate-80 emulsifier concern applies to the micellar formulation; the phytosome and submicron-particle formulations do not contain it.
- Several medicines processed by cytochrome P450 3A4 — the broad cytochrome P450 3A4 inhibition comes from piperine; the phytosome, submicron-particle and solid lipid particle formulations do not contain piperine.
- Gallstones — curcumin increases bile flow (the cholagogue effect described above), which is the reason the research raises a concern about concentrated curcumin for people with gallstones, most of all when the stones are causing symptoms.
- Human leukocyte antigen (HLA)-B*35:01 carriers, or an earlier herb-induced liver injury — the research raises a concern about concentrated curcumin supplements, not culinary turmeric, for people who carry this gene variant or who have had liver injury from an herbal product before; the trials above tracked liver enzymes.
For acute episodes of inflammation, curcumin is not a rescue medication — in the trials above its effects were measured after weeks to months of daily use. Nonsteroidal anti-inflammatory drugs (NSAIDs) act on acute pain and inflammation within hours, and carry known risks to the stomach and the heart and blood vessels. Curcumin has been studied as a long-term anti-inflammatory and add-on therapy.
What Curcumin Supplement Labels Show
The supplement market is full of marketing language that obscures rather than illuminates the bioavailability question. Points that labels often leave unclear:
- "Turmeric extract" vs "curcumin extract" vs "95% curcuminoids" — these are not interchangeable. "Turmeric extract" can mean almost anything; "curcumin extract" usually implies higher curcuminoid content; "95% curcuminoids" means the active fraction is standardized.
- The total milligram weight on the label is not the curcumin dose — a 500 mg phytosome capsule contains about 100 mg actual curcuminoids and 400 mg of carrier phospholipid and excipients. A 1000 mg "turmeric root powder" capsule contains about 20–70 mg of curcuminoids. Labels that state the curcuminoid content give the actual dose.
- The named delivery system — the delivery systems described on this page (phytosome, submicron particle, solid lipid particle, micelle, turmeric essential oil, cyclodextrin, piperine) each have at least one published human pharmacokinetic study. A label that names the delivery system lets the reader match the product to those studies.
- "Enhanced bioavailability" with no delivery system named — the phrase alone does not say which mechanism, if any, is involved, and the label gives no way to tell the product apart from plain curcumin powder.
- Liquid extracts and tinctures — even in oil-based tinctures, the absorption is modest. Concentrated liquid extracts in propylene glycol or ethanol are not equivalent to phytosome or micelle formulations.
- "Organic" and "non-GMO" claims are about ingredient sourcing and have no bearing on bioavailability. A bioavailability-enhanced organic product is fine; an organic plain-powder product still has <1% absorption.
- Adulteration — some imported turmeric powder has been adulterated with lead chromate (a bright yellow pigment) for color enhancement. The USP Verified mark means the United States Pharmacopeia has tested the product for its listed ingredients and for harmful levels of specified contaminants, including heavy metals.
Key Research Papers
- Shoba G et al. (1998). Influence of piperine on the pharmacokinetics of curcumin in animals and human volunteers. Planta Medica. — PubMed PMID: 9619120
- Cuomo J et al. (2011). Comparative absorption of a standardized curcuminoid mixture and its lecithin formulation. Journal of Natural Products. — PubMed PMID: 21413691
- Sasaki H et al. (2011). Innovative preparation of curcumin for improved oral bioavailability. Biological & Pharmaceutical Bulletin, 34(5), 660–665. — PubMed PMID: 21532153
- Gota VS et al. (2010). Safety and pharmacokinetics of a solid lipid curcumin particle formulation in osteosarcoma patients and healthy volunteers. Journal of Agricultural and Food Chemistry, 58(4), 2095–2099. — PubMed PMID: 20092313
- Schiborr C et al. (2014). The oral bioavailability of curcumin from micronized powder and liquid micelles is significantly increased in healthy humans and differs between sexes. Molecular Nutrition & Food Research, 58(3), 516–527. — PubMed PMID: 24402825
- Antony B et al. (2008). A pilot cross-over study to evaluate human oral bioavailability of BCM-95CG (Biocurcumax). Indian Journal of Pharmaceutical Sciences. — PubMed PMID: 20046768
- Anand P et al. (2007). Bioavailability of curcumin: Problems and promises. Molecular Pharmaceutics. — PubMed PMID: 17999464
- Jamwal R (2018). Bioavailable curcumin formulations: A review of pharmacokinetic studies in healthy volunteers. Journal of Integrative Medicine. — PubMed PMID: 30006023
- Purpura M et al. (2018). Analysis of different innovative formulations of curcumin for improved relative oral bioavailability in human subjects. European Journal of Nutrition, 57(3), 929–938. — PubMed PMID: 28204880
- Nelson KM et al. (2017). The essential medicinal chemistry of curcumin. Journal of Medicinal Chemistry. — PubMed PMID: 28074653
- Heger M et al. (2014). The molecular basis for the pharmacokinetics and pharmacodynamics of curcumin and its metabolites in relation to cancer. Pharmacological Reviews. — PubMed PMID: 24368738
- Prasad S et al. (2014). Recent developments in delivery, bioavailability, absorption and metabolism of curcumin: The golden pigment from golden spice. Cancer Research and Treatment. — PubMed PMID: 24520218
- Kanai M et al. (2012). Dose-escalation and pharmacokinetic study of nanoparticle curcumin, a potential anticancer agent with improved bioavailability, in healthy human volunteers. Cancer Chemotherapy and Pharmacology, 69(1), 65–70. — PubMed PMID: 21603867
- Rahmani S et al. (2016). Treatment of non-alcoholic fatty liver disease with curcumin: A randomized placebo-controlled trial. Phytotherapy Research, 30(9), 1540–1548. — PubMed PMID: 27270872
- Panahi Y et al. (2017). Efficacy and safety of phytosomal curcumin in non-alcoholic fatty liver disease: A randomized controlled trial. Drug Research, 67(4), 244–251. — PubMed PMID: 28158893
- Belcaro G et al. (2010). Product-evaluation registry of Meriva®, a curcumin-phosphatidylcholine complex, for the complementary management of osteoarthritis. Panminerva Medica, 52(2 Suppl 1), 55–62. — PubMed PMID: 20657536
- Belcaro G et al. (2010). Efficacy and safety of Meriva®, a curcumin-phosphatidylcholine complex, during extended administration in osteoarthritis patients. Alternative Medicine Review, 15(4), 337–344. — PubMed PMID: 21194249
- Belcaro G et al. (2014). Meriva®+Glucosamine versus Condroitin+Glucosamine in patients with knee osteoarthritis: an observational study. European Review for Medical and Pharmacological Sciences, 18(24), 3959–3963. — PubMed PMID: 25555891
- Madhu K, Chanda K, Saji MJ (2013). Safety and efficacy of Curcuma longa extract in the treatment of painful knee osteoarthritis: a randomized placebo-controlled trial. Inflammopharmacology, 21(2), 129–136. — PubMed PMID: 23242572
- Small GW et al. (2018). Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. American Journal of Geriatric Psychiatry, 26(3), 266–277. — PubMed PMID: 29246725
- Cox KH, Pipingas A, Scholey AB (2015). Investigation of the effects of solid lipid curcumin on cognition and mood in a healthy older population. Journal of Psychopharmacology, 29(5), 642–651. — PubMed PMID: 25277322
PubMed Topic Searches
- PubMed: Curcumin bioavailability formulations
- PubMed: Curcumin phosphatidylcholine phytosome
- PubMed: Colloidal submicron-particle curcumin pharmacokinetics
- PubMed: Solid lipid curcumin particle
- PubMed: Piperine curcumin absorption
- PubMed: Curcumin nanoparticle delivery
- PubMed: Curcumin glucuronide metabolism
Connections
- All Herbs
- Turmeric Benefits Hub
- Turmeric Overview
- Turmeric for Joint Health
- Turmeric for Liver Health
- Turmeric for Brain Health
- Black Pepper (Piperine)
- Ginger
- Boswellia
- Milk Thistle
- Anti-Inflammatory Diet
- C-Reactive Protein (Inflammation Marker)
- Arthritis
- Non-Alcoholic Fatty Liver Disease
- Alzheimer's Disease
- History