⚠ Evidence warning: Clinical trials or other evidence do not support the claims that curcumin liver injury resolved after stopping in all reported cases, that no case progressed to liver failure or transplant, that most cases involved bioavailability-enhanced forms, that the risk is below 1 per 100,000 users a year, that the long-term safety record is excellent, and the doses and absorption claims given for curcumin forms. This page keeps it as a report of what people, websites or other media say.
Turmeric for Liver Health and Detoxification
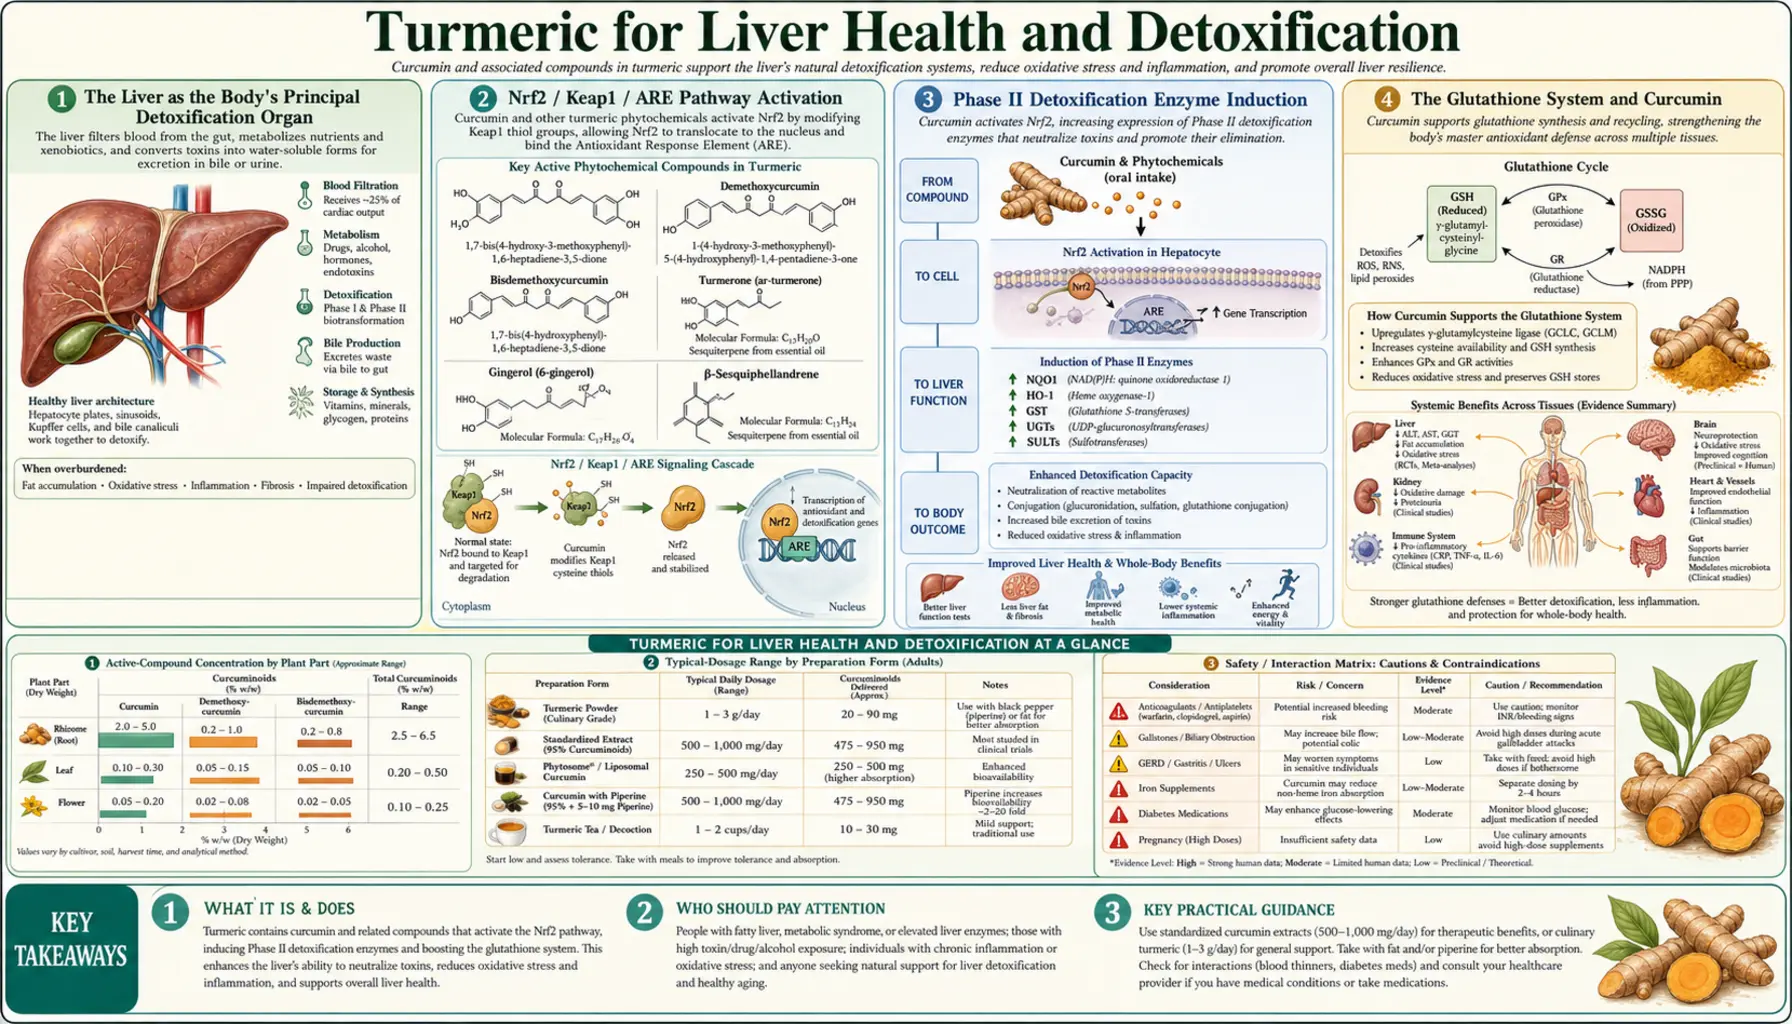
Curcumin's liver effects work through two complementary mechanisms. First, curcumin is one of the most potent dietary activators of the Nrf2 transcription factor, the master switch for Phase II detoxification enzyme induction. Activating Nrf2 upregulates glutathione S-transferase, NAD(P)H quinone dehydrogenase 1, heme oxygenase 1, and gamma-glutamylcysteine ligase — enzymes that conjugate and clear environmental toxins, drug metabolites, and oxidative-stress products from the liver and other tissues. Second, curcumin acts directly as an anti-inflammatory in hepatic Kupffer cells and stellate cells, reducing the cytokine signaling that drives nonalcoholic fatty liver disease (NAFLD) progression to non-alcoholic steatohepatitis (NASH) and fibrosis. The Rahmani 2016 and Panahi 2017 non-alcoholic fatty liver disease trials both reported reductions in the liver enzymes alanine aminotransferase (ALT) and aspartate aminotransferase (AST) and in liver fat on ultrasound with curcumin. Curcumin also has a classical cholagogue effect — stimulating bile flow and gallbladder contraction — that has been used in European herbal hepatology for two centuries. The important counterweight: turmeric supplements have caused drug-induced liver injury (DILI), sometimes severe and in one reported case fatal, with a strong association with the human leukocyte antigen-B*35:01 allele in susceptible individuals.
Table of Contents
- The Liver as the Body's Principal Detoxification Organ
- Nrf2 / Keap1 / ARE Pathway Activation
- Phase II Detoxification Enzyme Induction
- The Glutathione System and Curcumin
- Non-Alcoholic Fatty Liver Disease: The Rahmani 2016 Trial
- Non-Alcoholic Steatohepatitis, Fibrosis, and the Stellate Cell
- Hepatoprotection in Chemotherapy and Acetaminophen Injury
- The Cholagogue Effect — Bile Flow Stimulation
- Drug-Induced Liver Injury (DILI) Cases — A Real Caveat
- The Human Leukocyte Antigen-B*35:01 Allele Connection
- Doses Used in Liver Studies
- Key Research Papers
- Connections
- Featured Videos
The Liver as the Body's Principal Detoxification Organ
Every dietary, pharmaceutical, and environmental compound absorbed through the gut passes through the liver via the portal vein before reaching systemic circulation — the first-pass effect. The liver's job is to process this stream of compounds: nutrients are stored or distributed, while xenobiotics (foreign chemicals), drug molecules, and reactive metabolites are biotransformed and either excreted in bile or returned to the bloodstream for renal excretion. The biotransformation happens in two sequential phases:
- Phase I — primarily cytochrome P450 enzymes (the CYP superfamily) that oxidize, reduce, or hydrolyze the parent compound. This often produces a more reactive intermediate that can be more toxic than the parent compound, and it generates reactive oxygen species as a byproduct. Phase I "uncovers" or adds functional groups (hydroxyl, carboxyl) that Phase II can attach conjugates to.
- Phase II — conjugation reactions that attach water-soluble molecules (glutathione, glucuronic acid, sulfate, glycine, acetyl groups) to the Phase I intermediate, producing a less toxic and more water-soluble final product that can be excreted in bile or urine.
The bottleneck is often Phase II: if Phase I generates reactive intermediates faster than Phase II can conjugate them, the intermediates accumulate and damage the liver. Acetaminophen overdose is the canonical example — cytochrome P450 2E1 (CYP2E1) converts acetaminophen to the reactive NAPQI, which depletes glutathione and binds covalently to hepatocyte proteins, producing centrilobular necrosis. The treatment, N-acetylcysteine (NAC), replenishes glutathione and allows Phase II conjugation to catch up.
Curcumin's contribution to liver detoxification is primarily on the Phase II side: it strongly induces the Nrf2 transcription factor, which in turn upregulates the entire Phase II enzyme battery, increasing the liver's capacity to conjugate and clear reactive intermediates before they cause damage.
Nrf2 / Keap1 / ARE Pathway Activation
Nrf2 (nuclear factor erythroid 2-related factor 2) is a basic leucine zipper transcription factor that controls the cellular response to oxidative and electrophilic stress. In the resting state, Nrf2 is bound in the cytoplasm to its inhibitor Keap1 (Kelch-like ECH-associated protein 1), which targets Nrf2 for proteasomal degradation. Keap1 contains reactive cysteine residues that act as redox sensors — when they are oxidized or modified by electrophiles, Keap1 releases Nrf2, which translocates to the nucleus, dimerizes with small Maf proteins, and binds antioxidant response elements (ARE) in the promoter regions of dozens of cytoprotective genes.
Curcumin activates Nrf2 by modifying the reactive cysteine residues on Keap1 (Cys151 and Cys273 are the most reactive). The alpha-beta-unsaturated ketone groups in the curcumin molecule are electrophilic and react with Keap1 cysteines, freeing Nrf2 for nuclear translocation. This is essentially the same mechanism by which sulforaphane (from broccoli sprouts), allyl isothiocyanate (from mustard and wasabi), and certain triterpenoids (the synthetic compound CDDO-Me) activate the pathway. Curcumin is among the more potent dietary Nrf2 activators per gram, though sulforaphane is more potent per millimole. See our Broccoli Sprouts and Sulforaphane pages for related coverage.
The downstream effects of Nrf2 activation reach beyond classical detoxification. Nrf2 target genes include heme oxygenase 1 (HO-1, which produces the anti-inflammatory mediator bilirubin from heme), thioredoxin and thioredoxin reductase (redox regulators), gamma-glutamylcysteine ligase (rate-limiting enzyme in glutathione synthesis), and ferritin (iron storage protein that limits Fenton-reaction oxidative damage). Nrf2 activation produces a global shift toward cellular antioxidant defense and anti-inflammatory tone.
Phase II Detoxification Enzyme Induction
Curcumin-driven Nrf2 activation produces measurable upregulation of the principal Phase II enzymes in human and animal studies:
- Glutathione S-transferases (GSTs) — the largest family of Phase II enzymes, which conjugate glutathione to electrophilic xenobiotics, reactive drug metabolites, and lipid peroxidation products. The mu, pi, and alpha GST subfamilies are all Nrf2-regulated.
- UDP-glucuronosyltransferases (UGTs) — conjugate glucuronic acid to lipophilic compounds, dramatically increasing water solubility for biliary or renal excretion. UGT1A1 is particularly important for bilirubin clearance; UGT1A6 and UGT1A9 handle many drug substrates including curcumin itself.
- Sulfotransferases (SULTs) — conjugate sulfate to phenols, alcohols, and amines. The SULT1 family is the dominant hepatic isoform.
- NAD(P)H quinone dehydrogenase 1 (NQO1) — reduces quinones to less-reactive hydroquinones, preventing their participation in redox cycling that generates superoxide. NQO1 is one of the most strongly Nrf2-induced genes.
- Heme oxygenase 1 (HMOX1) — degrades free heme to biliverdin, carbon monoxide, and ferrous iron. Biliverdin is rapidly converted to bilirubin, a potent endogenous antioxidant. HMOX1 induction is anti-inflammatory and cytoprotective.
- Gamma-glutamylcysteine ligase (GCL) — the rate-limiting enzyme in de novo glutathione synthesis. Both the catalytic (GCLC) and modifier (GCLM) subunits are Nrf2-regulated.
The practical consequence is that chronic curcumin intake raises the liver's baseline antioxidant capacity and detoxification reserve. The system is most beneficial in settings of oxidative stress — alcohol exposure, polypharmacy, environmental toxin exposure (heavy metals, polycyclic aromatic hydrocarbons), and the metabolic stress of non-alcoholic fatty liver disease.
The Glutathione System and Curcumin
Glutathione (reduced glutathione, GSH) is the principal intracellular antioxidant and the substrate for GST-mediated Phase II conjugation. The tripeptide (glutamate-cysteine-glycine) is synthesized in two adenosine triphosphate-dependent steps: GCL condenses glutamate and cysteine to gamma-glutamylcysteine, and glutathione synthetase adds glycine. The cysteine sulfhydryl group is the reactive moiety that scavenges reactive oxygen species and conjugates electrophiles, becoming oxidized to glutathione disulfide (GSSG) in the process. Glutathione reductase regenerates reduced glutathione from GSSG using reduced nicotinamide adenine dinucleotide phosphate (NADPH), maintaining the reduced state.
Curcumin supports the glutathione system at multiple points:
- It induces GCL (the rate-limiting enzyme), increasing de novo glutathione synthesis capacity
- It spares glutathione consumption by directly scavenging some reactive species that would otherwise deplete reduced glutathione
- It induces glutathione reductase, accelerating reduced glutathione regeneration from GSSG
- It supports the upstream cysteine supply by mild induction of cystathionine gamma-lyase
The clinical translation is that curcumin can partially compensate for the glutathione depletion seen in chronic liver disease, alcohol use, and prolonged stress. It does not replace direct glutathione precursors like N-acetylcysteine or whey protein, but it complements them by upregulating the enzymes needed to use those precursors.
Non-Alcoholic Fatty Liver Disease: The Rahmani 2016 Trial
Non-alcoholic fatty liver disease (NAFLD) affects approximately 25% of adults globally and is the most common cause of chronic liver disease in the developed world. The pathogenesis involves hepatic insulin resistance, increased free fatty acid delivery from adipose tissue, increased de novo lipogenesis from dietary fructose and refined carbohydrate, and impaired beta-oxidation. The result is triglyceride accumulation in hepatocytes (steatosis), which can progress to non-alcoholic steatohepatitis (NASH) with inflammation and hepatocyte injury, then fibrosis, cirrhosis, and increased hepatocellular carcinoma risk.
In 2023 the disease was given a new name. A Delphi consensus process led by three large international liver associations, with 236 panellists from 56 countries, chose metabolic dysfunction-associated steatotic liver disease (MASLD) to replace non-alcoholic fatty liver disease, partly because most respondents felt the words “nonalcoholic” (61%) and “fatty” (66%) were stigmatising. The new definition is fat in the liver plus at least 1 of 5 heart-and-metabolic (cardiometabolic) risk factors. People with MASLD who drink more alcohol (140–350 g a week for women, 210–420 g for men) form a separate group called metabolic and alcohol-related liver disease (MetALD). The curcumin trials below were run before the change and use the older name.
The Rahmani S et al. 2016 double-blind trial in Phytotherapy Research randomized adults with ultrasound-confirmed non-alcoholic fatty liver disease to an amorphous dispersion curcumin formulation (500 mg/day, equivalent to 70 mg of curcumin) or a matched placebo for 8 weeks. Results, compared with placebo:
- Liver fat on ultrasound improved in 78.9% of the curcumin group vs 27.5% of the placebo group
- Alanine aminotransferase decreased significantly in the curcumin group
- Aspartate aminotransferase decreased significantly in the curcumin group
- Body mass index, total cholesterol, low-density lipoprotein (LDL) cholesterol, triglycerides, blood glucose and glycated hemoglobin (HbA1c) also fell in the curcumin group
- The authors reported curcumin was safe and well tolerated over the 8 weeks
This was followed by Panahi Y et al. 2017 in Drug Research, which randomized 102 people with non-alcoholic fatty liver disease to phytosomal (phospholipid-bound) curcumin 1,000 mg/day in 2 divided doses (50 people) or placebo (52 people) for 8 weeks; 87 completed the trial, and everyone received diet and lifestyle advice first. Liver ultrasound improved in 75.0% of the curcumin group vs 4.7% of the placebo group. Aspartate aminotransferase and alanine aminotransferase fell in the curcumin group and rose in the placebo group, and body mass index and waist size also fell with curcumin.
The pooled analyses are more cautious. A 2019 meta-analysis (Mansour-Ghanaei et al., Integrative Medicine Research) combined 4 randomized trials with 228 people: alanine aminotransferase showed only a trend toward reduction at 1,000 mg/day or more (−11.36 IU/L, a result that did not reach statistical significance), aspartate aminotransferase fell significantly in the 8-week studies (−9.22 IU/L), and liver fat was not pooled. The authors concluded curcumin “might have a favorable effect” at higher doses and called for larger, high-quality trials. A 2025 meta-analysis (Vajdi et al., Nutrition Reviews) of 15 randomized trials with 905 people found curcumin lowered alanine aminotransferase by about 4.1 U/L and aspartate aminotransferase by about 3.3 U/L compared with control, with no change in alkaline phosphatase. In the trials that combined curcumin with piperine (black pepper extract), there was no significant effect on either enzyme.
The mechanism in non-alcoholic fatty liver disease is multi-pronged: Nrf2-mediated reduction of hepatic oxidative stress, NF-kB-mediated reduction of hepatic inflammation, AMP-activated protein kinase (AMPK) activation that promotes beta-oxidation and inhibits de novo lipogenesis, and direct effects on PPAR-alpha and PPAR-gamma that improve hepatic insulin sensitivity. Curcumin is now included as an adjunct option in some integrative non-alcoholic fatty liver disease treatment algorithms, alongside the cornerstone interventions of weight loss, low-fructose diet, and exercise. See our non-alcoholic fatty liver disease page for the full management approach.
Non-Alcoholic Steatohepatitis, Fibrosis, and the Stellate Cell
When non-alcoholic fatty liver disease progresses to non-alcoholic steatohepatitis, hepatic stellate cells — normally quiescent vitamin A-storing cells in the space of Disse — become activated by transforming growth factor beta (TGF-beta), platelet-derived growth factor (PDGF), and oxidative stress signals from injured hepatocytes and Kupffer cells. Activated stellate cells transform into myofibroblasts and secrete type I collagen, producing the bridging fibrosis that is the hallmark of non-alcoholic steatohepatitis and the precursor of cirrhosis.
Curcumin has direct antifibrotic effects on activated stellate cells in vitro: it inhibits TGF-beta signaling (the master profibrotic cytokine), reduces collagen I deposition, induces stellate cell apoptosis, and reduces PDGF receptor expression. Animal models of carbon tetrachloride-induced fibrosis show consistent antifibrotic effect of curcumin; in one rat study (Park 2000), curcumin cut liver hydroxyproline, a marker of collagen, to 48% of the untreated level after 4 weeks of carbon tetrachloride injury. Human evidence in established non-alcoholic steatohepatitis fibrosis is still limited — the trials cited above focused on liver enzymes and steatosis rather than fibrosis biomarkers — but the mechanistic basis is solid and a small number of trials have shown reductions in elastography stiffness and serum markers like the Fibrosis-4 index with longer-term curcumin therapy.
Curcumin is not a proven treatment for advanced fibrosis or cirrhosis. The human curcumin trials were in early non-alcoholic fatty liver disease, and the measures that act on the underlying metabolic disease are weight loss, glucagon-like peptide-1 (GLP-1) agonists and dietary change.
For comparison, a medicine has now been tested in a large trial for steatohepatitis with fibrosis. Resmetirom is a liver-directed thyroid hormone receptor beta-selective agonist taken by mouth once a day. In the 2024 MAESTRO-NASH phase 3 trial (Harrison et al., New England Journal of Medicine), 966 adults with biopsy-confirmed non-alcoholic steatohepatitis and fibrosis stage F1B to F3 received resmetirom 80 mg, 100 mg or placebo. At 52 weeks, steatohepatitis resolved without worsening of fibrosis in 25.9% (80 mg) and 29.9% (100 mg) vs 9.7% on placebo, and fibrosis improved by at least one stage in 24.2% and 25.9% vs 14.2%. Diarrhea and nausea were more common with resmetirom; serious adverse events were similar across the groups (10.9%, 12.7% and 11.5%). See the FDA approval of resmetirom.
Hepatoprotection in Chemotherapy and Acetaminophen Injury
Several chemotherapeutic agents cause dose-limiting hepatotoxicity — methotrexate, asparaginase, capecitabine, oxaliplatin (sinusoidal obstruction syndrome), and many of the tyrosine kinase inhibitors. Pre-clinical and limited human data suggest curcumin reduces chemotherapy-induced liver injury, primarily through its Nrf2/Phase II induction and direct antioxidant effects. The Belcaro 2014 controlled study of a phospholipid-bound (lecithinized) curcumin in 160 people having chemotherapy or radiotherapy, referenced on the joint-health page, scored side effects on a visual analogue scale and reported that the curcumin “might alleviate the burden of side effects”; its abstract does not mention liver effects, and the authors called for larger trials.
For acetaminophen-induced liver injury, the canonical model of drug-induced liver damage, animal studies consistently show that curcumin pre-treatment reduces alanine aminotransferase/aspartate aminotransferase elevation, prevents centrilobular necrosis, and improves survival from otherwise-lethal acetaminophen doses. The mechanism is the Nrf2-mediated upregulation of glutathione synthesis and Phase II conjugation enzymes that detoxify the reactive NAPQI metabolite. Curcumin does not replace N-acetylcysteine as the standard treatment for acute acetaminophen overdose — N-acetylcysteine works much faster and provides direct glutathione precursor — but curcumin may offer some prophylactic protection in patients with chronic high-dose acetaminophen exposure (chronic pain management, post-surgical use).
Other documented hepatoprotective applications: alcohol-related liver injury (animal models and small human studies), iron-overload hepatotoxicity (curcumin chelates iron and prevents Fenton-reaction damage), and copper-overload hepatotoxicity in animal Wilson's disease models.
The Cholagogue Effect — Bile Flow Stimulation
Beyond the modern Nrf2/Phase II mechanism, turmeric has been used in European herbal hepatology since the 19th century as a cholagogue — an agent that stimulates bile production by the liver and bile expulsion by the gallbladder. The German Commission E monograph (the regulatory document underpinning German herbal medicine) approves turmeric for "dyspeptic complaints" largely on the strength of the cholagogue effect, which improves digestion of dietary fats and supports bile-mediated excretion of cholesterol and conjugated xenobiotics.
The cholagogue mechanism is partially mediated by direct stimulation of cholecystokinin (CCK) release from the duodenal mucosa when curcumin or other curcuminoids are present in the gut lumen. CCK in turn stimulates gallbladder contraction and bile expulsion into the duodenum. Curcumin also increases bile salt synthesis in hepatocytes through activation of the FXR (farnesoid X receptor) bile acid receptor pathway.
The clinical applications: gentle support for fat digestion (especially in people with sluggish bile flow but no obstruction), facilitation of biliary excretion of cholesterol (modest cholesterol-lowering effect documented in trials), and traditional use in nonobstructive cholestasis. The flip side is the contraindication noted in the joint-health page: symptomatic gallstones. If a patient has stones that intermittently obstruct the cystic or common bile duct, stimulating gallbladder contraction with curcumin can precipitate biliary colic or pancreatitis. This is why symptomatic gallstones (cholelithiasis) are treated as a contraindication to curcumin, and silent gallstones as a reason for caution.
Drug-Induced Liver Injury (DILI) Cases — A Real Caveat
Despite curcumin's reputation as a liver-supportive herb, turmeric and curcumin supplements have been linked to drug-induced liver injury (DILI). The most-cited case series is Halegoua-DeMarzio D et al. 2023 in the American Journal of Medicine, from the US Drug-Induced Liver Injury Network (DILIN). Reviewing every case the network enrolled from 2004 to 2022, it found 10 cases of turmeric-associated liver injury — all since 2011, and 6 since 2017. Eight of the 10 were women, the median age was 56 (range 35–71), and the time from starting the product to the injury (latency) was 1 to 4 months. Five patients were hospitalized, and 1 died of acute liver failure. The authors concluded that turmeric “causes potentially severe liver injury” and that such injury appears to be increasing in the United States, perhaps reflecting usage patterns or more frequent combination with black pepper.
Pattern of injury:
- Hepatocellular pattern — in 9 of the 10 DILIN cases the injury was hepatocellular (liver-cell injury, with marked alanine aminotransferase and aspartate aminotransferase elevation and modest or no alkaline phosphatase elevation), and in 1 it was mixed. Liver biopsies in 4 patients showed acute hepatitis or mixed cholestatic-hepatic injury with eosinophils. Some cases progressed to jaundice with bilirubin elevation.
- Idiosyncratic — the dose-response relationship is weak. Some cases occurred at modest supplement doses, others at higher doses; the pattern suggests an immune/genetic susceptibility rather than dose-dependent toxicity.
- Onset 1 to 4 months after starting — the latency the DILIN authors reported, consistent with an immunoallergic mechanism rather than direct toxicity.
- Resolution upon discontinuation — in all reported cases, alanine aminotransferase/aspartate aminotransferase normalized within weeks to a few months after stopping curcumin.
- No case progressed to fulminant hepatic failure or required transplantation.
- Association with bioavailability-enhanced formulations — most reported cases involved phospholipid-bound (phytosomal), colloidal nanoparticle, or piperine-enhanced curcumin rather than plain turmeric powder.
- The injury can be severe — in the DILIN series 5 of the 10 patients were hospitalized and 1 died of acute liver failure.
- Products tested — chemical analysis confirmed turmeric in all 7 products the DILIN investigators could test, and 3 of the 7 also contained piperine (black pepper extract), which is added to raise curcumin absorption. One proposed explanation is that higher systemic curcumin exposure enables the idiosyncratic immune reaction in susceptible individuals.
The absolute risk is small — given the volume of curcumin supplements sold globally, the reported case count corresponds to a rate likely below 1 per 100,000 users per year, though there is substantial underreporting. Reported cases are few compared with the large number of people who take turmeric supplements, but none of the sources on this page measures a rate per user, and there is substantial under-reporting. Acetaminophen, statins, isoniazid and amoxicillin-clavulanate are widely prescribed medicines that also carry a known DILI signal. The risk from turmeric supplements is real.
Practical facts: the DILIN injuries appeared 1 to 4 months after starting the product; liver-cell injury of this kind shows as a rise in alanine aminotransferase and aspartate aminotransferase on a liver blood test; and yellowing of the skin or eyes (jaundice), dark urine, pale stools and pain under the right ribs are signs of liver injury that hospitals treat as urgent. The long record of plain culinary turmeric in food is a separate matter from these supplement cases. The chronic-user safety record remains excellent for plain culinary turmeric and for the millions of supplement users who do not have this susceptibility.
The Human Leukocyte Antigen-B*35:01 Allele Connection
The Halegoua-DeMarzio 2023 case series and subsequent reports have identified an apparent association between curcumin-related DILI and the human leukocyte antigen-B*35:01 allele. In the DILIN series, human leukocyte antigen (HLA) typing showed that 7 of the 10 patients carried HLA-B*35:01, 2 of them with two copies (homozygous), giving an allele frequency of 0.450 compared with 0.056–0.069 in population controls; the authors described a “strong linkage” to the allele. The same allele has been associated with green tea extract (epigallocatechin gallate, EGCG) DILI, suggesting it may predispose to both.
Human leukocyte antigen-B*35:01 is present in approximately 5–10% of European populations and at lower frequencies elsewhere. The mechanistic hypothesis is that the allele's peptide-binding groove has a specific affinity for curcumin metabolites covalently bound to hepatocyte proteins, allowing presentation of the curcumin-modified self-peptide to CD8+ T cells, which then mount an immune attack on the hepatocytes that display the same modified self-antigen. This is the same proposed mechanism for the strong human leukocyte antigen-B*57:01 association with abacavir hypersensitivity and the human leukocyte antigen-B*15:02 association with carbamazepine Stevens-Johnson syndrome in Asian populations.
Routine human leukocyte antigen-B*35:01 testing before starting curcumin supplements is not standard of care. The research raises the most concern for people with a personal or family history of unexplained drug-induced liver injury, particularly with herbal products, and for known carriers of human leukocyte antigen-B*35:01, who made up 7 of the 10 DILIN cases.
Doses Used in Liver Studies
The doses used in the fatty liver trials, and the main curcumin forms:
- Amorphous dispersion curcumin, 500 mg a day (equivalent to 70 mg of curcumin) — the dose in the Rahmani 2016 non-alcoholic fatty liver disease trial, for 8 weeks.
- Phospholipid-bound (phytosomal) curcumin, 1,000 mg a day in 2 divided doses — the dose in the Panahi 2017 non-alcoholic fatty liver disease trial, for 8 weeks. Best documented in non-alcoholic fatty liver disease specifically.
- Colloidal nanoparticle curcumin — a submicron-particle form made for higher absorption; none of the liver trials described on this page tested it. At 90–180 mg twice daily it gives equivalent systemic exposure with the colloidal submicron-particle formulation.
- Turmeric-oil-combined curcumin — curcumin combined with turmeric essential oil to raise absorption; none of the liver trials described on this page tested it. At 500 mg twice daily, turmeric essential oil enhances absorption; well-tolerated in long-term studies.
- 95% curcuminoid extract 500 mg + 5 mg piperine, twice daily with meals, is a cost-effective option; absorption is via piperine-mediated glucuronidation inhibition. Curcuminoid extract with piperine — piperine raises absorption by inhibiting glucuronidation. In the 2025 meta-analysis, trials of curcumin plus piperine showed no significant effect on alanine aminotransferase or aspartate aminotransferase, and 3 of the 7 products tested in the DILIN liver-injury series contained piperine.
The trials above lasted 8 weeks; the DILIN liver injuries appeared 1 to 4 months after starting, and 7 of the 10 patients carried human leukocyte antigen-B*35:01. Liver enzymes are monitored at baseline, 1 month, and 3 months when any high-dose bioavailability-enhanced curcumin is started in a patient with pre-existing liver disease; the stop point described is alanine aminotransferase or aspartate aminotransferase rising above 3x baseline.
Other substances studied for the liver: milk thistle (silymarin) for hepatocyte membrane stabilization and Nrf2 activation through a different binding pocket; N-acetylcysteine for direct glutathione precursor supply; vitamin E (mixed tocopherols) as the lipid-phase antioxidant complement to curcumin's mixed-phase activity (PIVENS trial showed vitamin E efficacy in nondiabetic non-alcoholic steatohepatitis); broccoli sprouts for sulforaphane-mediated Nrf2 activation.
Key Research Papers
- Rahmani S et al. (2016). Treatment of non-alcoholic fatty liver disease with curcumin: A randomized placebo-controlled trial. Phytotherapy Research. — PubMed PMID: 27270872
- Panahi Y et al. (2017). Efficacy and safety of phytosomal curcumin in non-alcoholic fatty liver disease: A randomized controlled trial. Drug Research. — PubMed PMID: 28158893
- Mansour-Ghanaei F et al. (2019). Efficacy of curcumin/turmeric on liver enzymes in patients with non-alcoholic fatty liver disease: A systematic review of randomized controlled trials. Integrative Medicine Research. — PubMed PMID: 30949432
- Halegoua-DeMarzio D et al. (2023). Liver injury associated with turmeric — a growing problem: ten cases from the Drug-Induced Liver Injury Network [DILIN]. American Journal of Medicine. — PubMed PMID: 36252717
- Balogun E et al. (2003). Curcumin activates the haem oxygenase-1 gene via regulation of Nrf2 and the antioxidant-responsive element. Biochemical Journal. — PubMed PMID: 12570874
- Farzaei MH et al. (2018). Curcumin in liver diseases: A systematic review of the cellular mechanisms of oxidative stress and clinical perspective. Nutrients. — PubMed PMID: 29966389
- Reyes-Gordillo K et al. (2007). Curcumin protects against acute liver damage in the rat by inhibiting NF-kappaB, proinflammatory cytokines production and oxidative stress. Biochimica et Biophysica Acta. — PubMed PMID: 17383825
- Park EJ et al. (2000). Protective effect of curcumin in rat liver injury induced by carbon tetrachloride. Journal of Pharmacy and Pharmacology. — PubMed PMID: 10813555
- Vera-Ramirez L et al. (2013). Curcumin and liver disease. BioFactors. — PubMed PMID: 23303639
- Lukefahr AL et al. (2018). Drug-induced autoimmune hepatitis associated with turmeric dietary supplement use. BMJ Case Reports. — PubMed PMID: 30206065
- Belcaro G et al. (2014). A controlled study of a lecithinized delivery system of curcumin to alleviate the adverse effects of cancer treatment. Phytotherapy Research. — PubMed PMID: 23775598
- Rinella ME et al. (2023). A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology. — PubMed PMID: 37363821
- Vajdi M et al. (2025). Curcumin supplementation effect on liver enzymes in patients with nonalcoholic fatty liver disease: a GRADE-assessed systematic review and dose-response meta-analysis of randomized controlled trials. Nutrition Reviews. — PubMed PMID: 38213188
- Harrison SA et al. (2024). A phase 3, randomized, controlled trial of resmetirom in NASH with liver fibrosis. New England Journal of Medicine. — PubMed PMID: 38324483
PubMed Topic Searches
Connections
- All Herbs
- Turmeric Benefits Hub
- Turmeric Overview
- Turmeric for Joint Health
- Turmeric for Brain Health
- Bioavailability & Forms
- Milk Thistle (Silymarin)
- Broccoli Sprouts (Sulforaphane)
- Sulforaphane
- Cysteine
- Vitamin E (Non-Alcoholic Fatty Liver Disease)
- Non-Alcoholic Fatty Liver Disease (Fatty Liver)
- Cirrhosis
- Liver Function Tests
- Detoxification
- History