Brain Aging: Mechanisms, Biomarkers, and Evidence-Based Strategies
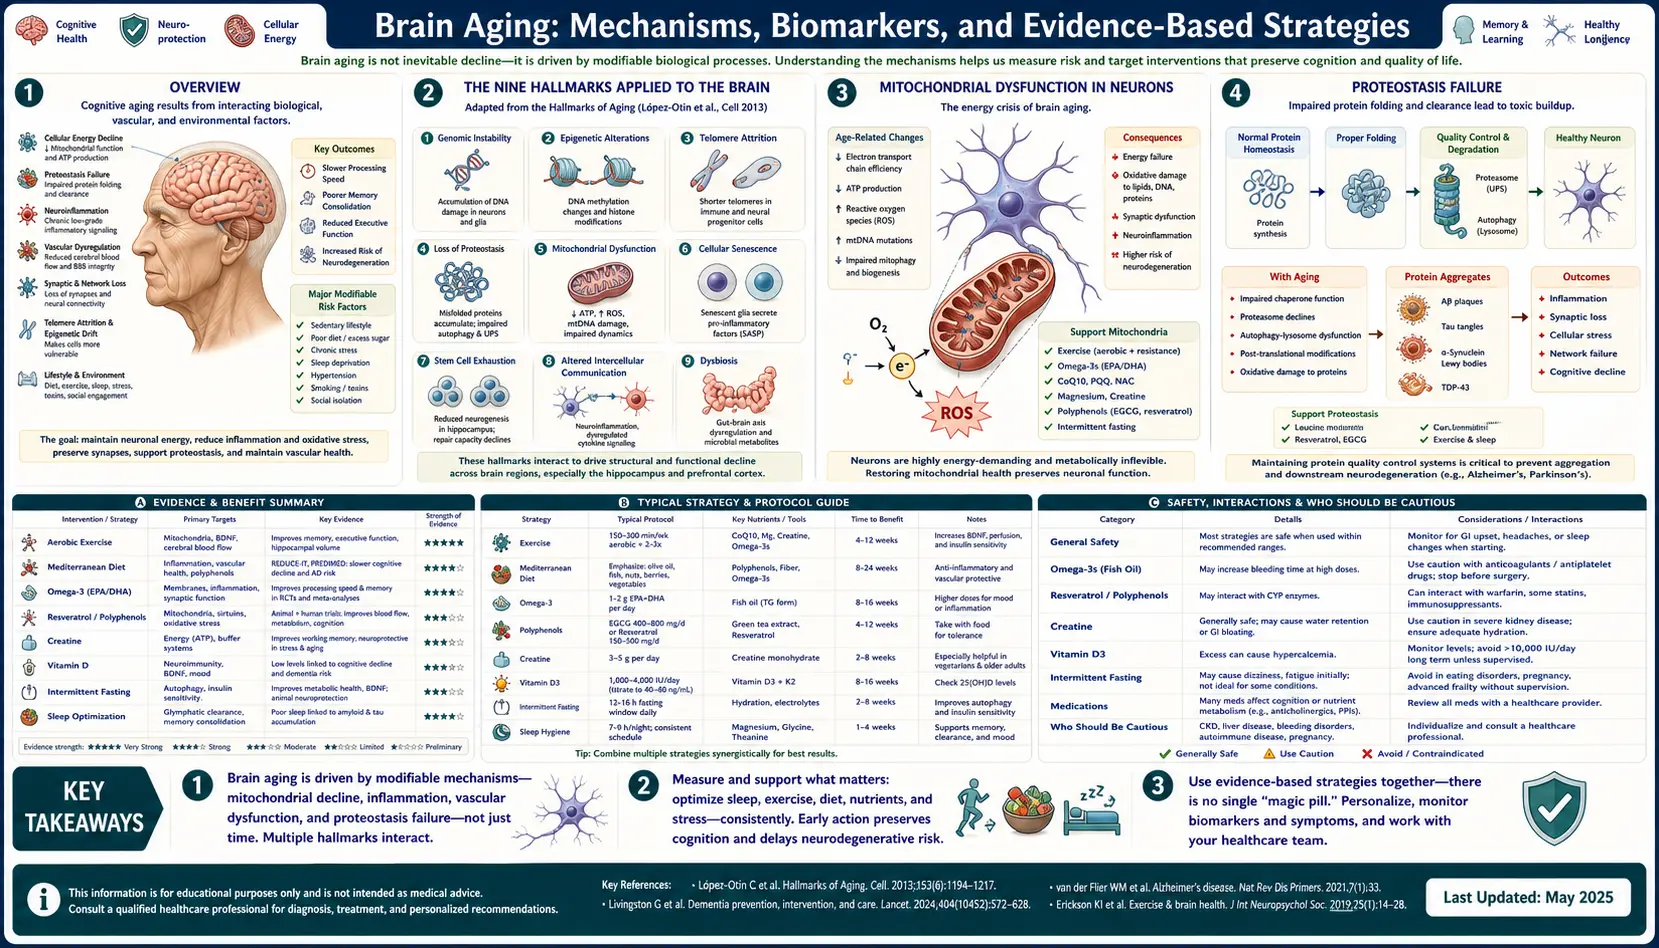
Table of Contents
- Overview
- The Nine Hallmarks Applied to the Brain
- Mitochondrial Dysfunction in Neurons
- Proteostasis Failure
- Glymphatic System and Sleep
- Neuroinflammation and Microglia Priming
- Vascular Contribution and Cerebral Small-Vessel Disease
- Insulin Resistance — "Type 3 Diabetes"
- Epigenetic Clocks Applied to Brain
- Sirtuins, Nicotinamide Adenine Dinucleotide, and Senescence
- Lifestyle Interventions With Strongest Evidence
- Targeted Supplements and Compounds
- Pharmacological Frontiers
- Biomarkers Worth Tracking
- Practical Synthesis
- Key Research Papers
- Connections
- Featured Videos
Overview
The phrase "brain aging" papers over two very different processes that happen to share a calendar. The first is biological brain aging — the slow accumulation of molecular and cellular damage in neurons, glia, and the vasculature, much of which proceeds silently for decades. The second is cognitive aging — the eventual appearance of subjective forgetfulness, reduced processing speed, mild executive slips, and (in the worst cases) frank dementia. The two are correlated but not identical: people with substantial Alzheimer's pathology at autopsy can have been cognitively normal in life (so-called "asymptomatic AD"), while others with relatively clean brains can decline catastrophically from vascular disease, depression, sleep apnea, alcohol, or polypharmacy.
The clinically useful split is between normal (healthy) aging and pathological decline. Healthy aging includes mildly slower recall of names, longer learning curves for new technical material, and a roughly linear shrinkage of total brain volume of about 0.2–0.5% per year after age 60. Pathological aging is defined by the accelerated loss of independence: difficulty managing finances, getting lost in familiar places, repeating questions within minutes, personality change, or motor parkinsonism. The transition zone — mild cognitive impairment (MCI) — is now the single most important intervention window, because the molecular damage driving Alzheimer's and Parkinson's begins 15–20 years before symptoms.
The encouraging finding of the past decade is that a meaningful fraction of late-life cognitive decline is modifiable. The 2024 Lancet Commission on dementia prevention concluded that addressing 14 risk factors across the lifespan could potentially prevent or delay up to 45% of dementia cases — including hearing loss, hypertension, smoking, obesity, depression, physical inactivity, diabetes, alcohol consumption, traumatic brain injury, air pollution, social isolation, low educational attainment, untreated visual impairment, and high low-density lipoprotein (LDL) cholesterol. The biology that drives the modifiable fraction is the focus of this page: how the brain actually ages at a molecular level, which biomarkers reflect that process, and which interventions have human evidence rather than mouse-only or marketing-only support.
The unifying frame is the hallmarks of aging framework first articulated by López-Otín and colleagues in Cell in 2013 and updated in 2023. The brain is not exempt from the same nine (now twelve) hallmarks that drive aging in every other organ — it just expresses them through neuron-specific failures. Understanding which hallmark dominates which clinical syndrome (proteostasis in Alzheimer's, mitochondrial dysfunction in Parkinson's, vascular and inflammatory hallmarks in vascular dementia) is the bridge from longevity research to actionable prevention.
The Nine Hallmarks Applied to the Brain
López-Otín's original nine hallmarks of aging map onto neurons and glia with disease-relevant specificity. The framework was expanded to twelve hallmarks in 2023 (adding disabled macroautophagy, chronic inflammation, and dysbiosis), and every one of them has been demonstrated in human cortex. Reviewing them in order clarifies why "brain aging" is not one thing but a portfolio of failures that can be measured and, in many cases, slowed.
1. Genomic instability. Neurons are postmitotic and cannot dilute damaged DNA by dividing, so single-strand and double-strand breaks accumulate over decades. Oxidative damage to mitochondrial DNA is particularly important because mtDNA lacks histones and has limited repair capacity. Markers of DNA damage (gamma-H2AX foci, 8-oxoguanine) increase with age in pyramidal neurons. 2. Telomere attrition. Though neurons rarely divide, telomere shortening in peripheral leukocytes correlates with smaller hippocampal volume and faster cognitive decline; the relationship is bidirectional, because chronic stress accelerates telomere loss systemically.
3. Epigenetic alterations. DNA methylation drifts with age in ways measurable by epigenetic clocks, including a cortex-specific clock (Shireby 2020); histone modifications and chromatin remodeling shift the transcriptome of aged neurons toward stress-response and inflammatory programs. 4. Loss of proteostasis. The capacity of the chaperone network (HSPs), the ubiquitin–proteasome system, and autophagy all decline with age, allowing aggregation-prone proteins (beta-amyloid, tau, alpha-synuclein, TDP-43) to accumulate. This is the central failure in classical neurodegeneration.
5. Deregulated nutrient sensing. Insulin/insulin-like growth factor 1 (IGF-1) signaling, mechanistic target of rapamycin (mTOR), AMP-activated protein kinase (AMPK), and sirtuins form an interconnected nutrient-sensing network. Hyperactive mechanistic target of rapamycin (from chronic overnutrition) suppresses autophagy and accelerates aging; conversely, calorie restriction, intermittent fasting, and rapamycin extend lifespan in every species tested. The brain is especially mechanistic target of rapamycin-sensitive because dendritic protein synthesis and synaptic plasticity depend on tightly regulated translation.
6. Mitochondrial dysfunction. Aged neurons show decreased Complex I and IV activity, increased reactive oxygen species (ROS) production, impaired calcium buffering, and accumulation of damaged mitochondria due to failing mitophagy. Because the brain uses 20% of resting energy expenditure for 2% of body mass, even modest bioenergetic deficits cascade into synaptic failure. 7. Cellular senescence. Senescent astrocytes and microglia accumulate in aged cortex and secrete the senescence-associated secretory phenotype (SASP) — interleukin-6 (IL-6), tumor necrosis factor-alpha, MMP-3, CCL2 — that drives chronic neuroinflammation. Senolytic compounds (dasatinib + quercetin, fisetin) selectively kill these cells in animal models with cognitive benefit.
8. Stem-cell exhaustion. Adult neurogenesis in the human hippocampal dentate gyrus has been documented through the ninth decade of life, but the rate falls steeply with age. Exercise, environmental enrichment, and brain-derived neurotrophic factor (BDNF) preserve neurogenic capacity; chronic stress, cortisol, alcohol, and inflammation suppress it. 9. Altered intercellular communication. The aging brain shows "inflammaging" — rising baseline cytokines, complement-mediated synapse pruning by microglia, and loss of synchronized network oscillations. The 2023 expanded hallmarks add disabled macroautophagy (especially mitophagy), chronic inflammation, and dysbiosis (the gut microbiome's growing recognition as a regulator of neuroinflammation via the vagus nerve and bacterial metabolites).
Mitochondrial Dysfunction in Neurons
The brain is the most mitochondrially demanding organ in the body. A resting neuron consumes roughly 4.7 billion adenosine triphosphate (ATP) molecules per second, almost all of it from oxidative phosphorylation, and the majority of that adenosine triphosphate fuels the Na+/K+ ATPase that maintains the resting membrane potential after each action potential. Even a 10–20% decline in oxidative capacity is enough to compromise synaptic transmission, particularly at the energy-hungry presynaptic terminals where vesicle recycling, calcium clearance, and neurotransmitter reuptake all draw on local adenosine triphosphate pools.
Aged neurons reliably show declines in Complex I and Complex IV activity, measurable both in postmortem cortex and in skin-derived fibroblasts from aged donors. Complex I (reduced nicotinamide adenine dinucleotide (NADH):ubiquinone oxidoreductase) is the largest and most fragile of the respiratory complexes, and its decline drives a corresponding rise in electron leak and superoxide production. The resulting reactive oxygen species (ROS) damage mitochondrial lipids, proteins, and especially mtDNA, which sits unprotected adjacent to the inner membrane. Because mtDNA encodes 13 essential subunits of the respiratory complexes, oxidative mtDNA damage creates a self-amplifying spiral — the mitochondrial theory of aging in its modern molecular form.
Calcium handling is the second mitochondrial vulnerability. Mitochondria buffer cytosolic Ca2+ during high-frequency firing through the mitochondrial calcium uniporter (MCU), and matrix Ca2+ in turn stimulates the TCA cycle dehydrogenases. In aged neurons, the inner membrane is more permeable, the mitochondrial permeability transition pore opens at lower Ca2+ loads, and prolonged Ca2+ overload triggers cytochrome c release and apoptosis. This pathway is centrally implicated in selective vulnerability of substantia nigra dopaminergic neurons in Parkinson's disease, where Ca2+-driven pacemaking imposes an unusually high mitochondrial workload.
Mitophagy — the selective autophagic clearance of damaged mitochondria via the PINK1/Parkin pathway — declines with age. Loss-of-function mutations in PINK1 and PRKN cause early-onset Parkinson's; even in sporadic disease, mitophagy flux is reduced. Compounds that restore mitophagy (urolithin A, spermidine, nicotinamide adenine dinucleotide (NAD+) precursors) are an active area of clinical investigation. UCP2 (mitochondrial uncoupling protein 2), expressed in neurons of the arcuate nucleus and substantia nigra, modulates reactive oxygen species production and calcium handling; its expression rises with caloric restriction and falls with chronic overnutrition, providing one mechanism by which diet directly influences brain bioenergetics.
Proteostasis Failure
The proteostasis network — chaperones, the ubiquitin–proteasome system, and autophagy — manages the lifecycle of every protein from synthesis through quality control to disposal. With age the network's capacity falls just as the demand on it rises: oxidized proteins accumulate, misfolded conformers escape chaperones, the 26S proteasome becomes less assembled, and the autophagic flux that should clear aggregates slows. The result is the visible pathology of late-life neurodegeneration — protein aggregates of various kinds in characteristic brain regions.
Beta-amyloid (Abeta). Sequential cleavage of the amyloid precursor protein (APP) by beta-secretase (BACE1) and gamma-secretase generates Abeta peptides of 38–43 residues. The longer, more hydrophobic Abeta42 is highly aggregation-prone, forming soluble oligomers (the most synaptotoxic species), protofibrils, and ultimately the extracellular plaques that define Alzheimer's disease. The "amyloid cascade hypothesis" — that Abeta accumulation is upstream of tau pathology, neuroinflammation, and neurodegeneration — was clinically validated by the modest but real benefit of the monoclonal antibodies lecanemab and donanemab, which clear amyloid and slow decline by ~25–35% over 18 months in early disease.
Tau. Tau is a microtubule-stabilizing protein in axons. Hyperphosphorylation (especially at sites recognized by the AT8 antibody) detaches tau from microtubules and allows it to aggregate into paired helical filaments — the neurofibrillary tangles of Alzheimer's. Crucially, tau pathology correlates with cognitive decline far better than amyloid burden; plasma p-tau217 has emerged as the single most useful blood biomarker for early AD, performing at the level of cerebrospinal fluid (CSF) assays and amyloid positron emission tomography (PET) in some cohorts. Tau also drives the primary tauopathies (progressive supranuclear palsy, corticobasal degeneration, frontotemporal lobar degeneration with tau pathology).
Alpha-synuclein aggregates into Lewy bodies in Parkinson's disease and Lewy body dementia; its prion-like spread from gut and olfactory bulb to brainstem to cortex (the Braak staging hypothesis) explains the long prodrome of constipation, anosmia, and REM sleep behavior disorder that precedes motor symptoms by 10–20 years. TDP-43 aggregates drive amyotrophic lateral sclerosis and the majority of frontotemporal dementia, and are also found in a large fraction of aged hippocampi as the "LATE" (limbic-predominant age-related TDP-43 encephalopathy) phenotype, often misdiagnosed as Alzheimer's.
The common thread is chaperone exhaustion and autophagy failure. Heat-shock proteins (HSP70, HSP90, HSP104 in yeast) fold and refold client proteins; the unfolded protein response (UPR) in the endoplasmic reticulum diverts translation when misfolded proteins accumulate. Both systems become less effective with age. Macroautophagy — especially the chaperone-mediated and mitophagy subsets — declines steeply, allowing aggregates that would have been cleared in youth to persist and seed further misfolding. Interventions that boost autophagy (caloric restriction, rapamycin, spermidine) are a leading anti-aging strategy precisely because they target proteostasis at its source.
Glymphatic System and Sleep
In 2012–2013, Maiken Nedergaard and colleagues at Rochester described the glymphatic system — a brain-wide network that uses cerebrospinal fluid (CSF) flowing along periarterial spaces, through the parenchyma via astrocytic aquaporin-4 (AQP4) channels, and out along perivenous routes to clear interstitial solutes including amyloid-beta and tau. The discovery filled a long-standing puzzle: the brain has no conventional lymphatic system, yet must dispose of metabolic waste from a tissue with the highest metabolic rate in the body.
The defining finding from Nedergaard's group, published in Science in 2013, was that in mice glymphatic clearance is dramatically more active during sleep than during wake. Using imaging in live mice, the group found that natural sleep (or anaesthesia) was associated with a 60% increase in the brain's interstitial space and a striking increase in the exchange of cerebrospinal fluid with interstitial fluid, and that injected radiolabeled Abeta was cleared twofold faster in sleeping than in awake mice (Xie 2013). The phenomenon depends on AQP4 polarization to astrocytic end-feet around blood vessels — a polarization that is lost in the aged brain and in AD, producing a measurable "glymphatic failure" that is itself an aging hallmark of the central nervous system.
The clinical implications are enormous. Chronic short sleep, fragmented sleep, and especially obstructive sleep apnea compromise glymphatic clearance and are now established risk factors for cognitive decline and dementia. Sleep apnea drives intermittent hypoxia, sympathetic activation, blood–brain barrier disruption, and direct impairment of slow-wave sleep architecture. Treatment with CPAP improves cognition in moderate-to-severe OSA in randomized trials, and screening with home sleep studies has become an essential part of any modern cognitive-decline workup.
Practical glymphatic-friendly sleep hygiene includes prioritizing seven to nine hours of opportunity for sleep, sleeping on the side (lateral position appears to optimize glymphatic flow in animal models), maintaining strict circadian regularity, treating sleep apnea aggressively, restricting alcohol (which suppresses slow-wave sleep), and limiting late-evening light exposure. Magnesium-L-threonate and apigenin (from chamomile) have modest evidence for improving sleep architecture; melatonin at low doses (0.3–1 mg) may help phase-shift the circadian clock in older adults. The single most powerful glymphatic intervention, however, is simply consistent, deep, undisrupted sleep.
Neuroinflammation and Microglia Priming
Microglia are the brain's resident immune cells, derived embryologically from yolk-sac progenitors and self-renewing locally throughout life. In youth they survey the neuropil with motile processes, prune underutilized synapses during development, and clear debris and pathogens. With age they undergo a profound shift toward a "primed" phenotype: shorter, less motile processes; elevated baseline production of IL-1beta, interleukin-6, and tumor necrosis factor-alpha; exaggerated response to subsequent inflammatory stimuli; and accumulation of dystrophic, senescent forms that secrete the senescence-associated secretory phenotype.
The NLRP3 inflammasome is a central driver of microglial inflammaging. NLRP3 assembles in response to a variety of damage-associated molecular patterns (DAMPs) including Abeta fibrils, mitochondrial reactive oxygen species, and extracellular adenosine triphosphate, recruiting caspase-1 to cleave pro-IL-1beta and pro-IL-18 into their active forms. Chronic NLRP3 activation produces a self-sustaining loop of microglial activation, synaptic dysfunction, and neuronal death. NLRP3 inhibitors (the small molecule MCC950 and structurally related compounds) reduce pathology in AD animal models and are in early human trials.
The complement cascade — specifically C1q, C3, and C3a — tags synapses for engulfment by microglia. Beth Stevens and colleagues showed that complement-mediated synaptic pruning, an essential developmental process, is inappropriately reactivated in the aging brain and dramatically so in AD models. Blocking C1q rescues synapse density and cognitive function in mice, and anti-C1q antibodies are entering human trials. This synaptic-pruning mechanism is one of the most direct molecular links between systemic inflammation and cognitive decline.
Imaging of neuroinflammation in living humans is now possible with TSPO PET (translocator protein, an outer mitochondrial membrane protein upregulated in activated microglia). TSPO signal is elevated in mild cognitive impairment, increases over time in AD, and correlates with tau pathology and clinical decline. Plasma GFAP (glial fibrillary acidic protein, an astrocyte intermediate filament) tracks astrocyte reactivity and has joined plasma p-tau217 and NfL as a standard biomarker triplet for early AD and other neurodegenerative diseases. Targeting senescent microglia with senolytics (dasatinib + quercetin, fisetin) is one of the most actively pursued strategies for reversing the neuroinflammatory component of brain aging.
Vascular Contribution and Cerebral Small-Vessel Disease
For most of the past century the vascular contribution to dementia was treated as a separate disease — "multi-infarct dementia" caused by discrete strokes. The modern picture is far more inclusive: cerebral small-vessel disease (cSVD), driven by endothelial dysfunction and chronic hypertension, contributes to the majority of late-life cognitive impairment and synergizes with Alzheimer's pathology in mixed dementia, which is in fact the most common pathological substrate found at autopsy in patients clinically diagnosed with AD.
The hallmark magnetic resonance imaging (MRI) findings of cSVD are white matter hyperintensities (WMH), lacunar infarcts, cerebral microbleeds, enlarged perivascular spaces, and cortical superficial siderosis. WMH burden — quantifiable as a Fazekas score on FLAIR MRI — is one of the strongest imaging predictors of future cognitive decline and stroke. WMH reflects chronic ischemic damage to the deep penetrating arterioles that supply the white matter, with axonal demyelination and gliosis the histological substrate. The Rotterdam, Framingham, and ARIC cohorts have repeatedly demonstrated that midlife hypertension (especially systolic blood pressure in the 50s and 60s) drives WMH expansion measured 20 years later.
Enlarged perivascular spaces (EPVS) in the basal ganglia and centrum semiovale, visible as small cerebrospinal fluid-intensity tubules on T2 magnetic resonance imaging, are now recognized as a marker of impaired glymphatic clearance. They are not benign: high EPVS burden predicts cognitive decline independent of WMH and amyloid load. Cerebral microbleeds (small hemosiderin deposits) reflect either hypertensive arteriolar damage (deep distribution) or cerebral amyloid angiopathy (lobar distribution); the latter is increasingly recognized as a risk factor for amyloid-related imaging abnormalities (ARIA) during anti-amyloid antibody therapy.
Berislav Zlokovic's work has highlighted the role of blood–brain barrier (BBB) breakdown in early aging and AD, demonstrable with dynamic contrast-enhanced magnetic resonance imaging and cerebrospinal fluid/plasma albumin ratios. BBB leakage is detectable in the hippocampus before measurable cognitive change and before amyloid positron emission tomography positivity in some APOE4 carriers, suggesting that vascular dysfunction may sometimes precede protein aggregation. The clinical lever is straightforward: aggressive treatment of midlife and late-life hypertension (the SPRINT MIND trial compared systolic blood pressure targets below 120 mm Hg and below 140 mm Hg: the lower target did not significantly reduce probable dementia, hazard ratio 0.83, 95% CI 0.67–1.04, but did reduce mild cognitive impairment, hazard ratio 0.81), control of diabetes, smoking cessation, regular aerobic exercise to maintain endothelial function, and treatment of atrial fibrillation to prevent embolic infarcts and silent strokes.
Insulin Resistance — "Type 3 Diabetes"
The term "Type 3 diabetes" for Alzheimer's disease, proposed in 2005 by Steen, de la Monte and colleagues, was provocative but biologically apt. The brain expresses insulin receptors densely in the hippocampus, entorhinal cortex, and hypothalamus; central insulin signaling regulates synaptic plasticity, glucose uptake by astrocytes, neuronal survival, and the trafficking of neurotransmitter receptors at the synapse. In AD brain, insulin and insulin-like growth factor 1 signaling are profoundly impaired — insulin receptor expression is reduced, downstream IRS-1 is hyperphosphorylated at inhibitory serine sites, and PI3K/Akt signaling is suppressed. The molecular picture closely parallels that of insulin-resistant skeletal muscle in type 2 diabetes.
One particularly elegant mechanism links peripheral and central insulin resistance through insulin-degrading enzyme (IDE). IDE is a metalloprotease that degrades both insulin and Abeta, and the two substrates compete for the enzyme. Chronic hyperinsulinemia saturates IDE with insulin, slowing Abeta clearance and tilting the brain toward amyloid accumulation. This is one molecular explanation for the epidemiologic finding that type 2 diabetes roughly doubles dementia risk independent of cerebrovascular disease.
The insulin/insulin-like growth factor 1 axis also overlaps with longevity biology in striking ways. Reduced insulin-like growth factor 1 signaling extends lifespan in worms (daf-2), flies (chico), and mice (Igf1r heterozygotes); centenarians more frequently carry insulin-like growth factor 1 receptor variants associated with reduced signaling. The brain-specific lesson is not that insulin-like growth factor 1 should be minimized (low insulin-like growth factor 1 in elderly humans is associated with frailty and worse outcomes) but that the brain needs responsiveness rather than chronic high signaling. Intermittent fasting, exercise, and metformin all sensitize the brain to insulin in animal models and improve cognitive outcomes in humans with prediabetes or type 2 diabetes.
Clinical levers include treating diabetes to hemoglobin A1c (HbA1c) targets that avoid hypoglycemia (severe hypoglycemia itself accelerates cognitive decline), reducing visceral adiposity, intermittent fasting or time-restricted eating (16:8 or 14:10), aerobic exercise (which acutely improves insulin sensitivity for 24–48 hours), resistance training (which improves long-term glycemic control by increasing muscle glucose disposal), and reducing dietary refined carbohydrates. Glucagon-like peptide-1 (GLP-1) receptor agonists have a biological rationale in AD, but in the two phase 3 EVOKE trials oral semaglutide did not slow clinical progression in early Alzheimer's disease (Cummings 2026; see Pharmacological Frontiers).
Epigenetic Clocks Applied to Brain
The discovery in 2013 by Steve Horvath of an epigenetic clock — a weighted sum of DNA methylation at ~353 CpG sites that predicts chronological age across nearly all human tissues with a median error under 4 years — transformed aging research from a phenotype-driven enterprise to a quantitative one. The clock works because DNA methylation drifts in stereotyped patterns across the genome with age, and that drift is largely tissue-independent. In 2020 Shireby and colleagues published a cortical-specific clock, built from 347 DNA methylation sites and trained on human cortex samples, that dramatically outperformed earlier clocks in cortex tissue; the authors suggested that earlier links between predicted methylation age and neurodegenerative conditions might be false positives from clocks not calibrated to brain tissue (Shireby 2020).
Second-generation clocks have moved beyond simply predicting chronological age to predicting biological age and mortality. PhenoAge (Levine et al., 2018) is trained against a composite of nine clinical markers (C-reactive protein (CRP), glucose, albumin, etc.) and predicts mortality, cancer risk, and disability better than the original Horvath clock. GrimAge (Lu et al., 2019) is trained against plasma proteins and smoking pack-years, and predicts time-to-death and time-to-dementia more accurately than any prior clock. DunedinPACE (Belsky et al., 2022) measures the current pace of aging from a single blood draw, calibrated against a longitudinal cohort followed from birth.
The magnetic resonance imaging-based brain age gap uses machine learning on T1-weighted structural magnetic resonance imaging to predict chronological age from gray matter morphology. The residual (predicted minus actual) is the brain age gap; positive values (brain appears older than chronological age) predict accelerated cognitive decline, AD progression, mortality, and a host of psychiatric outcomes. The metric is now routinely included in research-grade neuroimaging pipelines and is starting to appear in commercial direct-to-consumer reports.
The crucial caveat is that epigenetic clocks are biomarkers, not biological mechanisms. Slowing the clock per se is not the goal — reducing the underlying damage that drives clock acceleration is. Interventions documented to slow epigenetic clocks in human trials include caloric restriction (CALERIE trial: DunedinPACE slowed by ~2%), the Fahy et al. growth-hormone/metformin/DHEA combination (TRIIM trial: mean epigenetic age about 1.5 years below baseline after 1 year of treatment, a 2.5-year difference compared with no treatment), and the Mediterranean diet plus exercise (modest GrimAge slowing). Whether these represent true rejuvenation or merely epigenetic correlate change remains a live research question.
Sirtuins, Nicotinamide Adenine Dinucleotide, and Senescence
The seven mammalian sirtuins (SIRT1–7) are nicotinamide adenine dinucleotide-dependent deacylases originally discovered as longevity factors in yeast (Sir2). They sit at the intersection of nutrient sensing, mitochondrial biogenesis, DNA repair, and cellular senescence, and their activity falls with age primarily because of declining nicotinamide adenine dinucleotide availability. David Sinclair's laboratory and many others have shown that restoring nicotinamide adenine dinucleotide via the precursors nicotinamide riboside (NR) and nicotinamide mononucleotide (NMN) reverses aspects of mitochondrial decline, vascular function, and (in some models) cognitive aging in mice.
The age-related fall in tissue nicotinamide adenine dinucleotide has several causes. CD38, an NADase expressed on immune cells and vascular endothelium, increases dramatically with age and consumes nicotinamide adenine dinucleotide at a rate that outpaces synthesis. CD38 inhibitors (78c, apigenin at high doses) raise tissue nicotinamide adenine dinucleotide in rodents. NAMPT, the rate-limiting enzyme of the nicotinamide adenine dinucleotide salvage pathway, declines with age in muscle, liver, and brain. The net effect is that tissue nicotinamide adenine dinucleotide in 60-year-old humans is roughly half that of 30-year-olds, with corresponding decreases in SIRT1 and SIRT3 activity.
One particularly relevant brain-specific nicotinamide adenine dinucleotide pathway involves NMNAT2, a chaperone-like enzyme that synthesizes nicotinamide adenine dinucleotide locally in axons and is essential for axon survival. Loss of NMNAT2 triggers Wallerian degeneration — the active, self-destruction program of distal axons after injury — through activation of the NADase SARM1. SARM1 inhibitors are now in clinical trials for diabetic peripheral neuropathy and chemotherapy-induced neuropathy, and the same pathway is implicated in the axonal pathology of glaucoma, traumatic brain injury, and possibly Alzheimer's. Preserving axonal nicotinamide adenine dinucleotide may be one of the more underappreciated strategies for brain aging.
The human evidence for nicotinamide adenine dinucleotide precursors is mixed. Nicotinamide riboside and nicotinamide mononucleotide reliably raise blood nicotinamide adenine dinucleotide levels (nicotinamide mononucleotide somewhat more efficiently in some studies), and small trials have shown improvements in walking speed, blood pressure, and aerobic capacity in older adults. Larger, longer trials have not yet demonstrated meaningful cognitive benefit. In a 10-week placebo-controlled pilot trial of nicotinamide riboside (raised to 1 g/day) in 20 older adults with mild cognitive impairment, blood nicotinamide adenine dinucleotide rose 2.6-fold and cognition did not change; cerebral blood flow in one brain network fell, a result the authors noted would not have survived correction for multiple comparisons, and nicotinamide riboside was well tolerated (Orr 2024). Practitioners describe nicotinamide adenine dinucleotide precursors as a foundation rather than a magic bullet and combine them with exercise and CD38-inhibiting compounds (apigenin from parsley and chamomile, quercetin).
Lifestyle Interventions With Strongest Evidence
The single intervention with the strongest evidence base for slowing brain aging is aerobic exercise. Erickson and colleagues' landmark 2011 trial published in PNAS randomized 120 older adults to either one year of moderate-intensity aerobic exercise (40-minute walks 3x/week) or stretching control, and demonstrated a 2% increase in hippocampal volume in the exercise arm versus 1.4% decline in controls — effectively reversing two years of normal age-related hippocampal atrophy. The effect was mediated in part by exercise-induced brain-derived neurotrophic factor (BDNF), a master regulator of synaptic plasticity, neurogenesis, and neuronal survival. Subsequent meta-analyses have confirmed that aerobic exercise produces meaningful improvements in executive function, attention, and memory in older adults, and reduces incident dementia by 15–30% in long-term cohorts.
The dose-response relationship favors moderate-to-vigorous aerobic exercise for 150–300 minutes per week, including some interval-style work that produces a clear lactate response (which itself crosses the blood–brain barrier and acts as a neuronal fuel and signaling molecule). Resistance training adds independent benefit through preservation of muscle mass, improved insulin sensitivity, and stimulation of insulin-like growth factor 1 and myokines that cross the BBB. The combination of aerobic and resistance work is superior to either alone in head-to-head trials in older adults with MCI.
The Mediterranean diet and its variant the MIND diet (Mediterranean–DASH Intervention for Neurodegenerative Delay) have the strongest dietary evidence. Morris and colleagues' 2015 development and validation of the MIND diet in Alzheimer's & Dementia found that high adherence was associated with a 53% lower rate of AD (hazard ratio 0.47) over an average of 4.5 years of follow-up in the Rush Memory and Aging Project. The MIND diet emphasizes ten brain-healthy food groups (leafy greens, other vegetables, berries, nuts, beans, whole grains, fish, poultry, olive oil, modest wine) and five to limit (red meat, butter/margarine, cheese, pastries/sweets, fried/fast food). The FINGER trial in Finland and the MIND-China study tested multidomain programmes (in FINGER: diet, exercise, cognitive training and vascular risk monitoring) rather than the MIND diet alone; over 2 years FINGER found a statistically significant benefit on its main cognitive test battery (Ngandu 2015), and MIND-China is described by its investigators as a multimodal intervention study (Wang 2022). The randomized trial of the MIND diet itself, in 604 older adults without cognitive impairment followed for 3 years, found no significant difference in cognition or in brain MRI measures compared with a control diet, with mild calorie restriction in both groups (Barnes 2023).
Sleep architecture is the third pillar. As discussed under glymphatic clearance, slow-wave sleep is when the brain washes itself; chronic short sleep (<6 hours), fragmented sleep, and untreated sleep apnea are all independent dementia risk factors. The fourth pillar is cognitive and social engagement. Sustained intellectual activity (learning a new language, musical instrument, complex hobby) builds "cognitive reserve" — the brain's ability to maintain function despite accumulating pathology. Social isolation, conversely, accelerates cognitive decline and is associated with a 50% higher risk of dementia in meta-analyses. The Lancet Commission lists social isolation among its 14 modifiable risk factors precisely because the effect size is so large and the intervention so straightforward.
Targeted Supplements and Compounds
The supplement landscape for brain aging is enormous and the evidence quality varies dramatically. The compounds with the strongest human data for slowing cognitive decline or modifying meaningful biomarkers are concentrated in a small number of categories: omega-3 fatty acids, B-vitamins for homocysteine, magnesium, lithium, creatine, urolithin A, and methylene blue.
Omega-3 eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA). Docosahexaenoic acid constitutes roughly 30% of the brain's phospholipid fatty acids, particularly enriched in synaptic membranes where it modulates membrane fluidity, ion channel function, and the resolution of neuroinflammation through specialized pro-resolving mediators (resolvins, protectins, maresins). Higher dietary omega-3 intake and higher red blood cell omega-3 indices are associated with slower cognitive decline and lower dementia risk in epidemiological cohorts. Randomized trials are less impressive: the largest (AREDS2, VITAL-COG) showed modest or null effects on cognition in unselected older adults. The probable explanation is that high baseline omega-3 status (from fish-eating populations) blunts the response. APOE4 carriers and individuals with low baseline omega-3 status appear to benefit most. Practitioners commonly use 1–2 g/day of combined eicosapentaenoic acid+docosahexaenoic acid, taken with food, from fish oil or algae; oily fish is the whole-food source.
B12, folate, and B6 for homocysteine. Elevated plasma homocysteine is a strong independent predictor of brain atrophy, white matter hyperintensities, and dementia incidence. The VITACOG trial (Smith et al., Oxford) randomized 271 people over 70 with MCI (homocysteine was not an entry requirement) to high-dose B12 (500 µg), folic acid (800 µg), and B6 (20 mg) versus placebo for two years. Whole-brain atrophy on magnetic resonance imaging was 0.76% a year with the vitamins versus 1.08% with placebo; in participants whose homocysteine was above 13 µmol/L, the atrophy rate was 53% lower with the vitamins (Smith 2010). The benefit was concentrated in the temporal lobe regions vulnerable in AD. Subsequent analyses showed cognitive benefit specifically when omega-3 status was also adequate — suggesting that homocysteine-lowering and omega-3 sufficiency are synergistic. Practitioners who use this approach measure serum B12, holotranscobalamin, methylmalonic acid and homocysteine, and aim for a homocysteine below 9 µmol/L.
Magnesium-L-threonate is a specific magnesium chelate developed by Liu and colleagues that crosses the blood–brain barrier more efficiently than other magnesium forms and raises brain magnesium levels in animal models. A small 2016 trial showed cognitive improvement in older adults with subjective memory complaints. Magnesium is also important for sleep architecture, N-methyl-D-aspartate (NMDA) receptor regulation, and vascular function. Lithium orotate at microdoses (1–5 mg of elemental lithium) is used by some practitioners. The related research looks at lithium in drinking water and at prescription lithium: in Denmark, long-term exposure to more than 15 µg/L of lithium in drinking water was associated with a lower incidence of dementia (Kessing 2017); in Texas, trace lithium in well water was negatively correlated with the rise in Alzheimer's disease death rates (Fajardo 2018); and in a 12-month Brazilian trial in 45 people with amnestic MCI, lithium given at blood levels of 0.25–0.5 mmol/L — not a microdose — was associated with lower cerebrospinal fluid phosphorylated tau and better scores on a cognitive scale and on attention tasks (Forlenza 2011). Mechanism likely involves GSK-3-beta inhibition (which reduces tau hyperphosphorylation) and brain-derived neurotrophic factor induction. Practitioners who use microdoses point out that they are far below the doses used for bipolar disorder and describe them as having a wide safety margin.
Creatine (3–5 g/day) is best known for muscle performance but crosses the BBB modestly and supports brain bioenergetics; meta-analyses show small improvements in working memory and processing speed in older adults and vegetarians. Urolithin A is a gut-microbiome metabolite of ellagitannins from pomegranates and walnuts; it induces mitophagy in muscle and brain in animal models and has shown muscle-function benefit in human trials. Direct cognitive trial data are still preliminary. Methylene blue at low dose (0.5–4 mg/kg, or in the 10–50 mg range for adults) is an old dye and antimalarial with mitochondrial-enhancing and tau-aggregation-inhibiting effects in preclinical models; a 15-month phase 3 trial of its derivative leuco-methylthioninium (LMTM) in 891 people with mild to moderate Alzheimer's disease found no treatment benefit at either dose tested on its co-primary outcomes (Gauthier 2016). The methylene blue injection label carries a boxed warning that it may cause serious or fatal serotonin syndrome when used with serotonergic drugs and opioids, and directs that it not be used together with selective serotonin reuptake inhibitors (SSRIs), serotonin norepinephrine reuptake inhibitors (SNRIs), monoamine oxidase inhibitors (MAOIs) or opioids.
Pharmacological Frontiers
Several prescription compounds are now being repurposed for brain aging and AD prevention, alongside the first generation of disease-modifying anti-amyloid antibodies. The pace of clinical development is unprecedented, and the next decade is likely to redefine what "brain aging" treatment looks like.
Rapamycin and rapalogs. Rapamycin (sirolimus) is the most consistently lifespan-extending intervention across model organisms and the leading candidate small-molecule geroprotector. It works by inhibiting mechanistic target of rapamycin Complex 1 (mTORC1), thereby upregulating autophagy, reducing senescence burden, and improving immune function. In animal models of AD, rapamycin reduces amyloid and tau pathology and preserves cognition. In the 48-week PEARL trial (Moel, Harinath and colleagues, 2025), healthy, normally ageing adults took placebo or 5 mg or 10 mg of rapamycin once a week; adverse and serious adverse events were similar across all groups, and changes in blood biomarkers stayed within normal ranges. Observational cohorts of people taking rapamycin are ongoing. In PEARL, gastrointestinal symptoms were reported more often on rapamycin than on placebo (10 mg: 8; 5 mg: 7; placebo: 4). The U.S. sirolimus label, from daily dosing in the lung disease lymphangioleiomyomatosis, lists mouth sores (stomatitis) and high cholesterol among the most common side effects. The U.S. Food and Drug Administration-approved rapalog everolimus has been studied as an immunomodulator in older adults and produced improved influenza vaccine responses, a marker of immune rejuvenation.
Senolytics. The dasatinib + quercetin combination, developed by James Kirkland's group at Mayo Clinic, selectively kills senescent cells in mouse models and produced measurable reductions in senescent cell markers and improvements in physical function in early human trials. Fisetin, a flavonoid found in strawberries and onions, is a milder senolytic with a benign safety profile and is being tested in older adults at doses of 20 mg/kg administered for 2–3 consecutive days monthly. Senolytic strategies for the brain are particularly attractive because senescent microglia and astrocytes drive a large fraction of neuroinflammation; preclinical work shows that senolytics reduce neuroinflammation and improve cognition in aged and AD-model mice.
Glucagon-like peptide-1 receptor agonists. Semaglutide, liraglutide, and tirzepatide are revolutionizing obesity and diabetes treatment. Oral semaglutide (up to 14 mg once daily) was tested in two phase 3 trials, EVOKE and EVOKE+, as a treatment for people aged 55–85 with amyloid-confirmed mild cognitive impairment or mild dementia due to Alzheimer's disease. The rationale is multifold: glucagon-like peptide-1 receptors are expressed in brain regions affected by AD, glucagon-like peptide-1 signaling improves insulin sensitivity centrally, and glucagon-like peptide-1 reduces neuroinflammation in preclinical models. Early secondary analyses of diabetes trials suggested 30–40% reductions in dementia incidence, though confounding from improved metabolic control complicates interpretation. The results, published in the Lancet in 2026, showed no significant difference from placebo on the main outcome, the Clinical Dementia Rating–Sum of Boxes score (difference −0.08 in EVOKE and 0.10 in EVOKE+), and the investigators concluded that oral semaglutide was not efficacious in slowing clinical progression in early Alzheimer's disease; both trials were stopped because of the negative outcome (Cummings 2026).
Lecanemab and donanemab are the first anti-amyloid antibodies to show clinically meaningful disease modification, with ~25–35% reductions in cognitive decline rate over 18 months in early symptomatic AD. They define a new clinical reality: AD is now a treatable disease in its earliest stages, and the value of early biomarker-based diagnosis (plasma p-tau217, amyloid positron emission tomography (PET)) has correspondingly skyrocketed. ARIA — amyloid-related imaging abnormalities (edema and microhemorrhages) — remains the main safety issue, particularly in APOE4 homozygotes. The clinical implication for prevention is profound: identifying preclinical AD via plasma biomarkers and intervening before symptoms become manifest is now the central focus of the field.
Biomarkers Worth Tracking
The biomarker landscape for brain aging has transformed in the past five years, with plasma assays now approaching the accuracy of cerebrospinal fluid and positron emission tomography for AD-relevant pathology. The currently useful panel for tracking brain aging in research or aggressive personal-medicine contexts includes the following:
Plasma p-tau217 is the single most useful blood biomarker for early Alzheimer's. Commercial blood tests for amyloid and p-tau217 have demonstrated AUCs above 0.90 for distinguishing amyloid-positive from amyloid-negative individuals, and in May 2025 the U.S. Food and Drug Administration (FDA) cleared the first blood test to aid in diagnosing Alzheimer's disease, a plasma p-tau217/beta-amyloid 1-42 ratio for adults aged 55 and older with signs and symptoms of the disease. Plasma p-tau217 rises 15–20 years before symptom onset in autosomal dominant AD and is highly responsive to anti-amyloid therapy. Plasma GFAP tracks astrocyte reactivity and is elevated in preclinical AD, MCI, and a range of other neurodegenerative conditions. Plasma neurofilament light (NfL) reflects axonal injury and is elevated in essentially all neurodegenerative diseases, traumatic brain injury, MS, and stroke; its non-specificity actually makes it useful as a general "brain damage" screen and treatment response marker.
APOE genotype remains the single most important common genetic risk factor for late-onset AD. APOE4 heterozygotes have ~3x AD risk, homozygotes ~12x; APOE2 carriers are protected. APOE4 homozygotes can now be reframed as "stage 0" AD because their lifetime amyloid positron emission tomography conversion approaches 100% by their seventies. Knowledge of APOE status materially changes the calculus for early biomarker screening and lifestyle prioritization. Cognitive composites (the Preclinical Alzheimer Cognitive Composite, PACC; a computerised cognitive test battery; remote cognitive testing platforms) detect subtle decline years before clinical diagnosis. Annual cognitive testing in at-risk individuals is increasingly recommended.
Magnetic resonance imaging volumetry — hippocampal volume, entorhinal cortex thickness, brain age gap — provides a structural correlate of trajectory. Automated MRI volumetry software now provides normative comparisons accessible to clinicians. Quantitative WMH burden (Fazekas score, or volumetric measurement) tracks the vascular contribution to cognitive aging. Sleep tracking via consumer sleep trackers or polysomnography quantifies the duration and quality of slow-wave sleep, and screens for sleep apnea via overnight oximetry or home sleep studies. Practitioners include a single overnight home sleep study in the workup of older adults with subjective cognitive complaints.
Other increasingly used markers include homocysteine (treatable, see B-vitamin discussion), high-sensitivity C-reactive protein (hs-CRP) (systemic inflammation), hemoglobin A1c and fasting insulin (metabolic), omega-3 index, ferritin and transferrin saturation (iron metabolism), and the epigenetic clocks GrimAge or DunedinPACE (available as commercial epigenetic-age tests). The pace of biomarker development is brisk; the field anticipates plasma alpha-synuclein assays, plasma microglial markers, and digital phenotyping from smartphone use entering routine practice within five years.
Practical Synthesis
Practitioners who work on brain aging commonly arrange the options in tiers, with lifestyle foundations first and supplements and medicines added on top. The summary below sets out what the research on this page found and what practitioners use. The lifestyle measures in the first tier are also the cheapest and most accessible, and in practitioners' experience medicines added on top of poor foundations disappoint.
Foundation (free or near-free). The foundation tier is aerobic exercise of 150–300 minutes per week with some intervals, plus resistance training twice weekly; seven to nine hours of sleep opportunity nightly, side-sleeping, regular sleep times, and treatment of sleep apnea; a Mediterranean or MIND-style eating pattern with leafy greens daily, berries several times a week, fish two to three times a week, olive oil as the main fat, and little ultra-processed food or added sugar; and active social and cognitive engagement — learning new things, keeping up relationships, and treatment of depression and hearing loss. The 2024 Lancet Commission lists smoking, alcohol and untreated visual impairment among its 14 modifiable risk factors; practitioners commonly set an alcohol limit of fewer than 7 drinks a week.
Pillar 2 (labs and correction, low-cost). Practitioners in this field test and correct: blood pressure (target below 130/80), low-density lipoprotein cholesterol per current cardiovascular guidelines (with lower generally considered better for the brain), hemoglobin A1c (ideally below 5.7), homocysteine (below 9 µmol/L, using B12, folate and B6), 25-OH vitamin D (40–80 ng/mL), omega-3 index (above 8%), thyroid-stimulating hormone (TSH) and a thyroid panel, B12 with methylmalonic acid, and high-sensitivity C-reactive protein. They also screen for sleep apnea, obstructive uropathy disrupting sleep, and atrial fibrillation; some offer APOE genotyping to people with a family history, and plasma p-tau217 and GFAP to people over 60 with subjective cognitive complaints or a strong family history.
Pillar 3 (targeted compounds, moderate cost). Amounts practitioners use: omega-3 1–2 g/day when dietary intake is low; magnesium-L-threonate 1–2 g at night; vitamin D3 to reach the 25-OH target; a B-complex when homocysteine is high; and creatine 3–5 g/day. Some add lithium orotate microdoses (1–5 mg elemental lithium), spermidine (from wheat germ or a supplement), and nicotinamide adenine dinucleotide precursors (nicotinamide riboside or nicotinamide mononucleotide at 250–500 mg) for people already keeping to the foundations, and urolithin A at 500 mg/day for its effect on mitophagy.
Pillar 4 (prescription medicines). In people with metabolic syndrome or obesity, practitioners regard glucagon-like peptide-1 receptor agonists as possibly brain-protective beyond weight loss. For rapamycin, the safety data on this page come from the PEARL trial: with 5 mg or 10 mg once a week for 48 weeks, adverse and serious adverse events were similar across the placebo and rapamycin groups, and blood biomarker changes stayed within normal ranges (Moel 2025). Some practitioners use senolytic protocols (dasatinib plus quercetin, or fisetin) in periodic courses. Anti-amyloid antibodies (lecanemab, donanemab) are used in biomarker-confirmed early symptomatic AD; ARIA is their main safety issue, particularly in APOE4 homozygotes (see above).
What practitioners count as harmful. Polypharmacy — with anticholinergics (diphenhydramine, oxybutynin, many tricyclics) singled out as particularly damaging — benzodiazepines and Z-drugs for chronic sleep problems, proton pump inhibitors at chronic high doses (which may worsen B12 status), and long-term opioids; heavy alcohol; chronic short sleep; untreated depression; untreated hearing loss; a sedentary lifestyle; and social isolation. On hearing, the ACHIEVE randomized trial of 977 adults aged 70–84 found that a hearing intervention (counselling and hearing aids) did not change 3-year cognitive decline in its primary analysis; a pre-specified sensitivity analysis suggested it might reduce cognitive decline in the older, higher-risk group drawn from a long-running heart study (Lin 2023). Warning signs. Subjective cognitive decline progressing over months, getting lost in familiar places, family concern, repeated medication errors, or any functional decline are the warning signs for which a formal cognitive assessment, magnetic resonance imaging of the brain, and a plasma biomarker panel are done, rather than reassurance.
Key Research Papers
- López-Otín C, Blasco MA, Partridge L, Serrano M, Kroemer G. The hallmarks of aging. Cell. 2013;153(6):1194-1217. — PubMed PMID: 23746838 · doi:10.1016/j.cell.2013.05.039
- López-Otín C, Blasco MA, Partridge L, Serrano M, Kroemer G. Hallmarks of aging: an expanding universe. Cell. 2023;186(2):243-278. — PubMed PMID: 36599349 · doi:10.1016/j.cell.2022.11.001
- Xie L, Kang H, Xu Q, et al. Sleep drives metabolite clearance from the adult brain. Science. 2013;342(6156):373-377. — PubMed PMID: 24136970 · doi:10.1126/science.1241224
- Iliff JJ, Wang M, Liao Y, et al. A paravascular pathway facilitates CSF flow through the brain parenchyma and the clearance of interstitial solutes, including amyloid beta. Sci Transl Med. 2012;4(147):147ra111. — PubMed PMID: 22896675 · doi:10.1126/scitranslmed.3003748
- Sweeney MD, Sagare AP, Zlokovic BV. Blood-brain barrier breakdown in Alzheimer disease and other neurodegenerative disorders. Nat Rev Neurol. 2018;14(3):133-150. — PubMed PMID: 29377008 · doi:10.1038/nrneurol.2017.188
- Horvath S. DNA methylation age of human tissues and cell types. Genome Biol. 2013;14(10):R115. — PubMed PMID: 24138928 · doi:10.1186/gb-2013-14-10-r115
- Lu AT, Quach A, Wilson JG, et al. DNA methylation GrimAge strongly predicts lifespan and healthspan. Aging (Albany NY). 2019;11(2):303-327. — PubMed PMID: 30669119 · doi:10.18632/aging.101684
- Erickson KI, Voss MW, Prakash RS, et al. Exercise training increases size of hippocampus and improves memory. Proc Natl Acad Sci USA. 2011;108(7):3017-3022. — PubMed PMID: 21282661 · doi:10.1073/pnas.1015950108
- Morris MC, Tangney CC, Wang Y, Sacks FM, Bennett DA, Aggarwal NT. MIND diet associated with reduced incidence of Alzheimer's disease. Alzheimers Dement. 2015;11(9):1007-1014. — PubMed PMID: 25681666 · doi:10.1016/j.jalz.2014.11.009
- Mattson MP, Moehl K, Ghena N, Schmaedick M, Cheng A. Intermittent metabolic switching, neuroplasticity and brain health. Nat Rev Neurosci. 2018;19(2):63-80. — PubMed PMID: 29321682 · doi:10.1038/nrn.2017.156
- Smith AD, Smith SM, de Jager CA, et al. Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment: a randomized controlled trial. PLoS One. 2010;5(9):e12244. — PubMed PMID: 20838622 · doi:10.1371/journal.pone.0012244
- de la Monte SM, Wands JR. Alzheimer's disease is type 3 diabetes-evidence reviewed. J Diabetes Sci Technol. 2008;2(6):1101-1113. — PubMed PMID: 19885299 · doi:10.1177/193229680800200619
- Imai S, Guarente L. NAD+ and sirtuins in aging and disease. Trends Cell Biol. 2014;24(8):464-471. — PubMed PMID: 24786309 · doi:10.1016/j.tcb.2014.04.002
- Hou Y, Dan X, Babbar M, et al. Ageing as a risk factor for neurodegenerative disease. Nat Rev Neurol. 2019;15(10):565-581. — PubMed PMID: 31501588 · doi:10.1038/s41582-019-0244-7
- Madeo F, Eisenberg T, Pietrocola F, Kroemer G. Spermidine in health and disease. Science. 2018;359(6374):eaan2788. — PubMed PMID: 29371440 · doi:10.1126/science.aan2788
- Livingston G, Huntley J, Liu KY, et al. Dementia prevention, intervention, and care: 2024 report of the Lancet standing Commission. Lancet. 2024;404(10452):572-628. — PubMed PMID: 39096926 · doi:10.1016/S0140-6736(24)01296-0
- Cummings JL, Atri A, Sano M, et al. Efficacy and safety of oral semaglutide 14 mg (flexible dose) in early-stage symptomatic Alzheimer's disease (evoke and evoke+): two phase 3, randomised, placebo-controlled trials. Lancet. 2026;407(10544):2167-2179. — PubMed PMID: 41865758 · doi:10.1016/S0140-6736(26)00459-9
- SPRINT MIND Investigators for the SPRINT Research Group; Williamson JD, Pajewski NM, Auchus AP, et al. Effect of intensive vs standard blood pressure control on probable dementia: a randomized clinical trial. JAMA. 2019;321(6):553-561. — PubMed PMID: 30688979 · doi:10.1001/jama.2018.21442
- Lin FR, Pike JR, Albert MS, et al. Hearing intervention versus health education control to reduce cognitive decline in older adults with hearing loss in the USA (ACHIEVE): a multicentre, randomised controlled trial. Lancet. 2023;402(10404):786-797. — PubMed PMID: 37478886 · doi:10.1016/S0140-6736(23)01406-X
- Ngandu T, Lehtisalo J, Solomon A, et al. A 2 year multidomain intervention of diet, exercise, cognitive training, and vascular risk monitoring versus control to prevent cognitive decline in at-risk elderly people (FINGER): a randomised controlled trial. Lancet. 2015;385(9984):2255-2263. — PubMed PMID: 25771249 · doi:10.1016/S0140-6736(15)60461-5
- Wang Y, Han X, Zhang X, et al. Health status and risk profiles for brain aging of rural-dwelling older adults: data from the interdisciplinary baseline assessments in MIND-China. Alzheimers Dement (N Y). 2022;8(1):e12254. — PubMed PMID: 35441085 · doi:10.1002/trc2.12254
- Barnes LL, Dhana K, Liu X, et al. Trial of the MIND diet for prevention of cognitive decline in older persons. N Engl J Med. 2023;389(7):602-611. — PubMed PMID: 37466280 · doi:10.1056/NEJMoa2302368
- Shireby GL, Davies JP, Francis PT, et al. Recalibrating the epigenetic clock: implications for assessing biological age in the human cortex. Brain. 2020;143(12):3763-3775. — PubMed PMID: 33300551 · doi:10.1093/brain/awaa334
- Steen E, Terry BM, Rivera EJ, et al. Impaired insulin and insulin-like growth factor expression and signaling mechanisms in Alzheimer's disease—is this type 3 diabetes? J Alzheimers Dis. 2005;7(1):63-80. — PubMed PMID: 15750215 · doi:10.3233/jad-2005-7107
- Moel M, Harinath G, Lee V, Nyquist A, Morgan SL, Isman A, Zalzala S. Influence of rapamycin on safety and healthspan metrics after one year: PEARL trial results. Aging (Albany NY). 2025;17(4):908-936. — PubMed PMID: 40188830 · doi:10.18632/aging.206235
- Gauthier S, Feldman HH, Schneider LS, et al. Efficacy and safety of tau-aggregation inhibitor therapy in patients with mild or moderate Alzheimer's disease: a randomised, controlled, double-blind, parallel-arm, phase 3 trial. Lancet. 2016;388(10062):2873-2884. — PubMed PMID: 27863809 · doi:10.1016/S0140-6736(16)31275-2
- Orr ME, Kotkowski E, Ramirez P, et al. A randomized placebo-controlled trial of nicotinamide riboside in older adults with mild cognitive impairment. Geroscience. 2024;46(1):665-682. — PubMed PMID: 37994989 · doi:10.1007/s11357-023-00999-9
- Kessing LV, Gerds TA, Knudsen NN, et al. Association of lithium in drinking water with the incidence of dementia. JAMA Psychiatry. 2017;74(10):1005-1010. — PubMed PMID: 28832877 · doi:10.1001/jamapsychiatry.2017.2362
- Fajardo VA, Fajardo VA, LeBlanc PJ, MacPherson REK. Examining the relationship between trace lithium in drinking water and the rising rates of age-adjusted Alzheimer's disease mortality in Texas. J Alzheimers Dis. 2018;61(1):425-434. — PubMed PMID: 29103043 · doi:10.3233/JAD-170744
- Forlenza OV, Diniz BS, Radanovic M, Santos FS, Talib LL, Gattaz WF. Disease-modifying properties of long-term lithium treatment for amnestic mild cognitive impairment: randomised controlled trial. Br J Psychiatry. 2011;198(5):351-356. — PubMed PMID: 21525519 · doi:10.1192/bjp.bp.110.080044
- Fahy GM, Brooke RT, Watson JP, et al. Reversal of epigenetic aging and immunosenescent trends in humans. Aging Cell. 2019;18(6):e13028. — PubMed PMID: 31496122 · doi:10.1111/acel.13028
Connections
- All Remedies
- Menin Protein & Brain Aging
- Rapamycin
- Longevity Protocols
- Nicotinamide Adenine Dinucleotide / Nicotinamide Mononucleotide
- Gut–Brain Axis
- Alzheimer's Disease
- Parkinson's Disease
- Vitamin D3
- Vitamin B12
- Vitamin E
- Magnesium
- Zinc
- Selenium
- Berberine
- Morley Robbins
- Homocysteine
- Blackburn, Greider & Szostak — telomeres, telomerase, and what telomere length does and does not tell you