Peppermint for Irritable Bowel Syndrome (IBS) & Digestive Health
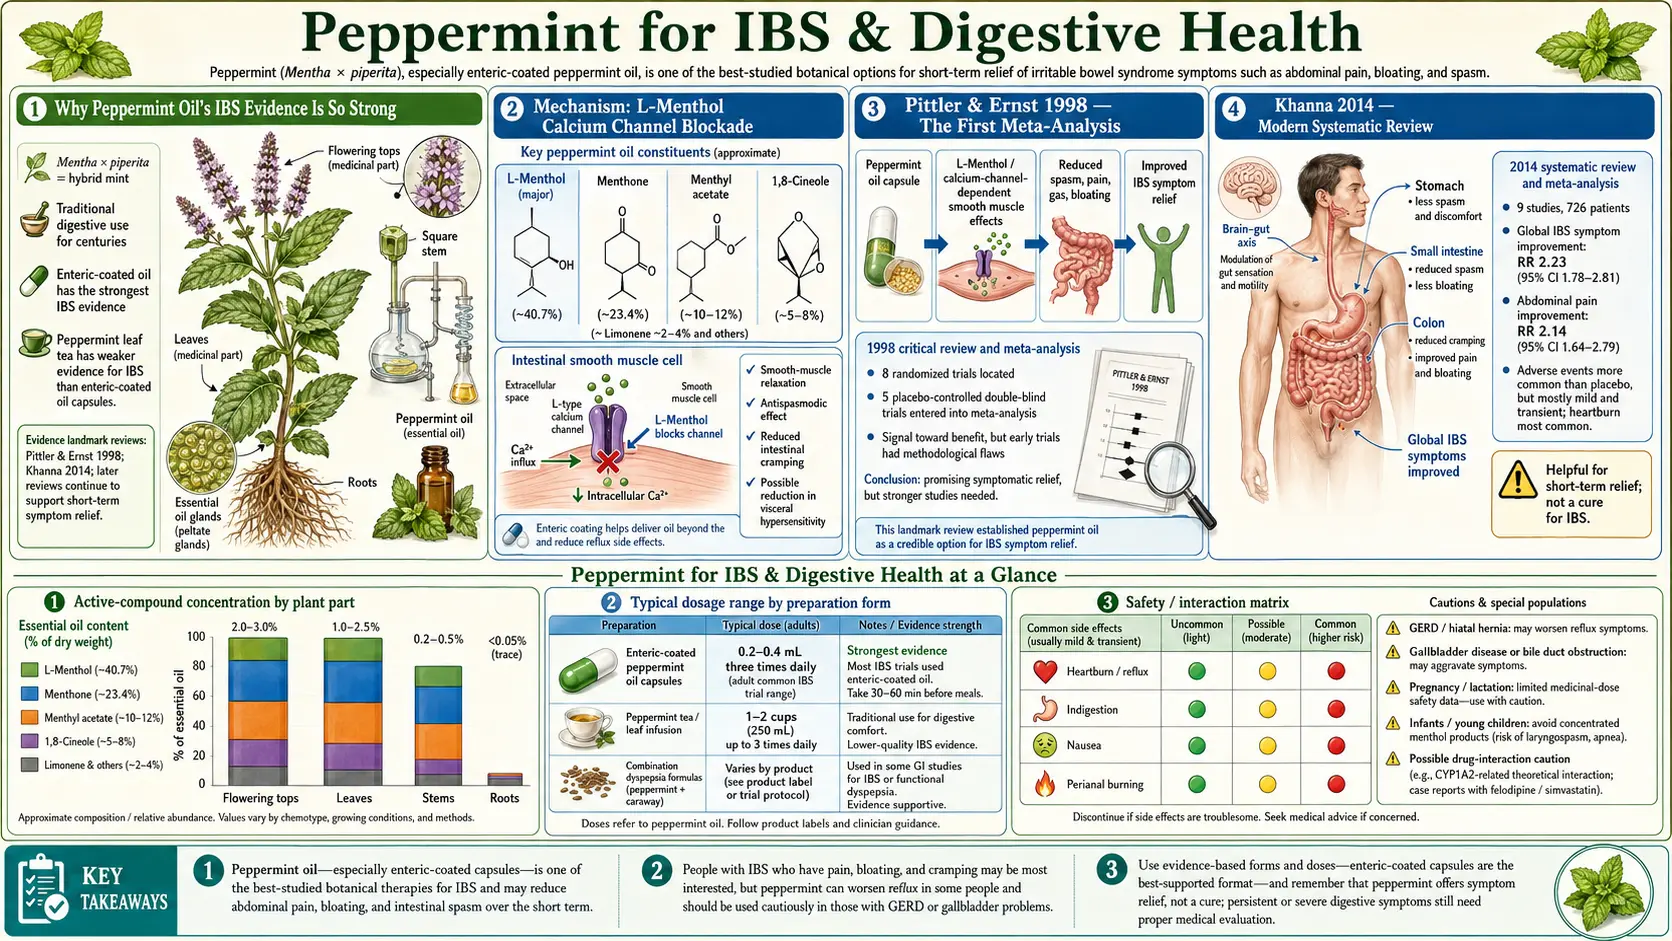
Enteric-coated peppermint oil for irritable bowel syndrome has produced some of the strongest randomized-trial evidence of any botanical preparation in any indication. The Khanna 2014 systematic review (9 trials, 726 patients) found peppermint oil significantly better than placebo, and the Alammar 2019 meta-analysis (12 trials, 835 patients) reported a number needed to treat of 3 for global irritable bowel syndrome (IBS) symptoms. A 2026 review of international guidelines lists peppermint oil as a first-line option in the 2021 American College of Gastroenterology guideline, the 2021 British Society of Gastroenterology guideline and the 2022 United European Gastroenterology and European Society for Neurogastroenterology and Motility guideline for diarrhea-predominant irritable bowel syndrome — in each case as a conditional or weak recommendation based on low- or very-low-quality evidence. The mechanism is precise and well-mapped: L-menthol blocks voltage-gated L-type calcium channels in intestinal smooth muscle, producing antispasmodic relaxation that reduces the visceral hypersensitivity and motility disturbances at the core of irritable bowel syndrome pathophysiology. This page walks through the mechanism, the pivotal trials, the formulation differences (regular enteric coating vs sustained-release microsphere capsules), the doses used in trials, the functional dyspepsia and small intestinal bacterial overgrowth (SIBO) crossover applications, and the critical gastroesophageal reflux disease (GERD) caution.
Table of Contents
- Why Peppermint Oil's Irritable Bowel Syndrome Evidence Is So Strong
- Mechanism: L-Menthol Calcium Channel Blockade
- Pittler & Ernst 1998 — The First Meta-Analysis
- Khanna 2014 — Modern Systematic Review
- Alammar 2019 — Pooled Meta-Analysis
- Sustained-Release Microsphere Capsules
- Doses Used in the Trials
- Functional Dyspepsia and Herbal Combinations
- Small Intestinal Bacterial Overgrowth and Herbal Antimicrobial Regimens
- Pre-Endoscopy Antispasmodic Use
- Gastroesophageal Reflux Disease — The Critical Caution
- Key Research Papers
- Connections
- Featured Videos
Why Peppermint Oil's Irritable Bowel Syndrome Evidence Is So Strong
It is genuinely unusual for a botanical preparation to accumulate the strength of evidence that enteric-coated peppermint oil has accumulated for irritable bowel syndrome. Most herbal interventions have, at best, a handful of small single-center trials with mixed results and minimal blinding. Peppermint oil for irritable bowel syndrome has, by contrast:
- More than a dozen well-conducted double-blind, placebo-controlled randomized trials spanning four decades and multiple continents
- Multiple independent meta-analyses (Pittler 1998, Ford 2008, Khanna 2014, Alammar 2019) consistently reporting clinically meaningful effect sizes
- A number needed to treat of approximately 3 for symptom improvement — comparable to or better than tricyclic antidepressants, selective serotonin reuptake inhibitors, and antispasmodics
- A first-line listing in the 2021 American College of Gastroenterology guideline, the 2021 British Society of Gastroenterology guideline and the 2022 United European Gastroenterology and European Society for Neurogastroenterology and Motility guideline for diarrhea-predominant irritable bowel syndrome, as summarised in a 2026 review of international guidelines (each a conditional or weak recommendation based on low- or very-low-quality evidence)
- A coherent and well-documented mechanism (L-type calcium channel blockade in intestinal smooth muscle) that maps directly onto the symptoms it improves (pain, cramping, bloating)
- An excellent safety profile when delivered via enteric coating — the dominant adverse effect is a small increase in heartburn risk, which is a known and predictable consequence of its relaxing effect on the lower esophageal sphincter
For comparison, the herbal interventions with similar evidence depth in other indications — St. John's Wort for mild-to-moderate depression, saw palmetto for benign prostatic hyperplasia, and Ginkgo biloba for vascular cognitive symptoms — all have produced more recent large-trial findings that complicated or contradicted the earlier positive findings. Peppermint oil's irritable bowel syndrome evidence base has actually strengthened over time as more trials have been completed.
Mechanism: L-Menthol Calcium Channel Blockade
The main mechanism of peppermint oil in irritable bowel syndrome is the same as that of the calcium-channel-blocking antispasmodic drugs otilonium and pinaverium, but produced by a natural product rather than a synthesized drug. (Other antispasmodic drugs, such as hyoscine and dicyclomine, work differently: they block the nerve messenger acetylcholine, and are called antimuscarinics.) L-menthol — the dominant constituent of peppermint essential oil at 35-55% by weight — blocks voltage-gated L-type calcium channels in intestinal smooth muscle. The result is reduced calcium influx during depolarization, reduced calcium-calmodulin activation of myosin light chain kinase, and reduced smooth muscle contraction.
This is the same fundamental mechanism as the dihydropyridine calcium-channel-blocker drug class (nifedipine, amlodipine, felodipine) used systemically for hypertension. The clinical difference is delivery: peppermint oil delivered via enteric-coated capsule releases its menthol in the small intestine and colon, where the absorption is local and the systemic concentrations remain low. The effect is therefore concentrated where it is wanted (gut smooth muscle) rather than affecting cardiac and vascular smooth muscle as systemic calcium channel blockers do.
Three additional mechanisms contribute:
- 5-HT3 receptor antagonism — menthol partially blocks 5-HT3 serotonin receptors on enteric sensory neurons, the same receptor target as the diarrhea-predominant irritable bowel syndrome (IBS-D) drug alosetron. This reduces visceral hypersensitivity (the abnormal pain response to normal gut distension that is a hallmark of irritable bowel syndrome).
- TRPM8 cold-receptor activation — menthol activates TRPM8 receptors on enteric afferents, which can produce a counter-irritant effect that crowds out competing visceral pain signaling.
- Anti-inflammatory effects — peppermint oil reduces production of pro-inflammatory cytokines (tumor necrosis factor-alpha, IL-1beta) in intestinal tissue, addressing the low-grade mucosal inflammation that contributes to a subset of irritable bowel syndrome cases.
The composite effect is reduced cramping pain, reduced bloating from improved transit, reduced urgency, and reduced visceral hypersensitivity — addressing the four symptom domains that dominate the irritable bowel syndrome clinical picture.
Pittler & Ernst 1998 — The First Meta-Analysis
The first systematic review and meta-analysis of peppermint oil for irritable bowel syndrome was published in 1998 by Max Pittler and Edzard Ernst at the University of Exeter Complementary Medicine unit. The authors pooled five double-blind, placebo-controlled randomized trials (197 total patients) of enteric-coated peppermint oil capsules and reported a statistically significant benefit on global irritable bowel syndrome symptoms with an odds ratio of approximately 2.7 favoring peppermint over placebo.
The authors themselves were cautious. They located eight randomized trials and pooled five, and wrote that “in view of the methodological flaws associated with most studies, no definitive judgment about efficacy can be given.” Their conclusion was that “the role of peppermint oil in the symptomatic treatment of IBS has so far not been established beyond reasonable doubt,” and they called for well-designed studies.
Further trials followed over the next two decades, and the later meta-analyses (Khanna 2014, Alammar 2019) pooled them and reported a significant benefit over placebo.
Khanna 2014 — Modern Systematic Review
Reshma Khanna and colleagues at the University of Western Ontario published an updated systematic review and meta-analysis in 2014, pooling nine randomized placebo-controlled trials with a total of 726 irritable bowel syndrome patients. The headline findings:
- Global irritable bowel syndrome symptom improvement: relative risk of improvement 2.23 (95% confidence interval (CI) 1.78-2.81) favoring peppermint over placebo
- Abdominal pain reduction: relative risk 2.14 (95% confidence interval 1.64-2.79) favoring peppermint
- People taking peppermint oil were significantly more likely to report an adverse event, but the events were mild and short-lived; heartburn was the most common
The authors concluded that peppermint oil is “a safe and effective short-term treatment for IBS,” and called for studies of its long-term efficacy and safety and of how it compares with other irritable bowel syndrome treatments.
For context, the number needed to treat of about 3 reported in the Alammar 2019 meta-analysis (below) compares favorably with most pharmaceutical irritable bowel syndrome therapies. Tricyclic antidepressants for irritable bowel syndrome have an NNT of approximately 4. Selective serotonin reuptake inhibitors have an NNT of approximately 4. The constipation-predominant irritable bowel syndrome (IBS-C) drug linaclotide has an NNT of approximately 7. The diarrhea-predominant irritable bowel syndrome drug rifaximin has an NNT of approximately 9. Peppermint oil's effect size is therefore in the upper tier of available irritable bowel syndrome interventions on average, and substantially exceeds placebo response by clinically meaningful margins.
Alammar 2019 — Pooled Meta-Analysis
The 2019 meta-analysis by Nour Alammar and colleagues at the Johns Hopkins University School of Medicine pooled 12 randomized placebo-controlled trials with 835 total irritable bowel syndrome patients — the largest meta-analysis to date. Key findings:
- Improvement in global irritable bowel syndrome symptoms: relative risk 2.39 (95% confidence interval 1.93-2.97) favoring peppermint
- Reduction in abdominal pain: relative risk 1.78 (95% confidence interval 1.43-2.20) favoring peppermint
- Both effects were statistically significant with no measured heterogeneity (I² = 0%), meaning the trials produced consistent results despite methodological variation
- Number needed to treat: 3 for global symptoms and 4 for abdominal pain
- Reported adverse effects did not differ significantly from placebo (9.3% vs 6.1%; relative risk 1.40, 95% confidence interval 0.87-2.26)
The authors described it as the most comprehensive meta-analysis to date and concluded that peppermint oil “was shown to be a safe and effective therapy for pain and global symptoms in adults with IBS.”
For more on the irritable bowel syndrome condition and the full menu of evidence-based treatment options, see our Irritable Bowel Syndrome page.
Sustained-Release Microsphere Capsules
One proprietary product is a sustained-release (triple-coated microsphere) peppermint oil capsule, designed to release the oil gradually in the small intestine rather than all at once like traditional enteric-coated capsules. In its trial, each capsule held 90 mg of peppermint oil in small triple-coated beads less than 1.5 mm across, and the dose was two capsules (180 mg) three times daily.
The clinical rationale is that traditional enteric-coated capsules release their full payload at a single point when the enteric coating dissolves at small-bowel pH, producing a high local concentration at one location and limited exposure elsewhere along the gut. The microsphere approach spreads the dose across the full length of the small intestine and into the proximal colon, producing more uniform smooth-muscle exposure.
The IBSREST randomized controlled trial (Cash et al. 2016) of this capsule in 72 people with mixed-type (IBS-M) or diarrhea-predominant (IBS-D) irritable bowel syndrome reported a 40% reduction in the Total IBS Symptom Score over 4 weeks, compared to a 24.3% reduction with placebo; the difference was already significant at 24 hours (19.6% vs 10.3%). The trial tested this one product rather than ordinary enteric-coated peppermint oil, and one of its three authors worked for the product's maker.
The sustained-release microsphere capsule is usually more expensive than ordinary enteric-coated peppermint oil capsules. Ordinary enteric-coated capsules are substantially cheaper and make up most of the trials in the meta-analyses above.
Doses Used in the Trials
Doses used across the trial literature:
- Generic enteric-coated peppermint oil: 0.2 mL (approximately 180 mg) per capsule, taken 1 capsule three times daily, 30-60 minutes before meals
- Sustained-release microsphere capsules: the IBSREST trial used 2 capsules (180 mg) three times daily, 30-90 minutes before meals
- Trial duration: Typical trials run 4-12 weeks. The clinical benefit is generally apparent within 1-2 weeks if it is going to occur. There is little trial information on use beyond 12 weeks.
- Timing relative to meals: Pre-meal dosing (30-60 minutes before) is the standard. Some practitioners suggest morning dosing for constipation-predominant irritable bowel syndrome and evening dosing for diarrhea-predominant irritable bowel syndrome, but the trial evidence supports the three-times-daily before-meals approach
- Reassessment point: The trials measured their results at 4-12 weeks, so they say little about people who have had no meaningful improvement by then.
Enteric-coated capsules are made to be swallowed whole — not chewed, crushed, or opened — because the enteric coating is what prevents upper-GI release that would produce heartburn and burping of peppermint flavor. Patients who chew the capsules or who use uncoated peppermint oil preparations typically experience uncomfortable upper-GI symptoms within minutes and discontinue.
Functional Dyspepsia and Herbal Combinations
Functional dyspepsia — chronic upper-GI discomfort, bloating, postprandial fullness, and early satiety without identifiable structural disease — shares many mechanistic features with irritable bowel syndrome, and peppermint has been studied as a treatment with positive results.
The most-studied combination product is a nine-herb liquid preparation (STW 5) from Germany, containing peppermint, caraway, chamomile, licorice root, milk thistle, lemon balm, angelica root, celandine, and bitter candytuft. It has more than two decades of clinical trial evidence in functional dyspepsia, with multiple randomized controlled trials (RCTs) showing meaningful symptom reduction. It is widely used in Germany and is available in the US as a dietary supplement. A related six-herb version (STW 5-II: bitter candytuft, chamomile flower, peppermint leaves, caraway, licorice root and lemon balm) was tested in a 2004 trial of 120 patients (Madisch et al.): after 8 weeks, 43.3% on the herbal preparation and 3.3% on placebo reported complete relief of symptoms.
For peppermint specifically (separate from the broader nine-herb preparation), the most-cited combination is peppermint oil + caraway oil. In a 2000 trial of 96 people with functional dyspepsia (May et al.), enteric-coated capsules of 90 mg peppermint oil and 50 mg caraway oil taken twice daily for 28 days reduced pain intensity by 40%, against 22% on placebo, and pressure, heaviness and fullness by 43% against 22%. In a 1999 head-to-head trial of 120 patients (Madisch et al.), the same peppermint-caraway oil combination reduced pain scores as much as the prokinetic drug cisapride (4.62 vs 4.60 points) — a drug since withdrawn from most markets.
The mechanism overlaps with irritable bowel syndrome: peppermint relaxes gastric smooth muscle and reduces postprandial spasm, while caraway adds carminative effects (reduces gas formation and bloating) and additional antispasmodic action.
For a comprehensive review of fennel, another carminative herb often used in similar functional gastrointestinal (GI) applications, see our Fennel page.
Small Intestinal Bacterial Overgrowth and Herbal Antimicrobial Regimens
Small intestinal bacterial overgrowth (SIBO) treatment protocols commonly include peppermint oil as one component of broader herbal antimicrobial regimens. Peppermint oil has documented antimicrobial activity against many of the bacterial species implicated in small intestinal bacterial overgrowth — E. coli, Klebsiella, Enterococcus, methanogenic archaea — in laboratory studies.
The Chedid et al. 2014 small intestinal bacterial overgrowth study at Johns Hopkins — a retrospective chart review rather than a randomized trial — compared herbal antimicrobial products (containing herbs such as thyme oil, oregano oil and berberine, but no peppermint) with the pharmaceutical antibiotic rifaximin in 104 small intestinal bacterial overgrowth patients. Breath tests turned negative in 46% on the herbal products and 34% on rifaximin, a difference that was not statistically significant (P=.24). Because no peppermint was used, this study does not test peppermint itself.
In standard integrative small intestinal bacterial overgrowth protocols, peppermint oil is typically used alongside oregano oil, berberine, allicin (garlic-derived), and neem — a combination intended to address the broader spectrum of small intestinal bacterial overgrowth bacteria including the methane-producing archaea that often resist single-agent therapy. The dual benefit of peppermint in this context is the antimicrobial action plus the antispasmodic relief of the cramping and bloating symptoms that small intestinal bacterial overgrowth produces.
For detailed small intestinal bacterial overgrowth management including the herbal-antimicrobial protocols, see our small intestinal bacterial overgrowth page and the deep-dive sub-article on herbal antimicrobials.
Pre-Endoscopy Antispasmodic Use
A less-publicized application of peppermint oil is as an antispasmodic during gut examinations. Placed directly inside the gut, peppermint oil has been reported to be a safe and useful antispasmodic for gastroscopy, colonoscopy and barium-enema X-rays.
In the Mizuno 2006 study in Japan, 205 people swallowed peppermint oil mixed with barium before an upper-gut barium X-ray (double-contrast barium meal) and were compared with 215 matched controls: spasm of the esophagus, lower stomach and duodenal bulb was significantly lower and the X-ray quality higher. In the Asao 2003 study of 383 barium-enema X-rays, peppermint oil mixed into the barium relaxed colonic spasm as well as an injection of the antispasmodic drug hyoscine butylbromide, and better in the caecum and ascending colon; the number of polyps found did not differ between the groups. The Inoue 2014 randomized trial of 226 colonoscopies found that L-menthol (the main compound in peppermint oil) sprayed onto the lining of the colon raised the adenoma (precancerous polyp) detection rate to 60.2%, against 42.6% with placebo, and left 71.2% of patients with no bowel contractions against 30.9%.
These procedure studies are not home treatments, but they show the antispasmodic effect in a setting (X-ray or real-time endoscopic observation) where it can be seen directly rather than inferred from symptom reports.
Gastroesophageal Reflux Disease — The Critical Caution
The most important practical caution for peppermint oil in irritable bowel syndrome is its effect on the lower esophageal sphincter (LES). The same smooth-muscle calcium-channel blockade that produces antispasmodic relief in the gut also reduces resting LES tone — the muscular ring that prevents stomach acid from refluxing into the esophagus. In patients with gastroesophageal reflux disease, hiatal hernia, or symptomatic acid reflux, peppermint can worsen symptoms substantially.
This is the most common scenario in which peppermint goes from helpful to harmful. Many irritable bowel syndrome patients also have overlapping gastroesophageal reflux disease — both involve visceral hypersensitivity and autonomic dysregulation, and the conditions co-occur much more often than chance. A patient who starts peppermint oil capsules for irritable bowel syndrome symptoms and develops worsening heartburn within 1-2 weeks is experiencing a predictable mechanism-based adverse effect, not an idiosyncratic reaction.
What the research describes:
- Reflux, hiatal hernia and active heartburn. People with gastroesophageal reflux disease, hiatal hernia, or active reflux symptoms are the group in whom peppermint most often worsens heartburn, whatever the severity of their irritable bowel syndrome.
- Enteric coating reduces but does not eliminate the LES effect. Absorbed menthol still circulates systemically.
- Heartburn that begins after starting peppermint is the typical sign of this effect. It usually appears within the first 1-2 weeks. Ongoing acid reflux can inflame the esophagus (esophagitis) over time.
- Approaches that do not relax the lower esophageal sphincter. For people with both reflux and irritable bowel syndrome, other approaches in use include ginger, fennel, soluble fiber (psyllium husk), low-FODMAP dietary management, and pharmaceutical antispasmodics that do not cross the blood-brain barrier or affect smooth muscle outside the gut wall.
The other significant cautions are: gallstones (peppermint increases bile flow and can precipitate biliary colic), infants and very young children under 2-5 years (menthol exposure is associated with rare cases of laryngospasm), and pregnancy (moderate dietary peppermint is common in food; high-dose essential oil supplements have no established safety record in pregnancy).
Key Research Papers
- Pittler MH, Ernst E (1998). Peppermint oil for irritable bowel syndrome: a critical review and meta-analysis. American Journal of Gastroenterology. — PubMed PMID: 9672344
- Ford AC et al. (2008). Effect of fibre, antispasmodics, and peppermint oil in the treatment of irritable bowel syndrome: systematic review and meta-analysis. BMJ. — PubMed PMID: 19008265
- Khanna R, MacDonald JK, Levesque BG (2014). Peppermint oil for the treatment of irritable bowel syndrome: a systematic review and meta-analysis. Journal of Clinical Gastroenterology. — PubMed PMID: 24100754
- Cash BD et al. (2016). A novel delivery system of peppermint oil is an effective therapy for irritable bowel syndrome symptoms (IBSREST trial). Digestive Diseases and Sciences. — PubMed PMID: 26319955
- Alammar N et al. (2019). The impact of peppermint oil on the irritable bowel syndrome: a meta-analysis of the pooled clinical data. BMC Complementary and Alternative Medicine. — PubMed PMID: 30654773
- Hawthorn M et al. (1988). The actions of peppermint oil and menthol on calcium channel-dependent processes in intestinal, neuronal and cardiac preparations. Alimentary Pharmacology & Therapeutics. — PubMed PMID: 2856502
- Chedid V et al. (2014). Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine. — PubMed PMID: 24891990
- Lacy BE et al. (2021). ACG Clinical Guideline: Management of Irritable Bowel Syndrome. American Journal of Gastroenterology. — PubMed PMID: 33315591
- Madisch A, Holtmann G, Mayr G, Vinson B, Hotz J (2004). Treatment of functional dyspepsia with a herbal preparation. A double-blind, randomized, placebo-controlled, multicenter trial (six-herb preparation STW 5-II). Digestion 69(1):45-52. — PubMed PMID: 14755152
- May B, Köhler S, Schneider B (2000). Efficacy and tolerability of a fixed combination of peppermint oil and caraway oil in patients suffering from functional dyspepsia. Alimentary Pharmacology & Therapeutics 14(12):1671-1677. — PubMed PMID: 11121917
- Madisch A, Heydenreich CJ, Wieland V, Hufnagel R, Hotz J (1999). Treatment of functional dyspepsia with a fixed peppermint oil and caraway oil combination preparation as compared to cisapride. A multicenter, reference-controlled double-blind equivalence study. Arzneimittelforschung 49(11):925-932. — PubMed PMID: 10604046
- Inoue K et al. (2014). L-menthol improves adenoma detection rate during colonoscopy: a randomized trial. Endoscopy 46(3):196-202. — PubMed PMID: 24573731
- Asao T, Kuwano H, Ide M, Hirayama I, Nakamura JI, Fujita KI, Horiuti R (2003). Spasmolytic effect of peppermint oil in barium during double-contrast barium enema compared with Buscopan. Clinical Radiology 58(4):301-305. — PubMed PMID: 12662951
- Mizuno S et al. (2006). Oral peppermint oil is a useful antispasmodic for double-contrast barium meal examination. Journal of Gastroenterology and Hepatology 21(8):1297-1301. — PubMed PMID: 16872313
- Pastras P, Aggeletopoulou I, Bali M, Triantos C (2026). Plant-Derived Treatments for IBS: Clinical Outcomes, Mechanistic Insights, and Their Position in International Guidelines. Nutrients 18(2). — PubMed PMID: 41599795
PubMed Topic Searches
Connections
- All Herbs
- Peppermint Overview
- Peppermint Benefits Hub
- Peppermint for Headache
- Peppermint for Respiratory
- Peppermint for Cognitive
- Irritable Bowel Syndrome
- Small Intestinal Bacterial Overgrowth
- Herbal Antimicrobials (Small Intestinal Bacterial Overgrowth)
- Low-FODMAP Diet
- Bloating
- Abdominal Pain
- Reflux and Heartburn
- Ginger
- Fennel
- Chamomile
- Gut Healing
- History