Peppermint for Respiratory & Cough
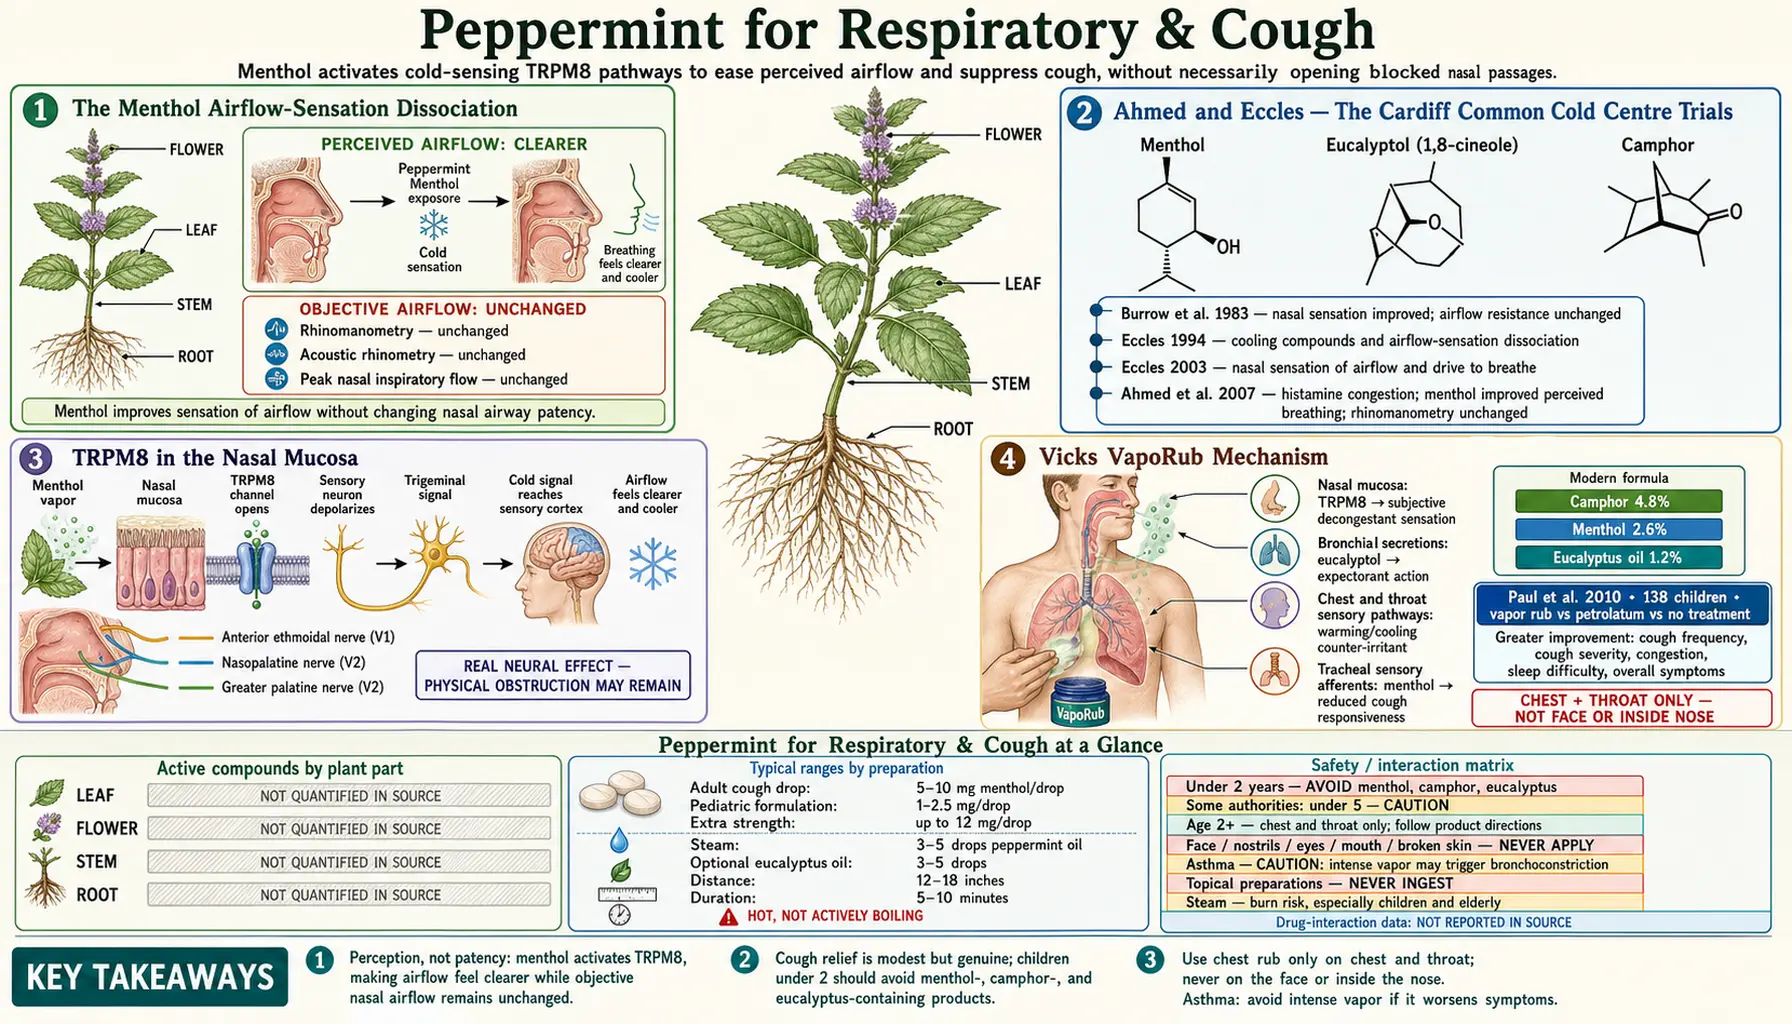
Peppermint and its dominant constituent menthol are the active components of essentially every over-the-counter decongestant rub, cough drop, and steam-inhalation preparation sold globally. The mechanism is paradoxical and instructive: menthol activates the TRPM8 cold-sensing receptor on intranasal sensory neurons, producing a subjective sensation of clearer airflow without actually changing the cross-sectional area of the nasal passages or the objective resistance to airflow. Ronald Eccles and colleagues in Cardiff reported this dissociation in 1983: after five minutes of camphor, eucalyptus or menthol vapour, most people felt a cold sensation and easier airflow in the nose while their measured nasal resistance to airflow did not change. A 2008 study in 42 schoolchildren likewise found no change in measured nasal airflow but a clear rise in how open the nose felt. This sounds like a placebo, but it is not — the cold receptor activation produces a genuine afferent signal that the brain interprets as "clear air," and the symptomatic relief is real and reproducible even when the physical obstruction is unchanged. Combined with menthol's antitussive (cough-suppressant) activity — which a 2013 guinea-pig study traced to TRPM8 cold-sensing nerves in the nose rather than in the windpipe — this explains the dominance of menthol-based preparations in over-the-counter (OTC) respiratory care. This page covers the Cardiff dissociation studies, how camphor-menthol-eucalyptus vapor rubs work, traditional steam inhalation, antitussive activity, and the safety findings on menthol use in infants and very young children.
Table of Contents
- The Menthol Airflow-Sensation Dissociation
- Eccles and Colleagues — The Cardiff Menthol Studies
- TRPM8 in the Nasal Mucosa
- How Camphor-Menthol-Eucalyptus Vapor Rubs Work
- Traditional Steam Inhalation
- Antitussive (Cough Suppression) Activity
- Chest Rubs and Pediatric Use
- Cough Drops and Lozenges
- Combination with Eucalyptus and Camphor
- Asthma and Bronchospasm Considerations
- Critical Infant and Young Child Safety
- Key Research Papers
- Connections
- Featured Videos
The Menthol Airflow-Sensation Dissociation
The single most important fact about menthol in respiratory care is that it makes nasal congestion feel better without actually opening the airway. This dissociation between subjective relief and objective airflow has been documented repeatedly across multiple research groups using multiple measurement modalities — rhinomanometry (direct measurement of nasal airflow resistance), acoustic rhinometry (sound-wave measurement of nasal cross-sectional area), and peak nasal inspiratory flow.
The pattern is consistent:
- Patients with naturally occurring or experimentally induced nasal congestion report a clear, immediate, dose-dependent improvement in their sense of nasal airflow after menthol exposure (inhaled vapor, nasal stick, peppermint candy)
- Simultaneous objective measurement of the same patients' nasal airflow shows no change — rhinomanometry remains unchanged, the nasal cavity cross-section remains unchanged, and the actual volume of air moving through the nose per unit time does not increase
- The subjective effect is real (it is not a placebo by the strict definition — it is a real neural effect that is reproducible and dose-dependent) but the objective effect is absent
- Patients prefer menthol-treated air to plain air at indistinguishable physical concentrations, and rate the menthol-treated air as "easier to breathe"
This is the central finding that distinguishes menthol from actual nasal decongestants like pseudoephedrine or oxymetazoline, which work by alpha-1 adrenergic vasoconstriction of nasal mucosal vasculature, physically reducing the swelling and opening the airway. Pseudoephedrine produces both subjective relief and measurable objective improvement in nasal airflow. Menthol produces only subjective relief.
From the patient's perspective, this distinction may not matter much — the symptomatic relief is what they want, and menthol provides it. But the distinction matters for understanding what menthol can and cannot do. Menthol cannot resolve a structural problem like a deviated septum, severe polyposis, or significant mucosal swelling from a sinus infection. It can make any of those feel less bothersome through its central cold-signal effect, but it cannot fix the underlying obstruction.
Eccles and Colleagues — The Cardiff Menthol Studies
Ronald Eccles and his group at the Common Cold Centre, Cardiff University, have published much of the mechanistic work on menthol in respiratory symptoms. The key papers:
- Eccles R (1994), "Menthol and related cooling compounds." A broad review of menthol's production, chemistry, pharmacology and toxicology, including its actions on the nose and on breathing reflexes. It predates the identification of the cold-and-menthol receptor TRPM8, which McKemy, Neuhausser and Julius reported in 2002.
- Eccles R (2003), "Menthol: effects on nasal sensation of airflow and the drive to breathe." A review of the mechanisms behind menthol's use for nasal congestion and of its effects on the drive to breathe and on breathlessness, written after the menthol receptor had been found.
- Burrow A, Eccles R, Jones AS (1983): five minutes of camphor, eucalyptus or menthol vapour had no effect on measured nasal resistance to airflow, but most subjects reported a cold sensation in the nose with a sensation of improved airflow. Exercise did the reverse — it lowered nasal resistance without any sensation of cold or improved airflow.
The Cardiff group has also done substantial work on menthol's effects on cough reflex sensitivity (next section), bronchodilation, and the role of the trigeminal nerve in respiratory sensation. The unifying theme of this body of work is that the sense of breathing is generated centrally from a complex of inputs — chemoreceptors monitoring blood gases, mechanoreceptors in the chest wall, and intranasal/intratracheal sensory neurons — and modifying any one of those inputs (in menthol's case, the intranasal TRPM8-positive neurons) can shift the subjective experience without changing the underlying physiology.
TRPM8 in the Nasal Mucosa
The molecular target for menthol in the nasal cavity is the same TRPM8 (transient receptor potential cation channel subfamily M member 8) that mediates the cooling sensation on skin. TRPM8 is expressed on a subset of trigeminal sensory neurons that innervate the nasal mucosa — specifically the branches of:
- The anterior ethmoidal nerve (a branch of V1 ophthalmic), supplying the anterior superior nasal mucosa
- The nasopalatine nerve (a branch of V2 maxillary), supplying the nasal septum
- The greater palatine nerve (V2), supplying portions of the lateral nasal wall
When menthol vapor reaches these neurons (either through inhalation of menthol-containing air or through topical contact via nasal sticks and rubs), TRPM8 channels open, the neurons depolarize, and the trigeminal sensory cortex receives a signal interpreted as cold. The brain's integration of this cold signal with the existing breath sensation produces the perception of clearer, cooler, more refreshing airflow.
This is the same fundamental mechanism as menthol's effect on skin cooling, oral cavity cooling (mint candy, toothpaste), and the topical headache relief discussed on our Headache Relief page. The receptor is the same; the location is different; the perceptual outcome is different.
How Camphor-Menthol-Eucalyptus Vapor Rubs Work
The petroleum-jelly-based camphor-menthol-eucalyptus chest rub is the prototypical menthol-based respiratory remedy. The active ingredients listed on current U.S. labels:
- Camphor 4.8% — TRPM8 activator (cooling) and TRPV1 activator (warming), plus mild local anesthetic effects
- Menthol 2.6% — the primary TRPM8 activator and the source of the characteristic cooling/airflow sensation
- Eucalyptus oil 1.2% — primarily eucalyptol (1,8-cineole), which has additional expectorant and mild antimicrobial properties
- Petrolatum base — provides a semisolid carrier that slowly releases the volatile actives through body-temperature vaporization
The labels direct application to the chest and throat and warn against putting the rub in the nostrils. Body heat vaporizes the active components, the vapors rise into the breathing zone, and the menthol/camphor/eucalyptus mixture is inhaled along with normal breathing. The TRPM8 activation in the nasal mucosa produces the subjective decongestant effect, the eucalyptol provides some genuine expectorant action, and the warming/cooling sensation in the chest produces a counter-irritant effect that may distract from chest tightness and cough urge.
The Paul 2010 trial published in Pediatrics compared vapor rub, petrolatum alone, and no treatment in 138 children aged 2 to 11 with nighttime cough and cold symptoms. In parents' ratings, vapor rub did better than no treatment on every outcome except runny nose, but did better than petrolatum only for cough severity, child and parent sleep difficulty, and the combined symptom score. Mild irritant side effects were more common with vapor rub. It is one of the few controlled trials of an over-the-counter cough remedy in children to report a benefit. (Safety findings for infants are discussed below.)
Traditional Steam Inhalation
Steam inhalation with added peppermint or menthol is a traditional remedy for upper respiratory symptoms. The proposed mechanism combines:
- Heat and humidity — warm humid air directly hydrates the respiratory mucosa, thins mucus secretions, and may transiently relieve some congestion through vasodilation
- Menthol vapor — TRPM8 activation in the nasal cavity provides the subjective airflow improvement
- Eucalyptol from added eucalyptus oil (if used) — mild expectorant and antimicrobial effects
- Bronchodilation — mild bronchodilator effect from the warm humid air, with possible additional contribution from menthol on bronchial smooth muscle
The traditional method: a bowl or large pot of water is brought to a boil and taken off the heat, 3-5 drops of peppermint essential oil (and sometimes 3-5 drops of eucalyptus oil) are added, a large towel is draped over the head to capture the steam, and the person leans over the bowl at a comfortable distance (typically 12-18 inches) and breathes through the nose for 5-10 minutes, with the water hot but no longer boiling. Burns from hot water in a steam-inhalation setup are a significant injury risk, especially in children and the elderly. The labels of camphor-menthol-eucalyptus rubs warn against heating the rub or adding it to hot water, because it may splatter and cause burns.
A 2017 Cochrane review of heated, humidified air for the common cold (6 trials, 387 participants) found it uncertain whether steam relieves cold symptoms: one form of analysis showed a benefit and another did not, and the authors graded the evidence as low quality. Some studies reported minor side effects such as discomfort or irritation of the nose.
For more detailed coverage of sinusitis treatment options, see our Sinusitis page.
Antitussive (Cough Suppression) Activity
Beyond the subjective decongestant effect, menthol has genuine antitussive (cough-suppressant) activity. Cough is a protective reflex initiated by activation of sensory C-fibers and rapidly adapting receptors in the trachea, larynx, and large bronchi. These afferents project through the vagus nerve to the nucleus tractus solitarius in the brainstem, where the cough reflex is coordinated.
Menthol affects cough through several mechanisms:
- TRPM8 activation in the nose — in a 2013 guinea-pig study, menthol vapour suppressed cough only when it was delivered to the upper airways; menthol applied to the windpipe (trachea) or delivered to the lower airways had no effect on cough, and the authors concluded that menthol suppresses cough mainly through a reflex that starts in the nose
- Central effects via trigeminal afferents — inhaled menthol activates trigeminal cold receptors that send afferent signals to the brainstem; these signals modulate the cough-coordinating circuits in the nucleus tractus solitarius
- Mild bronchodilation — menthol produces a small bronchodilator effect through unclear mechanisms (possibly TRPM8-mediated relaxation of bronchial smooth muscle)
- Counter-irritant effect — the cooling sensation in the throat may distract from the cough urge, similar to the headache counter-irritant mechanism
Laboratory and clinical evidence: the Plevkova 2013 study, in guinea pigs, found that menthol vapour delivered to the upper airways suppressed cough set off by citric acid on the windpipe, and that the active nerves were TRPM8-carrying trigeminal nerves in the nose. The Kenia 2008 study in 42 healthy children aged 10 and 11 found no effect of menthol on any spirometry measurement of nasal airflow, a significant increase in how open the nose felt, and a cough count after a citric acid challenge that was no different from placebo. Multiple older trials of menthol-containing cough drops and lozenges have shown reduced cough frequency compared to placebo lozenges.
The antitussive effect is modest compared to pharmaceutical cough suppressants like dextromethorphan or codeine, but it is reliable, low-risk, and adds to the subjective comfort of common cold and acute bronchitis symptoms.
Chest Rubs and Pediatric Use
Menthol-containing chest rubs (camphor-menthol-eucalyptus vapor rubs) have a longer continuous-use history in children than almost any other over-the-counter respiratory remedy, but the safety profile depends critically on age and application location.
For children 2 years and older, the labels direct application to the chest and throat, and the Paul 2010 randomized trial in children aged 2 to 11 reported benefit on cough, congestion, and sleep difficulty, with more mild irritant side effects. The labels warn against use in the nostrils, in the eyes, by mouth and on wounds or damaged skin; the reasons reported for each:
- The face or inside the nostrils (irritation, possible aspiration of vapor)
- Broken or irritated skin (chemical irritation)
- The eyes or near the eyes (severe irritation)
- The mouth (oral toxicity from camphor at higher doses)
For children under 2 years old, the vapor rub labels say "children under 2 years: do not use" (some labels say "ask a doctor"). The American Academy of Pediatrics and the U.S. Food and Drug Administration (FDA) have advised against menthol, camphor, and eucalyptus exposure in infants under 2 due to reports of paradoxical mucus hypersecretion, laryngospasm, and rare respiratory failure. This caution is detailed in the dedicated infant safety section below.
Cough Drops and Lozenges
Menthol throat lozenges (cough drops) are among the most widely used over-the-counter respiratory products globally. The mechanism for cough drops combines:
- Oromucosal menthol delivery — menthol is released as the lozenge dissolves, providing sustained low-dose oral and pharyngeal exposure
- Increased salivation — sucking on the lozenge stimulates saliva production, which lubricates the throat and reduces the sensation of dryness that can trigger cough
- Throat coating — the sugar, glycerin, or other base ingredients in the lozenge form a thin film that physically coats and soothes irritated pharyngeal tissue
- Distraction — the act of sucking on the lozenge is itself a behavioral counter to the cough impulse
Standard adult cough drops contain 5-10 mg of menthol per drop. Pediatric formulations typically contain 1-2.5 mg. Higher-potency "extra strength" menthol throat lozenges may contain up to 12 mg per drop. These doses are well below the threshold for systemic adverse effects in adults.
For a sore throat without significant cough, plain menthol cough drops are generally as effective as more expensive pharmacological lozenges containing benzocaine or dyclonine. The throat-soothing benefit comes mostly from the lozenge mechanics rather than from any specific active ingredient at typical over-the-counter doses.
Combination with Eucalyptus and Camphor
Peppermint/menthol is commonly combined with eucalyptus and camphor in respiratory preparations because the three actives produce complementary effects:
- Menthol (from peppermint or as isolated compound): primary TRPM8 cold-receptor activator; subjective airflow improvement; antitussive activity
- Eucalyptol (1,8-cineole, the main component of eucalyptus oil): genuine expectorant action through stimulation of bronchial secretion; mild antimicrobial activity; modest anti-inflammatory effect
- Camphor: dual TRPM8 and TRPV1 activation producing simultaneous cooling and warming sensations; mild local anesthetic effect; counter-irritant chest sensation
The combination of all three produces a fuller respiratory-symptom relief profile than any single component alone. The intense cold-warmth sensation that characterizes vapor rubs is the camphor and menthol combination working through both TRPM8 (cold) and TRPV1 (warm) at the same time. Eucalyptus oil adds the actual mucus-thinning expectorant effect that menthol alone does not provide.
For more on eucalyptus specifically, see our Eucalyptus page.
Asthma and Bronchospasm Considerations
The relationship between menthol and asthma is more complex than the relationship between menthol and uncomplicated upper respiratory infection. Two competing effects exist:
- Mild bronchodilation — menthol produces a modest direct bronchodilator effect in some studies, with possible benefit for mild bronchospasm and chest tightness
- Irritant bronchoconstriction — in some asthma patients, intense menthol vapor (such as from heavily mentholated chest rubs or steam inhalation) can act as a direct airway irritant, triggering bronchoconstriction rather than relieving it
The research therefore raises a concern for people whose asthma is sensitive to airway irritants, mainly with intense vapor exposure (steam inhalation with high concentrations of essential oils, prolonged enclosed-space exposure to vapor rubs); in some people symptoms improve and in others they worsen.
Menthol cigarettes are a separate issue with significant public-health relevance. The menthol additive reduces the throat irritation of tobacco smoke, allowing deeper and more frequent inhalation, and has been independently associated with greater nicotine addiction and worse cessation outcomes. In May 2022 the U.S. Food and Drug Administration published a proposed rule that would prohibit menthol as a characterizing flavor in cigarettes; the Federal Register lists it only as a proposed rule, and no final rule has been published. The mechanism of menthol's adverse role in tobacco use is the same TRPM8-mediated "cooler smoke" sensation that makes deeper inhalation tolerable.
Critical Infant and Young Child Safety
The labels of camphor-menthol-eucalyptus vapor rubs say "children under 2 years: do not use" (some say "ask a doctor"). Some authorities extend this caution to children under 5.
The risk in young children is multifold:
- Laryngospasm — rare but documented cases of severe laryngospasm after menthol exposure to the face or oropharynx of infants. The exact mechanism is unclear but may involve hyper-responsive trigeminal-vagal reflexes in the immature airway.
- Mucus hypersecretion — Abanses and colleagues described a toddler who developed severe breathing distress after a vapor rub was put directly under her nose. In their follow-up study in ferrets, the rub raised mucus (mucin) secretion by 63% in windpipe tissue and slowed the beating of the airway's hair-like cilia by 35%, and in ferrets with inflamed airways it raised mucus transport by 34%; the authors wrote that these changes may lead to mucus blocking the small airways and to increased nasal resistance.
- Camphor toxicity — the camphor that typically accompanies menthol in chest rubs is potently toxic if ingested in significant quantity. Infants and toddlers who put rubs into their mouths can ingest enough camphor to cause seizures, respiratory depression, or coma. Even seemingly small amounts can be dangerous.
- Apnea — rare reports of menthol-vapor-associated apnea in infants, particularly when products are applied directly under the nostrils
The U.S. Food and Drug Administration, the American Academy of Pediatrics, and the labels of camphor-menthol-eucalyptus vapor rubs all carry warnings about use in children under 2 years old (under 6 years for some Asian markets). In this age group the reported benefits are modest, and the safety reports, though rare, include serious events.
Measures without menthol or camphor that are used for infants and young children with respiratory infection symptoms include: cool-mist humidifiers (humidify the room air without volatile oils), saline nasal drops or sprays (thin secretions without pharmacological exposure), nasal aspiration (mechanical removal of secretions), elevated head positioning during sleep, and adequate fluid intake. The vapor rub labels list a cough that lasts more than 7 days, comes back, or occurs with fever, rash or a lasting headache as possible signs of a serious condition.
For older children and adults, the labels carry the same warnings: not for use in the eyes, in the nostrils or by mouth, and not on wounds or damaged skin. Skin irritation and unusual breathing symptoms are the reactions reported after use.
Key Research Papers
- Burrow A, Eccles R, Jones AS (1983). The effects of camphor, eucalyptus and menthol vapour on nasal resistance to airflow and nasal sensation. Acta Otolaryngologica. — PubMed PMID: 6613544
- Eccles R (1994). Menthol and related cooling compounds. Journal of Pharmacy and Pharmacology. — PubMed PMID: 7529306
- McKemy DD, Neuhausser WM, Julius D (2002). Identification of a cold receptor reveals a general role for TRP channels in thermosensation. Nature. — PubMed PMID: 11882888
- Eccles R (2003). Menthol: effects on nasal sensation of airflow and the drive to breathe. Current Allergy and Asthma Reports. — PubMed PMID: 12662469
- Paul IM et al. (2010). Vapor rub, petrolatum, and no treatment for children with nocturnal cough and cold symptoms. Pediatrics. — PubMed PMID: 21059712
- Singh M, Singh M, Jaiswal N, Chauhan A (2017). Heated, humidified air for the common cold. Cochrane Database of Systematic Reviews. — PubMed PMID: 28849871
- Plevkova J, Kollarik M, Poliacek I, Brozmanova M, Surdenikova L, Tatar M, Mori N, Canning BJ (2013). The role of trigeminal nasal TRPM8-expressing afferent neurons in the antitussive effects of menthol. Journal of Applied Physiology. — PubMed PMID: 23640596
- Kenia P et al. (2008). Does inhaling menthol affect nasal patency or cough? Pediatric Pulmonology. — PubMed PMID: 18435479
- Abanses JC, Arima S, Rubin BK (2009). [A camphor-menthol-eucalyptus vapor rub] induces mucin secretion, decreases ciliary beat frequency, and increases tracheal mucus transport in the ferret trachea. Chest. — PubMed PMID: 19136404