⚠ Evidence warning: Clinical trials or other evidence do not support the claim that cumin relieves functional dyspepsia and bloating and acts against methane-producing gut archaea. This page keeps it as a report of what people, websites or other media say.
Cumin as Digestive Aid
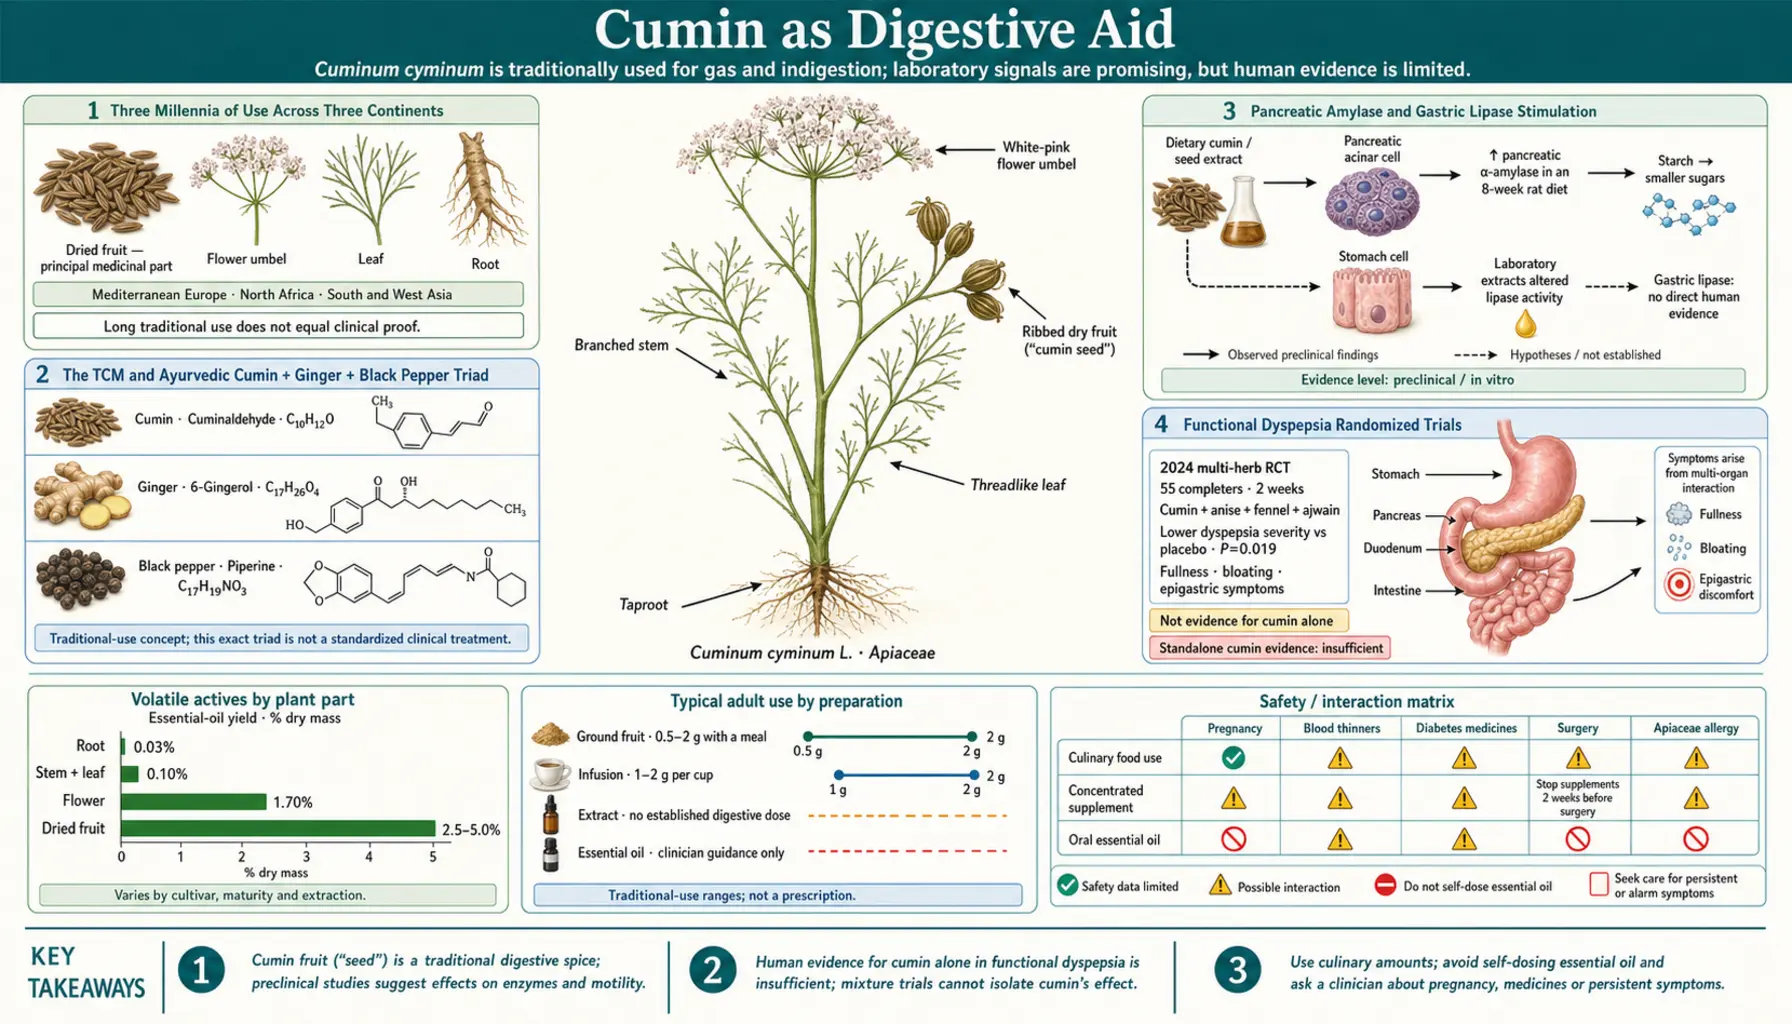
Cumin is the most widely used digestive herb in the global culinary tradition, period. From jeera pani in north India to kammun-spiced tagines in Morocco to the cumin + coriander + black pepper triads in classical Traditional Chinese Medicine and Ayurveda, the same plant has been independently selected by every major food culture between the Mediterranean and the Bay of Bengal as the go-to remedy for sluggish digestion, post-meal bloating, and the broad complaint Western medicine would now call functional dyspepsia. Proposed mechanisms include faster intestinal transit, less gas production and increased bile flow; in rats, an 8-week cumin diet raised pancreatic amylase, trypsin and chymotrypsin, an effect not seen after a single dose. Human evidence is thin: a small uncontrolled irritable bowel syndrome (IBS) case series and a 2024 placebo-controlled trial after abdominal surgery. The functional dyspepsia trials often quoted for cumin tested caraway-and-peppermint-oil or multi-herb products that contain no cumin. This deep-dive maps the mechanism, the trials, the dosing forms, and the cumin + ginger + black pepper triad that is the centerpiece of Eastern digestive medicine.
Table of Contents
- Three Millennia of Use Across Three Continents
- The Traditional Chinese Medicine (TCM) and Ayurvedic Cumin + Ginger + Black Pepper Triad
- Pancreatic Enzyme Stimulation in Rats
- Functional Dyspepsia: Trials of Related Herbal Oils
- The Irritable Bowel Syndrome Case Series
- Carminative Action and the Methanogen Problem
- Bile Secretagogue Effect and Fat Digestion
- Cumin Water (Jeera Pani) — Practical Preparation
- Small Intestinal Bacterial Overgrowth (SIBO) and Intestinal Methanogen Overgrowth (IMO) Considerations
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Three Millennia of Use Across Three Continents
The earliest written reference to cumin appears on a Sumerian cuneiform tablet from approximately 2,000 BCE, where it is listed as a medicinal seed for stomach complaints. Egyptian medical papyri from the Middle Kingdom (around 1,700 BCE) prescribe cumin for indigestion and intestinal pain. Cumin seeds have been recovered from pharaonic tombs as part of the funerary spice package — included specifically because of the digestive associations that would carry into the afterlife. The Greek physician Dioscorides in the first century CE wrote that cumin "stoppeth the belly that is loose, helpeth the colic, and dissolveth gas."
The Indian Ayurvedic tradition, formalized in the Charaka Samhita around 200 BCE but reflecting an oral tradition centuries older, classifies jeera (cumin) as deepana (kindler of digestive fire / agni) and pachana (digester of accumulated ama / metabolic waste). Both classifications place cumin in the small set of herbs considered foundational to digestive medicine, alongside ginger, black pepper, and ajwain. In modern Indian households, jeera pani (cumin water) is the most widely used home remedy for post-meal bloating — consumed daily by millions on an empty stomach as part of standard morning routine.
The Chinese tradition arrived at the same plant from a different direction. Ku-min appears in the Bencao Gangmu compendium of Li Shizhen (1578 CE) as a warming carminative classified to the spleen and stomach meridians — the energetic territory most associated with the Western concept of digestive function. The Mediterranean and Middle Eastern traditions agree: in Arabic medical texts cumin (kammun) is the first-line digestive herb for both children and adults, traditionally given as an infusion sweetened with honey. The convergence of three independent medical cultures on the same plant for the same indication is a striking feature of its history.
The Traditional Chinese Medicine (TCM) and Ayurvedic Cumin + Ginger + Black Pepper Triad
One pattern is so consistent across Eastern medicine traditions that it deserves its own section: the cumin + ginger + black pepper warming triad. The three spices are repeatedly combined in classical formulations from Ayurveda, TCM, Unani (Persian/Arab medical tradition), and Tibetan medicine for the same indication — the patient who presents with cold extremities, sluggish digestion, abdominal bloating after meals, and a coated tongue. The Ayurvedic name for this constellation is mandagni (weak digestive fire), and the triad is its standard treatment.
Each of the three spices contributes a distinct mechanism:
- Cumin (Cuminum cyminum) — stimulates pancreatic exocrine secretion and bile flow, providing the enzymatic horsepower for digestion. See the Cumin main page for the active-compound breakdown.
- Ginger (Zingiber officinale) — accelerates gastric emptying via 5-HT3 receptor modulation, reduces nausea, and provides the warming effect through gingerol activation of TRPV1 channels. Ginger is the single most-studied of the three for digestive indications, with strong evidence in chemotherapy-induced nausea, motion sickness, and pregnancy-induced nausea.
- Black pepper (Piper nigrum) — the piperine alkaloid is a potent inhibitor of cytochrome P450 3A4 and P-glycoprotein, dramatically increasing the bioavailability of co-ingested phytochemicals (the famous 2,000% increase in curcumin bioavailability when combined with piperine). In this triad, piperine boosts the systemic absorption of cuminaldehyde and gingerol.
The classical Ayurvedic preparation trikatu (literally "three pungents") is a related but different trio of ginger, black pepper and long pepper (Piper longum), with no cumin; cumin-based combinations such as the modern jeera-pippali-shunti formulations are sold across South Asian pharmacies. The triad is typically taken either as a tea (1 teaspoon each in 2 cups water, simmered 10 minutes) or as a small portion of equal-parts ground spice eaten with the first bite of a heavy meal. When you season a curry with all three, you are using the same formulation Ayurvedic physicians have prescribed for digestive complaints for over 2,000 years — the only difference is the explicit therapeutic intent.
Pancreatic Enzyme Stimulation in Rats
A proposed mechanism for cumin's digestive effect is that cuminaldehyde and the essential-oil monoterpenes act on chemoreceptors in the gastric mucosa and the upper duodenum, triggering a vagal reflex that stimulates pancreatic exocrine secretion, including pancreatic amylase (the enzyme that hydrolyzes starch to maltose). No study found for this page measured gastric lipase after cumin, and no human study of cumin and digestive enzymes was found.
Platel and Srinivasan published two rat studies, in 1996 in the International Journal of Food Sciences and Nutrition and in 2000 in Nahrung. In the 2000 study, rats fed cumin (1.25% of the diet) for 8 weeks had higher pancreatic amylase, trypsin and chymotrypsin activity; cumin was not among the spices that enhanced pancreatic lipase (curcumin, capsaicin, piperine, ginger, fenugreek and asafoetida did). This boost to the pancreatic enzymes was not seen when the spices were given as a single oral dose, which points to an adaptive rather than an acute response. In the 1996 study, the same 8-week cumin diet lowered the levels of phosphatases and sucrase in the lining of the small intestine, while curcumin, capsaicin, piperine and ginger raised intestinal lipase, sucrase and maltase. These are rat findings; neither study tested the cumin + ginger + pepper combination or measured bile flow.
If the rat findings carry over to people, cumin would act as an indirect digestive aid — not replacing pancreatic enzymes the way porcine pancreatin or fungal lipase preparations do, but prompting the body's own pancreas to release more of its native enzymes. In frank pancreatic insufficiency (cystic fibrosis, chronic pancreatitis, post-pancreaticoduodenectomy), cumin alone is inadequate — supplemental pancreatic enzymes are required; no study found for this page tested cumin alongside enzyme supplements.
Functional Dyspepsia: Trials of Related Herbal Oils
Functional dyspepsia is the formal Rome IV diagnostic category for chronic upper-abdominal discomfort, fullness, early satiety, and bloating that occurs in the absence of structural pathology (peptic ulcer, gastritis, biliary disease, malignancy). It is one of the most common reasons patients consult primary care, affecting approximately 10–20% of adults worldwide. Pharmacologic options are limited and unsatisfying — proton pump inhibitors help only the subset with overlap acid reflux, prokinetic agents like metoclopramide carry tardive dyskinesia risk with chronic use, and tricyclic antidepressants help some patients but with sedation and constipation side-effects.
No randomized trial of cumin itself in functional dyspepsia was found in PubMed. The trials often quoted in this context tested related herbal products that contain no cumin. In a 2000 trial, 96 outpatients with functional dyspepsia took enteric-coated capsules of 90 mg peppermint oil and 50 mg caraway oil (Carum carvi, a close cumin relative) or placebo twice daily for 28 days. Pain fell by 40% on the oil capsules vs 22% on placebo, the sensation of pressure, heaviness and fullness by 43% vs 22%, and 67% vs 21% of patients were rated much or very much improved. A 2004 double-blind, randomized, placebo-controlled, multicenter trial in 120 patients tested a six-herb preparation (bitter candy tuft, matricaria flower, peppermint leaves, caraway, licorice root and lemon balm): after 8 weeks, 43.3% on the herbal preparation and 3.3% on placebo reported complete relief of symptoms. Neither product contains cumin.
Cumin's own use for bloating, upper-abdominal fullness and post-meal discomfort rests on traditional use and on the rat enzyme studies above, not on a dyspepsia trial. As a kitchen spice it costs little, and the caraway + peppermint-oil and multi-herb trials are the nearest controlled evidence.
The Irritable Bowel Syndrome Case Series
A small uncontrolled case series of cumin essential oil in irritable bowel syndrome (the authors call it a pilot study) was published in 2013 by Agah et al. in Middle East Journal of Digestive Diseases. 57 patients meeting Rome II criteria for irritable bowel syndrome stopped their other treatments and took 20 drops per day of cumin essential oil; there was no placebo group. Symptoms were assessed with a questionnaire before treatment, 2 and 4 weeks after starting, and 2 and 4 weeks after stopping.
- Abdominal pain, bloating, incomplete defecation, fecal urgency and mucus in the stool decreased significantly during and after treatment
- Stool consistency and defecation frequency improved significantly in patients with the constipation-predominant pattern of irritable bowel syndrome
- In the full paper, the authors note that some patients had nausea, abdominal pain and dizziness after taking the cumin extract
What is not known: with no placebo group, the improvement cannot be separated from the placebo response, and the authors themselves call for placebo-controlled studies with larger samples.
The study is too small and uncontrolled to be definitive. In a 2026 network meta-analysis of 29 randomized irritable bowel syndrome trials of antispasmodics and antidepressants, anise oil showed benefits in specific irritable bowel syndrome subgroups and a cumin preparation (cumin sofouf) was among the treatments with the largest quality-of-life gains. Among the herbal oils, the strongest evidence base is for peppermint oil (which is in the Lamiaceae family and is described as relaxing intestinal smooth muscle via L-type calcium channel blockade). For more on irritable bowel syndrome management, see our Irritable Bowel Syndrome page.
Carminative Action and the Methanogen Problem
A "carminative" in classical pharmacology is an agent that reduces flatulence and abdominal distention. The mechanism for cumin combines two effects: relaxation of intestinal smooth muscle (reducing trapped-gas pockets) and direct antimicrobial activity against the gut bacteria responsible for fermentation gas production.
The only placebo-controlled human trial of cumin on gut function found for this page was in a different setting. In a 2024 triple-blind randomized trial, 74 patients after abdominal surgery took two 250 mg capsules of cumin extract (4 hours after surgery and 1 hour later) or a starch placebo. First gas passed at 9.03 ± 3.41 vs 11.72 ± 4.21 hours and the first bowel movement came at 16.97 ± 5.02 vs 26 ± 9.87 hours, and abdominal pain, bloating, nausea and vomiting were significantly less frequent in the cumin group.
The most important target in this regard is Methanobrevibacter smithii — the dominant methane-producing archaeon of the human gut and the principal pathogen in methane-positive small-intestinal bacterial overgrowth (IMO — intestinal methanogen overgrowth, formerly called methane-SIBO). Methane production slows colonic transit, producing the chronic constipation, bloating, and abdominal distention that is the most common constipation-predominant irritable bowel syndrome (IBS-C) presentation. No study of cumin oil against human-gut Methanobrevibacter was found in PubMed: the only cumin–methanogen studies found are a dairy-cow rumen study of mixed plant-based feed additives and a computer docking study, so an effect of cumin in the constipation-predominant irritable bowel syndrome / methane-positive small intestinal bacterial overgrowth (SIBO) picture is not established. Prescription rifaximin + neomycin combination antibiotic therapy is the drug treatment used for methane-positive overgrowth.
The carminative effect is also relevant after meals high in fermentable carbohydrates (FODMAPs, legumes, cruciferous vegetables) that produce gas predictably. The traditional Indian post-meal mouth freshener mukhwas — a mixture of cumin, fennel seeds, ajwain, and sometimes coriander — is traditionally used for exactly this purpose: a small dose of mixed Apiaceae carminatives at the end of the meal to suppress the gas production that would otherwise begin in the next several hours.
Bile Secretagogue Effect and Fat Digestion
Cumin is a "cholagogue" in the traditional pharmacology classification — an agent that promotes bile flow from the gallbladder into the small intestine. The mechanism is again mediated by cuminaldehyde stimulation of chemoreceptors in the duodenum, which trigger cholecystokinin (CCK) release. CCK is the master hormone of fat digestion: it contracts the gallbladder, relaxes the sphincter of Oddi, and stimulates pancreatic secretion. Cumin essentially mimics the chemosensory signal that fat itself would normally produce.
The clinical implication is that cumin supports fat digestion specifically. Patients with bile insufficiency (post-cholecystectomy, biliary sludge, fatty liver disease with intrahepatic cholestasis, primary biliary cholangitis) often complain of fat-meal intolerance — nausea, right-upper-quadrant fullness, and steatorrhea after meals containing significant fat. Cumin is traditionally added to fat-containing meals (the cumin-spiced lamb dishes of Central Asian cuisine, for example, or the cumin + olive oil base of Middle Eastern lentil stews) to improve tolerance. Bitter herbs (gentian, artichoke leaf, dandelion root) provide a stronger version of the same effect for patients with more pronounced bile insufficiency.
The cholagogue effect also contributes to cumin's lipid-lowering mechanism discussed on our Cholesterol and Weight deep-dive page — increased bile flow means increased bile-acid excretion in stool, which forces the liver to synthesize new bile acids from cholesterol, lowering serum low-density lipoprotein (LDL). This is the same mechanism cholestyramine (a bile-acid sequestrant resin) uses pharmacologically.
Cumin Water (Jeera Pani) — Practical Preparation
Jeera pani is the most widely used cumin preparation in the world. It is consumed on an empty stomach in the morning, typically before any food or other beverage, across most of South Asia. The preparation is simple but the timing matters — the 8–12 hour overnight soak is required for full extraction of the essential-oil monoterpenes and the water-soluble phenolics.
- Cumin seeds: 1–2 teaspoons (5–10 grams) of whole seeds. Whole seeds are preferred to ground; the intact pericarp protects the essential oils from oxidation during the soak.
- Water: 300 ml filtered water at room temperature.
- Soak: 8–12 hours overnight. The water turns yellowish-brown by morning with a distinct cumin aroma — this is the visual cue that extraction is complete.
- Drink: Room temperature, or gently warmed (not boiling — high heat volatilizes the essential oils and degrades cuminaldehyde). You can strain the seeds out or consume them with the water.
- Timing: 15–30 minutes before the first meal of the day, on an empty stomach.
- Frequency: Daily is the traditional regimen. Some practitioners recommend cycling 5 days on / 2 days off to prevent any potential adaptive blunting.
A faster alternative is the warm cumin tea preparation — 1 teaspoon ground cumin in 1 cup hot (not boiling) water, steeped 10 minutes, sipped while warm. This produces a faster onset of effect (within 20–30 minutes) but less complete extraction than the overnight soak, and the heat does degrade some cuminaldehyde. For acute use after a heavy meal, the tea is fine; for daily maintenance, the overnight soak is the canonical preparation.
Small Intestinal Bacterial Overgrowth (SIBO) and Intestinal Methanogen Overgrowth (IMO) Considerations
The picture is more nuanced in small-intestinal bacterial overgrowth (SIBO). On one hand, cumin essential oil has direct antimicrobial activity against many of the small intestinal bacterial overgrowth-relevant bacterial species, including E. coli, Klebsiella, and various Streptococcus and Enterococcus isolates. On the other hand, cumin's prokinetic-stimulating and bile-secretagogue effects could theoretically be helpful (more bile = more antimicrobial activity in the small bowel) or theoretically counterproductive (faster transit could move bacteria from colon to ileum).
The clinical reality is that most small intestinal bacterial overgrowth patients tolerate cumin well, particularly when used as a culinary spice rather than a concentrated essential-oil supplement. The cumin + ginger + black pepper triad described above is frequently used as an adjunct during the recovery phase after antibiotic small intestinal bacterial overgrowth treatment — helping restore normal motility and digestive function while the gut microbiome rebalances. For more on small intestinal bacterial overgrowth management strategies, see our small intestinal bacterial overgrowth Overview and the deep-dive sub-articles on root causes and prokinetics. For people with high-FODMAP sensitivity, cumin itself is listed as low-FODMAP in normal culinary quantities (per Monash University FODMAP database).
Cautions and Drug Interactions
- Pregnancy — uterine activity — cumin essential oil at high doses has shown uterine-stimulating activity in animal models. Culinary quantities (the cumin in a typical curry or chili recipe) are traditionally used in pregnancy; the animal findings raise a concern for concentrated essential oil supplements in pregnancy.
- Diabetic patients on hypoglycemic medications — cumin can lower blood glucose, potentially additively with metformin, sulfonylureas, or insulin. See our Blood Sugar deep-dive page for the full discussion. Daily medicinal amounts of cumin can therefore add to the effect of these drugs.
- Patients with biliary obstruction — the cholagogue effect can precipitate biliary colic in patients with gallstones obstructing the cystic duct. The concern applies to concentrated cumin preparations in people with known gallstones (cholelithiasis).
- Drug bioavailability — the piperine question — if cumin is used as part of the cumin + ginger + black pepper triad, the piperine component will increase the bioavailability of many co-administered drugs (theophylline, phenytoin, beta-blockers such as propranolol, statins, immunosuppressants).
- Allergic reactions — Apiaceae-family allergy can produce cross-reactive reactions to cumin, fennel, anise, coriander, dill, and celery. The cross-reactivity matters most for people with known carrot or celery allergy.
- Concentrated essential oil – topical and oral — cumin essential oil is photo-sensitizing (contains furocoumarins). Topical application to skin before sun exposure can cause phytodermatitis. The only human study of oral cumin essential oil cited on this page used 20 drops per day for 4 weeks.
Key Research Papers
- Platel K, Srinivasan K (1996). Influence of dietary spices or their active principles on digestive enzymes of small intestinal mucosa in rats. International Journal of Food Sciences and Nutrition. — PubMed PMID: 8616674
- Platel K, Srinivasan K (2000). Influence of dietary spices and their active principles on pancreatic digestive enzymes in albino rats. Nahrung. — PubMed PMID: 10702999
- Agah S et al. (2013). Cumin extract for symptom control in patients with irritable bowel syndrome: a case series. Middle East Journal of Digestive Diseases. — PubMed PMID: 24829694
- May B, Köhler S, Schneider B (2000). Efficacy and tolerability of a fixed combination of peppermint oil and caraway oil in patients suffering from functional dyspepsia. Alimentary Pharmacology and Therapeutics. — PubMed PMID: 11121917
- Madisch A, Holtmann G, Mayr G, Vinson B, Hotz J (2004). Treatment of functional dyspepsia with a herbal preparation. A double-blind, randomized, placebo-controlled, multicenter trial. Digestion. — PubMed PMID: 14755152
- Amin EA, Ismail E, Mahboobeh R, Tabandeh S (2024). The effect of Cuminum cyminum on the return of bowel motility after abdominal surgery: a triple-blind randomized clinical trial. BMC Complementary Medicine and Therapies. — PubMed PMID: 38965524
- Ismaiel A, Leucuta DC, Boitos I, et al. (2026). From Visceral Pain to Emotional Distress: Comparative Effectiveness of Antispasmodics and Antidepressants in Irritable Bowel Syndrome — Systematic Review and Network Meta-analysis. Journal of Gastrointestinal and Liver Diseases. — PubMed PMID: 42470701
- Srinivasan K (2018). Cumin (Cuminum cyminum) and black cumin (Nigella sativa) seeds: traditional uses, chemical constituents, and nutraceutical effects. Food Quality and Safety. — doi:10.1093/fqsafe/fyx031
PubMed Topic Searches
Connections
- All Herbs
- Cumin Overview
- Cumin Benefits Hub
- Cumin for Blood Sugar
- Cumin Antioxidant & Anti-Inflammatory
- Cumin for Cholesterol & Weight
- Ginger (Triad Partner)
- Fennel (Carminative Partner)
- Ajwain
- Coriander Seeds
- Turmeric
- Peppermint
- Irritable Bowel Syndrome
- Small Intestinal Bacterial Overgrowth
- Gut Healing
- Parasites
- History