⚠ Evidence warning: Clinical trials or other evidence do not support the claim that combining cumin with cinnamon adds to its blood-sugar effect, as described in integrative-medicine writing for prediabetes. This page keeps it as a report of what people, websites or other media say.
Cumin for Blood Sugar
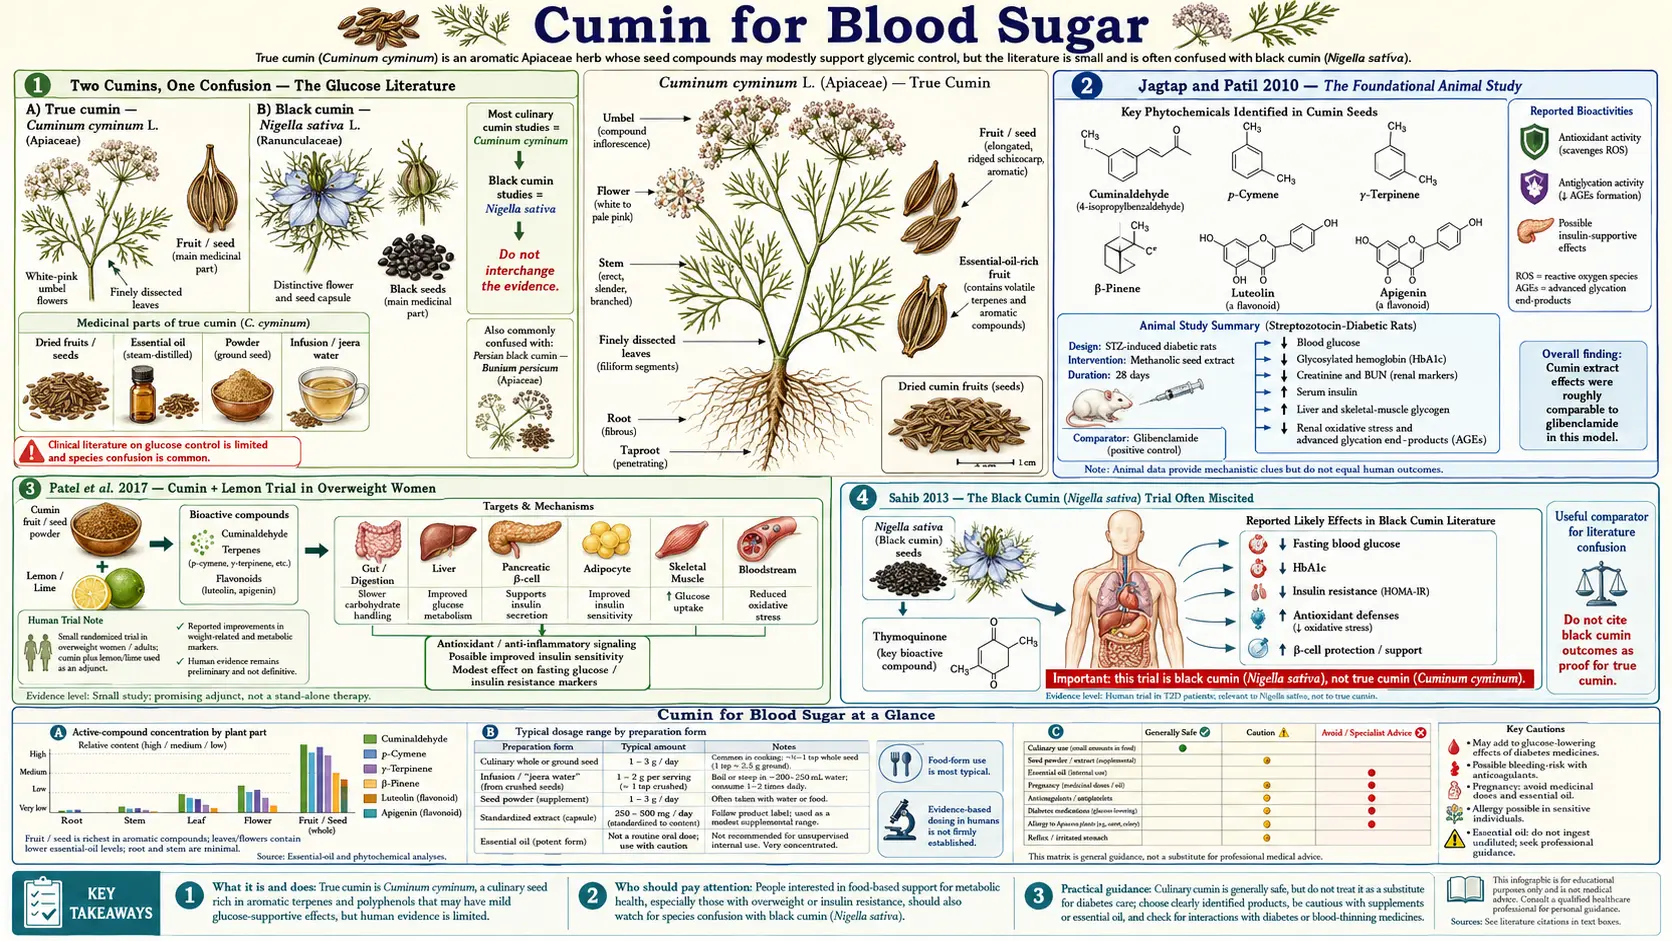
The cumin-and-glucose literature is one of the more interesting niche stories in nutraceutical pharmacology. Beginning with Jagtap and Patil's 2010 streptozotocin-diabetic-rat work showing antihyperglycemic activity comparable to the diabetes drug glibenclamide and suppression of advanced glycation end-product formation, and continuing through Taghizadeh and colleagues' 2016 trial of cumin + lime capsules in 72 overweight adults, which reported reduced fasting plasma glucose alongside weight loss, and a 2017 placebo-controlled trial of cumin essential oil in people with type 2 diabetes, the case for true cumin (Cuminum cyminum) as a glycemic adjunct has accumulated steadily. The mechanism involves at least three parallel pathways: cuminaldehyde's direct alpha-amylase and alpha-glucosidase inhibition (slowing carbohydrate absorption in the small intestine), alpha-pinene's effect on the muscle glucose transporter GLUT4 (seen in mouse muscle cells), and the phenolic antioxidants' suppression of glucotoxicity-driven beta-cell apoptosis. Critically, this article distinguishes true cumin from black cumin (Nigella sativa) — an unverifiable 2013 dyslipidemia report frequently miscited as cumin evidence actually tested Nigella, an unrelated species with stronger glycemic data of its own.
Table of Contents
- Two Cumins, One Confusion — The Glucose Literature
- Jagtap and Patil 2010 — The Foundational Animal Study
- Taghizadeh et al. 2016 — The Cumin + Lime Trial in Overweight Adults
- Two 2021 Meta-Analyses Disagree
- The Black Cumin (Nigella sativa) Trials Often Miscited as Cumin
- Alpha-Amylase and Alpha-Glucosidase Inhibition
- Alpha-Pinene and Peripheral Insulin Sensitization
- Cuminaldehyde and Advanced Glycation End-Products
- Clinical Positioning in Pre-Diabetes and Type 2 Diabetes
- Dosing and Forms for Glycemic Use
- Cautions and Hypoglycemia Risk
- Key Research Papers
- Connections
- Featured Videos
Two Cumins, One Confusion — The Glucose Literature
Before reviewing the glucose evidence, the nomenclature issue must be confronted directly. The popular and even the academic literature routinely conflates two unrelated plants:
- True cumin (Cuminum cyminum) — the elongated, ridged, brownish-yellow seed of an Apiaceae-family flowering plant. Dominant active: cuminaldehyde. This is the cumin in your spice rack, the cumin in chili powder, the cumin in jeera pani, and the cumin in the Taghizadeh and Zare trials. This is the only cumin discussed on this Benefits hub.
- Black cumin / black seed (Nigella sativa) — the small, jet-black, angular seed of a Ranunculaceae-family plant. Dominant active: thymoquinone. Often sold as "kalonji," "Habba Sauda," or simply "black seed oil." Stronger glycemic effect than true cumin per its own clinical literature, but a completely different plant. Has its own page outside this hub.
A 2013 report on type-2 diabetics with dyslipidemia (in a journal PubMed does not index, so it cannot be verified here), frequently cited in popular health-magazine writing as evidence for "cumin" lowering blood sugar, actually tested Nigella sativa. The conclusions are valid evidence for Nigella, not for Cuminum cyminum. Both plants do lower glucose, but through different mechanisms (cuminaldehyde and alpha-pinene for true cumin; thymoquinone for Nigella), at different magnitudes (Nigella evidence is generally stronger), and from different safety profiles. The remainder of this article discusses true cumin only; Nigella sativa evidence is summarized at the end of this section but not throughout.
Jagtap and Patil 2010 — The Foundational Animal Study
The seminal preclinical work establishing true cumin's antihyperglycemic effect was Jagtap AG and Patil PB (2010) in Food and Chemical Toxicology: "Antihyperglycemic activity and inhibition of advanced glycation end product formation by Cuminum cyminum in streptozotocin induced diabetic rats." Streptozotocin (STZ) is a beta-cell-toxic compound used to induce a model of type-1-like diabetes in rodents — it is the standard preclinical model for testing antihyperglycemic agents.
The Jagtap and Patil protocol gave STZ-diabetic rats a methanolic extract of Cuminum cyminum seeds for 28 days, alongside a comparison group given the diabetes drug glibenclamide. The study abstract reports, against untreated diabetic controls:
- Blood glucose was reduced
- Glycated hemoglobin (hemoglobin A1c, HbA1c) was reduced
- Creatinine and blood urea nitrogen fell, and serum insulin and liver and muscle glycogen improved
- Oxidative stress and advanced glycation end-products (AGEs) in the kidney were significantly reduced, more than with glibenclamide
- The antidiabetic effect was comparable to glibenclamide
The study abstract does not state the dose, so no human-equivalent dose can be derived from it. The human trials are a separate matter: Zare (2014) found no effect on fasting blood sugar at 3 g/day of cumin powder, and the cumin-plus-lime trial that did move glucose used only 150 mg/day. A four-week rat study is not evidence that the human trials measured the same effect the rats did.
Taghizadeh et al. 2016 — The Cumin + Lime Trial in Overweight Adults
This section previously described a “Patel et al. 2017” cumin-plus-lemon trial in the Journal of Functional Foods. No such paper exists. The real study it was garbled from is Taghizadeh M, Memarzadeh MR, Abedi F, et al., Iranian Red Crescent Medical Journal 2016;18(8):e34212 — a cumin-plus-lime trial, and its actual protocol differs from the one previously given here in almost every particular. Since the corrected numbers change the picture, they are set out plainly.
The real protocol. 72 overweight adults aged 18–50, randomized into three arms of 24: high-dose Cuminum cyminum plus lime capsules (75 mg each), low-dose capsules (25 mg each), or placebo — each taken twice daily for eight weeks. Note what that means: the high-dose arm received 150 mg per day of encapsulated cumin, not three grams of cumin powder, and the comparison was high dose versus low dose versus placebo, not “cumin plus citrus versus cumin alone.”
What the trial reported, high dose versus low dose and placebo:
- Weight loss of 2.1 kg, versus 1.2 kg on low dose and a 0.2 kg gain on placebo (P < 0.001)
- Body mass index (BMI) fell 0.8 kg/m², versus 0.5 and a 0.1 rise (P < 0.001)
- A significant reduction in fasting plasma glucose
- A rise in QUICKI, an insulin-sensitivity index (+0.02 versus +0.01 and +0.01; P = 0.01). The trial reported QUICKI, not homeostatic model assessment of insulin resistance (HOMA-IR); the previously stated “homeostatic model assessment of insulin resistance decreased by approximately 25%” was not one of its findings.
- Triglycerides −14.1 mg/dL, total cholesterol −18.4 mg/dL, low-density lipoprotein (LDL) −11.8 mg/dL, each versus increases or smaller falls in the comparison arms
The trial cannot separate cumin from lime. Every arm received both, so the citrus contribution is unresolved — there was no lime-alone arm and no cumin-alone arm. Any claim that lemon or lime “adds independently” to cumin has no trial behind it.
The dose problem this exposes
The 150 mg/day used here is roughly one-twentieth of the 3 g/day that cumin-and-glucose writing usually recommends, including the recommendation further down this page. Two readings are possible and honesty requires stating both: either a very small encapsulated dose is enough, which would be surprising, or the weight and glucose changes owe something to the eight weeks of trial participation and the accompanying attention. The trial does not settle it.
The other human trials, including the negative ones
- Zare et al. (2014) gave 88 overweight and obese women 3 g/day of cumin powder in yogurt at two meals for three months. Cholesterol, triglycerides and low-density lipoprotein improved, high-density lipoprotein (HDL) rose, and weight, body mass index, waist circumference and fat mass all fell. But on the endpoint this page is about, the paper's own conclusion is explicit: it had no effect on fasting blood sugar. That is a null glucose result at exactly the dose and duration recommended below, and it belongs in view.
- Taghizadeh et al. (2015) compared cumin capsules, orlistat and placebo, each taken three times a day for eight weeks, in 78 overweight adults. Cumin matched orlistat on weight and body mass index: weight fell 1.1 kg on cumin and 0.9 kg on orlistat, and rose 0.2 kg on placebo. It beat both comparators on insulin metabolism — serum insulin fell 1.4 µIU/ml on cumin, the homeostatic model assessment of beta-cell function (HOMA-B) fell, and QUICKI rose. On paper this is the strongest human signal that cumin does something to insulin handling, but the trial carries an expression of concern (Annals of Nutrition and Metabolism 2023, PMID 37334987): the journal cited discrepancies in the group sizes within the article, and between the article and the trial registration in the participants' demographic data and the trial start date, referred the matter to Iran's National Committee for Ethics in Biomedical Research, and stated that readers should interpret the data with caution.
- Morovati et al. (2019) is the trial most often left out. In a randomized, triple-blind, placebo-controlled trial, cumin essential oil 75 mg three times daily for eight weeks in patients with metabolic syndrome produced no effect on any metabolic-syndrome component except diastolic blood pressure — glucose included.
- Jafari et al. (2017) is the trial in people with type 2 diabetes. In a double-blind, randomized, placebo-controlled trial, patients took cumin essential oil capsules of 100 mg/day or 50 mg/day, or placebo (33 people in each group), for 8 weeks. Fasting blood sugar, glycosylated hemoglobin (HbA1c) and serum insulin fell significantly in both cumin groups, and rose in the placebo group.
The fair summary is narrower than the enthusiastic one: cumin appears to help modestly with weight and with insulin-sensitivity indices in short overweight-adult trials, while its effect on fasting glucose itself is inconsistent — positive in the cumin-plus-lime trial, absent in two others. The one trial in people with diagnosed type 2 diabetes (Jafari 2017, cumin essential oil) reported falls in fasting blood sugar and hemoglobin A1c.
Two 2021 Meta-Analyses Disagree
Two reviews published in 2021 each pooled eight trials of cumin and reached opposite answers on blood sugar.
- Karimian and colleagues (Phytotherapy Research; eight randomized controlled trials, 552 participants) found that cumin supplementation did not significantly alter fasting blood sugar (weighted mean difference −17.77 mg/dl; 95% confidence interval −36.42 to 0.87; p = .06), serum insulin, or the homeostasis model assessment of insulin resistance (HOMA-IR) index.
- Tavakoli-Rouzbehani and colleagues (Journal of Ethnopharmacology; eight controlled clinical trials in patients with different chronic diseases) reported that cumin significantly reduced fasting blood sugar and HbA1c and increased QUICKI, with no significant effect on insulin.
The Black Cumin (Nigella sativa) Trials Often Miscited as Cumin
Popular cumin-and-blood-sugar writing routinely borrows the Nigella sativa glucose trials without saying that they tested a different plant. The paper usually named for this — a 2013 Iraqi Journal of Pharmaceutical Sciences report on Nigella sativa seed oil — is in a journal PubMed does not index, so it cannot be verified here and its numbers are not repeated. Two Nigella sativa trials that can be checked make the same point:
- Bamosa AO, Kaatabi H, Lebdaa FM, et al. (2010), Indian Journal of Physiology and Pharmacology 54(4):344-354 — Nigella sativa seeds and glycemic control in type 2 diabetes. PubMed 21675032
- Kaatabi H, Bamosa AO, Badar A, et al. (2015), PLoS ONE 10(2):e0113486 — a placebo-controlled participant-blinded trial reporting improved glycemic control and reduced oxidative stress in type 2 diabetes. PubMed 25706772
The figures previously quoted in this section (a 45 mg/dL fall in fasting glucose and a 1.5-point hemoglobin A1c drop) came from the unverifiable source and have been removed rather than restated. What remains true is the point the section exists to make:
These are larger effects than any true cumin trial has demonstrated. They are real, and they reflect genuine pharmacology of Nigella sativa, particularly the thymoquinone content. They are not transferable to Cuminum cyminum, which has a different essential-oil composition (cuminaldehyde rather than thymoquinone), a different non-volatile chemistry, and demonstrably smaller clinical effects on the same endpoints. For true cumin, the only trial at 3 g/day (Zare 2014) found no effect on fasting blood sugar, and in a 2021 meta-analysis of eight trials the pooled fall in fasting blood sugar (−17.77 mg/dl) was not statistically significant (p = .06); Nigella produces larger effects but is a different plant with different sourcing and a separate evidence base. The two are not interchangeable.
Alpha-Amylase and Alpha-Glucosidase Inhibition
The most directly studied glycemic mechanism for true cumin is enzymatic. Cuminaldehyde and the broader cumin essential-oil fraction inhibit two key carbohydrate-digesting enzymes:
- Alpha-amylase (salivary and pancreatic) — hydrolyzes dietary starch to maltose and maltotriose in the mouth and small intestine
- Alpha-glucosidase (brush-border) — cleaves the resulting maltose to free glucose for absorption
This is the same target as the prescription drug acarbose, which is the prototype alpha-glucosidase inhibitor. Acarbose works clinically by blunting post-meal glucose spikes — carbohydrate that cannot be fully digested in the small intestine is not absorbed there, and instead passes to the colon where it is fermented (producing the characteristic acarbose flatulence side-effect). Cumin produces a milder version of the same effect through the same mechanism, with proportionally milder side-effects.
In a 2005 laboratory study (Lee), cuminaldehyde inhibited alpha-glucosidase taken from rats with an IC₅₀ of 0.5 mg/mL and was about 1.8 times less potent than acarbose; that study did not test alpha-amylase. Whether this laboratory effect changes post-meal glucose in people was not measured in any of the human trials described on this page.
Alpha-Pinene and Peripheral Insulin Sensitization
A second cumin mechanism is the peripheral insulin-sensitizing effect of alpha-pinene, one of the minor essential-oil monoterpenes in cumin (and a major one in pine and rosemary). In a 2024 study in mouse muscle cells (C2C12), alpha-pinene, tested as a main component of pine essential oil, increased transcription of the Glut4 gene, which raised the amount of the GLUT4 glucose transporter produced and its presence at the cell membrane — the authors describe this as emulating insulin's effect on GLUT4. GLUT4 is the same downstream target as exercise-mediated glucose uptake.
The effect size from alpha-pinene alone is modest, and cumin contains only small quantities of alpha-pinene compared to dedicated alpha-pinene sources like rosemary essential oil or fresh pine needle tea.
The cumin + cinnamon combination, common in Middle Eastern cooking and sometimes recommended in integrative medicine for pre-diabetes, leverages both mechanisms: cumin contributes the alpha-glucosidase inhibition and the alpha-pinene effect; cinnamon contributes its proanthocyanidin-mediated insulin receptor sensitization.
Cuminaldehyde and Advanced Glycation End-Products
Long-term hyperglycemia drives the formation of advanced glycation end-products (AGEs) — covalent adducts formed when glucose reacts non-enzymatically with the free amino groups of proteins (lysine, arginine) and nucleic acids. AGEs accumulate in collagen, basement membranes, and crystallin (the lens protein), contributing to diabetic complications including nephropathy, retinopathy, neuropathy, atherosclerosis, and the protein-cross-link aspect of aging itself. AGE production is the molecular basis for the well-known clinical association between sustained hyperglycemia and the macrovascular and microvascular complications of diabetes.
Jagtap and Patil 2010 specifically measured AGE suppression as a primary endpoint, finding that Cuminum cyminum extract significantly reduced AGE formation in STZ-diabetic rats even at glucose levels where AGEs would be expected to accumulate. The proposed mechanism is direct trapping of reactive carbonyl intermediates (methylglyoxal, glyoxal, 3-deoxyglucosone) by cuminaldehyde and the other essential-oil aldehydes, plus the radical-scavenging activity of the phenolic antioxidant fraction. The clinical implication is potentially important: even if cumin's glucose-lowering effect were modest, an additional AGE-suppressing effect could provide complication-prevention value above and beyond what hemoglobin A1c alone would predict.
This is currently a preclinical observation only — no human trial has measured AGE formation as a primary endpoint with cumin supplementation. But the mechanism is biologically plausible and the rat data are robust enough to warrant the trial. For more on the related diabetic complication mechanisms, see our Diabetes page.
Clinical Positioning in Pre-Diabetes and Type 2 Diabetes
Realistic positioning of cumin in glycemic management requires honesty about effect sizes:
- Healthy adults with normal glucose — cumin produces no measurable harm and no clear glycemic benefit. The case for daily cumin use here is general (digestive, antioxidant, iron content) not glycemic.
- Pre-diabetes (fasting glucose 100–125 mg/dL or hemoglobin A1c 5.7–6.4%) — the human trials did not select people by prediabetes: they enrolled overweight adults (Taghizadeh 2016), overweight and obese women (Zare 2014), people with metabolic syndrome (Morovati 2019) and people with type 2 diabetes (Jafari 2017). Cumin is a cheap kitchen spice. The trials in overweight adults showed modest weight loss and better insulin-sensitivity indices, an inconsistent effect on fasting glucose (Taghizadeh 2016 positive; Zare 2014 and Morovati 2019 null), and nothing at all on long-term outcomes. No trial has compared cumin with metformin: metformin has decades of outcome data behind it, while cumin's human trials are short and measure surrogate endpoints such as fasting glucose and insulin.
- Type 2 diabetes — the one trial in people with type 2 diabetes (Jafari 2017) tested cumin essential oil for 8 weeks; fasting blood sugar, HbA1c and insulin fell in both cumin groups and rose in the placebo group. No trial has tested cumin as a replacement for standard care (metformin, lifestyle, the glucagon-like peptide-1 (GLP-1) agonist class).
- Type 1 diabetes — cumin has no role as primary therapy. It will not replace insulin and the AGE-trapping mechanism, while theoretically attractive, has not been clinically demonstrated in type 1 diabetes.
For more on integrated approaches to blood sugar control, see our Blood Sugar Control page and the various lifestyle interventions (continuous glucose monitoring on CGM, time-restricted eating, resistance training).
Dosing and Forms for Glycemic Use
- Whole seeds (jeera pani / cumin water) — 1–2 teaspoons (5–10 g) whole seeds soaked overnight in 300 ml room-temperature water; traditionally drunk in the morning on an empty stomach. This is the canonical traditional preparation and provides full essential-oil extraction. See our Digestive Aid deep-dive for the full protocol.
- Ground cumin powder taken with food — 1 ½ – 2 teaspoons (3 g) daily, divided across two meals, taken with yogurt or as a generous seasoning on prepared meals. This is the dose used in the Zare 2014 trial — which improved lipids and body composition but, on its own account, did not change fasting blood sugar. The one human trial that did move fasting glucose used 150 mg/day of encapsulated cumin with lime, so no human trial actually supports 3 g/day as a glycemic dose. The alpha-glucosidase mechanism gives a theoretical reason for taking it before a meal: the enzyme acts on carbohydrate as it is digested, so the cumin would need to reach the small intestine (duodenum) before the carbohydrate does.
- Cumin essential oil (concentrated) — not the canonical glycemic preparation. The human trials used 50 or 100 mg/day (Jafari 2017, type 2 diabetes) and 75 mg three times daily (Morovati 2019, metabolic syndrome). Higher doses risk hepatotoxicity and photosensitivity.
- Cumin extract capsules — standardized products are available providing the equivalent of approximately 3 g whole seed per day in capsule form. Convenient but more expensive than buying whole seeds at the grocery store.
- Adjuncts — the cumin + cinnamon combination is described in integrative-medicine writing as additive for insulin sensitization; no human study of the combination was found. The cumin + fenugreek combination is traditional in Ayurveda for diabetes and has its own modest trial evidence.
Cautions and Hypoglycemia Risk
- Hypoglycemia risk in patients on sulfonylureas or insulin — any glucose-lowering effect of cumin adds to that of these medications, and low blood sugar (hypoglycemia) is the risk of that combination; the type 2 diabetes trial that reported falls in fasting blood sugar used 50 or 100 mg/day of cumin essential oil (Jafari 2017). Metformin coadministration carries less hypoglycemia risk because metformin alone rarely causes hypoglycemia.
- Surgery — procedures that require perioperative glucose management (e.g., cardiac surgery, transplant surgery) run on glucose-control protocols, and medicinal-dose cumin is an unpredictable added glucose-lowering factor in them.
- Pregnancy with gestational diabetes — culinary quantities are safe; concentrated supplemental doses are not adequately studied in pregnancy, and none of the human trials described on this page tested cumin in pregnant women or in gestational diabetes.
- Apiaceae cross-allergy — rare but real. People with known allergy to carrot, celery, fennel, anise, or coriander, plants of the same family, are the group at risk of reacting to cumin.
- Children — culinary cumin is safe in children. Medicinal-dose supplementation (3 g/day for glycemic purposes) is not adequately studied in pediatric populations; the human trials described on this page enrolled adults.
Key Research Papers
- Jagtap AG, Patil PB (2010). Antihyperglycemic activity and inhibition of advanced glycation end product formation by Cuminum cyminum in streptozotocin induced diabetic rats. Food and Chemical Toxicology 48(8-9):2030-2036. Animal. — PubMed PMID: 20451573
- Taghizadeh M, Memarzadeh MR, Abedi F, et al. (2016). The effect of Cumin cyminum L. plus lime administration on weight loss and metabolic status in overweight subjects: a randomized double-blind placebo-controlled clinical trial. Iranian Red Crescent Medical Journal 18(8):e34212. Human RCT, n=72, 150 mg/day. — PubMed PMID: 27781121
- Taghizadeh M, Memarzadeh MR, Asemi Z, Esmaillzadeh A (2015). Effect of the Cumin cyminum L. intake on weight loss, metabolic profiles and biomarkers of oxidative stress in overweight subjects: a randomized double-blind placebo-controlled clinical trial. Annals of Nutrition and Metabolism 66(2-3):117-124. Human RCT. — PubMed PMID: 25766448 — Expression of concern (Ann Nutr Metab 2023: PubMed PMID: 37334987)
- Zare R, Heshmati F, Fallahzadeh H, Nadjarzadeh A (2014). Effect of cumin powder on body composition and lipid profile in overweight and obese women. Complementary Therapies in Clinical Practice 20(4):297-301. Human RCT, 3 g/day — improved lipids and body composition; explicitly reported NO effect on fasting blood sugar. — PubMed PMID: 25456022
- Morovati A, Pourghassem Gargari B, Sarbakhsh P (2019). Effects of cumin (Cuminum cyminum L.) essential oil supplementation on metabolic syndrome components: a randomized, triple-blind, placebo-controlled clinical trial. Phytotherapy Research 33(12):3261-3269. Human RCT — NEGATIVE: no effect on any metabolic-syndrome component, glucose included, except diastolic blood pressure. — PubMed PMID: 31478290
- Jafari S, Sattari R, Ghavamzadeh S (2017). Evaluation the effect of 50 and 100 mg doses of Cuminum cyminum essential oil on glycemic indices, insulin resistance and serum inflammatory factors on patients with diabetes type II: a double-blind randomized placebo-controlled clinical trial. Journal of Traditional and Complementary Medicine 7(3):332-338. Human RCT in type 2 diabetes, three groups of 33. — PubMed PMID: 28725629
- Karimian J, Farrokhzad A, Jalili C (2021). The effect of cumin (Cuminum cyminum L.) supplementation on glycemic indices: a systematic review and meta-analysis of randomized controlled trials. Phytotherapy Research 35(8):4127-4135. Meta-analysis, 8 RCTs, 552 participants — no significant effect on fasting blood sugar. — PubMed PMID: 33720457
- Tavakoli-Rouzbehani OM, Faghfouri AH, Anbari M, et al. (2021). The effects of Cuminum cyminum on glycemic parameters: a systematic review and meta-analysis of controlled clinical trials. Journal of Ethnopharmacology 281:114510. Meta-analysis, 8 studies — significant falls in fasting blood sugar and HbA1c. — PubMed PMID: 34371114
- Lee HS (2005). Cuminaldehyde: aldose reductase and alpha-glucosidase inhibitor derived from Cuminum cyminum L. seeds. Journal of Agricultural and Food Chemistry 53(7):2446-2450. In vitro. — PubMed PMID: 15796577
- Feriotto G, Tagliati F, Costa V, et al. (2024). α-Pinene, a main component of Pinus essential oils, enhances the expression of insulin-sensitive glucose transporter type 4 in murine skeletal muscle cells. International Journal of Molecular Sciences 25(2):1252. In vitro (mouse cells). — PubMed PMID: 38279251
- Patil SB, Takalikar SS, Joglekar MM, Haldavnekar VS, Arvindekar AU (2013). Insulinotropic and β-cell protective action of cuminaldehyde, cuminol and an inhibitor isolated from Cuminum cyminum in streptozotocin-induced diabetic rats. British Journal of Nutrition 110(8):1434-1443. Animal. — PubMed PMID: 23507295
- Dhandapani S, Subramanian VR, Rajagopal S, Namasivayam N (2002). Hypolipidemic effect of Cuminum cyminum L. on alloxan-induced diabetic rats. Pharmacological Research 46(3):251-255. Animal. — PubMed PMID: 12220968
- Bamosa AO, Kaatabi H, Lebdaa FM, et al. (2010). Effect of Nigella sativa seeds on the glycemic control of patients with type 2 diabetes mellitus. Indian Journal of Physiology and Pharmacology 54(4):344-354. Human — black cumin, a different plant. — PubMed PMID: 21675032
- Kaatabi H, Bamosa AO, Badar A, et al. (2015). Nigella sativa improves glycemic control and ameliorates oxidative stress in patients with type 2 diabetes mellitus: placebo controlled participant blinded clinical trial. PLoS ONE 10(2):e0113486. Human — black cumin, a different plant. — PubMed PMID: 25706772