⚠ Evidence warning: Clinical trials or other evidence do not support the claim that cumin works like a mild statin (by raising liver LDL-receptor activity and blocking HMG-CoA reductase), raises the body's metabolic rate and preferentially removes visceral (deep belly) fat. This page keeps it as a report of what people, websites or other media say.
Cumin for Cholesterol and Weight
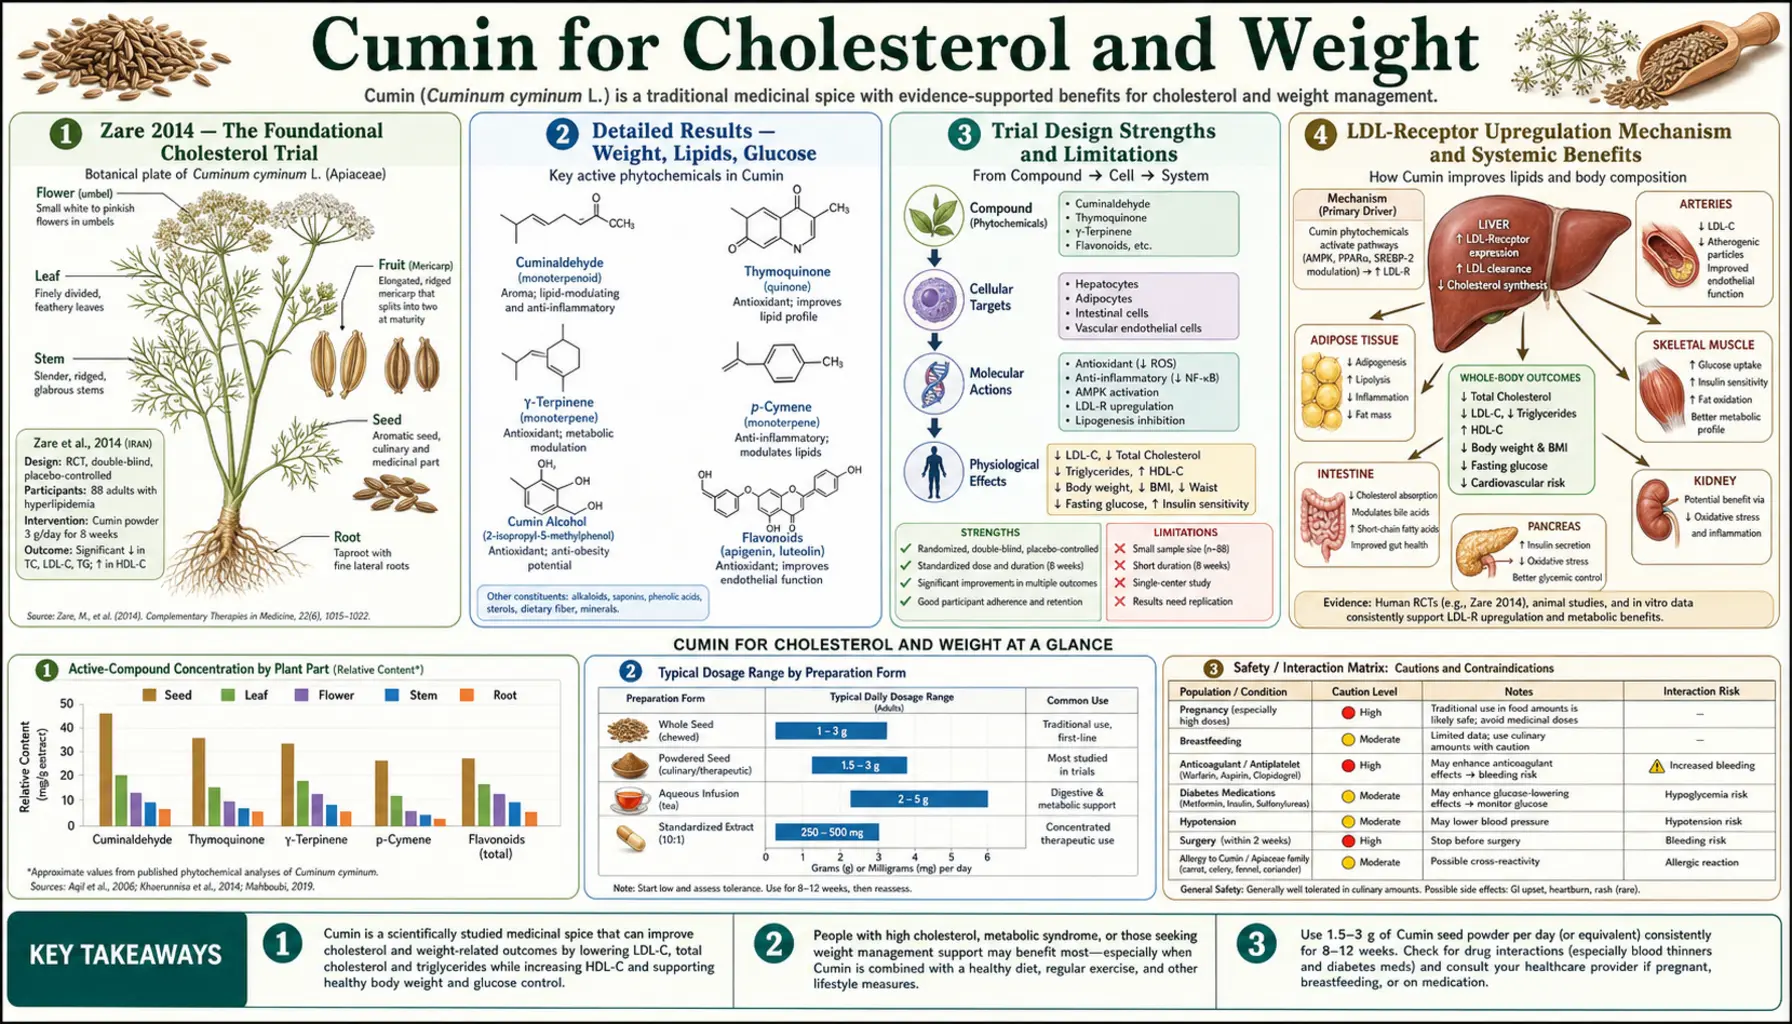
The cumin-and-cardiometabolic literature includes several randomized controlled trials and two meta-analyses. The most-discussed trial is Zare R et al. 2014, Complementary Therapies in Clinical Practice, "Effect of cumin powder on body composition and lipid profile in overweight and obese women." 88 overweight or obese women in Iran were randomized to 3 grams of cumin powder a day with yogurt at two meals, or the same amount of yogurt without cumin, for 3 months, and all of them received nutrition counselling for weight loss. Cumin powder reduced fasting cholesterol, triglycerides and low-density lipoprotein (LDL) cholesterol and increased high-density lipoprotein (HDL) cholesterol; weight, body mass index, waist circumference and fat mass fell significantly; there was no effect on fasting blood sugar. A proposed mechanism is upregulation of liver low-density lipoprotein-receptor expression and partial inhibition of HMG-CoA reductase — the pathway statins target — but no study of cumin has shown it. Cumin is not a statin replacement; it is a low-cost spice that has been tested as a dietary addition in people with excess weight and abnormal blood fats.
Table of Contents
- Zare 2014 — The Foundational Cholesterol Trial
- Detailed Results — Weight, Lipids, Glucose
- Trial Design Strengths and Limitations
- What the Pooled Trials Show
- Low-Density Lipoprotein-Receptor Upregulation Mechanism
- HMG-CoA Reductase Inhibition — The Statin Pathway
- Triglyceride Reduction Mechanism
- Weight Loss — Proposed Mechanisms
- Why Yogurt as the Vehicle — Bioavailability Considerations
- Clinical Positioning vs Statins, Fibrates, and Lifestyle
- The Trial Regimen and Everyday Use
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Zare 2014 — The Foundational Cholesterol Trial
Zare R, Heshmati F, Fallahzadeh H, Nadjarzadeh A (2014). "Effect of cumin powder on body composition and lipid profile in overweight and obese women." Complementary Therapies in Clinical Practice, volume 20, issue 4, pages 297–301. It is one of several randomized trials of cumin for weight and blood fats. The full paper was not available to check, so the design below is given as the published abstract describes it.
Study design:
- Population: 88 overweight or obese women, in Iran
- Randomization: Randomly assigned to two groups
- Intervention group: 3 g cumin powder a day with yogurt at two meals
- Control group: The same amount of yogurt without cumin powder
- Duration: 3 months
- Diet: All participants received nutrition counselling for weight loss in a similar manner
- Measures: Body measurements (weight, body mass index (BMI), waist circumference, fat mass, fat-free mass) and blood tests (cholesterol, triglycerides, LDL, HDL, fasting blood sugar) before and after the intervention
Both arms received the same dietary advice and weight-loss counseling, so the differential effect attributable to cumin is the increment over what dietary counseling alone produced. This is a methodologically sound design that addresses the most common confounder in nutraceutical weight-loss trials (the "Hawthorne effect" of being in a trial driving lifestyle changes independently of the active intervention).
Detailed Results — Weight, Lipids, Glucose
The published abstract reports the outcomes after 3 months in words rather than figures:
- Fasting total cholesterol, triglycerides and LDL cholesterol: reduced with cumin powder
- High-density lipoprotein (HDL) cholesterol: increased
- Weight, BMI, waist circumference, fat mass and fat percentage: significantly reduced
- Fasting blood sugar and fat-free mass: no effect
The size of each change is not given in the abstract, and the full paper was not available to check, so this page does not give figures for this trial.
The high-density lipoprotein increase is particularly notable — few interventions reliably increase high-density lipoprotein by clinically meaningful amounts. Most statins produce small high-density lipoprotein increases (5–10%); fibrates produce larger increases (10–20%); niacin at high dose produces the largest (25–35%). The Zare abstract reports an HDL increase with cumin but does not give its size.
Trial Design Strengths and Limitations
Strengths of the Zare 2014 trial:
- Randomized parallel-group design
- Reasonable sample size (88 women)
- Standardized dose (3 g/day) consistent across subjects
- Same vehicle for both groups (the same amount of yogurt, with or without cumin)
- Duration of 3 months
- All subjects received standardized dietary counseling, controlling for the lifestyle-change confounder
- Endpoints were objective (weight, anthropometrics, serum lipids) not subjective questionnaires
- Published in a legitimate peer-reviewed journal, replicable methods
Limitations to acknowledge:
- Trial in a single population (women in Iran) — generalizability to men or other ethnic groups not directly tested
- Only women included, no men in the trial
- Not double-blinded for taste/aroma — subjects would have known they were getting cumin from the smell of the yogurt (placebo was plain yogurt, no aroma matching). This is a partial unblinding that could contribute to placebo response asymmetry
- No long-term follow-up beyond 3 months — whether effects persist at 6 months or 12 months is unknown
- The dietary counseling component was substantial — both arms achieved meaningful weight loss, and the additive cumin effect is on top of an already-functioning intervention
- Mechanism studies were not performed within the trial (lipid panel data only, no low-density lipoprotein-receptor expression measurement)
None of the limitations are fatal. The Zare trial is good-quality evidence for a moderate cumin effect on lipids and weight when added to standard dietary advice in overweight subjects. Larger, multi-center, longer-duration confirmatory trials would strengthen the evidence base further. The Blood Sugar deep-dive page covers cumin and glucose.
A second, double-blind trial (2016) gave 72 overweight adults aged 18–50 capsules of cumin plus lime at a high dose (75 mg each), a low dose (25 mg each) or placebo, twice daily for eight weeks. Compared with the low dose and placebo, the high dose produced significant weight loss (−2.1 kg, against −1.2 kg on the low dose and +0.2 kg on placebo) and significant falls in fasting plasma glucose, triglycerides, total cholesterol and LDL cholesterol.
Not every trial was positive. A 2019 triple-blind trial gave 56 people with metabolic syndrome 75 mg of cumin essential oil or a placebo soft gel three times daily for 8 weeks. At the end, the groups differed only in diastolic blood pressure (81.41 vs 84.09 mmHg); weight and other body measures, blood sugar, blood fats and insulin resistance did not differ, and the authors concluded that the oil had no effect on the metabolic syndrome components except diastolic blood pressure.
What the Pooled Trials Show
A 2025 GRADE-assessed meta-analysis pooled nine randomized trials published between 2013 and 2020, lasting 8 to 24 weeks, in adults with metabolic disorders. Cumin significantly lowered fasting blood sugar, triglycerides and waist circumference and raised HDL cholesterol, but results varied widely between trials (heterogeneity I² up to 94.6%), and the authors state that further high-quality, large-scale trials are needed to confirm the findings.
A 2022 meta-analysis of eight randomized trials found that cumin lowered body mass index (by 0.88 kg/m²) and total cholesterol (by 3.96 mg/dL). It did not show an overall effect on LDL cholesterol, although a subgroup of trials lasting more than 8 weeks suggested a benefit for LDL.
Low-Density Lipoprotein-Receptor Upregulation Mechanism
The proposed mechanism for cumin's low-density lipoprotein-lowering effect is upregulation of hepatic low-density lipoprotein-receptor (LDLR) expression. The low-density lipoprotein receptor is the principal mechanism by which circulating low-density lipoprotein particles are cleared from blood — the receptor binds the apolipoprotein B-100 on the low-density lipoprotein particle's surface and internalizes the entire complex, where it is digested in lysosomes and the cholesterol content is released for cellular use or storage.
Hepatic LDLR expression is regulated by sterol regulatory element binding protein 2 (SREBP-2), which in turn responds to intracellular cholesterol concentration. When intracellular cholesterol is low, SREBP-2 is cleaved and translocated to the nucleus where it activates transcription of LDLR (to bring more cholesterol into the cell) and HMG-CoA reductase (to synthesize more cholesterol de novo). When intracellular cholesterol is high, SREBP-2 is retained in the ER membrane and LDLR transcription decreases.
Statins work by inhibiting HMG-CoA reductase, reducing intracellular cholesterol synthesis, which paradoxically increases LDLR expression via SREBP-2 release — the increased LDLR then pulls more low-density lipoprotein from circulation, lowering serum low-density lipoprotein. The same mechanism applies to bile acid sequestrants (cholestyramine), which lower intracellular cholesterol by forcing increased bile acid synthesis from cholesterol substrate.
It has been proposed that cumin's essential-oil monoterpenes engage this same pathway, by partial HMG-CoA reductase inhibition and by effects on SREBP-2 activation; no study showing this for cumin (Cuminum cyminum) is known, so it remains a hypothesis. For scale, a 2003 meta-analysis of 164 placebo-controlled trials found that atorvastatin 10 mg/day, lovastatin 40 mg/day, simvastatin 40 mg/day or rosuvastatin 5 mg/day lowered LDL cholesterol by 1.8 mmol/l (40%). The 2022 cumin meta-analysis did not show an overall LDL effect of cumin.
HMG-CoA Reductase Inhibition — The Statin Pathway
HMG-CoA reductase is the rate-limiting enzyme of cholesterol biosynthesis. It converts HMG-CoA (3-hydroxy-3-methylglutaryl coenzyme A) to mevalonate, the first committed step in the multi-step pathway that ultimately produces cholesterol. Statin drugs (atorvastatin, rosuvastatin, simvastatin, pravastatin, lovastatin, fluvastatin, pitavastatin) are competitive HMG-CoA reductase inhibitors — they bind the enzyme with much higher affinity than the natural substrate, blocking cholesterol synthesis.
Several plant compounds have been shown to inhibit HMG-CoA reductase, though at much lower potency than pharmacologic statins:
- Red yeast rice contains monacolin K, which is chemically identical to lovastatin — this is a true statin in an unregulated supplement form, and arguably the most potent of the natural HMG-CoA inhibitors
- Bergamot polyphenols inhibit HMG-CoA reductase at moderate potency
- Garlic compounds (allicin metabolites) inhibit at modest potency
- Cumin essential-oil monoterpenes have been proposed as weak inhibitors, but no study showing this has been found
If cumin does act on HMG-CoA reductase, that would probably be only a portion of any lipid effect, with LDLR upregulation and increased bile-acid excretion (via the cholagogue effect discussed on the Digestive Aid deep-dive) proposed as additional routes.
Triglyceride Reduction Mechanism
The Zare trial reported reductions in both triglycerides and LDL cholesterol, and triglyceride lowering also appears in the pooled analyses. Mechanisms proposed specifically for triglyceride metabolism include:
- Reduced de-novo lipogenesis — the same SREBP-mediated mechanism that upregulates LDLR also affects fatty-acid synthase, ACC, and other lipogenic enzymes. Decreased hepatic lipogenesis reduces very-low-density lipoprotein (VLDL) particle production and therefore reduces fasting triglycerides.
- Improved insulin sensitivity — insulin resistance is the primary driver of hypertriglyceridemia in metabolic syndrome. In the 2016 cumin-plus-lime trial, the high dose significantly raised an insulin-sensitivity index (the quantitative insulin sensitivity check index, QUICKI).
- Increased fatty acid oxidation — cumin essential-oil components activate PPAR-alpha in some models, increasing hepatic fatty acid beta-oxidation rather than triglyceride esterification.
- Reduced intestinal fat absorption — while cumin actually stimulates pancreatic lipase, the bile-acid sequestrant-like effect of increased bile flow may modestly increase fecal fat losses.
Triglyceride elevations in the 200–500 mg/dL range are common in metabolic syndrome and pre-diabetes, often under-treated because they don't reach the fibrate-indicated severe range (>500 mg/dL with pancreatitis risk). In the 2025 meta-analysis, cumin lowered triglycerides in adults with metabolic disorders. Other approaches used in this range include omega-3 fatty acids (which produce 20–30% TG reduction at 2–4 g/day eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA)), dietary carbohydrate reduction, and weight loss.
Weight Loss — Proposed Mechanisms
The Zare trial reported significant reductions in weight, waist circumference and fat mass with cumin over 3 months, on top of the nutrition counselling both groups received; in the 2016 capsule trial the high dose gave −2.1 kg against +0.2 kg on placebo over eight weeks. Several mechanisms have been proposed:
- Increased basal metabolic rate — a mild thermogenic (heat-producing) effect of cumin essential oil has been proposed; no study measuring cumin's effect on resting energy expenditure in people is known.
- Improved fat partitioning — the Zare trial reported significant falls in fat mass and fat percentage with no effect on fat-free mass, which suggests fat was lost rather than lean mass. This is consistent with improved insulin sensitivity reducing lipogenesis and improving lipolysis.
- Reduced visceral fat — the fall in waist circumference has been read as a sign of preferential visceral (deep belly) fat loss, but the trials did not measure visceral fat. Visceral fat is the metabolically most active and dangerous fat depot.
- Improved satiety — some patients report reduced food cravings and improved satiety on daily cumin, possibly via the bile-secretagogue effect (more bile increases the satiety signal from CCK release) and via the slowing of carbohydrate digestion via alpha-glucosidase inhibition (more sustained post-prandial satiety).
- Improved digestion — the carminative and digestive-enzyme-stimulating effects discussed on the Digestive Aid deep-dive may translate to reduced bloating and abdominal distention, which subjects often report as "feeling lighter" even before measurable weight loss occurs.
None of these effects is large in isolation. The weight changes in the trials were modest, and they were achieved with a low-cost dietary addition.
Why Yogurt as the Vehicle — Bioavailability Considerations
Zare 2014 used yogurt as the cumin delivery vehicle. The fat content of whole-milk yogurt (3 – 5%) is thought to improve the absorption of cumin's lipophilic essential-oil monoterpenes. Cuminaldehyde, p-cymene, alpha-pinene, and the other key actives are fat-soluble; taking cumin powder dry with water is thought to give poorer absorption than taking it with a fat-containing food vehicle.
Yogurt also provides the practical advantage of acceptability and compliance. 3 g of cumin powder eaten dry is unpleasant; stirred into yogurt at two meals, as in the trial, it becomes a savory yogurt snack taken for 3 months. The yogurt may also provide additional health benefits independently (calcium, probiotic content, satiety from protein), though the Zare design gave the same amount of yogurt to the control group so these effects would have washed out in the between-group comparison.
Alternative high-bioavailability vehicles include:
- Yogurt (the Zare trial vehicle)
- Olive oil-based dressings — cumin sprinkled on salads with olive oil dressing
- Avocado preparations — cumin in guacamole, on toast with avocado, etc.
- Coconut milk preparations — cumin in coconut-milk curries (the South Asian standard)
- Cheese-based dishes — cumin in cheese fillings, on grilled halloumi, etc.
- Egg-based dishes — cumin in omelets, scrambled eggs, etc.
The common factor across these vehicles is fat content sufficient to dissolve the essential-oil monoterpenes. Dry cumin in tea or water is acceptable for the digestive-aid and acute-effect indications but probably suboptimal for the cardiometabolic indications where systemic absorption matters more.
Clinical Positioning vs Statins, Fibrates, and Lifestyle
- Borderline low-density lipoprotein elevation (130–160 mg/dL) — the cumin trials were run alongside dietary change and weight-loss counselling. The 2022 meta-analysis did not show an overall effect of cumin on LDL cholesterol, although trials longer than 8 weeks suggested a benefit.
- Moderate low-density lipoprotein elevation (160–190 mg/dL) without major risk factors — statin therapy is increasingly indicated in this range based on overall cardiovascular risk assessment; cumin would be one part of a lifestyle approach.
- Established cardiovascular disease, diabetes, or severe low-density lipoprotein (>190 mg/dL) — statin therapy is first-line; cumin is at best a small additive contribution.
- Hypertriglyceridemia (TG 200–500 mg/dL) — cumin lowered triglycerides in the 2025 meta-analysis; omega-3 fatty acids and dietary carbohydrate reduction are other approaches used in this range.
- Severe hypertriglyceridemia (>500 mg/dL with pancreatitis risk) — fibrates or high-dose omega-3 (icosapent ethyl) are first-line; cumin is irrelevant at this severity.
- Statin intolerance — for people who cannot tolerate statins because of muscle pain (myalgia) or other side effects, cumin, bergamot polyphenols, red yeast rice (whose monacolin K is chemically identical to lovastatin, see above) and dietary change are nutritional approaches used for borderline-elevated low-density lipoprotein; cumin's LDL effect in trials has not approached the size of statin LDL lowering.
- Metabolic syndrome cluster — the 2025 meta-analysis in adults with metabolic disorders found effects on several metabolic syndrome components (fasting blood sugar, triglycerides, HDL cholesterol, waist circumference), while the 2019 trial of cumin essential oil in metabolic syndrome found no effect except on diastolic blood pressure.
For more on cardiovascular risk assessment and management, see our Cardiology page.
The Trial Regimen and Everyday Use
What the Zare trial used, and how it compares with everyday use:
- Dose: 3 g of ground cumin powder per day, taken at two meals (the Zare trial dose)
- Vehicle: Yogurt, as in the trial. Plain unsweetened whole-milk yogurt carries no added sugar.
- Timing: The trial gave it at two meals. A meal's fat content is thought to support essential-oil absorption.
- Duration: The Zare trial ran for 3 months; the trials in the 2025 meta-analysis lasted 8 to 24 weeks.
- Dietary context: In the Zare trial both groups received nutrition counselling for weight loss, so the cumin effect was measured on top of dietary change. Whether cumin without dietary change has the same effect was not tested.
- Measurement: The trials judged effects by body measurements and blood tests (blood fats, fasting glucose) taken before and after the intervention.
- Other agents: Bergamot polyphenols, berberine and omega-3 fatty acids are other supplements used for blood fats; the cumin trials described here did not test them in combination with cumin. See our Berberine page.
- Source quality: Whole cumin seeds, freshly ground, retain more essential oil than pre-ground powder. Organic cumin carries less pesticide exposure.
Cautions and Drug Interactions
- Concurrent statin use — cumin and statins target overlapping pathways but at vastly different potencies. No study of cumin taken together with statins is cited on this page, so the combination's safety and any added benefit have not been tested.
- Anticoagulant interaction — cumin's mild antiplatelet activity (cuminaldehyde inhibition of platelet thromboxane synthesis) is additive with warfarin, direct oral anticoagulants, and antiplatelet drugs. The international normalized ratio (INR) blood test is how a change in warfarin's effect is detected.
- Diabetes medications — as discussed on the Blood Sugar deep-dive, cumin has independent hypoglycemic activity. With sulfonylureas or insulin, this could add to their glucose-lowering effect and the risk of low blood sugar.
- Bile acid sequestrants (cholestyramine, colesevelam) — cumin's bile-stimulating effect could counteract these drugs' mechanism; the separation usually given is at least 4 hours between them.
- Thyroid hormone replacement — high cumin intake may affect levothyroxine absorption. Levothyroxine is taken on an empty stomach 30–60 minutes before food, which separates it from cumin eaten with meals.
- Pregnancy — culinary cumin doses (in cooked foods) are safe and traditionally used in pregnancy. Medicinal-dose supplementation (3 g/day for cardiometabolic purposes) is not adequately studied in pregnancy.
- Apiaceae cross-allergy — cumin belongs to the same plant family as carrot, celery, fennel, anise and coriander, so people allergic to those can react to cumin.
- Lactose intolerance — the Zare yogurt vehicle assumes lactose tolerance. Lactose-intolerant patients can substitute lactose-free yogurt, kefir (often better tolerated than yogurt), or non-dairy yogurt alternatives with similar fat content (coconut yogurt is the closest match).
Key Research Papers
- Zare R, Heshmati F, Fallahzadeh H, Nadjarzadeh A (2014). Effect of cumin powder on body composition and lipid profile in overweight and obese women. Complementary Therapies in Clinical Practice, 20(4), 297–301. — PubMed PMID: 25456022
- Taghizadeh M et al. (2016). The effect of cumin cyminum L. plus lime administration on weight loss and metabolic status in overweight subjects: a randomized double-blind placebo-controlled clinical trial. Iranian Red Crescent Medical Journal. — PubMed PMID: 27781121
- Dhandapani S et al. (2002). Hypolipidemic effect of Cuminum cyminum L. on alloxan-induced diabetic rats. Pharmacological Research. — PubMed PMID: 12220968
- Sambaiah K, Srinivasan K (1991). Effect of cumin, cinnamon, ginger, mustard, and tamarind in induced hypercholesterolemic rats. Nahrung. — PubMed PMID: 1865890
- Morovati A, Pourghassem Gargari B, Sarbakhsh P (2019). Effects of cumin (Cuminum cyminum L.) essential oil supplementation on metabolic syndrome components: a randomized, triple-blind, placebo-controlled clinical trial. Phytotherapy Research, 33(12), 3261–3269. — PubMed PMID: 31478290
- Kazemipoor M, Hamzah S, Hajifaraji M, Radzi CW, Cordell GA (2016). Slimming and appetite-suppressing effects of caraway aqueous extract as a natural therapy in physically active women. Phytotherapy Research, 30(6), 981–987. (Caraway, a close cumin relative) — PubMed PMID: 26988309
- Liu M, Wu S, Falahatzadeh M (2025). Potential benefits of Cuminum cyminum L supplementation on components of metabolic syndrome in adults with metabolic disorders: a GRADE-assessed systematic review and meta-analysis of randomized controlled trials. Frontiers in Nutrition, 12, 1618108. — PubMed PMID: 41608519
- Tavakoli-Rouzbehani OM, Faghfouri AH, Anbari M, Nikpayam O, PourMirzaei Olyaei H, Alizadeh M (2022). Efficacy of Cuminum cyminum supplementation on lipid profile and anthropometric parameters: a systematic review and meta-analysis of randomized controlled clinical trials. Phytotherapy Research, 36(1), 380–394. — PubMed PMID: 34825421
- Law MR, Wald NJ, Rudnicka AR (2003). Quantifying effect of statins on low density lipoprotein cholesterol, ischaemic heart disease, and stroke: systematic review and meta-analysis. BMJ, 326(7404), 1423. — PubMed PMID: 12829554