⚠ Evidence warning: Clinical trials or other evidence do not support the claim that cilantro or coriander, alone or with chlorella, removes mercury, lead and other metals from the body. This page keeps it as a report of what people, websites or other media say.
Coriander Seeds & Heavy Metal Chelation (Honest Evidence Review)
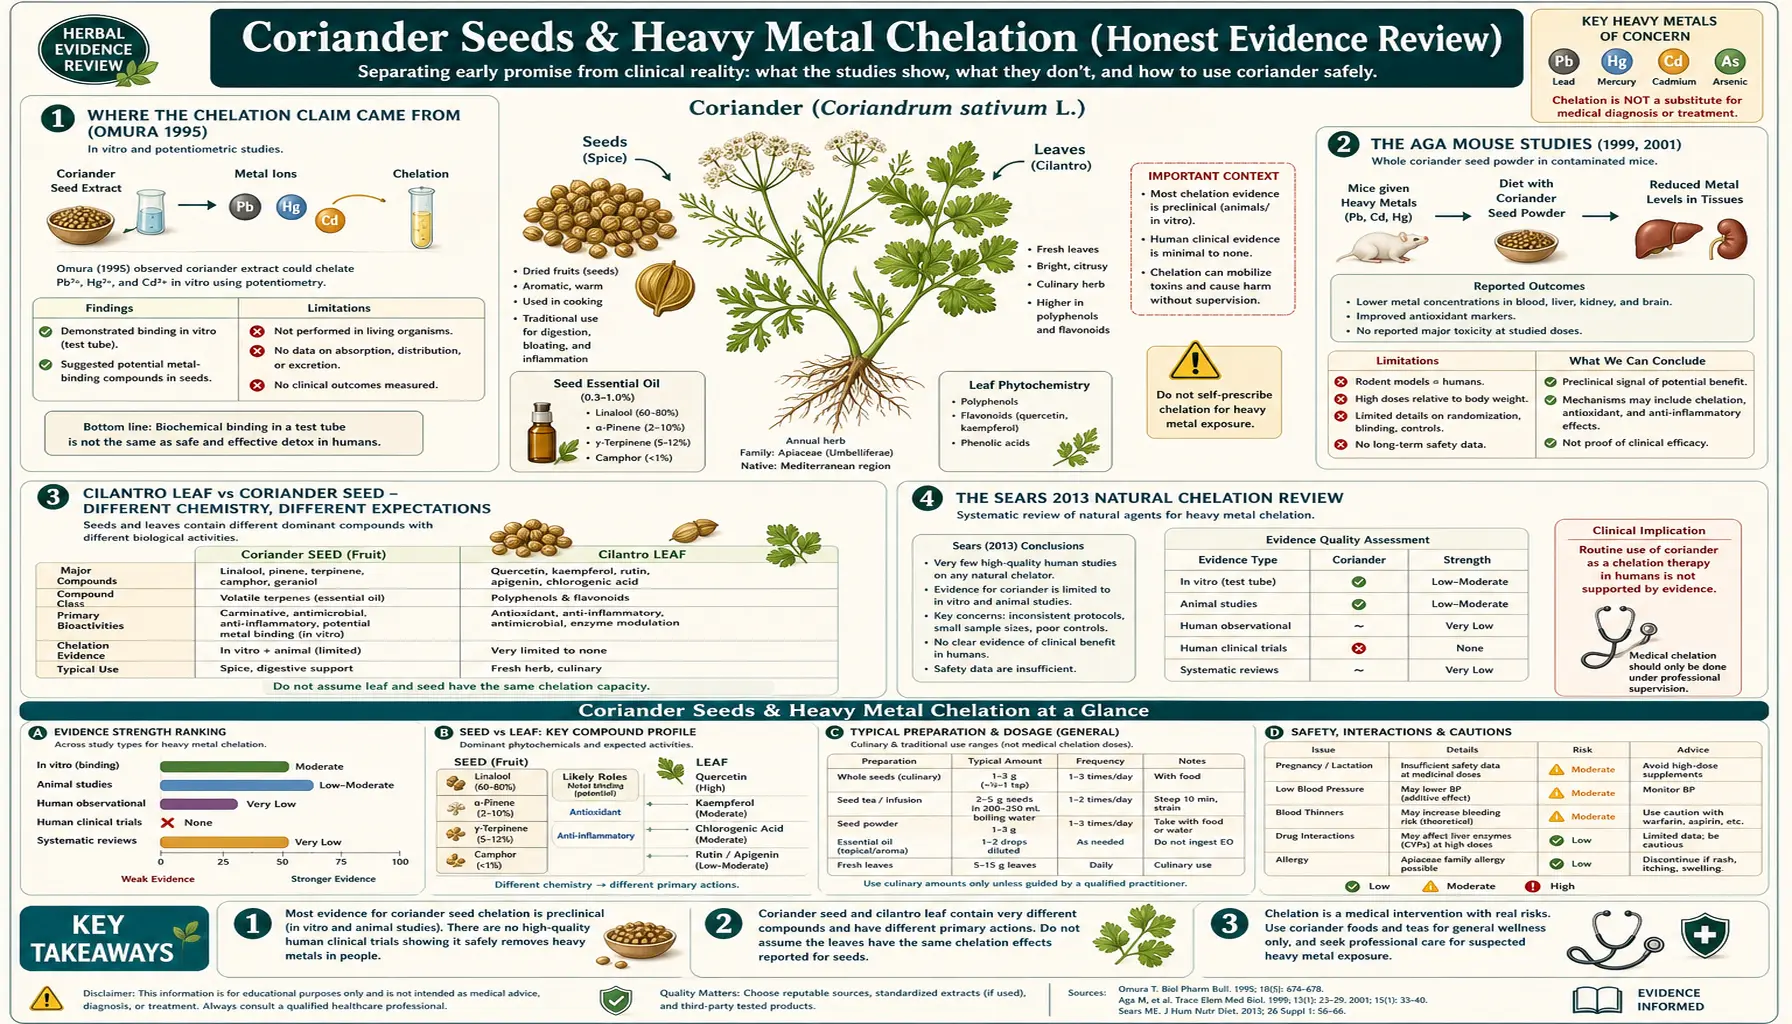
The claim that coriander (most often the leaf, sold as cilantro) chelates heavy metals — mercury, lead, aluminum, arsenic — and accelerates their excretion from the human body is one of the most widely circulated assertions in alternative medicine. It anchors many "natural detox" protocols, dental amalgam removal regimens, and post-vaccine "metal cleanses." The honest scientific reading is less dramatic. The original 1995 Omura report, on mercury deposits and resistant infections, is a small open case series with no control group stated in its abstract. The 2001 mouse study by Aga and colleagues is real, peer-reviewed, and worth taking seriously — it reports that coriander given during lead exposure reduced lead deposition in the thigh bone. The Sears 2013 review calls the evidence for cilantro limited and describes one trial in lead-exposed children aged 3 to 7, in which a cilantro extract did no better than placebo at raising lead excretion in urine. No head-to-head clinical trial of coriander versus standard chelator drugs for measured heavy-metal excretion in humans has been located. This deep-dive lays out exactly what the literature does and does not support, why cilantro leaf chemistry differs from coriander seed chemistry, and what role (if any) culinary coriander has within a documented heavy-metal-toxicity workup.
Table of Contents
- Where the Chelation Claim Came From (Omura 1995)
- The Aga Mouse Study (2001)
- Cilantro Leaf vs Coriander Seed — Different Chemistry
- The Sears 2013 Natural Chelation Review
- How Prescription Chelation Is Used and Measured (DMSA, DMPS, EDTA)
- The Coriander + Chlorella Combination Claim
- The "Provoked Urine Test" Trap
- When Heavy Metal Toxicity is Actually Documented
- What Coriander Is Genuinely Good For (Not Chelation)
- Safety Facts and Reported Concerns
- Key Research Papers
- Connections
- Featured Videos
Where the Chelation Claim Came From (Omura 1995)
The popular claim that cilantro / coriander chelates heavy metals can be traced largely to a 1995 case series by Yoshiaki Omura and S. L. Beckman published in the journal Acupuncture & Electro-Therapeutics Research. The paper's main subject is resistant infections. Its abstract (PubMed's copy is cut off, and the full text was not read for this page) says Omura, a Japanese physician practicing in New York, found mercury in his own organs, which he attributed to radioactive thallium-201 injected for a heart scan, and that the deposits cleared after he ate Vietnamese soup containing "Chinese parsley" (cilantro). The authors state that the herb speeds the loss of mercury, lead and aluminum in urine. They then gave people with Chlamydia trachomatis or herpes-family infections doxycycline or the fish oils EPA with DHA, plus Chinese parsley, and report that in 11 subjects given Chinese parsley tablets with drug uptake enhancement methods, the last traces of infection and symptoms disappeared. Deposits and infection sites were located with the "Bi-Digital O-Ring Test".
Popular accounts tie the paper to patients having dental amalgam fillings removed, describing elevated urinary mercury for several weeks and faster excretion once cilantro was added to the diet. The Sears 2013 review also mentions a soup reported to enhance mercury excretion after amalgam removal. The available abstract does not mention amalgam and states no urinary figures.
The "Bi-Digital O-Ring Test" is a form of applied kinesiology / muscle testing; mainstream diagnostic medicine does not use it, and its reproducibility under blinded conditions has not been established. The abstract describes no control group, no blinding and no pre-specified outcome measures, in a small, mixed group of patients. Urinary mercury excretion varies from day to day with hydration, recent fish intake and prior amalgam disturbance. The paper appeared in an acupuncture research journal rather than a toxicology journal.
The Omura paper was widely cited in the alternative-medicine community as foundational evidence for cilantro chelation. It was integrated into the Cutler protocol for chronic mercury toxicity, into the popular Klinghardt protocol for dental amalgam removal, and into countless "natural detox" books and websites. The claim escaped into the mainstream wellness culture and is now widely repeated in social media and consumer health content, usually without mention that the primary evidence is a single open case series.
The Aga Mouse Study (2001)
More credible evidence exists in a peer-reviewed mouse study by Aga and colleagues published in Journal of Ethnopharmacology in 2001. It is a real laboratory experiment with proper controls, blinded measurements of tissue metal content, and published in a mainstream pharmacology / toxicology venue.
The 2001 study examined male ICR mice given lead acetate in their drinking water for 32 days. Chinese parsley (Coriandrum sativum) was given by stomach tube for 25 days, from day 7 of the lead exposure to the end, and meso-2,3-dimercaptosuccinic acid (DMSA), a chelating drug, served as the positive control. The mice were then sacrificed and lead distribution was compared. Headline findings:
- Lead reached its highest concentration in the femur (thigh bone). DMSA and Chinese parsley each significantly decreased lead deposition there; the abstract gives no size comparison between them
- Chinese parsley also significantly decreased severe lead-induced kidney injury and lowered urinary delta-aminolevulinic acid, a marker that rises with lead intake
- The authors attribute the effect to "chelation of lead by some substances contained in Chinese parsley". The idea that coriander works better before lead exposure, by interfering with intestinal absorption, is not something the abstract tests: it describes no pre-treatment arm
- No obvious toxicity from coriander treatment at the doses used
Accounts of this research also describe a 1999 mouse study with similar reductions in mercury deposition, in the Journal of Health Science, and a 2004 mouse study with more equivocal results. No record of either paper could be located in Crossref or Europe PMC. A paper that can be read is Sharma and colleagues (2010): coriander extract given daily alongside lead nitrate prevented, "to some extent", the fall in blood testosterone and sperm density in lead-exposed mice and improved the look of testis tissue.
What the mouse data actually supports:
- There is some biological plausibility for coriander affecting heavy-metal kinetics in mice.
- The effect is most pronounced for lead, somewhat less consistent for mercury, and essentially untested for arsenic, cadmium, and aluminum.
- A "blocking absorption" mechanism, with the largest effect when coriander is given before metal exposure, has been proposed as an alternative to true chelation of stored metal; the 2001 abstract does not test it.
- The mechanism remains unclear at the molecular level — no specific chelating compound in coriander has been isolated and characterized at the rigor seen for synthetic chelators.
- Mouse data does not reliably translate to human therapeutic dosing or clinical outcomes.
What the mouse data does not support: that consuming culinary amounts of cilantro or coriander seed in humans produces clinically meaningful reductions in stored body burden of mercury, lead, or other metals. The one human trial described in the Sears 2013 review, a cilantro extract in lead-exposed children, found no advantage over placebo; no larger trial has been located.
Cilantro Leaf vs Coriander Seed — Different Chemistry
A point routinely conflated in popular coverage: the chelation claims in the Omura paper and the Aga study all involved cilantro leaf (the fresh herb, also called Chinese parsley or coriander leaf), not coriander seed (the dried, ripe fruits used as a culinary spice). The chemistry of the two is substantially different.
The leaf chemistry is dominated by long-chain aliphatic aldehydes — decanal, (E)-2-decenal, (E)-2-dodecenal, and related saturated and unsaturated C8-C12 aldehydes. These compounds are responsible for the leaf's characteristic flavor (which roughly 14% of the human population finds soapy or offensive due to a polymorphism in the OR6A2 olfactory receptor gene) and have been credited with the leaf's antimicrobial activity. The proposed metal-binding mechanism in the leaf has been attributed variably to:
- Aldehyde groups that could potentially form Schiff bases with metal-bound amino acids
- Sulfur-containing volatile compounds at trace levels
- The polyphenol fraction (quercetin, kaempferol, rutin)
- Mucilage and dietary fiber that bind metal in the gut lumen and reduce reabsorption
None of these proposed mechanisms has been definitively validated. The seed chemistry, by contrast, is dominated by the monoterpene alcohol linalool, with smaller fractions of alpha-pinene, gamma-terpinene, geraniol, and camphor — a profile much closer to lavender or basil than to the leaf. The aldehydes that dominate the leaf are present at much lower concentrations in the seed.
The practical implication: the popular chelation claim, to the extent it has any animal-study support, is largely a leaf claim, not a seed claim. Products sold as coriander seed extract or coriander seed oil are unlikely to provide the leaf's aldehyde fraction in meaningful amounts. Fresh cilantro leaf (the whole herb, not the dried seed) is the form that accounts of the Omura and Aga work describe.
The one seed study on this page's list did not measure metal removal. Velaga and colleagues (2014) gave rats lead for 4 weeks, then a water-and-alcohol extract of coriander seed at 250 or 500 mg per kg of body weight for 7 days, and report that oxidative stress (chemical damage to cells) in brain regions eased to a different degree in each tissue. It is a rat result about oxidative stress, not about getting lead out of the body.
For the seed itself, the credible benefit claims center on digestive carminative use, hypoglycemic activity, and food-safety antimicrobial preservation. Heavy-metal chelation is not a credible standalone seed claim.
The Sears 2013 Natural Chelation Review
The most commonly cited modern review of natural chelation candidates is Sears (2013) in The Scientific World Journal titled "Chelation: harnessing and enhancing heavy metal detoxification — a review." Sears surveyed the published evidence for several natural agents claimed to chelate or otherwise reduce body burden of heavy metals, including coriander, chlorella, garlic, modified citrus pectin, alpha-lipoic acid, glutathione precursors, and others.
The review's whole cilantro passage is three sentences, and says:
- Cilantro gained attention when a soup was reported to enhance mercury excretion after dental amalgam removal, and it "remains popular despite limited evidence"
- In animals, it decreased lead absorption into bone and inhibition of the delta-aminolevulinic acid dehydratase enzyme
- In a trial in lead-exposed children aged 3 to 7, a cilantro extract "was as effective as placebo" in increasing lead excretion in urine; improvements in both groups were ascribed to better diet during the study
The following points are not in Sears; they are commentary often attached to the review:
- Coriander has biological plausibility based on the Aga mouse study and a small number of in-vitro binding studies
- The effect size, even if real, is described as likely modest compared with pharmaceutical chelators
- Coriander is eaten as a food, and some people include it in a broader detoxification approach on that basis
- It is not described as a substitute for pharmaceutical chelation in documented clinical toxicity
The Sears review is frequently cited in popular literature as validation of cilantro chelation, but a careful reading shows it is more an inventory of candidate natural agents with biological plausibility than an endorsement of clinical efficacy. Its central caveat for cilantro is the children's trial, which Sears cites from the Journal of Birjand University of Medical Sciences (Deldar and colleagues, 2008); only Sears's description of that trial was read for this page.
How Prescription Chelation Is Used and Measured (DMSA, DMPS, EDTA)
For comparison, these are the pharmaceutical chelators commonly used in mainstream clinical toxicology:
- DMSA (meso-2,3-dimercaptosuccinic acid, generic name succimer) — oral chelator, U.S. Food and Drug Administration-approved for childhood lead poisoning at blood lead >45 mcg/dL. Dosed at 10 mg/kg every 8 hours for 5 days, then every 12 hours for 14 days. Pharmacokinetics, dose-response, and excretion are well-characterized. Used off-label for mercury toxicity. Its U.S. label states that it is not indicated for prevention of lead poisoning in a lead-containing environment, and that the source of lead is to be identified and eliminated before treatment begins.
- DMPS (2,3-dimercapto-1-propanesulfonic acid) — oral or intravenous (IV) chelator, not U.S. Food and Drug Administration-approved in the US but used in Europe and available via compounding pharmacies. Particularly favored for mercury, including dental amalgam mercury elimination.
- CaNa2-EDTA (calcium disodium ethylenediaminetetraacetic acid) — chelator given by intravenous infusion or intramuscular injection, U.S. Food and Drug Administration-approved to reduce blood levels and stored lead in lead poisoning (acute and chronic) and lead encephalopathy, in children and adults. Dosed at 1,000-1,500 mg/m²/day for 5 days. Risk of nephrotoxicity, requires monitoring.
- BAL (British anti-Lewisite, dimercaprol) — older intramuscular chelator, used for acute arsenic, gold, mercury, and lead poisoning, particularly when oral chelation is not feasible. Painful injection, significant side-effect profile.
- Deferoxamine, deferasirox, deferiprone — iron-specific chelators for transfusion-dependent iron overload (thalassemia, sickle cell disease).
These agents have molar-equivalent metal-binding constants in the range of 10^15 to 10^25, characterized by formal stability constant measurements. They have been studied in formal pharmacokinetic, pharmacodynamic, and toxicity studies in humans. Their efficacy is measured by quantitative reduction in blood, urine, tissue, and bone metal burden using validated atomic absorption or ICP-MS analytical methods. They are administered under physician supervision with laboratory monitoring.
Coriander, even in the most optimistic reading of the Aga mouse data, does not approach this level of evidence or this level of effect size. Substituting culinary coriander for medical chelation in a person with documented clinically significant heavy metal toxicity delays effective treatment, and that delay is the danger.
The drugs have trade-offs of their own. One 2017 review reports that DMSA has considerably lower toxicity than BAL and is less toxic than DMPS, and its authors propose DMSA in place of calcium EDTA for moderate lead poisoning. A 2016 review reports that in experimental animals repeated BAL raised brain uptake of arsenic, lead and mercury, and that calcium EDTA, but not DMSA, raised brain uptake of lead.
A similar name hides a different drug. From 2003 to 2005, three deaths from cardiac arrest caused by low blood calcium during chelation were reported to the U.S. Centers for Disease Control and Prevention. Two were children, both treated with edetate disodium, which is not the calcium disodium EDTA listed above; the adult case was still under investigation when the report was written.
The Coriander + Chlorella Combination Claim
A common variation on the chelation theme is the Klinghardt-attributed protocol pairing cilantro (the proposed "mobilizer" of stored mercury) with chlorella (the proposed "binder" that supposedly prevents reabsorption from the gut). The underlying logic is that cilantro draws mercury out of intracellular storage into the bloodstream, and chlorella in the gut binds the biliary-secreted mercury before it can be reabsorbed in the enterohepatic circulation.
The evidence base for this specific combination protocol is weaker than the evidence base for either component individually. There are no peer-reviewed randomized controlled trials of the combination. Chlorella does contain peptides and cell-wall components that bind metals in vitro, and animal studies have shown reduced cadmium and lead absorption when chlorella is co-administered with the metal. The proposed clinical translation to chronic stored body burden in humans is, again, not validated.
What is reported for people who follow this protocol on their own initiative:
- Users describe the protocol as safe as long as the cilantro is genuine fresh herb (washed; no agricultural contamination risk) and the chlorella product is from a clean-water source with third-party heavy-metal testing (some pond-grown chlorella products are themselves contaminated with the metals they purport to remove)
- Magnitude of clinical effect is unknown and likely modest if any
- For symptoms attributed to heavy metal toxicity, the tested route is a toxicology workup with blood/urine metals, with medical chelation where levels call for it
- The protocol does not remove an ongoing exposure (amalgam fillings, contaminated drinking water, occupational exposure)
The "Provoked Urine Test" Trap
A common pattern in clinics offering chelation therapy is the "provoked urine test" — a patient is given a single dose of DMSA, DMPS, or EDTA, then provides a 6-hour or 24-hour urine sample which is sent to a lab for heavy-metal quantification. Because the chelator pulls metals into urine that would otherwise have been excreted only slowly, the provoked urine inevitably shows higher metal values than an unprovoked baseline urine.
The patient is then told that this elevated provoked urine level represents stored body burden of toxic metal that requires further chelation therapy. The problem: the reference ranges quoted by these labs are typically unprovoked reference ranges. Of course a provoked urine will exceed an unprovoked reference range. The American College of Medical Toxicology issued a position statement on post-chelator challenge urine testing in 2010 and in 2017 stated that it recommends against the test. A 2013 review in its journal refers to recommendations against the test "by professional and government organizations". Accounts also name the American Academy of Clinical Toxicology and the U.S. Centers for Disease Control and Prevention; statements from those two could not be located. Standard assessment uses whole-blood levels for lead and mercury, with consideration of hair and tissue analysis in specific clinical scenarios.
That 2013 review (Ruha) reports that volunteer studies found mercury in the urine of most people even with no known exposure, and that urinary mercury rises after any chelator, whatever the exposure history and in an unpredictable way. It reports no standard, validated challenge test and no established reference ranges for provoked samples in healthy people. Its conclusion is that the tests "should not be utilized". The first prospective check, published in 2022 (Weiss and colleagues), looked at 74 toxicology-clinic patients who arrived with provoked results. A board-certified medical toxicologist tied the illness to heavy metal exposure in only 3 of them, a positive predictive value of 4.3%.
Coriander does not directly cause this diagnostic pitfall, but the broader "natural detox" framing in which the cilantro chelation claim sits often leads patients into chelation clinics that use provoked urine testing as the entry point. The in-vitro/animal evidence for coriander (interesting but inconclusive) is a separate matter from provoked-urine testing (described by toxicology sources as misleading and potentially harmful, by driving unnecessary chelation in people with no actual toxicity).
When Heavy Metal Toxicity is Actually Documented
Some patients do have genuine, clinically significant heavy-metal toxicity that warrants formal investigation and treatment. The common scenarios:
- Childhood lead poisoning from pre-1978 paint, contaminated soil, contaminated drinking water (Flint, Michigan), or imported folk remedies (Greta, Azarcon)
- Occupational lead exposure — battery workers, smelter workers, demolition workers, lead glaziers, stained-glass artists
- Methylmercury from large predatory fish — swordfish, tilefish, king mackerel, large tuna; particularly relevant in high-consumption populations and during pregnancy
- Elemental mercury exposure from broken thermometers, fluorescent tube breakage, dental amalgam disturbance, or rare occupational exposures
- Arsenic from contaminated well water — particularly in parts of Bangladesh, India, parts of the American Southwest, and some private well water
- Cadmium from cigarette smoking and from occupational exposure (pigment workers, battery workers)
The workup toxicology sources describe for suspected toxicity is:
- Detailed exposure history (occupational, residential, dietary, recreational, medical)
- Whole-blood lead and mercury (NOT provoked urine)
- Hair and 24-hour unprovoked urine in specific scenarios
- Tissue biopsy in rare cases (e.g. bone lead via X-ray fluorescence in chronic occupational exposure)
- Pediatric Environmental Health Specialty Unit (PEHSU) consultation for children
- Adult medical toxicology consultation for occupational or unusual exposures
- Pharmaceutical chelation if blood levels exceed treatment thresholds (e.g. blood lead >45 mcg/dL in children)
Coriander, cilantro, and other "natural chelators" are not part of the recommended workup or treatment for clinically significant toxicity. Food amounts are not reported to be harmful, and people may keep eating them during medical chelation for cultural or personal reasons, but they do not replace that care.
What Coriander Is Genuinely Good For (Not Chelation)
The evidence base supports coriander seed for several genuine clinical applications — just not the heavy-metal one for which it is most famous in popular wellness culture. Stronger-evidence indications include:
- Carminative for irritable bowel syndrome (IBS) and functional dyspepsia — a placebo-controlled pilot trial (Vejdani 2006, 32 people with IBS) tested a three-herb product containing Melissa officinalis, Mentha spicata and Coriandrum sativum, given with loperamide or psyllium, so not coriander seed alone and not functional dyspepsia; well-characterized mechanism through linalool calcium-channel modulation and gamma-aminobutyric acid-A potentiation
- Mild hypoglycemic / glucose-lowering activity — mouse studies (Gray 1999) and small human pilots showing modest fasting glucose reduction
- Broad-spectrum antimicrobial for food-safety preservation — extensive in-vitro data against Salmonella, E. coli, Listeria, Candida
- Mild anxiolytic and sleep-supportive effect — via the linalool / gamma-aminobutyric acid-A mechanism (Emamghoreishi 2005 mouse data)
- Antioxidant capacity from the flavonoid fraction (quercetin, kaempferol, rutin)
- Bioavailability enhancement of other phytochemicals when combined in traditional South Asian spice blends
The takeaway: coriander seed is genuinely useful in the herbal toolkit. It is unfortunate that its most-marketed benefit (heavy-metal chelation) is also its least-supported. The better-evidenced uses are listed above.
Safety Facts and Reported Concerns
- Delay of a toxicology workup — when heavy-metal toxicity is suspected, the greatest risk of the cilantro-chelation narrative is not direct harm from coriander itself but rather delay of evidence-based diagnosis and treatment.
- Provoked urine tests as a basis for chelation referral — these tests overestimate body burden and drive unnecessary chelation in people who do not have clinically significant exposure.
- Ongoing exposure — no detox protocol of any kind can succeed if exposure continues. Sources include drinking water (lead from old pipes, arsenic from well water), occupational exposures, dietary mercury (large predatory fish), and lead-based folk remedies.
- Chlorella product quality — some chlorella products are themselves contaminated; third-party heavy-metal testing and clean-water sourcing are what set the others apart.
- Pregnancy — suspected heavy-metal exposure during pregnancy (lead, methylmercury) is handled by obstetric and toxicology services. Cilantro/coriander in culinary amounts is reported as safe in pregnancy; supplemental extract use during documented exposure can delay assessment.
- Children — suspected lead poisoning in a child is diagnosed by a blood lead test, available through pediatricians and local public health departments. Cilantro is not a substitute.
- Hypoglycemia in diabetic patients — high-dose coriander supplementation (not culinary amounts) can additively lower blood glucose in people taking insulin or sulfonylureas.
Key Research Papers
- Aga M, Iwaki K, Ueda Y, Ushio S, Masaki N, Fukuda S, et al. (2001). Preventive effect of Coriandrum sativum (Chinese parsley) on localized lead deposition in ICR mice. Journal of Ethnopharmacology. — PubMed PMID: 11535365
- Omura Y, Beckman SL (1995). Role of mercury (Hg) in resistant infections & effective treatment of Chlamydia trachomatis and Herpes family viral infections (and potential treatment for cancer) by removing localized Hg deposits with Chinese parsley and delivering effective antibiotics using various drug uptake enhancement methods. Acupuncture & Electro-Therapeutics Research. — PubMed PMID: 8686573
- Sears ME (2013). Chelation: harnessing and enhancing heavy metal detoxification — a review. The Scientific World Journal. — PubMed PMID: 23690738
- American College of Medical Toxicology (2010). American College of Medical Toxicology position statement on post-chelator challenge urinary metal testing. Journal of Medical Toxicology 6(1):74–75. — PubMed PMID: 20354920
- American College of Medical Toxicology (2017). ACMT Recommends Against Use of Post-Chelator Challenge Urinary Metal Testing. Journal of Medical Toxicology 13(4):352–354. — PubMed PMID: 28726084
- Ruha AM (2013). Recommendations for provoked challenge urine testing. Journal of Medical Toxicology 9(4):318–325. — PubMed PMID: 24113861
- Weiss ST, Campleman S, Wax P, McGill W, Brent J, Toxicology Investigators Consortium (2022). Failure of chelator-provoked urine testing results to predict heavy metal toxicity in a prospective cohort of patients referred for medical toxicology evaluation. Clinical Toxicology 60(2):191–196. — PubMed PMID: 34184587
- Bjorklund G, Mutter J, Aaseth J (2017). Metal chelators and neurotoxicity: lead, mercury, and arsenic. Archives of Toxicology. — PubMed PMID: 29063135
- Andersen O, Aaseth J (2016). A review of pitfalls and progress in chelation treatment of metal poisonings. Journal of Trace Elements in Medicine and Biology. — PubMed PMID: 27150911
- Mehrandish R, Rahimian A, Shahriary A (2019). Heavy metals detoxification: a review of herbal compounds for chelation therapy in heavy metals toxicity. Journal of Herbmed Pharmacology 8(2):69–77. — doi:10.15171/jhp.2019.12
- Sharma V, Kansal L, Sharma A (2010). Prophylactic efficacy of Coriandrum sativum (coriander) on testis of lead-exposed mice. Biological Trace Element Research. — PubMed PMID: 19902160
- Velaga MK, Yallapragada PR, Williams D, Rajanna S, Bettaiya R (2014). Hydroalcoholic seed extract of Coriandrum sativum (coriander) alleviates lead-induced oxidative stress in different regions of rat brain. Biological Trace Element Research. — PubMed PMID: 24793421
- Klaassen CD (2018). Casarett and Doull's Toxicology: The Basic Science of Poisons (9th ed.) — reference text on heavy-metal toxicology and chelation. — PubMed
- Brown MJ, Willis T, Omalu B, Leiker R (2006). Deaths resulting from hypocalcemia after administration of edetate disodium: 2003-2005. Pediatrics — cautionary tale on wrong-EDTA-formulation chelation deaths. — PubMed PMID: 16882789