⚠ Evidence warning: Clinical trials or other evidence do not support the claim that Pau d'Arco eases osteoarthritis, rheumatoid arthritis, gout, bursitis, psoriasis, eczema, seborrheic dermatitis, acne or inflammatory bowel disease in people, or that cycling it with breaks prevents a fading response; the mechanisms on this page come from cell and animal studies, and no controlled human trial of Pau d'Arco for these conditions is cited. This page keeps it as a report of what people, websites or other media say.
Pau d'Arco for Anti-Inflammatory Effects
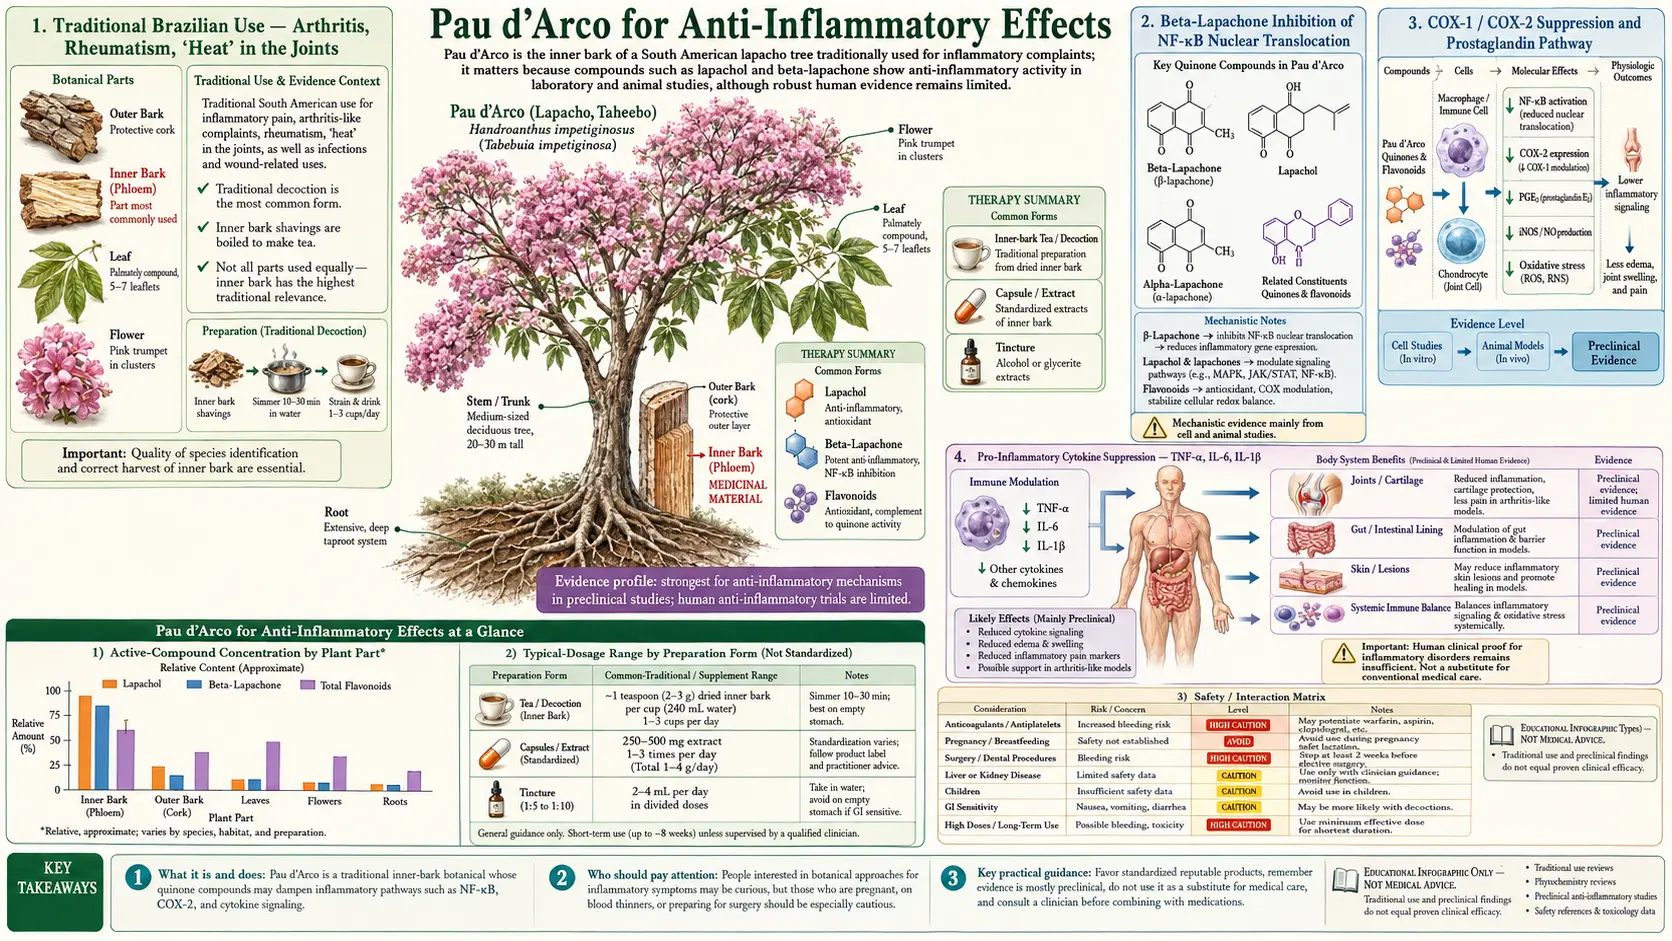
Pau d'Arco has a deep traditional reputation in Brazilian and Argentinian folk medicine for joint pain, arthritis, low-back pain, "rheumatism," chronic boils, and a wide range of inflammatory skin conditions — uses that closely parallel its modern in-vitro and in-vivo profile as an NF-κB inhibitor and cyclooxygenase suppressor. Beta-lapachone, the more potent of the two principal naphthoquinones, blocks the IκB-kinase complex that normally releases NF-κB p65 from cytoplasmic restraint, preventing its translocation to the nucleus and suppressing transcription of tumor necrosis factor-α, interleukin-6 (IL-6), interleukin-1 beta (IL-1β), cyclooxygenase-2 (COX-2), inducible nitric oxide synthase (iNOS), and several adhesion molecules. The mechanism overlaps directly with curcumin, boswellic acids, resveratrol, and the parthenolide of feverfew. This deep-dive walks through the molecular pharmacology, the traditional Brazilian arthritis preparations, the realistic dose ranges, and where Pau d'Arco does — and does not — fit alongside the conventional anti-inflammatory drug classes.
Table of Contents
- Traditional Brazilian Use — Arthritis, Rheumatism, "Heat" in the Joints
- Beta-Lapachone Inhibition of NF-κB Nuclear Translocation
- Cyclooxygenase-1 / Cyclooxygenase-2 Suppression and Prostaglandin Pathway
- Pro-Inflammatory Cytokine Suppression — Tumor Necrosis Factor-α, Interleukin-6, Interleukin-1β
- iNOS and Nitric Oxide Modulation in Chronic Inflammation
- Practical Applications — Osteoarthritis, Rheumatoid Arthritis, Gout, Bursitis
- Inflammatory Bowel Conditions — Theoretical Application and Realistic Limits
- Inflammatory Skin Conditions — Psoriasis, Eczema, Chronic Dermatitis
- Dosing for Anti-Inflammatory Effect
- Combining with Curcumin, Boswellia, Omega-3, and Other Anti-Inflammatory Agents
- Cautions Specific to Anti-Inflammatory Use
- Key Research Papers
- Connections
- Featured Videos
Traditional Brazilian Use — Arthritis, Rheumatism, "Heat" in the Joints
The traditional Brazilian and Argentinian use of Pau d'Arco for arthritis and rheumatic complaints is one of the most consistent threads in the South American materia medica. The Tupi-Guaraní healers of the lowland forests, the Kallawaya of the high Andes, and the Portuguese-Brazilian rural folk tradition all converge on the same indications: hot, swollen, painful joints; chronic low-back pain that worsens with weather change; "rheumatism" of the hands and shoulders; chronic gout flares; and the diffuse joint pain that often accompanies recurrent fever and infection.
The traditional preparation is generally an oral decoction of cut inner bark — 2 tablespoons of bark per quart of water, simmered 15-20 minutes, drunk as 2-4 cups daily over weeks to months. Topical poultices of warm, moist bark were also applied directly over the painful joint, sometimes wrapped in a wool cloth to retain heat. For gout specifically, the recommendation was often a combination of the oral decoction with dietary modification (reducing organ meats, sardines, beer — the same purine-source modifications a modern gout dietitian would recommend).
The herb was selected for inflammatory joint complaints in part because of its observable effect — pain and swelling visibly improved over 2-4 weeks of continuous use — and in part because of its traditional categorization as a "cooling" herb that reduced "heat" in the affected tissue. The cooling framing maps imperfectly but recognizably onto modern anti-inflammatory pharmacology.
Beta-Lapachone Inhibition of NF-κB Nuclear Translocation
NF-κB (nuclear factor kappa-light-chain-enhancer of activated B cells) is the master transcription factor of inflammation. In resting cells, the active p65/p50 heterodimer is held inactive in the cytoplasm by binding to IκB inhibitor proteins. When the cell receives an inflammatory signal (tumor necrosis factor (TNF) receptor engagement, Toll-like receptor activation, oxidative stress, certain cytokines), the IκB-kinase (IKK) complex phosphorylates IκB, marking it for proteasomal degradation. Free NF-κB then translocates to the nucleus, where it binds κB response elements in the promoter regions of hundreds of inflammatory target genes: tumor necrosis factor-α, interleukin-6, interleukin-1β, cyclooxygenase-2, iNOS, intercellular adhesion molecule-1 (ICAM-1), vascular cell adhesion molecule-1 (VCAM-1), E-selectin, and many more.
Beta-lapachone has been shown in cell-line studies to inhibit NF-κB activation at concentrations in the 1-10 μM range. A 1999 study found that it blocked tumor necrosis factor-induced NF-κB activation, p65 translocation and IκBα breakdown in human myeloid U937 cells, and that it was also inhibitory in T cells and epithelial cells; reducing agents (dithiothreitol and N-acetylcysteine) reversed the effect, which points to a critical sulfhydryl group as its target. A 2007 study found the same NF-κB block, through stopped IκBα breakdown, in brain immune cells (BV2 microglia) stimulated with bacterial lipopolysaccharide. Both are cell studies. The mechanism involves direct interference with the IκB-kinase complex, with downstream consequences for the entire NF-κB-dependent inflammatory gene set. Importantly, the inhibition is most pronounced at sub-cytotoxic concentrations — making this a genuine pharmacologic effect rather than a non-specific consequence of cell stress.
The mechanistic overlap with other natural NF-κB inhibitors is striking:
- Curcumin (from turmeric) inhibits IKK and p65 nuclear translocation through similar but not identical mechanisms
- Resveratrol (from grapes, polygonum cuspidatum) inhibits NF-κB through SIRT1-dependent and -independent pathways
- Parthenolide (from feverfew) covalently modifies cysteine residues in IKKβ
- Epigallocatechin gallate (EGCG) (from green tea) inhibits p65 nuclear translocation
- Boswellic acids (from Boswellia serrata) inhibit 5-lipoxygenase and also have NF-κB effects
This shared mechanism explains why these herbs are often combined in clinical practice — their effects on the NF-κB node are at least partly additive, and the redundancy reduces the chance that an individual patient's pharmacogenomic variation will prevent benefit.
Cyclooxygenase-1 / Cyclooxygenase-2 Suppression and Prostaglandin Pathway
Cyclooxygenase (COX) is the enzyme that converts arachidonic acid to prostaglandin H2, the precursor of all downstream prostaglandins and thromboxane. Cyclooxygenase-1 (COX-1) is constitutively expressed in most tissues and produces the prostaglandins responsible for gastric mucus protection, renal blood flow autoregulation, and platelet aggregation. Cyclooxygenase-2 is the inducible form upregulated in inflammation and is the target of selective nonsteroidal anti-inflammatory drugs (NSAIDs) like celecoxib.
Beta-lapachone has documented suppression of cyclooxygenase-2 expression at the transcriptional level (through NF-κB inhibition, since the cyclooxygenase-2 gene is NF-κB-regulated) and to a lesser extent direct enzymatic inhibition. The net effect is reduced prostaglandin E2 production in inflamed tissue, which is the primary driver of the swelling, redness, warmth, and pain of inflammation.
The cell data behind the COX-2 effect come from cancer research. In human prostate cancer cells (DU145), beta-lapachone lowered COX-2 mRNA and protein without significant changes in COX-1, and prostaglandin E2 (PGE2) synthesis fell with it. This is a cancer-cell finding, not an arthritis study.
The whole bark has been tested in mice and in cells. In a 2008 study, a water extract of the inner bark (taheebo) given by mouth at 100 mg/kg for 1 week completely diminished mouse ear swelling caused by arachidonic acid, an activator of COX-2, but not swelling caused by croton oil, an activator of lipoxygenase. In mouse macrophage cells (RAW264.7) stimulated with lipopolysaccharide, the same extract significantly suppressed the production of PGE2 and nitric oxide. These are animal and cell results.
The cyclooxygenase-2-preferential profile is clinically attractive because it suggests potential anti-inflammatory benefit without the gastric and platelet effects of cyclooxygenase-1 inhibition (which is why most patients on chronic ibuprofen develop gastric irritation or risk gastrointestinal (GI) bleeding). However, this comparison has limits — the absolute potency of Pau d'Arco's cyclooxygenase-2 effect at oral doses achievable in humans is far below that of celecoxib or ibuprofen. Pau d'Arco is best thought of as a mild, broad-spectrum anti-inflammatory adjunct, not a replacement for nonsteroidal anti-inflammatory drug (NSAID) therapy in significant inflammatory disease.
Pro-Inflammatory Cytokine Suppression — Tumor Necrosis Factor-α, Interleukin-6, Interleukin-1β
The pro-inflammatory cytokines tumor necrosis factor-α, interleukin-6 (IL-6), and interleukin-1β are the central mediators of the systemic inflammatory response. They are produced primarily by activated macrophages and monocytes in response to infection or tissue damage, and they orchestrate fever, acute-phase protein production by the liver, neutrophil recruitment, and the malaise of acute and chronic inflammation. They are also the molecular drivers of several major chronic inflammatory diseases — tumor necrosis factor-α is the target of adalimumab, infliximab, and etanercept; interleukin-6 is the target of tocilizumab; interleukin-1β is the target of canakinumab.
Beta-lapachone reduces the production of all three cytokines in stimulated macrophage cell lines and in murine inflammation models, again at sub-cytotoxic concentrations and through the NF-κB mechanism. The magnitude of the effect in vitro is comparable to other plant NF-κB inhibitors but, again, far below that of monoclonal antibody biologics. The clinical implication is that Pau d'Arco can modestly damp the chronic low-grade inflammation of conditions like osteoarthritis, mild rheumatoid arthritis, and chronic skin inflammation — but it is not a substitute for biologic disease-modifying antirheumatic drug (DMARD) therapy in moderate-to-severe rheumatoid arthritis, severe psoriasis, or active inflammatory bowel disease.
For patients on biologic therapy who add a mild plant adjunct, Pau d'Arco is generally described as well tolerated — the two points that matter are the anticoagulant (blood-thinning) activity of lapachol, one of the bark's naphthoquinones, and the herb's immune-modulating effects (see the Cautions & Cancer Research page).
iNOS and Nitric Oxide Modulation in Chronic Inflammation
Inducible nitric oxide synthase (iNOS, encoded by the NOS2 gene) is the enzyme that produces large amounts of nitric oxide (NO) in activated macrophages and other inflammatory cells. iNOS is NF-κB-regulated and is upregulated in chronic inflammatory tissue. While NO has many physiologic roles (the constitutive eNOS produces small amounts of NO for vascular smooth muscle relaxation), the large amounts produced by iNOS in chronic inflammation contribute to tissue damage and the perpetuation of the inflammatory state.
Beta-lapachone's NF-κB inhibition translates to reduced iNOS expression and reduced NO production in inflammatory cells. This effect has been documented in macrophage cell lines, in murine arthritis models, and in cell-line models of inflammatory bowel disease. The reduction is modest but consistent.
This is part of a broader pattern in the integrative-medicine literature in which several plant-derived NF-κB inhibitors (Pau d'Arco, curcumin, boswellic acids, epigallocatechin gallate, resveratrol) collectively produce a "broadly anti-inflammatory" effect through coordinated suppression of cytokines, cyclooxygenase-2, iNOS, and adhesion molecules. The strategy of using multiple complementary plant agents at modest doses rather than a single agent at high dose is one of the operating principles of much of clinical herbalism, and it is largely supported by the molecular pharmacology.
Practical Applications — Osteoarthritis, Rheumatoid Arthritis, Gout, Bursitis
This section lists where practitioners place Pau d'Arco for inflammatory joint disease.
- Mild-to-moderate osteoarthritis — used by practitioners as an adjunct alongside the standard triad of exercise, weight management, and topical or oral nonsteroidal anti-inflammatory drug as needed. The dose they describe is 500-1,000 mg standardized extract twice daily for 12 weeks, followed by a review. Often combined with curcumin 500 mg twice daily, omega-3 fish oil 2-3 g daily, and glucosamine + chondroitin. Practitioners report modest pain reduction and possibly a modest reduction in nonsteroidal anti-inflammatory drug use.
- Rheumatoid arthritis — complementary to (NOT a substitute for) DMARD therapy. Practitioners describe its use mainly in milder seropositive rheumatoid arthritis (RA) on methotrexate alone, where low-grade anti-inflammatory adjuncts are described as helping with breakthrough symptoms without escalating immunosuppression. It is not used as monotherapy for active rheumatoid arthritis.
- Gout — the traditional indication has a basis — modest anti-inflammatory effect — but does NOT replace allopurinol or febuxostat for uric acid lowering, and does not replace colchicine or nonsteroidal anti-inflammatory drug for acute flare management. Practitioners use it as an adjunct for chronic interval management alongside dietary purine restriction. See Gout.
- Bursitis and tendinitis — mild adjunct, more useful for chronic recurrent forms than for acute flares. Practitioners describe adding warm compresses of bark decoction to oral use, and 3-6 weeks of consistent use before a measurable effect.
- Polymyalgia rheumatica — the standard therapy is low-dose prednisone, and Pau d'Arco is not a substitute. May have modest adjunctive value for patients trying to minimize the prednisone dose, but not a primary intervention.
- Lyme arthritis — the antimicrobial and immune-modulating mechanisms make Pau d'Arco one of several plant adjuncts that integrative Lyme practitioners use alongside antibiotics. See Lyme Disease.
Inflammatory Bowel Conditions — Theoretical Application and Realistic Limits
The NF-κB and cytokine suppression mechanisms of Pau d'Arco are mechanistically attractive for inflammatory bowel disease (IBD), but the practical application is more nuanced than for joint disease. Active ulcerative colitis and active Crohn's disease require evidence-based induction therapy (5-aminosalicylates, corticosteroids, immunomodulators, biologics) and are not appropriate settings for plant-based monotherapy.
Pau d'Arco may have a role in:
- Mild interval management of inflammatory bowel disease in remission, alongside maintenance 5-aminosalicylic acid (5-ASA) therapy, gut-healing nutrients, and dietary modification
- Microscopic colitis (lymphocytic, collagenous) as part of an integrative protocol after gastroenterology evaluation
- Post-infectious irritable bowel syndrome with low-grade inflammatory component
- Functional bowel patterns with concurrent suspected fungal overgrowth — here the dual antifungal + anti-inflammatory profile is potentially additive
The cautions for inflammatory bowel disease use are real: paradoxically, the same naphthoquinone redox-cycling that delivers therapeutic benefit can also irritate inflamed gut mucosa at higher doses, producing diarrhea or worsening symptoms. Practitioners describe starting at the low end of the dose range (500 mg standardized extract once daily with food), raising the dose slowly, and stopping at any worsening, and they hold off plant-medicine use during active flares of inflammatory bowel disease until remission.
In mice with chemically induced colitis (dextran sulfate sodium, DSS), a taheebo water extract given by mouth significantly reduced body weight loss and colon tissue inflammation. In the gut lymph nodes of these mice it raised anti-inflammatory Th2 and Foxp3+ regulatory T cells and sharply lowered pro-inflammatory Th1 and Th17 cells. This is a mouse study.
For more on gut-related interventions, see Gut Healing and Crohn's Disease.
Inflammatory Skin Conditions — Psoriasis, Eczema, Chronic Dermatitis
The dual antifungal and anti-inflammatory profile of Pau d'Arco translates well to several inflammatory skin conditions where chronic low-grade fungal contribution is part of the picture:
- Seborrheic dermatitis — the chronic flaky red rash of the scalp, eyebrows, and nasolabial folds is driven by Malassezia yeast colonization plus an inflammatory response to it. Topical Pau d'Arco decoction or salve combines antifungal (against Malassezia) and anti-inflammatory effects directly at the site. Often combined with topical zinc pyrithione or ketoconazole shampoo.
- Psoriasis — the chronic NF-κB-driven plaque-forming inflammatory skin disease. Pau d'Arco at oral doses contributes mild systemic NF-κB suppression. Topical preparations can be applied directly to plaques. NOT a substitute for biologic therapy in moderate-severe psoriasis; practitioners use it as an adjunct in mild disease or for patients trying to delay biologic initiation.
- Atopic dermatitis (eczema) — particularly for patients with eczema and concurrent gut candidiasis or recurrent skin yeast infection, the dual mechanism is useful. The Th2-dominant pattern of allergic eczema may also benefit from the Th1-shifting effect (see Immune Modulation page).
- Acne (inflammatory rather than comedonal) — the anti-inflammatory and modest antimicrobial effects against Cutibacterium acnes are why practitioners use Pau d'Arco as an adjunct for inflammatory acne. NOT a substitute for tretinoin, benzoyl peroxide, or oral antibiotic / isotretinoin therapy for moderate-severe disease. See Acne.
- Chronic urticaria — the chronic histamine-driven hive condition with some inflammatory component. Mild adjunct, results variable.
Dosing for Anti-Inflammatory Effect
The anti-inflammatory dose range for Pau d'Arco is generally at the lower end of the overall dose range:
- Standardized extract capsule: 500-1,500 mg of dried-bark equivalent twice daily, with meals. Products sold this way are standardized to 3-10% combined naphthoquinones. The lower end of this range (500 mg twice daily of an 8% standardized product) is often sufficient for anti-inflammatory effect; the higher end is more appropriate when there is concurrent antifungal target.
- Alcohol tincture (1:5 in 40-50% ethanol): 3-6 mL twice daily, diluted in water or juice.
- Decoction: 2-3 cups daily of the standard preparation (2 tbsp bark per quart of water, simmered 15-20 minutes). The lowest-potency form — useful for general tonic anti-inflammatory effect, less useful for active inflammatory flare.
Practitioners describe 2-6 weeks before a measurable effect on chronic inflammatory conditions. Pau d'Arco is not an acute flare intervention — it has no rapid pharmacologic effect comparable to ibuprofen or prednisone. Practitioners use it as steady-state tonic management, with conventional anti-inflammatory drugs for acute flares.
Practitioners describe breaks in continuous use beyond 12 weeks — 1-2 weeks off every 8-12 weeks — to prevent tachyphylaxis (a fading response) and to allow assessment of whether continued use is still providing benefit. Many users report that intermittent 8-12 week courses with 2-4 week breaks provide better long-term efficacy than continuous indefinite dosing.
Combining with Curcumin, Boswellia, Omega-3, and Other Anti-Inflammatory Agents
The most pragmatic clinical strategy for chronic inflammatory disease is combination of multiple complementary mechanisms at modest doses, rather than mono-therapy at high dose. Pau d'Arco fits well into combination protocols:
- Curcumin — the most-studied plant NF-κB inhibitor. 500-1,000 mg twice daily of a bioavailability-enhanced formulation (phytosome or nano-particle curcumin, or with piperine). Mechanistically additive with Pau d'Arco.
- Boswellia serrata (boswellic acids) — selective 5-lipoxygenase inhibition reduces leukotrienes (the inflammatory mediators not addressed by nonsteroidal anti-inflammatory drugs). 300-500 mg of standardized extract (typically enriched in acetyl-11-keto-beta-boswellic acid (AKBA)) twice daily.
- Omega-3 fish oil (eicosapentaenoic acid (EPA) + docosahexaenoic acid (DHA)) — substrate competition with arachidonic acid for COX and lipoxygenase (LOX) enzymes; resolvins and protectins as actively pro-resolving mediators. 2-3 g combined eicosapentaenoic acid+docosahexaenoic acid daily. See Omega-3 Fatty Acids.
- Bromelain — pineapple stem proteolytic enzyme with bradykinin and complement modulation. Useful for acute inflammation and post-surgical recovery. 500 mg twice daily between meals.
- Quercetin — flavonoid with mast cell stabilization and modest NF-κB effect. Particularly useful for allergic-inflammatory patterns. 500-1,000 mg twice daily.
- S-adenosylmethionine (SAMe) — methyl donor with documented anti-inflammatory effect in osteoarthritis. 400-1,200 mg daily.
- Magnesium glycinate — magnesium deficiency exacerbates many inflammatory conditions; the glycinate form is well tolerated. 200-400 mg elemental magnesium at bedtime.
A typical "chronic osteoarthritis / mild rheumatoid arthritis / chronic inflammatory pain" stacking protocol might include Pau d'Arco 500 mg twice daily + curcumin 500 mg twice daily + boswellia 300 mg twice daily + omega-3 2 g daily, alongside conventional nonsteroidal anti-inflammatory drug or DMARD as needed. The expectation is modest steady-state improvement and possibly reduced nonsteroidal anti-inflammatory drug dose requirement, not pharmaceutical-grade rapid pain relief.
Cautions Specific to Anti-Inflammatory Use
Most cautions are covered in detail on the Cautions & Cancer Research page. Anti-inflammatory use brings a few specific concerns:
- Concurrent nonsteroidal anti-inflammatory drug use — Pau d'Arco does not reduce the gastric or renal toxicity of nonsteroidal anti-inflammatory drugs. People taking chronic ibuprofen or naproxen keep those risks; gastroprotection (proton pump inhibitor or H2 blocker) and kidney monitoring are the usual measures.
- Concurrent anticoagulant use — this is the most consequential interaction. Nonsteroidal anti-inflammatory drugs already increase bleeding risk; adding lapachol (the main naphthoquinone of the bark), which has its own vitamin-K-antagonist action like warfarin, compounds the risk substantially. A 1984 laboratory study found that lapachol blocks vitamin K epoxide reductase in rat liver in the same way as the coumarin blood thinners, which explains the anticoagulant (blood-thinning) activity of lapachol seen earlier in both rats and humans. Because of this bleeding effect, practitioners stop Pau d'Arco at least 2 weeks before a planned surgical procedure.
- Concurrent corticosteroid use — no direct interaction documented, but corticosteroids already provide substantial NF-κB inhibition through their genomic mechanism. Adding Pau d'Arco may provide modest additive effect.
- Concurrent biologic DMARD use — the immune-modulating effects of Pau d'Arco could theoretically interact with the biologic mechanism, though no specific interactions have been clinically documented.
- Pregnancy — listed as an absolute contraindication for any indication, including arthritis.
- Liver function — both Pau d'Arco and many anti-inflammatory drugs (methotrexate, leflunomide, sulfasalazine, chronic nonsteroidal anti-inflammatory drugs) can affect liver function. Periodic liver function testing is the usual practice when they are combined.
- Human safety data — a small 2022 trial gave 1,050 mg/day of encapsulated Pau d'Arco for eight weeks to twelve healthy women aged 18-45 with period pain (primary dysmenorrhea); it was single-arm and open-label, with no placebo group. Nine of 12 completed the study and nine of 12 reported an adverse event, most of them mild and none serious. Prothrombin time (a clotting test) was among the laboratory markers collected; most markers stayed within normal limits, with a few clinically mild abnormalities. Pain intensity fell significantly from baseline, and the inflammation marker high-sensitivity C-reactive protein (hs-CRP) fell, but not significantly.
Key Research Papers
- Moon DO, Choi YH, Kim ND, Park YM, Kim GY (2007). Anti-inflammatory effects of beta-lapachone in lipopolysaccharide-stimulated BV2 microglia. International Immunopharmacology, 7(4), 506-514. — PubMed PMID: 17321474
- Manna SK, Gad YP, Mukhopadhyay A, Aggarwal BB (1999). Suppression of tumor necrosis factor-activated nuclear transcription factor-kappaB, activator protein-1, c-Jun N-terminal kinase, and apoptosis by beta-lapachone. Biochemical Pharmacology, 57(7), 763-774. — PubMed PMID: 10075082
- de Almeida ER, da Silva Filho AA, dos Santos ER, Lopes CA (1990). Anti-inflammatory action of lapachol. Journal of Ethnopharmacology. — PubMed PMID: 2374436
- Aggarwal BB, Sung B (2009). Pharmacological basis for the role of curcumin in chronic diseases: an age-old spice with modern targets. Trends in Pharmacological Sciences, 30(2), 85-94. — PubMed PMID: 19110321 (NF-κB mechanism background applicable to Pau d'Arco.)
- Lee JH, Cheong J, Park YM, Choi YH (2005). Down-regulation of cyclooxygenase-2 and telomerase activity by beta-lapachone in human prostate carcinoma cells. Pharmacological Research, 51(6), 553-560. — PubMed PMID: 15829436
- Byeon SE, Chung JY, Lee YG, Kim BH, Kim KH, Cho JY (2008). In vitro and in vivo anti-inflammatory effects of taheebo, a water extract from the inner bark of Tabebuia avellanedae. Journal of Ethnopharmacology, 119(1), 145-152. — PubMed PMID: 18634864
- Goel A et al. (2008). Curcumin as "Curecumin": from kitchen to clinic. Biochemical Pharmacology. — PubMed PMID: 17900536
- Sethi G, Sung B, Aggarwal BB (2008). TNF: a master switch for inflammation to cancer. Frontiers in Bioscience, 13, 5094-5107. — PubMed PMID: 18508572 (Background on the TNF-α-driven inflammation that Pau d'Arco modulates.)
- Preusch PC, Suttie JW (1984). Lapachol inhibition of vitamin K epoxide reductase and vitamin K quinone reductase. Archives of Biochemistry and Biophysics, 234(2), 405-412. — PubMed PMID: 6497379
- Park HJ, Lee SW, Kwon DJ, Heo SI, Park SH, Kim SY, Hong S (2017). Oral administration of taheebo (Tabebuia avellanedae Lorentz ex Griseb.) water extract prevents DSS-induced colitis in mice by up-regulating type II T helper immune responses. BMC Complementary and Alternative Medicine, 17(1), 448. — PubMed PMID: 28877696
- McClure C, Bollen M, Buttolph L, Stack E, Langley BO, Hanes D, Wright KM, Tibbitts D, Bradley R (2022). Safety and tolerability of Pau d' Arco (Tabebuia avellanedae) for primary dysmenorrhea: A single-arm, open-label trial on adults ages 18-45. Advances in Integrative Medicine, 9(3), 159-166. — PubMed PMID: 36960315