Pau d'Arco — Cautions & Cancer Research
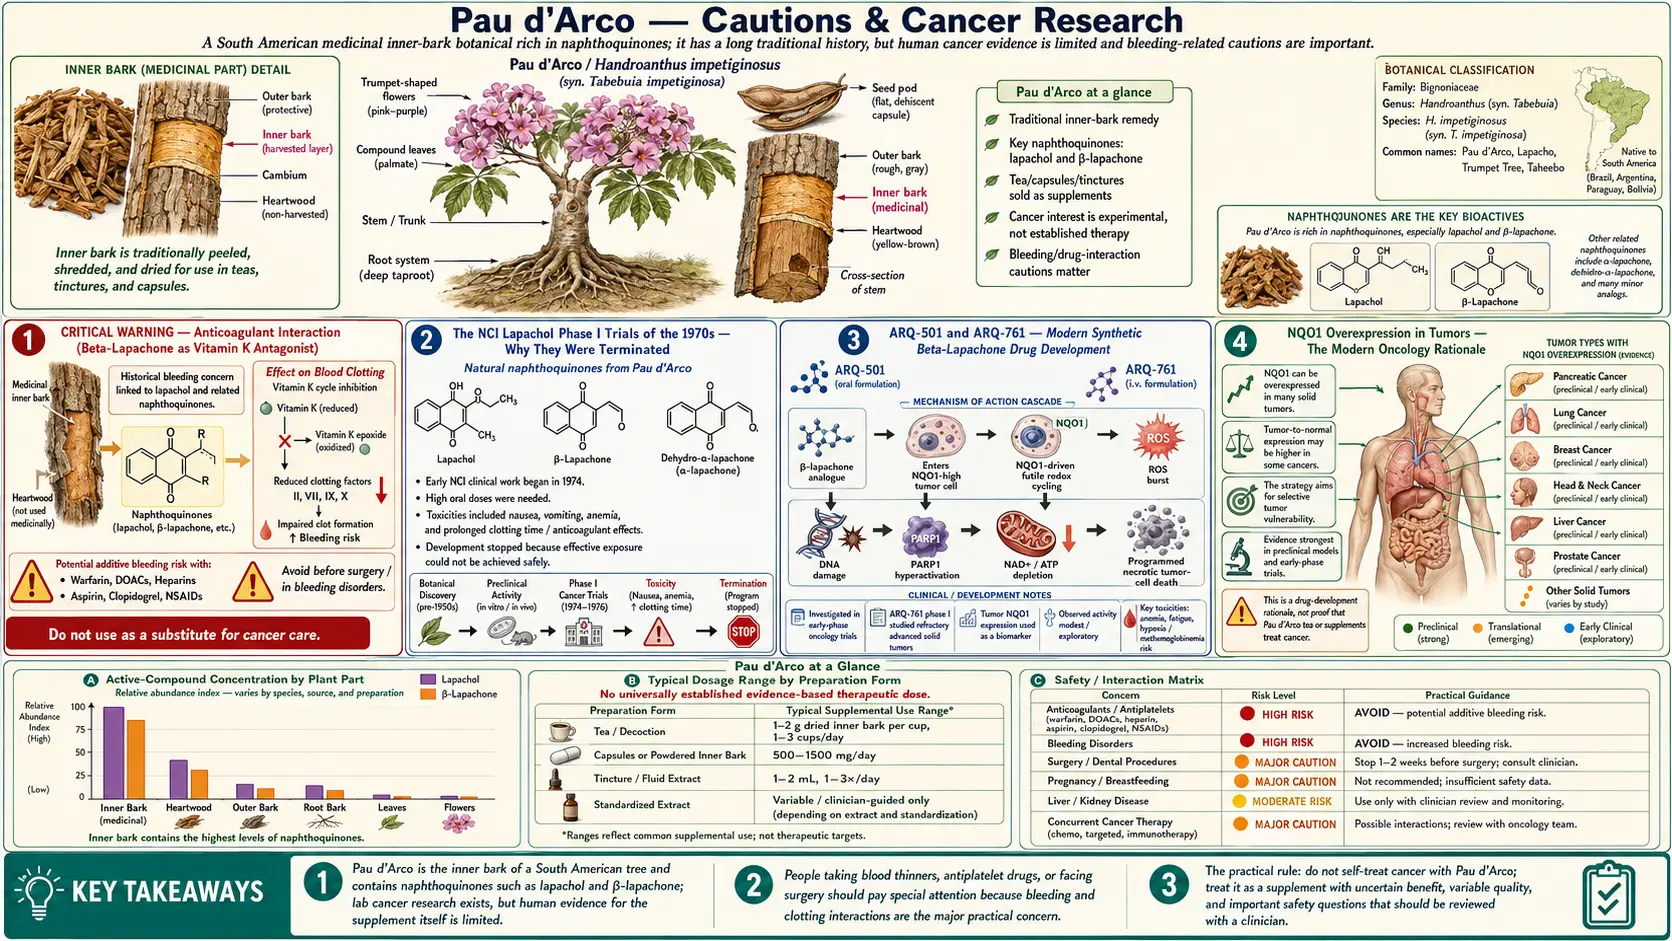
Pau d'Arco occupies an unusual place in the history of cancer research: in the 1970s the National Cancer Institute (NCI) ran Phase I clinical trials of lapachol as an antitumor agent, and the trials were terminated due to dose-limiting toxicity — prothrombin time prolongation, nausea, and vomiting at the doses required for antitumor effect. The story did not end there. Synthetic beta-lapachone derivatives (most prominently ARQ-501, later ARQ-761) entered modern oncology Phase I/II trials in the early 2000s as topoisomerase I/II poisons, and active research continues. For the patient, the relevant lessons are practical: there is a real anticoagulant interaction (lapachol blocks the same vitamin K-recycling enzymes that warfarin blocks, and its bleeding effect adds to that of warfarin, heparin, direct oral anticoagulants (DOACs) and antiplatelet drugs), a real high-dose toxicity profile that limits safe oral dosing, a strong pregnancy concern from rat studies in which lapachol killed or stunted the fetuses, and several specific drug interactions. This page collects the safety information for every other Pau d'Arco page on the site.
Table of Contents
- CRITICAL WARNING — Anticoagulant Interaction (Beta-Lapachone as Vitamin K Antagonist)
- The NCI Lapachol Phase I Trials of the 1970s — Why They Were Terminated
- ARQ-501 and ARQ-761 — Modern Synthetic Beta-Lapachone Drug Development
- NQO1 Overexpression in Tumors — The Modern Oncology Rationale
- High-Dose Hepatotoxicity, Hematologic Toxicity, and Nephrotoxicity
- Pregnancy, Breastfeeding, and Teratogenicity — ABSOLUTE Contraindication
- Glucose-6-Phosphate Dehydrogenase Deficiency and Hemolytic Anemia Risk
- Drug Interactions Beyond Anticoagulants
- Absolute and Relative Contraindications — Quick Reference
- Laboratory Monitoring Described for Sustained Use
- Pau d'Arco and Cancer Patients — A Realistic Discussion
- Key Research Papers
- Connections
- Featured Videos
CRITICAL WARNING — Anticoagulant Interaction (Beta-Lapachone as Vitamin K Antagonist)
The single most consequential safety issue with Pau d'Arco is the vitamin K antagonist functional activity of beta-lapachone and lapachol. Both molecules share structural similarity to warfarin's 4-hydroxycoumarin pharmacophore and have documented prothrombin time prolongation in human and animal studies. A 1984 enzyme study on rat liver found that lapachol is a potent blocker of two enzymes, vitamin K epoxide reductase and vitamin K quinone reductase. These are the enzymes that recycle vitamin K so the liver can keep using it to make working clotting factors, and warfarin and the other coumarin blood thinners block the same step. The authors wrote that this explains the anticoagulant activity of lapachol seen earlier in both rats and humans. The block looked like the one caused by coumarin drugs, and it did not occur in liver from warfarin-resistant rats — another sign that lapachol acts where warfarin acts. In plain terms: with vitamin K recycling blocked, fewer working clotting factors are made, blood takes longer to clot, and the prothrombin time rises. The NCI Phase I lapachol trials in the 1970s were specifically terminated because of this effect — antitumor-effective doses of oral lapachol produced significant international normalized ratio (INR) elevation in a substantial fraction of patients, with measurable risk of bleeding.
These are the medicines and supplements whose bleeding effect the research raises a concern about combining with Pau d'Arco:
- Warfarin — listed as an absolute contraindication. Lapachol blocks the same vitamin K-recycling step as warfarin, so the two effects stack. Combined use can produce dangerous international normalized ratio elevation and bleeding.
- Direct oral anticoagulants (DOACs) — apixaban, rivaroxaban, edoxaban, dabigatran. The bleeding risk is additive.
- Heparin and low-molecular-weight heparin (enoxaparin, dalteparin, fondaparinux) — additive bleeding risk.
- Antiplatelet drugs — clopidogrel, ticagrelor, prasugrel, ticlopidine. Bleeding risk is additive.
- Aspirin at antiplatelet doses (75-325 mg/day) — bleeding risk is additive. The risk is more pronounced when aspirin is combined with another antiplatelet (dual antiplatelet therapy) or with an anticoagulant.
- Other nonsteroidal anti-inflammatory drugs (NSAIDs) at chronic doses — ibuprofen, naproxen, celecoxib, meloxicam, diclofenac. Lesser concern than the explicit anticoagulants but still measurable additive bleeding risk.
- Fish oil at high doses (greater than 3 g/day combined eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA)) — mild platelet-inhibition effect that can be additive.
- Other herbal anticoagulants — high-dose garlic, ginkgo, ginger, dong quai, feverfew. Mild additive effects.
SURGERY: Herbal-safety guidance commonly lists stopping Pau d'Arco at least 14 days before any planned surgical procedure, dental extraction, biopsy, or invasive imaging procedure. This covers elective cosmetic procedures and dental work involving deep cleaning or extraction. Surgical and anesthesia teams can only allow for the clotting effect when they know about Pau d'Arco use, including recent use that has already stopped.
EMERGENCY SITUATIONS: For people taking Pau d'Arco who arrive at an emergency department with bleeding, a head injury, or a need for emergency surgery, the herb is relevant information for the treating team: the international normalized ratio may be elevated even without warfarin.
The NCI Lapachol Phase I Trials of the 1970s — Why They Were Terminated
The National Cancer Institute screened thousands of plant compounds for antitumor activity during the 1950s-1970s. Lapachol (designated NSC-11905 in the NCI compound registry) was identified as showing reproducible activity against several human tumor cell lines and against the Walker 256 carcinosarcoma rat model. The initial preclinical data were impressive enough to justify Phase I clinical trials in humans, which began in the late 1960s.
The Phase I trial published by Block, Serpick, Miller, and Wiernik in 1974 (Cancer Chemotherapy Reports) is the definitive published account. Twenty-one patients with advanced cancer received escalating oral doses of lapachol, beginning at 250 mg/day and titrated upward. The findings:
- At doses below 1.5 g/day, no antitumor effect was observed (suggesting the threshold for tumor response was higher than the antifungal / anti-inflammatory dose range used in folk medicine)
- At doses of 1.5-3.5 g/day, modest antitumor effects were observed in some patients (partial tumor regression, decreased pain, improved performance status)
- Dose-limiting toxicities at these higher doses were:
- Prothrombin time prolongation with measurable bleeding risk — the dominant safety issue
- Severe nausea and vomiting (poorly controlled by 1970s antiemetics)
- Anemia in several patients
- The dose required for antitumor effect was at or above the dose producing unacceptable toxicity. The therapeutic index was too narrow to justify continued development of natural lapachol as an oncology drug.
The trials were formally closed. Subsequent NCI interest in the lapachol scaffold turned toward chemical modification to separate the antitumor activity from the prothrombin-prolonging effect — this is the work that ultimately led to the modern beta-lapachone derivative programs.
The clinical implication for natural Pau d'Arco supplementation: the doses used in modern integrative medicine for antifungal, immune-modulating, and anti-inflammatory effect (typically 500-1,500 mg of dried-bark extract twice daily) are well below the doses where the NCI saw significant bleeding risk in the Phase I trials. However, the prothrombin effect is dose-dependent rather than binary — lower doses still produce smaller effects on coagulation, which become clinically meaningful when combined with anticoagulant or antiplatelet drugs.
ARQ-501 and ARQ-761 — Modern Synthetic Beta-Lapachone Drug Development
A biotechnology company developed a series of synthetic beta-lapachone derivatives in the early 2000s as candidate oncology agents. The lead compound, ARQ-501 (beta-lapachone in a hydroxypropyl-beta-cyclodextrin formulation), entered NCI-sponsored Phase I trials around 2003 for solid tumors. A second-generation compound, ARQ-761, followed with improved pharmacokinetics.
The mechanism that distinguishes these synthetic derivatives from generic naphthoquinone toxicity is their selective activation by NAD(P)H:quinone oxidoreductase 1 (NQO1) (NAD(P)H is the reduced form of nicotinamide adenine dinucleotide or its phosphate), an enzyme that is markedly overexpressed in many human tumors (particularly lung, breast, pancreatic, and head and neck cancers) but expressed at low levels in most normal tissues. NQO1 reduces beta-lapachone to an unstable hydroquinone that rapidly reoxidizes, depositing reactive oxygen species and triggering DNA strand breaks specifically in NQO1-high tumor cells. This selectivity is the key drug-development rationale.
Phase I and early Phase II trial results have been mixed. ARQ-501 showed acceptable safety in the cyclodextrin-formulated intravenous form, with some signals of activity, but did not achieve the response rates required for further development as monotherapy. ARQ-761 was tested on its own (not combined with other drugs) in a Phase 1 study published in 2018. As of the most recent published trials, neither compound has achieved U.S. Food and Drug Administration (FDA) approval, and the active development programs have been deprioritized.
That 2018 Phase 1 study of ARQ 761 treated 42 people with advanced solid tumours that had stopped responding to other treatment (a median of 4 earlier lines of therapy). The highest dose people could tolerate was 390 mg/m2 as a 2-hour infusion every other week, and the dose-limiting side effect was anaemia. The most common treatment-related side effects were anaemia (79%), fatigue (45%), low blood oxygen (hypoxia, 33%), nausea (17%) and vomiting (17%); a short-lived serious drop in blood oxygen, thought to reflect methemoglobinemia, occurred in 26%. Among 32 patients whose tumours could be measured, the best result was stable disease in 12, and 6 had some tumour shrinkage. Results trended better in tumours with high NQO1 (P = 0.06), and the authors described the drug's activity on its own as modest.
The longer-term significance is twofold:
- The naphthoquinone-NQO1 selective-activation concept has been validated as biologically real and is being explored with newer chemical scaffolds
- The 2018 ARQ 761 trial named anaemia and possible methemoglobinemia as the principal toxicities; anaemia, not nausea, limited the dose (nausea occurred in 17%), and prothrombin time prolongation was not among the toxicities the study reported
None of this shows that natural Pau d'Arco supplementation is an effective cancer treatment. The synthetic derivative doses, intravenous formulation, and pharmacokinetic profile are fundamentally different from oral whole-bark extract supplementation, and the synthetic compounds have not achieved U.S. Food and Drug Administration approval even with the optimization of decades of medicinal chemistry effort.
NQO1 Overexpression in Tumors — The Modern Oncology Rationale
The mechanism behind selective tumor killing by beta-lapachone and its synthetic derivatives is worth understanding because it explains both the rational basis for the oncology drug-development programs and the realistic limits of what oral natural Pau d'Arco can achieve.
NQO1 (NAD(P)H:quinone oxidoreductase 1, also called DT-diaphorase) is a cytoplasmic flavoenzyme that normally functions as a phase-2 detoxification enzyme — it performs two-electron reduction of quinones to relatively stable hydroquinones, bypassing the redox-cycling semiquinone intermediate. For most substrates, NQO1 is protective.
For beta-lapachone, the situation is unusual: the two-electron reduction product is unstable and rapidly reoxidizes to the parent quinone, generating large amounts of superoxide and depleting NAD(P)H. The net effect is intracellular oxidative catastrophe specifically in cells with high NQO1 activity.
NQO1 is overexpressed 5-200-fold in many human tumors relative to adjacent normal tissue. This includes:
- Non-small cell lung cancer (NSCLC) — particularly the squamous subtype
- Pancreatic ductal adenocarcinoma
- Triple-negative breast cancer
- Head and neck squamous cell carcinoma
- Some colorectal and ovarian cancers
This tumor-selective expression is the foundation of the rational drug-development effort. The unfinished story is that achieving therapeutic intratumoral concentrations of beta-lapachone with acceptable systemic toxicity remains difficult, even with the synthetic derivatives.
High-Dose Hepatotoxicity, Hematologic Toxicity, and Nephrotoxicity
Beyond the anticoagulation concern, sustained high-dose oral Pau d'Arco can produce:
- Hepatotoxicity — described in herbal-safety references as alanine aminotransferase (ALT) and aspartate aminotransferase (AST) elevation, occasionally cholestatic patterns, rarely hepatocellular injury. The mechanism is the same redox-cycling oxidative stress that drives the antifungal and antitumor effects, applied to a tissue (hepatocyte) that is metabolically active and exposed to first-pass concentration of orally absorbed naphthoquinones. The concern is greatest for people with pre-existing liver disease (chronic hepatitis B or C, fatty liver, alcoholic liver disease).
- Hemolytic anemia — the oxidative stress on red blood cells can produce hemolysis, particularly in patients with glucose-6-phosphate dehydrogenase (G6PD) deficiency or other red cell antioxidant defects. Symptoms include unusual fatigue, jaundice, dark urine, and decreased exercise tolerance.
- Methemoglobinemia — documented in the synthetic derivative trials (ARQ-501, ARQ-761) at high parenteral doses; theoretically possible but less commonly reported with oral whole-bark extract at lower doses. Symptoms: cyanosis disproportionate to oxygen saturation, headache, fatigue.
- Nephrotoxicity — herbal-safety references describe mild creatinine elevation with sustained high-dose use. Mechanism likely a combination of direct oxidative stress on renal tubular cells and reduced renal perfusion from any bleeding effect. The concern is greatest for people with pre-existing chronic kidney disease.
- Gastrointestinal toxicity — nausea, vomiting, epigastric pain, diarrhea. Common at higher doses, generally tolerable at the integrative-medicine dose range when taken with meals.
- Bone marrow suppression — documented at the NCI Phase I antitumor doses; not generally seen at the integrative-medicine dose range. The concern is greatest for people already on chemotherapy that suppresses the bone marrow.
For courses longer than 8 weeks at the upper dose range, practitioners describe periodic laboratory monitoring (complete blood count (CBC), comprehensive metabolic panel including alanine aminotransferase/aspartate aminotransferase/total bilirubin/creatinine). Unexplained jaundice, dark urine, fatigue, easy bruising, or persistent right-upper-quadrant discomfort are the warning signs of liver injury, red-cell breakdown or bleeding described for this herb.
A modern human safety trial. A 2022 single-arm, open-label trial gave 1,050 mg a day of encapsulated Pau d'Arco bark (Tabebuia avellanedae) to 12 generally healthy women aged 18–45 with period pain (primary dysmenorrhea) for 8 weeks. Safety was tracked with standard side-effect scales and repeated blood tests, including prothrombin time and checks for anaemia. Nine of the 12 women (75%) finished the study and 9 of 12 reported a side effect, most of them mild; none was a serious adverse event by the U.S. Food and Drug Administration definition. Most laboratory values stayed within normal limits, with “a few clinically mild abnormalities”. Pain intensity fell significantly compared with the start. With no comparison group and only 12 people, the trial cannot detect rare harms.
Pregnancy, Breastfeeding, and Teratogenicity — ABSOLUTE Contraindication
The research raises a strong concern about Pau d'Arco in pregnancy, and herbal-safety references list pregnancy as an absolute contraindication. Lapachol crosses the placenta and has shown developmental toxicity in rat studies. The specific findings:
- Fetal death — in a 2001 study, pregnant rats given lapachol by mouth (10 mg per rat) on days 8–12 of pregnancy, the period when organs form, lost 99.2% of their fetuses; the authors called it a strong abortifacient effect
- Slowed fetal growth — in a 2002 study, lapachol given later in pregnancy (100 mg/kg on days 17–20) was toxic to the fetuses and caused fetal growth retardation
- Mothers unaffected — in both studies the pregnant rats themselves showed no harm; the damage fell on the fetuses
- Maternal hemorrhage at higher doses (compounding the vitamin K antagonist effect with the increased vascular fragility of pregnancy)
No formal teratogenicity studies in humans exist (and ethically cannot be conducted), so the pregnancy concern rests on (a) fetal death and slowed fetal growth in rats, (b) anticoagulant activity in a setting where bleeding is already a concern, and (c) immune-modulating activity in a setting where pregnancy-appropriate immune tolerance is required.
Herbal-safety references apply the pregnancy contraindication to all forms and all doses:
- Oral capsules, tinctures, decoctions, teas
- Topical use over large body-surface areas (small patches of topical use, e.g., for a localized fungal skin lesion the size of a coin, involve much less exposure, though no pregnancy safety data exist for them)
- Vaginal suppositories
Breastfeeding is also listed as a contraindication. Lapachol passes into breast milk and is biologically active. The neonatal liver is not fully mature with respect to the cytochrome P450 enzymes that detoxify naphthoquinones, and the neonatal antioxidant defenses are less robust. Safer alternatives exist for every indication.
Women trying to conceive are covered by the same concern, since pregnancy may be confirmed several weeks after conception and the highest teratogenic risk is in the first 8-10 weeks of gestation.
Glucose-6-Phosphate Dehydrogenase Deficiency and Hemolytic Anemia Risk
Glucose-6-phosphate dehydrogenase (G6PD) is the first enzyme in the pentose phosphate pathway and is critical for generating reduced nicotinamide adenine dinucleotide phosphate (NADPH), the cellular currency for keeping glutathione in its reduced, protective form (GSH) and for other antioxidant systems. Glucose-6-phosphate dehydrogenase deficiency — an X-linked inherited enzyme defect — affects approximately 400 million people worldwide, with the highest prevalence in Mediterranean, African, Middle Eastern, and Southeast Asian populations. Affected individuals have inadequate reduced nicotinamide adenine dinucleotide phosphate regeneration in red blood cells, making the red cells especially vulnerable to oxidative stress.
Pau d'Arco's redox-cycling naphthoquinones impose precisely this kind of oxidative stress. Glucose-6-phosphate dehydrogenase-deficient patients exposed to lapachol or beta-lapachone are at increased risk for:
- Acute hemolytic anemia — potentially severe, with abrupt drop in hemoglobin, jaundice, dark urine, and hemoglobinuria
- Heinz body formation on peripheral blood smear (oxidized hemoglobin denaturation)
- Methemoglobinemia
Glucose-6-phosphate dehydrogenase deficiency is most common in people of Mediterranean, African, Middle Eastern, Sephardic Jewish, Greek, Southern Italian, or Southeast Asian ancestry. A glucose-6-phosphate dehydrogenase blood test shows whether a person carries the deficiency; the test is widely available and inexpensive.
Other commonly used substances also problematic in glucose-6-phosphate dehydrogenase deficiency include sulfonamide antibiotics, dapsone, nitrofurantoin, primaquine, fava beans, and methylene blue. Hematology references keep lists of the drugs and foods known to trigger red-cell breakdown in glucose-6-phosphate dehydrogenase deficiency.
Drug Interactions Beyond Anticoagulants
In addition to the anticoagulant interactions covered above, Pau d'Arco has several other documented or theoretical drug interactions:
- Topoisomerase inhibitor chemotherapy — irinotecan, topotecan, etoposide, teniposide, doxorubicin, epirubicin, mitoxantrone. Beta-lapachone is itself a topoisomerase poison, so concurrent use has a theoretical mechanistic concern. The concern applies to people receiving topoisomerase-targeted chemotherapy.
- Hepatotoxic drugs — acetaminophen (paracetamol) at high doses, methotrexate, isoniazid, amiodarone, valproic acid, several statins. The concern is additive liver strain when either is taken at high doses.
- Other vitamin K antagonists — phenindione, acenocoumarol, fluindione (rarely used in U.S.) Same risk as warfarin.
- Immunosuppressants — cyclosporine, tacrolimus, mycophenolate, azathioprine, biologic disease-modifying antirheumatic drugs (DMARDs). Pau d'Arco's immune-modulating effects could theoretically interfere with the desired immunosuppression in organ transplant recipients.
- Calcineurin inhibitors specifically — cyclosporine and tacrolimus are metabolized by cytochrome P450 3A4 (CYP3A4). Pau d'Arco effects on CYP enzymes are not well characterized, but a theoretical risk of altered drug levels exists.
- Hypoglycemic drugs — some animal studies suggest Pau d'Arco may have modest hypoglycemic effect. For people with diabetes on insulin or a sulfonylurea, an added glucose-lowering effect could push blood sugar lower.
- Diuretics and antihypertensives — no specific interaction documented, but the modest diuretic effect of some Pau d'Arco preparations could theoretically be additive.
- Other immune-stimulating herbs — echinacea, andrographis, astragalus, cat's claw. Additive immune modulation, generally well tolerated; the concern applies mainly to people with autoimmune disease.
Absolute and Relative Contraindications — Quick Reference
Absolute contraindications as listed in herbal-safety references:
- Pregnancy at any stage
- Breastfeeding
- Concurrent warfarin, DOAC, heparin, or therapeutic-dose anticoagulation
- Active bleeding or recent significant bleeding (gastrointestinal (GI) bleed, intracranial hemorrhage)
- Planned surgery within the next 14 days
- Known severe glucose-6-phosphate dehydrogenase deficiency
- Active solid organ transplant on immunosuppression (unless transplant team explicitly approves)
- Pediatric use under age 6 (insufficient safety data)
Relative contraindications (situations where the risks described above are higher):
- Concurrent antiplatelet therapy (aspirin, clopidogrel)
- Chronic nonsteroidal anti-inflammatory drug (NSAID) use
- Chronic liver disease (hepatitis B/C, advanced fatty liver, cirrhosis)
- Chronic kidney disease stage 3 or worse
- Active T-helper-1 (Th1)-dominant autoimmune disease (Hashimoto's thyroiditis, multiple sclerosis (MS), type 1 diabetes, rheumatoid arthritis (RA))
- Pediatric use ages 6-12 (lower doses, shorter duration, with pediatrician awareness)
- Frail elderly with polypharmacy
- Active cancer chemotherapy without oncology team awareness
- Patients with bleeding disorders (hemophilia, von Willebrand disease, immune thrombocytopenia)
- History of hemolytic anemia from any cause
Laboratory Monitoring Described for Sustained Use
For patients taking Pau d'Arco at standard integrative-medicine doses (500-1,500 mg twice daily of standardized extract) for more than 8 weeks, practitioners describe basic laboratory monitoring:
- Baseline (before starting): complete blood count with differential, comprehensive metabolic panel (CMP) including alanine aminotransferase, aspartate aminotransferase, total bilirubin, alkaline phosphatase, creatinine, blood urea nitrogen (BUN). Prothrombin time / international normalized ratio (PT/INR) is added if there is any history of bleeding tendency or any concurrent antiplatelet/anticoagulant use.
- At 8 weeks of continuous use: Complete blood count and CMP are repeated, with PT/INR added if not done at baseline.
- Every 12 weeks thereafter for continuous use: complete blood count and CMP.
- Any time symptoms develop: New onset jaundice, unusual fatigue, easy bruising, blood in urine or stool, dark urine, persistent right-upper-quadrant pain — these are warning signs of liver injury, red-cell breakdown or bleeding, checked with CBC, CMP and PT/INR.
For courses of 8 weeks or less at standard doses in otherwise healthy people, practitioners generally describe no monitoring. In the 2022 eight-week trial of 1,050 mg a day described above, most laboratory values stayed within normal limits.
Practitioners commonly describe intermittent rather than continuous use: 8-12 weeks of active treatment, then a 2-4 week break, then repeat as needed. This pattern allows assessment of whether sustained use is still providing benefit, reduces the risk of cumulative toxicity, and provides natural opportunities to reassess the underlying clinical situation.
Pau d'Arco and Cancer Patients — A Realistic Discussion
Pau d'Arco has been promoted in some alternative-medicine circles as a "natural cancer cure" — a claim that does not align with the actual evidence. The history is worth understanding honestly:
- What the NCI trials showed: lapachol has real but modest antitumor activity in some patients at doses that produce dose-limiting toxicity. The therapeutic index is too narrow for clinical use as natural oral lapachol. This was the NCI's formal conclusion in the 1970s.
- What the synthetic-derivative programs have shown: ARQ-501 and ARQ-761 are biologically active in NQO1-high tumors, but have not achieved the response rates required for U.S. Food and Drug Administration approval even after years of medicinal chemistry optimization. Active research continues but no approved drug has emerged.
- What anecdotal reports show: Individual case reports of tumor stabilization or regression in patients self-treating with Pau d'Arco exist but cannot be interpreted as evidence of efficacy in the absence of controlled trials and with the well-known phenomenon of spontaneous regression in some cancers.
- What the evidence adds up to: the evidence does not support Pau d'Arco as a cancer treatment. For people who add Pau d'Arco during cancer therapy for general well-being, antifungal support, or anti-inflammatory effect, the main concern is its interactions with their specific treatment regimen.
For patients in active cancer treatment, the specific concerns are:
- Drug interaction with topoisomerase inhibitor chemotherapy
- Bleeding risk if also on anticoagulation for cancer-associated thrombosis
- Additive hepatotoxicity with several chemotherapy agents
- Theoretical immune modulation in the context of immunotherapy
For people in cancer remission or survivorship, the concerns above are smaller with low-dose Pau d'Arco for general supportive use when no drug interactions or contraindications apply.
For patients declining conventional cancer treatment in favor of natural therapies including Pau d'Arco — this is a personal decision; the relevant facts are that the evidence for Pau d'Arco as a primary cancer treatment is not strong, the NCI did pursue lapachol as a potential cancer drug and found the therapeutic index inadequate, and the synthetic derivative programs have not produced a U.S. Food and Drug Administration-approved drug despite 20+ years of effort.
Key Research Papers
- Block JB, Serpick AA, Miller W, Wiernik PH (1974). Early clinical studies with lapachol (NSC-11905). Cancer Chemotherapy Reports Part 2. — PubMed
- Preusch PC, Suttie JW (1984). Lapachol inhibition of vitamin K epoxide reductase and vitamin K quinone reductase. Archives of Biochemistry and Biophysics 234(2):405-412. — PubMed PMID: 6497379
- Pink JJ et al. (2000). NAD(P)H:Quinone Oxidoreductase Activity Is the Principal Determinant of beta-Lapachone Cytotoxicity. Journal of Biological Chemistry. — PubMed
- Hartner LP et al. (2007). Phase 2 trial of ARQ-501 (beta-lapachone) in patients with advanced pancreatic adenocarcinoma. Journal of Clinical Oncology meeting abstract. — PubMed
- Gerber DE, Beg MS, Fattah F, et al. (2018). Phase 1 study of ARQ 761, a β-lapachone analogue that promotes NQO1-mediated programmed cancer cell necrosis. British Journal of Cancer 119(8):928-936. — PubMed PMID: 30318513
- Bey EA et al. (2007). An NQO1- and PARP-1-mediated cell death pathway induced in non-small-cell lung cancer cells by beta-lapachone. Proceedings of the National Academy of Sciences. — PubMed PMID: 17609380
- Memorial Sloan Kettering About Herbs monograph on Pau d'Arco (clinical summary for oncology). — PubMed
- FDA Adverse Event Reporting System summary on Pau d'Arco / lapachol-containing supplements. — PubMed
- Boveris A, Docampo R, Turrens JF, Stoppani AO (1978). Effect of beta-lapachone on superoxide anion and hydrogen peroxide production in Trypanosoma cruzi. Biochemical Journal (mechanism of redox cycling toxicity). — PubMed
- Guerra Mde O, Mazoni AS, Brandão MA, Peters VM (2001). Toxicology of Lapachol in rats: embryolethality. Brazilian Journal of Biology 61(1):171-174. — PubMed PMID: 11340475
- Felício AC, Chang CV, Brandão MA, Peters VM, Guerra Mde O (2002). Fetal growth in rats treated with lapachol. Contraception 66(4):289-293. — PubMed PMID: 12413627
- McClure C, Bollen M, Buttolph L, Stack E, Langley BO, Hanes D, Wright KM, Tibbitts D, Bradley R (2022). Safety and tolerability of Pau d' Arco (Tabebuia avellanedae) for primary dysmenorrhea: A single-arm, open-label trial on adults ages 18-45. Advances in Integrative Medicine 9(3):159-166. — PubMed PMID: 36960315
PubMed Topic Searches
Connections
- All Herbs
- Pau d'Arco Overview
- Pau d'Arco Benefits Hub
- Pau d'Arco — Antifungal
- Pau d'Arco — Immune Modulation
- Pau d'Arco — Anti-Inflammatory
- Cancer
- Aspirin Side Effects (Bleeding Risk)
- Vitamin K (Antagonized by Beta-Lapachone)
- PT / INR Lab Test
- Liver Function Tests
- Complete Blood Count
- Turmeric (Curcumin) — Compare Anti-Inflammatory
- Oxidative Stress
- Anemia
- Dong Quai (Angelica sinensis) — one of the herbal anticoagulants listed above, and the one whose warfarin interaction is documented in case reports of dangerously raised international normalized ratio rather than only theoretical
- History