Eucalyptus — Benefits Deep Dive
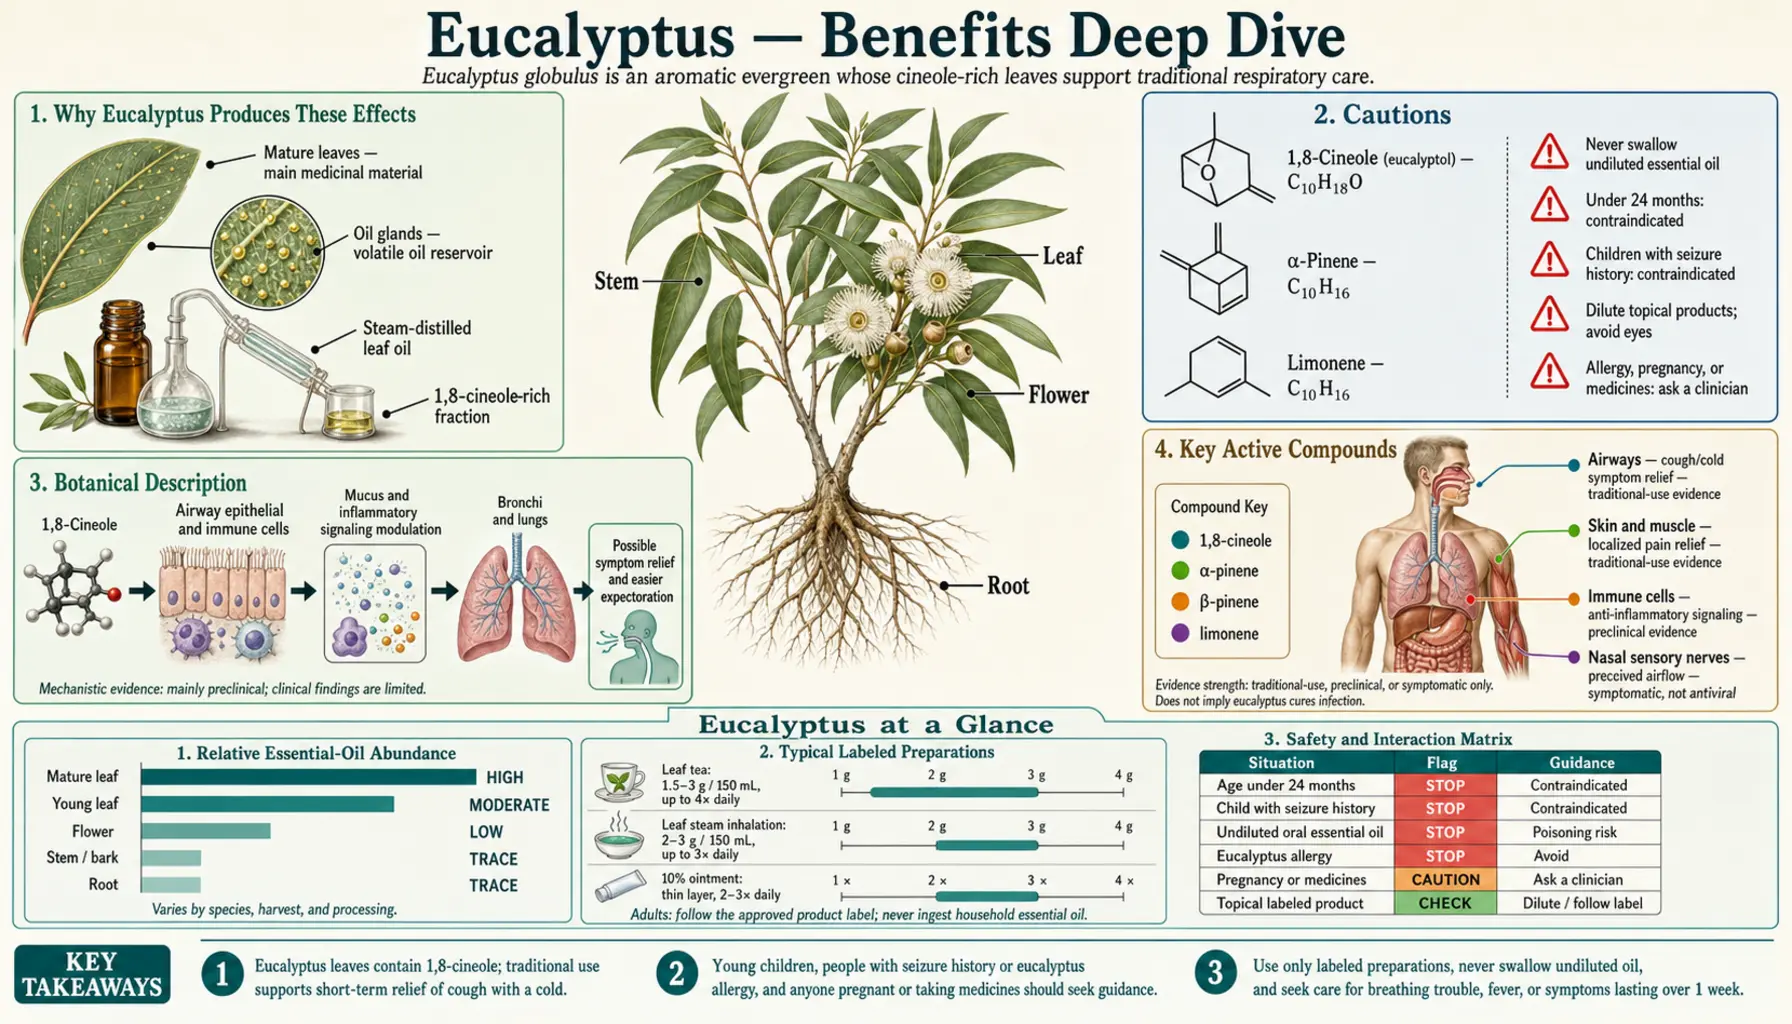
Eucalyptus is the rare medicinal plant that bridges Australian Aboriginal traditional medicine and twenty-first-century pharmacology — Aboriginal healers applied the tree's kino (a red gum resin that oozes from the bark) to wounds for tens of thousands of years, while the leaves yield a separate product, the steam-distilled essential oil, whose principal active compound, 1,8-cineole (eucalyptol), is found in camphor-menthol-eucalyptus chest rubs, menthol-eucalyptus throat lozenges, and a prescription 1,8-cineole capsule sold in Germany that has been studied in placebo-controlled trials for acute sinusitis. Two species do most of the medicinal work: Eucalyptus globulus (Tasmanian Blue Gum) supplies the 70–90% 1,8-cineole oil that drives the respiratory benefits, and Eucalyptus citriodora (lemon eucalyptus) supplies the oil from which para-menthane-3,8-diol (PMD) is refined — a mosquito repellent a 2006 review described as having DEET-like efficacy. The U.S. Centers for Disease Control and Prevention (CDC) lists oil of lemon eucalyptus as one of two plant-derived ingredients (the other is 2-undecanone) among the six EPA-registered repellent ingredients it names. The four benefit pages below explore the four clinical domains where eucalyptus produces the largest measurable effect: respiratory tract infections and chronic obstructive pulmonary disease (COPD) exacerbations, broad-spectrum antimicrobial action including methicillin-resistant Staphylococcus aureus (MRSA), topical pain and joint relief, and antifungal plus insect-repellent applications.
Deep-Dive Articles
Respiratory Health
1,8-cineole as the principal secretolytic, expectorant, and mucolytic active. The 200 mg enteric-coated 1,8-cineole capsule trials — Kehrl 2004 in acute non-purulent rhinosinusitis and Worth 2009 in chronic obstructive pulmonary disease — the traditional steam-inhalation route, over-the-counter (OTC) camphor-menthol-eucalyptus chest rubs, menthol-eucalyptus throat lozenges, and how cineole liquefies mucin disulfide bonds while disrupting respiratory biofilms.
Read the deep dive →Antimicrobial & Wound
Broad-spectrum essential-oil activity against Gram-positive and Gram-negative pathogens, methicillin-resistant Staphylococcus aureus inhibition in vitro at 0.125–1.0% v/v, dental and oral biofilm disruption (Streptococcus mutans, Porphyromonas gingivalis), the eucalyptol in essential-oil mouthwashes, and Australian Aboriginal use of kino gum-resin as a topical wound antiseptic.
Read the deep dive →Pain & Joint Relief
Topical eucalyptus for arthritis, muscle pain, tension headache, and post-surgical pain. The counter-irritant mechanism: in cell studies 1,8-cineole switches on TRPM8 cold receptors and blocks TRPA1 irritation receptors. Comparison to the menthol and camphor counter-irritant class, with which it is commonly co-formulated.
Read the deep dive →Antifungal & Insect Repellent
Candida inhibition in vitro, oil of lemon eucalyptus (OLE) for onychomycosis (nail fungus), and the standout application: lemon-eucalyptus-derived PMD (para-menthane-3,8-diol) on the U.S. Centers for Disease Control and Prevention's list of EPA-registered repellent ingredients alongside DEET, picaridin, IR3535 and 2-undecanone. PMD chemistry, EPA registration, and protection-time data against Aedes, Anopheles, and Culex.
Read the deep dive →Table of Contents
Why Eucalyptus Produces These Effects
Most medicinal plants are studied as crude leaf or bark preparations whose active compound mixture is poorly characterized. Eucalyptus is unusual in that its principal active compound, 1,8-cineole (also called eucalyptol), has been isolated to pharmaceutical purity, formulated into enteric-coated capsules (a prescription 1,8-cineole capsule sold in Germany), and tested in placebo-controlled clinical trials (see Key Research Papers). The mechanism behind each of the four benefit categories on this hub maps to a different physical or biochemical property of cineole and its companion terpenoids.
- 1,8-cineole as a secretolytic and mucolytic — cineole breaks the disulfide bonds in mucin glycoproteins, the high-molecular-weight gel-formers that give respiratory mucus its viscous character. By liquefying mucus, cineole both eases expectoration and exposes mucus-embedded respiratory bacteria (Haemophilus influenzae, Streptococcus pneumoniae, Moraxella catarrhalis) to immune clearance. This is the mechanism behind every result on the Respiratory Health page.
- Membrane-disrupting terpenoid mixture — cineole, alpha-pinene, limonene, p-cymene, and globulol are all lipophilic terpenoids that integrate into the phospholipid bilayer of bacterial cell membranes, increasing permeability and collapsing the proton motive force. Because the antibacterial effect is multi-target, bacteria struggle to develop resistance — the basis for the in-vitro methicillin-resistant Staphylococcus aureus activity covered on the Antimicrobial & Wound page.
- Counter-irritant action through TRP channels — nerve endings in the skin carry tiny temperature and irritation sensors. TRPM8 is the cold sensor that menthol also switches on; TRPA1 is a sensor for harsh cold and irritation. A 2012 laboratory study (Takaishi 2012) screened essential oils on human sensors grown in cells and found that 1,8-cineole from eucalyptus oil switched on TRPM8 (producing the characteristic cooling sensation) but not TRPA1, and blocked TRPA1 when other irritants such as menthol or mustard-oil chemicals tried to switch it on. In animal tests it calmed the irritation those chemicals caused. The authors called 1,8-cineole a rare natural blocker of human TRPA1. A closely related compound in the same oil, 1,4-cineole, switched on both sensors. These are cell and animal results, not human trials. This is the same chemical-cooling counter-irritant mechanism used by menthol (from peppermint) and camphor; the three are commonly co-formulated in chest rubs and topical muscle balms. Mechanism is detailed on the Pain & Joint Relief page.
- PMD from lemon eucalyptus as a non-DEET repellent — E. citriodora produces a fundamentally different oil dominated by citronellal, which is converted into para-menthane-3,8-diol (PMD) when the oil is refined. PMD interferes with mosquito olfactory receptors (octenol-sensing and CO2-sensing) at concentrations that approach DEET's efficacy. The U.S. Centers for Disease Control and Prevention lists oil of lemon eucalyptus and PMD among six EPA-registered repellent ingredients, with DEET, picaridin, IR3535 and 2-undecanone; it labels oil of lemon eucalyptus and 2-undecanone as plant-derived. Detail on the Antifungal & Insect Repellent page.
One safety fact stands above the rest for concentrated essential oil: undiluted eucalyptus oil on mucous membranes, inside the nostrils, or on the face of a young child is a recognised hazard. Concentrated 1,8-cineole vapor applied near the airway of a child under six can trigger reflex laryngospasm or bronchospasm severe enough to cause respiratory arrest. The same caution applies to ingestion — as little as 3.5 mL of essential oil has been fatal in pediatric case reports. The purified 1,8-cineole capsules described on the Respiratory Health page are a separate pharmaceutical preparation from the raw essential oil.
Key Research Papers
- Kehrl W, Sonnemann U, Dethlefsen U (2004). Therapy for acute nonpurulent rhinosinusitis with cineole: results of a double-blind, randomized, placebo-controlled trial. Laryngoscope 114(4):738–742. — PubMed PMID: 15064633
- Worth H, Schacher C, Dethlefsen U (2009). Concomitant therapy with cineole (eucalyptol) reduces exacerbations in COPD: a placebo-controlled double-blind trial. Respiratory Research 10(1):69. — PubMed PMID: 19624838
- Juergens UR, Dethlefsen U, Steinkamp G, Gillissen A, Repges R, Vetter H (2003). Anti-inflammatory activity of 1,8-cineol (eucalyptol) in bronchial asthma: a double-blind placebo-controlled trial. Respiratory Medicine 97(3):250–256. — PubMed PMID: 12645832
- Carroll SP, Loye J (2006). PMD, a registered botanical mosquito repellent with deet-like efficacy. Journal of the American Mosquito Control Association 22(3):507–514. — PubMed PMID: 17067054
- Mulyaningsih S, Sporer F, Zimmermann S, Reichling J, Wink M (2010). Synergistic properties of the terpenoids aromadendrene and 1,8-cineole from the essential oil of Eucalyptus globulus against antibiotic-susceptible and antibiotic-resistant pathogens. Phytomedicine 17(13):1061–1066. — PubMed PMID: 20727725
- Takaishi M, Fujita F, Uchida K, Yamamoto S, Sawada Shimizu M, Hatai Uotsu C, Shimizu M, Tominaga M (2012). 1,8-cineole, a TRPM8 agonist, is a novel natural antagonist of human TRPA1. Molecular Pain 8:86. — PubMed PMID: 23192000
- Miyazawa M, Shindo M, Shimada T (2001). Oxidation of 1,8-cineole, the monoterpene cyclic ether originated from eucalyptus polybractea, by cytochrome P450 3A enzymes in rat and human liver microsomes. Drug Metabolism and Disposition 29(2):200–205. — PubMed PMID: 11159812
- Flaman Z, Pellechia-Clarke S, Bailey B, McGuigan M (2001). Unintentional exposure of young children to camphor and eucalyptus oils. Paediatrics & Child Health 6(2):80–83. — PubMed PMID: 20084213
External Authoritative Resources
- U.S. Centers for Disease Control and Prevention — Preventing Mosquito Bites (lists oil of lemon eucalyptus and PMD among six EPA-registered repellent ingredients)
- EPA — Registered Skin-Applied Repellent Active Ingredients (PMD as one of seven registered actives)
- European Medicines Agency — Eucalypti aetheroleum (Eucalyptus oil) HMPC monograph
- European Medicines Agency — Eucalypti folium (Eucalyptus leaf) HMPC monograph
- MedlinePlus — Eucalyptus
- U.S. National Institutes of Health (NIH) U.S. National Center for Complementary and Integrative Health (NCCIH) — Eucalyptus
- PubMed — All eucalyptus globulus / 1,8-cineole research (>5,000 papers)
Cautions
- Undiluted essential oil on mucous membranes. Concentrated 1,8-cineole on nasal, oral, or ocular mucosa can cause chemical burns. Chest-rub labels warn against applying inside the nostrils.
- Children under six. Topical eucalyptus or mentholated chest rubs on the face, chest near the chin, or inside the nostrils of an infant or toddler can trigger reflex laryngospasm and bronchospasm severe enough to cause respiratory arrest. Caution against any application of camphor- or eucalyptus-containing topical preparations under age two is common; many pediatricians extend the caution to age six. Aromatherapists describe E. radiata oil at low dilution as the gentler eucalyptus species for older children.
- Lemon-eucalyptus repellents and children under 3. The U.S. Centers for Disease Control and Prevention states that products containing oil of lemon eucalyptus (OLE) or para-menthane-3,8-diol (PMD) are not for use on children under 3 years old.
- Asthma patients can experience paradoxical bronchospasm on inhaling concentrated essential oil, even though the same patients often tolerate (and benefit from) purified oral cineole capsules. Aromatherapy practice is to try a low concentration first.
- Ingestion of essential oil is potentially fatal. Three-and-a-half millilitres of pure eucalyptus essential oil has caused death in pediatric case reports; 5 mL has caused serious adult toxicity. Only pharmaceutical-grade enteric-coated cineole capsules are made for oral use, and they were studied at a 200 mg dose. A Toronto poison-centre review (Flaman 2001) counted 251 children reported to have swallowed an essential oil or oil product between December 1995 and March 1997, 50 of them eucalyptus oil; the most common symptoms were cough and vomiting, and two children had seizures and recovered. Among 18 published reports of children swallowing camphor or eucalyptus oils or products, the main symptoms were vomiting, lethargy, coma and seizures, and one child died.
- Seizure threshold. High-dose monoterpene exposure can lower seizure threshold, a concern that matters most for people with epilepsy using concentrated inhalation or oral cineole.
- Liver enzyme CYP3A4. A laboratory study of rat and human liver samples (Miyazawa 2001) found that 1,8-cineole is broken down (metabolised) mainly by the liver enzyme CYP3A4, the same enzyme that clears many prescription drugs. That study did not test whether cineole changes the levels of other medicines.
- Pregnancy and breastfeeding. Topical at proper dilution and brief steam inhalation are generally considered low-risk. There is limited safety data on oral cineole capsules in pregnancy and breastfeeding.
Connections
- All Herbs
- Eucalyptus (Main Page)
- Eucalyptus for Respiratory Health
- Eucalyptus — Antimicrobial & Wound
- Eucalyptus for Pain & Joint Relief
- Eucalyptus — Antifungal & Insect Repellent
- Antibacterial Herbs
- Peppermint (Menthol)
- Tea Tree
- Thyme
- Oregano
- Rosemary
- Sinusitis
- Chronic Obstructive Pulmonary Disease
- Asthma
- Pneumonia
- Staphylococcus aureus & Methicillin-Resistant Staphylococcus Aureus
- Cold & Flu Treatments
- Immune Boosting
- History