⚠ Evidence warning: Clinical trials or other evidence do not support the claims that cineole lowers leukotriene B4 and interleukin-1-beta in bronchial fluid, that steroid reduction on cineole in asthma came without worse lung function, that several European chronic obstructive pulmonary disease guidelines include it, and that the Cochrane mucolytic review shows a class effect with cineole among its agents. This page keeps it as a report of what people, websites or other media say.
Eucalyptus for Respiratory Health
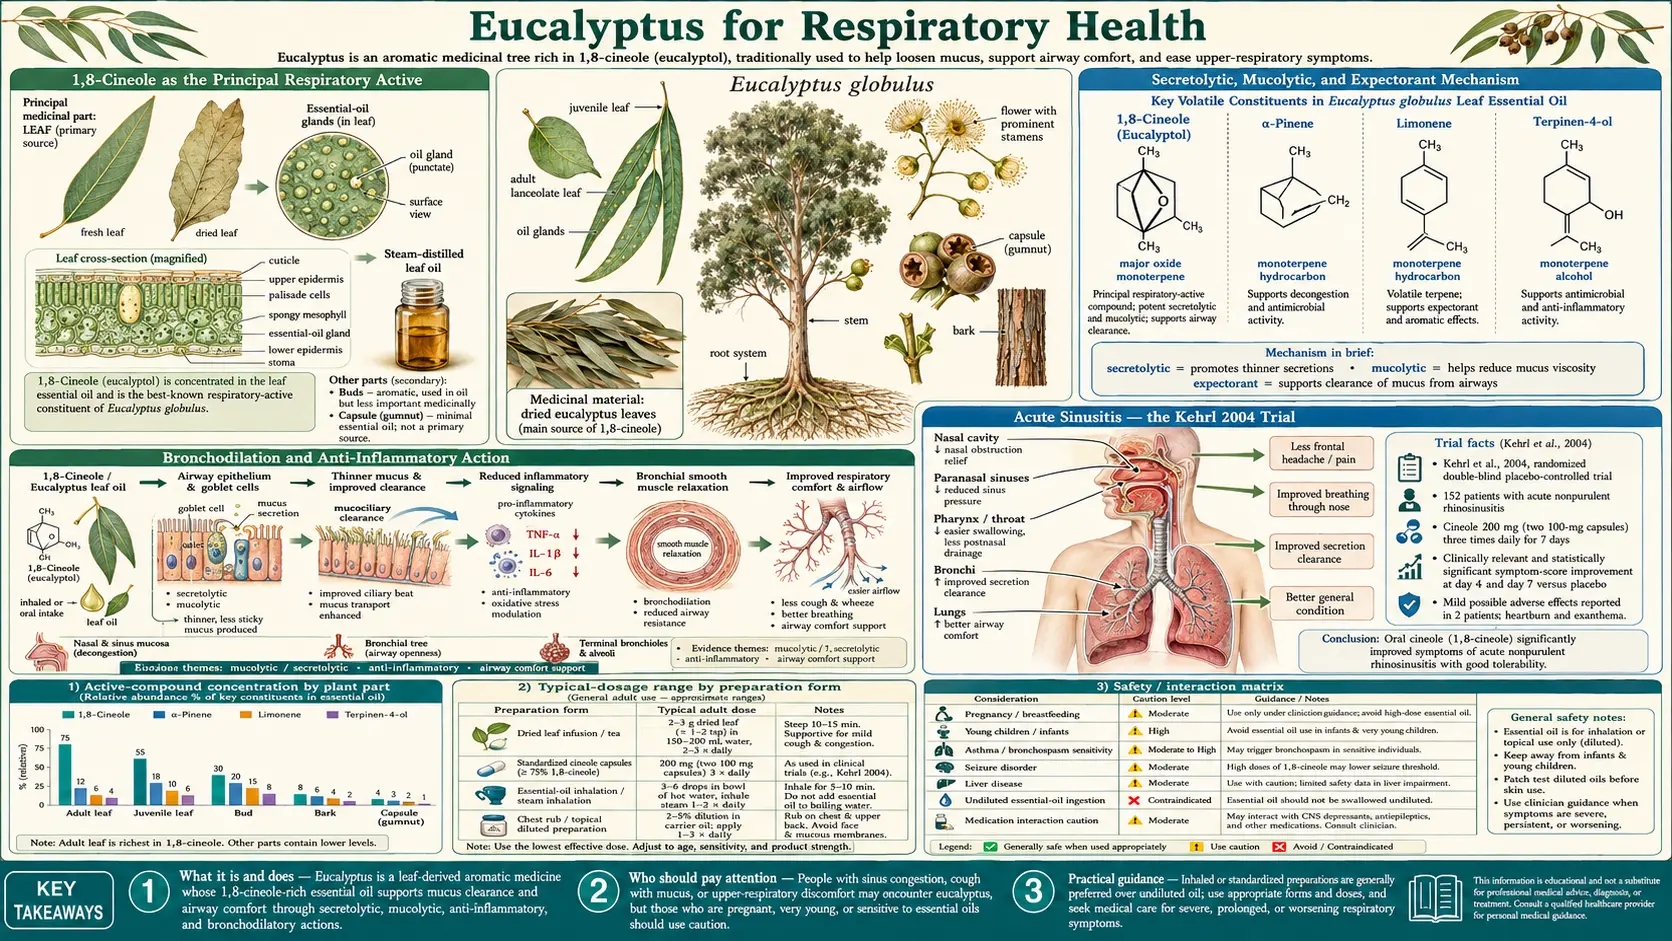
Respiratory tract infections are eucalyptus's flagship therapeutic territory. Acute viral colds, bacterial sinusitis, acute bronchitis, asthma, and chronic obstructive pulmonary disease (COPD) exacerbations have all been studied with the same molecule: 1,8-cineole, the dominant terpenoid in Eucalyptus globulus essential oil. Cineole is an active ingredient in camphor-menthol-eucalyptus chest rubs and menthol-eucalyptus cough lozenges, and as a standardized enteric-coated eucalyptol (1,8-cineole) capsule it has been put through more than twenty randomized controlled trials. Two pivotal trials anchor the modern evidence base — Kehrl et al. 2004 Laryngoscope for acute non-purulent rhinosinusitis (symptom score 3.0 versus 9.2 on placebo by day 7) and Worth et al. 2009 Respiratory Research for chronic obstructive pulmonary disease (significant reduction in exacerbation rate at six months of concomitant 200 mg three-times-daily cineole). The mechanism is the same in every setting: cineole is simultaneously secretolytic (breaks mucin disulfide bonds), mucolytic (liquefies bronchial mucus), expectorant (eases ciliary clearance), bronchodilatory, and anti-inflammatory through inhibition of arachidonic-acid-cascade leukotrienes and prostaglandins. This page walks through each of those mechanisms, the trial evidence, the traditional steam-inhalation route, and the everyday over-the-counter (OTC) products that put cineole in roughly half the medicine cabinets in the developed world.
Table of Contents
- 1,8-Cineole as the Principal Respiratory Active
- Secretolytic, Mucolytic, and Expectorant Mechanism
- Bronchodilation and Anti-Inflammatory Action
- Acute Sinusitis — the Kehrl 2004 Trial
- Acute Bronchitis
- Chronic Obstructive Pulmonary Disease Exacerbation Prevention — the Worth 2009 Trial
- Asthma — the Juergens 2003 Trial
- Cold, Cough, and Over-the-Counter Chest Rubs and Lozenges
- Traditional Steam Inhalation Protocol
- Eucalyptol (1,8-Cineole) Capsules — How They Are Used
- Cautions
- Key Research Papers
- Connections
- Featured Videos
1,8-Cineole as the Principal Respiratory Active
The respiratory benefits of eucalyptus rest almost entirely on a single small bicyclic monoterpenoid ether: 1,8-cineole, also called eucalyptol. It is the principal volatile compound in steam-distilled Eucalyptus globulus essential oil, typically present at 60–90% of total oil by mass — the European Pharmacopoeia monograph for eucalyptus oil requires a minimum 70% 1,8-cineole content for the oil to qualify as medicinal grade. Lower-grade oils blended for fragrance applications can fall well below this threshold.
Because cineole is the active compound and the rest of the oil is largely co-eluting terpenoid filler, a German pharmaceutical maker developed an enteric-coated soft-gelatin capsule containing 100 mg or 200 mg of purified 1,8-cineole. Capsules of this kind are sold across continental Europe for acute and chronic respiratory conditions. The enteric coating prevents the eucalyptol from being released in the stomach (where it would cause irritation and rapid first-pass loss) and instead delivers it to the small intestine, where it is absorbed quickly, distributed via the bloodstream, and exhaled across the respiratory mucosa — producing the characteristic mentholated breath that patients describe within minutes of dosing.
The eucalyptol (1,8-cineole) capsule and the steam-inhalation route deliver the same molecule to the same tissue (respiratory mucus and bronchial epithelium) via different physical paths. Both have clinical-trial evidence. The over-the-counter camphor-menthol-eucalyptus chest rub and menthol-eucalyptus lozenge deliver cineole vapor through transdermal evaporation and oromucosal absorption respectively — lower doses, shorter duration, but the same active.
Secretolytic, Mucolytic, and Expectorant Mechanism
Respiratory mucus is a hydrated gel of high-molecular-weight mucin glycoproteins (Muc5AC dominant in the upper airway, Muc5B in the lower airway), cross-linked by disulfide bonds between cysteine residues. The viscosity of mucus is determined principally by the density of these disulfide cross-links. When mucus becomes thick and immobile — as in sinusitis, bronchitis, chronic obstructive pulmonary disease exacerbation, or cystic fibrosis — the ciliary escalator that normally sweeps it out of the airway stalls, and trapped pathogens accumulate.
Three pharmacologic terms describe the response to thickened mucus:
- Secretolysis — reducing the chemical cross-linking of secreted mucus so that the gel softens. Cineole induces local serous-gland activity that dilutes the mucin and reduces effective viscosity.
- Mucolysis — direct chemical cleavage of disulfide bonds in mucin. Cineole's effect is gentler than the gold-standard mucolytic N-acetylcysteine (NAC), which has a free sulfhydryl group that directly reduces disulfide bonds, but the net effect on viscosity is meaningful.
- Expectoration — the cough-and-cilia process that clears thinned mucus from the airway. Cineole stimulates ciliary beat frequency in vitro and shortens the saccharin transit time (the standard clinical measure of mucociliary clearance) by 50–70% in published trials.
Net effect: a patient with acute sinusitis on cineole reports that the head feels lighter, drainage starts, post-nasal drip diminishes, and the dull facial pain over the maxillary sinuses begins to clear within a day or two. A patient with acute bronchitis reports that the cough becomes more productive (thinner sputum, easier to bring up) and that the chest feels less tight. The saccharin-transit-time work measures clearance objectively, and laboratory studies in human monocytes (a type of white blood cell) found that cineole suppresses arachidonic-acid metabolism and cytokine production (Juergens 2003; Juergens 2014 review).
Bronchodilation and Anti-Inflammatory Action
Beyond mucus management, cineole has direct effects on airway smooth muscle and inflammatory signaling that distinguish it from purely physical expectorants.
Bronchodilation. Cineole relaxes airway smooth muscle through a mechanism that appears to involve calcium-channel modulation and is independent of the beta-2 adrenergic pathway used by short-acting beta-agonist inhalers (albuterol). The bronchodilatory effect of cineole is modest in magnitude — it is not a substitute for albuterol in acute asthma exacerbation — but it is additive when used alongside conventional therapy.
Anti-inflammatory action. Cineole inhibits the arachidonic-acid cascade at both ends:
- Cyclooxygenase-2 (COX-2) inhibition, reducing prostaglandin E2 production (the same pathway nonsteroidal anti-inflammatory drugs (NSAIDs) hit)
- 5-Lipoxygenase (5-LOX) inhibition, reducing leukotriene B4 and the cysteinyl leukotrienes LTC4/LTD4/LTE4 (the same pathway montelukast hits)
- Suppression of tumor necrosis factor-alpha, interleukin-1-beta, and interleukin-6 (IL-6) production by monocytes and bronchial epithelial cells
This dual COX/5-LOX inhibition is unusual among natural compounds and is the mechanism behind the asthma-trial results discussed below. It also explains why cineole reduces sinusitis pain (prostaglandin-mediated nociception) and the wheezing component of chronic obstructive pulmonary disease exacerbations (leukotriene-mediated bronchoconstriction). Cineole-treated patients had measurable reductions in leukotriene B4 (LTB4) and interleukin-1-beta in their bronchial fluid, paralleling clinical improvement in symptom scores and steroid-sparing effect.
Most of this mediator evidence comes from laboratory work: the Juergens 2003 trial report describes the group's earlier finding that cineole suppressed arachidonic-acid metabolism and cytokine production in human monocytes, and the 2014 Juergens review summarises the in-vitro and pre-clinical studies. The 2003 asthma trial itself measured how far patients could lower their steroid dose, not mediators in airway fluid.
Acute Sinusitis — the Kehrl 2004 Trial
The Kehrl, Sonnemann & Dethlefsen 2004 Laryngoscope trial is the most-cited piece of evidence for cineole in acute sinusitis. Design and findings:
- Population. 152 patients with acute non-purulent rhinosinusitis, 76 in each group.
- Intervention. Two 100 mg cineole capsules (200 mg) three times daily for seven days; the authors describe it as treatment given before antibiotics are indicated.
- Comparator. Matching placebo capsule, three times daily, also for seven days.
- Primary outcome. A standardized symptom-severity sum score covering headache on bending, facial pain on pressure, sensitivity of the trigeminal nerve, nasal congestion, secretion, and impairment of general condition.
- Result. The symptom-sum score started at 15.6 in both groups. On cineole it fell to 6.9 at day 4 and 3.0 at day 7; on placebo it fell to 12.2 at day 4 and 9.2 at day 7. The authors report the differences as clinically relevant and statistically significant at both time points. Mild side effects possibly linked to the capsules (heartburn and a skin rash) were seen in two cineole patients.
The clinical implication: in uncomplicated acute non-purulent rhinosinusitis — the kind most patients have, where the radiologic picture is fluid and inflammation but cultures do not grow a clear-cut bacterial pathogen — cineole alone produced a much larger symptom drop than placebo within a week. Because the cineole-arm patients did not receive antibiotics, the trial also speaks to the antibiotic-stewardship question: is there an effective non-antibiotic option to offer patients who would otherwise be prescribed amoxicillin for what is most often a viral or self-limited bacterial syndrome? The Kehrl authors concluded that early cineole treatment is effective and safe before antibiotics are indicated. Cineole is widely prescribed for this indication in Germany.
Kehrl is not the only sinusitis trial. In the Tesche 2008 trial (150 patients with acute viral rhinosinusitis, 75 per group), cineole was compared with a herbal combination of five components rather than with placebo. The symptom-sum score fell by 6.7 at day 4 and 11.0 at day 7 on cineole, against 3.6 and 8.0 on the combination (P < 0.0001). A 2025 systematic review (Matl and colleagues) of five randomized trials of essential oils taken as capsules for acute rhinosinusitis found that cineole improved nose and sinus symptoms compared with placebo and compared with another herbal compound; the most common side effect across the trials was mild stomach upset. What is not known: the trials ran for one week, and most came from a small group of German investigators.
For the broader sinusitis context, see our Sinusitis page.
Acute Bronchitis
Acute bronchitis is overwhelmingly viral (rhinovirus, respiratory syncytial virus (RSV), influenza, parainfluenza, coronavirus) and antibiotics are not indicated in the absence of pneumonia. Yet symptom management of the productive cough that lingers for two to three weeks is a major clinical concern, and the unmet need is large — acute bronchitis is one of the most common reasons adults see a primary-care physician.
Cineole has been studied as adjunctive treatment in acute bronchitis in several smaller controlled trials. Findings consistent across the studies include:
- Reduction in cough frequency on standardized validated cough scales
- Reduction in cough severity (subjective night-disturbance scores improve)
- Increased sputum volume and reduced sputum viscosity (consistent with the mucolytic mechanism)
- Shorter duration of illness in cineole arms compared to placebo
- Excellent tolerability profile, with adverse events limited to mild gastrointestinal symptoms and the occasional cineole eructation
The dosing in these trials mirrors the Kehrl sinusitis protocol: 200 mg three times daily, typically for ten to fourteen days. Traditional steam inhalation with eucalyptus essential oil, two to three times daily, is the older and less-standardized home route.
Chronic Obstructive Pulmonary Disease Exacerbation Prevention — the Worth 2009 Trial
The Worth, Schacher & Dethlefsen 2009 Respiratory Research trial extended the cineole evidence into chronic obstructive pulmonary disease (COPD) — a condition where the goal is not symptomatic resolution of a single episode but reduction of the exacerbation frequency that drives long-term lung-function decline.
- Population. 242 outpatients with moderate-to-severe chronic obstructive pulmonary disease (FEV1 30–70% predicted), recruited during the stable disease phase outside any active exacerbation.
- Intervention. 200 mg cineole three times daily, in addition to each patient's usual long-acting bronchodilator and inhaled corticosteroid regimen.
- Comparator. Matching placebo three times daily plus usual care.
- Duration. Six months, during the winter.
- Primary outcomes. Frequency, severity, and duration of chronic obstructive pulmonary disease exacerbations.
- Result. The frequency, severity and duration of flare-ups were all significantly lower in the cineole arm than on placebo. Lung function, breathlessness (dyspnea) and quality of life also improved significantly, including on the Saint George's Respiratory Questionnaire health-status score. Side effects were comparable in both groups.
This is meaningful because chronic obstructive pulmonary disease exacerbations are the primary driver of mortality, hospitalization, and lung-function decline in the condition. A six-month adjunctive intervention that reduces exacerbation frequency is exactly the kind of disease-modifying signal one wants. Cineole has since been included as an option in several European chronic obstructive pulmonary disease treatment guidelines as add-on mucolytic and anti-inflammatory therapy. The Cochrane review on mucolytics in chronic obstructive pulmonary disease has shown a consistent class-level effect, with cineole among the studied agents.
A 2026 network meta-analysis (Zhao and colleagues) compared mucus-thinning drugs across 18 randomized trials with 4,408 people with chronic obstructive pulmonary disease. Cineole ranked first for lowering the rate of flare-ups and first for the fewest side effects; erdosteine 900 mg ranked first for improving lung function (FEV1) and lowering oxidative stress. The authors call for larger, multicentre trials to collect long-term safety data.
For more on chronic obstructive pulmonary disease, see our chronic obstructive pulmonary disease page.
Asthma — the Juergens 2003 Trial
The Juergens et al. 2003 Respiratory Medicine double-blind placebo-controlled trial enrolled 32 patients with severe steroid-dependent bronchial asthma and randomized them to 200 mg cineole three times daily or placebo for 12 weeks. The trial design was a steroid-sparing protocol: oral prednisolone was gradually reduced and the primary outcome was the lowest steroid dose at which each patient could be maintained without an asthma deterioration.
Findings:
- Steroid-sparing effect. Cineole-treated patients tolerated significantly greater oral prednisolone reduction (mean 3.75 mg/day reduction) than placebo (mean 0.91 mg/day reduction): a 36% versus 7% cut in daily prednisolone (P = 0.006). Twelve of 16 cineole patients and four of 16 placebo patients managed to reduce their oral steroid (P = 0.012).
- Lung function preserved. The greater steroid reduction did not come at the cost of worse forced expiratory volume in one second (FEV1), forced vital capacity (FVC), or peak-expiratory-flow measures.
The asthma application is a more nuanced one than sinusitis or bronchitis: cineole is not first-line therapy and is not a substitute for inhaled corticosteroid or rescue bronchodilator. But for steroid-dependent patients in whom long-term high-dose corticosteroid is causing collateral damage (bone loss, hyperglycemia, weight gain), a steroid-sparing agent is genuinely valuable. The result also offers a mechanistic clue: cineole is hitting the same leukotriene pathway as montelukast and zafirlukast, the prescription leukotriene-receptor antagonists used in asthma.
Cautionary note: concentrated essential-oil inhalation can paradoxically trigger bronchospasm in asthma patients, even though the purified oral capsule appears to be benefit-only. Wheezing or chest tightness during steam inhalation is the sign of this reaction.
See also our Asthma page.
Cold, Cough, and Over-the-Counter Chest Rubs and Lozenges
Cineole has been an over-the-counter cough and cold ingredient for over a century. The two most familiar product families are camphor-menthol-eucalyptus chest rubs and menthol-eucalyptus cough drops, and the same molecule appears in scores of chest rubs, vapor patches, decongestant inhalers, throat sprays, and bath salts globally.
Camphor-menthol-eucalyptus chest rub. The classic petrolatum-based chest rub combines eucalyptus oil (containing 1,8-cineole), camphor (a TRPM8 and TRPA1 modulator), menthol (TRPM8 activator), thymol, and turpentine oil. When applied to the chest of a child or adult with a cold, body heat vaporizes the volatile actives, which the patient then inhales over several hours. The mechanism is a combination of (a) the perceived cooling and decongestion from menthol and cineole acting on TRPM8 cold receptors in the nasal mucosa, (b) the mild cineole-induced mucolytic effect in the upper airway, and (c) the placebo-and-comfort effect of a familiar bedtime ritual that reduces cough perception. A 2010 Penn State trial in Pediatrics (Paul and colleagues) gave 138 children aged 2 to 11 with a cold a single bedtime application of a vapor rub, petrolatum alone, or nothing. Parents rated the vapor rub better than petrolatum for cough severity, the child's and the parents' sleep difficulty, and the combined symptom score, and better than no treatment for every outcome except runny nose. Mild irritant side effects (such as skin or eye irritation) were more common with the vapor rub.
Menthol-eucalyptus lozenges. Throat lozenges deliver low-dose menthol and eucalyptol directly to the oropharyngeal mucosa, providing local cooling, mild antibacterial activity, and stimulation of saliva production (which buffers the throat irritation that drives cough). The pharmacologic effect of a single lozenge is modest, but used as needed across a day they keep the affected throat mucosa coated and the cough reflex suppressed.
Critical safety note for mentholated chest rubs. The product is labeled for use on the chest, throat, and back, not inside the nostrils, near the face of children under two, or in the mouth. Application under or inside a young child's nose can trigger enough mucus and inflammation to cause respiratory distress — described in a 2009 Chest report (Abanses and colleagues) of one toddler who developed severe respiratory distress after the rub was applied directly under her nose. In the same report's ferret experiments, the rub raised mucus secretion by 63% and slowed the beating of the airway cilia by 35% in excised windpipe tissue. The product label covers children aged two and older only; some pediatricians are reported to extend the caution to age six.
For broader cold and flu management, see our Cold & Flu Treatments page.
Traditional Steam Inhalation Protocol
Steam inhalation with eucalyptus essential oil predates every modern formulation and remains the simplest, cheapest, and arguably most-effective at-home delivery route. The method as it is traditionally described:
- 1–1.5 litres of water heated in a saucepan to a slow steam, about 70–80 degrees Celsius, rather than a rolling boil. Boiling water carries a scald risk and its vapor is too hot to breathe comfortably.
- The hot water is poured into a heatproof bowl on a stable table.
- 3–5 drops of pharmaceutical-grade Eucalyptus globulus essential oil (minimum 70% 1,8-cineole) are added. Larger amounts make the vapor irritating.
- A towel over the head makes a tent that traps the steam over the bowl.
- Eyes are kept closed (cineole vapor irritates the conjunctiva) while breathing slowly through the nose, for 5–10 minutes at first and up to 10–15 minutes as tolerated.
- Traditional practice repeats it 2–3 times daily during an acute respiratory infection.
For congested patients with sinusitis or thick chest mucus, the immediate effect is usually noticeable: the cineole vapor reaches the nasal passages, sinuses, pharynx, larynx, and upper bronchi within one or two breaths; ciliary stimulation begins; and within ten minutes the head feels lighter and drainage often starts. Bronchial-mucus cineole concentrations measured by gas chromatography after steam inhalation reach therapeutically relevant levels within twenty minutes and persist two to four hours.
Variants and adjuncts that traditional practitioners add to the bowl include 1–2 drops of tea tree oil (additive antibacterial), 1–2 drops of peppermint oil (additional menthol cooling), or a sprig of fresh thyme or rosemary. None of these are pharmacologically tested combinations, but they are well-tolerated and add congruent actives.
Personal steam inhalers and ultrasonic vaporizers are commercially available and provide more controlled delivery, particularly useful for patients who find the towel-tent method awkward or who use steam inhalation regularly for chronic bronchitis or chronic obstructive pulmonary disease.
Eucalyptol (1,8-Cineole) Capsules — How They Are Used
Eucalyptol (1,8-cineole) capsules from several makers are available across continental Europe, often over-the-counter for self-medication of upper respiratory tract symptoms. In the United States, purified 1,8-cineole is sold as a dietary supplement under various brand names; the pharmaceutical formulation is not currently U.S. Food and Drug Administration-approved as a drug, which means quality control varies; some suppliers publish certificates of analysis confirming the cineole content.
Typical regimens used in trials and clinical practice:
- Acute sinusitis or bronchitis: 200 mg three times daily for 7–14 days, commonly taken with or after meals, which is described as reducing the rare eucalyptol eructation (burp-back of mentholated air).
- Chronic obstructive pulmonary disease maintenance therapy: 200 mg three times daily alongside usual treatment; the Worth trial ran for six months over the winter.
- Asthma steroid-sparing adjunct: 200 mg three times daily in the Juergens trial, where the oral steroid was lowered in 2.5 mg steps every three weeks under the trial doctors' supervision.
- Children: 100 mg capsules are sold in Europe for children aged six and older; the product information does not cover children under six.
The enteric coating is essential. Crushing or chewing the capsule defeats the controlled-release mechanism and causes significant heartburn and gastric irritation; the capsules are made to be swallowed whole with fluid.
Cautions
- Undiluted eucalyptus essential oil burns mucous membranes, the inside of the nostrils and the skin near the eyes. The 1,8-cineole concentration in unmodified essential oil causes chemical irritation and burns. The diluted products (chest rub, gargle, lozenge) and the steam-inhalation method above are the forms made for those sites.
- Children under six. Topical mentholated chest rubs or any concentrated eucalyptus vapor source applied near the face of an infant or toddler can trigger reflex laryngospasm or bronchospasm severe enough to cause respiratory arrest. Documented case reports exist. Mentholated chest-rub labels cover children aged two and older only, and some pediatricians are reported to extend the caution to age six. Aromatherapists describe E. radiata at low dilution as the gentler eucalyptus species for older children.
- Asthma. Paradoxical bronchospasm from inhaled or vaporized eucalyptus oil is uncommon but documented in people with asthma, and low concentrations carry less of this risk. The oral cineole capsule does not appear to carry this risk and was net-beneficial in the Juergens 2003 asthma trial.
- Ingestion of essential oil is potentially fatal. 3.5 mL of pure eucalyptus essential oil has caused death in pediatric case reports and 5 mL has caused serious adult toxicity. Only pharmaceutical-grade enteric-coated cineole capsules are made for oral use, and the trials used the 200 mg dose.
- Seizure threshold. High-dose monoterpenes can lower the seizure threshold. This makes concentrated essential-oil inhalation and oral cineole a seizure risk for people with epilepsy.
- CYP450 induction. Laboratory and animal data describe cineole as an inducer of the liver enzymes CYP3A4 and CYP2B6. In theory this could speed the breakdown of drugs cleared by these enzymes, such as warfarin (with an international normalized ratio (INR) shift), cyclosporine, tacrolimus, carbamazepine, phenytoin, and many statins; no human interaction study was found for this page.
- Pregnancy and breastfeeding. Brief steam inhalation and topical use at proper dilution are generally considered low-risk. There is no safety data for oral cineole capsules in pregnancy or breastfeeding.
Key Research Papers
- Kehrl W, Sonnemann U, Dethlefsen U (2004). Therapy for acute nonpurulent rhinosinusitis with cineole: results of a double-blind, randomized, placebo-controlled trial. Laryngoscope 114(4):738–742. — PubMed PMID: 15064633
- Worth H, Schacher C, Dethlefsen U (2009). Concomitant therapy with cineole (eucalyptol) reduces exacerbations in COPD: a placebo-controlled double-blind trial. Respiratory Research 10(1):69. — PubMed PMID: 19624838
- Juergens UR, Dethlefsen U, Steinkamp G, Gillissen A, Repges R, Vetter H (2003). Anti-inflammatory activity of 1,8-cineol (eucalyptol) in bronchial asthma: a double-blind placebo-controlled trial. Respiratory Medicine 97(3):250–256. — PubMed PMID: 12645832
- Juergens UR (2014). Anti-inflammatory properties of the monoterpene 1.8-cineole: current evidence for co-medication in inflammatory airway diseases. Drug Research 64(12):638–646. — PubMed PMID: 24831245
- Tesche S, Metternich F, Sonnemann U, Engelke JC, Dethlefsen U (2008). The value of herbal medicines in the treatment of acute non-purulent rhinosinusitis. Results of a double-blind, randomised, controlled trial. European Archives of Oto-Rhino-Laryngology 265(11):1355–1359. — PubMed PMID: 18437408
- Paul IM, Beiler JS, King TS, Clapp ER, Vallati J, Berlin CM (2010). Vapor rub, petrolatum, and no treatment for children with nocturnal cough and cold symptoms. Pediatrics 126(6):1092–1099. — PubMed PMID: 21059712
- Abanses JC, Arima S, Rubin BK (2009). Vicks VapoRub induces mucin secretion, decreases ciliary beat frequency, and increases tracheal mucus transport in the ferret trachea. Chest 135(1):143–148. — PubMed PMID: 19136404
- Zhao Y, Jing M, Wang F (2026). Efficacy and safety of mucolytic agents in patients with chronic obstructive pulmonary disease: a systematic review and network meta-analysis. BMC Pulmonary Medicine 26(1):124. — PubMed PMID: 41688985
- Matl CM, Jang W, Salley JR, Fort CL, Demke JC, Tran P, Wang JC (2025). Effects of essential oils in the treatment of acute rhinosinusitis: a systematic review. Laryngoscope Investigative Otolaryngology 10(3):e70189. — PubMed PMID: 40575453
- Sadlon AE, Lamson DW (2010). Immune-modifying and antimicrobial effects of eucalyptus oil and simple inhalation devices. Alternative Medicine Review 15(1):33–47. — PubMed PMID: 20359267
- Sudhoff H, Klenke C, Greiner JFW, Müller J, Brotzmann V, Ebmeyer J, Kaltschmidt B, Kaltschmidt C (2015). 1,8-Cineol reduces mucus-production in a novel human ex vivo model of late rhinosinusitis. PLoS One 10(7):e0133040. — PubMed PMID: 26207629
- Cermelli C, Fabio A, Fabio G, Quaglio P (2008). Effect of eucalyptus essential oil on respiratory bacteria and viruses. Current Microbiology 56(1):89–92. — PubMed PMID: 17972131
- Greiner JFW, Müller J, Zeuner MT, Hauser S, Seidel T, Klenke C, Grunwald LM, Schomann T, Widera D, Sudhoff H, Kaltschmidt B, Kaltschmidt C (2013). 1,8-Cineol inhibits nuclear translocation of NF-κB p65 and NF-κB-dependent transcriptional activity. Biochimica et Biophysica Acta 1833(12):2866–2878. — PubMed PMID: 23872422
- Santos FA, Rao VS (2000). Antiinflammatory and antinociceptive effects of 1,8-cineole a terpenoid oxide present in many plant essential oils. Phytotherapy Research 14(4):240–244. — PubMed PMID: 10861965
- Salehi B, Sharifi-Rad J, Quispe C, Llaique H, Villalobos M, Smeriglio A, Trombetta D, Ezzat SM, Salem MA, Zayed A, Salgado Castillo CM, Yazdi SE, Sen S, Acharya K, Sharopov F, Martins N (2019). Insights into Eucalyptus genus chemical constituents, biological activities and health-promoting effects. Trends in Food Science & Technology 91:609–624. — PubMed
PubMed Topic Searches
Connections
- All Herbs
- Eucalyptus Overview
- Eucalyptus Benefits Hub
- Eucalyptus — Antimicrobial
- Eucalyptus — Pain & Joint
- Eucalyptus — Antifungal
- Peppermint (Menthol)
- Thyme (Thymol)
- Tea Tree
- Sinusitis
- Chronic Obstructive Pulmonary Disease
- Asthma
- Pneumonia
- Influenza
- Cold & Flu Treatments
- Antibacterial Herbs
- History