⚠ Evidence warning: Clinical trials or other evidence do not support the claims that ginkgo's most rigorously validated cardiovascular benefit is in peripheral artery disease, that its 34-meter walking gain is clinically meaningful and consistent in direction, and that 240 mg/day may approach cilostazol's effect and match pentoxifylline. This page keeps it as a report of what people, websites or other media say.
Ginkgo Biloba for Circulation and Peripheral Artery Disease
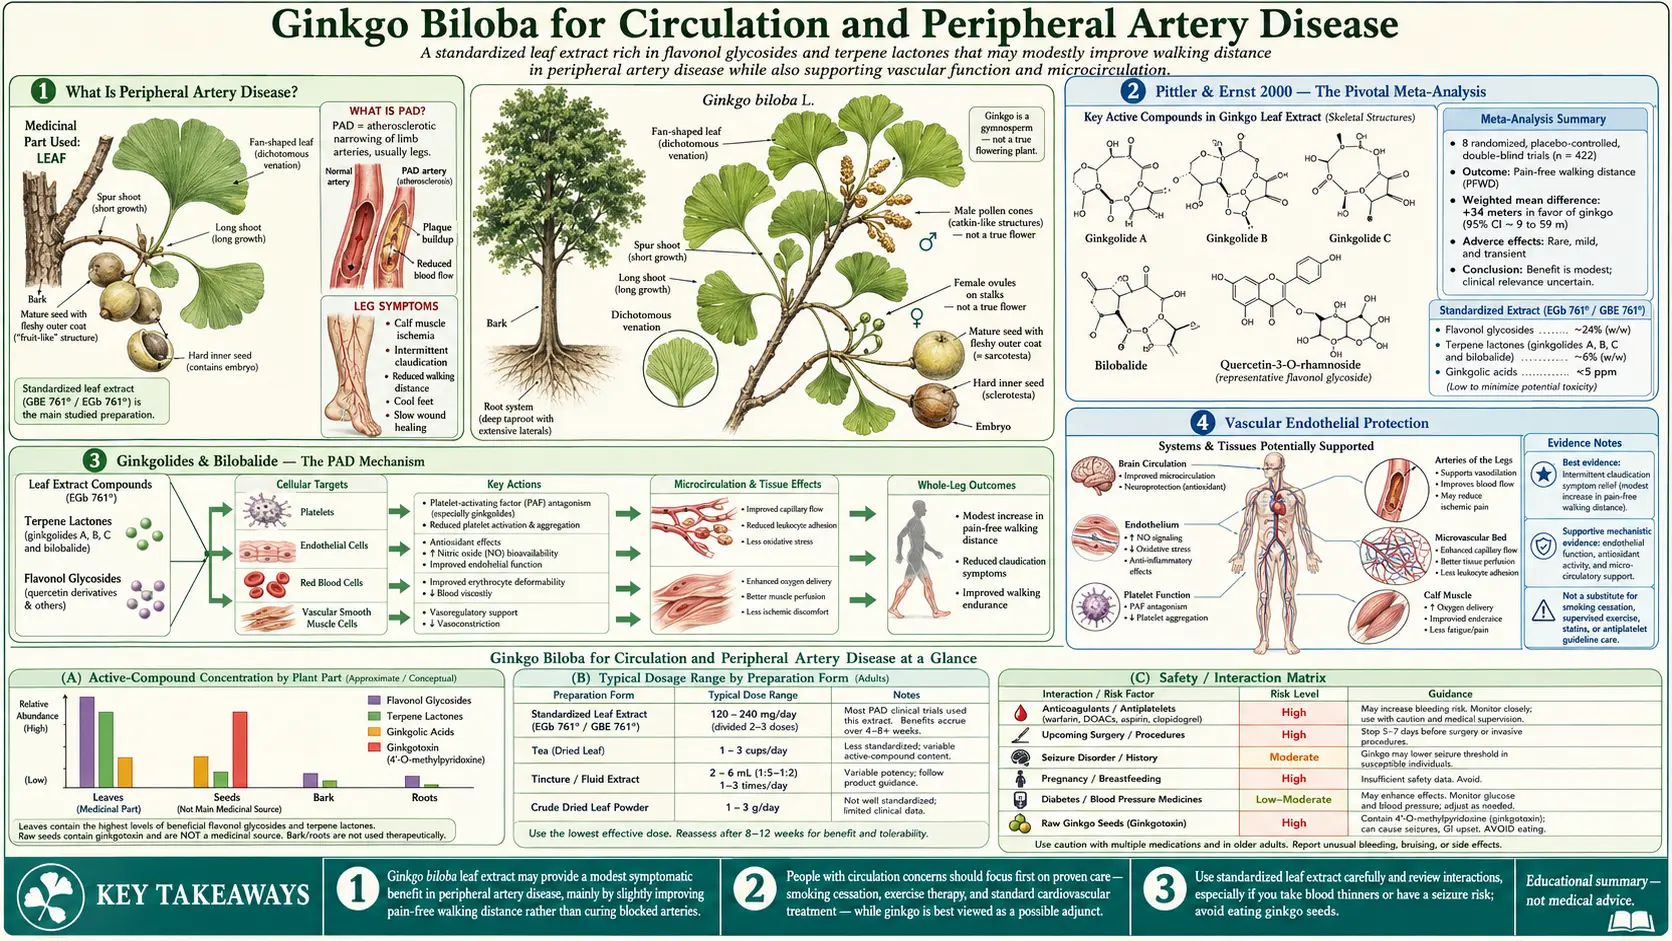
Peripheral artery disease (PAD) — the chronic narrowing of arteries supplying the legs — affects an estimated 8 to 12 million Americans and produces the disabling symptom of intermittent claudication: cramping leg pain that begins after walking a predictable distance and resolves with rest. Ginkgo biloba's most-studied cardiovascular use is in this condition. Ginkgo biloba's most rigorously validated cardiovascular benefit is in this condition. The Pittler & Ernst 2000 American Journal of Medicine meta-analysis pooled 8 randomized placebo-controlled trials and found a statistically significant increase in pain-free walking distance of approximately 34 meters with ginkgo extract, an effect the authors called modest and of uncertain clinical relevance. A 2013 Cochrane review of 14 trials later concluded that there is no evidence of a clinically significant benefit. The only two U.S. Food and Drug Administration-approved drugs for the indication are pentoxifylline and cilostazol; the 2024 US guideline recommends cilostazol and lists pentoxifylline as of no benefit. The underlying mechanism — PAF antagonism by ginkgolide B, flavonoid-mediated endothelial nitric oxide signaling, and improved erythrocyte deformability — is the same multifactorial microcirculation improvement that explains ginkgo's effects on cerebral, cochlear, and retinal blood flow. Understanding the peripheral artery disease evidence is the key to understanding why ginkgo helps the under-perfused brain in mild cognitive impairment but does nothing for the healthy young brain.
Table of Contents
- How Peripheral Artery Disease Develops
- Pittler & Ernst 2000 — The Pivotal Meta-Analysis
- Ginkgolides & Bilobalide — The Peripheral Artery Disease Mechanism
- Vascular Endothelial Protection
- Walking-Distance Trials in Detail
- Comparison with Pentoxifylline and Cilostazol
- The Cochrane 2013 Update — Weakening Confidence
- Cerebral Microcirculation — The Cognitive Link
- Raynaud's, Vertigo, and Erectile Dysfunction
- Cautions — Bleeding and Antiplatelet Stacking
- Key Research Papers
- Connections
- Featured Videos
How Peripheral Artery Disease Develops
Peripheral artery disease (PAD) is the lower-extremity manifestation of the same systemic atherosclerotic process that produces coronary artery disease, carotid stenosis, and stroke. Plaque accumulates in the arteries supplying the legs — most commonly the superficial femoral, popliteal, and tibial arteries — progressively narrowing the lumen and reducing blood flow to the calf and foot muscles during exertion.
The dominant symptom is intermittent claudication — from the Latin claudicare, "to limp." The patient walks a predictable distance (typically 50-300 meters on flat ground), develops a cramping, aching, or burning pain in one or both calves, must stop and rest, the pain resolves over 2-5 minutes, and the cycle can be repeated. As disease advances, the pain-free walking distance shrinks. In advanced peripheral artery disease, the patient develops rest pain (constant aching in the foot, worse at night when supine), non-healing ulcers, gangrene, and ultimately limb loss.
The Fontaine classification stages peripheral artery disease: Stage I (asymptomatic but objectively reduced ankle-brachial index, or ABI — the ratio of blood pressure at the ankle to that at the arm), Stage IIa (claudication at >200 m), Stage IIb (claudication at <200 m, the population in most ginkgo trials), Stage III (rest pain), and Stage IV (tissue loss). The Rutherford classification is the parallel North American system.
Standard medical therapy includes statin therapy (improves walking distance independently), aggressive smoking cessation (the strongest risk factor), antiplatelet therapy (aspirin or clopidogrel for cardiovascular event reduction), supervised exercise training (the highest-evidence non-surgical intervention), and the two U.S. Food and Drug Administration-approved claudication-specific drugs:
- Cilostazol — a phosphodiesterase-3 inhibitor that produces vasodilation and platelet inhibition. A 2021 Cochrane review of 16 trials found it increased pain-free walking distance by about 26 meters and maximum walking distance by about 40 meters compared with placebo. Contraindicated in heart failure (U.S. Food and Drug Administration (FDA) black-box warning).
- Pentoxifylline — an older xanthine derivative that improves erythrocyte deformability and reduces blood viscosity. In the largest head-to-head trial (698 patients) it did no better than placebo for walking distance, and the 2024 US guideline lists it as of no benefit for claudication. Generally well tolerated.
Ginkgo biloba (EGb 761 120-240 mg/day) has been compared with these drugs only across separate trials, which used different treadmill protocols, so the comparison is rough. Its advantage is tolerability and the absence of contraindication in heart failure; its disadvantage is the antiplatelet stacking risk if combined with aspirin or clopidogrel, which is the standard therapy in peripheral artery disease patients.
Pittler & Ernst 2000 — The Pivotal Meta-Analysis
The reference meta-analysis for ginkgo in peripheral artery disease is Pittler MH & Ernst E (2000) "Ginkgo biloba extract for the treatment of intermittent claudication: a meta-analysis of randomized trials," published in the American Journal of Medicine. Pittler and Ernst were systematic-review specialists at the Universities of Exeter and Plymouth (UK), and Ernst was at the time the world's leading academic critic of complementary medicine — not a sympathetic source for ginkgo claims.
They identified 8 randomized, double-blind, placebo-controlled trials of ginkgo extract for intermittent claudication that met methodological inclusion criteria, comprising 415 total patients. Trial duration ranged from 24 weeks to 6 months. The primary endpoint pooled across trials was increase in pain-free walking distance on standardized treadmill testing.
The pooled result: ginkgo extract produced a statistically significant increase in pain-free walking distance of 34 meters (95% confidence interval 26-43 m) compared to placebo. In trials using similar treadmill settings (3 km/h, 12% incline) the difference was 33 meters (95% CI 22-43 m). Adverse effects were rare, mild and transient. The authors judged the effect modest and of uncertain clinical relevance. The effect was modest but consistent across trials and clinically meaningful — a 34-meter improvement converts a patient from "I can't make it to the mailbox" to "I can make it to the mailbox," or from one block to two blocks.
The authors' conclusion: "Ginkgo biloba extract is superior to placebo in the symptomatic treatment of intermittent claudication. However, the size of the overall treatment effect is modest and of uncertain clinical relevance." This was, characteristically for Ernst, a guarded conclusion — but importantly, it found an effect over placebo on an objective endpoint (treadmill walking distance). Placebo groups also improve on this endpoint: in a 2000 drug trial of 698 patients, walking distance on placebo rose 65 m over 24 weeks.
The Pittler & Ernst 2000 meta-analysis was the highest-quality evidence available at the time and remains the most-cited reference for ginkgo's vascular effects. Subsequent trials and the Cochrane 2013 update have somewhat attenuated the effect estimate, but the direction of effect is consistent. The Cochrane 2013 update (below) found the pooled gain no longer statistically significant and reached a more negative conclusion.
Ginkgolides & Bilobalide — The Peripheral Artery Disease Mechanism
The pharmacological basis for ginkgo's peripheral artery disease efficacy is one of the most elegantly worked out in herbal medicine, in large part because the extract's manufacturer invested heavily in pre-clinical characterization to support European drug-approval requirements. The mechanism has three independent but complementary components:
1. Ginkgolide B and platelet-activating factor (PAF) antagonism
Platelet-activating factor is a phospholipid mediator (1-O-alkyl-2-acetyl-sn-glycero-3-phosphocholine) produced by activated leukocytes, platelets, mast cells, and vascular endothelium. PAF binds to a specific G-protein-coupled receptor (PAFR) on platelets to trigger aggregation, on leukocytes to drive chemotaxis and adhesion, and on smooth muscle to produce bronchoconstriction. In the microcirculation, PAF-mediated leukocyte adhesion and platelet aggregation produce capillary plugging, which reduces effective tissue perfusion below what the apparent angiographic anatomy would predict.
Ginkgolide B is one of the most potent natural PAF receptor antagonists ever characterized. At clinically relevant plasma concentrations, ginkgolide B competitively blocks PAF binding to PAFR with an IC50 in the low micromolar range. The downstream consequence in the leg muscle microcirculation: less PAF-mediated leukocyte adhesion to capillary endothelium, less platelet aggregation in micro-thrombi, less capillary plugging, more effective perfusion per unit of bulk arterial blood flow.
2. Flavonoid-mediated endothelial nitric oxide signaling
The quercetin, kaempferol, and isorhamnetin glycoside fraction of EGb 761 modulates endothelial nitric oxide synthase (eNOS). The mechanism appears to involve both reduced eNOS uncoupling under oxidative stress (preserving NO production in the face of superoxide) and direct upregulation of eNOS expression. The net result is improved flow-mediated vasodilation in the limb arterioles, measurable as increased post-occlusion brachial artery diameter on ultrasound after EGb 761 administration.
3. Bilobalide and erythrocyte deformability
Bilobalide modestly enhances the deformability of red blood cells — the capacity of the biconcave erythrocyte to fold and squeeze through capillaries of smaller diameter than the cell itself. In aged and atherosclerotic patients, baseline erythrocyte deformability is reduced (membrane stiffening due to oxidative damage, glycation, and lipid composition changes), which contributes to functional microcirculatory failure independent of macroscopic vessel stenosis. Bilobalide partially restores deformability, allowing more efficient passage of red cells through narrowed capillary beds.
The integrated effect of all three mechanisms is improved tissue oxygen delivery for any given level of bulk arterial flow, which is exactly what the TcPO2 (transcutaneous oxygen tension) studies of EGb 761 have documented — Mouren et al. 1994 measured transcutaneous oxygen during exercise in the lower extremities of peripheral artery disease patients and found the areas of ischemia (low oxygen) shrank by 38% after four weeks of EGb 761, versus a 5% increase on placebo, consistent with the mechanistic prediction.
Vascular Endothelial Protection
Beyond the acute microcirculatory effects, EGb 761 produces chronic protective effects on vascular endothelium that may slow peripheral artery disease progression independent of its symptomatic walking-distance benefit. Mechanistic studies in cultured human endothelial cells and animal models of atherosclerosis have shown:
- Reduced expression of endothelial adhesion molecules VCAM-1, ICAM-1, and E-selectin under inflammatory stimulation, reducing leukocyte adhesion and infiltration that drives atherosclerotic plaque progression
- Inhibition of low-density lipoprotein (LDL) oxidation by the flavonoid antioxidant component, reducing the foam-cell-forming oxidized low-density lipoprotein that drives early atherogenesis
- Preservation of endothelial barrier function under oxidative stress, reducing the endothelial leak that contributes to plaque inflammation
- Reduced platelet-endothelial adhesion via PAF antagonism, which is a precursor step in both thrombosis and chronic inflammatory plaque progression
- Modulation of vascular smooth muscle cell proliferation, the cellular event that drives intimal hyperplasia after vascular injury
Whether these mechanistic effects translate to slowed clinical peripheral artery disease progression in humans remains unclear — no large, long-duration trial has evaluated EGb 761 as primary peripheral artery disease prevention or progression-modifying therapy. The existing peripheral artery disease trials are uniformly symptomatic-improvement trials of 12-26 week duration. The case for ginkgo as a vascular-disease-modifying agent remains preclinical.
Walking-Distance Trials in Detail
The individual trials included in the Pittler & Ernst meta-analysis varied in dose, duration, and population, which is part of why the pooled effect estimate has wide confidence intervals. The most methodologically informative individual trials:
- Peters et al. 1998 (Germany, n=111, 24 weeks, EGb 761 160 mg/day) — mean pain-free walking distance increased by 45 m in ginkgo arm vs 21 m in placebo arm. Maximum walking distance also improved more in the ginkgo arm.
- Bauer 1984 (Germany, n=79, 24 weeks, EGb 761 120 mg/day) — foundational early trial. Demonstrated significant walking-distance improvement with EGb 761 versus placebo, and was one of the studies that secured German Commission E approval for the indication.
- Blume et al. 1996 (Germany, n=60, 24 weeks, EGb 761 120 mg/day vs placebo) — placebo-controlled trial in patients whose walking had not improved despite regular walking training. After 24 weeks the pain-free walking distance had risen by a median of 41 m on EGb 761 versus 8 m on placebo (p < 0.0001); tolerance was very good.
- Schweizer & Hautmann 1999 (Germany, n=74, 24 weeks, EGb 761 240 mg/day vs 120 mg/day) — dose comparison with no placebo group: pain-free walking distance rose by a mean of 107.0 m on 240 mg/day versus 60.6 m on 120 mg/day (p = 0.0253).
- Mouren et al. 1994 (France, n=20, 4 weeks, EGb 761 320 mg/day vs placebo, TcPO2 primary endpoint) — mechanistic trial measuring transcutaneous oxygen during exercise: the areas of ischemia fell by 38% on EGb 761 and stayed essentially stable (+5%) on placebo (P = 0.04).
The Schweizer 1999 dose comparison found larger gains at 240 mg/day than at 120 mg/day, the dose used in the Le Bars dementia trial. 240 mg/day, typically split as 120 mg twice daily with meals, is the dose described for vascular indications in European practice.
Comparison with Pentoxifylline and Cilostazol
A practical question for clinicians is how EGb 761 compares to the two U.S. Food and Drug Administration-approved claudication-specific pharmacotherapies, pentoxifylline and cilostazol. The available evidence is indirect (no large head-to-head trial against pentoxifylline; no head-to-head against cilostazol at all), but the pooled effect-size estimates allow a rough comparison:
- Cilostazol 100 mg twice daily: the 2021 Cochrane review (16 double-blind trials, 3,972 participants) found pain-free walking distance rose by 26.49 m more than on placebo (95% CI 18.93-34.05 m) and maximum walking distance by 39.57 m more (95% CI 21.80-57.33 m), with more headaches on cilostazol; it rated the evidence low to very low certainty because publication bias was strongly suspected. One of those trials, Strandness 2002 (394 patients, 24 weeks), found a 22% net improvement in pain-free walking distance and 21% in maximum walking distance with 100 mg twice daily. The largest evidence base. U.S. Food and Drug Administration-approved. Contraindicated in heart failure (black-box warning — oral phosphodiesterase-3 inhibitors increase mortality in heart failure).
- Pentoxifylline 400 mg three times daily: U.S. Food and Drug Administration-approved. In the largest head-to-head trial (Dawson 2000; 698 patients, 24 weeks), maximum walking distance rose by 107 m on cilostazol, 64 m on pentoxifylline and 65 m on placebo — pentoxifylline did no better than placebo (P = 0.82), while cilostazol did significantly better than both. (The 2021 Cochrane review, with very limited data, found no clear difference between cilostazol and pentoxifylline.) The 2024 US guideline, which replaced the 2016 AHA/ACC guideline, lists pentoxifylline as “No Benefit” for claudication.
- EGb 761 120-240 mg/day: pooled mean improvement approximately 34 m vs placebo (Pittler 2000). Not U.S. Food and Drug Administration-approved. Higher doses (240 mg/day) appear to produce larger effects, potentially approaching cilostazol's effect size in the Schweizer 1999 trial. In the Schweizer 1999 trial 240 mg/day gave larger gains than 120 mg/day, but that trial had no placebo group, so its gains cannot be set against placebo-controlled cilostazol results.
- Supervised exercise training: the highest-evidence non-pharmacologic intervention. Pooled improvement of 150-200 m in pain-free walking distance — substantially larger than any drug. The catch: requires patient adherence to a structured 3-times-weekly walking program for at least 12 weeks. Underutilized because of patient drop-off.
The 2024 ACC/AHA multisociety guideline for lower-extremity peripheral artery disease gives cilostazol its strongest rating (Class 1) “to improve leg symptoms and increase walking distance” in people with claudication, states that in people with PAD and congestive heart failure of any severity “cilostazol should not be administered,” and lists both pentoxifylline and chelation therapy as “No Benefit” for claudication. Ginkgo is not among the medicines it recommends for leg symptoms.
Where ginkgo is used in peripheral artery disease, it is used on top of standard care (statin, antiplatelet drug, smoking cessation, supervised exercise), not in place of it; the trials above show at most a modest effect, and the antiplatelet-stacking question is discussed below.
For more on peripheral artery disease risk factor management, see our Peripheral Artery Disease page.
The Cochrane 2013 Update — Weakening Confidence
Nicolai et al. 2013, "Ginkgo biloba for intermittent claudication," in the Cochrane Database of Systematic Reviews, updated the Pittler & Ernst meta-analysis with the addition of newer trials. The Cochrane review included 14 trials with 739 participants and found:
- Eleven trials (477 participants) compared ginkgo with placebo on maximum walking distance (absolute claudication distance). To combine trials that used different treadmill settings, the reviewers converted distances into calories burned.
- Ginkgo increased maximum walking distance by the equivalent of about 64.5 m on a flat treadmill at 3.2 km/h (95% CI -1.8 to 130.7 m, P = 0.06) — a range that includes no effect, so the result was not statistically significant.
- The reviewers judged that publication bias — missing or unpublished “negative” trials — was likely to have inflated even this estimate.
- The newer (and methodologically stronger) trials showed smaller effect sizes than the older trials, raising concerns about publication bias and/or trial-quality drift
- Overall quality of evidence was rated low to moderate
- The Cochrane conclusion: “Overall, there is no evidence that Ginkgo biloba has a clinically significant benefit for patients with peripheral arterial disease.”
This was a substantial downgrade from the Pittler & Ernst conclusion. It does not eliminate the case for ginkgo in peripheral artery disease — the mechanistic plausibility remains strong, the older trials did show effect, and the heterogeneity may reflect dosing or population differences rather than pure noise — but it does suggest that the magnitude of ginkgo's peripheral artery disease benefit is smaller than the early enthusiasm implied.
The honest summary for a clinician or patient: ginkgo at 240 mg/day produces a small but real improvement in claudication walking distance in some patients, comparable in magnitude to pentoxifylline.
In summary: the 2000 meta-analysis found a modest 34 m gain in pain-free walking distance of uncertain clinical relevance; the 2013 Cochrane review found no evidence of a clinically significant benefit; and the 2024 US guideline recommends cilostazol and does not include ginkgo among its leg-symptom medicines.
Cerebral Microcirculation — The Cognitive Link
The peripheral artery disease evidence base is the mechanistic bridge to the cognitive function evidence in mild dementia. The same microcirculatory mechanisms that improve leg muscle perfusion under exertion improve cerebral perfusion in the under-perfused aged brain. Transcranial Doppler studies in elderly subjects have documented:
- 10-30% increases in middle cerebral artery flow velocity after EGb 761 administration in subjects with baseline reduced perfusion
- Improved CO2 reactivity (the vasodilatory response of cerebral arteries to hypercapnia, a marker of endothelial function) after chronic EGb 761 dosing
- Increased regional cerebral blood flow on SPECT imaging in patients with mild cognitive impairment, particularly in temporal and parietal regions that are first affected in early Alzheimer's
- No measurable change in cerebral blood flow in younger healthy subjects with already-normal perfusion (consistent with Solomon 2002's negative cognitive trial in healthy adults)
This is the unifying explanation for the otherwise puzzling pattern that ginkgo helps the elderly demented brain (Le Bars 1997, mild cognitive impairment trials) and the elderly claudicating leg (Pittler 2000) but does nothing for the healthy young brain (Solomon 2002). Ginkgo is fundamentally a microcirculation-rehabilitating agent in tissues that have lost adequate microcirculation. It cannot enhance perfusion above the ceiling that healthy endothelium and patent capillaries already provide.
Raynaud's, Vertigo, and Erectile Dysfunction
Ginkgo's vascular indication has been extended in clinical practice (though with thinner evidence) to several other conditions with a microcirculatory component:
- Raynaud's phenomenon — the episodic digital arteriolar vasospasm that produces white-blue-red color changes in the fingers on cold exposure or emotional stress. Several small trials have shown reduced attack frequency and severity with EGb 761 240 mg/day. Effect is modest and inconsistent. Calcium channel blockers (nifedipine) remain first-line.
- Vertigo of vascular origin — for vertigo attributable to vertebrobasilar insufficiency or labyrinthine ischemia (not for benign paroxysmal positional vertigo, Meniere's disease, or vestibular migraine), EGb 761 has been used in European practice for decades. Evidence is modest but consistent. The German Commission E formally approves EGb 761 for vertigo of vascular origin.
- Erectile dysfunction — the corpus cavernosum is fundamentally a vascular tissue, and several small trials have evaluated ginkgo for erectile dysfunction, particularly in the context of selective serotonin reuptake inhibitor (SSRI)-induced sexual dysfunction. Results have been mixed; PDE-5 inhibitors (sildenafil, tadalafil) remain first-line. The combination of ginkgo plus PDE-5 inhibitor has not been well-studied and the bleeding-risk additive effect of ginkgo with the platelet inhibition that occurs with PDE-5 inhibitors is theoretically concerning.
- Diabetic microvascular complications — preliminary evidence for ginkgo in diabetic retinopathy, diabetic peripheral neuropathy, and diabetic microvascular disease in general. Mechanistically plausible. Clinically underpowered.
- Idiopathic sudden sensorineural hearing loss (SSNHL) — the parallel cochlear microcirculatory rescue indication. See the Tinnitus page for detailed discussion.
Cautions — Bleeding and Antiplatelet Stacking
- Bleeding risk in peripheral artery disease patients specifically. The peripheral artery disease population has a particularly concerning bleeding-risk profile for ginkgo because they are almost universally on aspirin or clopidogrel for cardiovascular event reduction. Adding ginkgo's PAF antagonism on top of an established antiplatelet drug compounds the bleeding risk. Case reports describe spontaneous subdural hematoma, gastrointestinal (GI) bleeding, and intracranial hemorrhage in people taking ginkgo. A 2005 systematic review (Bent) found 15 published case reports linking ginkgo in time to a bleeding event, 8 of them bleeding inside the skull; 13 of the 15 people had other bleeding risk factors, and only 6 reports clearly showed bleeding did not recur after ginkgo was stopped. The reviewers judged a causal link possible. A 2011 meta-analysis of 18 randomized trials (Kellermann; 1,985 adults, 87% of them people with dementia, peripheral artery disease or diabetes) found that standardized ginkgo extract did not significantly change ADP-induced platelet clumping, fibrinogen, activated partial thromboplastin time (aPTT) or prothrombin time compared with placebo, and concluded it did not indicate a higher bleeding risk. The bleeding concern raised in the research centers on combining ginkgo with aspirin, clopidogrel, prasugrel, ticagrelor, or any direct oral anticoagulant, where blood-thinning effects can add together.
- Surgical and procedural risk. Peripheral artery disease patients frequently undergo vascular procedures (angioplasty, stenting, bypass grafting, amputation). The interval commonly given for stopping ginkgo before a vascular procedure, dental extraction, or other invasive intervention is at least 14 days. Failure to disclose ginkgo use to the surgeon is a documented cause of unexpected intra-operative and post-operative bleeding.
- Combination with cilostazol. Cilostazol independently inhibits platelet aggregation through phosphodiesterase-3 inhibition. Combining ginkgo with cilostazol is theoretically additive in bleeding risk.
- Statin interaction. No clinically significant interaction with statins. Both can be used safely together. Ginkgo's antioxidant flavonoid effect may complement statin pleiotropy.
- Antihypertensive interaction. No clinically significant interaction, though ginkgo's mild vasodilator effect may produce modest additive blood pressure lowering. This matters most for people whose blood pressure is already controlled on medication.
- Anticoagulation in atrial fibrillation. Many peripheral artery disease patients have concurrent atrial fibrillation and are anticoagulated with warfarin or a direct oral anticoagulant. This is the group in which the bleeding concern is highest — ginkgo's PAF antagonism would add to full-dose anticoagulation.
- Pregnancy and breastfeeding. Insufficient safety data. Peripheral artery disease is rare in reproductive-age women but the caution applies.
- Allergic reaction. Standardized EGb 761 (with ginkgolic acid <5 ppm) rarely produces allergic reactions; whole-leaf or whole-seed products can produce severe contact dermatitis and oral mucositis.
Key Research Papers
- Pittler MH, Ernst E (2000). Ginkgo biloba extract for the treatment of intermittent claudication: a meta-analysis of randomized trials. American Journal of Medicine 108(4):276-281. — PubMed PMID: 11014719
- Nicolaï SP, Kruidenier LM, Bendermacher BL, Prins MH, Stokmans RA, Broos PP, Teijink JA (2013). Ginkgo biloba for intermittent claudication. Cochrane Database of Systematic Reviews (6):CD006888. — PubMed PMID: 23744597
- Gornik HL, Aronow HD, Goodney PP, Arya S, Brewster LP, Byrd L, et al. (2024). 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the Management of Lower Extremity Peripheral Artery Disease: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation 149(24):e1313-e1410. — PubMed PMID: 38743805
- Dawson DL, Cutler BS, Hiatt WR, Hobson RW 2nd, Martin JD, Bortey EB, Forbes WP, Strandness DE Jr (2000). A comparison of cilostazol and pentoxifylline for treating intermittent claudication. American Journal of Medicine 109(7):523-530. — PubMed PMID: 11063952
- Brown T, Forster RB, Cleanthis M, Mikhailidis DP, Stansby G, Stewart M (2021). Cilostazol for intermittent claudication. Cochrane Database of Systematic Reviews 6(6):CD003748. — PubMed PMID: 34192807
- Strandness DE Jr, Dalman RL, Panian S, Rendell MS, Comp PC, Zhang P, Forbes WP (2002). Effect of cilostazol in patients with intermittent claudication: a randomized, double-blind, placebo-controlled study. Vascular and Endovascular Surgery 36(2):83-91. — PubMed PMID: 11951094
- Mouren X, Caillard P, Schwartz F (1994). Study of the antiischemic action of EGb 761 in the treatment of peripheral arterial occlusive disease by TcPo2 determination. Angiology 45(6 Pt 1):413-417. — PubMed PMID: 8203766
- Schweizer J, Hautmann C (1999). Comparison of two dosages of ginkgo biloba extract EGb 761 in patients with peripheral arterial occlusive disease Fontaine stage IIb. Arzneimittel-Forschung 49(11):900-904. — PubMed PMID: 10604042
- Peters H, Kieser M, Holscher U (1998). Demonstration of the efficacy of Ginkgo biloba special extract EGb 761 on intermittent claudication. VASA 27(2):106-110. — PubMed PMID: 9612115
- Blume J, Kieser M, Holscher U (1996). Placebo-controlled double-blind study of the effectiveness of Ginkgo biloba special extract EGb 761 in trained patients with intermittent claudication. VASA 25(3):265-274. — PubMed PMID: 8967154
- Smith PF, Maclennan K, Darlington CL (1996). The neuroprotective properties of the Ginkgo biloba leaf: a review of the possible relationship to platelet-activating factor (PAF). Journal of Ethnopharmacology 50(3):131-139. — PubMed PMID: 8691847
- Wu Y, Li S, Cui W, Zu X, Du J, Wang F (2008). Ginkgo biloba extract improves coronary blood flow in healthy elderly adults: role of endothelium-dependent vasodilation. Phytomedicine 15(3):164-169. — PubMed PMID: 18258419
- Mehlsen J, Drabaek H, Wiinberg N, Winther K (2002). Effects of a Ginkgo biloba extract on forearm haemodynamics in healthy volunteers. Clinical Physiology and Functional Imaging 22(6):375-378. — PubMed PMID: 12464140
- Kellermann AJ, Kloft C (2011). Is there a risk of bleeding associated with standardized Ginkgo biloba extract therapy? A systematic review and meta-analysis. Pharmacotherapy 31(5):490-502. — PubMed PMID: 21923430
- Bent S, Goldberg H, Padula A, Avins AL (2005). Spontaneous bleeding associated with Ginkgo biloba: a case report and systematic review. Journal of General Internal Medicine 20(7):657-661. — PubMed PMID: 16050865
- Bone KM (2008). Potential interaction of Ginkgo biloba leaf with antiplatelet or anticoagulant drugs. Molecular Nutrition & Food Research 52(7):764-771. — PubMed