Ginkgo Biloba for Cognitive Function and Memory
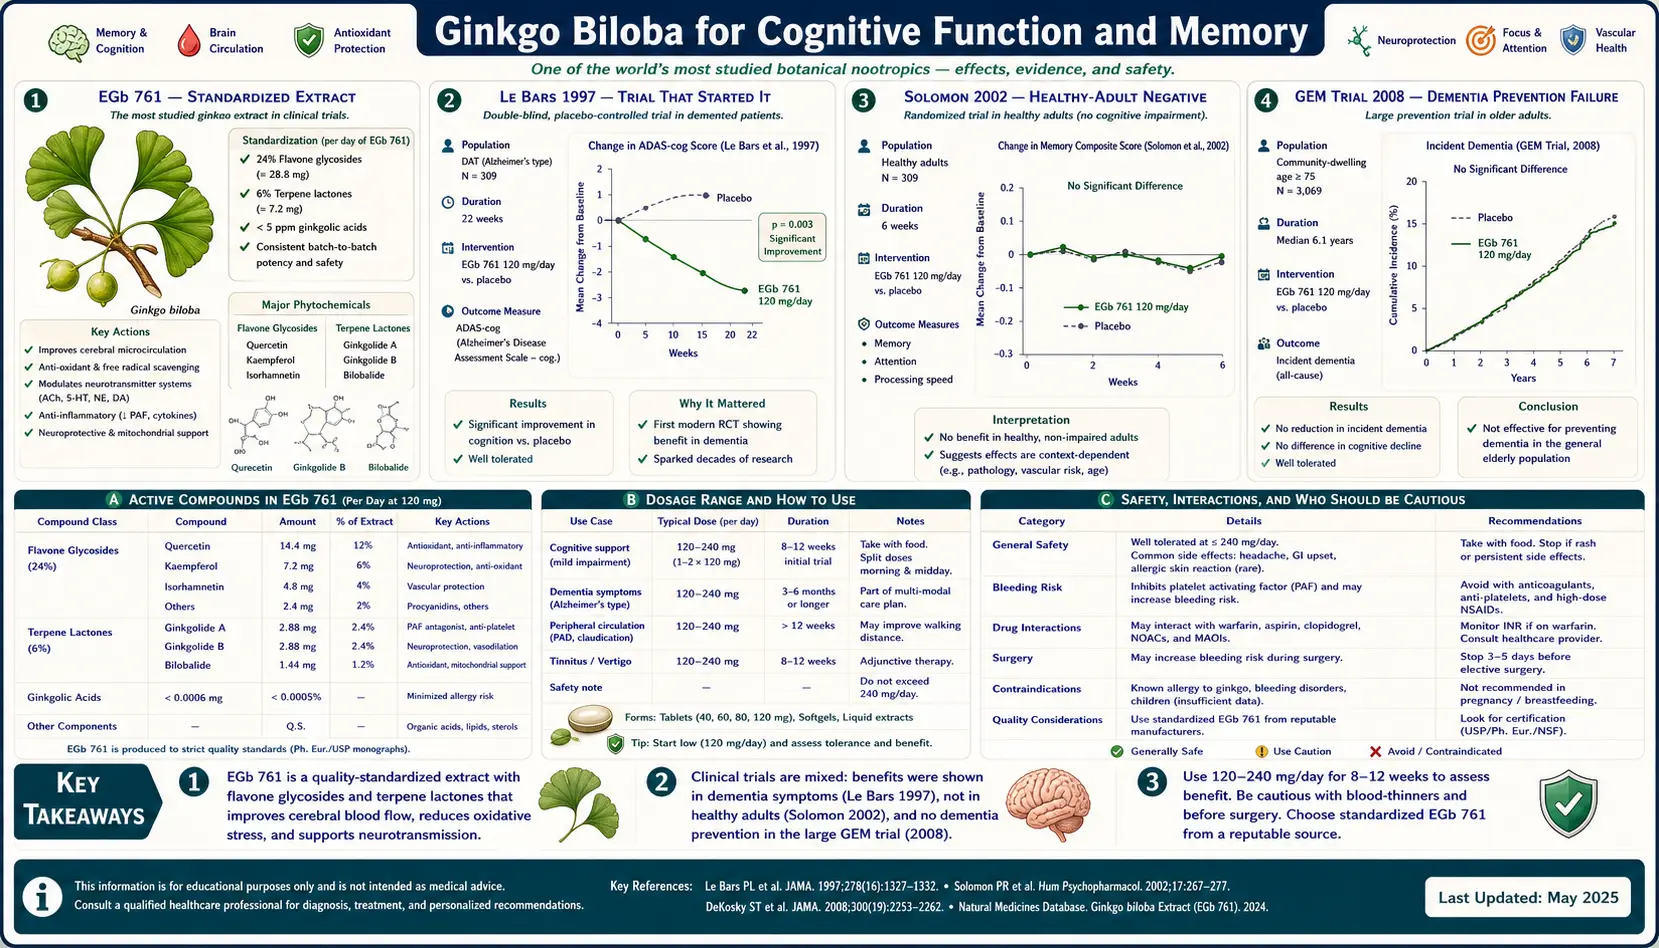
Ginkgo biloba is the single most-studied botanical for memory and cognitive function. In Germany, the standardized extract EGb 761 carries formal regulatory approval for treatment of mild dementia and is the most commonly prescribed cognitive medication after the cholinesterase inhibitors. In the United States, ginkgo's reputation is more divided — the Le Bars 1997 JAMA trial produced a sensation by showing measurable cognitive improvement in Alzheimer's patients, while the much larger 2008 GEM (Ginkgo Evaluation of Memory) trial conclusively showed that ginkgo does not prevent dementia in cognitively normal older adults. The pattern that emerges across roughly 100 randomized trials is that ginkgo helps the under-perfused brain (mild vascular cognitive impairment, early dementia) but does nothing useful for the healthy brain. The size of the benefit is real but modest, most trials showing benefit used the standardized EGb 761 at 240 mg/day, and the comparison to donepezil is closer than either side of the cholinesterase-inhibitor debate likes to admit.
Table of Contents
- EGb 761 — The Standardized Extract
- Le Bars 1997 — The Trial That Started It
- Solomon 2002 — The Healthy-Adult Negative
- The GEM Trial 2008 — Dementia Prevention Failure
- Mild Cognitive Impairment (MCI) — The Sweet Spot
- Comparison to Donepezil
- European Regulatory Position
- Mechanism — Why It Works (When It Works)
- Dosing Protocol — What the Trials Used
- Cautions — Bleeding, Seizures, and Selective Serotonin Reuptake Inhibitor Interaction
- Key Research Papers
- Connections
- Featured Videos
EGb 761 — The Standardized Extract
Virtually every clinically relevant ginkgo trial since 1965 has used the same standardized extract: EGb 761, made in Germany. EGb 761 is a 50:1 leaf extract specified to contain:
- 24% flavone glycosides — primarily quercetin, kaempferol, and isorhamnetin conjugated to sugars (rutin, isoquercitrin, and related glycosides). These provide antioxidant and endothelial nitric oxide synthase (NOS) modulating effects.
- 6% terpene lactones — divided approximately 3% ginkgolides (A, B, C, and J), 2.6% bilobalide, and trace ginkgolide M. Ginkgolide B is the primary platelet-activating factor (PAF) receptor antagonist; bilobalide is the GABAergic neuroprotectant.
- Less than 5 parts per million ginkgolic acid — the allergenic and potentially neurotoxic resorcinolic-acid contaminant from the ginkgo seed coat. EGb 761's industrial-scale purification reduces ginkgolic acid to safe levels; cheap generic extracts often fail this specification.
The clinical relevance of this specification cannot be overstated. A pharmacist's 2008 product survey of commercial US ginkgo products found that fewer than half met the EGb 761 standardization specification, several contained no detectable terpene lactones at all, and a substantial minority were contaminated with ginkgolic acid above the EU-permitted 5 parts per million limit. Trials of standardized EGb 761 cannot be extrapolated to generic ginkgo products. Most of the trials described on this page used this standardized extract.
The standardization story is also why ginkgo has retained scientific credibility in European regulatory medicine while it has slowly drifted toward dietary-supplement skepticism in the US: in Germany and France, ginkgo prescriptions are filled with one specific standardized extract (EGb 761), while in the US the same patient asking for "ginkgo" gets one of dozens of products with widely varying potency.
Le Bars 1997 — The Trial That Started It
The publication that catapulted ginkgo from European obscurity to American mainstream prescription was Le Bars, Katz, Berman, Itil, Freedman & Schatzberg (1997) "A Placebo-Controlled, Double-Blind, Randomized Trial of an Extract of Ginkgo Biloba for Dementia," published in JAMA. This trial enrolled 309 patients with mild-to-severe dementia of the Alzheimer's or multi-infarct type at several centers (a multicenter trial), randomized them to either EGb 761 120 mg/day or placebo for 52 weeks, and measured cognitive change via the ADAS-Cog (Alzheimer's Disease Assessment Scale — Cognitive subscale) and the GERRI (Geriatric Evaluation by Relative's Rating Instrument).
Results:
- ADAS-Cog: in the intent-to-treat analysis the ginkgo group's score was 1.4 points better than the placebo group's (p=0.04), roughly comparable to the magnitude of improvement seen with the first-generation cholinesterase inhibitor tacrine.
- GERRI (caregiver-rated daily function): the ginkgo group improved measurably; the placebo group declined. Difference was significant (p=0.004).
- Clinical Global Impression of Change: no difference between groups.
- Adverse events: no excess gastrointestinal, hematologic, or hepatic adverse events in the ginkgo group versus placebo. No bleeding excess at 120 mg/day.
The trial was widely covered in the US lay press and triggered a roughly tenfold increase in ginkgo sales over the following two years. It also triggered immediate methodologic criticism: only 202 of the 309 patients in the intent-to-treat analysis provided evaluable data at 52 weeks, with substantially different reasons for dropout in the two arms; the primary endpoint analysis used last-observation-carried-forward, which can be biased when dropouts are unequal; the effect size, while statistically significant, was small enough to be of debatable clinical importance.
Subsequent re-analysis and replication attempts have produced mixed results — Mazza 2006 found no relevant difference in efficacy between the ginkgo extract and donepezil, and McCarney 2008 (a pragmatic UK community trial) found no benefit. The Le Bars trial remains the historical reference, but the field has moved toward higher dosing and toward the milder mild-cognitive-impairment population.
Solomon 2002 — The Healthy-Adult Negative
Five years after Le Bars set off the ginkgo gold rush in the US, Solomon, Adams, Silver, Zimmer & DeVeaux (2002) "Ginkgo for Memory Enhancement: A Randomized Controlled Trial," also in JAMA, addressed the much-larger question of whether ginkgo improves memory in cognitively normal older adults.
Solomon randomized 230 cognitively normal community-dwelling older adults (age 60+) to EGb 761 120 mg/day or placebo for 6 weeks. The primary outcome was a standardized battery of 14 neuropsychological tests covering memory, attention, executive function, and verbal fluency.
Results: no difference between ginkgo and placebo on any of the 14 cognitive measures. No difference on the self-rated memory questionnaire. No difference on the caregiver-rated function questionnaire. Solomon's conclusion: "When taken following the manufacturer's instructions, ginkgo provides no measurable benefit in memory or related cognitive function to adults with healthy cognitive function."
This was a methodologically clean trial (6-week duration may have been too short, but the cognitive assessment battery was state-of-the-art) and it has been broadly cited as the definitive negative trial of ginkgo for cognitive enhancement in healthy adults. The result is also consistent with everything we now understand about ginkgo's mechanism: a perfusion-enhancing platelet-activating factor antagonist will not improve a brain that already has adequate perfusion. The Solomon trial does not contradict Le Bars (different population, different baseline pathology) but it sharply narrows the group in which ginkgo has shown a cognitive effect.
The GEM Trial 2008 — Dementia Prevention Failure
The Ginkgo Evaluation of Memory (GEM) trial was the largest, longest, and most methodologically rigorous ginkgo trial ever conducted. Funded by the National Center for Complementary and Alternative Medicine (NCCAM) at U.S. National Institutes of Health (NIH), principal investigator Steven DeKosky at the University of Pittsburgh, GEM enrolled 3,069 community-dwelling adults aged 75 years or older with normal cognition or mild cognitive impairment (MCI), randomized them to EGb 761 240 mg/day (2 × 120 mg) or matching placebo, and followed them for a median of 6.1 years — long enough to capture the conversion to dementia in those who would develop it.
DeKosky et al. 2008, "Ginkgo biloba for Prevention of Dementia: A Randomized Controlled Trial," JAMA:
- Primary outcome — incidence of dementia: 277 dementia cases in the ginkgo arm versus 246 in the placebo arm. Hazard ratio 1.12 (95% confidence interval (CI) 0.94 to 1.33). No reduction in dementia incidence. If anything, a non-significant trend toward more dementia in the ginkgo arm.
- Alzheimer's-specific dementia: 246 cases ginkgo vs 216 placebo. No difference.
- Vascular dementia: no difference.
- Cognitive trajectories (Snitz et al. 2009 follow-up analysis): no slower cognitive decline in the ginkgo arm versus placebo on any of 9 cognitive instruments.
- Safety: no excess of bleeding, hepatic enzyme elevation, or major adverse cardiovascular events. Mortality the same in both arms.
The GEM result is the gold-standard refutation of the hypothesis that ginkgo prevents dementia in older adults. It does not refute Le Bars 1997 (different population — established dementia versus prevention), but it does demolish the marketing claim that healthy older adults can take ginkgo to "stave off Alzheimer's." After GEM, the evidence reads: ginkgo may have some benefit for already-symptomatic mild dementia, but it has no role in primary prevention. The U.S. National Center for Complementary and Integrative Health (NCCIH) (which absorbed NCCAM) now states this explicitly in its consumer fact sheet on ginkgo.
Mild Cognitive Impairment (MCI) — The Sweet Spot
Between the negative healthy-adult evidence (Solomon, Snitz) and the negative dementia-prevention evidence (GEM) lies the population where ginkgo has the most consistent positive evidence: mild cognitive impairment (MCI) — the syndrome of measurable cognitive deficit that is greater than expected for age but does not yet meet criteria for dementia. MCI patients have subjective memory complaints, perform abnormally on objective testing (typically 1.5 standard deviations below age-matched norms on memory or executive measures), but maintain activities of daily living independently.
Trials and a meta-analysis in mild cognitive impairment report measurable benefit:
- Gavrilova 2014 (Russian MCI population with neuropsychiatric symptoms, n=160, EGb 761 240 mg/day, 24 weeks): significant improvement versus placebo in the Neuropsychiatric Inventory (NPI), the State-Trait Anxiety Inventory, the informants' global impression of change, and both Trail-Making Tests
- Grass-Kapanke 2011 (very mild cognitive impairment, 300 adults aged 45 to 65, 12 weeks): EGb 761 240 mg once daily produced a significant improvement beyond practice effects on an attention test and trends in its favour on memory tests; the effects were larger and more consistent in people with lower memory function at the start
- Yang 2016 meta-analysis (21 trials, 2,608 patients, trial quality moderate to poor): ginkgo added to conventional medicine raised Mini-Mental State Examination (MMSE) scores more than conventional medicine alone at 24 weeks — by 1.90 points in MCI and 2.39 points in Alzheimer's disease; compared with placebo, individual trials gave similar but inconsistent findings
The MCI evidence is the basis for the European Medicines Agency's 2014 monograph that recommends EGb 761 240 mg/day as a treatment option for "improvement of (age-related) cognitive impairment and of quality of life in mild dementia." It is also the basis for the German Leitlinie (clinical practice guideline) on dementia, which lists EGb 761 240 mg/day as a treatment option for mild to moderate Alzheimer's and vascular dementia, alongside donepezil, rivastigmine, galantamine, and memantine.
The American Academy of Neurology's practice guideline takes a more skeptical view, citing GEM and the heterogeneity of the MCI trials — but does not actively recommend against ginkgo, instead listing it as "evidence inconclusive." This trans-Atlantic divergence reflects a different weighting of the same studies rather than fundamentally different data.
Comparison to Donepezil
Donepezil, the most commonly prescribed acetylcholinesterase inhibitor for Alzheimer's disease, is the natural comparator for ginkgo in mild-to-moderate dementia. Both produce small but measurable improvements in cognition and caregiver-rated function; both have modest effect sizes on the order of 2 to 4 ADAS-Cog points; both work for some patients and not others; and neither alters the underlying neurodegenerative trajectory.
The pivotal head-to-head trial was Mazza, Capuano, Bria, & Mazza (2006) "Ginkgo biloba and donepezil: a comparison in the treatment of Alzheimer's dementia in a randomized placebo-controlled double-blind study," in the European Journal of Neurology. This trial randomized 76 patients with mild-to-moderate Alzheimer's to one of three arms: donepezil 5 mg/day, EGb 761 160 mg/day, or placebo, for 24 weeks.
- Cognition and dementia severity (the Syndrom Kurz test, SKT, a cognitive test battery, and the Mini-Mental State Examination, MMSE): both donepezil and EGb 761 produced improvement versus placebo; the difference between donepezil and EGb 761 was not statistically significant. EGb 761 showed a slightly larger numerical improvement, but the trial was not powered to demonstrate non-inferiority formally.
- Adverse events: donepezil produced the expected cholinergic adverse-event profile (nausea, diarrhea, anorexia, vivid dreams); EGb 761 had a placebo-like adverse-event profile.
- Tolerability: EGb 761 was better tolerated, with fewer dropouts due to adverse events.
A 2015 systematic review and meta-analysis (Tan 2015; nine trials of 22-26 weeks, 2,561 patients) found EGb 761, mainly at 240 mg/day, better than placebo for cognition, daily activities and global change in cognitive impairment and dementia, with no important safety concerns. A 2009 exploratory trial of 96 patients with Alzheimer's and neuropsychiatric features (Yancheva 2009) found results similar for EGb 761 240 mg/day, donepezil, and the two combined over 22 weeks, with a lower adverse-event rate on EGb 761 than on donepezil alone.
In mild-to-moderate Alzheimer's or vascular dementia, the German guideline described below lists EGb 761 240 mg/day as a treatment option alongside the cholinesterase inhibitors, and the trials above tested it both instead of and together with donepezil, whose gastrointestinal adverse effects some patients cannot tolerate. The trials cited here did not test ginkgo as a replacement for memantine in moderate-to-severe disease, or for management of vascular risk factors (hypertension, diabetes, atrial fibrillation, statin therapy), which remain the foundation of vascular cognitive impairment prevention.
European Regulatory Position
Ginkgo's regulatory status in Europe reflects a half-century of mainstream clinical use. The European Medicines Agency (EMA) Committee on Herbal Medicinal Products (HMPC) maintains a formal monograph on standardized ginkgo leaf dry extract. The German Commission E (the regulatory body that established the modern European framework for herbal medicine pharmacovigilance) approved ginkgo for symptomatic treatment of deficits in mental performance, intermittent claudication (peripheral artery disease, PAD), and vertigo/tinnitus of vascular origin. The French Pharmacopoeia lists EGb 761 as an officially recognized medicine.
In Germany specifically, EGb 761 is sold under several brand names as a prescription pharmaceutical, covered by the statutory health insurance system for dementia indications, and prescribed by neurologists alongside or instead of donepezil and memantine. The German Leitlinie on dementia management lists EGb 761 240 mg/day with an evidence grade of "0" (positive evidence available, sufficient for recommendation), the same evidence grade as the cholinesterase inhibitors.
In the US, ginkgo remains a dietary supplement under the Dietary Supplement Health and Education Act of 1994 (DSHEA). No manufacturer has pursued U.S. Food and Drug Administration (FDA) approval as a drug for dementia, partly because the patent on EGb 761's manufacturing process expired decades ago and the economics of a generic-eligible compound do not support new drug-approval trials. The American Academy of Neurology's clinical practice guideline notes ginkgo's European use but does not recommend it for routine dementia management, citing the GEM trial and inconsistent results across MCI trials.
This regulatory divergence is the single biggest reason that patients in the US and Europe receive different advice from their physicians on ginkgo for cognitive concerns. The underlying clinical evidence is the same; the regulatory weighting of that evidence differs.
Mechanism — Why It Works (When It Works)
The mechanistic basis for ginkgo's cognitive effect (in populations where it works) is best understood as multifactorial improvement of cerebral microcirculation and neuronal stress resistance:
- Cerebral microcirculation enhancement. Ginkgolide B antagonizes the platelet-activating factor (PAF) receptor, reducing PAF-mediated microvascular thrombosis in cerebral capillaries. Flavonoid glycosides activate endothelial nitric oxide synthase (eNOS), producing flow-mediated vasodilation. Bilobalide enhances erythrocyte deformability through membrane fluidity effects. The net result, documented in transcranial Doppler studies, is a 10-30% increase in middle cerebral artery flow velocity in elderly subjects with baseline reduced perfusion.
- Mitochondrial protection. Bilobalide preserves the mitochondrial membrane potential under ischemic stress, reduces cytochrome-c release from compromised mitochondria, and inhibits the mitochondrial permeability transition pore opening that initiates apoptosis. In animal models of cerebral ischemia and reperfusion, pretreatment with EGb 761 significantly reduces infarct volume.
- Antioxidant protection. The flavonoid component scavenges reactive oxygen species (singlet oxygen, hydroxyl radicals, peroxynitrite) and chelates iron and copper, reducing Fenton-reaction free-radical generation. This is particularly relevant in the aged brain, where oxidative stress accumulates with normal aging and accelerates in the context of vascular disease.
- Neurotransmitter modulation. Ginkgo extract modestly inhibits monoamine oxidase activity (MAO-A and MAO-B), increases brain norepinephrine and dopamine turnover, and modulates gamma-aminobutyric acid-A receptor function. These effects are small relative to dedicated psychotropic drugs but may contribute to the cognitive and mood effects observed in trials.
- Beta-amyloid interaction. In vitro and animal-model evidence suggests EGb 761 can reduce beta-amyloid aggregation and neurotoxicity, though clinical correlates are unclear — the GEM trial was a direct test of whether this preclinical signal translates to prevention of human Alzheimer's and the answer was negative.
The unifying theme is that all five mechanisms target the under-perfused, oxidatively stressed, aged brain. None of them produces a measurable effect on the healthy young or middle-aged brain — which is precisely the pattern observed in the Solomon 2002 healthy-adult trial.
For related cognitive-support herbs that work through different mechanisms, see our Bacopa Monnieri page (cholinergic, brain-derived neurotrophic factor, BDNF), Ashwagandha (hypothalamic-pituitary-adrenal-axis modulation), and Rhodiola Rosea (adaptogenic stress resilience).
Dosing Protocol — What the Trials Used
- Mild cognitive impairment / mild dementia: EGb 761 240 mg/day, typically split as 120 mg twice daily with meals; the trials assessed response after 22-24 weeks. Most positive trials used this regimen.
- Le Bars 1997 trial dose: EGb 761 120 mg/day (40 mg three times daily). This is the lower end of the dose range studied; most later trials used 240 mg/day.
- Intermittent claudication: EGb 761 120-240 mg/day for 24 weeks (see the Circulation & peripheral artery disease page).
- Tinnitus: EGb 761 240 mg/day for 12 weeks (see the Tinnitus page).
- Healthy adults: the Solomon 2002 trial found no benefit on any of 14 cognitive measures in cognitively normal adults aged 60 and over.
- Form: standardized EGb 761 extract is the only form with consistent clinical evidence. Crude leaf powder, leaf tea, and unspecified "ginkgo extract" cannot be assumed to produce the same effect.
- Time to effect: cognitive endpoints typically take 8-12 weeks to demonstrate measurable change; trials lasting less than 12 weeks are systematically biased toward negative results.
Cautions — Bleeding, Seizures, and Selective Serotonin Reuptake Inhibitor Interaction
- Bleeding risk — the most clinically important caution. Ginkgolide B blocks the platelet-activating factor receptor, the proposed basis for a bleeding effect. Case reports document spontaneous subdural hematoma, intracerebral hemorrhage, subarachnoid hemorrhage, retrobulbar hemorrhage, and postoperative bleeding in ginkgo users. The concern centres on surgery, dental extraction, epidural injection and other invasive procedures (see Surgery and anesthesia below), and on combination with drugs that themselves reduce clotting: warfarin, aspirin, clopidogrel, prasugrel, ticagrelor, direct oral anticoagulants (DOACs: apixaban, rivaroxaban, dabigatran, edoxaban), heparin, nonsteroidal anti-inflammatory drugs (NSAIDs) at chronic high dose, or high-dose fish oil. The Kellermann & Kloft 2011 meta-analysis of 18 randomized trials (1,985 adults) found no significant effect of standardized ginkgo extract on platelet aggregation, fibrinogen or clotting times, and concluded that the hemostasis results did not indicate a higher bleeding risk.
- Selective serotonin reuptake inhibitor (SSRI) interaction. Selective serotonin reuptake inhibitors (fluoxetine, sertraline, paroxetine, citalopram, escitalopram, fluvoxamine) reduce platelet serotonin uptake and independently impair platelet function. Combining selective serotonin reuptake inhibitor with ginkgo compounds the bleeding risk. Several case reports describe spontaneous bleeding in patients on the combination who tolerated each drug individually.
- Seizure threshold lowering — contraindicated in epilepsy. Ginkgo seeds contain 4'-O-methylpyridoxine ("ginkgotoxin"), a vitamin B6 antagonist that lowers seizure threshold. Standardized EGb 761 extract is rigorously purified to remove ginkgotoxin, but case reports describe breakthrough seizures in well-controlled epileptics who started ginkgo supplements — either due to contamination of non-standardized products or possibly due to as-yet-unidentified seizure-promoting flavonoid effects. Ginkgo is contraindicated in epilepsy, history of seizures, and head injury with seizure risk.
- Surgery and anesthesia. The American Society of Anesthesiologists recommends discontinuing all herbal medicines including ginkgo at least 2 weeks before elective surgery. Failure to disclose ginkgo use is a recognized cause of unexpected intraoperative bleeding.
- Pregnancy and breastfeeding. There is not enough safety data for pregnancy or breastfeeding, so its safety there is unknown.
- Diabetes. Ginkgo modestly affects insulin secretion and glucose disposition. For people on insulin or sulfonylureas, blood glucose can shift when ginkgo is started; low blood sugar (hypoglycemia) is the pattern of concern.
- Cytochrome P450 interactions. Ginkgo modestly induces CYP2C19 (reducing the area-under-the-curve of substrates including omeprazole, clopidogrel's active metabolite, and phenytoin) and modestly affects cytochrome P450 3A4 (CYP3A4). Clinical significance is generally small; it matters most for narrow-therapeutic-index drugs, where small changes in blood level matter.
- Allergic reaction. Contact with the seed coat (ginkgolic acid) can produce severe dermatitis similar to poison ivy. Standardized EGb 761 has ginkgolic acid below 5 parts per million and rarely produces allergic reactions; whole-seed products and unstandardized teas can.
Key Research Papers
- Le Bars PL, Katz MM, Berman N, Itil TM, Freedman AM, Schatzberg AF (1997). A placebo-controlled, double-blind, randomized trial of an extract of Ginkgo biloba for dementia. JAMA 278(16):1327-1332. — PubMed PMID: 9343463
- Solomon PR, Adams F, Silver A, Zimmer J, DeVeaux R (2002). Ginkgo for memory enhancement: a randomized controlled trial. JAMA 288(7):835-840. — PubMed PMID: 12186600
- DeKosky ST, Williamson JD, Fitzpatrick AL et al. (2008). Ginkgo biloba for prevention of dementia: a randomized controlled trial (GEM). JAMA 300(19):2253-2262. — PubMed PMID: 19017911
- Snitz BE, O'Meara ES, Carlson MC et al. (2009). Ginkgo biloba for preventing cognitive decline in older adults. JAMA 302(24):2663-2670. — PubMed PMID: 20040554
- Mazza M, Capuano A, Bria P, Mazza S (2006). Ginkgo biloba and donepezil: a comparison in the treatment of Alzheimer's dementia in a randomized placebo-controlled double-blind study. European Journal of Neurology 13(9):981-985. — PubMed PMID: 16930364
- McCarney R, Fisher P, Iliffe S et al. (2008). Ginkgo biloba for mild to moderate dementia in a community setting. International Journal of Geriatric Psychiatry 23(12):1222-1230. — PubMed PMID: 18537221
- Birks J, Grimley Evans J (2009). Ginkgo biloba for cognitive impairment and dementia. Cochrane Database of Systematic Reviews (1):CD003120. — PubMed PMID: 19160216
- Ihl R, Bachinskaya N, Korczyn AD et al. (2011). Efficacy and safety of a once-daily formulation of Ginkgo biloba extract EGb 761 in dementia with neuropsychiatric features. International Journal of Geriatric Psychiatry 26(11):1186-1194. — PubMed PMID: 21140383
- Kanowski S, Hoerr R (2003). Ginkgo biloba extract EGb 761 in dementia: intent-to-treat analyses of a 24-week, multi-center, double-blind, placebo-controlled, randomized trial. Pharmacopsychiatry 36(6):297-303. — PubMed PMID: 14663654
- Yang G, Wang Y, Sun J, Zhang K, Liu J (2016). Ginkgo biloba for mild cognitive impairment and Alzheimer's disease: a systematic review and meta-analysis of randomized controlled trials. Current Topics in Medicinal Chemistry 16(5):520-528. — PubMed PMID: 26268332
- Tan MS, Yu JT, Tan CC et al. (2015). Efficacy and adverse effects of ginkgo biloba for cognitive impairment and dementia: a systematic review and meta-analysis. Journal of Alzheimer's Disease 43(2):589-603. — PubMed PMID: 25114079
- Yancheva S, Ihl R, Nikolova G, Panayotov P, Schlaefke S, Hoerr R (2009). Ginkgo biloba extract EGb 761(R), donepezil or both combined in the treatment of Alzheimer's disease with neuropsychiatric features: a randomised, double-blind, exploratory trial. Aging & Mental Health 13(2):183-190. — PubMed PMID: 19347685
- Gauthier S, Schlaefke S (2014). Efficacy and tolerability of Ginkgo biloba extract EGb 761 in dementia: a systematic review and meta-analysis of randomized placebo-controlled trials. Clinical Interventions in Aging 9:2065-2077. — PubMed PMID: 25506211
- Gavrilova SI, Preuss UW, Wong JW, Hoerr R, Kaschel R, Bachinskaya N (2014). Efficacy and safety of Ginkgo biloba extract EGb 761 in mild cognitive impairment with neuropsychiatric symptoms: a randomized, placebo-controlled, double-blind, multi-center trial. International Journal of Geriatric Psychiatry 29(10):1087-1095. — PubMed PMID: 24633934
- Grass-Kapanke B, Busmane A, Lasmanis A, Hoerr R, Kaschel R (2011). Effects of Ginkgo biloba special extract EGb 761 in very mild cognitive impairment (vMCI). Neuroscience and Medicine 2(1):48-56. — doi:10.4236/nm.2011.21007
- Kellermann AJ, Kloft C (2011). Is there a risk of bleeding associated with standardized Ginkgo biloba extract therapy? A systematic review and meta-analysis. Pharmacotherapy 31(5):490-502. — PubMed PMID: 21923430
PubMed Topic Searches
Connections
- All Herbs
- Ginkgo Biloba Overview
- Ginkgo Biloba Benefits Hub
- Ginkgo for Circulation & Peripheral Artery Disease
- Ginkgo for Tinnitus
- Ginkgo for Vision
- Bacopa Monnieri
- Ashwagandha
- Rhodiola Rosea
- Turmeric
- Alzheimer's Disease
- Dementia
- Anxiety
- Cognitive Enhancement & Attention-Deficit/Hyperactivity Disorder
- Vitamin E
- Magnesium
- History