Peripheral Artery Disease
Interactive Visualization Nitric Oxide — make an artery relax Watch the endothelium turn L-arginine into nitric oxide and widen the artery — then let oxidative stress uncouple eNOS and stiffen it, or pour in beet nitrate to rescue the flow. Launch →
Table of Contents
- Overview
- Epidemiology
- Pathophysiology
- Etiology and Risk Factors
- Clinical Presentation
- Diagnosis
- Treatment
- Complications
- Prognosis
- Prevention
- Recent Research and Advances
- Key Research Papers
- Connections
- Featured Videos
1. Overview
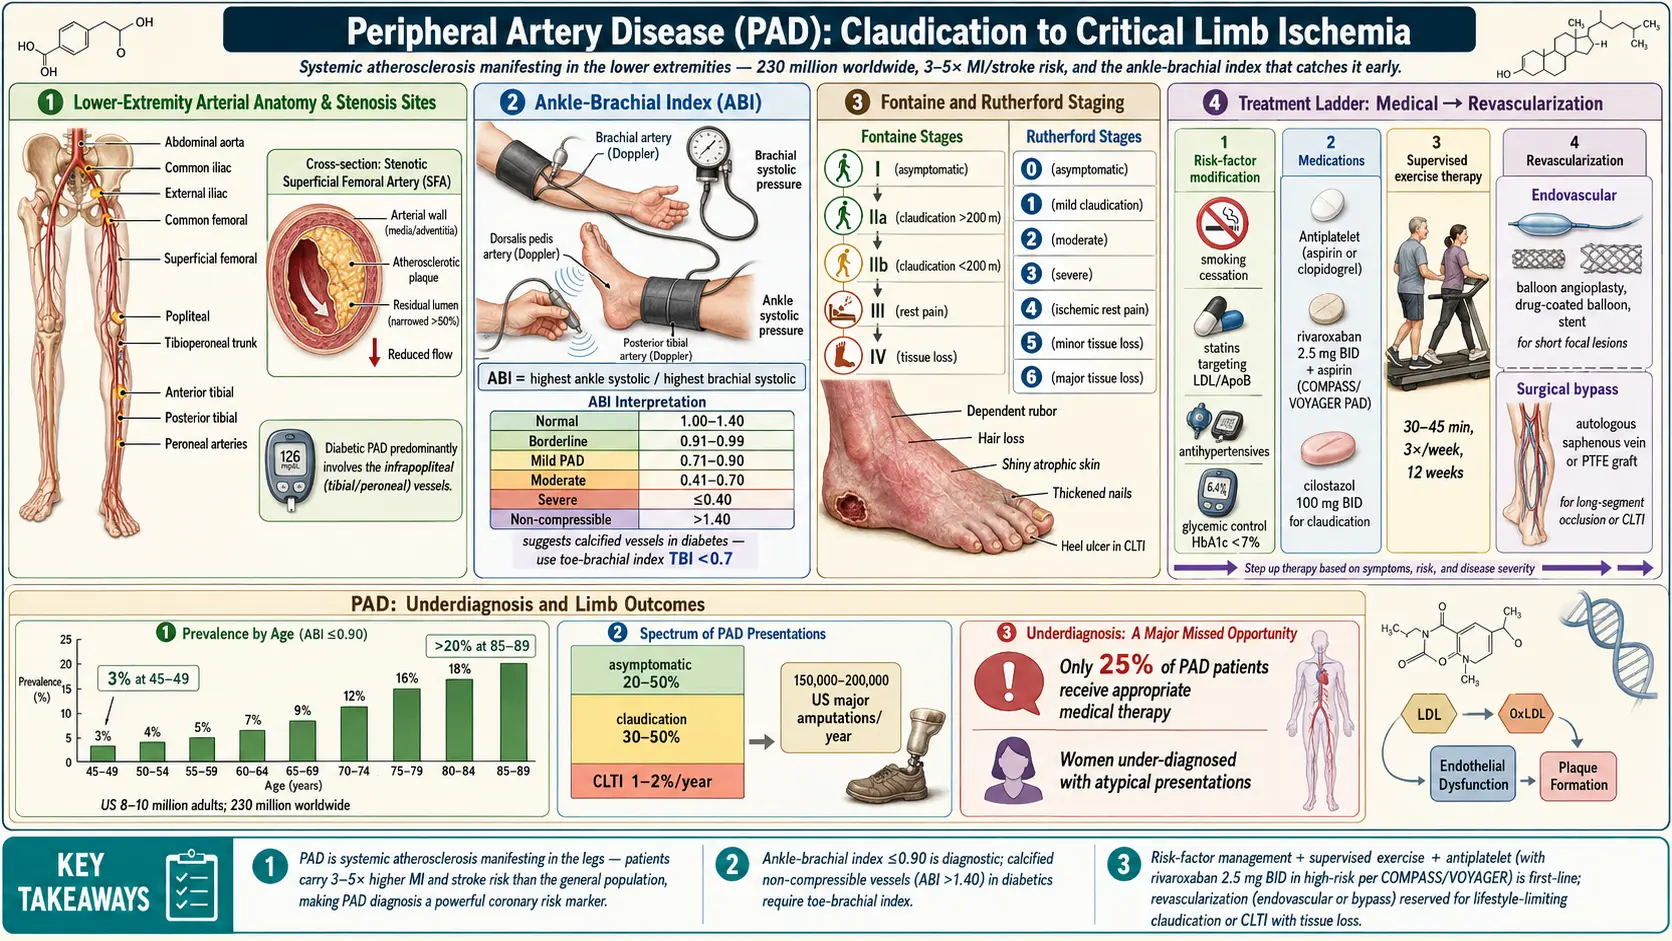
Peripheral artery disease (PAD) is a manifestation of systemic atherosclerosis characterized by stenosis or occlusion of the arteries supplying the extremities — predominantly the lower limbs — resulting in impaired blood flow and tissue ischemia. Peripheral artery disease is both a significant cause of limb morbidity and a powerful marker of generalized cardiovascular disease, with affected patients carrying a 3- to 5-fold increased risk of myocardial infarction and stroke compared to the general population.
The term "peripheral artery disease" most commonly refers to lower extremity arterial disease (LEAD), though the condition encompasses atherosclerotic involvement of the renal, mesenteric, and upper extremity arteries as well. The spectrum of lower-extremity peripheral artery disease ranges from asymptomatic disease (diagnosed by ankle-brachial index) to intermittent claudication, to the most severe form — chronic limb-threatening ischemia (CLTI), formerly termed critical limb ischemia — which encompasses rest pain, non-healing ulcers, and gangrene.
2. Epidemiology
Peripheral artery disease affected about 237 million people worldwide aged 25 and older in 2015, a global prevalence of 5.6% (Song 2019). Prevalence increases sharply with age: from 3% in those aged 45–49 to over 20% in adults aged 85–89. In the United States, approximately 8–10 million adults are affected.
Peripheral artery disease exhibits marked geographic variation. About 73% of people with peripheral artery disease live in low- and middle-income countries, although prevalence is higher in high-income countries (7.4% vs 5.1%) (Song 2019), while sub-Saharan Africa and Oceania have the fastest-growing prevalence. Among racial/ethnic groups in the US, non-Hispanic Black individuals have a 2-fold higher prevalence than non-Hispanic White individuals, even after adjusting for traditional cardiovascular risk factors — likely reflecting disparities in hypertension prevalence, access to care, and socioeconomic factors.
Symptomatic claudication affects approximately 2% of adults over 50; however, the majority of peripheral artery disease patients (20–50%) remain asymptomatic. CLTI affects approximately 1–2% of peripheral artery disease patients annually, with an estimated 150,000–200,000 major amputations performed per year in the US.
Peripheral artery disease is significantly underdiagnosed: only 25% of patients with peripheral artery disease receive appropriate medical therapy. Women with peripheral artery disease often present atypically (less classic claudication, more functional limitations) and are diagnosed and treated less aggressively than men.
3. Pathophysiology
The fundamental pathologic process in peripheral artery disease is atherosclerosis — a chronic inflammatory disorder of medium and large arteries driven by lipid deposition, endothelial dysfunction, and immune activation.
Atherosclerotic Plaque Formation
Endothelial dysfunction — triggered by oxidative stress, turbulent shear forces, dyslipidemia, hypertension, and smoking-derived toxins — leads to upregulation of adhesion molecules (VCAM-1, ICAM-1, P-selectin) and chemokines (MCP-1). Circulating monocytes adhere, transmigrate into the intima, and differentiate into macrophages. Macrophages engulf oxidized low-density lipoprotein (LDL) via scavenger receptors (SR-A, CD36), becoming foam cells and forming the lipid-rich necrotic core of the atherosclerotic plaque.
Smooth muscle cells migrate from the media to the intima under PDGF and TGF-β stimulation, proliferating and secreting extracellular matrix proteins (collagen, elastin) that form the fibrous cap. Progressive plaque growth leads to luminal narrowing, and plaque rupture or erosion triggers acute thrombosis, causing acute limb ischemia.
Hemodynamic Consequences
Hemodynamically significant stenosis (>50% luminal diameter reduction, or >75% cross-sectional area) impairs distal blood flow. During exercise, peripheral vasodilation cannot overcome the fixed resistance of the stenosis, creating a pressure gradient that reduces perfusion pressure distal to the lesion — manifesting as claudication. In CLTI, resting perfusion is insufficient to maintain tissue viability, leading to ischemic rest pain (typically at night when legs are elevated) and tissue loss.
Collateral Circulation and Angiogenesis
Chronic ischemia stimulates collateral vessel formation via VEGF, FGF, and angiopoietin signaling pathways. The adequacy of collateral development determines the clinical severity of symptoms for a given degree of stenosis. Diabetic patients have impaired angiogenic responses, partly explaining their disproportionate risk of CLTI and amputation.
Microvascular Disease
In diabetic peripheral artery disease, concurrent microvascular disease (arteriolar sclerosis, capillary basement membrane thickening) compounds macrovascular occlusion, worsening tissue ischemia and impairing wound healing. Diabetic neuropathy exacerbates foot ulceration by reducing protective pain sensation.
Inflammation and Coagulation
Systemic inflammation (elevated C-reactive protein, interleukin-6 (IL-6), tumor necrosis factor alpha (TNF-α), fibrinogen) promotes platelet activation, endothelial dysfunction, and plaque vulnerability. Hypercoagulable states (antiphospholipid syndrome, factor V Leiden) can accelerate thrombotic occlusion in peripheral artery disease.
4. Etiology and Risk Factors
Traditional Cardiovascular Risk Factors
- Cigarette smoking: Strongest modifiable risk factor for peripheral artery disease (odds ratio (OR) 2.3–4.0); dose-dependent relationship; smoking cessation reduces progression risk by 30–50%
- Diabetes mellitus: 2- to 4-fold increased peripheral artery disease risk; accelerates atherosclerosis and microvascular disease; hemoglobin A1c (HbA1c) >7% associated with worse outcomes; diabetic peripheral artery disease predominantly affects infrapopliteal (tibial/peroneal) vessels
- Hypertension: 2.5-fold increased risk; end-organ damage compounds lower extremity ischemia
- Dyslipidemia: Elevated low-density lipoprotein cholesterol (LDL-C) (particularly small dense low-density lipoprotein particles), low high-density lipoprotein cholesterol (HDL-C), elevated triglycerides, and elevated Lp(a) all increase peripheral artery disease risk
- Chronic kidney disease: Strong independent predictor; estimated glomerular filtration rate (eGFR) <60 mL/min/1.73m² associated with 2-fold peripheral artery disease risk
Non-Modifiable Risk Factors
- Age >65 years (strongest predictor)
- Male sex (though female prevalence approaches male in older cohorts)
- Family history of premature atherosclerosis
- African American race
Other Risk Factors
- Hyperhomocysteinemia
- Elevated C-reactive protein and inflammatory markers
- Elevated lipoprotein(a)
- Hypercoagulable states (antiphospholipid antibody syndrome, thrombophilias)
- Human immunodeficiency virus (HIV) infection (accelerated atherosclerosis from chronic inflammation and antiretroviral therapy)
Non-Atherosclerotic Causes
- Buerger disease (thromboangiitis obliterans): Inflammatory segmental arteritis in young heavy smokers
- Popliteal artery entrapment syndrome: Congenital anomalous muscle-artery relationship
- Cystic adventitial disease
- Radiation-induced arteriopathy
- Takayasu arteritis and giant cell arteritis (large vessel vasculitis)
- Fibromuscular dysplasia (more common in renal and carotid arteries)
5. Clinical Presentation
Asymptomatic Peripheral Artery Disease
Approximately 40–50% of peripheral artery disease patients are asymptomatic, identified only by abnormal ankle-brachial index (ABI). Despite absent symptoms, these individuals carry the same cardiovascular risk as symptomatic patients.
Intermittent Claudication
The classic presentation of symptomatic peripheral artery disease is intermittent claudication — reproducible cramping, aching, or tightness pain in the exercising muscle groups distal to the stenosis, consistently reproduced by a fixed exercise distance (claudication distance), and relieved within 2–5 minutes of rest. Claudication location identifies the approximate level of disease:
- Calf claudication: Femoropopliteal disease (most common)
- Thigh and buttock claudication: Aortoiliac disease; Leriche syndrome (bilateral claudication, absent femoral pulses, erectile dysfunction)
- Foot claudication: Tibial/peroneal disease
Fontaine and Rutherford Classification
The Fontaine classification stages peripheral artery disease severity:
- Stage I: Asymptomatic, ABI <0.9
- Stage IIa: Mild claudication (>200 m walking distance)
- Stage IIb: Moderate to severe claudication (≤200 m walking distance)
- Stage III: Ischemic rest pain
- Stage IV: Ulceration or gangrene
The Rutherford classification (Grades 0–III, Categories 0–6) is used in clinical research with greater granularity. The updated WIfI classification (Wound, Ischemia, foot Infection) is specifically designed for CLTI to predict amputation risk and revascularization benefit.
Chronic Limb-Threatening Ischemia (CLTI)
CLTI represents the most severe form of peripheral artery disease and is defined by:
- Ischemic rest pain: Persistent pain at rest (usually forefoot/toes) for >2 weeks, typically worse at night and partially relieved by leg dependency; ABI <0.4, ankle pressure <50 mmHg, or toe pressure <30 mmHg
- Ischemic ulceration: Non-healing wounds persisting >2 weeks despite optimal wound care; punched-out ulcers with pale bases, often on toes, heel, or pressure points
- Gangrene: Dry (mummified) or wet (infected) tissue necrosis; wet gangrene constitutes a surgical emergency
Acute Limb Ischemia (ALI)
The six Ps characterize ALI: Pain, Pallor, Pulselessness, Paresthesias, Paralysis (most ominous), and Poikilothermia (coolness). ALI is a vascular emergency requiring intervention within 6 hours to prevent irreversible ischemia. The Rutherford classification for ALI grades severity from I (viable) to III (irreversible/major tissue loss).
6. Diagnosis
Ankle-Brachial Index (ABI)
The ABI is the primary diagnostic test: ratio of systolic blood pressure at the ankle (posterior tibial or dorsalis pedis) to the higher brachial systolic pressure. Measured using a continuous wave Doppler probe and sphygmomanometer.
- Normal: 1.00–1.40
- Borderline: 0.91–0.99
- Peripheral artery disease: ≤0.90 (sensitivity 79%, specificity 96% for angiographically confirmed ≥50% stenosis)
- Severe ischemia: ≤0.40
- Non-compressible (falsely elevated, >1.40): Due to medial arterial calcification — common in diabetes and chronic kidney disease (CKD); requires toe-brachial index (TBI; normal ≥0.70)
Exercise ABI (post-treadmill 5 minutes at 3.2 km/h, 10% grade): Drop of ≥20% from resting ABI confirms claudication when resting ABI is borderline or normal despite suggestive symptoms.
Additional Vascular Studies
- Segmental limb pressures and pulse volume recordings (PVRs): Localize disease level; PVRs qualitatively assess flow waveform morphology
- Duplex ultrasound: Defines anatomy, stenosis severity (peak systolic velocity ratio >2.0 indicates ≥50% stenosis), plaque morphology; operator-dependent
- Computed tomography (CT) angiography (CTA): High-resolution 3D arterial mapping; excellent for pre-procedural planning; risk of contrast nephropathy and radiation; artifact from arterial calcification
- Magnetic resonance angiography (MRA): No ionizing radiation; gadolinium-enhanced MRA provides excellent anatomic detail; limited by metallic implants and nephrogenic systemic fibrosis risk in severe chronic kidney disease
- Digital subtraction angiography (DSA): Gold standard for anatomy definition; reserved for when non-invasive imaging is inconclusive or immediately preceding intervention
- Transcutaneous oxygen pressure (TcPO₂): Measures tissue oxygenation; TcPO₂ <30 mmHg predicts impaired wound healing; useful in patients with non-compressible arteries
- Toe pressures: Absolute toe pressure <50 mmHg (or <30 mmHg with diabetes) defines CLTI
Laboratory Evaluation
- Fasting lipid panel, hemoglobin A1c, fasting glucose
- CBC, CMP, coagulation studies
- Creatinine and estimated glomerular filtration rate (pre-contrast administration)
- Homocysteine, Lp(a) in young patients or atypical presentations
- Inflammatory markers (high-sensitivity C-reactive protein (hsCRP), erythrocyte sedimentation rate (ESR)) if vasculitis suspected
- Hypercoagulable workup when appropriate (antiphospholipid antibodies, protein C/S, antithrombin III)
Differential Diagnosis
- Neurogenic claudication (lumbar spinal stenosis): Pain with walking and standing; relieved by sitting/forward flexion; normal ABI
- Venous claudication: Bursting thigh pain with exercise; associated with post-thrombotic syndrome
- Musculoskeletal pain (osteoarthritis, hip disease): Not consistently reproducible with same exercise distance
- Compartment syndrome (chronic exertional): Young athletes; pain with exercise, rapid relief with rest
- Diabetic neuropathic ulcers: Plantar pressure points; warm foot; bounding pulses (unless concurrent peripheral artery disease)
- Venous ulcers: Medial malleolus location; associated lipodermatosclerosis, varicosities
7. Treatment
Medical Management (All Peripheral Artery Disease Patients)
Optimal medical therapy (OMT) reduces cardiovascular events and limb outcomes in all peripheral artery disease patients regardless of symptom severity.
- Antiplatelet therapy:
- Aspirin 75–100 mg/day: Reduces myocardial infarction (MI), stroke, and cardiovascular death; class I recommendation for symptomatic peripheral artery disease
- Clopidogrel 75 mg/day: Marginally superior to aspirin in PAD (CAPRIE trial: 23.8% relative risk reduction vs. aspirin); preferred in aspirin-intolerant patients or those with concurrent coronary artery disease
- Aspirin + rivaroxaban 2.5 mg twice daily (COMPASS regimen): Reduces major adverse limb events (MALE) by 46% and major adverse cardiovascular events (MACE) by 28% compared to aspirin alone (COMPASS trial, 2017); U.S. Food and Drug Administration-approved for peripheral artery disease; increases bleeding risk
- Ticagrelor: Not superior to clopidogrel in PAD (EUCLID trial, 2017)
- Statin therapy: High-intensity statin therapy (atorvastatin 40–80 mg, rosuvastatin 20–40 mg); low-density lipoprotein cholesterol target <55 mg/dL (ESC 2019) or <70 mg/dL (AHA/ACC); reduces MACE and MALE; PCSK9 inhibitors (evolocumab, alirocumab) for patients not at low-density lipoprotein cholesterol goal on maximally tolerated statin
- Blood pressure control: Target <130/80 mmHg; angiotensin-converting enzyme inhibitors (ACE inhibitors) or angiotensin receptor blockers (ARBs) preferred (HOPE trial: ramipril 10 mg reduced MACE by 22% in high-risk patients including peripheral artery disease); beta-blockers are not contraindicated in peripheral artery disease and may be used for compelling indications (post-MI, HF)
- Glycemic control: hemoglobin A1c <7–8% in most diabetic peripheral artery disease patients; sodium-glucose cotransporter-2 (SGLT2) inhibitors (empagliflozin, canagliflozin) reduce cardiovascular events and may have specific limb benefit (though canagliflozin associated with amputation signal in CANVAS trial)
- Smoking cessation: Most impactful single intervention; reduces claudication progression by 30–50% and major amputation risk; pharmacotherapy (varenicline, bupropion, nicotine replacement) and behavioral support
- Cilostazol (phosphodiesterase III inhibitor): 100 mg twice daily; improves maximum and pain-free walking distance by 40–60% in claudication (U.S. Food and Drug Administration-approved); contraindicated in heart failure of any severity; drug interactions with CYP3A4/CYP2C19 inhibitors
- Pentoxifylline: 400 mg three times daily; modest benefit; generally second-line to cilostazol
Supervised Exercise Therapy
Structured, supervised exercise programs (SET) — typically 30–60 minutes of treadmill walking 3 times/week for 12 weeks — improve maximum walking distance by 100–150% and are guideline-recommended as first-line therapy for claudication (Class I, Level A). In the CLEVER trial in aortoiliac peripheral artery disease, supervised exercise improved peak treadmill walking time more than stenting at 6 months, while disease-specific quality of life improved more with stenting (Murphy 2012); revascularization plus exercise may be complementary.
Revascularization
Revascularization is indicated for: (1) lifestyle-limiting claudication refractory to OMT + SET; (2) CLTI (urgent/emergent in ALI). The BEST-CLI trial (2022) compared surgical bypass vs. endovascular therapy in CLTI patients and found surgical bypass (specifically with single-segment great saphenous vein conduit) was superior in patients with adequate conduit.
- Endovascular therapy (EVT):
- Percutaneous transluminal angioplasty (PTA): Balloon dilation of stenotic/occlusive lesions
- Bare-metal stents (BMS) and drug-eluting stents (DES): Nitinol self-expanding stents for femoropopliteal disease; DES (paclitaxel, sirolimus-eluting) reduce restenosis vs. BMS
- Drug-coated balloons (DCB): Paclitaxel-coated; improve patency in femoropopliteal disease
- Atherectomy (directional, rotational, orbital, laser): Debulking prior to balloon/stent; role in calcified lesions
- Covered stent-grafts: For SFA occlusions; VIBRANT trial
- Surgical bypass:
- Aortobifemoral bypass: Gold standard for aortoiliac occlusive disease (Leriche syndrome); 5-year patency 85–90%
- Femoropopliteal bypass: Above-knee (prosthetic or vein, 5-year patency 70–75%) vs. below-knee (vein preferred, 5-year patency 65–70%)
- Tibial bypasses: For CLTI with infrapopliteal disease; autologous vein essential
- Hybrid procedures: Combination of surgical inflow reconstruction and endovascular outflow treatment in multilevel disease
- Amputation: Major amputation (below-knee or above-knee) is the procedure of last resort when revascularization is not technically feasible or patient is not a candidate; multidisciplinary limb salvage programs aim to reduce major amputation rates
8. Complications
- Major adverse cardiovascular events (MACE): Myocardial infarction is the leading cause of death in peripheral artery disease patients; 3- to 5-fold increased risk; annual cardiovascular death rate 5–7%
- Major adverse limb events (MALE): Acute limb ischemia, major amputation, urgent revascularization; annual risk 5–10% in claudicants; much higher in CLTI
- Major amputation: 25–40% of CLTI patients require major amputation within 1 year without revascularization; 1-year mortality after major amputation is 30–50%
- Acute limb ischemia (ALI): Sudden thrombotic or embolic arterial occlusion; surgical emergency; 30-day mortality 15–20%; 30-day amputation rate 10–30%
- Wound complications: Non-healing ulcers, osteomyelitis, gas gangrene (wet gangrene) requiring emergency amputation
- Restenosis: Following endovascular intervention; rates of 30–50% at 1 year for femoropopliteal disease with plain balloon angioplasty; reduced with DCB and DES
- Graft failure: Prosthetic graft infection is a devastating complication requiring explantation
- Contrast nephropathy: Following angiographic procedures, particularly in diabetic or chronic kidney disease patients
- Functional decline and depression: Claudication significantly limits physical activity, social participation, and quality of life
9. Prognosis
Peripheral artery disease is a marker of systemic atherosclerosis and portends significant cardiovascular morbidity and mortality. The "rule of thirds" for claudication (over 5 years): one-third improve, one-third remain stable, one-third worsen. However, 20–30% of claudicants progress to CLTI over 10 years, particularly those who continue to smoke or have diabetes.
- Cardiovascular mortality: Annual cardiovascular death rate 5–7% in symptomatic peripheral artery disease; 10-year mortality approximately 50%, predominantly from myocardial infarction and stroke
- CLTI outcomes: Without revascularization, 1-year mortality is 25%, 1-year amputation rate is 25%; together (death or amputation) affecting 50% of CLTI patients at 1 year
- Post-revascularization: Successful revascularization in CLTI improves limb salvage to 75–85% at 1 year; long-term survival remains poor due to cardiovascular comorbidities
- ABI as prognostic marker: Each 0.10 decrease in ABI below normal is associated with a 10% increase in cardiovascular event risk; ABI <0.40 is associated with the highest cardiovascular mortality
- Prognostic factors: Continued smoking, diabetes, renal insufficiency, low serum albumin (nutritional status), and absence of revascularization are associated with poorer outcomes
10. Prevention
Primary Prevention
- Smoking cessation is paramount — the single greatest modifiable risk factor
- Aggressive dyslipidemia management; statin therapy in all high-risk patients
- Optimal blood pressure control (<130/80 mmHg)
- Diabetes screening and glycemic optimization
- Regular physical activity (150+ minutes/week of moderate-intensity exercise)
- Healthy dietary patterns (Mediterranean or DASH diet)
- Weight management (body mass index (BMI) <30 kg/m²)
- Annual foot examination in diabetic patients for early ulcer detection
Secondary Prevention
- Antiplatelet therapy in all symptomatic peripheral artery disease patients
- Anticoagulation (aspirin + low-dose rivaroxaban) consideration per COMPASS criteria
- High-intensity statin therapy with low-density lipoprotein cholesterol target <55–70 mg/dL
- Angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker (ARB) therapy
- Supervised exercise rehabilitation
- Diabetic foot care programs: Protective footwear, podiatric surveillance, patient education
- Multidisciplinary wound care teams for early ulcer management
- Cardiac risk factor optimization and cardiology co-management
11. Recent Research and Advances
- COMPASS trial (2017): Aspirin 100 mg + rivaroxaban 2.5 mg twice daily vs. aspirin alone demonstrated 46% reduction in MALE and 28% reduction in MACE in peripheral artery disease patients; led to U.S. Food and Drug Administration (FDA) approval of this combination regimen and transformed peripheral artery disease medical management.
- BEST-CLI trial (2022): First randomized trial comparing bypass surgery vs. endovascular therapy for CLTI; demonstrated superiority of surgical bypass (using single-segment great saphenous vein) for the primary endpoint of major adverse limb events, death, or major amputation in cohort 1 (adequate single-segment GSV); opened important discussions about patient selection for revascularization strategy.
- VOYAGER-PAD trial (2020): Rivaroxaban 2.5 mg twice daily + aspirin vs. aspirin alone post-PAD revascularization; 15% relative risk reduction in MACE/MALE; established DOAC role in post-revascularization patients.
- Drug-coated balloons (DCB) advances: Multiple randomized trials (IN.PACT ADMIRAL, ILLUMENATE) demonstrate DCB superiority over plain balloon angioplasty for femoropopliteal disease; ongoing investigation of safety (paclitaxel mortality signal subsequently addressed by larger meta-analyses).
- Cell-based therapies and gene therapy: Angiogenic gene therapy (HIF-1α, VEGF, FGF) and autologous cell therapies (bone marrow-derived mononuclear cells, CD34+ cells) in phase II/III trials for no-option CLTI patients; TAMARIS trial (non-rAd-VEGF165 for CLTI) was negative; newer approaches with plasmid-based delivery (VM202/pVGI.1) show promise in early trials.
- Intravascular lithotripsy (IVL): Shockwave Medical device for heavily calcified peripheral artery disease lesions; disrupts vascular calcification without wire trauma; improving EVT outcomes in calcified vessels.
- Artificial intelligence and peripheral artery disease: AI algorithms for automated ABI interpretation, wound classification (WIfI scoring), and 3D vessel analysis from computed tomography angiography are improving diagnostic accuracy and procedural planning.
- Sodium-glucose cotransporter-2 inhibitor effects on peripheral artery disease: Post-hoc analyses of EMPA-REG, CANVAS, CREDENCE, and DECLARE trials evaluating specific limb outcomes; conflicting signals between agents warrant dedicated peripheral artery disease trials.
Key Research Papers
- Gornik HL, Aronow HD, Goodney PP, et al. (2024). 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the Management of Lower Extremity Peripheral Artery Disease: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation — PubMed PMID: 38743805
- Song P, Rudan D, Zhu Y, et al. (2019). Global, regional, and national prevalence and risk factors for peripheral artery disease in 2015: an updated systematic review and analysis. The Lancet. Global Health — PubMed PMID: 31303293
- Anonymous (1996). A randomised, blinded, trial of clopidogrel versus aspirin in patients at risk of ischaemic events (CAPRIE). CAPRIE Steering Committee. Lancet (London, England) — PubMed PMID: 8918275
- Anand SS, Bosch J, Eikelboom JW, et al. (2018). Rivaroxaban with or without aspirin in patients with stable peripheral or carotid artery disease: an international, randomised, double-blind, placebo-controlled trial. Lancet (London, England) — PubMed PMID: 29132880
- Hiatt WR, Fowkes FG, Heizer G, et al. (2017). Ticagrelor versus Clopidogrel in Symptomatic Peripheral Artery Disease. The New England Journal of Medicine — PubMed PMID: 27959717
- Bonaca MP, Bauersachs RM, Anand SS, et al. (2020). Rivaroxaban in Peripheral Artery Disease after Revascularization. The New England Journal of Medicine — PubMed PMID: 32222135
- Farber A, Menard MT, Conte MS, et al. (2022). Surgery or Endovascular Therapy for Chronic Limb-Threatening Ischemia. The New England Journal of Medicine — PubMed PMID: 36342173
- Murphy TP, Cutlip DE, Regensteiner JG, et al. (2012). Supervised exercise versus primary stenting for claudication resulting from aortoiliac peripheral artery disease: six-month outcomes from the claudication: exercise versus endoluminal revascularization (CLEVER) study. Circulation — PubMed PMID: 22090168
PubMed Topic Searches
The following PubMed topic searches return current peer-reviewed literature relevant to this condition. Each link opens a live PubMed query.
- PubMed: Peripheral artery disease epidemiology
- PubMed: Ankle brachial index
- PubMed: Intermittent claudication
- PubMed: Critical limb ischemia
- PubMed: Peripheral artery disease revascularization
- PubMed: Peripheral artery disease supervised exercise
- PubMed: Peripheral artery disease guidelines
- PubMed: Cilostazol claudication
- PubMed: Peripheral artery disease statin
- PubMed: Peripheral artery disease smoking
- PubMed: Peripheral artery disease diabetes
- PubMed: Peripheral artery disease mortality
Connections
- Cardiology
- Nitric Oxide & Vessel Dilation — interactive animation
- Stroke
- Hypertension
- Cardiovascular Disease
- Coronary Artery Disease
- Atherosclerosis
- Aortic Aneurysm
- Deep Vein Thrombosis
- Cold Hands and Feet
- Lipid Panel
- Inflammatory Markers
- Garlic
- Omega-3 Fatty Acids
- Diabetes
- Erectile Dysfunction
- Aspirin
- Heart Failure
- Ginkgo Biloba
- Lipoprotein a
- Varicose Veins