⚠ Evidence warning: Clinical trials or other evidence do not support the claims that ginkgo improves or stabilises normal-tension glaucoma, dry macular degeneration or early diabetic eye disease. This page keeps it as a report of what people, websites or other media say.
Ginkgo Biloba for Vision and Macular Degeneration
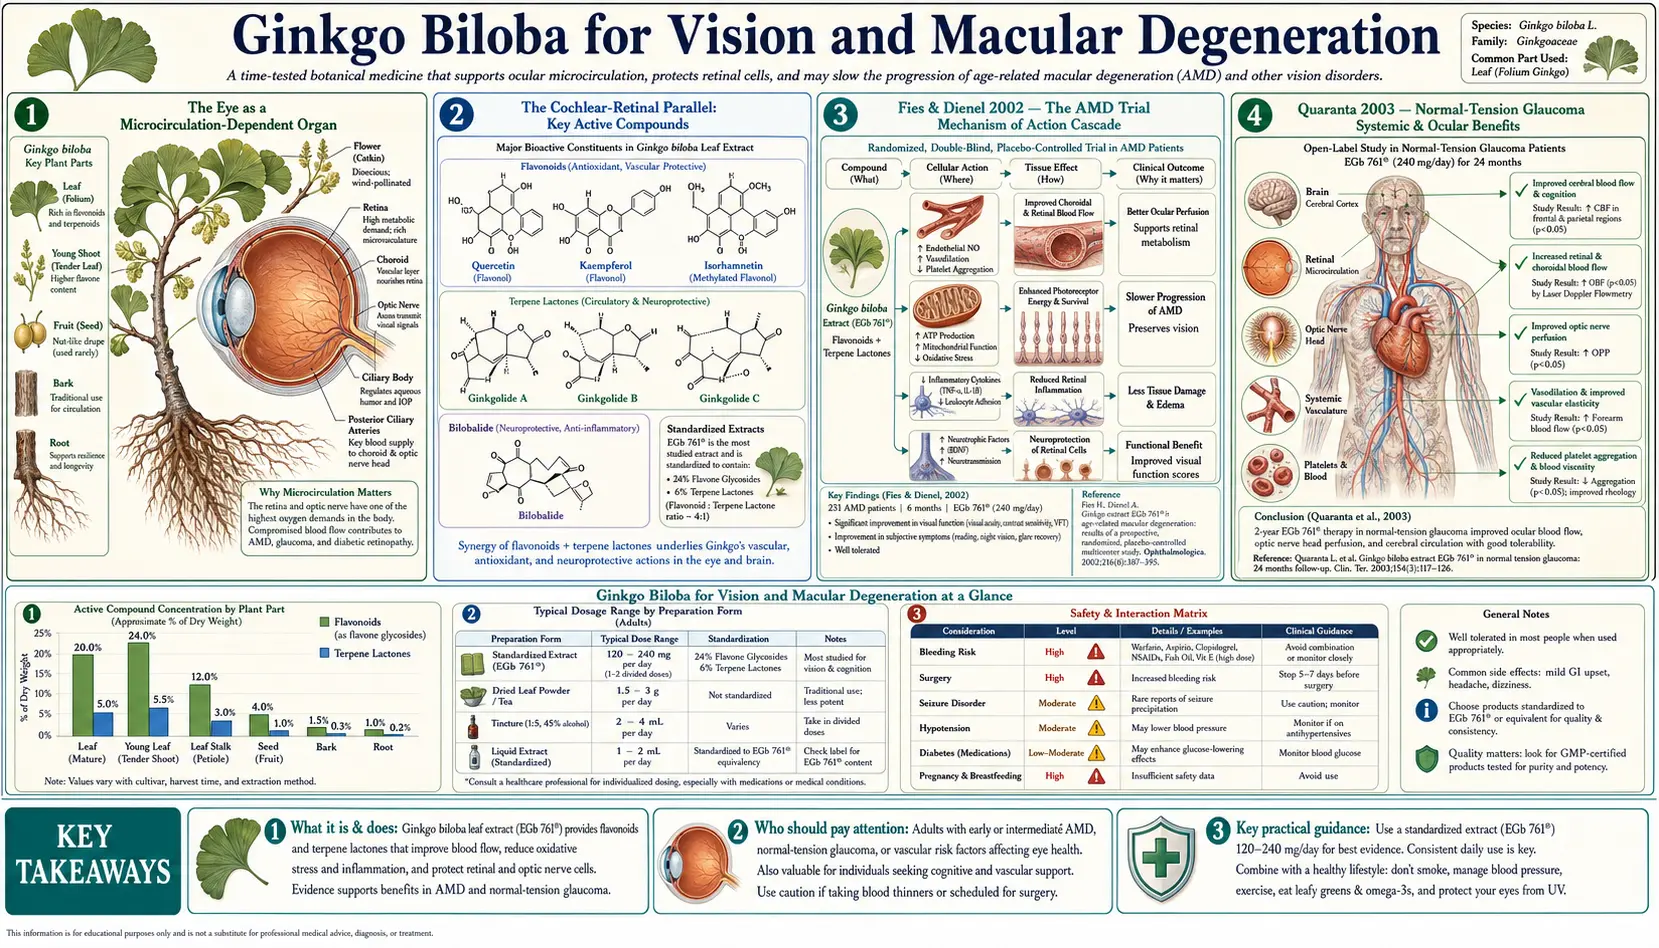
The eye, like the inner ear, is a microcirculation-dependent organ: the retina is the most metabolically active tissue in the body per unit weight, and the choroidal and retinal vessels supplying it are end-arteries with limited collateral reserve. This is the conceptual reason why ginkgo's mechanism — platelet-activating factor (PAF) antagonism, flavonoid antioxidant protection, and erythrocyte deformability improvement — has been hypothesized and tested in three distinct ophthalmologic conditions: normal-tension glaucoma (where the optic nerve is damaged despite normal intraocular pressure (IOP), implicating vascular insufficiency), age-related macular degeneration (where chronic choroidal microcirculatory dysfunction contributes to photoreceptor loss), and diabetic retinopathy (the classic microvascular endpoint of diabetes). The Fies & Dienel 2002 trial in dry age-related macular degeneration (AMD) reported visual acuity improvement with the extract EGb 761 at two doses, without a placebo group; the Quaranta 2003 crossover trial in normal-tension glaucoma reported visual field improvement, and a 2014 trial of the same dose and design did not repeat it; the cochlear-retinal microcirculation parallel ties the ophthalmologic evidence to the broader ginkgo mechanism. The evidence base is smaller and less consistent than for cognitive or peripheral artery disease (PAD) indications. Practitioners describe ginkgo as an add-on for eye disease of microcirculatory origin on the strength of its proposed mechanism.
Table of Contents
- The Eye as a Microcirculation-Dependent Organ
- The Cochlear-Retinal Parallel
- Fies & Dienel 2002 — The Age-Related Macular Degeneration Trial
- Quaranta 2003 — Normal-Tension Glaucoma
- Age-Related Macular Degeneration — Mechanism & Trials
- Glaucoma — NTG vs POAG
- Diabetic Retinopathy
- Direct Retinal Blood Flow Measurement
- The AREDS Question — Why Ginkgo Is Not in the Formula
- Doses Used in Trials and in Practice
- Cautions — Retrobulbar Hemorrhage and Glaucoma Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Eye as a Microcirculation-Dependent Organ
The retina's metabolic demand is exceptional. The outer retina (photoreceptors and retinal pigment epithelium, RPE) consumes oxygen at one of the highest rates of any tissue in the body — the photoreceptors maintain a continuous dark current that requires constant adenosine triphosphate (ATP) supply, and the renewal of photoreceptor outer segments is one of the most metabolically demanding processes in adult cell biology. The retinal pigment epithelium phagocytizes shed outer segment discs daily, generating lipofuscin and reactive oxygen species at high rates.
This metabolic demand is supplied by two distinct vascular systems:
- The retinal vasculature — the central retinal artery and its branches supply the inner retina (ganglion cell layer, inner nuclear layer, inner plexiform layer). These vessels are visible on fundoscopy. Their dysfunction produces diabetic retinopathy, retinal vein occlusion, and the inner-retinal layer ischemia of arterial occlusive disease.
- The choroidal vasculature — a dense network of fenestrated capillaries (the choriocapillaris) supplies the outer retina (photoreceptors and retinal pigment epithelium) by diffusion across Bruch's membrane. The choroid has the highest blood flow per gram of tissue of any organ in the body. Choroidal microcirculatory dysfunction is implicated in age-related macular degeneration.
The optic nerve has its own distinct microcirculation, supplied by branches of the short posterior ciliary arteries. The optic nerve head circulation is exquisitely sensitive to perfusion pressure (the difference between blood pressure and intraocular pressure), and chronic optic nerve ischemia is the proposed mechanism behind normal-tension glaucoma.
All three vascular beds — retinal, choroidal, and optic nerve head — share the basic structural and functional properties that make them susceptible to ginkgo's microcirculatory mechanism: end-artery anatomy, high metabolic demand, sensitivity to viscosity and erythrocyte deformability, vulnerability to PAF-mediated platelet aggregation and leukocyte adhesion in capillaries, and dependence on adequate endothelial nitric oxide signaling for flow regulation. The clinical question is whether the mechanistic plausibility translates to measurable clinical benefit in patients with established ophthalmologic disease.
The Cochlear-Retinal Parallel
The most elegant conceptual frame for understanding ginkgo's ophthalmologic potential is the cochlear-retinal microcirculation parallel. The cochlea and the retina share an unusual set of structural features that no other major organs share:
- Both are supplied by end-arteries with limited collateral circulation (labyrinthine artery for the cochlea, central retinal artery and short posterior ciliary arteries for the retina)
- Both contain sensory cells (cochlear hair cells, retinal photoreceptors and ganglion cells) that are terminally differentiated and non-regenerating in mammals
- Both have exceptional metabolic demand relative to mass (stria vascularis in the cochlea, photoreceptors and RPE in the retina)
- Both are vulnerable to the same insults: aminoglycoside antibiotics damage cochlear hair cells and retinal ganglion cells; loop diuretics damage cochlear stria vascularis and can cause retinal toxicity at high intravenous (IV) dose; hyperviscosity syndromes affect both cochlear and retinal capillary perfusion; chronic hypertension produces both cochlear microvascular damage and retinal microvascular changes
- Both demonstrate age-related microcirculatory decline (presbycusis and age-related macular changes), and both are vulnerable to the same systemic conditions (diabetes, hyperlipidemia, atherosclerosis)
The clinical correlate of this anatomical parallel is the well-documented epidemiologic association between hearing loss and visual impairment in aging populations (dual sensory impairment increases dramatically after age 70), and the parallel mechanistic case for ginkgo in both cochlear ischemia (tinnitus, sudden sensorineural hearing loss) and retinal ischemia (normal-tension glaucoma, age-related macular degeneration). For the cochlear side of this parallel, see our Tinnitus page.
Fies & Dienel 2002 — The Age-Related Macular Degeneration Trial
The reference trial for ginkgo in age-related macular degeneration is Fies P & Dienel A (2002) "Ginkgo extract in impaired vision — treatment with special extract EGb 761 of impaired vision due to dry senile macular degeneration," published in Wiener Medizinische Wochenschrift. This was a randomized double-blind dose-comparison trial of two EGb 761 doses (60 mg/day vs 240 mg/day) in 99 patients with dry (non-neovascular) age-related macular degeneration over 6 months.
The primary outcome was change in corrected visual acuity in the more severely affected eye. Secondary outcomes included near visual acuity, contrast sensitivity, and patient-reported visual function.
Results:
- Vision improved in both groups from four weeks on. After 24 weeks, visual acuity had risen by 0.13 in the 240 mg/day group (50 patients) and by 0.10 in the 60 mg/day group (49 patients). The share of patients who improved by at least 0.2 was nearly twice as large at 240 mg/day, but with p = 0.08 that difference is not statistically significant.
- Contrast sensitivity improved more in the 240 mg/day arm
- Patient-reported visual function (reading speed, recognition of faces, ability to perform fine visual tasks) improved more in the 240 mg/day arm
- The investigator rated tolerability as favorable at both doses. The Cochrane review of these trials states that adverse effects and quality of life were not reported
The Fies & Dienel trial has several methodologic limitations: there was no placebo arm (both dose groups received active drug, which limits inference about absolute effect size); the trial was relatively short (6 months) for an age-related macular degeneration outcome; the sample size was modest; the visual acuity improvement was small enough that its clinical significance is debatable in the context of a slowly progressive degenerative disease.
The trial used the same 240 mg/day dose as the cognitive and peripheral artery disease trials, and it did not show a statistically significant difference between doses. The authors concluded that the extract was effective in dry age-related macular degeneration. It has not been followed by large definitive placebo-controlled trials, partly because the modern age-related macular degeneration treatment landscape has been dominated by supplementation from the Age-Related Eye Disease Study (AREDS) and (for wet age-related macular degeneration) anti-vascular endothelial growth factor (anti-VEGF) intravitreal injections.
Quaranta 2003 — Normal-Tension Glaucoma
The reference trial for ginkgo in glaucoma is Quaranta L, Bettelli S, Uva MG, Semeraro F, Turano R, Gandolfo E (2003) "Effect of Ginkgo biloba extract on preexisting visual field damage in normal tension glaucoma," published in Ophthalmology. This was a randomized double-blind crossover trial in 27 patients with bilateral normal-tension glaucoma (NTG), comparing ginkgo extract 40 mg three times daily vs placebo for 4 weeks each, with an 8-week washout between phases.
Normal-tension glaucoma is the variant of primary open-angle glaucoma in which intraocular pressure is consistently within the statistically normal range (under 22 mmHg) but progressive optic nerve damage and visual field loss occur. The proposed mechanism is vascular dysregulation at the optic nerve head — impaired autoregulation of optic nerve perfusion, vasospasm of the short posterior ciliary arteries, and impaired endothelial function. NTG is the glaucoma subtype with the strongest mechanistic case for ginkgo benefit.
The primary outcome was change in Humphrey visual field mean defect (a quantitative measure of visual field loss in decibels; the larger the loss, the more damage).
Results:
- Ginkgo phase: mean deviation improved from 11.40 ± 3.27 dB at baseline to 8.78 ± 2.56 dB after treatment (P = 0.0001); the abstract calls the extract ginkgo biloba extract and does not name EGb 761
- Placebo phase: no significant change in visual field defect
- The between-phase difference was statistically significant
- Intraocular pressure did not change in either phase (excluding IOP-lowering as the mechanism)
- No significant adverse events on ginkgo extract at 40 mg three times daily for 4 weeks
This was a striking result — visual field improvement in a chronic neurodegenerative condition is uncommon. The trial's limitations are the small sample size (n=27), the short treatment duration (4 weeks per arm), and the crossover design (which can be vulnerable to carryover effects in glaucoma trials). The result has been broadly cited as supporting the NTG-specific ginkgo indication. The closest repeat did not reproduce it: a 2014 Chinese crossover trial used the same dose and design in 35 people with normal-tension glaucoma, 28 of whom completed testing. Changes in visual field and contrast sensitivity did not differ between ginkgo and placebo (P > 0.2), and the authors concluded that the extract “had no effect on mean defect or contrast sensitivity.”
In practice: some practitioners add ginkgo extract for normal-tension glaucoma patients who are already on maximum tolerable IOP-lowering therapy (prostaglandin analogs, beta-blockers, alpha agonists, carbonic anhydrase inhibitors, rho kinase inhibitors) and who continue to show visual field progression. The 240 mg/day often used in practice is double the 120 mg/day this trial gave, and the evidence base is small.
Age-Related Macular Degeneration — Mechanism & Trials
Age-related macular degeneration (AMD) is the leading cause of irreversible vision loss in adults over 65 in developed countries. It exists in two major forms:
- Dry (non-neovascular) age-related macular degeneration — the more common form. Characterized by accumulation of drusen (extracellular lipid-rich deposits) beneath the retinal pigment epithelium, with progressive loss of RPE cells and overlying photoreceptors in the macula. Slowly progressive over years. Two eye injections now slow its late form, geographic atrophy: pegcetacoplan, the first treatment the US Food and Drug Administration approved for it, slowed lesion growth by 16-22% at 24 months in two phase 3 trials, with no difference in visual function tests, while new wet disease appeared in 6-13% of treated patients against 2-4% on sham; avacincaptad pegol showed a 14% difference in growth at 12 months. The AREDS / AREDS2 supplementation regimen reduces risk of advanced age-related macular degeneration by approximately 25% in patients with intermediate-stage disease.
- Wet (neovascular) age-related macular degeneration — the less common but more rapidly visually devastating form. Characterized by choroidal neovascularization — new abnormal blood vessels growing through Bruch's membrane into the subretinal space, leaking fluid and blood that disrupts retinal architecture. Treatment is intravitreal anti-VEGF injection (ranibizumab, bevacizumab, aflibercept, brolucizumab, faricimab) on monthly to quarterly intervals indefinitely.
The mechanistic case for ginkgo in dry age-related macular degeneration has several components:
- Choroidal microcirculation — choroidal blood flow declines progressively with age, and impaired choroidal perfusion has been documented in dry age-related macular degeneration using indocyanine green (ICG) angiography and optical coherence tomography (OCT) angiography. Ginkgo's PAF-antagonist and flavonoid-NO mechanisms target the same microcirculation
- Oxidative stress reduction — oxidative damage to the RPE is a major driver of dry age-related macular degeneration progression. Flavonoid antioxidant scavenging of reactive oxygen species in the RPE is mechanistically protective
- Reduced inflammatory cell adhesion — chronic low-grade choroidal inflammation contributes to age-related macular degeneration progression. Ginkgolide-B's PAF antagonism reduces PAF-mediated leukocyte adhesion and chemotaxis
- Iron and copper chelation — iron accumulation in the RPE contributes to oxidative stress through Fenton-reaction free-radical generation. Flavonoid metal chelation may modestly reduce this oxidative burden
The Cochrane 2013 review of ginkgo for age-related macular degeneration (Evans 2013) included only 2 trials with 119 patients and concluded that the question of whether people with age-related macular degeneration should take ginkgo to slow the disease “has not been answered by research to date,” adding that two small trials “have suggested possible benefit of Gingko biloba on vision and further trials are warranted.” The Fies & Dienel 2002 trial and the Lebuisson 1986 trial (the original French trial that showed visual acuity improvement with EGb 761 vs placebo) are the most-cited individual trials, but neither was large or definitive.
Where it sits: ginkgo has not been tested as a replacement for AREDS / AREDS2 supplementation (which has high-quality evidence in the appropriate age-related macular degeneration population) or for anti-VEGF injection in wet age-related macular degeneration. Some people with dry age-related macular degeneration take it alongside other supplements; the evidence is modest. For more on age-related macular degeneration see our Macular Degeneration page.
Glaucoma — NTG vs POAG
The positive ginkgo glaucoma reports come mostly from normal-tension glaucoma rather than primary open-angle glaucoma (POAG), though results in normal-tension glaucoma are mixed too. The proposed reason is the underlying mechanism — NTG is the glaucoma subtype with the strongest vascular component, while elevated-pressure POAG is dominated by mechanical injury to retinal ganglion cell axons at the optic nerve head.
- Normal-tension glaucoma (NTG) — intraocular pressure consistently below 22 mmHg with progressive optic nerve damage. Vascular dysregulation (vasospasm, impaired autoregulation, endothelial dysfunction) is the dominant proposed mechanism. The Quaranta 2003 trial is the key positive trial and the 2014 Guo trial above the key negative one. The Park 2011 trial (30 patients, ginkgo extract 80 mg twice daily or placebo for 4 weeks) measured peripapillary retinal blood flow with a Heidelberg retina flowmeter and documented increased flow with the extract. The longest record is a Korean retrospective study of 42 treated patients followed a mean 12.3 years on 80 mg twice daily: visual field loss slowed from -0.619 to -0.379 dB per year after starting ginkgo. It had no control group, so it cannot separate ginkgo from other changes. A 2025 systematic review (8 studies, 428 people, median follow-up 3.7 months) found no difference between ginkgo and control groups in eye pressure, mean deviation or corrected pattern standard deviation, and said the evidence is not sufficient to conclude an effect.
- Primary open-angle glaucoma (POAG) — elevated intraocular pressure with progressive optic nerve damage. Mechanical pressure-induced injury is the dominant mechanism. Ginkgo trials in pure POAG have shown smaller and less consistent benefits. Ginkgo is not a substitute for IOP-lowering therapy in POAG.
- Acute angle-closure glaucoma — medical and surgical emergency requiring urgent IOP reduction. Ginkgo has no role.
- Pseudoexfoliation and pigmentary glaucoma — secondary open-angle glaucomas with specific mechanical drainage system pathology. Ginkgo is not a primary therapy; practitioners sometimes add it after IOP control is optimized.
- Neovascular glaucoma — caused by retinal ischemia (diabetic, or after a central retinal vein occlusion). Ginkgo is not a primary therapy; treatment is anti-VEGF and panretinal photocoagulation.
The Ritch 2000 hypothesis paper "Potential role for Ginkgo biloba extract in the treatment of glaucoma" in Medical Hypotheses is the most-cited theoretical framework for ginkgo in NTG and remains the conceptual basis for clinical use in this specific subtype. The 2012 Cybulska-Heinrich paper is a narrative review offering what it calls a scientific opinion on ginkgo as an adjuvant in glaucoma, not a patient series. For more on glaucoma management, see our Glaucoma page.
Diabetic Retinopathy
Diabetic retinopathy is the leading cause of vision loss in working-age adults in developed countries. It is fundamentally a microvascular disease of the retina, with two major stages:
- Non-proliferative diabetic retinopathy (NPDR) — microaneurysms, dot-blot hemorrhages, hard exudates, cotton-wool spots, retinal edema, intraretinal microvascular abnormalities. Driven by hyperglycemia-induced endothelial damage, pericyte loss, capillary basement membrane thickening, and capillary nonperfusion.
- Proliferative diabetic retinopathy (PDR) — new vessel growth from the optic disc or elsewhere in response to retinal ischemia. Treatment is panretinal photocoagulation or anti-VEGF injection.
The mechanistic case for ginkgo in early NPDR is the same as in other microvascular indications: PAF antagonism reduces microvascular thrombosis and leukocyte adhesion, flavonoid antioxidant scavenging reduces hyperglycemia-induced oxidative damage, and improved erythrocyte deformability improves flow through narrowed capillaries.
The Lanthony & Cosson 1988 double-blind trial in 29 people with early diabetic retinopathy measured color vision (an early functional marker of retinal dysfunction in diabetes) over 6 months and reported a tendency to improvement with ginkgo extract and worsening on placebo. The improvement reached statistical significance only on one color test (the Desaturated Panel D-15) among people without retinal ischemia. Subsequent small trials have suggested benefit on visual field, retinal sensitivity, and microaneurysm count. The evidence base is too small to be definitive.
In practice: for people with established diabetes and early NPDR (no center-involving edema, no proliferative changes), practitioners describe ginkgo at 240 mg/day as an add-on to glycemic control, statin therapy, blood pressure control, and angiotensin-converting enzyme inhibitor (ACE inhibitor) therapy. It has not been tested as a replacement for those treatments. In proliferative disease, ginkgo has no documented role and the bleeding-risk concern is amplified by the underlying retinal vascular fragility.
Direct Retinal Blood Flow Measurement
Blood flow in the eye has been measured directly before and after ginkgo. Studies using color Doppler imaging, a laser flowmeter, laser Doppler velocimetry, and OCT angiography point in both directions:
- Chung 1999 — in 11 healthy volunteers, ginkgo extract 40 mg three times daily for 2 days raised end-diastolic flow velocity in the ophthalmic artery from 6.5 to 7.7 cm/sec (23% change, p=0.023)
- Park 2011 — increased peripapillary retinal blood flow on a Heidelberg retina flowmeter in 30 NTG patients after 4 weeks of ginkgo extract 80 mg twice daily or placebo
- Wimpissinger 2007 — in 15 healthy men, a single 240 mg dose of EGb 761 left retinal and choroidal blood flow unchanged; optic nerve head flow rose against baseline but not significantly against placebo. The authors concluded that a single dose “does not influence ocular blood flow to a relevant degree”
- Hodgson 2025 — in 17 treated primary open-angle glaucoma patients, 120 mg twice daily for 4 months gave no significant change in macular perfusion density (p = 0.17) and a significantly lower peripapillary density (0.44 versus 0.42, p = 0.02); the authors reported no clinically significant improvement
- Hirooka 2004 — measured nerve cell survival in rats, not blood flow in people: retinal ganglion cell loss was 4.6% with EGb 761 against 29.8% untreated at 5 months
The OCT angiography era (post-2014) has enabled quantitative measurement of macular and peripapillary capillary perfusion at much higher resolution than was previously possible. OCT angiography studies of ginkgo's effects on retinal capillary perfusion are still few; the 2025 Hodgson trial above did not find the improvement the mechanism predicts, and its authors said larger studies are needed.
The AREDS Question — Why Ginkgo Is Not in the Formula
A frequent patient question is why ginkgo is not included in the AREDS or AREDS2 supplementation formula, given its plausibility for age-related macular degeneration. The answer reflects the trial-design history rather than a definitive judgment about ginkgo's efficacy:
- The original AREDS formula (2001) was developed in the late 1990s by National Eye Institute investigators who selected antioxidants and zinc based on the prevailing epidemiologic evidence at the time — Vitamin C, Vitamin E, beta-carotene, zinc, and copper. Ginkgo was not on the candidate list because the dry age-related macular degeneration efficacy trials were still pending.
- The AREDS2 formula (2013) modified the original by substituting lutein and zeaxanthin for beta-carotene (which had increased lung cancer risk in former smokers) and added omega-3 fatty acids in one arm (which did not show additional benefit). Ginkgo was again not included because no large definitive trial had been performed in age-related macular degeneration.
- No pharmaceutical or supplement sponsor has funded a large definitive trial of EGb 761 in age-related macular degeneration — the patent has long expired, the regulatory pathway in the US is the dietary supplement framework rather than the drug framework, and the age-related macular degeneration treatment landscape has been dominated by intravitreal anti-VEGF for wet age-related macular degeneration.
- The German practice pattern of adding EGb 761 240 mg/day to AREDS for dry age-related macular degeneration patients does not have randomized controlled trial (RCT) support comparable to AREDS itself.
In short: AREDS or AREDS2 is the nutritional intervention with the stronger evidence for intermediate-stage dry age-related macular degeneration. Ginkgo extract has smaller and less consistent evidence.
Doses Used in Trials and in Practice
- Dose: The Fies & Dienel 2002 trial compared EGb 761 at 240 mg/day and 60 mg/day and did not show a statistically significant difference (p = 0.08). The glaucoma trials used 40 mg three times daily (Quaranta, Guo) or 80 mg twice daily (Park). Practitioners commonly describe 240 mg/day, split as 120 mg twice daily with meals.
- Duration: the trials above ran from 4 weeks to 6 months. Practitioners describe at least 12 weeks before a first assessment, and 6 months or longer for eye outcomes. For chronic conditions (NTG, dry age-related macular degeneration), they describe continuing indefinitely if it is tolerated and appears to help.
- Form: the Fies & Dienel and Wimpissinger studies used the standardized study extract EGb 761; several other trial abstracts say only ginkgo biloba extract.
- Combination with AREDS2: no significant interaction is described; some people with dry age-related macular degeneration take both.
- Who practitioners expect to respond (a practice impression, not a trial finding): dry age-related macular degeneration with baseline preserved central acuity, NTG with documented visual field progression on maximum IOP-lowering therapy, early NPDR with optimal glycemic control.
- Who practitioners do not expect to respond (also a practice impression): end-stage dry age-related macular degeneration with severe geographic atrophy, wet age-related macular degeneration without anti-VEGF therapy, advanced POAG, proliferative diabetic retinopathy.
- How response is followed: serial Humphrey visual fields for glaucoma; OCT macular thickness and visual acuity on the Early Treatment Diabetic Retinopathy Study (ETDRS) chart for age-related macular degeneration; serial fundus photography and color vision testing for early diabetic retinopathy.
Cautions — Retrobulbar Hemorrhage and Glaucoma Drug Interactions
- Retrobulbar hemorrhage risk during ocular procedures — one published case describes a retrobulbar hemorrhage after a peribulbar local anaesthetic injection for cataract surgery in a woman taking ginkgo tablets, which the authors said “may have predisposed her”; the link is possible, not established. No case tied to vitrectomy or intravitreal injection was found. Some practitioners describe stopping ginkgo about 14 days before a planned ocular procedure, including cataract surgery, vitreoretinal surgery, glaucoma drainage device implantation, and corneal transplant; no study of that interval was found.
- Bleeding risk in patients on antiplatelet therapy for cardiovascular disease — older age-related macular degeneration patients are commonly on aspirin or clopidogrel. The ginkgo-plus-aspirin combination has been associated with spontaneous bleeding including intraocular hemorrhage.
- Interaction with topical glaucoma drugs — no clinically significant pharmacokinetic interaction with prostaglandin analogs, beta-blockers, alpha agonists, carbonic anhydrase inhibitors, rho kinase inhibitors, or topical pilocarpine. Ginkgo is compatible with maximum tolerable medical IOP-lowering therapy.
- Interaction with anti-VEGF intravitreal therapy — no documented pharmacokinetic interaction. Bleeding-risk concerns lead some practitioners to describe the same 14-day stop before a scheduled injection; no study of that interval was found.
- Subconjunctival hemorrhage — mild spontaneous subconjunctival bleeding is occasionally reported with ginkgo and is benign but cosmetically distressing.
- Pregnancy and breastfeeding — insufficient safety data. Age-related macular degeneration and glaucoma are rare in reproductive-age women but the caution applies.
- Diabetes — ginkgo modestly affects insulin secretion and glucose disposition. Glucose patterns can shift after starting ginkgo, including low blood sugar (hypoglycemia). Tight glycemic control is the foundation of diabetic retinopathy prevention; ginkgo has been used only as an add-on.
- Seizure threshold — ginkgo is contraindicated in epilepsy. Topiramate (a carbonic anhydrase inhibitor with anticonvulsant properties) is labelled for epilepsy and migraine, not glaucoma, and people taking it for seizures fall under that concern. Its label warns of acute myopia and secondary angle closure glaucoma, which “can lead to permanent visual loss.”
- Pre-operative anesthesia disclosure — in the published case above, the ginkgo use came to light only after the bleed. Ginkgo and other herbal supplements belong on the surgical pre-operative medication list for that reason.
Key Research Papers
- Quaranta L, Bettelli S, Uva MG, Semeraro F, Turano R, Gandolfo E (2003). Effect of Ginkgo biloba extract on preexisting visual field damage in normal tension glaucoma. Ophthalmology 110(2):359-362. — PubMed PMID: 12578781
- Fies P, Dienel A (2002). Ginkgo extract in impaired vision — treatment with special extract EGb 761 of impaired vision due to dry senile macular degeneration. Wiener Medizinische Wochenschrift 152(15-16):423-426. — PubMed PMID: 12244891
- Evans JR (2013). Ginkgo biloba extract for age-related macular degeneration. Cochrane Database of Systematic Reviews (1):CD001775. — PubMed PMID: 23440785
- Lebuisson DA, Leroy L, Rigal G (1986). Treatment of senile macular degeneration with Ginkgo biloba extract. A preliminary double-blind drug versus placebo study. Presse Med 15(31):1556-1558. — PubMed PMID: 2947098
- Park JW, Kwon HJ, Chung WS, Kim CY, Seong GJ (2011). Short-term effects of Ginkgo biloba extract on peripapillary retinal blood flow in normal tension glaucoma. Korean Journal of Ophthalmology 25(5):323-328. — PubMed PMID: 21976939
- Cybulska-Heinrich AK, Mozaffarieh M, Flammer J (2012). Ginkgo biloba: an adjuvant therapy for progressive normal and high tension glaucoma. Molecular Vision 18:390-402. — PubMed PMID: 22355250
- Ritch R (2000). Potential role for Ginkgo biloba extract in the treatment of glaucoma. Medical Hypotheses 54(2):221-235. — PubMed PMID: 10790757
- Chung HS, Harris A, Kristinsson JK, Ciulla TA, Kagemann C, Ritch R (1999). Ginkgo biloba extract increases ocular blood flow velocity. Journal of Ocular Pharmacology and Therapeutics 15(3):233-240. — PubMed PMID: 10385132
- Hirooka K, Tokuda M, Miyamoto O, Itano T, Baba T, Shiraga F (2004). The Ginkgo biloba extract (EGb 761) provides a neuroprotective effect on retinal ganglion cells in a rat model of chronic glaucoma. Current Eye Research 28(3):153-157. — PubMed PMID: 14977516
- Lanthony P, Cosson JP (1988). The course of color vision in early diabetic retinopathy treated with Ginkgo biloba extract. Journal Français d'Ophtalmologie 11(10):671-674. — PubMed PMID: 3072365
- Wimpissinger B, Berisha F, Garhoefer G, Polak K, Schmetterer L (2007). Influence of Ginkgo biloba on ocular blood flow. Acta Ophthalmologica Scandinavica 85(4):445-449. — PubMed PMID: 17324220
- Mozaffarieh M, Flammer J (2007). Is there more to glaucoma treatment than lowering IOP? Survey of Ophthalmology 52 Suppl 2:S174-179. — PubMed PMID: 17998043
- Guo X, Kong X, Huang R, Jin L, Ding X, He M, Liu X, Patel MC, Congdon NG (2014). Effect of Ginkgo biloba on visual field and contrast sensitivity in Chinese patients with normal tension glaucoma: a randomized, crossover clinical trial. Investigative Ophthalmology & Visual Science 55(1):110-6. — PubMed PMID: 24282229
- Prinz J, Prokosch V, Wang X, Feng Y, Walter P, Fuest M, Migliorini F (2025). Efficacy of Ginkgo biloba on parameters in glaucoma: A systematic review. PLoS One 20(2):e0314644. — PubMed PMID: 39951447
- Lee J, Sohn SW, Kee C (2013). Effect of Ginkgo biloba extract on visual field progression in normal tension glaucoma. Journal of Glaucoma 22(9):780-4. — PubMed PMID: 22595937
- Hodgson K, Palakkamanil MM, Zhang A, Dyachok OM, Smith CA, Nicolela MT, Chauhan BC, Shuba LM (2025). Effect of ginkgo biloba extract on macula and peripapillary perfusion examined using optical coherence tomography angiography. Canadian Journal of Ophthalmology 60(4):e566-e571. — PubMed PMID: 39961352
- Fong KC, Kinnear PE (2003). Retrobulbar haemorrhage associated with chronic Gingko biloba ingestion. Postgraduate Medical Journal 79(935):531-2. — PubMed PMID: 13679551
- Heier JS, Lad EM, Holz FG, Rosenfeld PJ, Guymer RH, Boyer D, et al. (2023). Pegcetacoplan for the treatment of geographic atrophy secondary to age-related macular degeneration (OAKS and DERBY): two multicentre, randomised, double-masked, sham-controlled, phase 3 trials. Lancet 402(10411):1434-1448. — PubMed PMID: 37865470
- Khanani AM, Patel SS, Staurenghi G, Tadayoni R, Danzig CJ, Eichenbaum DA, et al. (2023). Efficacy and safety of avacincaptad pegol in patients with geographic atrophy (GATHER2): 12-month results from a randomised, double-masked, phase 3 trial. Lancet 402(10411):1449-1458. — PubMed PMID: 37696275