Beets for Nitrates and Blood Pressure
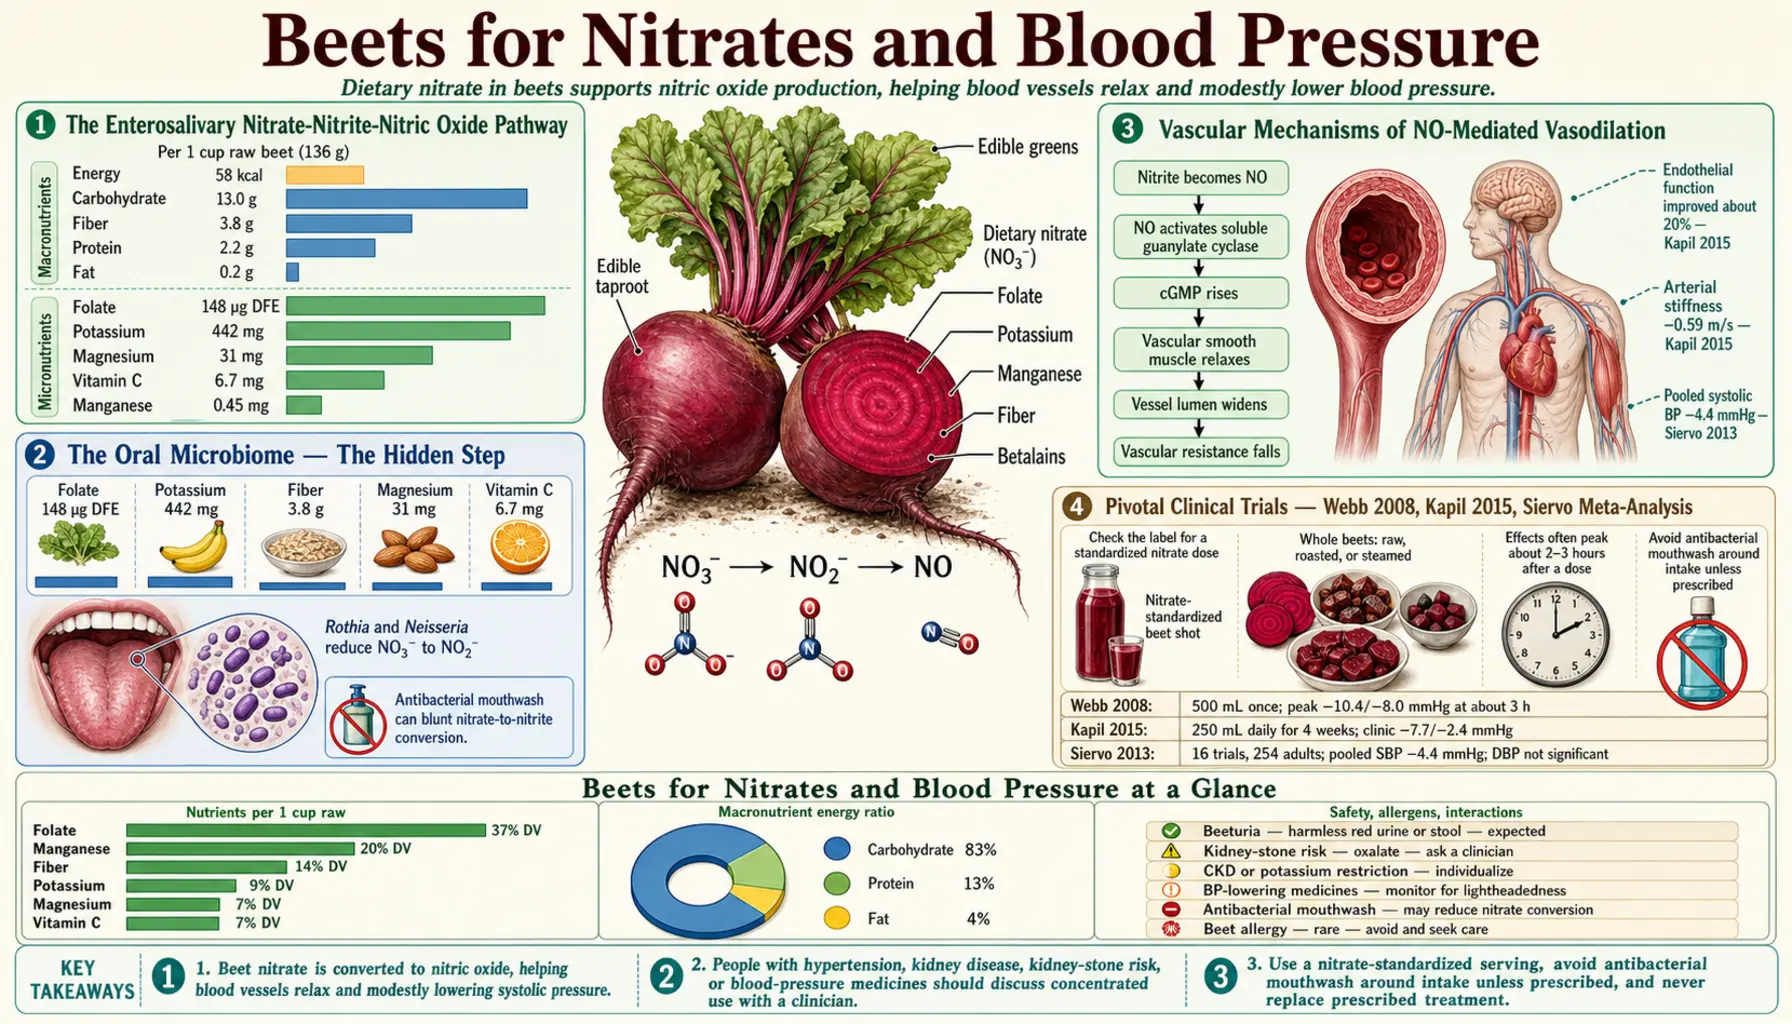
Beetroot juice has become one of the most rigorously studied dietary interventions for blood pressure in the past two decades. The mechanism is no longer in doubt: dietary inorganic nitrate (NO3−) is absorbed in the upper small intestine, concentrated 10-fold in the salivary glands, reduced to nitrite (NO2−) by oral commensal bacteria, swallowed, and then reduced to bioactive nitric oxide (NO) in the acidic stomach and in hypoxic peripheral tissues. The downstream NO produces vasodilation, platelet inhibition, and blood-pressure reduction. In a 2008 trial in 14 healthy volunteers, a single 500 mL dose of beetroot juice lowered blood pressure by up to 10.4/8 mmHg about 3 hours later; at 24 hours systolic pressure was still 4.4 mmHg lower than with water, a difference that was not statistically significant. Sustained daily intake produces ongoing reductions in treated hypertensive patients. This page walks through the enterosalivary pathway in detail, the pivotal clinical trials, dosing, the mouthwash and proton pump inhibitor (PPI) gotchas, and how beets fit into broader hypertension management.
Table of Contents
- The Enterosalivary Nitrate-Nitrite-Nitric Oxide Pathway
- The Oral Microbiome — The Hidden Step
- Vascular Mechanisms of NO-Mediated Vasodilation
- Pivotal Clinical Trials — Webb 2008, Kapil 2015, Siervo Meta-Analysis
- Dosing — Juice, Concentrate, Powder, Whole Root
- The Antibacterial Mouthwash Trap
- The Proton-Pump-Inhibitor Trap
- How Beets Fit Into Hypertension Management
- Cautions, Oxalates, and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Enterosalivary Nitrate-Nitrite-Nitric Oxide Pathway
For decades, the standard textbook account held that all biological nitric oxide came from one source: the L-arginine / endothelial nitric oxide synthase (eNOS) pathway, in which the amino acid L-arginine is converted to L-citrulline and NO by eNOS in vascular endothelial cells. This is still the dominant pathway under normal physiological conditions, but it is not the only one. Beginning in the mid-1990s, work by Jon Lundberg, Mark Gladwin, and Nathan Bryan established a parallel pathway that runs in reverse: nitrate is reduced to nitrite, and nitrite is reduced to NO, completely independent of the eNOS enzyme.
The pathway works as follows. Dietary nitrate from leafy greens, beets, and other vegetables is rapidly and almost completely absorbed in the upper small intestine, entering the bloodstream and circulating systemically. Within roughly 30 minutes of ingestion, plasma nitrate concentration rises 10–20 fold above baseline. Crucially, the salivary glands actively take up nitrate from the blood and concentrate it in saliva to roughly 10 times the plasma concentration — this is an active, energy-dependent process mediated by the sialin transporter (SLC17A5) on salivary acinar cells.
The concentrated salivary nitrate, on contact with the tongue and oral cavity, is reduced to nitrite by facultative anaerobic bacteria that colonize the posterior tongue and tonsillar crypts. The dominant nitrate-reducing genera are Veillonella, Actinomyces, Rothia, Neisseria, and Prevotella. These organisms use nitrate as a terminal electron acceptor in anaerobic respiration, producing nitrite as a metabolic byproduct. The host benefits, the bacteria benefit, and the relationship is one of the cleanest examples of a true mutualistic symbiosis in human physiology.
The nitrite-rich saliva is then swallowed. In the acidic stomach (pH 1–3 fasting, pH 3–5 with food), some nitrite is protonated to nitrous acid (HNO2) and disproportionates to NO, NO2, and water. The rest is absorbed intact into the bloodstream. Once in circulation, nitrite is reduced to NO by several enzymes that have nitrite-reductase activity under hypoxic or acidic conditions: deoxyhemoglobin, deoxymyoglobin, xanthine oxidoreductase, mitochondrial cytochromes, and aldehyde oxidase. Crucially, all of these enzymes increase their nitrite-reductase activity as oxygen tension falls, so the pathway preferentially delivers NO to hypoxic, ischemic, or acidotic tissue — exactly where vasodilation is most needed.
The result is a redundant, hypoxia-targeted, microbiome-dependent NO-generation system that complements the classical eNOS pathway and remains active even when eNOS is impaired by aging, endothelial dysfunction, hypercholesterolemia, or diabetes.
The Oral Microbiome — The Hidden Step
The dependence of the entire nitrate-NO pathway on oral commensal bacteria is one of the most surprising and clinically important findings in modern nitric oxide biology. Mammalian cells contain little to no nitrate-reductase activity — the enzymes simply do not exist in human tissue. Without the bacterial intermediate, dietary nitrate is largely excreted in the urine unchanged.
Two human experiments show this hidden step. In Webb's 2008 trial, volunteers who spat out all their saliva during and for 3 hours after drinking 500 mL of beetroot juice did not get the rise in blood nitrite, and the fall in blood pressure and the reduced platelet clumping seen when they swallowed normally did not happen. In a 2015 randomized crossover trial by Bondonno and colleagues, 15 adults with treated high blood pressure (mean age 65) used an antibacterial mouthwash for 3 days or water for 3 days; no beetroot juice was given. The mouthwash reduced the mouth's conversion of nitrate to nitrite and lowered saliva nitrite, and systolic blood pressure was 2.3 mmHg higher than with water (95% CI 0.5 to 4.0), with no change in diastolic pressure.
The clinical implications are striking. Patients with hypertension who use daily antibacterial mouthwash may be inadvertently raising their own blood pressure by suppressing the nitrate-reduction pathway. Observational studies have found higher 5-year incidence of hypertension among twice-daily antibacterial mouthwash users. The human evidence is mixed, though: a 2026 scoping review of nine studies found that five showed a significant rise in blood pressure after mouthwash use and four found none, and its authors concluded that no firm conclusion can yet be drawn. Periodontal therapy guidelines have begun to acknowledge this tradeoff — short-course chlorhexidine after surgical procedures is fine, but long-term daily use is no longer recommended for routine oral hygiene.
For someone eating beets for blood pressure, the relevant finding is that three days of antibacterial mouthwash raised systolic pressure by 2.3 mmHg in the Bondonno trial. Mechanical hygiene (brushing, flossing, tongue scraping) does not harm the nitrate-reducing flora because these bacteria colonize the posterior tongue surface in biofilms that mechanical hygiene does not reach. Alcohol-containing mouthwashes are also broadly antibacterial — the alcohol itself kills the relevant flora — so alcohol-free, non-antiseptic rinses are the ones described as leaving this flora intact.
Vascular Mechanisms of NO-Mediated Vasodilation
Once nitric oxide is generated in the vasculature, the downstream signaling is well-characterized. NO diffuses freely across cell membranes (it is a small uncharged radical with a half-life of about 1–5 seconds in tissue) and binds to the heme group of soluble guanylyl cyclase (sGC) in vascular smooth muscle cells. sGC activation increases intracellular cyclic GMP (cGMP), which activates protein kinase G (PKG). PKG phosphorylates several substrates that collectively reduce intracellular calcium availability, dephosphorylate myosin light chains, and relax the smooth muscle — producing vasodilation.
The same pathway is targeted by sildenafil, tadalafil, and other phosphodiesterase-5 (PDE5) inhibitors, which prevent the breakdown of cGMP and prolong NO signaling. Beetroot juice and sildenafil work on the same downstream pathway and additively lower blood pressure — which is why the research raises a concern about excess blood-pressure lowering when high-dose beet supplements are added to PDE5 inhibitors.
NO also has direct antiplatelet effects (NO inhibits platelet activation through cGMP-mediated reduction in intracellular calcium), endothelial-protective effects (NO scavenges superoxide and reduces oxidative damage), and anti-inflammatory effects (NO inhibits leukocyte adhesion to the endothelial surface). The downstream effects of beetroot juice in human trials include not only the blood-pressure reduction but also measurable reductions in platelet aggregation (Webb 2008), improved flow-mediated dilation, and reduced markers of endothelial dysfunction.
Notably, the NO generated from dietary nitrate appears to be selectively delivered to hypoxic and ischemic tissue, because the enzymes that reduce nitrite to NO (deoxyhemoglobin, xanthine oxidoreductase) work better at low oxygen tension and low pH. This means the same dose of dietary nitrate produces greater vasodilation in tissue that needs it most — exercising muscle, ischemic myocardium, or hypoxic peripheral vasculature — than in well-oxygenated tissue. This is a beautifully targeted physiological design.
Pivotal Clinical Trials — Webb 2008, Kapil 2015, Siervo Meta-Analysis
The modern era of beetroot juice cardiology research began with Webb and colleagues at Barts and the London Medical School in 2008. In a small open-label crossover trial, 14 healthy volunteers drank 500 mL of beetroot juice (containing about 23 mmol nitrate) or water. Within 3 hours, systolic blood pressure dropped by 10.4 mmHg and diastolic by 8.0 mmHg in the beetroot arm, with no change in the water arm. At 24 hours systolic pressure was 4.4 mmHg lower than with water, which was not statistically significant (P = 0.058), and diastolic pressure no longer differed. Mechanistic substudies confirmed elevated plasma nitrite, ex vivo platelet inhibition, and improved flow-mediated dilation. The trial established three things at once: that the effect was real, that it was driven by nitrate (not other beet phytochemicals), and that it worked through the nitrite-to-NO pathway.
The Kapil 2015 trial extended this to hypertensive patients. In this double-blind trial, 68 patients with high blood pressure aged 18 to 85 — 34 not yet taking blood-pressure medicines and 34 already treated — were randomized to 250 mL daily beetroot juice or nitrate-free beetroot juice (placebo) for 4 weeks. Results:
- Clinic blood pressure (BP) reduced by 7.7/2.4 mmHg (systolic/diastolic) in the beetroot arm; the clinic diastolic change was borderline (P = 0.050)
- 24-hour ambulatory blood pressure reduced by 7.7/5.2 mmHg
- Home blood pressure reduced by 8.1/3.8 mmHg
- Flow-mediated dilation improved by 20%
- Arterial stiffness (pulse wave velocity) decreased by 0.59 m/s
- No tachyphylaxis — the effect persisted through the full 4 weeks
The magnitude of blood-pressure reduction in the Kapil 2015 trial was comparable to a single antihypertensive medication and was achieved with a simple food intervention. The trial's authors described dietary nitrate as a possible affordable, readily available add-on treatment for high blood pressure.
The Siervo meta-analysis (2013) pooled 16 randomized crossover trials with 254 participants, each lasting between 2 hours and 15 days. The pooled estimate was a 4.4 mmHg reduction in systolic blood pressure with dietary nitrate (mostly from beetroot juice or supplements); the 1.1 mmHg diastolic reduction was not statistically significant (P = 0.06). A larger daily nitrate dose was associated with a larger fall in systolic pressure. Subsequent larger meta-analyses have confirmed the effect in both healthy normotensives (smaller effect, around 2–3 mmHg systolic) and treated hypertensives (larger effect, 4–7 mmHg systolic).
A 2022 meta-analysis limited to people with high blood pressure pooled 7 randomized trials with 218 participants, who drank 70–250 mL of beetroot juice a day for 3 to 60 days. Systolic pressure fell by 4.95 mmHg compared with control, while the 0.90 mmHg change in diastolic pressure was not statistically significant.
What is not yet known is how well the effect holds up over months. The trials in the Siervo meta-analysis lasted at most 15 days, and its authors called for long-term trials in people at higher heart risk. Not every trial finds a benefit: in a 2024 randomized crossover trial, 15 men and women aged 56 to 71 with treated high blood pressure drank about 400 mg of nitrate as beetroot juice twice a day for 4 weeks. Nitrate and nitrite rose in their blood and saliva, but 24-hour and home blood pressure and forearm blood flow did not differ from nitrate-depleted juice.
For context, a 5 mmHg reduction in systolic blood pressure across a population is associated with roughly a 10% reduction in stroke risk and a 7% reduction in coronary heart disease risk — clinically meaningful effects for an inexpensive food intervention.
Dosing — Juice, Concentrate, Powder, Whole Root
The effective dose of dietary nitrate for blood-pressure reduction is in the range of 5–8 mmol per day (approximately 310–500 mg of nitrate as NO3−). This can be achieved through several practical preparations:
- Fresh beetroot juice — 250 mL (about 8 oz) typically contains 5–8 mmol nitrate, depending on growing conditions and variety. The Kapil 2015 trial used 250 mL a day; the Webb 2008 trial used a single 500 mL dose. Effect onset is 2–3 hours after ingestion, peak at about 3 hours, duration roughly 24 hours.
- Concentrated beetroot juice ("beetroot shots") — commercial concentrated beetroot juice shots pack 5–8 mmol nitrate into 70 mL. These are the products most commonly used in athletic-endurance research.
- Beetroot powder — nitrate content varies enormously by processing method. Cold-processed dehydrated beet powder retains most of the nitrate; high-heat-processed or fermented beet powder may have very little. Some products list nitrate content per serving (typically 250–500 mg per serving for products in the effective range).
- Whole cooked beets — one large (200 g) cooked beet contains approximately 3–6 mmol nitrate. Two beets at one sitting reach the effective dose. Boiling reduces nitrate content slightly because nitrate leaches into cooking water; roasting preserves it.
- Beetroot greens — the leaves are actually higher in nitrate than the root by weight (roughly 200–300 mg per 100 g) but most people eat them in smaller quantities. Equivalent to spinach or arugula in nitrate density.
Timing matters for both blood-pressure and athletic-performance applications. Peak plasma nitrite (the active intermediate) is reached 2–3 hours after ingestion. For athletic use, this places the peak 2–3 hours after the juice is drunk. For sustained blood-pressure benefit, daily intake is more important than precise timing; once-daily morning or evening dosing works equally well.
The Antibacterial Mouthwash Trap
Reiterating from the microbiome section for emphasis: daily antibacterial mouthwash interferes with the step that activates dietary nitrate, and practitioners describe it as a common reason for "non-response" to beets taken for blood pressure. The bacterial nitrate-reduction step is genuinely essential to the entire pathway.
What the nitrate research describes about mouth care:
- Daily antibacterial mouthwash. Chlorhexidine, cetylpyridinium chloride and alcohol-containing antiseptic rinses all impair the nitrate-reducing flora; in the Bondonno trial, 3 days of an antibacterial mouthwash raised systolic pressure by 2.3 mmHg. Short courses after dental procedures are a separate, standard dental use.
- Mechanical hygiene. Brushing, flossing, and tongue scraping (gently) do not impair the relevant flora, which colonize biofilms deep in tongue papillae and tonsillar crypts.
- Non-antiseptic rinses. Salt water, baking soda water, or alcohol-free fluoride rinses do not harm the nitrate-reducing bacteria.
- Tongue scraping is debated. Light scraping is fine, but aggressive scraping that removes the bacterial biofilm from the posterior tongue surface may temporarily impair nitrate reduction.
The Proton-Pump-Inhibitor Trap
The second site of nitrite-to-NO reduction is the acidic stomach. When salivary nitrite reaches the stomach, gastric acid (pH 1–3 fasting) protonates nitrite to nitrous acid, which spontaneously decomposes to NO and other reactive nitrogen species. This is a non-enzymatic chemical reaction that depends critically on low gastric pH.
Proton pump inhibitors (omeprazole, esomeprazole, pantoprazole, lansoprazole) raise gastric pH to 4–6 or higher. At these less-acidic pHs, the nitrite-to-NO reduction in the stomach is markedly reduced, and the cardiovascular and antiplatelet effects of dietary nitrate are blunted (though not eliminated, because the systemic xanthine oxidoreductase / deoxyhemoglobin pathway still converts circulating nitrite to NO).
H2 blockers (ranitidine before its withdrawal, famotidine) have a smaller effect because they produce more modest pH elevation. Antacids taken occasionally do not meaningfully impair the pathway.
Proton pump inhibitors (PPIs) are often continued for years without periodic reassessment. For someone relying on dietary nitrate, long-term use means the acid-dependent stomach step described above is reduced; the other long-term proton pump inhibitor effects reported are lower calcium absorption, lower vitamin B12 absorption and changes in the gut microbiome.
How Beets Fit Into Hypertension Management
Beetroot juice produces blood-pressure reductions on the order of 4–7 mmHg systolic in mild hypertensives — comparable to a single low-dose antihypertensive medication. It does not replace pharmacotherapy in moderate or severe hypertension, but it is a useful adjunct in several specific scenarios:
- Stage 1 hypertension, lifestyle-management phase — patients with mild hypertension (SBP 130–139) who are using lifestyle interventions to delay or avoid medication. Daily beetroot juice plus the DASH diet, sodium restriction, regular aerobic exercise, weight loss, and stress reduction can collectively bring many patients back below the treatment threshold.
- Pre-hypertension — patients with SBP 120–129 who want to prevent progression. The blood-pressure reduction is more modest in this population (2–3 mmHg) but still meaningful at the population level.
- Treated hypertension, residual blood-pressure elevation — patients already on antihypertensive medication whose blood pressure remains above target. Adding daily beetroot juice can reduce blood pressure further without adding another medication. Half of the 68 patients in the Kapil 2015 trial were already taking blood-pressure medicines.
- Endothelial dysfunction without overt hypertension — patients with documented impaired flow-mediated dilation (e.g., diabetics, hypercholesterolemics, smokers). Dietary nitrate improves flow-mediated dilation through the same NO-mediated pathway.
- Athletic performance, secondary to blood-pressure benefit — endurance athletes who use beetroot juice for performance (see our athletic endurance deep dive) also get the cardiovascular benefit as a bonus.
The effect is not limited to juice shots. In the Danish Diet, Cancer, and Health Study of 53,150 adults followed for 23 years, people in the top fifth for vegetable nitrate intake (median 141 mg a day, from ordinary vegetables) had 2.58 mmHg lower systolic and 1.38 mmHg lower diastolic blood pressure at the start of the study than people in the bottom fifth. A moderate intake (median 59 mg a day, about the amount the authors equate with roughly 1 cup of green leafy vegetables) was linked to a 15% lower risk of cardiovascular disease than the lowest intake; this is an observational link, not proof of cause.
For more on hypertension management generally, see our Hypertension page.
Cautions, Oxalates, and Drug Interactions
- Beeturia (red urine) — about 10–14% of the population excretes intact betanin pigment in urine after beet ingestion, turning urine pink to dark red. This is a benign genetic variant unrelated to iron status (an older theory linked beeturia to iron deficiency; this has not held up in modern studies). Beeturia is harmless but can be alarming if mistaken for hematuria.
- Oxalates and kidney stones — beet root contains moderate oxalate (about 76 mg per 100 g), and beet greens are very high in oxalate (610 mg per 100 g). The oxalate load matters most for people with a history of calcium-oxalate kidney stones, and beet greens and concentrated beet supplements carry the most. Pairing beets with a calcium source (cheese, yogurt) at the same meal reduces oxalate absorption by precipitating calcium oxalate in the gut lumen.
- Combining with antihypertensive medication — the additive effect of beet juice with antihypertensives can produce excessive blood-pressure lowering in occasional patients, especially those on multiple agents. This additive effect is why blood pressure is tracked when daily beet juice is added to existing antihypertensive therapy.
- PDE5 inhibitors (sildenafil, tadalafil, vardenafil) — both work through the NO-cGMP pathway. Concurrent use can produce excessive vasodilation, hypotension, and dizziness. The concern raised is with high-dose beet supplements.
- Nitrate vasodilators (isosorbide mononitrate, nitroglycerin) — same downstream pathway. The same concern is raised for therapeutic-dose dietary nitrate taken with prescription nitrates.
- Pregnancy — beets in ordinary dietary amounts are a normal food. Concentrated beet supplements and beet powders have not been well-studied in pregnancy.
- Methemoglobinemia in infants — the classical concern with high-nitrate vegetables was infant methemoglobinemia from contaminated well water and pureed spinach/beets in young infants (under 6 months). This risk has been re-evaluated and is now considered minimal for healthy infants over 3 months. Conservative pediatric practice still avoids beets in infants under 3 months.
- Nitrate from vegetables vs cured meats — one of the most important distinctions in this field. Dietary nitrate from vegetables is consistently associated with improved cardiovascular outcomes. Nitrate and nitrite added to processed cured meats are associated with increased colorectal cancer risk, likely because of co-formation of N-nitroso compounds with meat-derived amines. The same compound has opposite associations depending on the food matrix.
Key Research Papers
- Webb AJ et al. (2008). Acute blood pressure lowering, vasoprotective, and antiplatelet properties of dietary nitrate via bioconversion to nitrite. Hypertension 51:784-790. — PubMed PMID: 18250365
- Kapil V, Khambata RS, Robertson A, Caulfield MJ, Ahluwalia A (2015). Dietary nitrate provides sustained blood pressure lowering in hypertensive patients: a randomized, phase 2, double-blind, placebo-controlled study. Hypertension 65:320-327. — PubMed PMID: 25421976
- Siervo M et al. (2013). Inorganic nitrate and beetroot juice supplementation reduces blood pressure in adults: a systematic review and meta-analysis. Journal of Nutrition 143:818-826. — PubMed PMID: 23596162
- Bondonno CP, Liu AH, Croft KD, Considine MJ, Puddey IB, Woodman RJ, Hodgson JM (2015). Antibacterial mouthwash blunts oral nitrate reduction and increases blood pressure in treated hypertensive men and women. American Journal of Hypertension 28(5):572-575. — PubMed PMID: 25359409
- Lundberg JO, Weitzberg E, Gladwin MT (2008). The nitrate-nitrite-nitric oxide pathway in physiology and therapeutics. Nature Reviews Drug Discovery 7:156-167. — PubMed PMID: 18167491
- Larsen FJ, Ekblom B, Sahlin K, Lundberg JO, Weitzberg E (2006). Effects of dietary nitrate on blood pressure in healthy volunteers. NEJM 355(26):2792-2793. — PubMed PMID: 17192551
- Hyde ER et al. (2014). Metagenomic analysis of nitrate-reducing bacteria in the oral cavity: implications for nitric oxide homeostasis. PLoS ONE 9:e88645. — PubMed PMID: 24670812
- Bondonno CP, Dalgaard F, Blekkenhorst LC, Murray K, Lewis JR, Croft KD, et al. (2021). Vegetable nitrate intake, blood pressure and incident cardiovascular disease: Danish Diet, Cancer, and Health Study. European Journal of Epidemiology 36(8):813-825. — PubMed PMID: 33884541
- Hobbs DA, Goulding MG, Nguyen A, Malaver T, Walker CF, George TW, Methven L, Lovegrove JA (2013). Acute ingestion of beetroot bread increases endothelium-independent vasodilation and lowers diastolic blood pressure in healthy men: a randomized controlled trial. Journal of Nutrition 143(9):1399-1405. — PubMed PMID: 23884387
- Velmurugan S et al. (2016). Dietary nitrate improves vascular function in patients with hypercholesterolemia: a randomized, double-blind, placebo-controlled study. American Journal of Clinical Nutrition 103:25-38. — PubMed PMID: 26607938
- Coles LT, Clifton PM (2012). Effect of beetroot juice on lowering blood pressure in free-living, disease-free adults: a randomized, placebo-controlled trial. Nutrition Journal 11:106. — PubMed PMID: 23231777
- Benjamim CJR, Porto AA, Valenti VE, Sobrinho ACDS, Garner DM, Gualano B, Bueno Júnior CR (2022). Nitrate Derived From Beetroot Juice Lowers Blood Pressure in Patients With Arterial Hypertension: A Systematic Review and Meta-Analysis. Frontiers in Nutrition 9:823039. — PubMed PMID: 35369064
- Fejes R, Lutnik M, Weisshaar S, Pilat N, Wagner KH, Stüger HP, et al. (2024). Increased nitrate intake from beetroot juice over 4 weeks affects nitrate metabolism, but not vascular function or blood pressure in older adults with hypertension. Food & Function 15(8):4065-4078. — PubMed PMID: 38546454
- Singh B, North P, Rushetsky ZM, Brito RC, Jenney FE (2026). The effect of antibacterial mouthwash on blood pressure in humans: a scoping review. BMC Cardiovascular Disorders 26(1). — PubMed PMID: 42754848