Chest Pain

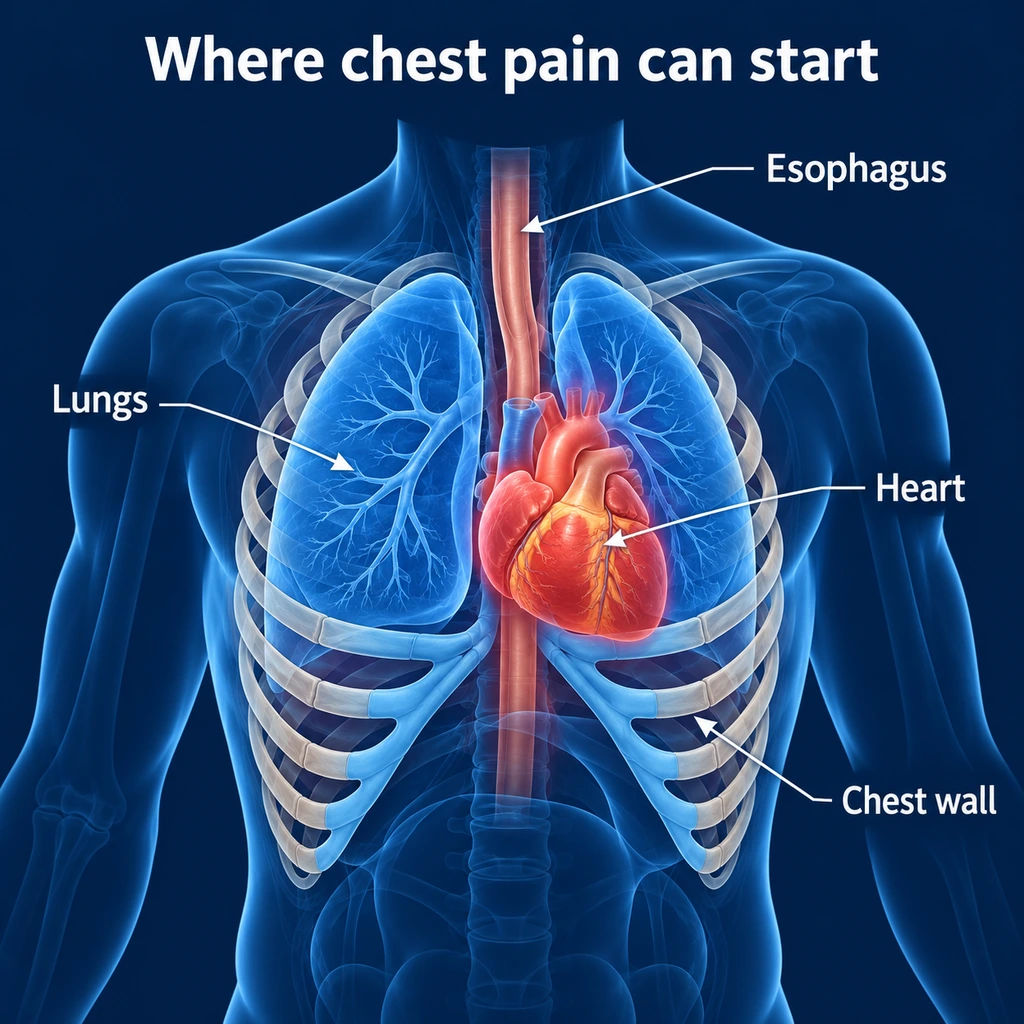
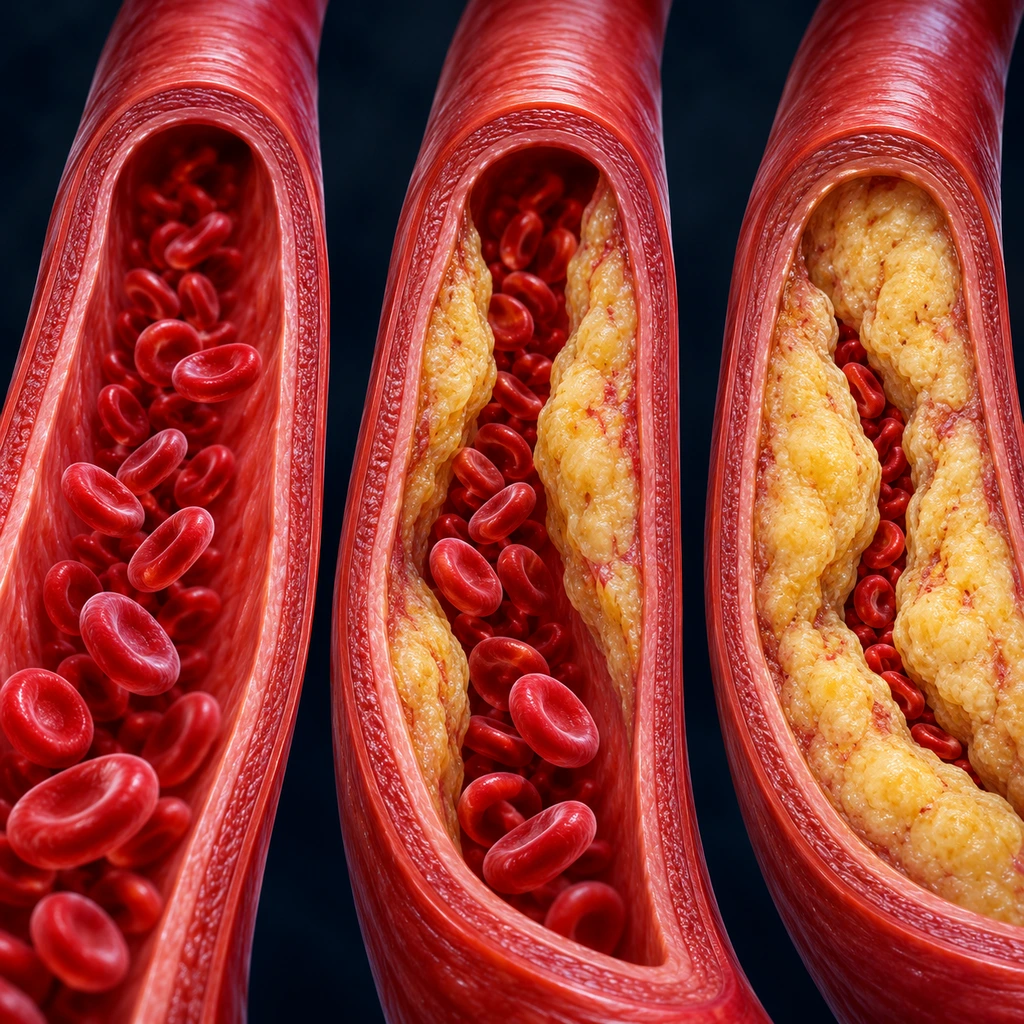
Table of Contents
Overview
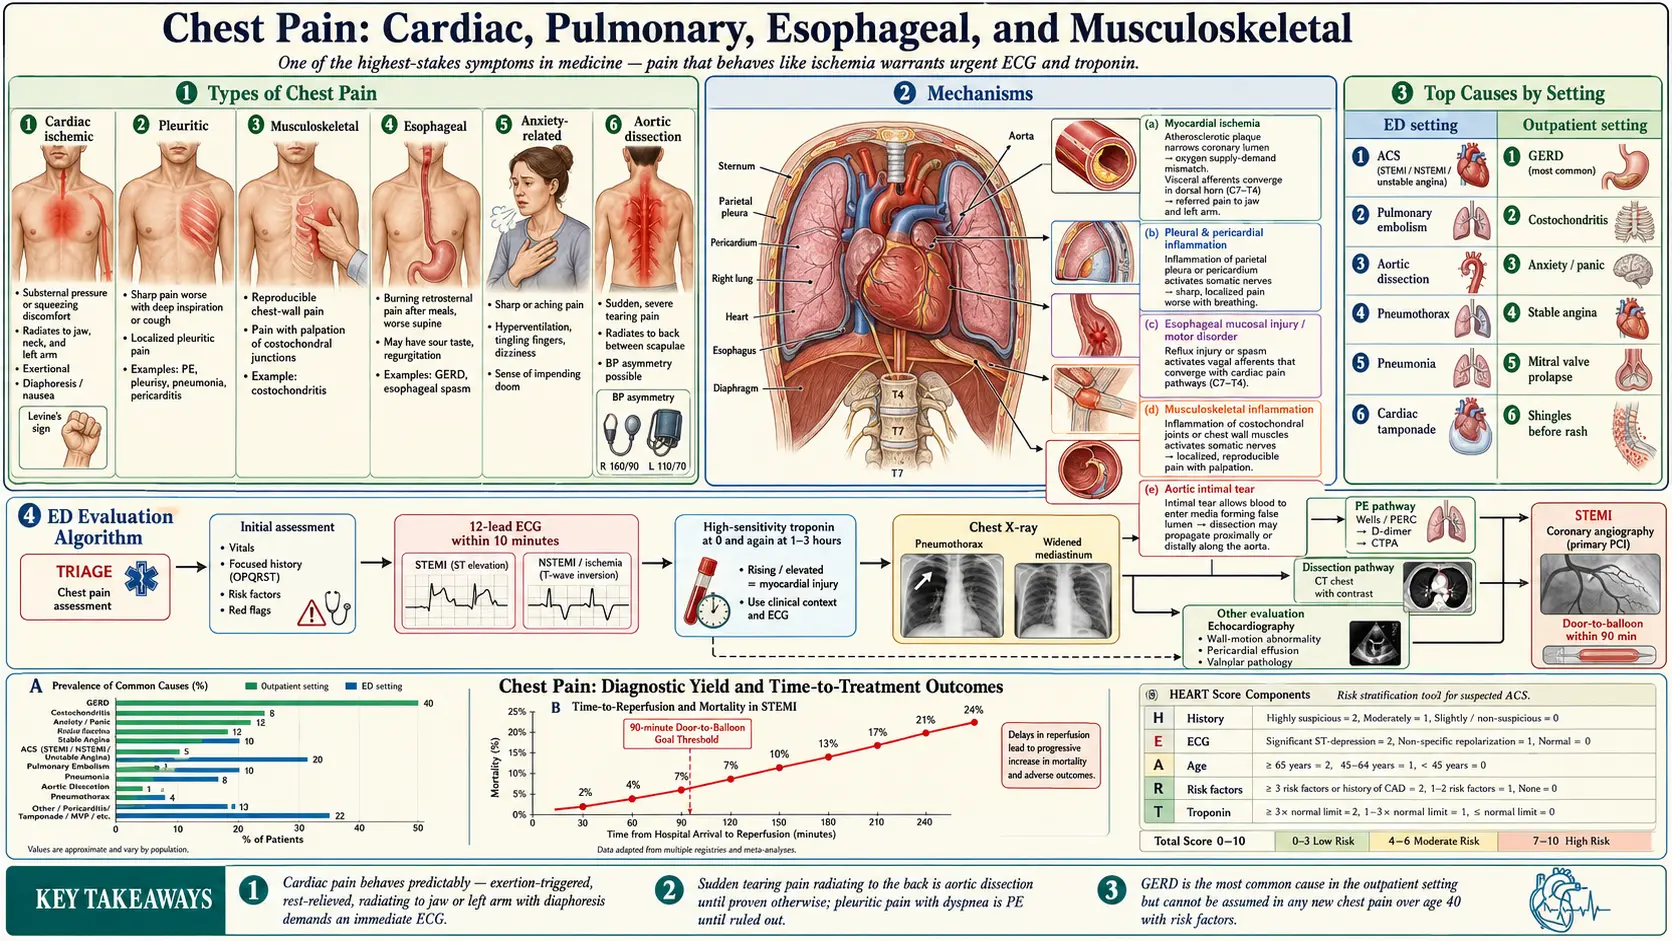
Chest pain is one of the most common reasons for emergency-department visits and one of the highest-stakes symptoms in medicine, because the same complaint can mean a harmless muscle strain or a heart attack. Most chest pain is benign — muscle strain, anxiety, or reflux — but a meaningful minority signals an acute coronary syndrome, pulmonary embolism, aortic dissection, or other life threat. In primary care, a review of 11 studies (about 6,500 patients) found an acute coronary syndrome or heart attack in 1.5–3.6% and any cardiovascular disease in 13.8–16.1%. Among patients in emergency departments, about 10% turn out to have an acute coronary syndrome. The clinically useful distinction is not what chest pain feels like (cardiac pain is famously variable) but how it behaves: pain that comes on with exertion and resolves with rest, with sweating (diaphoresis) or radiation to the jaw or left arm, in someone with cardiovascular risk factors, deserves urgent evaluation regardless of the descriptor.
Types of Chest Pain
- Cardiac ischemic pain (angina, myocardial infarction) — pressure or tightness, often substernal, with radiation to jaw, neck, or left arm; provoked by exertion or stress; relieved (at first) by rest or nitroglycerin. Relief from nitroglycerin does not separate heart pain from other pain: among 459 emergency patients, it relieved pain in 35% of those with active coronary disease and 41% of those without, and the authors state it “should not be used to guide diagnosis.”
- Pleuritic pain — sharp, worse with deep breath or cough; suggests pulmonary embolism, pleurisy, pneumonia, pericarditis.
- Musculoskeletal pain — reproducible with palpation or movement; costochondritis, rib injury, muscle strain.
- Esophageal pain — burning, often after meals or lying down; may be indistinguishable from cardiac pain.
- Anxiety-related pain — sharp or aching, often with hyperventilation, tingling (paresthesias), panic; often resolves with breathing slowing.
- Aortic dissection pain — tearing, ripping pain that radiates to the back; sudden onset; surgical emergency.
Common Causes
- Coronary artery disease and acute coronary syndromes — stable angina, unstable angina, non-ST-elevation myocardial infarction (NSTEMI), ST-elevation myocardial infarction (STEMI).
- Heart failure and cardiomyopathy — chest discomfort with shortness of breath, exercise intolerance.
- Pericarditis and myocarditis — sharp pleuritic chest pain, worse lying flat (supine), better leaning forward.
- Aortic dissection — sudden tearing pain, blood-pressure asymmetry between arms; surgical emergency.
- Pulmonary embolism — pleuritic chest pain, shortness of breath (dyspnea), fast heart rate (tachycardia), possible coughing up blood (hemoptysis).
- Pneumothorax — sudden unilateral pleuritic pain with dyspnea.
- Pneumonia and pleurisy — pleuritic pain with fever, cough, abnormal lung exam.
- Gastroesophageal reflux disease (GERD) and esophageal spasm — burning chest pain, especially after meals or lying flat; common in the outpatient setting. Primary care studies put the chest wall first: a review of 11 studies found chest wall syndrome in 24.5–49.8%, esophageal disorders in 6.0–7.1% and gastrointestinal disorders in 5.6–9.7%. A Swiss series of 672 patients found musculoskeletal pain in 49% and digestive causes in 8%, with unstable angina, heart attack and pulmonary embolism uncommon (1.8%).
- Costochondritis and Tietze syndrome — reproducible chest-wall tenderness; benign.
- Panic and anxiety — chest tightness with hyperventilation and tingling.
- Mitral valve prolapse — common, usually benign source of palpitations and atypical chest pain.
- Herpes zoster (shingles) before rash — unilateral dermatomal pain.
Mechanisms
- Myocardial ischemia — oxygen demand exceeds supply because of obstructive coronary disease or coronary vasospasm; visceral afferents converge with somatic dermatomes, producing referred pain to jaw, neck, and arm.
- Pleural and pericardial inflammation — sensitive parietal surfaces produce sharp, position- and breath-dependent pain.
- Esophageal mucosal injury and motor disorders — acid exposure or spasm activates vagal and spinal afferents that share central pathways with cardiac afferents, explaining clinical overlap.
- Musculoskeletal inflammation or strain — well-localized somatic pain, reproducible with palpation.
- Aortic intimal tear — abrupt, severe, tearing pain from dissection plane propagation.
Evaluation
- History — onset, character, radiation, provoking and relieving factors, associated symptoms (shortness of breath, sweating, fainting (syncope)), risk factors (age, smoking, diabetes, family history), recent surgery or immobility (risk of pulmonary embolism).
- 12-lead electrocardiogram (ECG) — first test in any concerning chest pain; repeat if pain changes.
- High-sensitivity troponin — serial measurements at presentation and 1–3 hours; cornerstone of myocardial infarction (MI) diagnosis.
- Chest X-ray — rule out pneumothorax, pneumonia, widened mediastinum (dissection).
- D-dimer plus computed tomography (CT) pulmonary angiogram — if pulmonary embolism is suspected by the Wells score or the Pulmonary Embolism Rule-out Criteria (PERC).
- Computed tomography chest with contrast — if aortic dissection is suspected.
- Echocardiogram — for wall-motion abnormalities, pericardial effusion, valvular disease.
- Stress testing or coronary computed tomography angiography — for stable, intermediate-risk chest pain in the outpatient setting.
- Coronary angiography — gold standard for high-risk presentations; emergent for ST-elevation myocardial infarction.
- Esophageal evaluation — if non-cardiac chest pain persists; pH-impedance, manometry, upper endoscopy.
Single symptoms are weak guides. A review of 58 emergency department studies found that the findings most suggestive of an acute coronary syndrome raised the odds only modestly: a prior abnormal stress test (likelihood ratio 3.1), peripheral arterial disease (2.7) and pain into both arms (2.6). A low score of 0–3 on the History, Electrocardiogram, Age, Risk factors, Troponin (HEART) score lowered the odds (likelihood ratio 0.20). The review concluded that history, examination and electrocardiogram alone did not confirm or exclude the diagnosis.
Management
This list predates the 2023 European Society of Cardiology and 2025 American College of Cardiology/American Heart Association guidelines on acute coronary syndromes and is a general outline of long-standing practice. A 2026 review reports that the 2025 guideline brings both kinds of heart attack into one framework and prefers ticagrelor or prasugrel to clopidogrel when an artery is opened with a stent or balloon.
- ST-elevation myocardial infarction — immediate primary percutaneous coronary intervention (PCI, opening the blocked artery with a balloon or stent) within 90 minutes of first medical contact; aspirin, a P2Y12 inhibitor (a second drug that stops platelets clumping), anticoagulation, beta-blocker, statin.
- Non-ST-elevation myocardial infarction / unstable angina — aspirin, P2Y12 inhibitor, anticoagulation, early invasive strategy in high-risk patients.
- Stable angina — lifestyle (smoking cessation, exercise, Mediterranean diet), statin, antiplatelet, beta-blocker, nitrates as needed; revascularization for refractory or anatomically high-risk disease.
- Pulmonary embolism — anticoagulation; thrombolytics or thrombectomy in massive or sub-massive pulmonary embolism.
- Aortic dissection — immediate surgical repair (Type A) or aggressive blood-pressure control (Type B).
- Gastroesophageal reflux disease — proton pump inhibitor (PPI), lifestyle measures, weight loss; fundoplication surgery is used when symptoms do not respond.
- Costochondritis — nonsteroidal anti-inflammatory drugs (NSAIDs), reassurance, rest.
- Anxiety / panic disorder — cognitive behavioral therapy (CBT), selective serotonin reuptake inhibitors (SSRIs), breathing retraining.
Beta-blockers after a heart attack. Routine use is being rethought. Pooling five open-label trials and 17,801 patients with a normal heart pumping measure (ejection fraction of at least 50%) and no other reason for the drug, death, a new heart attack or heart failure occurred in 8.1% with a beta-blocker and 8.3% without (hazard ratio 0.97), with no difference in death.
Pulmonary embolism. The first American Heart Association/American College of Cardiology guideline on acute pulmonary embolism was released on February 19, 2026. A 2026 open-label trial of 558 intermediate-high-risk patients added the clot-busting drug alteplase, given through a catheter, to blood thinners. Death, recurrence or collapse within 7 days occurred in 0.7% vs 6.8%, driven mainly by less collapse. Major bleeding was 1.4% vs 2.2%, and bleeding inside the head occurred in 2 vs 0 patients.
When to Seek Medical Care
- Crushing, squeezing, or pressure-like chest pain — especially with shortness of breath, sweating, nausea, or radiation to jaw, neck, or left arm. Call 911.
- Sudden severe tearing pain radiating to the back, particularly with hypertension or known aneurysm.
- Chest pain with sudden severe dyspnea, low oxygen saturation, or unilateral leg swelling (a pattern seen with pulmonary embolism).
- Loss of consciousness or near-fainting during chest pain.
- Chest pain in a patient with known coronary disease that is more frequent, more severe, or occurring at rest.
- Pleuritic chest pain with fever, productive cough, or recent surgery.
- Any new chest pain in a patient over 40 with cardiovascular risk factors that has not been previously evaluated.
Connections
- All Symptoms
- Pulmonary Embolism
- Anxiety
- Cardiomyopathy
- Coronary Artery Disease
- Heart Failure
- Pneumonia
- Gastroesophageal Reflux Disease
- Shortness of Breath
- Hypertension
- Heart Palpitations
- Myocarditis
- Arrhythmia
- Reflux
- Inflammatory Markers
- Cardiovascular Disease
- Sickle Cell Disease
- Tuberculosis
- Dizziness
- Shoulder Pain
Key Research Papers
Historical Background
The systematic study of chest pain dates to William Heberden's 1768 description of "angina pectoris." The 20th century brought the electrocardiogram (Einthoven, 1903), troponin assays in the 1990s, and the concept of door-to-balloon time in primary percutaneous coronary intervention. The 2021 AHA/ACC chest pain guideline replaced "atypical/typical" terminology with risk-stratified pathways, recognizing that women, the elderly, and diabetics often present with non-classic ischemic symptoms.
Key Research Papers
- Gulati M, Levy PD, Mukherjee D, et al. 2021 AHA/ACC/ASE/CHEST/SAEM/SCCT/SCMR guideline for the evaluation and diagnosis of chest pain. Circulation. 2021;144(22):e368-e454. — doi:10.1161/CIR.0000000000001029
- Reichlin T, Hochholzer W, Bassetti S, et al. Early diagnosis of myocardial infarction with sensitive cardiac troponin assays. New England Journal of Medicine. 2009;361(9):858-867. — PubMed PMID: 19710484
- Lee TH, Goldman L. Evaluation of the patient with acute chest pain. New England Journal of Medicine. 2000;342(16):1187-1195. — doi:10.1056/nejm200004203421607
- Collet JP, Thiele H, Barbato E, et al. 2020 ESC guidelines for the management of acute coronary syndromes in patients presenting without persistent ST-segment elevation. European Heart Journal. 2021;42(14):1289-1367. — doi:10.1093/eurheartj/ehaa575
- Konstantinides SV, Meyer G, Becattini C, et al. 2019 ESC guidelines for the diagnosis and management of acute pulmonary embolism. European Heart Journal. 2020;41(4):543-603. — doi:10.1093/eurheartj/ehz405
- Fanaroff AC, Rymer JA, Goldstein SA, Simel DL, Newby LK. Does this patient with chest pain have acute coronary syndrome? JAMA. 2015;314(18):1955-1965. — doi:10.1001/jama.2015.12735
- Hiratzka LF, Bakris GL, Beckman JA, et al. 2010 ACCF/AHA/AATS guidelines for the diagnosis and management of patients with thoracic aortic disease. Circulation. 2010;121(13):e266-e369. — doi:10.1161/CIR.0b013e3181d4739e
- Isselbacher EM, Preventza O, Hamilton Black J III, et al. 2022 ACC/AHA Guideline for the Diagnosis and Management of Aortic Disease. Journal of the American College of Cardiology. 2022;80(24):e223-e393. — PubMed PMID: 36334952
- Konstantinides SV, Vicaut E, Danays T, et al. Impact of Thrombolytic Therapy on the Long-Term Outcome of Intermediate-Risk Pulmonary Embolism. Journal of the American College of Cardiology. 2017;69(12):1536-1544. — PubMed PMID: 28335835
- Drossman DA. Functional gastrointestinal disorders: history, pathophysiology, clinical features, and Rome IV. Gastroenterology. 2016;150(6):1262-1279. — doi:10.1053/j.gastro.2016.02.032
- Bhatt DL, Lopes RD, Harrington RA. Diagnosis and treatment of acute coronary syndromes: a review. JAMA. 2022;327(7):662-675. — doi:10.1001/jama.2022.0358
- Haasenritter J, Biroga T, Keunecke C, et al. Causes of chest pain in primary care--a systematic review and meta-analysis. Croat Med J. 2015;56(5):422-430. — PubMed PMID: 26526879
- Verdon F, Herzig L, Burnand B, et al. Chest pain in daily practice: occurrence, causes and management. Swiss Med Wkly. 2008;138(23-24):340-347. — PubMed PMID: 18561039
- Henrikson CA, Howell EE, Bush DE, et al. Chest pain relief by nitroglycerin does not predict active coronary artery disease. Ann Intern Med. 2003;139(12):979-986. — PubMed PMID: 14678917
- Byrne RA, Rossello X, Coughlan JJ, et al. 2023 ESC Guidelines for the management of acute coronary syndromes. Eur Heart J Acute Cardiovasc Care. 2024;13(1):55-161. — PubMed PMID: 37740496
- Restrepo VJ, Rao SV. Known Unknowns: Unpacking Controversies and Uncertainties in the 2025 Guidelines for Management of Acute Coronary Syndromes. Curr Cardiol Rep. 2026;28(1):105. — PubMed PMID: 42832065
- Kristensen AMD, Rossello X, Atar D, et al. Beta-Blockers after Myocardial Infarction with Normal Ejection Fraction. N Engl J Med. 2026;394(6):540-550. — PubMed PMID: 41211954
- Patel N. 2026 AHA/ACC guideline for the evaluation and management of acute pulmonary embolism in adults. J Hosp Med. 2026. — PubMed PMID: 42693678
- Kroupa J, Radvan M, Mrozek J, et al. Catheter-Directed Thrombolysis in Intermediate-High-Risk Pulmonary Embolism. N Engl J Med. 2026. — PubMed PMID: 42678032
PubMed Topic Searches
Featured Videos