Eating Disorders
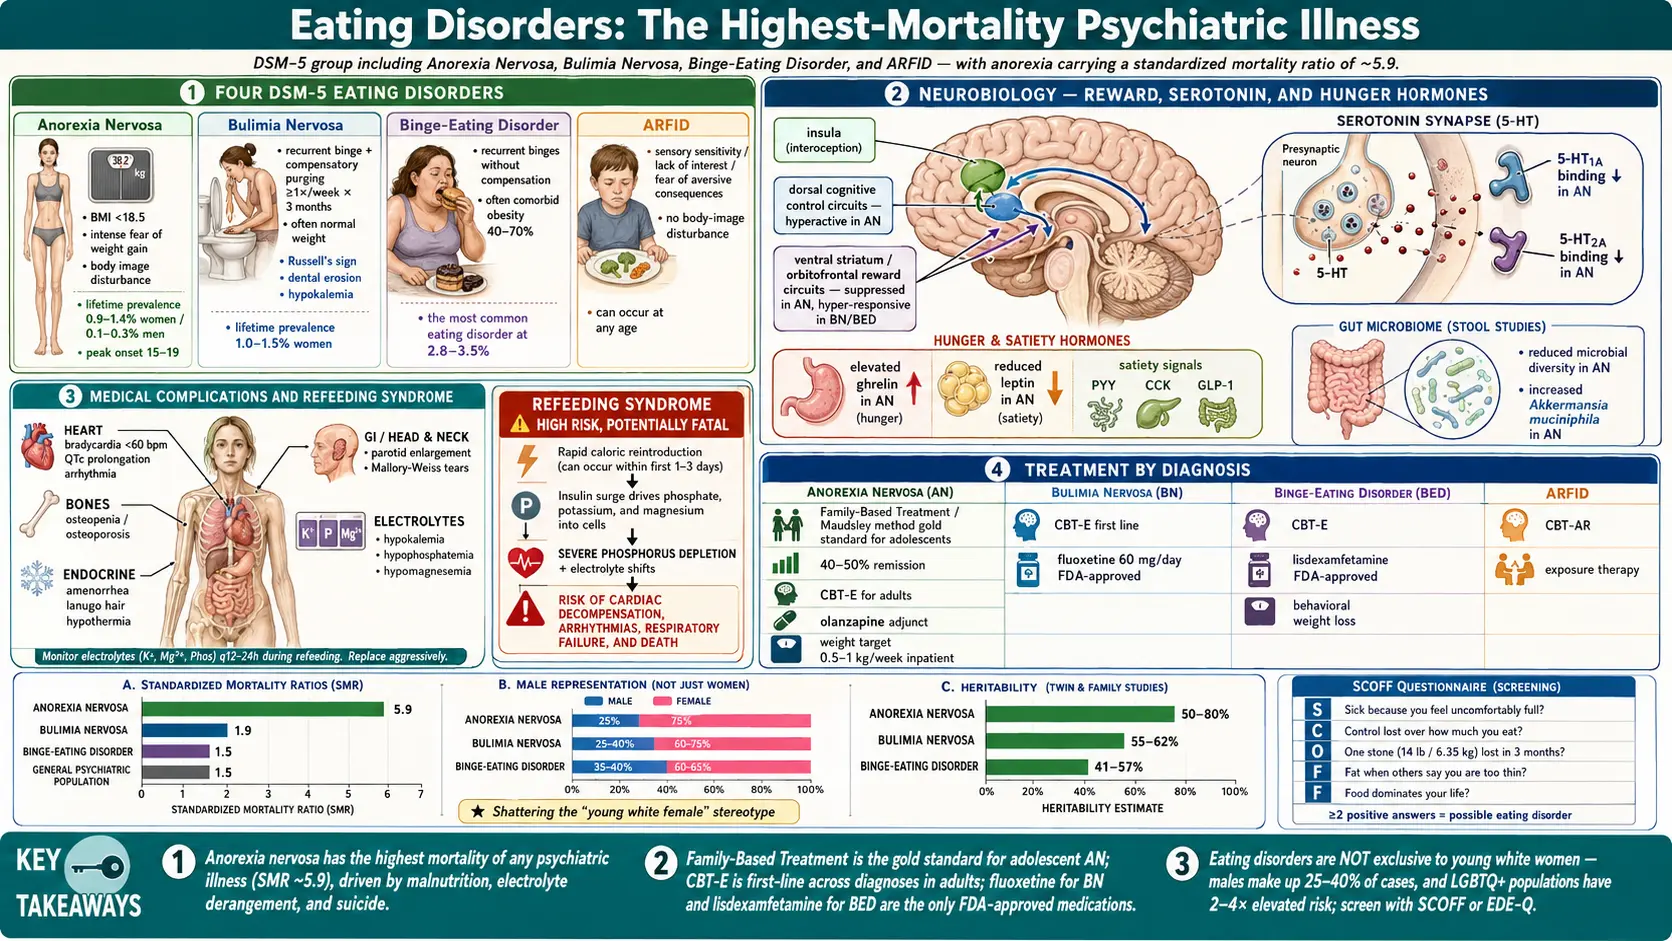
Table of Contents
1. Overview
Eating disorders are a group of serious psychiatric conditions characterized by persistent disturbances in eating behavior and the associated distressing thoughts and emotions. The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) recognizes several distinct eating disorder diagnoses, the most prominent being Anorexia Nervosa (AN), Bulimia Nervosa (BN), Binge-Eating Disorder (BED), Avoidant/Restrictive Food Intake Disorder (ARFID), Pica, and Rumination Disorder. These conditions involve complex interactions between psychological, biological, and sociocultural factors, resulting in behaviors that severely compromise physical health, psychosocial functioning, and quality of life.
Eating disorders carry the highest mortality rate of any psychiatric illness. Anorexia nervosa has a standardized mortality ratio (SMR) of approximately 5.9, meaning affected individuals are nearly six times more likely to die prematurely compared to the general population. Deaths result from medical complications of malnutrition, purging behaviors, and suicide. Despite their severity, eating disorders remain significantly underdiagnosed and undertreated, with only approximately 20-30% of affected individuals receiving adequate treatment.
The DSM-5 (2013) brought significant changes to eating disorder classification, including the addition of Binge-Eating Disorder as a formal diagnosis (previously in the appendix), the removal of the amenorrhea criterion for anorexia nervosa, the reduction of binge/purge frequency threshold for bulimia nervosa from twice to once per week, and the introduction of ARFID as a new diagnosis replacing the childhood-limited "feeding disorder of infancy and early childhood." These changes improved diagnostic sensitivity and better captured the full spectrum of eating pathology.
2. Epidemiology
Anorexia Nervosa has a lifetime prevalence of approximately 0.9-1.4% in women and 0.1-0.3% in men. Peak age of onset is 15-19 years. AN is more common in industrialized countries and among Caucasian populations, though recent evidence suggests it occurs across all racial and ethnic groups. Incidence has remained relatively stable over the past several decades.
Bulimia Nervosa has a lifetime prevalence of approximately 1.0-1.5% in women and 0.1-0.5% in men. Mean age of onset is 18-21 years. BN incidence peaked in the 1980s-1990s and has subsequently declined in some Western countries, possibly reflecting a shift toward binge-eating disorder diagnoses.
Binge-Eating Disorder is the most common eating disorder, with a lifetime prevalence of 3.5% in women and 2.0% in men in the United States National Comorbidity Survey Replication (Hudson and colleagues, 2007). The gender ratio is more balanced than for AN or BN. Mean age of onset is 21-25 years, and BED is significantly more prevalent among individuals seeking obesity treatment (30-50%).
The World Health Organization World Mental Health Surveys (24,124 adults in 14 countries, 2013) found binge-eating disorder more common than bulimia nervosa (median lifetime prevalence 1.4% vs 0.8%). Binge-eating disorder lasted a median of about 4 years (bulimia about 6.5 years), and fewer than half of the people who had either disorder in their lifetime ever received treatment.
Eating disorders are increasingly recognized in males (accounting for approximately 25% of AN cases, 25-40% of BN cases, and 35-40% of BED cases), LGBTQ+ populations (2-4 fold elevated risk), athletes (particularly in aesthetic and weight-class sports), and across all racial and ethnic groups. The misconception that eating disorders primarily affect young, White, affluent women continues to contribute to diagnostic disparities.
3. Pathophysiology
Neurotransmitter Systems
Serotonergic dysfunction plays a central role in eating disorder pathophysiology. Individuals with AN show elevated 5-HT1A receptor binding and reduced 5-HT2A receptor binding in cortical regions, patterns that persist after weight restoration and may represent trait markers. Serotonin dysregulation contributes to the characteristic anxiety, perfectionism, obsessionality, and harm avoidance seen in AN. In BN, altered serotonergic function is linked to impulsivity and impaired satiety signaling. Dopaminergic dysfunction is also implicated, with AN patients showing altered striatal dopamine release contributing to anhedonia, aberrant reward processing, and paradoxical reward from starvation. BED is associated with reduced striatal dopamine D2 receptor availability, resembling patterns seen in substance addiction.
Appetite and Energy Homeostasis
Eating disorders involve profound disruption of the hormonal systems regulating hunger, satiety, and energy balance. In AN, ghrelin (the "hunger hormone") is paradoxically elevated while leptin (the satiety hormone) is markedly reduced, reflecting the body's attempt to counteract energy deficit. Peptide YY, cholecystokinin, and glucagon-like peptide-1 (GLP-1) (satiety signals) show variable alterations. These hormonal changes contribute to the peculiar absence of hunger drive in chronic AN despite severe caloric restriction. In BED, impaired postprandial satiety signaling and blunted ghrelin suppression after eating may contribute to binge episodes.
Brain Structure and Function
Neuroimaging reveals characteristic patterns across eating disorders. AN is associated with global gray matter volume reduction (partially reversible with weight restoration), altered insula function (interoceptive processing), and hyperactive dorsal cognitive control circuits with reduced ventral reward circuits, consistent with the ability to override hunger signals. BN and BED show impaired prefrontal inhibitory control and enhanced reward region activation to food cues, particularly in the ventral striatum and orbitofrontal cortex, paralleling neural patterns in addiction. Default mode network alterations across eating disorders correlate with body image disturbance and self-referential processing abnormalities.
Gut Microbiome
Emerging research demonstrates significant gut microbiome alterations in eating disorders. AN patients show reduced microbial diversity, increased representation of mucin-degrading bacteria (e.g., Akkermansia muciniphila), and altered short-chain fatty acid production. These changes may influence mood, appetite regulation, and immune function through the gut-brain axis. Microbiome composition partially normalizes with weight restoration but may not fully recover, potentially contributing to relapse vulnerability.
4. Etiology and Risk Factors
Genetic Factors
- Heritability estimated at 50-80% for AN, 55-62% for BN, and 39-57% for BED (a 2022 review of twin and family studies)
- Genome-wide association studies (GWAS) have identified 8 genome-wide significant loci for AN, including associations near genes involved in metabolism, lipid biology, and physical activity
- AN shows significant positive genetic correlations with obsessive-compulsive disorder (OCD), major depression, anxiety, and schizophrenia, and negative genetic correlations with body mass index (BMI), obesity, and type 2 diabetes — suggesting metabolic factors are intrinsic to the disorder
- First-degree relatives of AN probands have a 10-12 fold increased risk
Psychological Factors
- Perfectionism — one of the most robust personality risk factors, particularly for AN
- Low self-esteem and negative self-evaluation
- Cognitive rigidity and detail-focused processing style (weak central coherence)
- Interoceptive deficits — difficulty identifying and responding to internal body signals
- Emotion regulation difficulties — bingeing and purging often function as maladaptive emotion regulation strategies
- Body dissatisfaction — a consistent and potent risk factor across eating disorders
Sociocultural Factors
- Thin ideal internalization — media-promoted beauty standards emphasizing thinness
- Social media exposure — appearance-focused content, fitspiration, pro-eating disorder communities
- Dieting behavior — restrictive dieting is a significant proximal risk factor for all eating disorders
- Weight stigma and fat phobia — societal discrimination based on body weight
- Athletic and professional pressures — sports emphasizing leanness (gymnastics, ballet, wrestling, distance running)
- Peer influences — weight-related teasing, social comparison, peer dieting behaviors
Trauma and Adversity
- Childhood sexual abuse — associated with approximately 3-fold increased risk of developing an eating disorder
- Physical and emotional abuse
- Bullying, particularly weight-related bullying
- Adverse childhood experiences (ACEs) — dose-response relationship with eating disorder risk
5. Clinical Presentation
Anorexia Nervosa
Restricting type: weight loss achieved primarily through dieting, fasting, and/or excessive exercise. Binge-eating/purging type: recurrent episodes of bingeing and/or purging (self-induced vomiting, laxative misuse). Clinical features include:
- Significantly low body weight (body mass index <18.5 kg/m2 in adults; below expected growth trajectory in children/adolescents)
- Intense fear of gaining weight or persistent behavior interfering with weight gain
- Body image disturbance — distorted perception of body size and shape; undue influence of weight on self-evaluation; denial of seriousness of low weight
- Physical signs: lanugo hair, acrocyanosis, bradycardia (heart rate <60 bpm), hypotension, hypothermia, edema, dry skin, hair loss, parotid gland enlargement (in purging subtype)
- Medical consequences: amenorrhea, osteoporosis, cardiac arrhythmias (a lengthened corrected QT interval (QTc) on the heart tracing), renal impairment, hepatic dysfunction, pancytopenia
Bulimia Nervosa
- Recurrent binge eating episodes — eating an objectively large amount of food with a sense of loss of control, occurring at least once per week for 3 months
- Compensatory behaviors — self-induced vomiting (80-90% of cases), laxative abuse (approximately 60%), diuretic misuse, fasting, excessive exercise
- Self-evaluation unduly influenced by body shape and weight
- Often normal weight or slightly overweight
- Physical signs: Russell's sign (calluses on knuckles from induced vomiting), dental erosion (perimolysis), parotid enlargement (chipmunk facies), Mallory-Weiss tears
- Electrolyte disturbances: hypokalemia (most dangerous), metabolic alkalosis from vomiting, metabolic acidosis from laxative abuse
Binge-Eating Disorder
- Recurrent binge eating episodes (at least once per week for 3 months) characterized by eating rapidly, eating until uncomfortably full, eating large amounts when not hungry, eating alone due to embarrassment, feeling disgusted/depressed/guilty afterward
- Marked distress regarding binge eating
- Absence of regular compensatory behaviors (distinguishing BED from BN)
- Strong association with obesity — in the World Health Organization World Mental Health Surveys (community samples in 14 countries), 32.8-41.7% of people with BED or bulimia nervosa were obese, against 15.8% of people with no eating disorder
- Binge episodes are often triggered by negative emotions, interpersonal stress, dietary restriction, or boredom
ARFID (Avoidant/Restrictive Food Intake Disorder)
- Significant failure to meet nutritional needs not explained by lack of food availability, cultural practice, or another medical/psychiatric condition
- No body image disturbance or fear of weight gain (distinguishing from AN)
- Three common presentations: sensory sensitivity (avoidance based on taste, texture, smell), lack of interest in eating, and concern about aversive consequences of eating (choking, vomiting, pain)
- Can occur at any age; increasingly recognized in adults
6. Diagnosis
DSM-5 Diagnostic Criteria for Anorexia Nervosa
- A: Restriction of energy intake relative to requirements, leading to significantly low body weight
- B: Intense fear of gaining weight or becoming fat, or persistent behavior that interferes with weight gain
- C: Disturbance in the way body weight or shape is experienced, undue influence of weight on self-evaluation, or persistent lack of recognition of the seriousness of low body weight
- Subtypes: Restricting type vs. Binge-eating/Purging type
- Severity based on body mass index: Mild (≥17), Moderate (16-16.99), Severe (15-15.99), Extreme (<15)
Screening Tools
- SCOFF Questionnaire — 5-item screen (Sick, Control, One stone, Fat, Food); score ≥2 indicates probable eating disorder; sensitivity 78-100%, specificity 72-90%
- Eating Disorder Examination Questionnaire (EDE-Q) — 28-item self-report; global score ≥4.0 suggests clinical significance
- Eating Disorder Examination (EDE) — gold standard semi-structured clinical interview; 36 items across 4 subscales (restraint, eating concern, shape concern, weight concern)
- Eating Attitudes Test (EAT-26) — 26-item self-report; widely used for screening; score ≥20 indicates significant eating pathology
Medical Evaluation
A medical assessment usually includes:
- Basic metabolic panel — electrolytes (especially potassium, sodium, phosphorus, magnesium), glucose, renal function
- Complete blood count — leukopenia, anemia, thrombocytopenia in severe AN
- Thyroid function tests — sick euthyroid syndrome common in AN
- Electrocardiogram — QTc prolongation, bradycardia, ST-T wave changes
- Dual-energy X-ray absorptiometry (DEXA) scan — bone mineral density assessment (osteopenia/osteoporosis in AN)
- Liver function tests, amylase/lipase, phosphorus levels
7. Treatment
Treatment of Anorexia Nervosa
Nutritional rehabilitation and weight restoration are the foundation of AN treatment. Target weight gain of 0.5-1.0 kg/week for inpatient and 0.25-0.5 kg/week for outpatient settings. Monitoring for refeeding syndrome is critical during early weight restoration — characterized by hypophosphatemia, hypokalemia, hypomagnesemia, fluid shifts, and cardiac complications. Phosphorus supplementation is routinely provided.
Psychotherapy for AN:
- Family-Based Treatment (FBT / Maudsley method) — gold standard for adolescent AN; parents take temporary charge of their child's eating; typically 15-20 sessions over 12 months; remission rates of 40-50% at end of treatment
- Enhanced Cognitive Behavioral Therapy for Eating Disorders (CBT-E) — enhanced transdiagnostic cognitive behavioral therapy (CBT); 40 sessions for underweight patients; addresses overvaluation of shape/weight, dietary restraint, and maintaining mechanisms
- Specialist Supportive Clinical Management (SSCM) — combines clinical management (nutritional counseling, weight monitoring) with supportive psychotherapy
- Maudsley Model of Anorexia Nervosa Treatment for Adults (MANTRA) — addresses cognitive-interpersonal maintaining factors including cognitive rigidity, emotional avoidance, and pro-anorexia beliefs
Pharmacotherapy for AN: No medication has demonstrated robust efficacy for the core symptoms of AN or weight restoration. Olanzapine (2.5-10 mg/day) has modest evidence for weight gain and anxiety reduction. Selective serotonin reuptake inhibitors (SSRIs) are generally ineffective during the underweight state (likely due to tryptophan depletion) and have also been tested after weight restoration. In a 2006 randomized trial, 93 people with anorexia nervosa whose weight had been restored took fluoxetine or a placebo for up to one year, all with individual cognitive behavioral therapy: about the same share stayed well for the full year (26.5% on fluoxetine vs 31.5% on placebo), and fluoxetine did not delay relapse. The authors concluded the study "failed to demonstrate any benefit from fluoxetine" after weight restoration.
The American Psychiatric Association published a practice guideline for the treatment of patients with eating disorders in 2023.
Treatment of Bulimia Nervosa
- Cognitive behavioral therapy for Bulimia Nervosa (CBT-BN) — first-line treatment; typically 16-20 sessions; achieves abstinence from bingeing/purging in 30-50% of patients; addresses dietary restraint, body image disturbance, and triggers
- Interpersonal Psychotherapy (IPT) — comparable long-term efficacy to cognitive behavioral therapy though slower onset of action
- Fluoxetine 60 mg/day — the only U.S. Food and Drug Administration-approved medication for BN; reduces binge/purge frequency by approximately 50-70%; often combined with cognitive behavioral therapy for optimal results
- Topiramate (25-400 mg/day) — reduces binge frequency and promotes weight loss; useful when comorbid obesity is present
Treatment of Binge-Eating Disorder
- Cognitive behavioral therapy (individual or group) — first-line psychotherapy; reduces binge frequency but may not produce significant weight loss
- Lisdexamfetamine 50-70 mg/day — U.S. Food and Drug Administration-approved for moderate-to-severe BED. In the 2015 11-week trial of 255 adults, binge days fell by about 4 per week from the starting level on 50 or 70 mg/day, against about 3.3 per week on placebo; 42-50% stopped bingeing for 4 weeks, against 21% on placebo. Average weight loss was about 5 kg (about 0.1 kg on placebo), and side effects of any kind were reported by 85% of people on the drug and 59% on placebo. It is the only medication with U.S. Food and Drug Administration (FDA) approval specifically for BED
- Topiramate — in the 2003 14-week trial in BED with obesity, doses ran from 25 to 600 mg/day (median 212 mg/day); reduces binge frequency and body weight; significant side effect burden limits use
- Selective serotonin reuptake inhibitors — moderate efficacy for binge reduction (fluoxetine, sertraline, fluvoxamine at standard antidepressant doses)
- Behavioral weight loss (BWL) — addresses comorbid obesity; comparable binge reduction to cognitive behavioral therapy in some studies
Levels of Care
- Outpatient — appropriate for medically stable patients with adequate motivation
- Intensive outpatient (IOP) — 3-5 days/week, 3-4 hours/day
- Partial hospitalization (PHP) — 5 days/week, 6-10 hours/day with supervised meals
- Residential treatment — 24-hour care in a non-hospital setting; typically 30-90 days
- Inpatient medical/psychiatric hospitalization — for acute medical instability (heart rate <40 bpm, blood pressure <90/60, temperature <36C, severe electrolyte abnormalities, suicidality)
8. Complications
- Cardiac complications — bradycardia, QTc prolongation, mitral valve prolapse, pericardial effusion, congestive heart failure (during refeeding), sudden cardiac death
- Electrolyte abnormalities — hypokalemia (risk of fatal cardiac arrhythmia), hypophosphatemia (refeeding syndrome), hyponatremia, hypomagnesemia
- Endocrine disruption — hypothalamic amenorrhea, low estrogen/testosterone, hypothyroidism (sick euthyroid), elevated cortisol, growth hormone resistance
- Skeletal complications — osteopenia and osteoporosis (affecting up to 85% of AN patients); increased fracture risk; may be irreversible even after weight restoration
- Gastrointestinal — delayed gastric emptying, constipation, superior mesenteric artery syndrome, esophageal tears (Mallory-Weiss), Barrett's esophagus, pancreatitis
- Dental — perimolysis (enamel erosion from repeated vomiting), dental caries, parotid gland hypertrophy
- Neurological — cerebral atrophy (partially reversible), peripheral neuropathy, seizures (electrolyte-related)
- Renal — chronic dehydration, hypokalemic nephropathy, renal failure
- Hematological — pancytopenia, immunosuppression, impaired wound healing
- Psychiatric — major depression, anxiety disorders, substance use disorders, self-harm, suicide (AN has the highest suicide rate of any psychiatric disorder after adjusting for mortality)
- Fertility and pregnancy — infertility, increased risk of miscarriage, low birth weight infants, postpartum depression
9. Prognosis
Anorexia Nervosa: Long-term outcome studies (10-20 year follow-up) indicate that approximately 46% of patients achieve full recovery, 33% show improvement but remain symptomatic, and 21% develop a chronic course. The crude mortality rate is approximately 5-6% per decade of illness, with deaths due to medical complications (approximately 50%), suicide, and other causes. A 2011 meta-analysis of 36 studies counted about 5 deaths per 1,000 person-years in anorexia nervosa, 1.7 in bulimia nervosa and 3.3 in other eating disorders, and found that 1 in 5 people with anorexia nervosa who died had died by suicide. The standardized mortality ratio of 5.9 is the highest of any psychiatric disorder. Median time to recovery is approximately 7 years. Predictors of better outcome include younger age at onset, shorter duration of illness, and higher body mass index at presentation. Onset after age 25 and very low body mass index at presentation predict poorer outcomes.
Bulimia Nervosa: Approximately 55-70% of patients achieve full or partial remission over 5-10 years. The crude mortality rate is approximately 2% per decade. Crossover to AN occurs in approximately 10-15% of cases. Early treatment response (within the first 4-6 weeks of cognitive behavioral therapy) is a strong predictor of eventual outcome.
Binge-Eating Disorder: BED has the most favorable prognosis among eating disorders, with remission rates of approximately 50-80% over 4-5 years. However, weight management remains a significant challenge, and many patients continue to struggle with obesity-related medical complications even after binge cessation.
10. Prevention
- Media literacy programs — teaching critical evaluation of appearance-focused media messages; programs like Media Smart and Body Project have demonstrated efficacy in reducing eating disorder risk factors
- The Body Project (dissonance-based prevention) — participants critique the thin ideal through verbal, written, and behavioral exercises; in a randomized trial of 481 teenage girls with body dissatisfaction, it cut the risk of eating-disorder onset by 60% compared with girls who were only assessed, over 3 years of follow-up
- School-based prevention programs — targeting body image, self-esteem, and healthy eating behaviors; most effective when interactive and delivered over multiple sessions
- Screening in high-risk populations — athletes, dancers, models, military personnel, individuals with type 1 diabetes
- Anti-weight stigma initiatives — reducing weight-based discrimination and bullying in schools and workplaces
- Social media regulation — age-appropriate content filters, warning labels on digitally altered images, bans on pro-eating disorder content
- Training healthcare providers — improving early detection in primary care, pediatrics, and dental settings
- Family-based approaches — positive family meal environments, avoiding diet talk and weight commentary, modeling healthy relationships with food
- Addressing dieting culture — promoting Health at Every Size (HAES) and intuitive eating principles
11. Recent Research and Advances
Genomic and metabolomic discoveries have fundamentally reframed our understanding of anorexia nervosa. The Eating Disorders Working Group of the Psychiatric Genomics Consortium published landmark GWAS findings demonstrating that AN has significant metabo-psychiatric underpinnings — genetic risk factors overlap with metabolic traits (low body mass index, low insulin resistance) in addition to psychiatric disorders. This suggests AN should be reconceptualized as a metabo-psychiatric disorder rather than a purely psychological condition, with implications for treatment development targeting metabolic pathways.
Psilocybin-assisted therapy is being investigated for AN, with the rationale that psychedelic-induced cognitive flexibility and emotional processing may help overcome the rigid thinking patterns characteristic of AN. The published study so far is a small phase 1 open-label study (2023): 10 women with AN received a single 25-mg dose with psychological support. It was designed to test safety, not benefit; there were no clinically significant changes in heart tracing, vital signs or suicidal thinking, two women had low blood sugar without symptoms that cleared within 24 hours, and the authors judged the treatment safe, tolerable and acceptable. Whether it improves AN is not yet known; that needs larger controlled trials.
Gut microbiome-targeted interventions represent a novel treatment frontier. Fecal microbiota transplantation (FMT) is being studied in clinical trials for AN, with the hypothesis that restoring healthy gut microbial communities may improve appetite regulation, reduce gastrointestinal symptoms, and modulate brain function through the gut-brain axis. Probiotic supplementation trials are also underway.
Digital interventions are expanding treatment access. Internet-based cognitive behavioral therapy programs and a meal-logging smartphone app have shown efficacy comparable to guided self-help in reducing binge/purge symptoms. A chatbot app for eating disorder support is being evaluated in clinical trials. Smartphone-based ecological momentary interventions deliver personalized support at moments of vulnerability identified through real-time symptom monitoring.
Neuroimaging-guided treatments are advancing toward precision medicine. Real-time functional magnetic resonance imaging (fMRI) neurofeedback training patients to modulate activation in brain regions involved in self-referential processing and body image has shown promising preliminary results in AN. Repetitive transcranial magnetic stimulation (rTMS) targeting the left dorsolateral prefrontal cortex has been tested in BN and BED. A 2026 meta-analysis of brain-stimulation studies (rTMS and transcranial direct current stimulation) found a drop in food craving, based mainly on one single-session experiment, but no significant reduction in binge episodes, vomiting episodes or eating-disorder symptoms; the authors called these treatments investigational rather than therapeutic.
Key Research Papers
Historical Background
The earliest medical descriptions of self-starvation date to the medieval period, with accounts of "holy fasting" among female saints. Richard Morton provided the first medical case report of anorexia nervosa in 1689, describing a patient with "nervous consumption." The condition was independently described and named by Sir William Gull in London ("anorexia nervosa," 1873) and Charles Lasegue in Paris ("anorexie hysterique," 1873). Gerald Russell defined bulimia nervosa as a distinct syndrome in his landmark 1979 paper, describing an "ominous variant of anorexia nervosa." Albert Stunkard described binge eating in obese patients in 1959; in 1955 he had described the separate "night eating syndrome". Hilde Bruch's influential 1973 book Eating Disorders: Obesity, Anorexia Nervosa, and the Person Within transformed clinical understanding by emphasizing body image disturbance and deficits in interoceptive awareness as core psychopathology.
Key Research Papers
- Arcelus J, Mitchell AJ, Wales J, Nielsen S. Mortality rates in patients with anorexia nervosa and other eating disorders: a meta-analysis of 36 studies. Arch Gen Psychiatry. 2011;68(7):724-731. — doi:10.1001/archgenpsychiatry.2011.74
- Watson HJ, Yilmaz Z, Thornton LM, et al. Genome-wide association study identifies eight risk loci and implicates metabo-psychiatric origins for anorexia nervosa. Nat Genet. 2019;51(8):1207-1214. — doi:10.1038/s41588-019-0439-2
- Fairburn CG, Cooper Z, Doll HA, et al. Transdiagnostic cognitive-behavioral therapy for patients with eating disorders: a two-site trial with 60-week follow-up. Am J Psychiatry. 2009;166(3):311-319. — doi:10.1176/appi.ajp.2008.08040608
- Lock J, Le Grange D, Agras WS, et al. Randomized clinical trial comparing family-based treatment with adolescent-focused individual therapy for adolescents with anorexia nervosa. Arch Gen Psychiatry. 2010;67(10):1025-1032. — doi:10.1001/archgenpsychiatry.2010.128
- Kessler RC, Berglund PA, Chiu WT, et al. The prevalence and correlates of binge eating disorder in the World Health Organization World Mental Health Surveys. Biol Psychiatry. 2013;73(9):904-914. — doi:10.1016/j.biopsych.2012.11.020
- Russell G. Bulimia nervosa: an ominous variant of anorexia nervosa. Psychol Med. 1979;9(3):429-448. — doi:10.1017/S0033291700031974
- McElroy SL, Hudson JI, Mitchell JE, et al. Efficacy and safety of lisdexamfetamine for treatment of adults with moderate to severe binge-eating disorder: a randomized clinical trial. JAMA Psychiatry. 2015;72(3):235-246. — doi:10.1001/jamapsychiatry.2014.2162
- Zipfel S, Giel KE, Bulik CM, et al. Anorexia nervosa: aetiology, assessment, and treatment. Lancet Psychiatry. 2015;2(12):1099-1111. — doi:10.1016/S2215-0366(15)00356-9
- Steinglass J, Foerde K, Kostro K, et al. Restrictive food intake as a choice — a paradigm for study. Int J Eat Disord. 2015;48(1):59-66. — doi:10.1002/eat.22345
- Frank GKW, Shott ME, DeGuzman MC. The neurobiology of eating disorders. Child Adolesc Psychiatr Clin N Am. 2019;28(4):629-640. — doi:10.1016/j.chc.2019.05.007
- Treasure J, Duarte TA, Schmidt U. Eating disorders. Lancet. 2020;395(10227):899-911. — doi:10.1016/S0140-6736(20)30059-3
- Stice E, Marti CN, Spoor S, et al. Dissonance and healthy weight eating disorder prevention programs: long-term effects from a randomized efficacy trial. J Consult Clin Psychol. 2008;76(2):329-340. — doi:10.1037/0022-006X.76.2.329
- Mack I, Cuntz U, Gramer C, et al. Weight gain in anorexia nervosa does not ameliorate the faecal microbiota, branched chain fatty acid profiles, and gastrointestinal complaints. Sci Rep. 2016;6:26752. — doi:10.1038/srep26752
- Bulik CM, Sullivan PF, Tozzi F, et al. Prevalence, heritability, and prospective risk factors for anorexia nervosa. Arch Gen Psychiatry. 2006;63(3):305-312. — doi:10.1001/archpsyc.63.3.305
- Walsh BT, Kaplan AS, Attia E, et al. Fluoxetine after weight restoration in anorexia nervosa: a randomized controlled trial. JAMA. 2006;295(22):2605-2612. — doi:10.1001/jama.295.22.2605
- Ramanathan B, Vijayan S, Mohan M, et al. Non-invasive brain stimulation as an experimental treatment approach for bulimia nervosa and binge eating disorders: a meta-analysis and systematic review of literature. Indian J Psychiatry. 2026;68(5):411-428. — doi:10.4103/indianjpsychiatry_986_25
- Peck SK, Shao S, Gruen T, et al. Psilocybin therapy for females with anorexia nervosa: a phase 1, open-label feasibility study. Nat Med. 2023;29(8):1947-1953. — doi:10.1038/s41591-023-02455-9
- Crone C, Fochtmann LJ, Attia E, et al. The American Psychiatric Association practice guideline for the treatment of patients with eating disorders. Am J Psychiatry. 2023;180(2):167-171. — doi:10.1176/appi.ajp.23180001
- Stunkard AJ. Eating patterns and obesity. Psychiatr Q. 1959;33:284-295. — doi:10.1007/BF01575455
- Stunkard AJ, Grace WJ, Wolff HG. The night-eating syndrome; a pattern of food intake among certain obese patients. Am J Med. 1955;19(1):78-86. — doi:10.1016/0002-9343(55)90276-x
PubMed Topic Searches
- PubMed: anorexia nervosa treatment
- PubMed: bulimia nervosa CBT
- PubMed: binge eating disorder
- PubMed: eating disorder family based therapy
- PubMed: eating disorder epidemiology
- PubMed: eating disorder mortality
- PubMed: refeeding syndrome
- PubMed: eating disorder genetics
- PubMed: ARFID avoidant restrictive
- PubMed: eating disorder gut microbiome
- PubMed: eating disorder adolescents
- PubMed: eating disorder comorbidity
Connections
- Psychiatry
- Hunger, Leptin & Why Diets Fight Back — interactive animation
- Anxiety
- Depression
- Obsessive-Compulsive Disorder
- Obesity
- Magnesium
- Zinc
- Iron
- Vitamin B12
- Vitamin D3
- Stress Management
- Loss of Appetite
- Gut Microbiome
- Gut-Brain Axis
- Tryptophan
- Fasting
- Osteoporosis
- Pellagra and Niacin Deficiency
- Gut Healing