Obsessive-Compulsive Disorder (OCD)
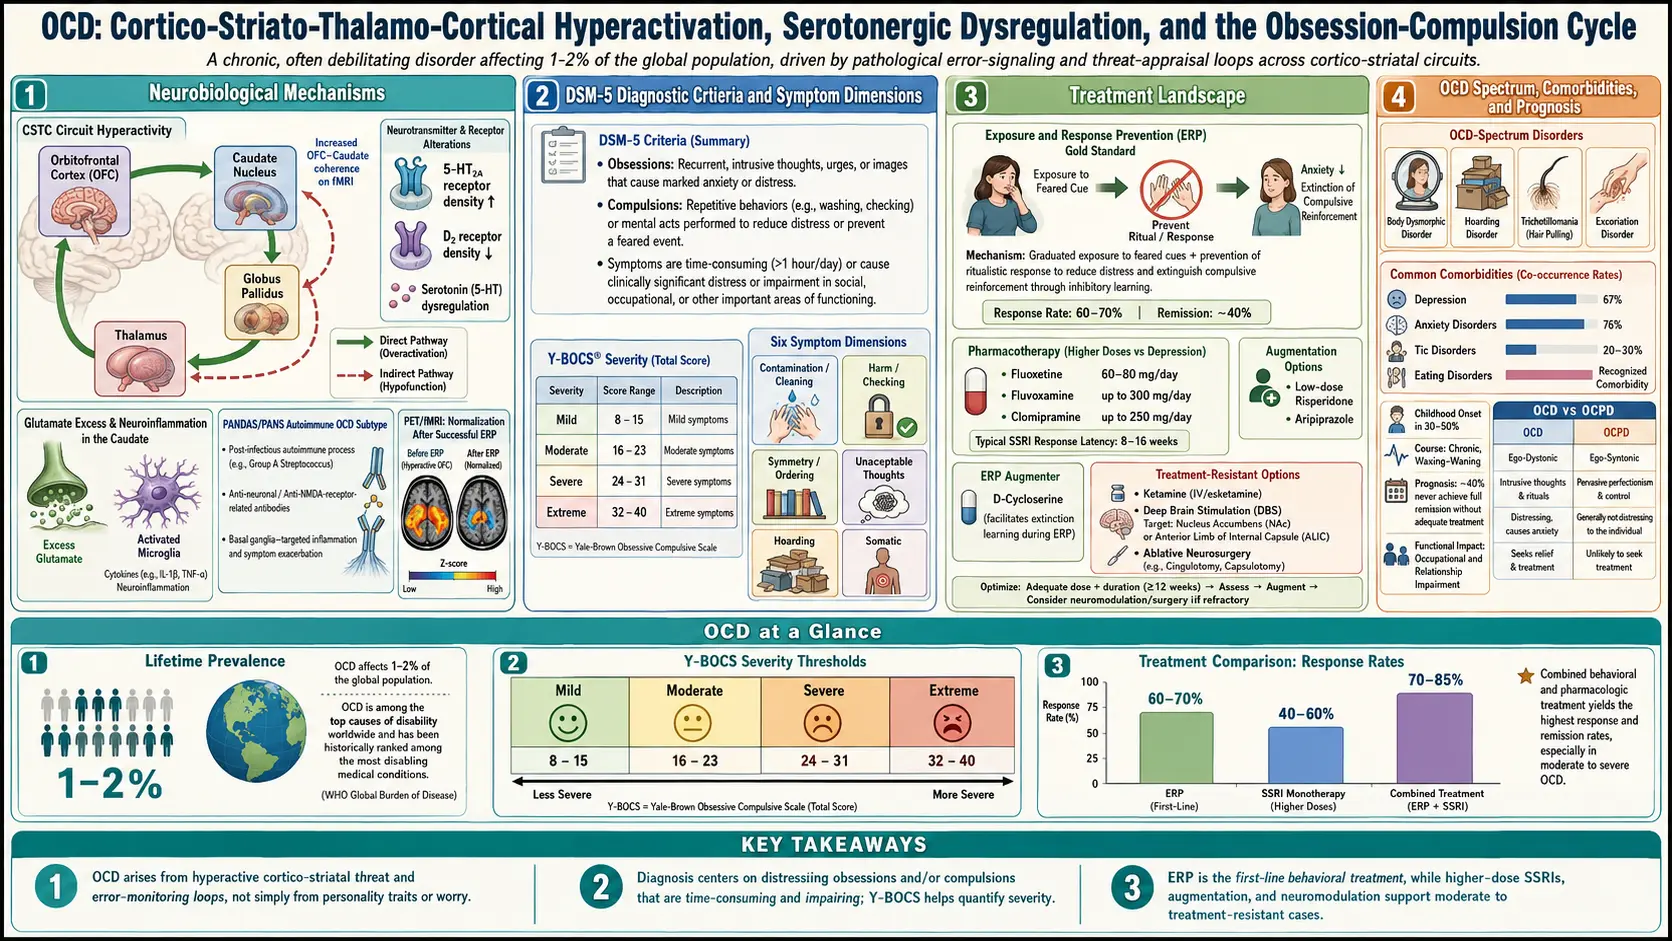
Table of Contents
1. Overview
Obsessive-Compulsive Disorder (OCD) is a chronic neuropsychiatric disorder characterized by the presence of obsessions (recurrent, intrusive, and unwanted thoughts, images, or urges that cause marked anxiety or distress) and/or compulsions (repetitive behaviors or mental acts that the individual feels driven to perform in response to an obsession or according to rigid rules). Obsessive-compulsive disorder was reclassified in the DSM-5 (2013) from the anxiety disorders category into its own chapter, Obsessive-Compulsive and Related Disorders, reflecting its distinct neurobiological profile and clinical phenomenology.
Obsessive-compulsive disorder is recognized by the World Health Organization as one of the top 10 most disabling illnesses worldwide in terms of lost income and diminished quality of life. The disorder typically follows a waxing and waning course, with symptom severity fluctuating in response to stress, life changes, and other factors. Obsessive-compulsive disorder symptoms are ego-dystonic, meaning patients generally recognize that their obsessions are irrational or excessive, although insight varies considerably and the DSM-5 includes specifiers for good or fair insight, poor insight, and absent insight/delusional beliefs.
The disorder is closely related to several conditions now grouped in the obsessive-compulsive disorder spectrum, including body dysmorphic disorder, hoarding disorder, trichotillomania (hair-pulling disorder), and excoriation (skin-picking) disorder. Obsessive-compulsive disorder also has significant overlap with tic disorders, and a tic-related specifier is included in the DSM-5. Understanding obsessive-compulsive disorder as a disorder of the cortico-striato-thalamo-cortical (CSTC) circuit has been one of the most successful examples of translational neuroscience in psychiatry.
2. Epidemiology
Obsessive-compulsive disorder has a lifetime prevalence of approximately 2.0-3.0% globally, making it one of the most common psychiatric disorders. The 12-month prevalence in the United States is approximately 1.0-1.2%. Obsessive-compulsive disorder affects males and females approximately equally in adulthood, though males predominate in childhood-onset cases (2:1 male-to-female ratio for onset before age 10). The mean age of onset is 19.5 years, with approximately 25% of cases beginning by age 14. There is a bimodal distribution of onset, with peaks in pre-adolescence (ages 10-12) and early adulthood (ages 20-22).
The average delay from symptom onset to diagnosis and treatment is disturbingly long, estimated at 7-10 years in most studies. This treatment gap is attributed to shame, poor recognition, and the secretive nature of many obsessions. Obsessive-compulsive disorder has been identified across all cultures studied, though symptom content varies culturally — religious obsessions are more common in highly religious societies, while contamination fears show relative consistency across cultures.
Comorbidity rates are high: the US National Comorbidity Survey Replication (2,073 adults assessed; lifetime OCD 2.3%, 12-month 1.2%) found OCD associated with substantial comorbidity, not only with anxiety and mood disorders but also with impulse-control and substance use disorders (Ruscio 2010). The most common comorbidities include major depressive disorder (63%), anxiety disorders (76%), tic disorders (30% in childhood-onset cases), and attention-deficit/hyperactivity disorder (ADHD). Approximately 25-30% of individuals with Tourette syndrome also meet criteria for obsessive-compulsive disorder.
3. Pathophysiology
Cortico-Striato-Thalamo-Cortical (CSTC) Circuit
The most well-established neurobiological model of obsessive-compulsive disorder involves dysfunction in the CSTC circuit, a series of parallel loops connecting cortical regions to the basal ganglia and thalamus. In obsessive-compulsive disorder, there is hyperactivity in the "direct" (excitatory) pathway through the basal ganglia, which normally facilitates cortical activation, and relative underactivity of the "indirect" (inhibitory) pathway, which normally suppresses unwanted motor and cognitive programs. This imbalance results in a failure to inhibit intrusive thoughts and repetitive behaviors. Neuroimaging studies consistently demonstrate hyperactivation of the orbitofrontal cortex (OFC), anterior cingulate cortex (ACC), and caudate nucleus at rest and during symptom provocation, with normalization following successful treatment.
Serotonergic System
The serotonin hypothesis of obsessive-compulsive disorder is supported by the selective efficacy of serotonin reuptake inhibitors (SRIs) in treating obsessive-compulsive disorder, while noradrenergic reuptake inhibitors are generally ineffective. Evidence includes altered serotonin transporter (SERT) binding in the midbrain and thalamus, abnormal responses to serotonergic challenge agents (such as m-chlorophenylpiperazine, which exacerbates obsessive-compulsive disorder symptoms), and genetic associations with serotonin system genes. However, the serotonin hypothesis alone is insufficient, as SRIs produce only partial response in many patients.
Glutamatergic and Dopaminergic Systems
Glutamate, the primary excitatory neurotransmitter, has emerged as a critical player in obsessive-compulsive disorder neurobiology. Elevated glutamate levels have been detected in the caudate nucleus and orbitofrontal cortex of obsessive-compulsive disorder patients using magnetic resonance spectroscopy. Glutamatergic hyperactivity in cortico-striatal projections may drive the circuit hyperactivation observed in obsessive-compulsive disorder. The dopaminergic system is particularly relevant in obsessive-compulsive disorder with comorbid tics, where dopamine D2 receptor blockade with antipsychotics can augment SRI response. Altered dopamine transporter and D2 receptor binding has been demonstrated in the basal ganglia of obsessive-compulsive disorder patients.
Immune and Inflammatory Mechanisms
Pediatric Autoimmune Neuropsychiatric Disorders Associated with Streptococcal infections (PANDAS) and the broader concept of Pediatric Acute-onset Neuropsychiatric Syndrome (PANS) represent an immune-mediated subtype of obsessive-compulsive disorder. In this model, molecular mimicry between streptococcal antigens and basal ganglia proteins triggers autoimmune inflammation, producing acute-onset obsessive-compulsive disorder and/or tic symptoms. Elevated anti-basal ganglia antibodies, pro-inflammatory cytokines, and microglial activation have been observed in broader obsessive-compulsive disorder populations, suggesting immune dysregulation may contribute beyond the PANDAS subtype.
4. Etiology and Risk Factors
Genetic Factors
- Heritability estimated at 40-65% from twin studies, higher for childhood-onset obsessive-compulsive disorder
- First-degree relatives of obsessive-compulsive disorder patients have a 4-8 fold increased risk
- Candidate genes: SLC6A4 (serotonin transporter), SLC1A1 (glutamate transporter), DLGAP1, PTPRD, and GRIK2 (glutamate receptor)
- Genome-wide association studies (GWAS) have identified common variants of small effect, with polygenic architecture similar to other psychiatric disorders
Neuroanatomical Factors
- Reduced gray matter volume in the orbitofrontal cortex, anterior cingulate cortex, and caudate
- White matter abnormalities in the cingulum bundle and corpus callosum
- Increased caudate volume in pediatric obsessive-compulsive disorder, potentially normalizing with treatment
Environmental Factors
- Perinatal complications — birth trauma, prematurity, and maternal stress during pregnancy
- Childhood trauma — physical and sexual abuse, emotional neglect
- Streptococcal infections — PANDAS/PANS mechanism for acute-onset obsessive-compulsive disorder
- Stressful life events — often precipitate onset or exacerbations in predisposed individuals
- Cognitive style — inflated sense of responsibility, overestimation of threat, perfectionism, intolerance of uncertainty
Developmental Factors
- Early-onset obsessive-compulsive disorder (before age 10) is more familial, more prevalent in males, more commonly associated with tics, and often has a different treatment response profile
- Postpartum onset — obsessive-compulsive disorder can emerge or dramatically worsen in the peripartum period, with obsessions typically centered on harm to the infant
5. Clinical Presentation
Common Obsession Themes
- Contamination — fear of dirt, germs, bodily fluids, environmental toxins, or illness (approximately 50% of patients)
- Harm — intrusive images or thoughts of harming oneself or others (stabbing, pushing someone into traffic)
- Symmetry and exactness — need for things to be arranged, aligned, or balanced in a particular way
- Forbidden or taboo thoughts — unwanted sexual, religious, or violent intrusions (pedophilic obsessive-compulsive disorder, scrupulosity)
- Doubt — persistent uncertainty about whether one has completed an action correctly (locked the door, turned off the stove)
- Somatic obsessions — excessive preoccupation with bodily functions (breathing, swallowing, heartbeat)
Common Compulsion Types
- Washing and cleaning — excessive handwashing, showering, cleaning rituals (often causing dermatitis)
- Checking — repeated verification of locks, appliances, safety measures
- Ordering and arranging — symmetrical arrangement of objects, counting, repeating actions a specific number of times
- Mental compulsions — silent counting, praying, mentally reviewing events, thought neutralization
- Reassurance seeking — repeatedly asking others for confirmation of safety or correctness
- Avoidance — avoiding triggers (knives, bridges, children) — considered a compulsive behavior in obsessive-compulsive disorder
Symptom Dimensions
Factor analytic studies consistently identify four major symptom dimensions that tend to cluster together and may have distinct neurobiological underpinnings:
- Contamination/washing
- Symmetry/ordering/counting/repeating
- Forbidden thoughts (aggressive, sexual, religious)
- Hoarding (now a separate disorder in DSM-5 but still commonly co-occurs)
Insight Variability
The DSM-5 includes an insight specifier recognizing that obsessive-compulsive disorder exists on a continuum of insight. Approximately 4% of obsessive-compulsive disorder patients have absent insight/delusional beliefs about their obsessions, presenting diagnostic challenges and overlap with psychotic disorders. Poor insight is associated with worse treatment outcomes and higher rates of comorbidity.
6. Diagnosis
DSM-5 Diagnostic Criteria
- Criterion A: Presence of obsessions, compulsions, or both
- Criterion B: The obsessions or compulsions are time-consuming (e.g., take more than 1 hour per day) or cause clinically significant distress or impairment in social, occupational, or other important areas of functioning
- Criterion C: Symptoms are not attributable to the physiological effects of a substance or another medical condition
- Criterion D: Symptoms are not better explained by another mental disorder
Specifiers: tic-related; insight level (good/fair, poor, absent/delusional)
Clinical Assessment Tools
- Yale-Brown Obsessive Compulsive Scale (Y-BOCS) — gold standard clinician-administered rating; 10 items scored 0-4 each; total score range 0-40; severity categories: mild (8-15), moderate (16-23), severe (24-31), extreme (32-40)
- Y-BOCS-II — updated version with improved severity ratings and avoidance assessment
- Obsessive-Compulsive Inventory-Revised (OCI-R) — 18-item self-report; cutoff score of 21 suggests clinical obsessive-compulsive disorder
- Dimensional Obsessive-Compulsive Scale (DOCS) — 20-item self-report measuring four symptom dimensions
- Children's Yale-Brown Obsessive Compulsive Scale (CY-BOCS) — for pediatric assessment
Differential Diagnosis
Obsessive-compulsive disorder is distinguished from generalized anxiety disorder (worry about real-life concerns rather than ego-dystonic intrusions), body dysmorphic disorder (preoccupation limited to perceived appearance flaws), hoarding disorder, illness anxiety disorder, obsessive-compulsive personality disorder (ego-syntonic traits rather than ego-dystonic symptoms), tic disorders, psychotic disorders (particularly in patients with poor insight), autism spectrum disorder (restricted interests and repetitive behaviors), and eating disorders (food-related rituals).
7. Treatment
First-Line Psychotherapy: Exposure and Response Prevention (ERP)
Exposure and Response Prevention (ERP) is the gold standard psychotherapy for obsessive-compulsive disorder and is effective in approximately 60-70% of patients who complete treatment. ERP involves systematic, graduated exposure to feared obsessional triggers while voluntarily refraining from compulsive rituals. Treatment typically consists of 13-20 sessions over 3-5 months. Mean Y-BOCS reductions of 10-15 points (approximately 50-60% symptom reduction) are typical. ERP can be delivered individually, in group format, or via intensive (daily) programs for severe cases. Key elements include:
- Hierarchy development — constructing a ranked list of feared situations (SUDS ratings 0-100)
- In vivo exposure — direct confrontation with feared stimuli
- Imaginal exposure — for obsessions that cannot be directly confronted (e.g., harm thoughts)
- Ritual prevention — voluntary abstention from compulsive behaviors during and after exposures
Other Evidence-Based Psychotherapies
- Acceptance and Commitment Therapy (ACT) — emphasis on psychological flexibility, acceptance of intrusive thoughts, and values-based action
- Inference-based cognitive behavioral therapy (I-CBT) — targets the reasoning process underlying obsessional doubts rather than the content of obsessions; emerging evidence suggests comparable efficacy to ERP
- Metacognitive therapy — addresses beliefs about thinking (e.g., thought-action fusion, importance of controlling thoughts)
Pharmacotherapy
First-line: Serotonin Reuptake Inhibitors (SRIs)
- Fluvoxamine — 100-300 mg/day; U.S. Food and Drug Administration-approved for obsessive-compulsive disorder
- Fluoxetine — 40-80 mg/day; U.S. Food and Drug Administration-approved for obsessive-compulsive disorder (note: higher doses than for depression)
- Sertraline — 50-200 mg/day; U.S. Food and Drug Administration-approved for obsessive-compulsive disorder
- Paroxetine — 40-60 mg/day; U.S. Food and Drug Administration-approved for obsessive-compulsive disorder
- Clomipramine — tricyclic SRI; 100-250 mg/day; U.S. Food and Drug Administration-approved; often the most potent SRI for obsessive-compulsive disorder but with greater side effect burden (anticholinergic effects, seizure risk at high doses, cardiac conduction changes)
Key pharmacotherapy principles for obsessive-compulsive disorder:
- Obsessive-compulsive disorder requires higher selective serotonin reuptake inhibitor (SSRI) doses than depression (e.g., fluoxetine 60-80 mg versus 20 mg for depression)
- Longer trial duration required: minimum 8-12 weeks at adequate dose before judging response (versus 4-6 weeks for depression)
- Response rates to first selective serotonin reuptake inhibitor trial: approximately 40-60% (defined as ≥25-35% Y-BOCS reduction)
Augmentation strategies for SRI partial responders:
- Low-dose antipsychotic augmentation — risperidone (0.5-2 mg/day), aripiprazole (2-15 mg/day), or haloperidol; most evidence for tic-related obsessive-compulsive disorder. In a 2013 randomized trial of 100 adults who still had at least moderate symptoms despite an SRI, adding 8 weeks of risperidone (up to 4 mg/day) was no better than placebo, while adding exposure and ritual prevention (17 sessions) was better than both: 80% responded with ERP, against 23% with risperidone and 15% with placebo, and 43%, 13% and 5% reached minimal symptoms (Simpson 2013). The authors concluded that patients in this situation should be offered ERP before antipsychotics, given its better results and fewer side effects.
- Glutamate modulators — memantine (5-20 mg/day), N-acetylcysteine (2400-3000 mg/day); emerging evidence
- Combination SRI + ERP — combining medication with psychotherapy generally produces better outcomes than either alone
Neurosurgical and Neuromodulation Treatments
- Deep Brain Stimulation (DBS) — U.S. Food and Drug Administration-approved under Humanitarian Device Exemption for treatment-refractory obsessive-compulsive disorder; targets the ventral capsule/ventral striatum (VC/VS) or subthalamic nucleus; response rates approximately 50-60%
- Transcranial Magnetic Stimulation (TMS) — U.S. Food and Drug Administration-cleared for obsessive-compulsive disorder (2018); deep TMS targeting the medial prefrontal cortex and anterior cingulate; response rates approximately 38% — in a 2019 trial of 99 patients at 11 centers, 38.1% responded to 6 weeks of daily active deep TMS against 11.1% with sham treatment (45.2% against 17.8% one month later), with Y-BOCS drops of 6.0 and 3.3 points (Carmi 2019)
- Anterior capsulotomy and cingulotomy — ablative neurosurgery reserved for the most severe, treatment-refractory cases after exhaustive pharmacological and psychotherapeutic trials
8. Complications
- Severe functional impairment — some patients spend 8+ hours per day on rituals, rendering work and social functioning impossible
- Major depressive disorder — comorbid in approximately 63% of obsessive-compulsive disorder patients; often secondary to the burden of obsessive-compulsive disorder symptoms
- Suicidality — suicide attempt rates of 10-15%; suicidal ideation in up to 50% of obsessive-compulsive disorder patients, particularly those with unacceptable/taboo obsessions
- Dermatological damage — contact dermatitis, eczema, and skin breakdown from excessive washing and cleaning compulsions
- Social isolation — shame and secrecy about symptoms lead to avoidance of relationships and social situations
- Academic and occupational failure — concentration difficulties, time consumed by rituals, avoidance behaviors
- Substance use disorders — self-medication with alcohol, cannabis, or benzodiazepines
- Family burden — family accommodation (modifying routines to accommodate obsessive-compulsive disorder) occurs in 60-97% of families and paradoxically maintains symptoms
- Financial costs — estimated annual healthcare costs 2-3 times higher than general population
9. Prognosis
Obsessive-compulsive disorder is generally a chronic condition with a waxing and waning course. Over the long term, full recovery is uncommon: a Swedish study of patients admitted to hospital with OCD in 1947–1953 and re-examined about 40 years later (mean 47 years from onset) found improvement in 83%, including recovery in 48% — complete recovery in 20% and recovery with mild leftover symptoms in 28%; 48% had OCD for more than 30 years. Early age of onset, having both obsessions and compulsions, low social functioning at the start and a chronic course in the 1950s were linked to a worse outcome (Skoog and Skoog 1999). Among those receiving adequate treatment, the trajectory is more favorable: approximately 60-70% of patients show clinically meaningful response to first-line treatments (ERP and/or SRIs), though full remission is achieved in only approximately 25-30% of treated patients.
Predictors of better outcome include shorter duration of untreated illness, good insight, absence of comorbid depression or personality disorders, predominantly compulsive symptoms (rather than predominantly obsessional), and availability of family support without excessive accommodation. Predictors of poorer outcome include childhood onset with tics, hoarding symptoms, poor insight, severe comorbid depression, and high family accommodation.
Long-term studies suggest that treatment-refractory obsessive-compulsive disorder (failure to respond to multiple adequate SRI trials plus ERP) affects approximately 10-15% of patients. For these individuals, neuromodulation and neurosurgical options (DBS, TMS, capsulotomy) offer additional avenues of treatment with meaningful response rates. Importantly, maintenance SRI treatment is commonly continued for at least 1-2 years after acute response, with high relapse rates (approximately 50-90%) observed upon medication discontinuation.
10. Prevention
- Early identification and intervention — reducing the diagnostic delay (currently averaging 7-10 years) through public education, school-based screening, and primary care clinician training
- Addressing subclinical obsessive-compulsive symptoms — cognitive-behavioral strategies for individuals with elevated but subthreshold symptoms may prevent progression to full obsessive-compulsive disorder
- Testing for and treating streptococcal infections in children with sudden-onset obsessive-compulsive disorder or tic symptoms, as part of PANDAS/PANS evaluation
- Postpartum screening — monitoring for obsessive-compulsive disorder onset in the peripartum period, particularly in women with personal or family history
- Family psychoeducation — educating families about accommodation behaviors and their role in maintaining obsessive-compulsive disorder symptoms
- Stress management and resilience building — stress reduction techniques for at-risk individuals with family histories or subclinical symptoms
- Relapse prevention — booster ERP sessions and maintenance pharmacotherapy to prevent symptom recurrence after initial treatment response
- Anti-stigma campaigns — reducing shame and misconceptions about obsessive-compulsive disorder to encourage earlier help-seeking
11. Recent Research and Advances
Psilocybin-assisted therapy for obsessive-compulsive disorder has generated significant interest based on early clinical data. A 2006 pilot study by Moreno and colleagues gave 9 people with OCD up to four single doses of psilocybin, from very low to fully hallucinogenic; all had marked symptom drops (23%–100% on the Y-BOCS) in one or more sessions, but there was no significant effect of dose; one person had a short rise in blood pressure and no other significant side effects were seen. Effects are thought to work through 5-HT2A receptor agonism and disruption of rigid, repetitive thought patterns.
- 2025 two-dose study. Nineteen adults with at least moderate OCD received 1 mg and then 10 mg of oral psilocybin four weeks apart, with psychological support. One week after the 10 mg dose, Y-BOCS scores were clearly lower than after 1 mg (effect size 0.82), mostly in compulsions (0.74) rather than obsessions (0.50); the effect faded over the next three weeks. Psilocybin was well tolerated, with no serious side effects. The authors note the study was small and not randomized (Pellegrini 2025).
- 2026 repeated-dose randomized trial. Fifteen people were randomized to four weekly sessions of high-dose (300 µg/kg) or low-dose (100 µg/kg) psilocybin or an active placebo (lorazepam), followed by four more high-dose sessions. Psilocybin, but not placebo, lowered Y-BOCS scores. At 8 weeks, after at least four high doses, 73.3% had responded (a drop of 35% or more) and 40% were in remission; the benefits shrank but stayed substantial at 6 months. There were no serious side effects, no psychotic symptoms and no change in suicide-risk scores. The authors state that larger trials are needed (Moreno 2026).
- 2025 interview study. Interviews with 12 participants from the first randomized placebo-controlled trial of single-dose psilocybin for treatment-resistant OCD described acute effects that were often milder (“partial” experiences) than in other psilocybin trials, and some post-dose changes that resemble the working mechanisms of ERP and acceptance and commitment therapy (Ching 2025).
Glutamate-targeted therapies represent a major new pharmacological direction. Troriluzole (a prodrug of riluzole, a glutamate-modulating agent) showed promise in Phase II/III trials for obsessive-compulsive disorder augmentation. Rapastinel and other N-methyl-D-aspartate (NMDA) receptor modulators are being investigated for their ability to enhance extinction learning during ERP. Ketamine has shown rapid but transient anti-obsessional effects in small studies, with intravenous infusions producing rapid Y-BOCS reductions within hours.
Digital and technology-enhanced treatments are expanding access to ERP. App-based exposure and response prevention programs have been reported to perform comparably to in-person treatment in preliminary trials. Virtual reality exposure therapy (VRET) for contamination-type obsessive-compulsive disorder is under active investigation. Machine learning algorithms analyzing behavioral data from smartphone sensors may enable real-time symptom monitoring and intervention delivery.
Transcranial magnetic stimulation (TMS) protocols continue to evolve, with accelerated (multiple sessions per day) and theta-burst stimulation paradigms showing enhanced efficacy and reduced treatment duration compared to standard protocols. Personalized targeting using neuroimaging-guided coil placement based on individual functional connectivity maps is an emerging approach.
Immunological research is clarifying the role of neuroinflammation in obsessive-compulsive disorder beyond PANDAS. Studies using positron emission tomography (PET) imaging with TSPO radioligands have demonstrated elevated microglial activation in the CSTC circuit of adult obsessive-compulsive disorder patients, opening the possibility of anti-inflammatory treatment strategies including minocycline and celecoxib as adjunctive agents.
Key Research Papers
Historical Background
Obsessive-compulsive phenomena were recognized as early as the 17th century, with descriptions by Robert Burton in The Anatomy of Melancholy (1621) of individuals plagued by intrusive blasphemous thoughts. The French psychiatrist Jean-Etienne Dominique Esquirol provided detailed clinical descriptions of obsessional illness in the 1830s, terming it "monomanie raisonnante." Karl Westphal coined the German term "Zwangsvorstellung" (obsessional idea) in 1877, and the concept of "obsessional neurosis" was elaborated by Sigmund Freud in his famous "Rat Man" case (1909). The behavioral conceptualization by Victor Meyer at the Maudsley Hospital in 1966, who introduced exposure with response prevention, revolutionized obsessive-compulsive disorder treatment. Judith Rapoport's 1989 book The Boy Who Couldn't Stop Washing brought public attention to obsessive-compulsive disorder, and neuroimaging studies by Lewis Baxter and colleagues in the late 1980s established the CSTC circuit model.
Key Research Papers
- Ruscio AM, Stein DJ, Chiu WT, Kessler RC. The epidemiology of obsessive-compulsive disorder in the National Comorbidity Survey Replication. Mol Psychiatry. 2010;15(1):53-63. — doi:10.1038/mp.2008.94
- Menzies L, Chamberlain SR, Laird AR, et al. Integrating evidence from neuroimaging and neuropsychological studies of obsessive-compulsive disorder: the orbitofronto-striatal model revisited. Neurosci Biobehav Rev. 2008;32(3):525-549. — doi:10.1016/j.neubiorev.2007.09.005
- Skapinakis P, Caldwell DM, Hollingworth W, et al. Pharmacological and psychotherapeutic interventions for management of obsessive-compulsive disorder in adults: a systematic review and network meta-analysis. Lancet Psychiatry. 2016;3(8):730-739. — doi:10.1016/S2215-0366(16)30069-4
- Foa EB, Liebowitz MR, Kozak MJ, et al. Randomized, placebo-controlled trial of exposure and ritual prevention, clomipramine, and their combination in the treatment of obsessive-compulsive disorder. Am J Psychiatry. 2005;162(1):151-161. — doi:10.1176/appi.ajp.162.1.151
- Goodman WK, Price LH, Rasmussen SA, et al. The Yale-Brown Obsessive Compulsive Scale: I. Development, use, and reliability. Arch Gen Psychiatry. 1989;46(11):1006-1011. — doi:10.1001/archpsyc.1989.01810110048007
- Bloch MH, McGuire J, Landeros-Weisenberger A, et al. Meta-analysis of the dose-response relationship of SSRI in obsessive-compulsive disorder. Mol Psychiatry. 2010;15(8):850-855. — doi:10.1038/mp.2009.50
- Leckman JF, Denys D, Simpson HB, et al. Obsessive-compulsive disorder: a review of the diagnostic criteria and possible subtypes and dimensional specifiers for DSM-V. Depress Anxiety. 2010;27(6):507-527. — doi:10.1002/da.20669
- Denys D, Mantione M, Figee M, et al. Deep brain stimulation of the nucleus accumbens for treatment-refractory obsessive-compulsive disorder. Arch Gen Psychiatry. 2010;67(10):1061-1068. — doi:10.1001/archgenpsychiatry.2010.122
- Carmi L, Alyagon U, Barnea-Ygael N, et al. Clinical and electrophysiological outcomes of deep TMS over the medial prefrontal and anterior cingulate cortices in OCD patients. Brain Stimul. 2018;11(1):158-165. — doi:10.1016/j.brs.2017.09.004
- Moreno FA, Wiegand CB, Taitano EK, Delgado PL. Safety, tolerability, and efficacy of psilocybin in 9 patients with obsessive-compulsive disorder. J Clin Psychiatry. 2006;67(11):1735-1740. — doi:10.4088/JCP.v67n1110
- Pittenger C, Bloch MH, Williams K. Glutamate abnormalities in obsessive compulsive disorder: neurobiology, pathophysiology, and treatment. Pharmacol Ther. 2011;132(3):314-332. — doi:10.1016/j.pharmthera.2011.09.006
- Abramowitz JS, Taylor S, McKay D. Obsessive-compulsive disorder. Lancet. 2009;374(9688):491-499. — doi:10.1016/S0140-6736(09)60240-3
- Stewart SE, Yu D, Scharf JM, et al. Genome-wide association study of obsessive-compulsive disorder. Mol Psychiatry. 2013;18(7):788-798. — doi:10.1038/mp.2012.85
- Simpson HB, Foa EB, Liebowitz MR, et al. Cognitive-behavioral therapy vs risperidone for augmenting serotonin reuptake inhibitors in obsessive-compulsive disorder: a randomized clinical trial. JAMA Psychiatry. 2013;70(11):1190-1199. — doi:10.1001/jamapsychiatry.2013.1932
- Skoog G, Skoog I. A 40-year follow-up of patients with obsessive-compulsive disorder. Arch Gen Psychiatry. 1999;56(2):121-127. — doi:10.1001/archpsyc.56.2.121
- Carmi L, Tendler A, Bystritsky A, et al. Efficacy and Safety of Deep Transcranial Magnetic Stimulation for Obsessive-Compulsive Disorder: A Prospective Multicenter Randomized Double-Blind Placebo-Controlled Trial. Am J Psychiatry. 2019;176(11):931-938. — doi:10.1176/appi.ajp.2019.18101180
- Pellegrini L, Fineberg NA, O'Connor S, et al. Single-dose (10 mg) psilocybin reduces symptoms in adults with obsessive-compulsive disorder: A pharmacological challenge study. Compr Psychiatry. 2025;142:152619. — doi:10.1016/j.comppsych.2025.152619
- Moreno FA, Allen KE, Wiegand CB, et al. A randomized clinical trial of repeated doses of psilocybin for the treatment of obsessive-compulsive disorder. J Psychopharmacol. 2026;40(5):837-849. — doi:10.1177/02698811261424214
- Ching THW, Stahnke B, Shnayder S, et al. Acute and post-dosing effects of single-dose psilocybin for obsessive-compulsive disorder in a randomized, double-blind, placebo-controlled trial: an interpretative phenomenological analysis. Front Psychiatry. 2025;16:1726818. — doi:10.3389/fpsyt.2025.1726818
PubMed Topic Searches
- PubMed: OCD epidemiology prevalence
- PubMed: OCD exposure response prevention
- PubMed: OCD SSRI treatment
- PubMed: OCD clomipramine
- PubMed: OCD deep brain stimulation
- PubMed: OCD CSTC circuit neurobiology
- PubMed: OCD genetics GWAS
- PubMed: OCD children pediatric PANDAS
- PubMed: OCD body dysmorphic disorder
- PubMed: OCD hoarding disorder
- PubMed: OCD glutamate
- PubMed: OCD comorbidity anxiety
Connections
- Psychiatry
- Serotonin, Mood & Selective Serotonin Reuptake Inhibitors — interactive animation
- Depression
- Anxiety
- Post-Traumatic Stress Disorder
- Eating Disorders
- Stress Management
- Magnesium
- Natural Anxiety Relief
- Ashwagandha
- Vitamin B6
- Autism
- Attention-Deficit/Hyperactivity Disorder
- Insomnia
- Bipolar Disorder
- Sleep Hygiene
- Schizophrenia
- Inositol
- Mental Health
- Grief
- Postpartum Depression
- Body Dysmorphic Disorder (BDD)
- Trichotillomania
- Hoarding Disorder
- Hess & Moniz — the lobotomy prize, and how modern psychosurgery differs from it