Tendinitis
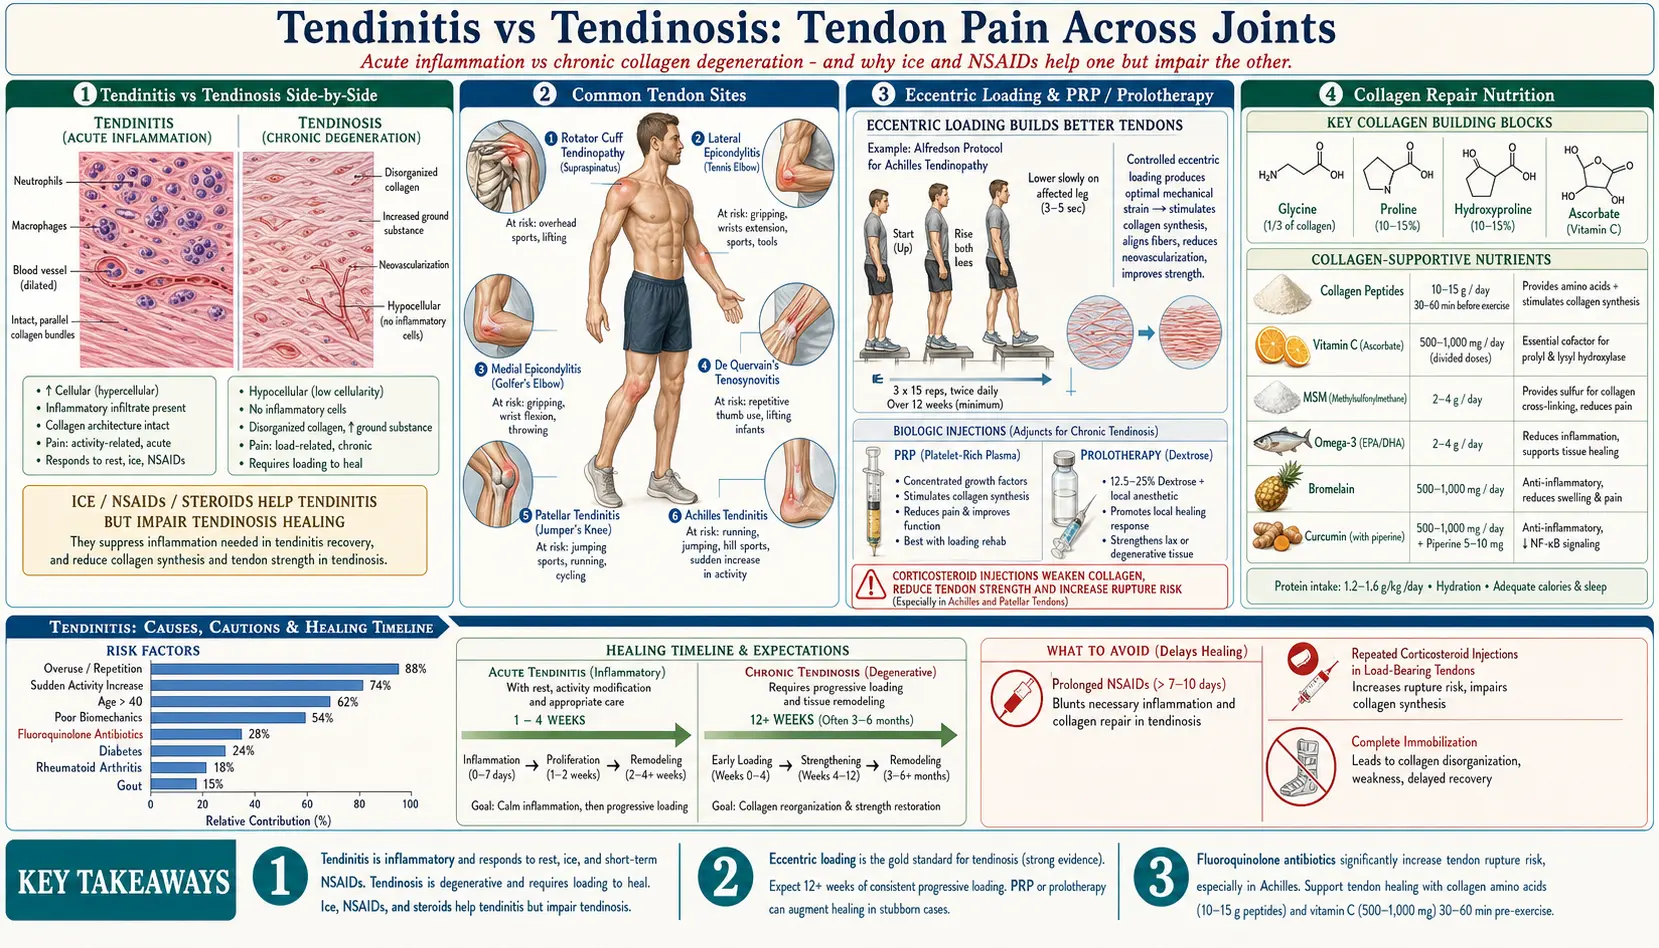
Table of Contents
- What Tendinitis Is
- Tendinitis vs. Tendinosis
- Common Types of Tendinitis
- Causes and Mechanisms
- Symptoms and Diagnosis
- Conventional Treatment
- Natural and Naturopathic Approaches
- Prolotherapy and PRP
- Eccentric Exercises
- Ergonomic Modifications
- Tendon Nutrition and Blood Supply
- Important Cautions
- Key Research Papers
- Featured Videos
What Tendinitis Is
Tendinitis (also spelled tendonitis) is the acute inflammation or irritation of a tendon, the thick fibrous cord that attaches muscle to bone. Tendons transmit the force of muscle contraction to the skeleton, enabling movement. When a tendon becomes inflamed due to overuse, injury, or poor biomechanics, the result is pain, swelling, and impaired function at the affected joint.
Tendinitis can occur in virtually any tendon in the body but most commonly affects the shoulders, elbows, wrists, knees, and heels. While often considered a minor condition, untreated tendinitis can progress to chronic tendon degeneration, significantly limiting mobility and quality of life.
Tendinitis vs. Tendinosis
Understanding the distinction between tendinitis and tendinosis is critical for proper treatment:
- Tendinitis: Acute inflammation of the tendon, typically occurring in the early stages of injury. Inflammatory cells are present, and the condition usually responds to anti-inflammatory interventions. Duration is typically days to a few weeks.
- Tendinosis: Chronic degeneration of the tendon's collagen fibers without the classic swelling-type inflammation; low-grade immune activity (increased immune cells and inflammatory mediators) is now described in tendinopathy tissue. The tendon shows disorganized collagen, increased ground substance, and neovascularization (new, abnormal blood vessel growth). This condition develops over weeks to months of continued stress.
Most cases that patients describe as "tendinitis" are actually tendinosis by the time they seek treatment. This distinction matters because anti-inflammatory treatments (ice, nonsteroidal anti-inflammatory drugs (NSAIDs), corticosteroid injections) may help true tendinitis but can actually impair healing in tendinosis, where the goal is to stimulate collagen repair rather than suppress inflammation.
Common Types of Tendinitis
Lateral Epicondylitis (Tennis Elbow)
Affects the tendons on the outside of the elbow, specifically the extensor carpi radialis brevis. Despite the name, it is far more common in non-athletes, particularly people who perform repetitive gripping, typing, or manual labor. Pain radiates from the outer elbow into the forearm and wrist.
Medial Epicondylitis (Golfer's Elbow)
Involves the tendons on the inside of the elbow (flexor-pronator mass). Common in golfers, throwing athletes, and workers who perform repetitive wrist flexion or forearm pronation. Pain is localized to the inner elbow and may radiate down the forearm.
Achilles Tendinitis
Inflammation of the Achilles tendon, the largest and strongest tendon in the body, connecting the calf muscles to the heel bone. Common in runners, particularly those who suddenly increase training intensity. Can occur at the mid-portion of the tendon or at its insertion point on the calcaneus.
Rotator Cuff Tendinitis
Affects one or more of the four rotator cuff tendons (supraspinatus, infraspinatus, teres minor, subscapularis), most commonly the supraspinatus. Often caused by repetitive overhead movements in swimming, throwing, or overhead work. Pain occurs with arm elevation and can disturb sleep when lying on the affected side.
Patellar Tendinitis (Jumper's Knee)
Inflammation of the patellar tendon connecting the kneecap to the shinbone. Prevalent in athletes who perform frequent jumping (basketball, volleyball) or running. Pain is localized just below the kneecap and worsens with squatting, jumping, or climbing stairs.
De Quervain's Tenosynovitis
Affects the tendons of the thumb (abductor pollicis longus and extensor pollicis brevis) as they pass through a narrow tunnel at the wrist. Common in new parents from repeatedly lifting infants, and increasingly seen with heavy smartphone use. Pain occurs at the thumb side of the wrist and may radiate into the thumb or forearm.
Causes and Mechanisms
- Overuse and repetitive strain: The most common cause. Repetitive motions create microtears in the tendon faster than the body can repair them. This is particularly problematic in tendons with limited blood supply.
- Sudden increase in activity: Rapidly increasing exercise intensity, duration, or frequency without adequate adaptation time (the "too much, too soon" phenomenon).
- Poor biomechanics: Faulty movement patterns, muscle imbalances, or poor posture place abnormal stress on tendons. Examples include running with excessive pronation or poor shoulder mechanics during overhead activities.
- Aging: Tendons become less elastic, less hydrated, and more susceptible to injury with age. Collagen turnover slows, and blood supply diminishes. Tendinitis becomes increasingly common after age 40.
- Inadequate warm-up: Exercising with cold, unstretched muscles and tendons increases strain on tendon fibers.
- Equipment and ergonomics: Improper workstation setup, ill-fitting shoes, worn-out athletic footwear, or incorrect tool grip sizes can all contribute.
- Medications: Fluoroquinolone antibiotics (ciprofloxacin, levofloxacin) are associated with increased risk of tendinitis and tendon rupture, particularly of the Achilles tendon. Statins may also impair tendon health in some individuals.
- Systemic conditions: Diabetes, rheumatoid arthritis, thyroid disorders, and gout increase tendinitis risk through metabolic and inflammatory mechanisms.
Symptoms and Diagnosis
Common symptoms of tendinitis include:
- Pain: Localized to the tendon, typically described as a dull ache that sharpens with movement or activity. Pain often worsens with use and improves with rest in early stages.
- Tenderness: The tendon is painful when pressed or palpated.
- Swelling: Mild to moderate swelling around the affected tendon, sometimes with warmth.
- Stiffness: The affected joint feels stiff, particularly in the morning or after periods of inactivity.
- Crepitus: A crackling or grating sensation when the tendon moves through its sheath.
- Weakness: Reduced strength in the affected muscle-tendon unit, either from pain inhibition or tendon damage.
Diagnosis is primarily clinical, based on history and physical examination. Imaging may include ultrasound (excellent for visualizing tendon structure, thickness, and tears) or magnetic resonance imaging (MRI) (gold standard for detailed tendon assessment). X-rays do not show tendons but can identify calcific tendinitis or bony abnormalities.
Conventional Treatment
RICE Protocol
The traditional first-line approach for acute tendinitis:
- Rest: Relative rest from the aggravating activity (not complete immobilization, which can impair healing).
- Ice: Applied for 15-20 minutes several times daily to reduce acute inflammation and pain.
- Compression: Elastic bandaging to reduce swelling.
- Elevation: Raising the affected limb above heart level when possible.
Nonsteroidal Anti-Inflammatory Drugs
Non-steroidal anti-inflammatory drugs (ibuprofen, naproxen) can reduce pain and inflammation in acute tendinitis. However, prolonged use may impair tendon healing by suppressing the inflammatory cascade needed for tissue repair. For this reason, courses of 7-10 days are commonly described.
Corticosteroid Injections
Provide rapid pain relief by powerfully suppressing inflammation. However, evidence shows that corticosteroids weaken tendon collagen, increase the risk of tendon rupture (particularly in the Achilles tendon), and are associated with worse long-term outcomes compared to physical therapy alone. In a 2013 trial of 165 people with tennis elbow, 83% of those given a steroid injection had recovered completely or improved greatly after 1 year, compared with 96% of those given a placebo injection, and the problem came back in 54% vs 12%. Most clinicians now limit injections to 1-2 per tendon site and avoid them in load-bearing tendons.
Physical Therapy
The cornerstone of tendinitis treatment. A physical therapist can identify biomechanical contributors, provide manual therapy, prescribe progressive loading exercises, and use modalities such as ultrasound therapy and dry needling to promote healing.
Natural and Naturopathic Approaches
Naturopathic management of tendinitis focuses on providing the raw materials for tendon repair, reducing inflammation through natural pathways, and optimizing the healing environment:
Collagen Peptides
Hydrolyzed collagen supplementation (10-15 grams daily) provides the specific amino acids (glycine, proline, hydroxyproline) needed for tendon repair. In one small study of 8 healthy men, 15 g of vitamin C-enriched gelatin taken an hour before 6 minutes of rope-skipping doubled a blood marker of collagen production; human tendons themselves were not measured (lab-grown ligament tissue treated with the men’s blood serum gained collagen). Type I collagen is the predominant form in tendons.
Vitamin C
Essential for collagen synthesis through its role in the hydroxylation of proline and lysine residues. Vitamin C deficiency impairs tendon repair. Supplementation of 500-1000 mg daily supports collagen production and provides antioxidant protection against oxidative damage at the injury site.
MSM (Methylsulfonylmethane)
An organic sulfur compound that supports connective tissue integrity and has mild anti-inflammatory properties. Sulfur is a critical component of the structural proteins in tendons and cartilage. Typical dosing is 2-4 grams daily.
Omega-3 Fatty Acids
Eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) (2-4 grams daily of combined fish oil) modulate the inflammatory response by promoting the production of resolvins and protectins, specialized pro-resolving mediators that help resolve inflammation without suppressing the healing process.
Bromelain
A proteolytic enzyme derived from pineapple stems with demonstrated anti-inflammatory and anti-edema effects. Bromelain reduces swelling and pain when taken on an empty stomach (500-1000 mg daily between meals). It works by modulating prostaglandin synthesis and reducing fibrin accumulation.
Turmeric and Curcumin
Curcumin, the active compound in turmeric, is a potent anti-inflammatory that inhibits nuclear factor kappa B (NF-kB), cyclooxygenase-2 (COX-2), and multiple inflammatory cytokines. Supplements use better-absorbed forms (with piperine, phospholipid complex, or nano-formulated), commonly at 500-1000 mg curcuminoids daily.
Topical Arnica
Arnica montana gel or cream applied topically to the affected tendon can reduce pain and swelling. In one trial of 204 people with hand osteoarthritis, an arnica gel worked as well as a 5% ibuprofen gel for pain and hand function over 21 days, with similar side-effect rates (4.8% vs 6.1%); that trial was in hand osteoarthritis, not tendinitis.
Dimethyl Sulfoxide
A naturally occurring solvent with potent anti-inflammatory and analgesic properties when applied topically. Dimethyl sulfoxide (DMSO) penetrates the skin rapidly and can reduce tendon pain and swelling. Practitioners typically apply it as a 70% solution. It may cause a garlic-like taste and mild skin irritation. Practitioners describe using pharmaceutical-grade dimethyl sulfoxide only. In a 1994 placebo-controlled trial of 157 people with acute shoulder or elbow tendon pain, a much weaker 10% dimethyl sulfoxide gel applied three times a day for 14 days left 44% pain-free, compared with 9% on the plain gel; side effects were seen in 8 vs 3 patients.
Naturopathic Care Trial in Rotator Cuff Tendinitis
A 2009 randomized trial in 85 Canadian postal workers with rotator cuff tendinitis compared 12 weeks of naturopathic care (diet counselling, acupuncture and an oral enzyme combination product, 2 tablets 3 times a day) with range-of-motion exercises plus a placebo. Shoulder pain-and-disability scores fell by 54.5% with naturopathic care and by 18% with exercises, and no serious side effects were seen.
Prolotherapy and PRP
Regenerative injection therapies represent an important treatment category for chronic tendinitis and tendinosis:
Prolotherapy
Involves injecting a dextrose (sugar water) solution into and around the damaged tendon. The controlled irritation triggers a localized inflammatory response that stimulates the body's natural healing cascade, including fibroblast proliferation and new collagen deposition. A series of 3-6 injections spaced 2-4 weeks apart is typical. Multiple studies support its efficacy for lateral epicondylitis, Achilles tendinopathy, and rotator cuff tendinitis.
Platelet-Rich Plasma (PRP)
The patient's own blood is drawn and centrifuged to concentrate platelets, which are rich in growth factors (platelet-derived growth factor (PDGF), transforming growth factor beta (TGF-beta), vascular endothelial growth factor (VEGF) and insulin-like growth factor 1 (IGF-1)). The concentrated platelet solution is then injected directly into the damaged tendon. PRP is meant to deliver a concentrated dose of the body's own healing factors. In a 2010 trial of 54 people with chronic Achilles tendinopathy who were also doing eccentric exercises, tendon scores improved by 21.7 points after a PRP injection and by 20.5 points after a saline (salt-water) injection, with no meaningful difference between the two.
A larger 2021 trial of 240 adults at 24 sites compared one PRP injection with a sham needle that did not enter the tendon. Tendon scores at 6 months were 54.4 vs 53.4 out of 100, no meaningful difference, and injection-site discomfort was more common with PRP (97 vs 73 patients). The authors concluded that the findings do not support this treatment for chronic mid-portion Achilles tendinopathy.
Eccentric Exercises
Eccentric exercises (controlled lengthening of the muscle-tendon unit under load) are considered the gold standard exercise intervention for tendinopathy:
- Mechanism: Eccentric loading stimulates tendon remodeling by promoting aligned collagen fiber production and increasing tendon cross-sectional area. It also disrupts the abnormal neovascularization (new blood vessel and nerve growth) associated with tendinosis.
- Achilles tendinitis protocol: The Alfredson protocol involves performing eccentric heel drops (3 sets of 15 repetitions, twice daily) from the edge of a step. Success rates of 60-90% are commonly quoted for mid-portion Achilles tendinopathy. In Alfredson’s original 1998 study, a small non-randomized one, all 15 recreational athletes (average age 44) with long-standing Achilles pain were back to full running after 12 weeks, while all 15 conventionally treated comparison patients ended up having surgery.
- Tennis elbow protocol: The Tyler Twist using a rubber exercise bar, or eccentric wrist extensions with a light dumbbell (3 sets of 15 repetitions daily), are used for lateral epicondylitis. In the original randomized trial of 21 patients, adding the rubber-bar eccentric exercise to standard physical therapy improved disability scores by 76% vs 13% and pain by 81% vs 22%.
- Patellar tendinitis: Single-leg eccentric squats on a decline board (25-degree angle) are the standard protocol.
In these protocols the exercises are done slowly (taking 3-5 seconds per repetition); mild discomfort during the exercise is described as acceptable, lasting pain is not. Improvement typically occurs over 6-12 weeks of consistent daily practice.
Eccentric drops are not the only loading program studied. In a 2015 trial of 58 people with mid-portion Achilles tendinopathy, heavy slow resistance training (slow lifts with heavier loads, three times a week) for 12 weeks gave the same lasting improvement at 12 and 52 weeks as the eccentric program, and people completed more of their sessions (92% vs 78%).
Ergonomic Modifications
Addressing the environmental and biomechanical factors that contribute to tendinitis is essential for both treatment and prevention:
- Workstation setup: Monitor at eye level, elbows at 90 degrees, wrists in neutral position, feet flat on the floor. Ergonomic keyboards and mice are used to reduce strain on forearm tendons.
- Grip modification: Larger grip handles on tools and racquets reduce forearm tendon strain. Counterforce braces (tennis elbow straps) can reduce tension on the tendon origin.
- Footwear: Proper shoes with adequate arch support and cushioning. Running shoes are commonly replaced every 300-500 miles. Custom orthotics may be necessary for biomechanical imbalances contributing to Achilles or patellar tendinitis.
- Activity modification: Regular breaks during repetitive tasks (5 minutes every 30-60 minutes), alternating between different activities so that no tendon is loaded for long stretches, and a gradual increase in workload when returning to activity are the usual measures.
- Technique correction: Coaches and therapists work on movement patterns in sports and occupational tasks. Poor form is a leading contributor to tendinitis.
Tendon Nutrition and Blood Supply
Understanding tendon biology is crucial for effective naturopathic treatment:
- Blood supply: Tendons have relatively poor blood supply compared to muscles, which is why they heal slowly. The mid-portion of many tendons (such as the Achilles) is a "watershed zone" with particularly limited vascularity, making it vulnerable to degeneration and slow to recover.
- Collagen composition: Tendons are composed primarily of type I collagen (approximately 85% of dry weight), arranged in parallel fibers for maximum tensile strength. Collagen turnover in tendons is very slow. Earlier estimates of tendon protein half-life ranged from 2 months to 200 years. A 2013 study measured carbon-14 left in the body by the 1955-1963 nuclear bomb tests in 28 Achilles tendons: the tendon core matched the levels of roughly the first 17 years of life, showing that it is laid down while we grow and is essentially not renewed afterwards, unlike muscle, which renews continuously. This likely explains why tendons heal poorly.
- Nutritional support: Tendons require adequate protein intake (1.2-1.6 g/kg body weight daily), vitamin C, zinc, copper, and manganese for proper collagen synthesis and cross-linking. Silica (from horsetail herb or dietary sources) also supports connective tissue integrity.
- Hydration: Tendons are 60-70% water. Adequate hydration is essential for maintaining the proteoglycan matrix that gives tendons their viscoelastic properties and allows nutrient diffusion.
- Blood flow enhancement: Gentle, pain-free movement of the affected tendon promotes blood flow and nutrient delivery. Complete rest may actually slow healing by reducing an already limited blood supply.
Important Cautions
- Persistent tendon pain is a warning sign. Continuing to load an inflamed or degenerating tendon can lead to partial or complete tendon rupture, which may require surgical repair.
- Corticosteroid injections carry significant risks, including tendon weakening and rupture. Many clinicians do not inject the Achilles tendon or a tendon with a suspected partial tear. In the 2013 tennis elbow trial, recovery at 1 year was lower after a steroid injection than after a placebo injection (83% vs 96%) and recurrence was higher (54% vs 12%).
- Fluoroquinolone antibiotics (ciprofloxacin, levofloxacin, moxifloxacin) significantly increase tendon rupture risk, particularly in patients over 60 and those taking corticosteroids concurrently. The ciprofloxacin label lists previous tendon disorders as a risk factor, states that fluoroquinolones are to be avoided in people with a history of tendon disorders or tendinitis, and directs stopping the drug at the first pain, swelling or inflammation of a tendon.
- Bromelain and omega-3 supplements have mild blood-thinning properties. This matters most for people taking anticoagulant or antiplatelet medications and in the days before surgery.
- Dimethyl sulfoxide grade matters. Industrial-grade dimethyl sulfoxide may contain harmful impurities. Because dimethyl sulfoxide readily penetrates the skin and can carry other substances with it, topical medications or chemicals already on the skin can be carried into the body.
- Eccentric exercises may initially increase discomfort. Some mild discomfort during the exercise is described as acceptable; sharp pain or lasting soreness beyond 24 hours is taken as a sign that the load is too high.
- Signs of tendon rupture: a sudden pop or snap in a tendon, sudden inability to move a joint, or significant bruising and deformity may indicate a tendon rupture, which hospitals treat as urgent.
Key Research Papers
- Alfredson H, Pietilä T, Jonsson P, Lorentzon R. Heavy-load eccentric calf muscle training for the treatment of chronic Achilles tendinosis. American Journal of Sports Medicine. 1998;26(3):360-366. — PubMed PMID: 9617396
- Cook JL, Purdam CR. Is tendon pathology a continuum? A pathology model to explain the clinical presentation of load-induced tendinopathy. British Journal of Sports Medicine. 2009;43(6):409-416. — doi:10.1136/bjsm.2008.051193
- Khan KM, et al. Histopathology of common tendinopathies: update and implications for clinical management. Sports Medicine. 1999;27(6):393-408. — doi:10.2165/00007256-199927060-00004
- Nirschl RP, Ashman ES. Elbow tendinopathy: tennis elbow. Clinics in Sports Medicine. 2003;22(4):813-836. — doi:10.1016/s0278-5919(03)00051-6
- Tyler TF, Thomas GC, Nicholas SJ, McHugh MP. Addition of isolated wrist extensor eccentric exercise to standard treatment for chronic lateral epicondylosis: a prospective randomized trial. Journal of Shoulder and Elbow Surgery. 2010;19(6):917-922. — PubMed PMID: 20579907
- Maffulli N, et al. Tendon healing: can it be optimised? British Journal of Sports Medicine. 2002;36(5):315-316. — doi:10.1136/bjsm.36.5.315
- Coombes BK, et al. Effect of corticosteroid injection, physiotherapy, or both on clinical outcomes in patients with unilateral lateral epicondylalgia: a randomized controlled trial. JAMA. 2013;309(5):461-469. — doi:10.1001/jama.2013.129
- Bisset L, et al. Mobilisation with movement and exercise, corticosteroid injection, or wait and see for tennis elbow: randomised trial. BMJ. 2006;333(7575):939. — doi:10.1136/bmj.38961.584653.ae
- de Vos RJ, et al. Platelet-rich plasma injection for chronic Achilles tendinopathy: a randomized controlled trial. JAMA. 2010;303(2):144-149. — PubMed PMID: 20068208
- Malliaras P, et al. Patellar tendinopathy: clinical diagnosis, load management, and advice for challenging case presentations. Journal of Orthopaedic & Sports Physical Therapy. 2015;45(11):887-898. — doi:10.2519/jospt.2015.5987
- Shaw HM, Benjamin M. Structure-function relationships of entheses in relation to mechanical load and exercise. Scandinavian Journal of Medicine & Science in Sports. 2007;17(4):303-315. — doi:10.1111/j.1600-0838.2007.00689.x
- Millar NL, Silbernagel KG, Thorborg K, et al. Tendinopathy. Nature Reviews Disease Primers. 2021;7(1):1. — PubMed PMID: 33414454
- Kearney RS, Ji C, Warwick J, et al. Effect of Platelet-Rich Plasma Injection vs Sham Injection on Tendon Dysfunction in Patients With Chronic Midportion Achilles Tendinopathy: A Randomized Clinical Trial. JAMA. 2021;326(2):137-144. — PubMed PMID: 34255009
- Shaw G, Lee-Barthel A, Ross ML, et al. Vitamin C-enriched gelatin supplementation before intermittent activity augments collagen synthesis. American Journal of Clinical Nutrition. 2017;105(1):136-143. — PubMed PMID: 27852613
- Widrig R, Suter A, Saller R, Melzer J. Choosing between NSAID and arnica for topical treatment of hand osteoarthritis in a randomised, double-blind study. Rheumatology International. 2007;27(6):585-591. — PubMed PMID: 17318618
- Heinemeier KM, Schjerling P, Heinemeier J, et al. Lack of tissue renewal in human adult Achilles tendon is revealed by nuclear bomb (14)C. FASEB Journal. 2013;27(5):2074-2079. — PubMed PMID: 23401563
- Beyer R, Kongsgaard M, Hougs Kjær B, et al. Heavy Slow Resistance Versus Eccentric Training as Treatment for Achilles Tendinopathy: A Randomized Controlled Trial. American Journal of Sports Medicine. 2015;43(7):1704-1711. — PubMed PMID: 26018970
- Kneer W, Kühnau S, Bias P, Haag RF. [Dimethylsulfoxide (DMSO) gel in treatment of acute tendopathies. A multicenter, placebo-controlled, randomized study]. Fortschritte der Medizin. 1994;112(10):142-146. — PubMed PMID: 8194818
- Szczurko O, Cooley K, Mills EJ, et al. Naturopathic treatment of rotator cuff tendinitis among Canadian postal workers: a randomized controlled trial. Arthritis and Rheumatism. 2009;61(8):1037-1045. — PubMed PMID: 19644905
Historical Background
Tendon disorders have been recognized since antiquity, with Hippocrates describing tendon injuries around 400 BCE. The distinction between tendinitis (inflammatory) and tendinosis (degenerative) was clarified by Puddu and colleagues in 1976. Hakan Alfredson developed his landmark eccentric exercise protocol for Achilles tendinopathy in 1998, which transformed conservative treatment of tendon disorders.