Carpal Tunnel Syndrome
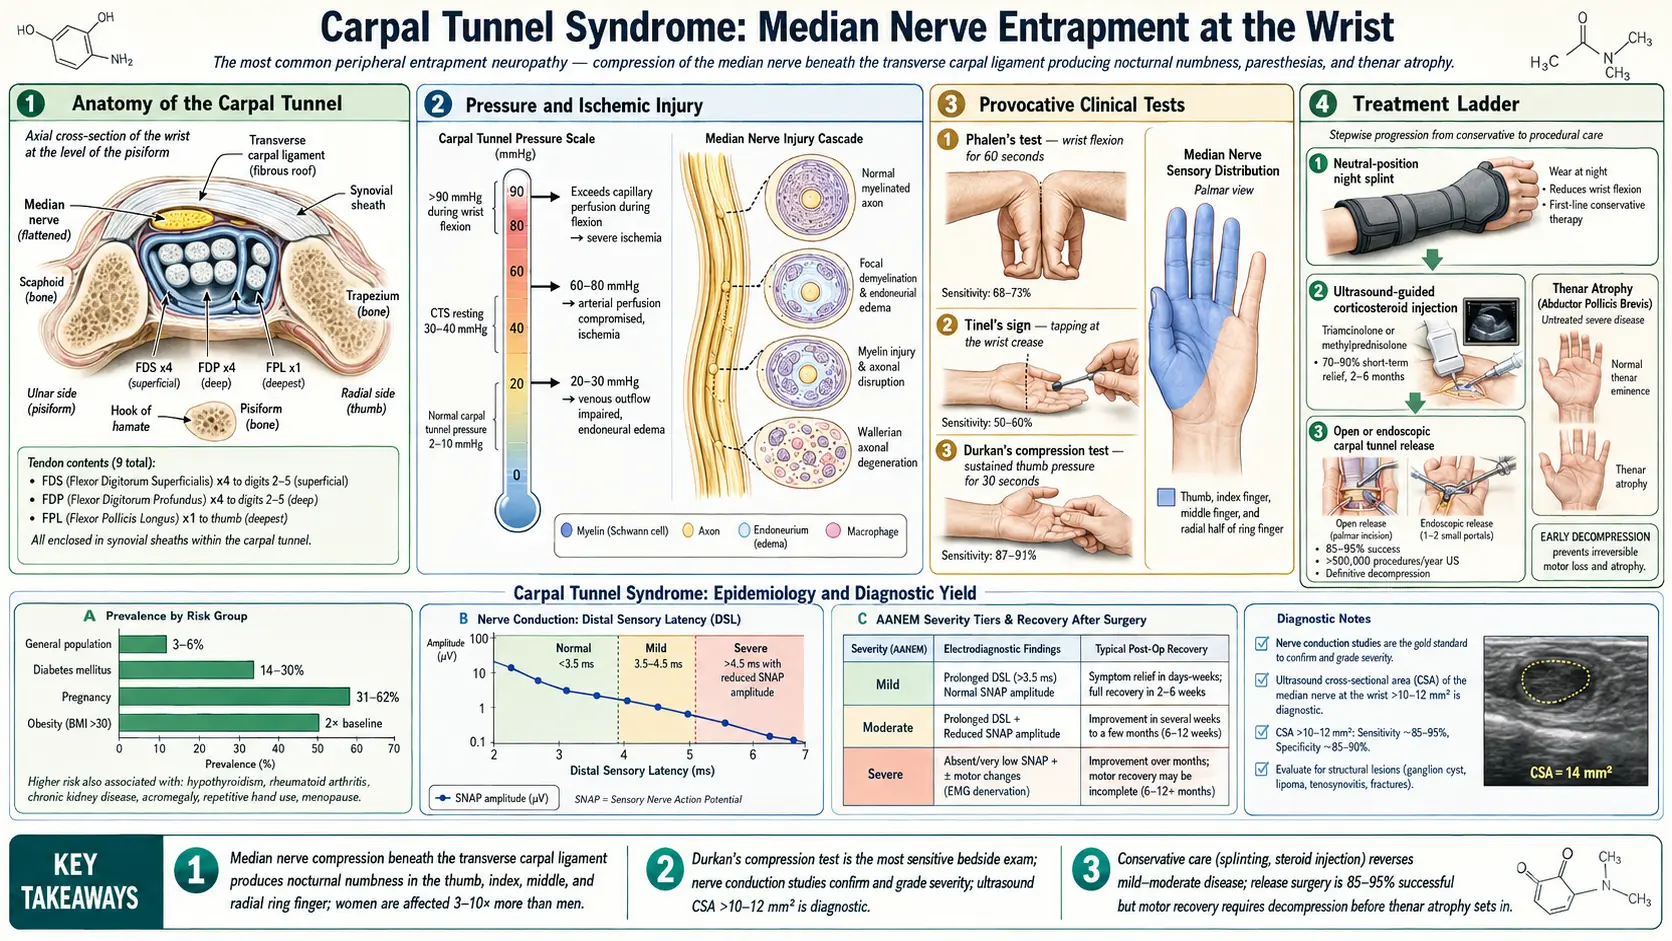
Table of Contents
1. Overview
Waking up in the middle of the night with a burning, tingling hand — and finding that shaking it vigorously makes it feel better — is the textbook story of carpal tunnel syndrome (CTS). It is the most common peripheral nerve entrapment neuropathy in the world, affecting an estimated 3–6% of the general adult population, and it is responsible for more lost work days than almost any other upper-extremity condition. Despite its prevalence, it is still frequently dismissed or delayed in diagnosis because the early symptoms of tingling and nocturnal numbness are easy to attribute to poor sleeping position or "overuse."
Carpal tunnel syndrome occurs when the median nerve is compressed as it travels through the carpal tunnel — a narrow, rigid passageway at the wrist formed by the carpal bones on three sides and the transverse carpal ligament (flexor retinaculum) on the fourth. Because there is no give in that bony and ligamentous channel, any increase in tissue volume within the tunnel — from tendon sheath swelling, fluid retention, arthritic spurs, or any of a dozen other causes — compresses the median nerve and produces the characteristic constellation of symptoms in the thumb, index, middle, and radial half of the ring finger.
The good news is that effective treatments exist at every stage of severity: splinting and injections for mild to moderate cases, and a brief surgical procedure (carpal tunnel release) that is one of the most consistently successful operations in all of medicine for moderate-to-severe or treatment-refractory disease.
2. Epidemiology
Carpal tunnel syndrome is a disease of working-age adults, with peak incidence in the fourth through sixth decades of life. Women are affected two to three times more often than men, a gap that reflects the smaller baseline carpal tunnel dimensions in women, hormonal influences on connective tissue and fluid balance, and the greater prevalence of predisposing conditions such as hypothyroidism and rheumatoid arthritis. Annual incidence in the US is estimated at approximately 3.4 per 1,000 person-years, with prevalence of 50–100 per 1,000 in working populations. Measured figures: a survey of 2,466 people in southern Sweden found 3.8% had clinically certain carpal tunnel syndrome and 2.7% had carpal tunnel syndrome confirmed both on examination and by nerve testing. Six pooled studies of US workers (4,321 people) found 7.8% had carpal tunnel syndrome at enrollment and 2.3 new cases per 100 person-years of follow-up.
Occupational associations are well documented. Jobs involving sustained or repetitive wrist flexion and extension, sustained grip or pinch, or hand-arm vibration — assembly-line work, meat packing, keyboard-intensive work, dentistry, carpentry — are associated with elevated carpal tunnel syndrome rates. However, the relationship between office keyboard use and carpal tunnel syndrome is actually weaker than popular belief suggests; typing at neutral wrist postures does not substantially increase pressure in the carpal tunnel at typical workloads. A meta-analysis found that among office workers, carpal tunnel syndrome was linked to computer use (odds ratio 1.34) and mouse use (odds ratio 1.93); its authors concluded that excessive computer use, particularly of a mouse, might be a minor occupational risk factor.
3. Anatomy of the Carpal Tunnel
The carpal tunnel is a rigid fibro-osseous canal at the base of the palm. Its floor and walls are formed by the carpal bones arranged in a concave arch: the scaphoid and trapezium radially, the hamate and pisiform ulnarly. The roof is the transverse carpal ligament (TCL), a thick fibrous band stretching between the medial and lateral bony prominences. This channel cannot expand in response to increased internal pressure — unlike fascial compartments elsewhere in the body, there is essentially no compliance.
The tunnel contains the median nerve and nine flexor tendons (the four flexor digitorum superficialis, four flexor digitorum profundus, and flexor pollicis longus tendons, each enclosed in their synovial sheaths). Normal carpal tunnel pressure is approximately 2–10 mmHg at rest. With wrist flexion or extension, pressure can spike to 30–90 mmHg; in patients with carpal tunnel syndrome, these pressures are substantially higher, impairing epineural blood flow and axonal transport within the nerve.
The median nerve provides sensory innervation to the palmar surface of the thumb, index, middle, and radial half of the ring finger, and motor innervation to the thenar muscles (abductor pollicis brevis, opponens pollicis, and the superficial head of flexor pollicis brevis). The abductor pollicis brevis is particularly important because thenar wasting — visible hollowing at the base of the thumb — indicates chronic, severe nerve compression that may not fully reverse even after surgical decompression.
4. Causes and Risk Factors
Carpal tunnel syndrome is caused by anything that increases pressure within the carpal tunnel or decreases the nerve's tolerance for compression. The most important predisposing conditions include:
- Hypothyroidism — glycosaminoglycan deposits in the tendons and connective tissue enlarge the tunnel contents. Carpal tunnel syndrome is present in 7–30% of hypothyroid patients and may be the presenting complaint before a thyroid diagnosis is established. Treating the hypothyroidism often improves carpal tunnel syndrome symptoms without other intervention. A meta-analysis of 18 studies found only a modest association once confounders were controlled for (effect size 1.44), with evidence of publication bias.
- Diabetes mellitus — peripheral neuropathy increases median nerve vulnerability to compression; the two conditions often co-exist. The "double crush hypothesis" describes one nerve under stress at two points along its length — here, the nerve damage of diabetes plus the pressure at the wrist. Diabetic patients have higher failure rates with conservative management.
- Pregnancy — fluid retention raises tunnel pressure. A systematic review reported carpal tunnel syndrome in 31–62% of pregnant women when diagnosed clinically and 7–43% when confirmed by nerve testing; in a Dutch study of 639 women, 34% reported symptoms. It typically develops in the second and third trimesters. Symptoms ease after delivery in some women but persist in many (see Pregnancy-associated carpal tunnel syndrome below), and conservative management is the usual approach during pregnancy.
- Rheumatoid arthritis — tenosynovial inflammation directly within the tunnel physically crowds the median nerve.
- Obesity — body mass index (BMI) is a significant independent risk factor; increased adiposity and higher fluid retention contribute to elevated tunnel pressure.
- Repetitive wrist use — sustained wrist postures in flexion or extension, particularly combined with forceful gripping, increase intracanal pressure and tendon sheath swelling.
- Acromegaly, amyloidosis, wrist fractures (especially distal radius fractures with carpal displacement), and space-occupying lesions (ganglia, lipomas) are less common but important causes in specific clinical contexts.
5. Clinical Presentation
The symptom pattern of carpal tunnel syndrome is distinctive enough that an experienced clinician can suspect the diagnosis strongly from the history alone, before any physical examination test or imaging is performed.
Sensory symptoms
The cardinal presenting symptoms are nocturnal paresthesias — tingling, numbness, or burning in the median nerve distribution (thumb, index, middle, radial ring finger) that wake the patient from sleep. This nocturnal predominance is thought to result from sustained wrist flexion during sleep, which maximizes carpal tunnel pressure, combined with the reduction in protective postural adjustments that occur during wakefulness. Patients characteristically describe shaking or "flicking" the wrist and hand to relieve symptoms — this is so specific to carpal tunnel syndrome that it was given a formal name, the flick sign, and has high diagnostic specificity.
As the condition progresses, daytime symptoms develop: tingling with sustained gripping (driving, holding a phone or book), difficulty with fine motor tasks (buttoning, handling coins), and dropping objects unexpectedly. Some patients describe the entire hand feeling numb, but careful questioning usually reveals the symptoms spare the little finger and ulnar half of the ring finger (ulnar nerve territory) — an important distinguishing feature.
Motor symptoms and thenar wasting
Weakness of thumb opposition and abduction develops in moderate to severe carpal tunnel syndrome. Thenar wasting — visible flattening or hollowing of the thenar eminence at the base of the thumb — indicates prolonged severe compression with axonal loss. At this stage, permanent motor deficit can occur even after successful decompression, making early intervention important for patients showing any motor involvement.
6. Diagnosis and Special Tests
Clinical examination tests
- Phalen's test. The patient holds both wrists in sustained maximum flexion (elbows extended, backs of hands touching) for 60 seconds. Onset of median nerve paresthesias within 60 seconds is positive. Sensitivity approximately 68–75%, specificity 47–80%.
- Tinel's sign. The examiner taps or percusses lightly over the median nerve at the wrist crease. A positive result is tingling or paresthesias radiating distally into the median nerve distribution. Sensitivity approximately 50–62%, specificity 55–77%.
- Durkan's (carpal compression) test. Direct thumb pressure over the carpal tunnel for 30 seconds reproducing symptoms; sensitivity approximately 87%, specificity 90% — somewhat better than either Phalen's or Tinel's in isolation.
- Thenar atrophy assessment. Wasting of the abductor pollicis brevis is a late finding indicating significant axonal loss and often prompts urgent surgical consideration.
Electrodiagnostic studies (nerve conduction and electromyography)
Nerve conduction studies (NCS) and electromyography (EMG) are the gold standard for objective confirmation of carpal tunnel syndrome diagnosis and severity grading. Key findings:
- Sensory nerve conduction testing is the most sensitive. Prolonged sensory latencies or reduced sensory nerve action potential (SNAP) amplitudes across the wrist are the earliest electrodiagnostic abnormality in carpal tunnel syndrome, detectable before motor changes.
- Distal motor latency >4.5 ms to the abductor pollicis brevis indicates significant median motor conduction slowing.
- Electromyography denervation changes (fibrillations, positive sharp waves) in thenar muscles indicate axonal loss and predict less complete recovery after decompression.
Electrodiagnostic severity grading (mild: sensory only; moderate: sensory + motor slowing without axonal loss; severe: axonal loss/denervation) guides prognosis and surgical urgency. Importantly, a mildly abnormal nerve conduction study in an asymptomatic individual does not warrant treatment; conversely, a patient with classic clinical carpal tunnel syndrome but a normal nerve conduction study may still have the condition — test sensitivity is approximately 85% for confirmed clinical carpal tunnel syndrome. The three grades above are a simple summary: a 2026 consensus guideline from the American Association of Neuromuscular and Electrodiagnostic Medicine counted 12 published severity scales and recommended one of them, the Bland neurophysiologic grading system, so that laboratories grade severity the same way.
7. Conservative Treatment
Wrist splinting
Neutral-position wrist splinting is the usual first treatment offered for mild-to-moderate carpal tunnel syndrome. Splinting the wrist in a neutral position (0–15 degrees of extension) prevents the extreme flexion and extension postures that maximally elevate intracanal pressure. Nocturnal splinting is most important because it addresses the most common and disabling symptom. Full-time splinting adds daytime benefit but reduces compliance in working patients. A 2023 Cochrane review (29 trials, 1,937 adults) found that splinting, compared with no active treatment, may provide little or no benefit in symptoms in the short term (0.37 points better on a 1–5 scale where about 1 point is the smallest change people notice), concluded there is insufficient evidence to say whether splinting benefits people with carpal tunnel syndrome, and added that small effects could still justify a cheap treatment with no plausible long-term harm. One small trial (80 people) suggested a greater chance of overall improvement with night splints. In a randomized trial of 234 adults, a single corticosteroid injection beat a night splint at 6 weeks (adjusted difference −0.32, p = 0.0001), with no significant difference at 12 or 24 months.
Corticosteroid injection
Injection of a corticosteroid (typically triamcinolone 40 mg or methylprednisolone 40 mg, combined with local anesthetic) into the carpal tunnel reduces tenosynovial swelling and provides meaningful symptom relief in 70–90% of patients. Duration of effect is limited: most patients experience benefit for 1–3 months, with approximately 50% maintaining relief at 6 months and declining benefit beyond 1 year. Injection is most useful to confirm the diagnosis, provide temporary relief during pregnancy (when surgery is deferred), or bridge patients to surgery.
Trial numbers: in a Swedish placebo-controlled trial (37 patients in each group, all with failed splinting), methylprednisolone 80 mg and 40 mg beat placebo at 10 weeks but not at 1 year, and 73%, 81% and 92% respectively had surgery within a year. In the 234-person trial above, 24 months after an injection or a night splint there was no significant difference in scores, and 22% versus 16% had undergone surgery.
Activity modification
Practitioners describe limiting sustained wrist flexion, reducing forceful grip, changing keyboard workstation ergonomics and taking regular breaks as ways to reduce symptom burden in occupation-related carpal tunnel syndrome. These measures are described as adjuncts, not substitutes for primary treatment in moderate-to-severe disease.
Vitamin B6
In a small randomized trial (40 patients with mild to moderate carpal tunnel syndrome, compared with a splint alone, no placebo), vitamin B6 at 120 mg a day for 3 months plus a splint improved night waking, pain, numbness, tingling and clumsiness, and sensory nerve test results; the splint-only group improved only on two hand tasks. That dose is above the US Tolerable Upper Intake Level for adults, 100 mg a day, which the National Academies set because of sensory nerve damage (neuropathy) reported at high long-term intakes.
Nerve-pain pills (gabapentinoids)
A 2025 systematic review found these pills probably do not improve carpal tunnel syndrome symptoms: 0.08 points better than placebo on a 1–5 scale at 8 weeks (two studies, 286 people). They probably cause more tiredness (risk ratio 1.67) and may cause more dizziness.
Ultrasound-guided fluid injection around the nerve (hydrodissection)
A 2025 network meta-analysis of 9 studies (458 patients) ranked 5% dextrose highest for hand function at 4, 12 and 24 weeks and for symptoms at 4 weeks, and platelet-rich plasma highest for symptoms at 12 and 24 weeks. The authors state that more research is needed to establish exact protocols.
8. Surgical Treatment
Carpal tunnel release (CTR) — surgical division of the transverse carpal ligament — is one of the most performed and most consistently successful operations in orthopedic and hand surgery, with patient satisfaction rates exceeding 90% in appropriately selected patients. Surgery is indicated for moderate-to-severe carpal tunnel syndrome that has failed 6–12 weeks of conservative management, for severe carpal tunnel syndrome with thenar wasting or electromyography denervation (urgent indication to prevent permanent motor loss), for carpal tunnel syndrome with constant numbness, and by patient preference after failed conservative measures.
Open versus endoscopic release
Two surgical techniques are used:
- Open carpal tunnel release — a 3–5 cm incision in the palm allows direct visualization of the transverse carpal ligament throughout its length before division. The traditional approach, highly reliable, and preferred for revision cases or complex anatomy. Main limitation: palmar scar tenderness ("pillar pain") lasting 2–4 months post-operatively.
- Endoscopic carpal tunnel release — one or two small wrist/palm incisions with a camera allow transverse carpal ligament division under visualization without opening the full palm. Earlier return to work or daily activities (a 2014 Cochrane review of 28 studies and 2,586 hands found about 8 days earlier than open release, on low-quality evidence), less palmar scar tenderness. Equivalent long-term outcomes to open carpal tunnel release in meta-analyses, with a marginally higher risk of incomplete release in learning-curve surgeons.
- Ultrasound-guided thread release — a newer incision-free method that cuts the ligament with a thread under ultrasound. In a 2025 randomized same-patient study of 11 people (one hand each way), function, pain and strength over 12 months matched mini-open surgery, and all but one preferred the thread side, citing quicker recovery and less pain.
Surgery compared with non-surgical treatment
A 2024 Cochrane review (14 trials, 1,231 people), updating the 2008 review, found that in the long term surgery probably gives a higher rate of clinical improvement than splinting (risk ratio 2.10) but probably does not provide a clinically important benefit in symptoms or hand function. It was uncertain whether improvement or symptom relief differs between surgery and corticosteroid injection. Surgery probably lowers the chance of further surgery: 41 of 93 people (44%) in the splint groups were referred for surgery, while none of 83 repeated it after surgery. The reviewers call the efficacy of surgery unclear and describe the decision as balancing small benefits against potential risks.
In a randomized trial of injection versus surgery (163 wrists), the authors report injection was as effective as surgery at 1 year, with an added benefit from surgery at 2 years. Over a mean follow-up of 6.3 years, 11.6% of the surgery group versus 41.8% of the injection group needed a new treatment, so about 58% of the injection group needed nothing further.
Recovery
Most patients notice immediate improvement in nocturnal paresthesias after surgery, even before the wound heals. Full recovery of sensation and grip strength typically takes 3–6 months. Thenar wasting reverses partially but may not fully resolve in longstanding severe cases. Return to light activities in 1–2 weeks; heavy manual labor in 4–6 weeks. Recurrence after carpal tunnel release is uncommon (<1% per year after initial success).
9. Outcomes and Special Populations
Pregnancy-associated carpal tunnel syndrome
Carpal tunnel syndrome during pregnancy is managed conservatively with neutral wrist splinting as first-line treatment. Corticosteroid injection is used cautiously for severe or disabling symptoms. Symptoms ease in some women after delivery as fluid retention and hormonal changes normalize, but a systematic review found symptoms persisted in more than 50% of patients after 1 year and in about 30% after 3 years. In an Italian study of 63 women, 54% still had symptoms a year later, and those whose symptoms began early in pregnancy were less likely to improve. Surgery during pregnancy is reserved for patients with progressive motor weakness or permanent sensory loss.
Diabetic carpal tunnel syndrome
Carpal tunnel syndrome in diabetic patients has higher rates of bilateral involvement, higher pre-operative nerve conduction severity, and slower post-operative recovery. Glucose control does not reliably reverse established carpal tunnel syndrome but is an important modifier of peripheral nerve health. Surgical outcomes are generally good, though complete sensory recovery may be less complete than in non-diabetic patients.
Recurrence
True anatomic recurrence after complete carpal tunnel release (reformation of the transverse carpal ligament) is rare. More common is persistent or recurrent symptoms from incomplete initial release, tenosynovial proliferation around an intact ulnar portion of the ligament, or development of perineural fibrosis. Revision surgery has lower success rates than primary release and is performed by hand surgery specialists.
Key Research Papers
- Chesterton LS, Blagojevic-Bucknall M, Burton C, et al. The clinical and cost-effectiveness of corticosteroid injection versus night splints for carpal tunnel syndrome (INSTINCTS trial): an open-label, parallel group, randomised controlled trial. Lancet. 2018;392(10156):1423–1433. — PubMed PMID: 30343858 — RCT of corticosteroid injection vs. splinting for carpal tunnel syndrome; injection superior short-term, outcomes converge at 1 year.
- Burton C, Rathod-Mistry T, Blackburn S, et al. The effectiveness of corticosteroid injection versus night splints for carpal tunnel syndrome: 24-month follow-up of a randomized trial. Rheumatology (Oxford). 2023;62(2):546–554. — PubMed PMID: 35394019
- Vasiliadis HS, Georgoulas P, Shrier I, Salanti G, Scholten RJ. Endoscopic release for carpal tunnel syndrome. Cochrane Database Syst Rev. 2014;(1):CD008265. — PubMed PMID: 24482073 — Cochrane review: endoscopic vs. open carpal tunnel release; equivalent long-term outcomes, faster early functional recovery endoscopic.
- Verdugo RJ, Salinas RA, Castillo JL, Cea JG. Surgical versus non-surgical treatment for carpal tunnel syndrome. Cochrane Database Syst Rev. 2008;(4):CD001552. — PubMed PMID: 18843618 — Cochrane review: surgical vs. non-surgical for carpal tunnel syndrome; concluded surgery relieves symptoms significantly better than splinting. Updated in 2024 (next entry).
- Lusa V, Karjalainen TV, Pääkkönen M, Rajamäki TJ, Jaatinen K. Surgical versus non-surgical treatment for carpal tunnel syndrome. Cochrane Database Syst Rev. 2024;1(1):CD001552. — PubMed PMID: 38189479
- Ly-Pen D, Andreu JL, Millán I, de Blas G, Sánchez-Olaso A. Long-term outcome of local steroid injections versus surgery in carpal tunnel syndrome: observational extension of a randomized clinical trial. Hand (N Y). 2022;17(4):639–645. — PubMed PMID: 32757777 — Long-term outcomes: corticosteroid injection vs. surgical decompression; as effective at 1 year, surgery better at 2 years and over a mean of 6.3 years.
- Atroshi I, Gummesson C, Johnsson R, Ornstein E, Ranstam J, Rosén I. Prevalence of carpal tunnel syndrome in a general population. JAMA. 1999;282(2):153–158. — PubMed PMID: 10411196 — Prevalence of carpal tunnel syndrome in the general population; 3.8% clinically certain, 2.7% clinically and electrophysiologically confirmed.
- Aroori S, Spence RA. Carpal tunnel syndrome. Ulster Med J. 2008;77(1):6–17. — PubMed PMID: 18269111 — Comprehensive review of carpal tunnel syndrome pathophysiology, diagnosis, and management; widely cited overview article.
- Padua L, Di Pasquale A, Pazzaglia C, Liotta GA, Librante A, Mondelli M. Systematic review of pregnancy-related carpal tunnel syndrome. Muscle Nerve. 2010;42(5):697–702. — PubMed PMID: 20976778 — Prevalence of carpal tunnel syndrome during pregnancy: systematic review; 31–62% clinically diagnosed, 7–43% neurophysiologically confirmed.
- Karjalainen TV, Lusa V, Page MJ, O'Connor D, Massy-Westropp N, Peters SE. Splinting for carpal tunnel syndrome. Cochrane Database Syst Rev. 2023;2(2):CD010003. — PubMed PMID: 36848651
- Atroshi I, Flondell M, Hofer M, Ranstam J. Methylprednisolone injections for the carpal tunnel syndrome: a randomized, placebo-controlled trial. Ann Intern Med. 2013;159(5):309–317. — PubMed PMID: 24026316
- Padua L, Aprile I, Caliandro P, et al. Carpal tunnel syndrome in pregnancy: multiperspective follow-up of untreated cases. Neurology. 2002;59(10):1643–1646. — PubMed PMID: 12451216
- Meems M, Truijens S, Spek V, Visser LH, Pop VJ. Prevalence, course and determinants of carpal tunnel syndrome symptoms during pregnancy: a prospective study. BJOG. 2015;122(8):1112–1118. — PubMed PMID: 25778497
- Shiri R. Hypothyroidism and carpal tunnel syndrome: a meta-analysis. Muscle Nerve. 2014;50(6):879–883. — PubMed PMID: 25204641
- Dale AM, Harris-Adamson C, Rempel D, et al. Prevalence and incidence of carpal tunnel syndrome in US working populations: pooled analysis of six prospective studies. Scand J Work Environ Health. 2013;39(5):495–505. — PubMed PMID: 23423472
- Shiri R, Falah-Hassani K. Computer use and carpal tunnel syndrome: a meta-analysis. J Neurol Sci. 2015;349(1–2):15–19. — PubMed PMID: 25582979
- Robinson LR, Al-Lawati ZJ, Andary M, et al. AANEM consensus-based guideline for grading the severity of carpal tunnel syndrome. Muscle Nerve. 2026 (online ahead of print). — PubMed PMID: 42728830
- Raatikainen S, Jaatinen K, Karjalainen T, Lusa V. Efficacy and safety of gabapentinoids in the treatment of carpal tunnel syndrome: a systematic review and meta-analysis. J Hand Surg Asian Pac Vol. 2025;30(3):243–253. — PubMed PMID: 39963092
- Talebi M, Andalib S, Bakhti S, Ayromlou H, Aghili A, Talebi A. Effect of vitamin B6 on clinical symptoms and electrodiagnostic results of patients with carpal tunnel syndrome. Adv Pharm Bull. 2013;3(2):283–288. — PubMed PMID: 24312849
- Lee K, Park JM, Yoon SY, et al. Ultrasound-guided nerve hydrodissection for the management of carpal tunnel syndrome: a systematic review and network meta-analysis. Yonsei Med J. 2025;66(2):111–120. — PubMed PMID: 39894044
- Meaike JJ, Hasley IB, Brault JS, Shin AY. Prospective, randomized, intra-subject controlled trial comparing ultrasound-guided thread and mini-open carpal tunnel release. J Surg Orthop Adv. 2025;34(1):31–36. — PubMed PMID: 40327736
- Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (Vitamin B6 chapter). Washington, DC: National Academies Press; 1998. — National Academies Press
- Carpal tunnel syndrome and hypothyroidism — PubMed search — Association between thyroid dysfunction and carpal tunnel syndrome.
- Carpal tunnel syndrome and diabetes double-crush — PubMed search — Interaction between peripheral neuropathy and entrapment in diabetic patients.
- Nerve conduction and electromyography diagnosis of carpal tunnel syndrome — PubMed search — Sensitivity and specificity of electrodiagnostic criteria.
- Wrist splinting for nocturnal carpal tunnel syndrome — PubMed search — Efficacy of neutral-position splinting for symptom control.
PubMed Topic Searches
The links below run live searches on PubMed, the U.S. National Library of Medicine's database of biomedical literature.
- PubMed: Carpal tunnel syndrome treatment outcomes
- PubMed: Carpal tunnel release surgery
- PubMed: Median nerve conduction and electromyography diagnosis
- PubMed: Carpal tunnel syndrome wrist splinting conservative
- PubMed: Carpal tunnel corticosteroid injection
- PubMed: Carpal tunnel syndrome in pregnancy
- PubMed: Carpal tunnel syndrome and diabetes neuropathy
- PubMed: Carpal tunnel syndrome and hypothyroidism
- PubMed: Endoscopic vs open carpal tunnel release
- PubMed: Carpal tunnel syndrome recurrence and revision surgery
- PubMed: Phalen Tinel test sensitivity specificity
- PubMed: Carpal tunnel syndrome occupational risk factors
Connections
- Orthopedics
- Tendinitis — repetitive-use tendon inflammation that co-occurs with carpal tunnel syndrome in many occupational settings.
- Rotator Cuff Tear — another upper-extremity condition; double-crush neuropathy can involve cervical and peripheral components.
- Hypothyroidism — a predisposing condition for carpal tunnel syndrome via glycosaminoglycan deposits in the tunnel (a meta-analysis found a modest association after controlling for confounders); treatment often relieves carpal tunnel syndrome.
- Diabetes — peripheral neuropathy increases median nerve vulnerability; diabetic carpal tunnel syndrome has higher treatment failure rates.
- Rheumatoid Arthritis — tenosynovial inflammation within the carpal tunnel directly compresses the median nerve.
- Peripheral Neuropathy — overlapping symptoms; electrodiagnostic studies distinguish carpal tunnel syndrome from diffuse neuropathy.
- All Conditions — complete disease index.