⚠ Evidence warning: Clinical trials or other evidence do not support the claim that treating sleep apnea brings people with fibromyalgia their biggest improvement. This page keeps it as a report of what people, websites or other media say.
Sleep and Non-Restorative Sleep in Fibromyalgia
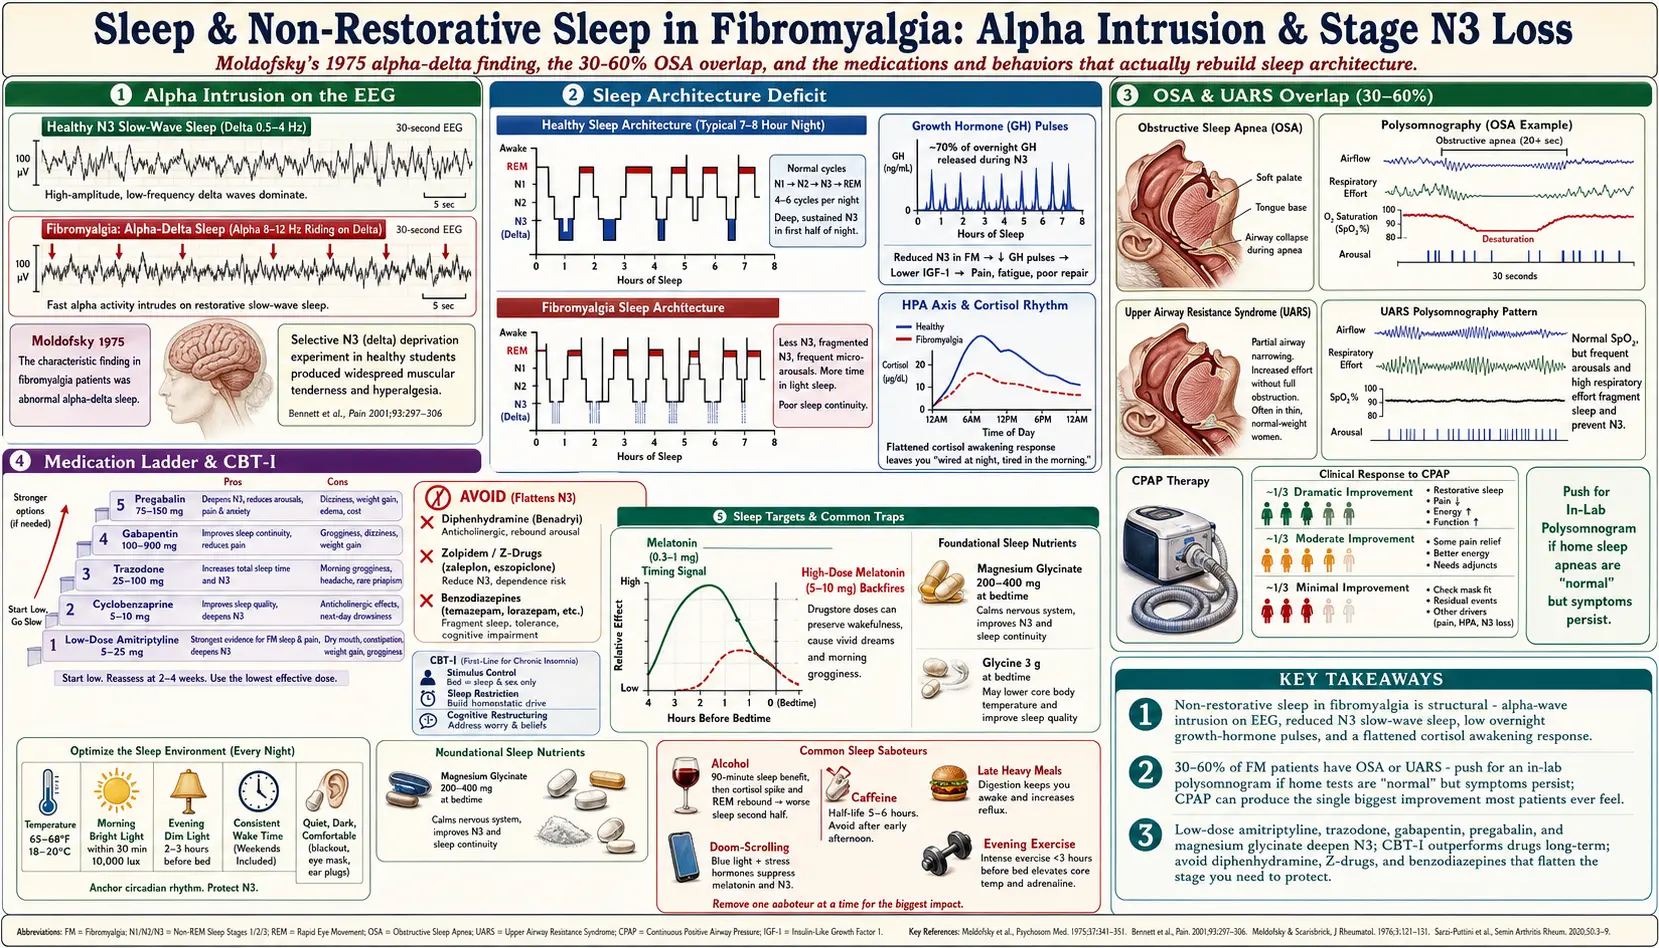
Table of Contents
- What “Non-Restorative Sleep” Actually Means
- Moldofsky and the Alpha-Intrusion Finding
- The Stage N3 (Slow-Wave) Deficit
- Hypothalamic-Pituitary-Adrenal Axis, Growth Hormone, and Why You Wake Up Sore
- Who Gets a Sleep Study and What It Shows
- OSA, UARS, and the 30–60% Overlap
- Restless Legs and PLMD
- CPAP When Indicated
- Bedtime Protocol: Light, Temperature, Schedule
- Medication Options — Pros, Cons, Dosing
- Why Melatonin Alone Rarely Fixes It — and Where Magnesium Glycinate Fits
- Cognitive Behavioral Therapy for Insomnia: The Treatment Nobody Offers You
- Common Traps: Alcohol, Late Caffeine, Doom-Scrolling
- Key Research Papers
- Connections
- Featured Videos
What “Non-Restorative Sleep” Actually Means
If you have fibromyalgia, you already know the pattern. You go to bed tired. You fall asleep — maybe quickly, maybe after an hour of staring at the ceiling. You might sleep eight hours by the clock. And you wake up feeling as if you have been run over by a truck. Stiff. Foggy. Somehow more exhausted than when you lay down.
That is non-restorative sleep. It is not the same as insomnia, although the two often coexist. Insomnia is a problem of quantity — you cannot get enough hours. Non-restorative sleep is a problem of quality — the hours are there, but the repair work that sleep is supposed to do never happens. Roughly 90% of fibromyalgia patients report this symptom, and in the ACR 2016 diagnostic criteria, non-restorative sleep is not a side effect of the disease. It is one of the core features used to diagnose it.
This article is about why sleep breaks in fibromyalgia, how to figure out which flavor of broken you have, and what actually helps — not just platitudes about “good sleep hygiene.” If you have been told to “try melatonin and a warm bath,” you already know that advice rarely moves the needle. There is more to it than that.
Moldofsky and the Alpha-Intrusion Finding
In 1975, a Canadian sleep researcher named Harvey Moldofsky published one of the most influential fibromyalgia papers ever written. He hooked up patients with what was then called “fibrositis” to electroencephalogram (EEG) machines overnight and discovered something strange. During deep sleep — the phase where brain waves should be slow and rolling, like ocean swells — their EEGs showed a faster, jagged wave pattern riding on top. That faster rhythm, around 8–12 Hz, is called the alpha rhythm, and it belongs to quiet wakefulness, not deep sleep.
Moldofsky called this alpha-delta sleep or alpha intrusion: the waking brain refusing to let go even while the body was, by every other measure, asleep. Then he did something even more striking. He deprived healthy subjects of stage 4 sleep (the deepest sleep, now counted as part of stage N3) using an external arousing stimulus. Those healthy volunteers temporarily developed musculoskeletal and mood symptoms comparable to the symptoms seen chronically in the patients.
That experiment is the foundation of the idea that in fibromyalgia, disordered deep sleep is not just a symptom — it is part of what drives the pain. Fifty years later, the mechanism has been refined and re-interpreted many times, and later work has not settled it: a 2015 systematic review of 42 studies concluded that “Current evidence cannot confirm the role played by sleep physiology in the pathogenesis or maintenance” of fibromyalgia symptoms, while finding it clear that sleep disturbances are present.
The Stage N3 (Slow-Wave) Deficit
Sleep comes in stages. Stage N1 is the drowsy edge as you drift off. N2 is light sleep, about half your night. N3 is slow-wave sleep — the deepest, most physically restorative phase. REM is the dreaming phase. You cycle through these roughly every 90 minutes, and most of your N3 happens in the first third of the night.
Polysomnography studies often report that fibromyalgia patients get less N3, more fragmented N3, and more micro-arousals (brief wake-ups so short you do not remember them), though not every study agrees. A 2017 meta-analysis of 19 sleep-study comparisons found a lower percentage of slow-wave sleep than in healthy controls (effect size g = −0.66), and more time awake after falling asleep. A 2015 systematic review found patients’ sleep less efficient, lighter and more fragmented, but added that “The evidence of a FMS signature on objective measures of sleep is inconsistent”, as most studies lacked statistical power. Roizenblatt and colleagues, in a 2001 study of 40 women in Arthritis & Rheumatism, documented three alpha-intrusion patterns and found that the phasic pattern correlated best with clinical symptoms, including worse pain after sleep. The worse the sleep architecture, the worse the daytime symptoms.
Why does this matter? Because N3 is when a long list of maintenance jobs happens: the glymphatic system flushes metabolic waste from the brain, the immune system regulates inflammatory cytokines, muscles repair micro-damage, and the pituitary releases the majority of your growth hormone pulse. Miss enough N3 and every one of those jobs falls behind. That is, in plain language, why you wake up feeling like you did not sleep at all.
Hypothalamic-Pituitary-Adrenal Axis, Growth Hormone, and Why You Wake Up Sore
Two hormonal systems take the biggest hit when deep sleep is disrupted.
Growth hormone (GH). About 70% of your daily GH is released in pulses during N3. In adults, growth hormone is not about getting taller — it drives tissue repair, collagen turnover, and insulin-like growth factor 1 (IGF-1) production. Fibromyalgia patients have measurably lower insulin-like growth factor 1 levels on average, consistent with chronic GH under-secretion. That is a plausible reason why minor exertion leaves you sore for days: the overnight repair cycle is running on a fraction of its normal output.
Hypothalamic-pituitary-adrenal (HPA) axis. This is your stress-and-cortisol system. Normally cortisol bottoms out around midnight and surges just before you wake — the cortisol awakening response. In fibromyalgia, the findings on this system are inconsistent. Two studies of women in a controlled hospital-hotel setting found lower cortisol than in healthy controls; the first describes “generally lower cortisol values, most pronounced upon awakening”, which fits the “tired” morning people describe. People with fibromyalgia describe the result as wired at bedtime, exhausted at 9 a.m.
You cannot fix either of these systems by willpower. You can influence them by protecting whatever N3 you still have, treating any co-existing sleep disorder that fragments it further, and using medications or routines that deepen sleep architecture rather than just knocking you unconscious.
Who Gets a Sleep Study and What It Shows
Many fibromyalgia patients go years without a formal sleep evaluation because the fatigue gets put down to “the fibro.” These are the signs on top of non-restorative sleep that sleep clinics treat as reasons for a sleep study (polysomnogram, or PSG):
- Loud snoring, witnessed pauses in breathing, or gasping awake.
- Morning headaches that fade through the day.
- Dry mouth or sore throat every morning.
- High blood pressure that is hard to control.
- A neck circumference over 16 inches (women) or 17 inches (men).
- Body mass index (BMI) over 30 — although thin patients get OSA too.
- Kicking or jerking legs that your partner notices.
- Daytime sleepiness severe enough to nod off while driving, reading, or in meetings.
Home sleep apnea tests are cheaper and more convenient, but they can miss upper airway resistance syndrome (UARS) and central apneas. So a “normal” home test does not rule these out when symptoms persist; an in-lab polysomnogram is the test that can catch them. The lab study captures electroencephalogram, leg movements, airflow, oxygen, and breathing effort.
OSA, UARS, and the 30–60% Overlap
This is the single most under-appreciated fact in fibromyalgia care. Depending on the study, 30% to 60% of fibromyalgia patients have obstructive sleep apnea (OSA). The range is wide because screening criteria differ and the samples are small clinic groups: a 1993 clinic found significant sleep apnea in 44% of men (11 of 25) against 2.2% of women (2 of 92, with only 4 women tested), and a 2023 pilot found it in 68% (17 of 25). Even the low end is staggeringly high compared to the general population (roughly 10–15%). In men with fibromyalgia, rates cluster near the top of that range.
OSA means your upper airway collapses partially or fully dozens or hundreds of times an hour while you sleep. Each collapse drops your oxygen and jolts you into a micro-arousal you do not remember. Those micro-arousals destroy N3. If you have fibromyalgia and untreated OSA, you have two engines wrecking your sleep architecture, and no amount of melatonin, amitriptyline, or sleep hygiene will fix the apnea piece.
UARS is the quieter cousin. Your airway does not fully collapse, but it narrows enough to make you work harder to breathe. You do not drop your oxygen, so a crude home test misses it, but the extra respiratory effort still triggers arousals. UARS patients are often thin women — exactly the demographic most likely to be told “you can’t have sleep apnea, you’re not overweight.” That dismissal is wrong. UARS requires esophageal pressure monitoring or a careful in-lab study to catch.
Some patients and practitioners describe treating OSA or UARS as the biggest improvement in fibromyalgia symptoms they have seen. A 3-month uncontrolled series of 28 people on CPAP plus exercise reported improved symptoms, and a case report describes symptoms clearing with a mandibular advancement device.
Restless Legs and PLMD
Restless legs syndrome (RLS) and periodic limb movement disorder (PLMD) are also over-represented in fibromyalgia, with prevalence estimates of 30–40%. One study found restless legs in 42.6% of 115 women with fibromyalgia, with worse sleep and quality-of-life scores than in those without it. RLS is the conscious, crawling, have-to-move sensation you get in the evening. PLMD is the involuntary leg jerking during sleep that you may not notice but your partner will.
Both fragment sleep, and both are often driven by low brain iron even when your blood iron looks “normal.” The usual test is a ferritin level. If it is under 75 ng/mL (some specialists use 100), oral or intravenous (IV) iron supplementation frequently resolves RLS within weeks. Other triggers include selective serotonin reuptake inhibitors (SSRIs), serotonin-norepinephrine reuptake inhibitors (SNRIs), and diphenhydramine (the antihistamine in most over-the-counter sleep aids) — all of which can worsen RLS and are commonly prescribed for fibromyalgia sleep complaints. Many patients are trapped in a loop where the drug for sleep is causing the leg problem that ruins the sleep.
CPAP When Indicated
If your sleep study shows an AHI (apnea-hypopnea index) over 5 with symptoms, or over 15 without, the treatment is usually continuous positive airway pressure (CPAP). CPAP blows a steady stream of air that splints your airway open.
CPAP has a reputation for being intolerable. Modern machines are quiet, the masks come in dozens of shapes, and the ramp features ease you in. The two keys to adherence are mask fit and pressure titration. Masks come in several styles — nasal pillow, nasal mask, full face — and people who dislike their first mask often change style. For pressure that feels suffocating, the alternatives are a BiPAP (separate inhale and exhale pressures) or an APAP (auto-adjusting). Insurance usually covers them.
Fibromyalgia patients who stick with CPAP describe different outcomes. Some feel dramatically better within a month — more energy, less pain, clearer head. Some feel moderate improvement. Some feel little change, usually because the apnea was not the main driver of their symptoms. Even for that last group, the cardiovascular and cognitive reasons for treating OSA remain.
Bedtime Protocol: Light, Temperature, Schedule
Sleep hygiene is boring, overprescribed advice — and many fibromyalgia clinicians still treat it as the foundation everything else sits on. The 2021 American Academy of Sleep Medicine guideline, written for chronic insomnia in general, suggests that clinicians not use sleep hygiene as a stand-alone treatment, while strongly recommending multicomponent cognitive behavioral therapy for insomnia. Three variables are the ones most often described.
Light. Your brain sets its circadian clock from light, not clocks. Sleep clinics describe bright outdoor light within 30 minutes of waking — even 10 minutes on a cloudy day is stronger than any indoor bulb — plus dim household lights after sunset and less blue-heavy screen light in the last hour before bed (through night-shift modes or amber glasses). If you have ever fallen asleep fine on vacation and lain awake for hours at home, your evening light exposure is probably the difference.
Temperature. Your core body temperature has to drop about 1–2°F to initiate and maintain deep sleep. A bedroom at 65–68°F (18–20°C) is the sweet spot for most adults. A hot bath or shower 90 minutes before bed sounds counterintuitive but works by dilating surface blood vessels and then rebound-cooling your core faster. Some light sleepers report that cooling mattress pads help.
Schedule. A consistent wake time every single day, weekends included, is worth more than a consistent bedtime. Sleep clinicians describe bedtime sorting itself out once the wake time is fixed. Variable wake times confuse the circadian clock and lock in fragmented sleep even when total hours look fine on paper.
Medication Options — Pros, Cons, Dosing
No drug fixes fibromyalgia sleep, but several partially rebuild sleep architecture or ease the specific bottleneck you are stuck on. All of these are off-label for sleep in most cases; doses below are starting ranges used in practice, and these are prescription drugs in the U.S.
A 2022 comparison of 36 trials (11,930 patients) gives one overall picture: amitriptyline ranked best for sleep, fatigue and quality of life, and duloxetine 120 mg best for pain and depression. Pregabalin, duloxetine and milnacipran were the drugs with FDA approval for fibromyalgia at the time of that analysis.
Low-dose amitriptyline. 5–25 mg at bedtime. The single most-studied fibromyalgia sleep drug. A tricyclic antidepressant in full doses (150 mg), but at 10–25 mg it is a sleep and pain modulator. Pros: cheap, decades of use; in the 2022 comparison it was linked to less sleep disturbance than placebo (standardized mean difference −0.97). Cons: the 2019 Cochrane review (nine studies, doses of 25–50 mg) found no first- or second-tier evidence, reported at least 50% pain relief with a number needed to treat of 4.1 on very low quality evidence, and found no consistent differences for fatigue or poor sleep; 78% had at least one adverse event against 47% on placebo. Morning grogginess, dry mouth, constipation and weight gain are described, and the research raises a concern for people with heart rhythm problems or glaucoma. People often describe taking it 2–3 hours before bed, not at lights-out.
Cyclobenzaprine. 5–10 mg at bedtime. Structurally similar to amitriptyline. Pros: relaxes muscles, improves perceived sleep quality, useful if stiffness is a big part of your presentation. Cons: next-day sedation, dry mouth, tolerance after a few weeks in many patients. Some clinicians rotate it 5 nights on, 2 nights off to preserve effect.
Under-the-tongue cyclobenzaprine. In August 2025 the FDA approved a bedtime sublingual form for fibromyalgia, described as the first new drug approved for it in more than 15 years. In a phase 3 trial of 456 people, pain scores fell 1.8 points vs 1.2 with placebo over 14 weeks, and sleep quality also improved more. A numb mouth was common (23.4% vs 0.4%).
Trazodone. 25–100 mg at bedtime. A serotonin modulator that at low doses is primarily sedating. Pros: non-habit-forming, helps sleep maintenance (not just onset), well-tolerated long-term, cheap. Cons: hangover, orthostatic dizziness, rarely priapism in men. Used for patients who cannot tolerate tricyclics.
Gabapentin. 100–900 mg at bedtime. A seizure drug with pain-modulating and sleep-deepening effects in the fibromyalgia population. Pros: improves slow-wave sleep, reduces nerve-type pain, useful if RLS is also present. Cons: weight gain, dizziness, swelling, withdrawal if stopped abruptly. Usually titrated up slowly over 1–2 weeks.
Pregabalin. 75–150 mg at bedtime, up to 450 mg/day in divided doses. U.S. Food and Drug Administration-approved for fibromyalgia. Similar mechanism to gabapentin with more predictable absorption. Pros: approved indication, proven sleep and pain benefit. In a post hoc analysis of a sleep-laboratory crossover trial (119 randomized), unbroken stretches of sleep lasted 15.25 minutes on pregabalin vs 11.58 on placebo, and the number of wake/sleep stretches fell to 33.24 vs 36.85. Cons: expensive, same side-effect profile as gabapentin, scheduled (Class V) in the U.S.
Sodium oxybate. Fibromyalgia trials reported better sleep, more slow-wave sleep and less pain, yet the FDA did not approve it for this use in 2010, mostly because of concerns about abuse.
The drugs that raise the most concern for long-term sleep use are diphenhydramine (most PM formulations), zolpidem and the other Z-drugs, and benzodiazepines. They induce sleep but flatten N3 — the exact stage you need to protect — and carry tolerance, cognitive, and falls risks that compound over time.
Why Melatonin Alone Rarely Fixes It — and Where Magnesium Glycinate Fits
Melatonin is a hormone, not a sedative. It is a timing signal that tells your brain “it is nighttime.” If your problem is that you cannot fall asleep at a reasonable clock time (delayed sleep phase, jet lag, shift work), melatonin 0.3–1 mg taken 2–4 hours before desired bedtime works beautifully. If your problem is that you do fall asleep but your sleep is fragmented, alpha-intruded, or apneic, the evidence for melatonin is preliminary: a 2023 review says early clinical studies suggest melatonin at different doses can reduce pain and ease mood and sleep disturbances in fibromyalgia. Many fibromyalgia patients still say “I tried melatonin, it didn’t help.”
Drugstore doses of 5–10 mg are too high. Supraphysiologic doses can cause vivid dreams, next-day fog, and receptor downregulation. People who use it for timing often start at 0.3 mg or 1 mg.
Magnesium glycinate at night is different and, for many fibromyalgia patients, genuinely useful. Magnesium is a cofactor for gamma-aminobutyric acid (GABA) activity and N-methyl-D-aspartate (NMDA) receptor regulation — both central to calming an overactive nervous system. Glycinate is a well-absorbed, non-laxative form (unlike magnesium oxide or citrate, which send you to the bathroom). A common dose is 200–400 mg elemental magnesium 30–60 minutes before bed. Many patients pair it with glycine itself (3 g) which independently lowers core body temperature and improves subjective sleep quality. Both are cheap, both are low-risk, and neither requires a prescription. See the nutrient gaps article for the full picture on why magnesium deficiency is so common in this population.
Cognitive Behavioral Therapy for Insomnia: The Treatment Nobody Offers You
Cognitive behavioral therapy for insomnia (CBT-I) is the first-line treatment recommended by the American College of Physicians for chronic insomnia — ahead of any drug. It is also the treatment most fibromyalgia patients never hear about. It is not “therapy for sleep anxiety.” It is a structured 6–8 session protocol that retrains your brain’s association between bed and sleep using three core tools: stimulus control (bed is only for sleep), sleep restriction (compressing your time in bed to rebuild sleep pressure), and cognitive restructuring (unwinding the catastrophizing that keeps you awake).
Cognitive behavioral therapy for insomnia has stronger long-term evidence for chronic insomnia than any medication. In fibromyalgia specifically, the SPIN randomized trial (113 people with fibromyalgia and insomnia) found that self-reported sleep improved with eight sessions of cognitive behavioral therapy for insomnia and stayed better at 6 months. “Neither treatment improved pain or mood” compared with the other groups overall: few people reached a pain reduction above 50%, and about one third reached a reduction above 30%.
Access is the hard part. Therapists who deliver this treatment in person are scarce. Free and low-cost digital programs are reported to work almost as well, including commercial apps and the VA’s free public CBT-i Coach app. For people who have tried one drug after another for sleep, it is often the treatment they have not yet tried.
Common Traps: Alcohol, Late Caffeine, Doom-Scrolling
Alcohol. A glass of wine is the most common self-prescribed sleep aid. It works for the first 90 minutes — you fall asleep faster — and then it wrecks the rest of the night. Alcohol suppresses REM early and fragments N3 late. As it metabolizes around 2–3 a.m., it triggers a cortisol spike that wakes you. For fibromyalgia sleep in particular, the net effect is deeply negative. Sleep clinics commonly describe finishing at least 3–4 hours before bedtime and keeping the total modest.
Caffeine. Caffeine has a half-life of 5–6 hours, meaning a 3 p.m. coffee still has well over a quarter of its dose circulating at 11 p.m. In slow metabolizers (a common genetic variant at CYP1A2), the half-life can exceed 8 hours. A common rule of thumb is no caffeine after noon. If you depend on afternoon coffee to function, that is a flag that your sleep is broken — not a reason to keep drinking it.
Doom-scrolling. The phone-in-bed problem is not mainly about blue light. It is about cognitive and emotional arousal. News, social media, and email trigger the same alerting systems you are trying to quiet. Moving the phone out of the bedroom (or at least across the room, on a real alarm clock) is the single highest-yield behavioral change most people can make. If the idea of sleeping without your phone next to you generates anxiety, that is diagnostic — it is exactly the arousal keeping you out of N3.
Other traps worth naming: heavy late meals (raise core temperature, trigger reflux), intense evening exercise (raises cortisol; morning or early afternoon is better), and weekend sleep-ins longer than an hour past your weekday wake time (recreates a mini jet lag every Monday).
Key Research Papers
- Moldofsky H, Scarisbrick P, England R, Smythe H. Musculoskeletal symptoms and non-REM sleep disturbance in patients with “fibrositis syndrome” and healthy subjects. Psychosom Med. 1975;37(4):341–351. — doi:10.1097/00006842-197507000-00008
- Roizenblatt S, Moldofsky H, Benedito-Silva AA, Tufik S. Alpha sleep characteristics in fibromyalgia. Arthritis Rheum. 2001;44(1):222–230. — PubMed PMID: 11212164
- Diaz-Piedra C, Di Stasi LL, Baldwin CM, Buela-Casal G, Catena A. Sleep disturbances of adult women suffering from fibromyalgia: a systematic review of observational studies. Sleep Med Rev. 2015;21:86–99. — PubMed PMID: 25456469
- Diaz-Piedra C, Catena A, Sánchez AI, Miró E, Martínez MP, Buela-Casal G. Sleep disturbances in fibromyalgia syndrome: the role of clinical and polysomnographic variables explaining poor sleep quality in patients. Sleep Med. 2015;16(8):917–925. — PubMed PMID: 26070854
- Bigatti SM, Hernandez AM, Cronan TA, Rand KL. Sleep disturbances in fibromyalgia syndrome: relationship to pain and depression. Arthritis Rheum. 2008. — doi:10.1002/art.23828
- Wu YL, Chang LY, Lee HC, Fang SC, Tsai PS. Sleep disturbances in fibromyalgia: a meta-analysis of case-control studies. J Psychosom Res. 2017;96:89–97. — PubMed PMID: 28545798
- McCrae CS, Williams J, Roditi D, et al. Cognitive behavioral treatments for insomnia and pain in adults with comorbid chronic insomnia and fibromyalgia: clinical outcomes from the SPIN randomized controlled trial. Sleep. 2019;42(3):zsy234. — PubMed PMID: 30496533
- Edinger JD, Arnedt JT, Bertisch SM, et al. Behavioral and psychological treatments for chronic insomnia disorder in adults: an American Academy of Sleep Medicine clinical practice guideline. J Clin Sleep Med. 2021;17(2):255–262. — PubMed PMID: 33164742
- Moore RA, Derry S, Aldington D, Cole P, Wiffen PJ. Amitriptyline for fibromyalgia in adults. Cochrane Database Syst Rev. 2019;5(7):CD011824. — PubMed PMID: 35658166
- Farag HM, Yunusa I, Goswami H, Sultan I, Doucette JA, Eguale T. Comparison of amitriptyline and US Food and Drug Administration-approved treatments for fibromyalgia: a systematic review and network meta-analysis. JAMA Netw Open. 2022;5(5):e2212939. — PubMed PMID: 35587348
- Lederman S, Arnold LM, Vaughn B, Engels JM, Kelley M, Sullivan GM. Pain relief by targeting nonrestorative sleep in fibromyalgia: a phase 3 randomized trial of bedtime sublingual cyclobenzaprine. Pain Med. 2026;27(1):86–94. — PubMed PMID: 40627411
- Abd-Elsayed A, Knezic A, Asfour J, Dewan P, Hasoon J, Reilly M. Sublingual cyclobenzaprine for fibromyalgia: pharmacokinetic rationale, clinical evidence, and place in therapy. Curr Pain Headache Rep. 2026;30(1). — PubMed PMID: 42479282
- Staud R. Sodium oxybate for the treatment of fibromyalgia. Expert Opin Pharmacother. 2011;12(11):1789–1798. — PubMed PMID: 21679091
- Roth T, Bhadra-Brown P, Pitman VW, Resnick EM. Pregabalin improves fibromyalgia-related sleep disturbance. Clin J Pain. 2016;32(4):308–312. — PubMed PMID: 26035523
- Riva R, Mork PJ, Westgaard RH, Rø M, Lundberg U. Fibromyalgia syndrome is associated with hypocortisolism. Int J Behav Med. 2010;17(3):223–233. — PubMed PMID: 20458566
- Riva R, Mork PJ, Westgaard RH, Lundberg U. Comparison of the cortisol awakening response in women with shoulder and neck pain and women with fibromyalgia. Psychoneuroendocrinology. 2012;37(2):299–306. — PubMed PMID: 21764519
- González-Flores D, López-Pingarrón L, Castaño MY, et al. Melatonin as a coadjuvant in the treatment of patients with fibromyalgia. Biomedicines. 2023;11(7):1964. — PubMed PMID: 37509603
- May KP, West SG, Baker MR, Everett DW. Sleep apnea in male patients with the fibromyalgia syndrome. Am J Med. 1993;94(5):505–508. — PubMed PMID: 8498395
- Meresh ES, Xu S, Palomino A, et al. The correlation of pain, psychological aspects, and sleep in fibromyalgia: a cross-sectional analysis. Open Access Rheumatol. 2023;15:237–246. — PubMed PMID: 38143566
- Üstün B, Gürer R, Mesci N, Geler-Külcü D, Icten S. The prevalence of fibromyalgia syndrome in individuals with obstructive sleep apnea syndrome and the impact of continuous positive airway pressure treatment on fibromyalgia symptoms. Sleep Breath. 2026;30(2). — PubMed PMID: 41865211
- Vantine F, Ettlin D, Meira-E-Cruz M. Resolution of fibromyalgia by controlling obstructive sleep apnea with a mandibular advancement device. Sleep Sci. 2021;14(3):291–295. — PubMed PMID: 35186209
- Civelek GM, Ciftkaya PO, Karatas M. Evaluation of restless legs syndrome in fibromyalgia syndrome: an analysis of quality of sleep and life. J Back Musculoskelet Rehabil. 2014;27(4):537–544. — PubMed PMID: 24867908
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on fibromyalgia sleep biology, sleep-disordered breathing overlap, and behavioral and pharmacologic interventions:
- PubMed: Fibromyalgia and non-restorative sleep
- PubMed: Alpha intrusion and EEG findings in fibromyalgia
- PubMed: Fibromyalgia and obstructive sleep apnea overlap
- PubMed: Fibromyalgia and upper airway resistance syndrome
- PubMed: Fibromyalgia, restless legs, and periodic limb movements
- PubMed: CBT-I in fibromyalgia patients
- PubMed: Amitriptyline and cyclobenzaprine for fibromyalgia sleep
- PubMed: Pregabalin and gabapentin effects on fibromyalgia sleep
- PubMed: Growth hormone, IGF-1, and fibromyalgia
- PubMed: HPA axis and cortisol rhythms in fibromyalgia
Connections
- Orthopedics
- Nutrient Gaps in Fibromyalgia
- Fibromyalgia Overview
- Insomnia
- Magnesium
- ACR 2016 Diagnostic Criteria
- Sleep Hygiene
- Fibromyalgia and Myalgic Encephalomyelitis/Chronic Fatigue Syndrome Overlap
- Low-Dose Naltrexone for Fibromyalgia
- Central Sensitization Explained
- Small-Fiber Neuropathy Overlap
- Exercise Pacing and Graded Movement
- Chronic Fatigue Syndrome
- Insomnia (Symptoms)
- Magnesium Glycinate
- Fatigue
- Obstructive Sleep Apnea
- Postural Orthostatic Tachycardia Syndrome
- Chronic Pain