Multiple Myeloma
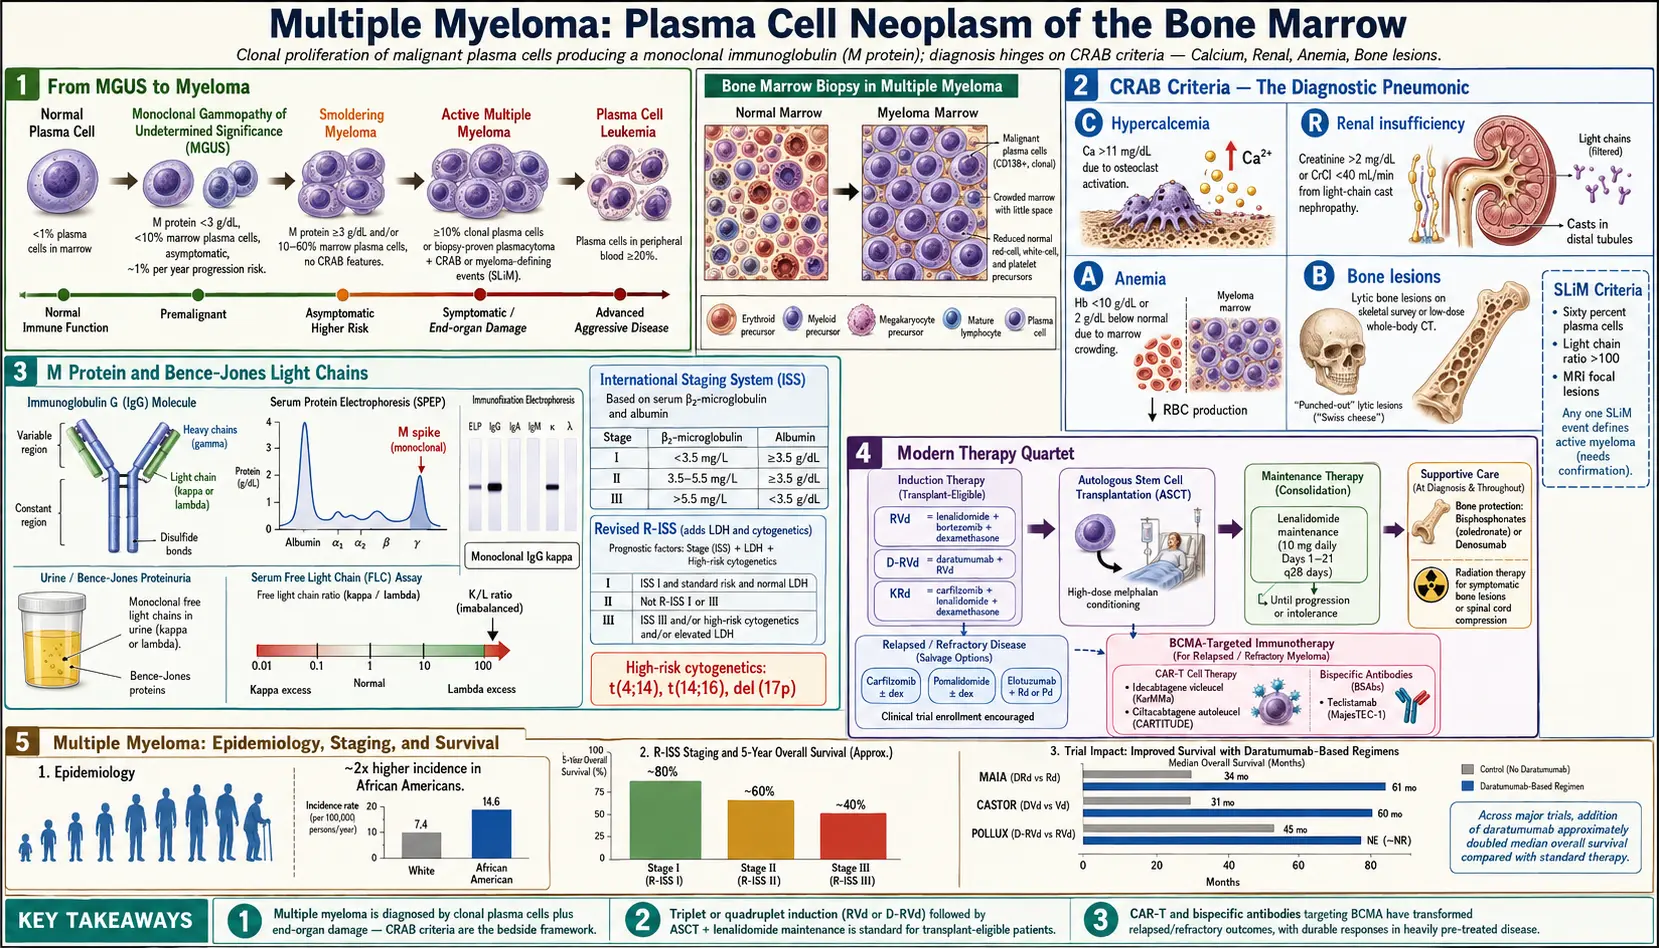
Table of Contents
What Multiple Myeloma Is
Multiple Myeloma is a type of cancer that forms in plasma cells, a kind of white blood cell that helps the body fight infections by making antibodies. In multiple myeloma, cancerous plasma cells accumulate in the bone marrow and crowd out healthy blood cells.
Causes and Risk Factors
The exact cause of multiple myeloma is not fully understood, but several risk factors have been identified:
- Age: Most people diagnosed with multiple myeloma are over 65.
- Gender: Men are slightly more likely to develop the disease than women.
- Race: African Americans have a higher risk compared to other races.
- Family history: A family history of multiple myeloma or other blood cancers may increase risk.
- Monoclonal gammopathy of undetermined significance (MGUS): This condition can develop into multiple myeloma over time. MGUS is found in about 3% of people aged 50 or older. In a study of 1,384 Minnesota patients followed for a median of 34 years, MGUS progressed to multiple myeloma or a related plasma-cell or lymphoid disorder in 11%; the risk of progression was 10% at 10 years, 18% at 20 years and 28% at 30 years. For MGUS that does not involve immunoglobulin M (non-IgM MGUS), the 20-year risk was 7% in people with neither of two risk factors (an abnormal free light-chain ratio and an M protein level of 1.5 g/dL or more) and 30% in people with both.
Symptoms of Multiple Myeloma
Common symptoms include:
- Bone pain, especially in the spine or chest
- Frequent infections due to a weakened immune system
- Fatigue or feeling weak
- Weight loss without trying
- Excessive thirst and dehydration
- Nausea or constipation
- Kidney problems caused by high levels of abnormal proteins
Diagnosis and Staging
Diagnostic Tests
To diagnose multiple myeloma, doctors may use the following tests:
- Blood tests: To detect abnormal proteins (M proteins), calcium levels, and other indicators.
- Urine tests: To check for the presence of Bence Jones proteins, which can point to multiple myeloma.
- Bone marrow biopsy: A sample of bone marrow is taken to look for myeloma cells.
- Imaging tests: Such as X-rays, magnetic resonance imaging (MRI), computed tomography (CT) scans, or positron emission tomography (PET) scans to detect bone damage.
Under the 2014 International Myeloma Working Group criteria, multiple myeloma is diagnosed when abnormal (clonal) plasma cells are found together with either “CRAB” damage — high blood calcium, kidney failure, anemia (too few red blood cells) and bone lesions — or validated biomarkers that predict near-certain development of that damage. The biomarkers were added because, without them, these patients would be labelled “smoldering” myeloma, and the working group judged that delaying the diagnosis and treatment could harm them.
Staging
Staging of multiple myeloma helps determine the extent of the disease. The International Staging System, published in 2005 from the records of 10,750 previously untreated patients in North America, Europe and Asia, uses two blood tests, beta-2 microglobulin and albumin:
- Stage I: Beta-2 microglobulin below 3.5 mg/L and albumin at or above 3.5 g/dL (median survival 62 months in the 2005 data).
- Stage II: Neither stage I nor stage III (median survival 44 months in the 2005 data).
- Stage III: Beta-2 microglobulin at or above 5.5 mg/L (median survival 29 months in the 2005 data).
The current Revised International Staging System combines beta-2 microglobulin, albumin and a third blood test, lactate dehydrogenase, with high-risk chromosome changes found in the myeloma cells (t(4;14), del(17p) and t(14;16)).
Treatment Options
Treatment varies based on the stage and the patient’s overall health:
- Targeted therapy: Drugs that target specific proteins in myeloma cells, such as proteasome inhibitors.
- Immunotherapy: Utilizes the immune system to fight cancer, using drugs that enhance the immune response.
- Chemotherapy: Kills rapidly growing cancer cells and is often used before stem cell transplant.
- Stem cell transplant: Involves replacing damaged bone marrow with healthy stem cells, typically following high-dose chemotherapy.
- Radiation therapy: Used to relieve pain and reduce the size of tumors in specific areas.
Recent Trial Results
In the PERSEUS phase 3 trial (2024), 709 newly diagnosed patients who were able to have a stem cell transplant received either the standard three-drug start (bortezomib, lenalidomide and dexamethasone) or the same three drugs plus daratumumab, an antibody injected under the skin. At 4 years, 84.3% of the daratumumab group and 67.7% of the three-drug group were alive without the disease progressing, and 75.2% vs 47.5% reached minimal-residual-disease negativity (myeloma cells below the detection level of sensitive tests). Serious side effects occurred in 57.0% vs 49.3%.
Chimeric antigen receptor T-cell (CAR-T) therapy, in which a patient’s own immune cells are modified to attack myeloma, has moved earlier in treatment. In the CARTITUDE-4 phase 3 trial, patients whose myeloma no longer responded to lenalidomide after one to three earlier lines of treatment were randomly assigned to a single infusion of ciltacabtagene autoleucel (208 patients) or standard care (211 patients). In the 2026 updated analysis (median follow-up 33.6 months), the median time without progression had not been reached in the CAR-T group, compared with 11.8 months on standard care, and the risk of death was lower (hazard ratio 0.55). Deaths numbered 24% vs 39%; six deaths in the CAR-T group (3%) were caused by treatment-related side effects, four of them infections, compared with five (2%) on standard care.
Prognosis
The prognosis for multiple myeloma depends on various factors, including the stage at diagnosis and the patient's response to treatment. While it is generally considered incurable, advancements in treatment have significantly improved survival rates and quality of life for patients.
A 2022 medical review gives current figures: about 34,920 people in the US are diagnosed with multiple myeloma each year. At diagnosis, about 73% have anemia, 79% have bone damage (osteolytic bone disease) and 19% have acute kidney injury. About 28% are diagnosed at Revised International Staging System stage I, and these patients have a 5-year survival of 82%. The standard three-drug first treatment (bortezomib, lenalidomide and dexamethasone) is associated with a median of 41 months before the disease progresses, compared with historical reports of 8.5 months without therapy. The median survivals of 62, 44 and 29 months from the 2005 staging study (see Staging above) are an older baseline.
Smoldering Myeloma: the Stage Before Symptoms
Smoldering multiple myeloma is a precursor of active myeloma: abnormal plasma cells and myeloma proteins are present, but without the CRAB organ damage described above. Before the AQUILA phase 3 trial (2025), no treatment had been approved for high-risk smoldering myeloma. In that trial, 390 patients received either daratumumab injections under the skin for up to 36 months or active monitoring. After a median follow-up of 65.2 months, 63.1% of the daratumumab group and 40.8% of the monitoring group were alive at 5 years without progression to active myeloma, and overall survival at 5 years was 93.0% vs 86.9%. The most common severe side effect was high blood pressure (5.7% vs 4.6%).
Key Research Papers
Historical Background
Multiple myeloma was first described in 1844 by Samuel Solly, who reported a case of bone disease associated with fragile bones. In 1848, Henry Bence Jones identified the characteristic urinary protein (now called Bence Jones protein). The disease was formally characterized by Otto Kahler in 1889, and for many years was known as "Kahler's disease." Jan Gosta Waldenstrom further distinguished myeloma from other plasma cell disorders in the 1940s.
- Facon T, Kumar S, Plesner T, et al. Daratumumab plus lenalidomide and dexamethasone for untreated myeloma (MAIA). N Engl J Med. 2019;380(22):2104-2115. — PubMed PMID: 31141632
- Munshi NC, Anderson LD Jr, Shah N, et al. Idecabtagene vicleucel in relapsed and refractory multiple myeloma (KarMMa). N Engl J Med. 2021;384(8):705-716. — doi:10.1056/NEJMoa2024850
- Rajkumar SV. Multiple myeloma: 2020 update on diagnosis, risk-stratification, and management. Am J Hematol. 2020;95(5):548-567. — doi:10.1002/ajh.25791
- Lonial S, Dimopoulos M, Palumbo A, et al. Elotuzumab therapy for relapsed or refractory multiple myeloma (ELOQUENT-2). N Engl J Med. 2015;373(7):621-631. — doi:10.1056/NEJMoa1505654
- Dimopoulos MA, Oriol A, Nahi H, et al. Daratumumab, lenalidomide, and dexamethasone for multiple myeloma (POLLUX). N Engl J Med. 2016;375(14):1319-1331. — doi:10.1056/NEJMoa1607751
- Palumbo A, Chanan-Khan A, Weisel K, et al. Daratumumab, bortezomib, and dexamethasone for multiple myeloma (CASTOR). N Engl J Med. 2016;375(8):754-766. — doi:10.1056/NEJMoa1606038
- Rajkumar SV, Dimopoulos MA, Palumbo A, et al. International Myeloma Working Group updated criteria for the diagnosis of multiple myeloma. Lancet Oncol. 2014;15(12):e538-e548. — doi:10.1016/S1470-2045(14)70442-5
- Stewart AK, Rajkumar SV, Dimopoulos MA, et al. Carfilzomib, lenalidomide, and dexamethasone for relapsed multiple myeloma (ASPIRE). N Engl J Med. 2015;372(2):142-152. — doi:10.1056/NEJMoa1411321
- Cowan AJ, Green DJ, Kwok M, et al. Diagnosis and management of multiple myeloma: a review. JAMA. 2022;327(5):464-477. — doi:10.1001/jama.2022.0003
- Greipp PR, San Miguel J, Durie BGM, et al. International staging system for multiple myeloma (ISS). J Clin Oncol. 2005;23(15):3412-3420. — doi:10.1200/JCO.2005.04.242
- Moreau P, Garfall AL, van de Donk NWCJ, et al. Teclistamab in relapsed or refractory multiple myeloma (MajesTEC-1). N Engl J Med. 2022;387(6):495-505. — doi:10.1056/NEJMoa2203478
- Richardson PG, Oriol A, Beksac M, et al. Pomalidomide, bortezomib, and dexamethasone for patients with relapsed or refractory multiple myeloma (OPTIMISMM). Lancet Oncol. 2019;20(6):781-794. — doi:10.1016/S1470-2045(19)30152-4
- Kyle RA, Larson DR, Therneau TM, et al. Long-Term Follow-up of Monoclonal Gammopathy of Undetermined Significance. N Engl J Med. 2018;378(3):241-249. — PubMed PMID: 29342381
- Sonneveld P, Dimopoulos MA, Boccadoro M, et al. Daratumumab, Bortezomib, Lenalidomide, and Dexamethasone for Multiple Myeloma. N Engl J Med. 2024;390(4):301-313. — PubMed PMID: 38084760
- Dimopoulos MA, Voorhees PM, Schjesvold F, et al. Daratumumab or Active Monitoring for High-Risk Smoldering Multiple Myeloma. N Engl J Med. 2025;392(18):1777-1788. — PubMed PMID: 39652675
- Einsele H, San-Miguel J, Dhakal B, et al. Cilta-cel in lenalidomide-refractory multiple myeloma (CARTITUDE-4): an updated analysis including overall survival from an open-label, multicentre, randomised, phase 3 trial. Lancet Oncol. 2026;27(2):254-268. — PubMed PMID: 41519141
PubMed Topic Searches
The following PubMed topic searches surface the current peer-reviewed literature on Multiple Myeloma. Each link opens a live PubMed query; results update as new papers are indexed.
- PubMed: Search: multiple myeloma
- PubMed: Search: multiple myeloma CRAB criteria
- PubMed: Search: multiple myeloma bortezomib proteasome inhibitor
- PubMed: Search: multiple myeloma lenalidomide
- PubMed: Search: multiple myeloma daratumumab
- PubMed: Search: multiple myeloma CAR T cell therapy
- PubMed: Search: multiple myeloma autologous stem cell transplant
- PubMed: Search: smoldering multiple myeloma
- PubMed: Search: monoclonal gammopathy undetermined significance
- PubMed: Search: multiple myeloma bone disease
- PubMed: Search: multiple myeloma minimal residual disease
- PubMed: Search: multiple myeloma bispecific antibody