Low-FODMAP Diet for Irritable Bowel Syndrome (IBS)
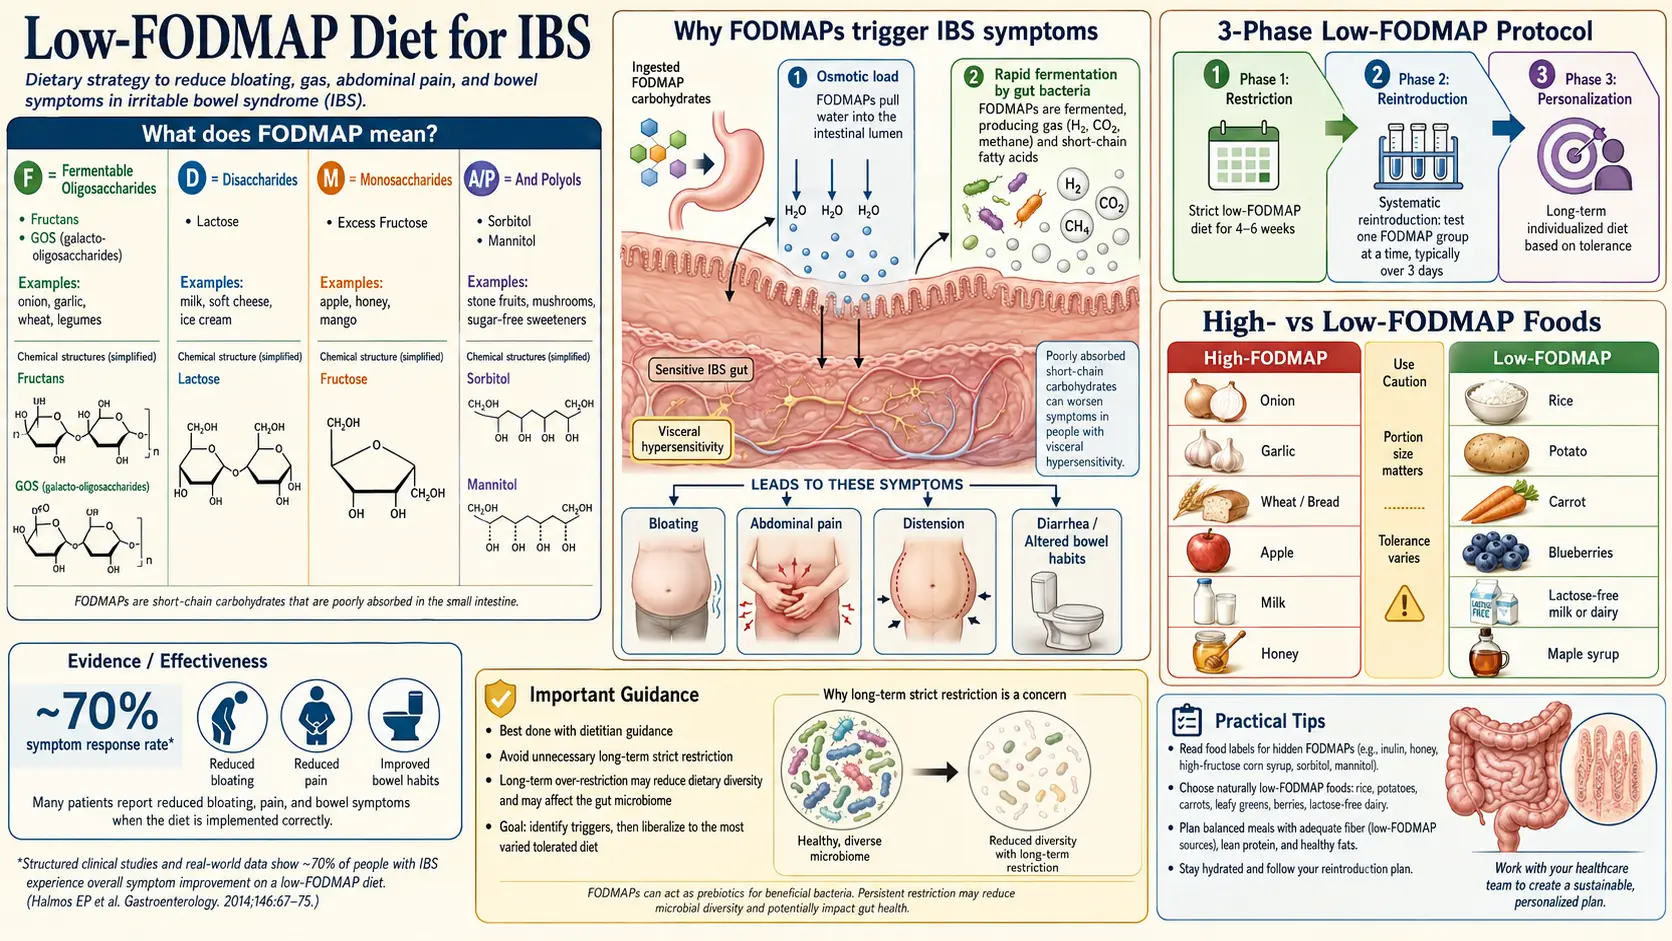
Table of Contents
- What FODMAPs Actually Are
- Why FODMAPs Trigger Symptoms
- Evidence and Response Rates
- The Monash Three-Phase Protocol
- Phase 1 — Strict Elimination (2–6 Weeks)
- Detailed Food Lists for the Elimination Phase
- Phase 2 — Systematic Reintroduction (About 8 Weeks)
- Phase 3 — Personalization
- FODMAP Stacking — The Principle Most People Miss
- The Monash App and Other Tools
- Practical Tactics: Oils, Packaged Foods, Eating Out
- Risks of a Prolonged Elimination Phase
- What Dietitian Guidance Covers
- When Low-FODMAP Doesn't Work
- The Gluten-Free Overlap
- Key Research Papers
- Connections
- Featured Videos
What FODMAPs Actually Are
FODMAP is an acronym coined by the research team at Monash University in Melbourne, Australia, in the mid-2000s. It stands for Fermentable Oligosaccharides, Disaccharides, Monosaccharides, And Polyols. Those are four families of short-chain carbohydrates and sugar alcohols that share two inconvenient properties: your small intestine absorbs them poorly, and your colon bacteria love to ferment them.
The four groups, translated into food:
- Oligosaccharides — short chains of sugars. The two that matter are fructans (in wheat, rye, onion, garlic, leeks, shallots, artichokes) and galacto-oligosaccharides (GOS) (in most beans, lentils, chickpeas, cashews, and pistachios). Humans have no enzyme to split these bonds — everyone, irritable bowel syndrome (IBS) or not, passes them undigested into the colon.
- Disaccharides — specifically lactose, the milk sugar. Whether lactose is a problem depends on whether you still produce the enzyme lactase. Roughly 65% of adults worldwide lose most of their lactase activity after childhood.
- Monosaccharides — specifically fructose in excess of glucose. Fructose is absorbed efficiently when paired 1:1 with glucose (as in table sugar) but poorly when it floats free in high amounts (as in apples, pears, mangoes, honey, agave, and high-fructose corn syrup).
- Polyols — sugar alcohols such as sorbitol and mannitol, naturally abundant in stone fruits (plums, peaches, apricots, cherries), mushrooms, cauliflower, and sugar-free gum and candy sweetened with xylitol, maltitol, or erythritol.
Note what FODMAPs are not. They are not gluten, not dairy protein, not histamine, not lectins, not nightshades, not oxalates. They are one specific family of fermentable carbohydrates, and a low-FODMAP diet is designed to target that chemistry and nothing else.
Why FODMAPs Trigger Symptoms
Two mechanisms, both normal physiology pushed past a threshold.
Osmotic pull. FODMAPs are small, dissolved, and osmotically active. When they sit in the small intestine unabsorbed, they drag water in with them. In a healthy gut with normal motility, the extra fluid moves along without trouble. In an irritable bowel syndrome gut — where the bowel wall is more reactive and motility is dysregulated — the added fluid stretches the small bowel and produces the characteristic cramping, urgency, and loose stools of diarrhea-predominant irritable bowel syndrome (IBS-D).
Rapid fermentation. Whatever reaches the colon still undigested becomes bacterial food. Colonic microbes ferment FODMAPs into short-chain fatty acids plus large volumes of gas — hydrogen, methane, and sometimes hydrogen sulfide. In healthy people this fermentation is slow and mostly comfortable. In irritable bowel syndrome, the gas is produced faster than the colon can move or absorb it, the bowel distends, and nerve endings that are already too sensitive (see visceral hypersensitivity) fire as if something is badly wrong. That signal reaches the brain as pain and bloating.
Low-FODMAP is not a food-allergy diet. FODMAPs are not doing anything toxic, and your immune system is not producing antibodies against them. The diet simply reduces the substrate that feeds the mechanical and fermentative triggers, giving the gut less raw material to react to.
Evidence and Response Rates
The low-FODMAP diet is the most-studied dietary intervention for irritable bowel syndrome. A 2022 network meta-analysis by Black, Staudacher and Ford pooled 13 randomized trials with 944 people and ranked the low-FODMAP diet first of all the diet approaches tested for overall symptoms, abdominal pain, bloating and bowel habit. Compared with people’s usual diet, the chance that symptoms did not improve was about one-third lower (relative risk 0.67). It also beat standard British dietary advice (from the British Dietetic Association and the National Institute for Health and Care Excellence) for bloating. Most of the trials were run in hospital clinics and did not test the reintroduction and personalisation phases, so long-term results of the full three-phase plan are less studied.
Halmos and colleagues (2014) ran the landmark feeding trial in which almost all food was provided to participants, ruling out most adherence problems. In 30 people with irritable bowel syndrome, each eating both diets for 21 days in turn, overall gastrointestinal symptom scores were 22.8 on the low-FODMAP diet versus 44.9 on a typical Australian diet (on a 0–100 mm scale). Staudacher and colleagues (2017) extended this with a placebo-controlled trial of 104 people in four groups: a low-FODMAP diet or a sham diet, each with either a probiotic or a placebo capsule. After 4 weeks, 57% on the low-FODMAP diet reported adequate symptom relief versus 38% on the sham diet — a difference just short of statistical significance (P = .051) when everyone who started was counted, and significant (61% versus 39%) among those who completed the trial as planned; the symptom-severity score was clearly lower on the low-FODMAP diet (173 versus 224). Böhn and colleagues (2015) in Sweden compared low-FODMAP against traditional irritable bowel syndrome dietary advice (regular meals, reduced fat, less caffeine, less insoluble fiber) in 75 people and found the two equivalent — 50% versus 46% had their symptom score cut by 50 points or more — a useful finding because it suggests that for some patients the simpler traditional advice is enough.
Response is usually apparent within one to two weeks and solid by week three or four.
The Monash Three-Phase Protocol
The Monash protocol — the version developed and tested by the Monash University research group — is three distinct phases, each depending on the one before it.
- Phase 1 (Elimination): 2 to 6 weeks of strict low-FODMAP eating to see whether symptoms improve at all.
- Phase 2 (Reintroduction): roughly 8 weeks of systematic challenges, adding back one FODMAP subgroup at a time to learn which specific sugars trigger you and at what dose.
- Phase 3 (Personalization): a lifelong, modified diet that excludes only the subgroups and portions you personally tolerate poorly, while reintroducing everything else.
The diet was never designed to be followed strictly for the rest of your life. The elimination phase is a diagnostic tool, not a destination. The reintroduction phase is where the real information is gathered. The personalized phase is the goal.
Phase 1 — Strict Elimination (2–6 Weeks)
During Phase 1 you remove — or sharply reduce — every food known to contain significant FODMAPs. This usually means reading labels, cooking most meals at home, and restaurant eating being awkward for a few weeks. The aim of the phase is to drop the FODMAP load below the reaction threshold; a "mostly low-FODMAP" compromise often gives ambiguous results.
The protocol allows at least two weeks before judging, and up to six when symptoms are severe or slow-responding. Clear improvement by week three or four shows FODMAPs are a real trigger, and the next step in the protocol is Phase 2. When four to six weeks of genuine compliance produces no change at all, FODMAPs are probably not the primary driver, and the protocol ends the diet there and looks at other causes (see When It Doesn't Work).
Detailed Food Lists for the Elimination Phase
These lists are a practical starting point. The authoritative reference — updated as Monash re-tests foods in the lab — is the Monash University FODMAP Diet app, published by the research group that developed the diet. Where the app and a generic web list disagree, the app reflects the newer laboratory testing.
Low-FODMAP Foods
- Grains: brown rice, basmati rice, jasmine rice, quinoa, oats (plain rolled oats in modest portions), corn tortillas, sourdough spelt bread, gluten-free bread that is also onion- and garlic-free, rice noodles, buckwheat.
- Proteins: virtually all plain meats, poultry, fish, and seafood; eggs; tempeh (a fermented soy food); small portions of canned lentils or chickpeas that have been drained and rinsed.
- Dairy and alternatives: hard cheeses (cheddar, parmesan, Swiss) and some soft cheeses such as brie and feta; lactose-free milk, yogurt, and ice cream; almond milk (unsweetened); small amounts of butter.
- Vegetables: carrots, cucumbers, zucchini, spinach, lettuce, kale, bell peppers (red/yellow/green in moderate portions), eggplant, green beans, bok choy, tomatoes, potatoes, sweet potato (about half a cup), parsnip, the green tops of scallions and leeks (not the white bulb), chives.
- Fruits: blueberries, strawberries, raspberries, oranges, grapes, kiwi, pineapple, cantaloupe, firm bananas (not overripe), lemons, limes. Portion matters — most fruits are low-FODMAP at one serving and high at two.
- Fats and extras: olive oil (fats and oils contain no FODMAPs), vinegars, most herbs and spices (not onion or garlic powder), maple syrup in small amounts, plain dark chocolate in small portions.
High-FODMAP Foods Removed in Phase 1
- Wheat, rye, and barley in any substantial portion — bread, pasta, couscous, pastries, flour tortillas, cereal, crackers. The issue is the fructans, not the gluten.
- Onion and garlic in any form — raw, cooked, powdered, dehydrated, in stock cubes, in sauces, in seasonings. This single exclusion is harder than it looks; garlic and onion are hidden in nearly every packaged savory product.
- Most beans and legumes — black beans, kidney beans, pinto beans, soybeans, and large portions of lentils or chickpeas.
- High-FODMAP fruits: apples, pears, mangoes, watermelon, cherries, peaches, plums, apricots, nectarines, blackberries, dried fruit, fruit juice concentrates.
- High-FODMAP vegetables: cauliflower, mushrooms, asparagus, sugar snap peas, artichoke, beetroot in large portions, the white part of leeks, Jerusalem artichoke.
- Regular dairy: cow's milk, regular yogurt, ice cream, soft cheeses such as ricotta and cottage cheese, condensed milk.
- Sweeteners: honey, agave, high-fructose corn syrup, and any sugar alcohol ending in -ol (sorbitol, mannitol, xylitol, maltitol, isomalt, erythritol is better tolerated but still a polyol). Sugar-free gum and mints are a classic hidden source.
- Cashews and pistachios — the two high-GOS nuts. Almonds, walnuts, peanuts, macadamia, and pecans are low-FODMAP in modest portions.
Phase 2 — Systematic Reintroduction (About 8 Weeks)
Phase 2 is the phase people most often skip. Without reintroduction, there is no way to learn which specific FODMAPs actually cause a particular person’s symptoms — and most people only react to two or three of the six subgroups, not all of them.
The method: continue the low-FODMAP baseline, then pick one FODMAP subgroup and test it on day 1, day 3, and day 5 of a week, at increasing doses, while logging symptoms. Between tests and between subgroups, return to a strict low-FODMAP diet for a few days so any reaction clearly belongs to the most recent challenge.
A standard test schedule, one subgroup per week:
- Week 1 — Mannitol: half a cup of button mushrooms, then one cup, then one and a half cups.
- Week 2 — Sorbitol: five blackberries, then ten, then half a cup.
- Week 3 — Lactose: half a cup of milk, then one cup, then one and a half cups.
- Week 4 — Fructose: half a teaspoon of honey, then one teaspoon, then one tablespoon.
- Week 5 — Fructans (wheat): one slice of wheat bread, then two, then three.
- Week 6 — Fructans (onion/garlic): a quarter of a small onion, then half, then a whole one.
- Week 7 — GOS: a quarter cup of chickpeas, then half, then three-quarters.
- Week 8 — Recheck and combine: re-test anything ambiguous, or start combining tolerated subgroups.
The result is a personal map. You will probably discover that one or two subgroups give you trouble at any dose, one or two give you trouble only at larger portions, and the rest you tolerate fine. That map is the whole point of the diet.
Phase 3 — Personalization
Phase 3 is the rest of your life. You keep whatever you learned in Phase 2 and build a diet that excludes, or limits, only your personal triggers. For most people this means one or two permanent restrictions (often onion, garlic, or apples/pears) and otherwise a broadly varied diet.
Every three to six months it is worth re-challenging a previously poorly-tolerated FODMAP. Gut physiology changes with time, stress, infections, and hormone cycles, and tolerances drift. Something that triggered symptoms last year may be fine now.
FODMAP Stacking — The Principle Most People Miss
FODMAPs add up. A single food may be rated "low-FODMAP" at one portion because it contains only a small amount of, say, fructans. Eat three different low-FODMAP fructan-containing foods at the same meal — a slice of sourdough, a bowl of lentil soup, and a cup of sugar snap peas — and the combined fructan load can cross your threshold and trigger symptoms even though no single item was "high" on the list.
This is FODMAP stacking, and it explains most "but I ate only low-FODMAP foods and still felt awful" complaints. The usual approach in the protocol is variety within a meal rather than several moderate sources of the same subgroup, with attention to the total daily load. The Monash app flags stacking risk when you log a meal.
The Monash App and Other Tools
Monash University publishes a FODMAP Diet app (iOS and Android). The Monash team physically tests foods in their laboratory and assigns a traffic-light rating (green, amber, red) at specific serving sizes. People use it for grocery shopping, restaurant decisions, and Phase 2 challenges.
Other tools people use:
- A food and symptom diary — paper or a symptom-tracking app. Phase 2 is very hard to interpret without written records.
- Certified low-FODMAP packaged foods — products laboratory-tested against the low-FODMAP thresholds.
- A registered dietitian trained in the Monash protocol (see the dietitian section for what that guidance covers).
Practical Tactics: Oils, Packaged Foods, Eating Out
The garlic and onion oil trick. Fructans are water-soluble, not oil-soluble. That means you can cook garlic cloves or onion chunks in olive oil, then remove and discard the solids, and keep the infused oil. The oil carries the flavor; the FODMAPs stayed behind in the solids you threw out. Garlic-infused olive oil is a kitchen staple on low-FODMAP and the single most important flavor rescue. Commercial garlic-infused oils are widely available; the low-FODMAP versions have no garlic pieces left suspended in the bottle.
Pre-made products. Certified low-FODMAP packaged foods include pasta sauces, salsas, ketchups, broths and taco seasonings made without onion or garlic. They save time in the elimination phase, particularly for sauces and soup bases, where hidden onion and garlic otherwise dominate.
Eating out. Three tactics people describe:
- Cuisines that can accommodate the diet. Plain grilled meats plus rice and vegetables (steakhouse, Japanese, Korean barbecue, some Thai) are easier than heavily sauced cuisines. Indian and Italian are hardest because of onion-garlic bases.
- Targeted questions. "I have a medical restriction on onion and garlic — does the sauce contain either?" gets a clearer answer than "I'm on a low-FODMAP diet," which servers rarely understand.
- Eating beforehand, or a small snack. When a restaurant has only two safe items, some people eat something solid first and treat the restaurant as a social venue.
Risks of a Prolonged Elimination Phase
Staying in Phase 1 indefinitely — as many patients do when nobody walks them through Phase 2 — causes real harm.
- Nutrient gaps. Long-term low-FODMAP eating can reduce calcium (from restricted dairy), fiber (from restricted wheat, fruit, and legumes), folate, thiamine, and some B vitamins. Studies show measurable drops in several micronutrients after six months of strict elimination.
- Microbiome reduction. FODMAPs are prebiotics. They feed beneficial bacteria, particularly Bifidobacteria. In the Staudacher 2017 trial, stool Bifidobacterium levels were lower after 4 weeks of the low-FODMAP diet than after the sham diet (8.8 versus 9.2 rRNA genes per gram, the study’s measure), the multistrain probiotic raised them (9.1 versus 8.8 on placebo), and overall microbial diversity did not change. The long-term consequences are not known; giving gut bacteria less of their preferred fuel for years may not be neutral.
- Disordered eating risk. Any restrictive diet carries a risk of triggering or worsening orthorexia, particularly in patients with prior eating-disorder history. Escalating fear of food is the warning sign of this risk.
- Social cost. Strict elimination constrains meals out, travel, and family eating. That cost is acceptable for a few weeks of diagnostic clarity; it becomes corrosive over years.
In the Monash protocol, reintroduction is a required step: Phase 1 exists to set up Phase 2.
What Dietitian Guidance Covers
In the clinical trials, the diet was taught through dietary counselling, and Monash runs a training course for registered dietitians in the low-FODMAP protocol; its website lists trained dietitians by country. The points that guidance covers are facts that can also be followed from this page:
- Nutrients that drop on a long elimination. Calcium falls when dairy is restricted, and fiber falls when wheat, fruit and legumes are restricted. Lactose-free milk and yogurt, the hard cheeses, tempeh, oats, brown rice, quinoa and the low-FODMAP fruits and vegetables in the lists above carry these nutrients within the diet.
- A time limit on Phase 1. The strict elimination lasts 2 to 6 weeks. Staying in Phase 1 past that point is the single most common failure of self-guided low-FODMAP attempts.
- One subgroup at a time in Phase 2. Each FODMAP subgroup is tested on its own, at rising doses, with a few strict low-FODMAP days between tests, as in the schedule above; the schedule can be fitted to a person’s own week.
In the U.S., many gastroenterology practices employ or refer to gastrointestinal-specialized dietitians, and telehealth visits are available in rural areas. Insurance coverage of nutrition counseling varies.
When Low-FODMAP Doesn't Work
Roughly one in four irritable bowel syndrome patients gets little or no benefit from a properly executed low-FODMAP trial. If you are one of them, it is a useful data point, not a failure. It means FODMAPs are not your main driver, and the answer lies elsewhere.
Common alternative drivers to investigate next:
- Small intestinal bacterial overgrowth (SIBO) — bacteria have migrated into the small bowel and ferment almost anything you eat, not just FODMAPs. Low-FODMAP may give partial short-term relief but never full relief because the underlying overgrowth is still there. The usual route is a breath test, then antibiotic or herbal treatment. See the irritable bowel syndrome and small intestinal bacterial overgrowth overlap article and the fuller small intestinal bacterial overgrowth overview plus its own low-FODMAP notes.
- Mast cell activation syndrome (MCAS) and histamine intolerance — symptoms are driven by mast-cell mediator release and by dietary histamine, not by fermentable sugars. Many supposedly "safe" low-FODMAP foods (aged cheese, spinach, tomatoes, fermented foods) are high-histamine. A low-histamine trial often works where low-FODMAP did not. See the mast cell activation syndrome page.
- Bile acid diarrhea — unabsorbed bile salts irritate the colon and cause urgent morning diarrhea. Responds dramatically to a bile-acid sequestrant such as colestipol or colesevelam; does not respond to low-FODMAP at all.
- Celiac disease — celiac disease causes irritable-bowel-like symptoms and is excluded with blood (serologic) testing before irritable bowel syndrome is diagnosed. See Celiac Disease.
- Alpha-gal syndrome — a delayed allergy to mammalian meat caused by tick bites, easily mistaken for irritable bowel syndrome because symptoms arrive hours after eating. See Alpha-Gal Syndrome.
- Brain-gut hypersensitivity — when visceral nerves are the main amplifier, dietary changes alone rarely help enough. Gut-directed hypnotherapy and cognitive behavioral therapy (CBT) carry evidence comparable to low-FODMAP. See hypnotherapy and cognitive behavioral therapy.
The Gluten-Free Overlap
A large fraction of people who "went gluten-free and felt better" did not actually react to gluten. Wheat is simultaneously the largest source of gluten and one of the largest sources of fructans in the Western diet. When they stopped eating wheat, they lost both at once — and for the majority, the improvement was the fructans, not the gluten.
The clearest test of this is a 2018 Norwegian trial by Skodje and colleagues. Fifty-nine people who had put themselves on a gluten-free diet, and in whom celiac disease had been excluded, were given muesli bars containing gluten, fructan or neither (placebo) for 7 days each, in random order, with neither they nor the researchers knowing which bar was which. Fructan caused more symptoms and more bloating than gluten (overall symptom scores 38.6 on fructan, 33.1 on gluten, 34.3 on placebo), and gluten caused no more symptoms than placebo. Twenty-four people felt worst on fructan, 13 on gluten and 22 on placebo. This was one trial, and it tested adding fructan back rather than removing it. A 2016 review by Nanayakkara and colleagues summarised the earlier trials of the low-FODMAP diet in irritable bowel syndrome. Celiac testing (blood tests plus, if positive or suspicion is high, endoscopic biopsy) is accurate only while gluten is still being eaten. Once celiac disease is excluded, a structured low-FODMAP trial tests fructans and the other FODMAP groups one at a time, which an open-ended gluten-free diet does not. See Celiac Disease and the broader Elimination Diet page.
Key Research Papers
- Halmos EP, Power VA, Shepherd SJ, Gibson PR, Muir JG. A diet low in FODMAPs reduces symptoms of irritable bowel syndrome. Gastroenterology. 2014;146(1):67–75.e5. doi:10.1053/j.gastro.2013.09.046 — PubMed PMID: 24076059
- Staudacher HM, Lomer MCE, Farquharson FM, Louis P, Fava F, Franciosi E, Scholz M, Tuohy KM, Lindsay JO, Irving PM, Whelan K. A diet low in FODMAPs reduces symptoms in patients with irritable bowel syndrome and a probiotic restores Bifidobacterium species: a randomized controlled trial. Gastroenterology. 2017;153(4):936–947. doi:10.1053/j.gastro.2017.06.010 — PubMed PMID: 28625832
- Böhn L, Störsrud S, Liljebo T, Collin L, Lindfors P, Törnblom H, Simrén M. Diet low in FODMAPs reduces symptoms of irritable bowel syndrome as well as traditional dietary advice: a randomized controlled trial. Gastroenterology. 2015;149(6):1399–1407.e2. doi:10.1053/j.gastro.2015.07.054 — PubMed PMID: 26255043
- Nanayakkara WS, Skidmore PM, O'Brien L, Wilkinson TJ, Gearry RB. Efficacy of the low FODMAP diet for treating irritable bowel syndrome: the evidence to date. Clin Exp Gastroenterol. 2016;9:131–142. doi:10.2147/CEG.S86798 — PubMed PMID: 27382323
- Skodje GI, Sarna VK, Minelle IH, Rolfsen KL, Muir JG, Gibson PR, Veierød MB, Henriksen C, Lundin KEA. Fructan, rather than gluten, induces symptoms in patients with self-reported non-celiac gluten sensitivity. Gastroenterology. 2018;154(3):529–539.e2. doi:10.1053/j.gastro.2017.10.040 — PubMed PMID: 29102613
- Black CJ, Staudacher HM, Ford AC. Efficacy of a low FODMAP diet in irritable bowel syndrome: systematic review and network meta-analysis. Gut. 2022;71(6):1117–1126. doi:10.1136/gutjnl-2021-325214 — PubMed PMID: 34376515
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on FODMAPs, irritable bowel syndrome diet, and related mechanisms:
- PubMed: Low-FODMAP diet and IBS
- PubMed: FODMAP reintroduction and personalization phase
- PubMed: FODMAP diet and microbiome / Bifidobacterium
- PubMed: Fructans and non-celiac wheat sensitivity
- PubMed: Lactose intolerance and IBS
- PubMed: Fructose malabsorption and IBS
- PubMed: Polyols, sorbitol, mannitol and IBS
- PubMed: Low-FODMAP diet and dietitian-led counseling
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Irritable Bowel Syndrome
- Low-FODMAP Diet for Small Intestinal Bacterial Overgrowth
- Small Intestinal Bacterial Overgrowth
- Celiac Disease
- Irritable Bowel Syndrome and Small Intestinal Bacterial Overgrowth Overlap
- Mast Cell Activation Syndrome
- Alpha-Gal Syndrome
- Elimination Diet
- Gut-Directed Hypnotherapy and Cognitive Behavioral Therapy
- Visceral Hypersensitivity and Brain-Gut Axis
- Peppermint, Probiotics, and Herbals
- Rome IV Subtypes
- Post-Infectious Irritable Bowel Syndrome
- Irritable Bowel Syndrome Medications Guide
- Low-Histamine Diet
- Gluten-Free Diet Guide
- Bloating
- Yogurt
- High Resistant Starch Foods — food rankings by RS grams per serving, the cook-and-cool RS3 protocol, a daily ~20g meal plan, and butyrate/short-chain fatty acid (SCFA) mechanism.