Sinusitis
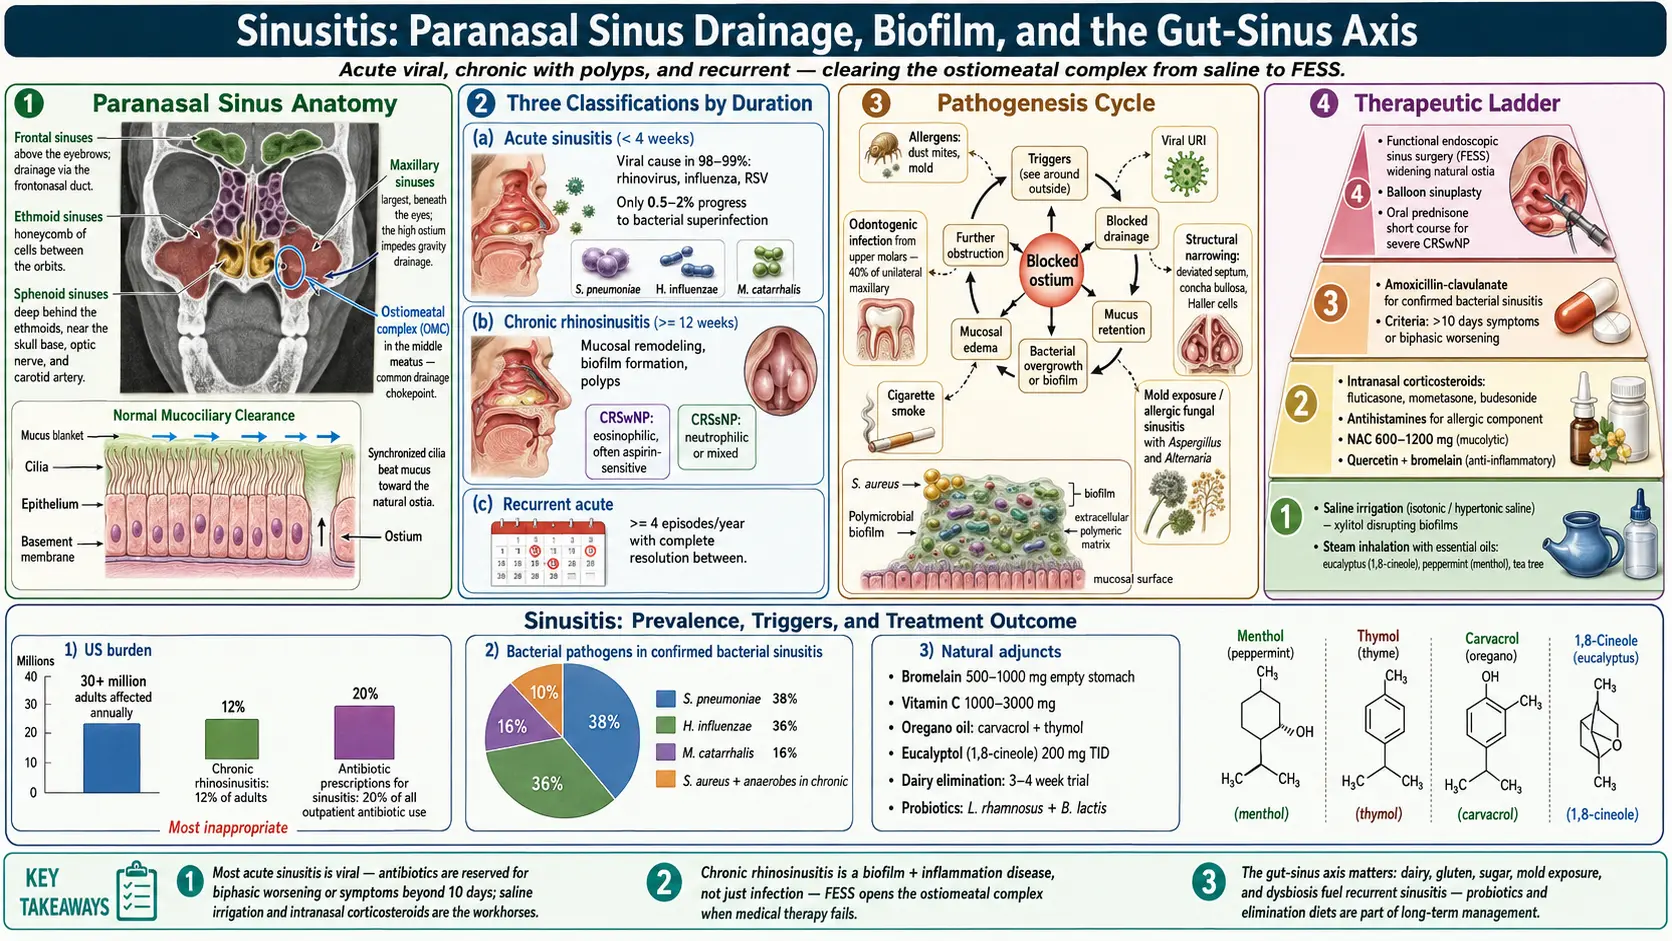
An overview of acute, chronic, and recurrent sinusitis that covers conventional treatment and the natural approaches used in naturopathic practice, with what the research shows for each.
Table of Contents
- What Is Sinusitis?
- Anatomy of the Sinuses
- Causes of Sinusitis
- Risk Factors
- Symptoms
- Conventional Treatment
- Natural and Naturopathic Approaches
- Nasal Irrigation and Steam Inhalation
- Essential Oils for Sinus Support
- Elimination of Dairy and Food Triggers
- Gut Health and Sinus Connection
- Mold Exposure as a Hidden Cause
- Cautions and Warning Signs
- Key Research Papers
- Featured Videos
What Is Sinusitis?
Sinusitis, also called rhinosinusitis, is inflammation of the mucous membranes lining the paranasal sinuses. It is one of the most common health conditions worldwide; a 2011 review of consensus guidelines estimated that rhinosinusitis affects about 1 in 7 adults in the United States (Meltzer and Hamilos 2011). Sinusitis is classified by duration and pattern:
Acute Sinusitis
Under the US guideline, acute sinusitis lasts less than 4 weeks (the European EPOS position paper uses less than 12 weeks), and it is most often triggered by a viral upper respiratory infection (the common cold). Symptoms typically include nasal congestion, purulent or discolored nasal discharge, facial pain or pressure, and reduced sense of smell. Most cases settle without antibiotics: in the placebo and no-treatment groups of the trials pooled by a 2018 Cochrane review, 46 percent of participants were cured after one week and 64 percent after 14 days (Lemiengre 2018). Bacterial infection is estimated to develop in only 0.5 to 2 percent of viral cases (Staudacher and Stevens 2019). Guidelines treat bacterial sinusitis as more likely when symptoms fail to improve within 7 to 10 days or worsen after initial improvement (Aring and Chan 2016).
Chronic Sinusitis
Chronic sinusitis is defined by symptoms lasting longer than 12 weeks, with sinonasal inflammation confirmed on nasal endoscopy or CT (Staudacher and Stevens 2019; Rosenfeld 2015). It is a fundamentally different condition from acute sinusitis, driven by persistent inflammation, mucosal remodeling, biofilm formation, and often an underlying immune or allergic component rather than simple infection. Chronic sinusitis with nasal polyps is a distinct subtype marked by type 2 (eosinophilic) inflammation; it often occurs with asthma, and aspirin-exacerbated respiratory disease is one of its most severe forms (Laidlaw 2021).
Recurrent Acute Sinusitis
Recurrent acute sinusitis is characterized by four or more episodes per year, each lasting less than 4 weeks, with complete resolution between episodes. The US guideline lists assessment for conditions that change management (asthma, cystic fibrosis, an immunocompromised state, ciliary dyskinesia) and, as an option, testing for allergy and immune function (Rosenfeld 2015).
Anatomy of the Sinuses
Understanding sinus anatomy helps explain why sinusitis occurs and why drainage is central to treatment.
The paranasal sinuses are four pairs of air-filled cavities within the facial bones:
- Maxillary sinuses — the largest sinuses, located in the cheekbones below the eyes; most commonly affected in sinusitis because their drainage opening (ostium) is located high on the medial wall, making gravity-dependent drainage difficult
- Frontal sinuses — located in the forehead above the eyebrows; drain through the narrow frontonasal duct into the middle meatus
- Ethmoid sinuses — a honeycomb of small air cells between the eyes; their thin walls are adjacent to the orbits, making orbital complications a concern in severe ethmoid sinusitis
- Sphenoid sinuses — deep sinuses behind the ethmoids near the base of the skull; infection here is less common but potentially more dangerous due to proximity to the brain, optic nerves, and carotid arteries
All sinuses are lined with ciliated pseudostratified columnar epithelium that produces mucus. The cilia beat in a coordinated wave to sweep mucus and trapped particles toward the natural ostia and into the nasal cavity. Any condition that causes mucosal swelling, impairs ciliary function, or increases mucus viscosity can obstruct drainage and set the stage for sinusitis.
Causes of Sinusitis
Viral
Viruses cause the vast majority of acute sinusitis episodes. Rhinovirus is the most common culprit, followed by influenza, parainfluenza, and respiratory syncytial virus. Viral infection causes mucosal edema that obstructs sinus ostia, traps mucus, and impairs ciliary clearance.
Bacterial
Bacterial sinusitis typically develops as a secondary complication of viral sinusitis. The most common pathogens are Streptococcus pneumoniae, Haemophilus influenzae, and Moraxella catarrhalis. In chronic sinusitis, Staphylococcus aureus, anaerobic bacteria, and polymicrobial biofilms play a more prominent role.
Fungal
Fungal sinusitis takes several forms. Allergic fungal sinusitis is a hypersensitivity reaction to fungal elements (commonly Aspergillus or Alternaria) trapped in thick mucus, and is a significant cause of chronic sinusitis with nasal polyps. Fungal ball (mycetoma) is a non-invasive mass of fungal hyphae, usually in the maxillary sinus. Invasive fungal sinusitis is a life-threatening emergency occurring in immunocompromised patients.
Allergic
Allergic rhinitis is one of the strongest risk factors for sinusitis. Allergen-triggered inflammation causes chronic mucosal swelling and mucus hypersecretion that predispose to sinus obstruction. Common aeroallergens include dust mites, mold spores, pet dander, and pollens.
Risk Factors
- Allergies — allergic rhinitis creates chronic mucosal inflammation that obstructs sinus drainage; both seasonal and perennial allergies increase sinusitis risk
- Structural abnormalities — deviated nasal septum, concha bullosa (pneumatized middle turbinate), paradoxical middle turbinate, and Haller cells can narrow the ostiomeatal complex and impair drainage
- Nasal polyps — benign growths arising from inflamed mucosa that physically obstruct sinus ostia
- Immune deficiency — IgA deficiency, common variable immunodeficiency, and other immune disorders predispose to recurrent and chronic sinusitis; HIV/AIDS increases risk of opportunistic fungal sinusitis
- Dental infections — the roots of the upper premolars and molars are separated from the maxillary sinus floor by only a thin layer of bone; periapical abscesses, periodontal disease, or complications from dental procedures can cause odontogenic sinusitis, which made up 45 percent of unilateral sinus disease with complete maxillary sinus opacification on CT in a 2019 prospective series (Turfe 2019) and about 70 percent of unilateral sinusitis in a Japanese chart review of 190 patients (Matsumoto 2015)
- Ciliary dyskinesia — primary ciliary dyskinesia and secondary impairment from smoking, pollution, or viral damage
- Environmental irritants — cigarette smoke, air pollution, chlorine, and occupational chemical exposure
- GERD — laryngopharyngeal reflux may contribute to chronic nasal and sinus inflammation
- Swimming and diving — chlorinated water and barotrauma can irritate sinus mucosa
Symptoms
The cardinal symptoms of sinusitis include:
- Nasal congestion and obstruction — difficulty breathing through one or both nostrils
- Nasal discharge — anterior (from the nose) or posterior (postnasal drip); may be clear, yellow, green, or blood-tinged
- Facial pain and pressure — location depends on which sinuses are affected: cheek and upper teeth (maxillary), forehead (frontal), between the eyes (ethmoid), or top of the head and behind the eyes (sphenoid)
- Reduced or lost sense of smell (hyposmia or anosmia)
- Headache — often worse with bending forward
- Ear fullness or pressure — due to eustachian tube dysfunction
- Cough — particularly at night from postnasal drip
- Fatigue and malaise
- Bad breath (halitosis) — from stagnant infected mucus
- Dental pain — upper teeth may ache due to maxillary sinus floor inflammation
Conventional Treatment
Antibiotics
Antibiotics are reserved for presumed bacterial sinusitis. For uncomplicated cases the 2015 US guideline gives clinicians two choices, watchful waiting without antibiotics or initial antibiotic treatment, and names amoxicillin with or without clavulanate for 5 to 10 days as first-line therapy when an antibiotic is used (Rosenfeld 2015); doxycycline or a respiratory fluoroquinolone are the alternatives usually listed for penicillin allergy. A 2018 Cochrane review of 15 trials found that only 5 to 11 more people per 100 were cured faster with antibiotics than with placebo or no treatment, while 13 more per 100 had side effects, and its authors concluded there is no place for antibiotics in uncomplicated acute rhinosinusitis (Lemiengre 2018). Overuse of antibiotics for viral sinusitis contributes to antibiotic resistance.
Corticosteroids
Intranasal corticosteroid sprays (fluticasone, mometasone, budesonide) are a mainstay of both acute and chronic sinusitis treatment. They reduce mucosal inflammation and edema, improving sinus drainage and symptom relief. Short courses of oral corticosteroids (prednisone) may be used for severe acute sinusitis or chronic sinusitis with nasal polyps.
Decongestants
Topical decongestants (oxymetazoline) provide rapid but temporary relief by constricting blood vessels in the nasal mucosa. Over-the-counter labeling limits their use to 3 days because longer use can cause rebound congestion (rhinitis medicamentosa). Oral decongestants (pseudoephedrine) can raise blood pressure.
Surgery
Functional endoscopic sinus surgery (FESS) is considered when medical therapy fails after adequate trials. FESS widens the natural sinus ostia, removes polyps and diseased tissue, and restores normal drainage pathways. It is performed endoscopically through the nostrils with no external incisions. Balloon sinuplasty is a less invasive alternative for select patients, using an inflatable catheter to dilate blocked ostia.
Natural and Naturopathic Approaches
Naturopathic practice approaches sinusitis with the aims of clearing infection, reducing inflammation, restoring mucosal health, addressing predisposing factors, and supporting immune function. The evidence behind the agents below varies widely. A 2006 systematic review of 10 randomized trials found limited evidence that any herbal medicine helps rhinosinusitis, particularly chronic rhinosinusitis, with the most encouraging results for bromelain and a standardized five-herb combination product as add-on treatments in acute sinusitis (Guo 2006).
N-Acetylcysteine (NAC) as a Mucolytic
NAC breaks disulfide bonds in mucus glycoproteins, reducing viscosity, and it replenishes intracellular glutathione. Most of its clinical evidence comes from lung disease: a 2015 meta-analysis of 13 studies in chronic bronchitis and COPD found fewer exacerbations with NAC (relative risk 0.75) and compared daily doses of up to 600 mg with doses above 600 mg (Cazzola 2015). In sinus disease, a small 2024 randomized trial of NAC irrigation after sinus surgery (49 patients with chronic sinusitis without polyps) reported less postnasal drip, smell loss, and crusting than with saline at two weeks, and no difference at one and three months (Wee 2024).
Quercetin
Quercetin is a flavonoid with anti-inflammatory and mast cell-stabilizing properties in laboratory research: it inhibits histamine release and reduces the production of pro-inflammatory cytokines and leukotrienes. These findings come from laboratory and animal studies rather than sinusitis trials in people, and the claim that pairing it with bromelain improves absorption has not been tested in such trials.
Bromelain
Bromelain, a proteolytic enzyme from pineapple stems, is reported to reduce mucosal inflammation and edema and to thin mucus. A 2006 systematic review found three randomized trials of bromelain in sinusitis, all reporting some positive findings; pooling the two trials in acute sinusitis suggested that bromelain added to standard treatment significantly improved some symptoms (Guo 2006).
Vitamin C
Vitamin C supports immune function through multiple mechanisms: enhancing neutrophil chemotaxis and phagocytosis, supporting epithelial barrier integrity, and providing antioxidant protection. Trials in sinusitis itself are lacking. For the common cold, a 2013 Cochrane review found that regular daily supplementation shortened colds in adults by 8 percent, while vitamin C started after symptoms began had no consistent effect on duration or severity (Hemilä and Chalker 2013).
Oregano Oil
Oil of oregano (Origanum vulgare) contains carvacrol and thymol, which have broad-spectrum antimicrobial activity against bacteria, fungi, and some viruses in laboratory studies. Its use in sinusitis, as capsules or in steam inhalation, rests on these laboratory findings rather than clinical trials. Undiluted oregano oil irritates mucous membranes.
Garlic
Garlic (Allium sativum) contains allicin and other sulfur compounds with antimicrobial and antiviral activity in laboratory studies; allicin forms when raw garlic is crushed. Trials in sinusitis are lacking. A 2014 Cochrane review of garlic for the common cold found only one eligible trial: 146 people taking a daily allicin-containing garlic supplement or placebo for 12 weeks reported 24 colds versus 65, but recovery time was similar, and the reviewers judged the evidence insufficient (Lissiman 2014).
Goldenseal and Berberine
Goldenseal (Hydrastis canadensis) and its primary alkaloid berberine have antimicrobial activity against common sinusitis pathogens including Staphylococcus aureus and Streptococcus species. Berberine also has anti-inflammatory and immune-modulating effects in laboratory research. The US National Center for Complementary and Integrative Health (NCCIH) states that no rigorous studies have evaluated goldenseal for health conditions in people, that goldenseal may change how the body processes many medications (in one NCCIH-funded study, metformin levels fell about 25 percent), and that wild goldenseal has been overharvested. Oregon grape root (Mahonia aquifolium) is another berberine-containing plant.
Nasal Irrigation and Steam Inhalation
Neti Pot and Saline Irrigation
Nasal saline irrigation is widely used for sinusitis. The 2016 Cochrane review of saline for chronic rhinosinusitis (Chong et al.) found only two trials: daily large-volume (150 ml) hypertonic saline irrigation showed some benefit over usual care, with the evidence rated low quality at three months and very low quality at six months, while a low-volume (5 ml) nebulised saline spray showed no benefit over intranasal corticosteroids. A 2016 primary-care trial of 871 adults with chronic or recurrent sinus symptoms found that advice to use daily saline irrigation gave a smaller benefit than earlier trials suggested, though more patients kept a clinically important improvement at six months (44.1 versus 36.6 percent) (Little 2016). Irrigation is thought to work by flushing mucus, allergens, bacteria, and inflammatory mediators from the nasal passages and reducing mucosal edema.
- Irrigation is done with a neti pot, squeeze bottle, or pulsating device, using isotonic or hypertonic saline; the trial with a benefit in the Cochrane review used 150 ml of 2 percent hypertonic saline daily (Chong 2016)
- The US FDA states that water for nasal rinsing must be distilled or sterile, tap water boiled for 3 to 5 minutes and cooled, or water passed through a filter designed to trap infectious organisms, because organisms such as amoebas in tap water can cause serious and, rarely, fatal infections
Xylitol Nasal Rinse
Xylitol has been studied as an irrigation solution. In a 2011 randomized crossover pilot study of 20 adults with chronic sinusitis (15 analysed), 10 days of xylitol-in-water irrigation improved SNOT-20 symptom scores more than saline, with no difference in visual analogue scores (Weissman 2011). Proposed mechanisms include reduced bacterial adherence to the mucosa and effects on biofilms.
Steam Inhalation
Steam inhalation is used to loosen thick mucus and soothe inflamed mucosa. In the 2016 primary-care trial, advice to use daily steam inhalation reduced headache but had no significant effect on other sinus outcomes, and the authors concluded it was not effective for chronic or recurrent sinus symptoms (Little 2016). Adding essential oils such as eucalyptus, peppermint, or tea tree is a common practice whose added effect has not been established. Warm, wet compresses on the face are another traditional comfort measure.
Essential Oils for Sinus Support
Several essential oils are used for sinus symptoms; the evidence for each differs.
Eucalyptus Oil
Eucalyptus (Eucalyptus globulus or E. radiata) contains 1,8-cineole (eucalyptol), which has mucolytic, anti-inflammatory, and antimicrobial properties. A randomized placebo-controlled trial in 152 patients with acute nonpurulent rhinosinusitis found that oral cineole capsules (200 mg three times daily for 7 days) significantly reduced a symptom score compared with placebo (Kehrl 2004). Eucalyptus oil is also used in steam inhalation or diluted on the chest and temples.
Peppermint Oil
Peppermint (Mentha piperita) contains menthol, which activates cold receptors in the nasal mucosa. In a randomized trial of 62 people with common-cold congestion, an 11 mg menthol lozenge improved the sensation of nasal airflow without changing measured nasal resistance (Eccles 1990): the feeling of easier breathing is a sensory effect rather than decongestion. Menthol is used in steam inhalation or diluted in a carrier oil on the skin; direct contact irritates the eyes and mucous membranes.
Tea Tree Oil
Tea tree (Melaleuca alternifolia) has broad-spectrum antimicrobial activity including against Staphylococcus aureus and fungal organisms relevant to chronic sinusitis in laboratory studies. It is toxic when swallowed: in one case report a 4-year-old who swallowed a small amount became ataxic and then unresponsive within 30 minutes and needed intubation before recovering (Morris 2003). Undiluted, it irritates the nasal passages.
Safety note: Essential oils are potent and concentrated. Undiluted oils irritate skin and mucous membranes, oils placed directly in the nose irritate the nasal lining, and swallowed oils have poisoned young children.
Elimination of Dairy and Food Triggers
Identifying food triggers is a central part of the naturopathic approach to chronic and recurrent sinusitis, though controlled research on most of these triggers is limited.
Dairy
Dairy is the food most often blamed for sinus congestion in naturopathic practice, but controlled research does not support the belief that milk increases mucus. A 2005 review reported that in people inoculated with a cold virus, milk intake was not associated with more nasal secretions or congestion, and that a taste-matched soy drink produced the same perceived mucus changes as cow's milk; people who believe in the milk-mucus link report more symptoms after drinking milk (Wüthrich 2005). Proposed, unproven mechanisms include:
- Casein protein triggering an inflammatory immune response in sensitive individuals
- A1 beta-casein (from conventional cow's milk) generating beta-casomorphin-7, which a 2010 hypothesis paper proposed could stimulate mucus secretion from respiratory MUC5AC glands, an idea its authors set out as still to be tested (Bartley and McGlashan 2010)
- Undiagnosed cow's milk allergy, which in a few documented cases has produced asthma-like symptoms (Wüthrich 2005)
Naturopathic practitioners use a strict dairy elimination of 3 to 4 weeks, followed by systematic reintroduction, to judge individual sensitivity.
Other Food Triggers
- Gluten — wheat and other gluten-containing grains may promote inflammation in sensitive individuals, even without celiac disease
- Refined sugar — held in naturopathic practice to promote inflammation
- Alcohol — causes nasal congestion through vasodilation and histamine release; beer and wine contain additional histamine and sulfites
- Histamine-rich foods — aged cheeses, fermented foods, cured meats, and vinegar may worsen symptoms in patients with histamine intolerance
- Food additives — sulfites, MSG, and artificial colorings may trigger nasal symptoms in sensitive individuals
An anti-inflammatory diet emphasizing vegetables, fruits, omega-3 fatty acids, and whole foods while minimizing processed foods, sugar, and common allergens is the dietary pattern naturopathic practice pairs with these eliminations.
Gut Health and Sinus Connection
Emerging research highlights the interconnection between gut health and respiratory mucosal immunity, often termed the gut-lung axis. Its relevance to chronic and recurrent sinusitis is still largely theoretical.
- Mucosal immune system — the gut-associated lymphoid tissue (GALT) and nasal-associated lymphoid tissue (NALT) are part of a common mucosal immune system; immune cells educated in the gut migrate to and protect respiratory mucosa
- Microbiome diversity — a diverse gut microbiome supports balanced immune function; dysbiosis (from antibiotics, poor diet, or stress) is thought to skew the immune response toward excessive inflammation and allergic reactivity
- Antibiotic disruption — repeated courses of antibiotics for sinusitis can deplete beneficial gut and nasal bacteria, and naturopathic practice holds that this feeds a cycle of recurrent infection; it pairs antibiotic courses with probiotics
- Probiotics for sinusitis — in a placebo-controlled trial of 77 patients with chronic sinusitis, an oral Lactobacillus rhamnosus strain (R0011) did not improve sinonasal quality of life compared with placebo (Mukerji 2009); for preventing acute upper respiratory infections in general, a 2022 Cochrane review of 23 trials found that probiotics (often Lactobacillus plantarum or Lactobacillus paracasei strains) may reduce the number of people with at least one infection (risk ratio 0.76, low-certainty evidence) (Zhao 2022)
- Intestinal permeability — increased gut permeability (leaky gut) is proposed to let food antigens and bacterial endotoxins enter the bloodstream and promote systemic inflammation that shows up as chronic sinus inflammation; this link remains a hypothesis
- Gut healing — addressing gut health through elimination of trigger foods, probiotic and prebiotic supplementation, glutamine, zinc carnosine, and anti-inflammatory herbs is aimed at an indirect benefit on chronic sinusitis
Mold Exposure as a Hidden Cause
Integrative practitioners regard mold exposure as an underrecognized cause of chronic sinusitis, particularly when symptoms persist or resist treatment. A 1999 Mayo Clinic study cultured fungi from the nasal mucus of 96 percent of 210 consecutive chronic sinusitis patients and proposed that most chronic sinusitis involves an eosinophilic response to fungi (Ponikau 1999); trials of antifungal treatment have not shown clear benefit (see below).
How Mold Causes Sinusitis
- Allergic response — mold spores are potent aeroallergens that trigger IgE-mediated inflammation in the nasal and sinus mucosa
- Fungal colonization — inhaled mold spores can colonize the warm, moist environment of the sinuses, especially in the setting of pre-existing mucosal damage or immune compromise
- Mycotoxin exposure — some mold species produce toxic secondary metabolites (mycotoxins) including aflatoxins, ochratoxin, and trichothecenes that can impair immune function, damage mucosal barriers, and promote chronic inflammation
- Inflammatory cascade — mold exposure is proposed to activate the innate immune system and drive a chronic inflammatory response even at exposure levels below those that trigger classic allergic symptoms
Identifying Mold Exposure
- Mold assessment looks for visible mold, water damage, musty odors, and humidity problems in the home and workplace
- Common problem areas include bathrooms, basements, HVAC systems, window sills, and behind walls with water damage
- Professional mold testing (air sampling, surface sampling) measures exposure levels
- Urine mycotoxin testing is used by some integrative practitioners; its value in diagnosing sinusitis has not been established in controlled studies
Addressing Mold-Related Sinusitis
- US EPA guidance is that small mold areas (under about 10 square feet) can usually be cleaned by householders, while larger areas or extensive water damage call for experienced remediation professionals
- HEPA air purifiers are used to reduce airborne mold spore counts
- EPA guidance is to keep indoor humidity below 60 percent, ideally between 30 and 50 percent
- Antifungal treatment has been tested: a 2018 Cochrane review of eight trials (490 adults), mostly of topical amphotericin B, found no clear benefit on quality of life or symptoms in chronic sinusitis and more local irritation (Head 2018), and the 2015 US guideline recommends against topical or systemic antifungals for chronic sinusitis (Rosenfeld 2015). Some practitioners use dilute povidone-iodine or colloidal silver irrigations; colloidal silver can cause argyria, a permanent blue-gray discoloration of the skin
- Mycotoxin-illness protocols use glutathione, NAC, activated charcoal, and cholestyramine with the aim of increasing mycotoxin clearance; these regimens lack controlled trial evidence in sinusitis
Cautions and Warning Signs
Most sinusitis settles without specialist care, but clinical guidelines describe the following as reasons for prompt medical evaluation:
- High fever (above 102 degrees F or 39 degrees C) with facial pain — may indicate severe bacterial infection
- Periorbital swelling, redness, or vision changes — orbital cellulitis is a serious complication of ethmoid sinusitis requiring urgent treatment
- Severe headache, stiff neck, or altered mental status — may indicate intracranial complications such as meningitis, epidural abscess, or cavernous sinus thrombosis
- Symptoms lasting beyond 10 days without improvement — meets the guideline picture of presumed bacterial sinusitis, for which the US guideline lists watchful waiting or antibiotics (Rosenfeld 2015)
- Recurrent episodes (four or more per year) — prompt assessment for underlying allergies, immune deficiency, structural abnormalities, or dental disease
- Unilateral symptoms with bloody nasal discharge — are evaluated to rule out dental infection, fungal disease, or, rarely, sinonasal malignancy
Important notes on natural treatments:
- Tap water used for nasal irrigation carries a risk of amoebic infection; the FDA lists distilled, sterile, boiled-and-cooled, or specially filtered water as safe
- Undiluted essential oils irritate the nasal passages
- NCCIH states that goldenseal should not be used during pregnancy or breastfeeding or given to infants, because its berberine can be harmful to newborns
- High-dose vitamin C can cause gastrointestinal discomfort and diarrhea
- Bromelain may increase bleeding risk in people taking anticoagulant medications
- Natural approaches are generally described as complements to, not replacements for, medical care for severe or complicated sinusitis
- Decisions about treatment belong with a clinician
Key Research Papers
- Rosenfeld RM, Piccirillo JF, Chandrasekhar SS, et al. Clinical practice guideline (update): adult sinusitis. Otolaryngol Head Neck Surg. 2015;152(2 Suppl):S1-S39. — doi:10.1177/0194599815572097
- Fokkens WJ, Lund VJ, Hopkins C, et al. European Position Paper on Rhinosinusitis and Nasal Polyps 2020 (EPOS 2020). Rhinology. 2020;58(Suppl S29):1-464. — doi:10.4193/Rhin20.600
- Meltzer EO, Hamilos DL. Rhinosinusitis diagnosis and management for the clinician: a synopsis of recent consensus guidelines. Mayo Clin Proc. 2011;86(5):427-443. — doi:10.4065/mcp.2010.0392
- Head K, Snidvongs K, Glew S, Scadding G, Schilder AG, Philpott C, Hopkins C. Saline irrigation for allergic rhinitis. Cochrane Database Syst Rev. 2018;6(6):CD012597. — PubMed PMID: 29932206
- Ponikau JU, Sherris DA, Kern EB, et al. The diagnosis and incidence of allergic fungal sinusitis. Mayo Clin Proc. 1999;74(9):877-884. — doi:10.4065/74.9.877
- Harvey R, Hannan SA, Badia L, Scadding G. Nasal saline irrigations for the symptoms of chronic rhinosinusitis. Cochrane Database Syst Rev. 2007;(3):CD006394. — doi:10.1002/14651858.cd006394 — Withdrawn (withdrawn April 2016 and replaced by Chong 2016, “Saline irrigation for chronic rhinosinusitis”; withdrawal notice: PubMed PMID: 27110699)
- Chong LY, Head K, Hopkins C, Philpott C, Glew S, Scadding G, Burton MJ, Schilder AG. Saline irrigation for chronic rhinosinusitis. Cochrane Database Syst Rev. 2016;4(4):CD011995. — PubMed PMID: 27115216
- Desrosiers MY, Kilty SJ. Treatment alternatives for chronic rhinosinusitis persisting after ESS: what to do when antibiotics, steroids and surgery fail. Rhinology. 2008;46(1):3-14. — PubMed PMID: 18444486
- Cazzola M, Calzetta L, Page CP, et al. Influence of N-acetylcysteine on chronic bronchitis or COPD exacerbations: a meta-analysis. Eur Respir Rev. 2015;24(137):451-461. — doi:10.1183/16000617.00002215
- Bachert C, Zhang L, Gevaert P. Current and future treatment options for adult chronic rhinosinusitis: focus on nasal polyposis. J Allergy Clin Immunol. 2015;136(6):1431-1440. — doi:10.1016/j.jaci.2015.10.010
- Laidlaw TM, Mullol J, Woessner KM, Amin N, Mannent LP. Chronic rhinosinusitis with nasal polyps and asthma. J Allergy Clin Immunol Pract. 2021;9(3):1133-1141. — doi:10.1016/j.jaip.2020.09.063
- Guo R, Canter PH, Ernst E. Herbal medicines for the treatment of rhinosinusitis: a systematic review. Otolaryngol Head Neck Surg. 2006;135(4):496-506. — doi:10.1016/j.otohns.2006.06.1254
- Ahovuo-Saloranta A, Rautakorpi UM, Borisenko OV, et al. Antibiotics for acute maxillary sinusitis in adults. Cochrane Database Syst Rev. 2014;(2):CD000243. — doi:10.1002/14651858.CD000243.pub3 — Withdrawn (withdrawn October 2015 and merged into the updated review “Antibiotics for acute rhinosinusitis in adults”, so that one review covers both clinically diagnosed and imaging-confirmed sinusitis; withdrawal notice: PubMed PMID: 26471061)
- Lemiengre MB, van Driel ML, Merenstein D, Liira H, Mäkelä M, De Sutter AI. Antibiotics for acute rhinosinusitis in adults. Cochrane Database Syst Rev. 2018;9(9):CD006089. — PubMed PMID: 30198548
- Aring AM, Chan MM. Current concepts in adult acute rhinosinusitis. Am Fam Physician. 2016;94(2):97-105. — PubMed PMID: 27419326
- Staudacher AG, Stevens WW. Sinus infections, inflammation, and asthma. Immunol Allergy Clin North Am. 2019;39(3):403-415. — PubMed PMID: 31284929
- Turfe Z, Ahmad A, Peterson EI, Craig JR. Odontogenic sinusitis is a common cause of unilateral sinus disease with maxillary sinus opacification. Int Forum Allergy Rhinol. 2019;9(12):1515-1520. — PubMed PMID: 31529785
- Matsumoto Y, Ikeda T, Yokoi H, Kohno N. Association between odontogenic infections and unilateral sinus opacification. Auris Nasus Larynx. 2015;42(4):288-293. — PubMed PMID: 25638394
- Wee JH, Park JH, Park MW, Choi YS, Jung HJ. Sinus irrigation with N-acetylcysteine after endoscopic sinus surgery for chronic rhinosinusitis: a preliminary report of a single-blind randomized controlled trial. Diagnostics (Basel). 2024;14(15):1678. — PubMed PMID: 39125554
- Hemilä H, Chalker E. Vitamin C for preventing and treating the common cold. Cochrane Database Syst Rev. 2013;(1):CD000980. — PubMed PMID: 23440782
- Lissiman E, Bhasale AL, Cohen M. Garlic for the common cold. Cochrane Database Syst Rev. 2014;(11):CD006206. — PubMed PMID: 25386977
- Little P, Stuart B, Mullee M, et al. Effectiveness of steam inhalation and nasal irrigation for chronic or recurrent sinus symptoms in primary care: a pragmatic randomized controlled trial. CMAJ. 2016;188(13):940-949. — PubMed PMID: 27431306
- Weissman JD, Fernandez F, Hwang PH. Xylitol nasal irrigation in the management of chronic rhinosinusitis: a pilot study. Laryngoscope. 2011;121(11):2468-2472. — PubMed PMID: 21994147
- Kehrl W, Sonnemann U, Dethlefsen U. Therapy for acute nonpurulent rhinosinusitis with cineole: results of a double-blind, randomized, placebo-controlled trial. Laryngoscope. 2004;114(4):738-742. — PubMed PMID: 15064633
- Eccles R, Jawad MS, Morris S. The effects of oral administration of (-)-menthol on nasal resistance to airflow and nasal sensation of airflow in subjects suffering from nasal congestion associated with the common cold. J Pharm Pharmacol. 1990;42(9):652-654. — PubMed PMID: 1981905
- Morris MC, Donoghue A, Markowitz JA, Osterhoudt KC. Ingestion of tea tree oil (Melaleuca oil) by a 4-year-old boy. Pediatr Emerg Care. 2003;19(3):169-171. — PubMed PMID: 12813303
- Wüthrich B, Schmid A, Walther B, Sieber R. Milk consumption does not lead to mucus production or occurrence of asthma. J Am Coll Nutr. 2005;24(6 Suppl):547S-555S. — PubMed PMID: 16373954
- Bartley J, McGlashan SR. Does milk increase mucus production? Med Hypotheses. 2010;74(4):732-734. — PubMed PMID: 19932941
- Mukerji SS, Pynnonen MA, Kim HM, Singer A, Tabor M, Terrell JE. Probiotics as adjunctive treatment for chronic rhinosinusitis: a randomized controlled trial. Otolaryngol Head Neck Surg. 2009;140(2):202-208. — PubMed PMID: 19201289
- Zhao Y, Dong BR, Hao Q. Probiotics for preventing acute upper respiratory tract infections. Cochrane Database Syst Rev. 2022;8(8):CD006895. — PubMed PMID: 36001877
- Head K, Sharp S, Chong LY, Hopkins C, Philpott C. Topical and systemic antifungal therapy for chronic rhinosinusitis. Cochrane Database Syst Rev. 2018;9(9):CD012453. — PubMed PMID: 30199594
Historical Background
Nasal disease was described in ancient medicine; the Hippocratic writers and later Galen wrote about the nasal passages and believed phlegm could descend from the brain. Leonardo da Vinci drew the paranasal sinuses around 1489, but his drawings stayed unpublished; Nathaniel Highmore's published description of the maxillary sinus in 1651 gave it the name antrum of Highmore. Walter Messerklinger in Graz, Austria, mapped mucociliary clearance of the sinuses, Heinz Stammberger developed and championed the endoscopic technique, and David Kennedy introduced functional endoscopic sinus surgery (FESS) to North America in the 1980s. A fuller account is on the History of Sinusitis page.
PubMed Topic Searches
The following PubMed topic searches retrieve current peer-reviewed literature on Sinusitis. Each link opens a live PubMed query so you always see the most recent publications.
- PubMed: Chronic rhinosinusitis review
- PubMed: Acute bacterial sinusitis diagnosis
- PubMed: Saline nasal irrigation sinusitis
- PubMed: Intranasal corticosteroid rhinosinusitis
- PubMed: Dupilumab chronic rhinosinusitis nasal polyps
- PubMed: Fungal sinusitis allergic
- PubMed: Endoscopic sinus surgery outcomes
- PubMed: Sinusitis antibiotic stewardship
- PubMed: Xylitol nasal spray sinusitis
- PubMed: Eucalyptus essential oil sinus
- PubMed: Quercetin allergic rhinitis sinus
Connections
- ENT
- Oregano
- Vitamin C
- Garlic
- Berberine
- Eucalyptus
- Quercetin
- Omega-3 Fatty Acids
- Probiotics
- Gut Healing
- Anti-Inflammatory Diet
- Thyme
- Oral Microbiome
- Immune Boosting
- Vitamin D3
- Goldenseal
- Allergies
- Peppermint
- NAC
- Hearing Loss
- Common Cold
- Strep Throat
- Ear Infections
- Trigeminal Neuralgia
- Herbs covered on this site that discuss this condition: Echinacea (Echinacea purpurea) · Elderberry (Sambucus nigra) · Andrographis (Andrographis paniculata) · Sage (Salvia officinalis) · Kencur (Kaempferia galanga) · Carum / Ajwain (Trachyspermum ammi)
- Tinnitus
- Herbs