⚠ Evidence warning: Clinical trials or other evidence do not support the claim that a 5% tea tree oil body wash reduces mite burden in a pig model of scabies. This page keeps it as a report of what people, websites or other media say.
Scabies
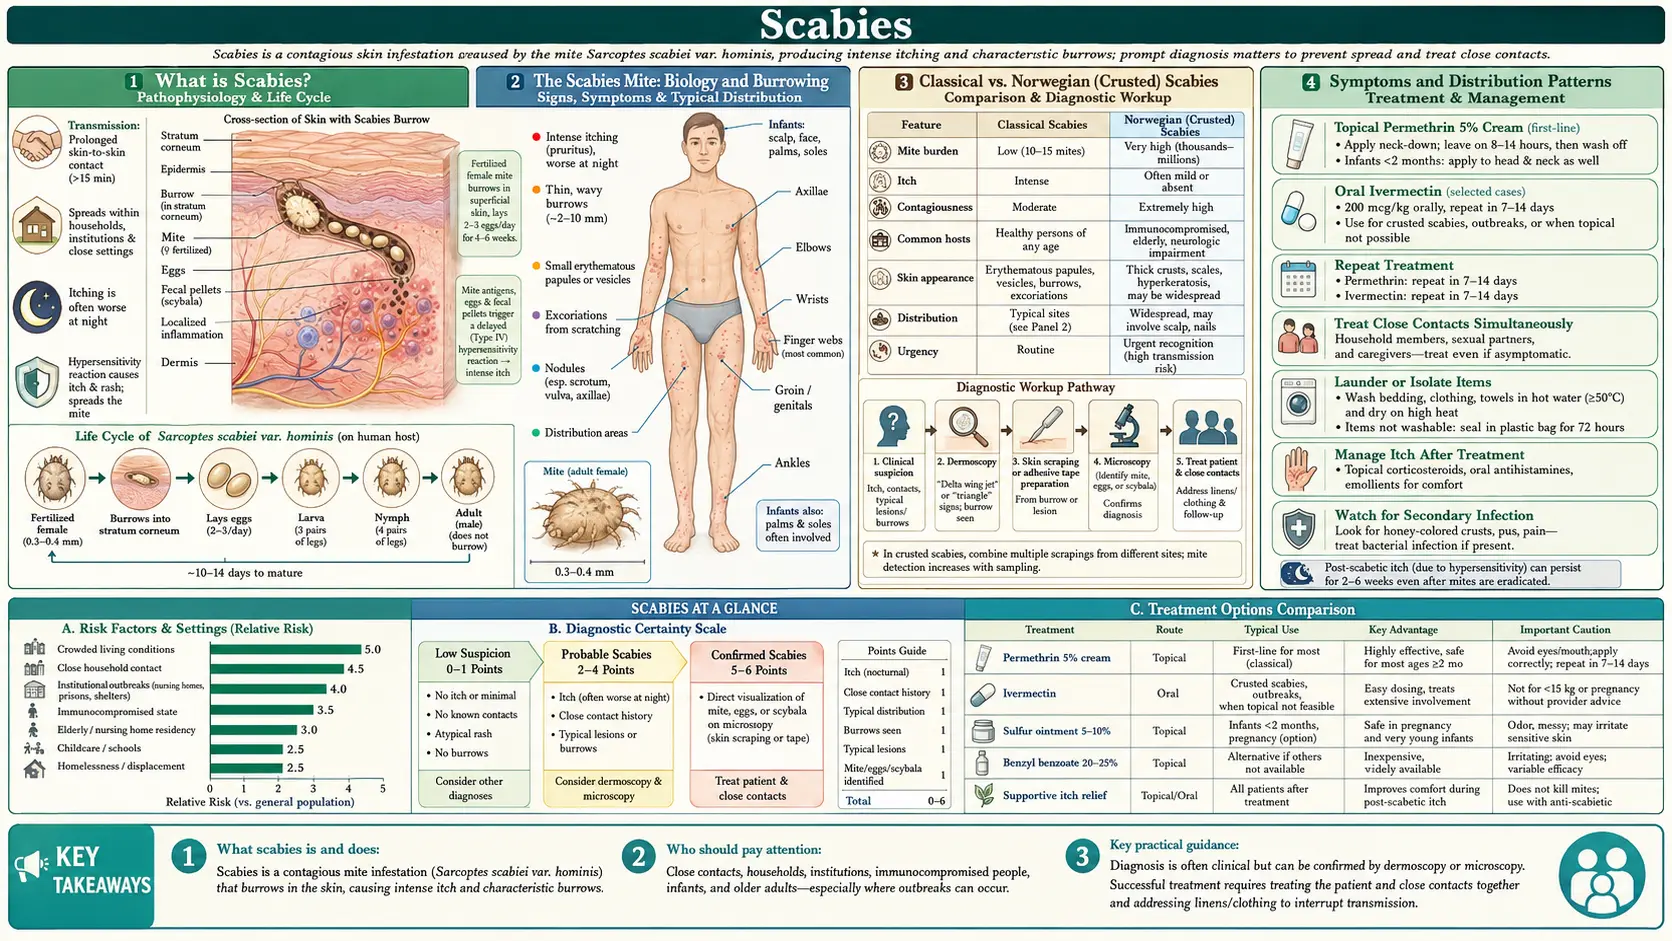
Table of Contents
- What Scabies Is
- The Scabies Mite: Biology and Burrowing
- Classical vs. Norwegian (Crusted) Scabies
- Symptoms and Distribution Patterns
- Diagnosis: Dermoscopy and Skin Scraping
- Treatment: Permethrin and Ivermectin
- Treating Household Members and Environment
- Natural and Supportive Approaches
- Complications
- Prevention and Contagion Control
- Key Research Papers
- PubMed Searches
- Connections
- Featured Videos
What Scabies Is
Scabies is a highly contagious parasitic skin infestation caused by the microscopic mite Sarcoptes scabiei var. hominis. The female mite burrows into the outermost layer of skin (stratum corneum) to lay eggs, triggering an immune reaction that causes intense, often unbearable itching. Scabies affects people of all ages, races, and socioeconomic groups and is considered a Neglected Tropical Disease by the World Health Organization, with an estimated 200–300 million cases worldwide annually.
The condition is not a sign of poor hygiene. Scabies spreads through prolonged skin-to-skin contact — it is common in households, nursing homes, prisons, and schools. Sexual transmission is a significant route in adults. The mite cannot jump or fly; it crawls at approximately 2.5 cm per minute on warm skin.
The Scabies Mite: Biology and Burrowing
- Taxonomy: Sarcoptes scabiei var. hominis; an obligate human parasite in the family Sarcoptidae. About 0.3–0.4 mm long (barely visible to the naked eye as a white dot).
- Female mite behavior: The fertilized female burrows into the stratum corneum at a rate of approximately 2 mm per day, creating a characteristic S-shaped tunnel. She lays 2–3 eggs per day and lives for 4–6 weeks on a human host.
- Eggs and lifecycle: Eggs hatch in 3–4 days into six-legged larvae, which migrate to the skin surface and molt through two nymph stages into adults within 10–15 days. Total lifecycle from egg to adult: approximately 10–17 days.
- Mite burden in typical scabies: Surprisingly low — only 10–15 mites on average in an immunocompetent person. The itching is caused largely by the host's immune response to mite saliva, feces (scybala), and shed cuticle, not by mite numbers per se.
- Survival off-host: Mites are commonly said to survive 24–72 hours in room-temperature conditions without human contact. A 1984 laboratory study measured 24 to 36 hours off the host at room conditions (21°C, 40–80% humidity), and the dog variety of the mite lasted 19 days at 10°C and 97% humidity. Live human-variety mites recovered from bed linen could still burrow into a host after 96 hours held off a host, in alternating 12-hour periods of room conditions and refrigeration. Higher temperatures and lower humidity shorten survival. Mites die within 1 hour at 50°C (122°F).
- Sensitization lag: On first-ever exposure, the immune system takes 2–6 weeks to mount a response — the incubation period. During this symptom-free window, an infected person is fully contagious. On re-exposure (reinfestation in someone who has had scabies before), sensitization occurs within 1–3 days, and symptoms appear much more rapidly.
Classical vs. Norwegian (Crusted) Scabies
Classical Scabies
- Occurs in immunocompetent individuals; limited to 10–15 mites total.
- Intensely itchy; transmitted mainly by sustained skin-to-skin contact (typically >15–20 minutes).
- Responds well to standard topical treatment.
Norwegian (Crusted) Scabies
- Occurs in immunocompromised or debilitated individuals: human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS), organ transplant recipients on immunosuppressants, elderly with dementia, leprosy patients, individuals with Down syndrome, malnutrition.
- Mite burden is massively amplified: Thousands to millions of mites (as many as 2 million reported) due to failure of the normal immune response to limit infestation.
- Appearance: Thick, gray-white, fissured hyperkeratotic crusts — particularly on hands, feet, scalp, elbows, and buttocks. Itching may paradoxically be less intense than classic scabies despite the enormous mite load.
- Extremely contagious: Even brief contact with the patient or their environment (bedding, furniture, clothing) can transmit scabies because of the massive mite shedding. Can trigger institutional outbreaks.
- Treatment: Requires combination therapy — oral ivermectin PLUS topical permethrin or benzyl benzoate, repeated over multiple weeks; keratolytic agents to remove crusts.
- A 2026 trial of the combination: 132 adults with severe (profuse or crusted) scabies took oral ivermectin on days 0, 7 and 14 plus 5% permethrin cream on days 0 and 7. Doubling the ivermectin dose to 400 micrograms per kilogram did not cure more people (75% cured, against 82% at 200 micrograms per kilogram), and no safety issues were identified. The trial gave ivermectin with food, while the US tablet label says an empty stomach. Both groups had the combination, so this trial does not compare the combination with either drug alone.
Symptoms and Distribution Patterns
- Intense pruritus: The hallmark symptom. Characteristically worse at night (warmth of bed increases mite activity and histamine release) and so severe it disrupts sleep. Described by patients as a "crawling" or "biting" sensation inside the skin.
- Burrows (pathognomonic sign): Small, grayish-white, slightly raised, thread-like lines 2–10 mm long. Best seen on the finger webs, wrists, and the sides of fingers. A dark dot (the mite) may be visible at the leading end with magnification.
- Papules, vesicles, and nodules: Inflammatory papules appear at burrow sites and in sensitized areas. Vesicles (tiny fluid-filled blisters) occur on palms and soles. Scabietic nodules (firm, red-brown, 5–20 mm) appear on the penis, scrotum, areolae, and axillae — these represent a hypersensitivity reaction and may persist for months after successful treatment.
- Distribution in adults: Finger webs (most specific location), wrists, elbows, axillae, periareolar area (women), genitalia (men), waistline, buttocks, and ankles. The face, neck, and scalp are usually spared in immunocompetent adults.
- Distribution in infants and young children: Different from adults — palms and soles commonly affected (vesicles and pustules); face, scalp, and neck may be involved. Nodular lesions common in diaper area.
- Excoriations and secondary changes: Intense scratching leads to crusting, lichenification, and secondary bacterial infection (impetigo, cellulitis). Postinflammatory hyperpigmentation in darker skin tones.
Diagnosis: Dermoscopy and Skin Scraping
Clinical Diagnosis
- High clinical suspicion in anyone with intractable nocturnal pruritus, characteristic distribution, and a household contact with similar symptoms. "Itch that spreads through families" is a strong historical clue.
- The burrow is pathognomonic but may be obscured by excoriations, eczematization, and secondary infection.
Dermoscopy (Dermatoscopy)
- Preferred non-invasive diagnostic tool: A handheld dermoscope (10× or higher magnification) allows visualization of the mite and burrow through the skin without sampling.
- "Delta-wing jet with contrails" sign: The darkly pigmented body and front legs of the mite (the "delta-wing") at the leading end of a white curvilinear burrow (the "contrail") is the dermoscopic signature of scabies. In a Paris study of 238 patients, sensitivity (how many real cases it finds) was 91% and specificity (how many non-cases it correctly rules out) was 86%; sensitivity was similar for the expert and for inexperienced users, while specificity differed. In a study of 125 patients in a resource-poor setting, sensitivity was 83% and specificity 46%.
- Can be performed in seconds at the bedside — now recommended as the first-line confirmatory tool in clinical practice.
Microscopic Skin Scraping
- A mineral oil–moistened blade scrapes the roof of a burrow or papule; the material is transferred to a glass slide and examined under light microscopy (×10–40).
- Positive finding: mites, eggs, or fecal pellets (scybala) — brown oval pellets about 0.1 mm long.
- Sensitivity ~50% (many scrapes are negative even in confirmed cases); remains the gold standard for Norwegian scabies where mite density is very high.
Differential Diagnosis
- Atopic dermatitis: Similar itch distribution but lacks burrows; family history; responds to corticosteroids.
- Contact dermatitis: Localized to exposure site; dermatographism negative.
- Psoriasis: Well-demarcated plaques; silvery scale; Auspitz sign (pinpoint bleeding on scale removal).
- Lichen planus: Violaceous flat-topped papules; Wickham's striae.
- Delusions of parasitosis: Somatic symptom disorder with no mites, eggs, or burrows found on examination.
Treatment: Permethrin and Ivermectin
Permethrin 5% Cream (First-Line Topical)
- Applied from neck to toes (in children and Norwegian scabies: include face, scalp, and behind ears), left on for 8–12 hours (typically overnight), then washed off.
- Mechanism: pyrethroid insecticide that disrupts sodium channel function in mite nerve cells, causing paralysis and death.
- Repeat application in 7–14 days to kill mites that hatch from eggs laid before the first treatment (permethrin is not ovicidal).
- Cure rate: approximately 89–95% with two applications.
- Side effects: mild transient burning, stinging, or itch at application — not a sign of treatment failure. Washing hands after application is part of the usual instructions.
- Safe in pregnancy and children ≥2 months old.
Oral Ivermectin (Preferred When Topicals Are Impractical or for Norwegian Scabies)
- Dose: 200 micrograms per kilogram of body weight (mcg/kg), taken on an empty stomach. Two doses, 2 weeks apart — the second dose is essential to kill mites that were eggs during the first treatment.
- Example: for a 70 kg adult, 200 mcg/kg works out to 14 mg on Day 1, repeated on Day 14. The tablet strength on the US label is 3 mg, and the label's 200 mcg/kg table for strongyloidiasis lists five 3 mg tablets for 66–79 kg.
- Mechanism: potentiates glutamate-gated chloride channels in mite neurons, causing hyperpolarization, paralysis, and death. Does not cross the human blood-brain barrier at therapeutic doses.
- Cure rate: often described as comparable to permethrin in classical scabies, but a 2026 French trial in 289 households (children over 15 kg and adults, each dose on days 0 and 10) reported otherwise: the whole household was clinically cured by day 28 in 71.8% with oral ivermectin and 88.5% with 5% permethrin cream. The authors reported that ivermectin was not shown to be non-inferior and that permethrin was statistically superior. Skin side effects occurred in 11.9% on ivermectin and 15.6% on permethrin. Combination therapy (ivermectin + permethrin) is described as superior for Norwegian scabies and is the recommended treatment, although randomized data on it were lacking until recently (see Norwegian scabies above).
- US label status: the ivermectin tablet label lists strongyloidiasis and onchocerciasis, not scabies, so scabies use in the US is off-label. The label states that safety and effectiveness in children under 15 kg have not been established and that safety in pregnancy has not been established; permethrin 5% is the treatment described as preferred in these groups.
- Widely used in mass drug administration (MDA) campaigns for community scabies control; highly cost-effective.
Alternative Topical Agents
- Benzyl benzoate 25% lotion: Effective and cheap; widely used in developing countries; applied for 24 hours on two consecutive days; more irritating than permethrin.
- Sulfur 6–33% in petrolatum: Oldest treatment; safe in neonates and pregnancy; applied for 3 nights consecutively; messy and malodorous.
- Crotamiton 10% cream: Antipruritic and scabicidal; lower cure rate (~60%); used mainly for symptom relief post-treatment.
- Lindane 1% (gamma-benzene hexachloride): Effective but neurotoxic — banned or restricted in many countries.
- Spinosad topical suspension: The US drug label lists it for scabies in adults and in children 4 years and older. Per the label it is rubbed in to cover the body from the neck down to the soles of the feet and left on for at least 6 hours before showering or bathing.
Treating Household Members and Environment
- Simultaneous treatment of all household members and close contacts is the standard approach, regardless of whether they have symptoms — asymptomatic contacts in the 2–6 week incubation window are still infectious and will reinfect treated individuals if not treated at the same time.
- Clothing and bedding: The usual steps are machine-washing in hot water (≥60°C/140°F) and machine-drying on high heat on the day of treatment. This kills mites that have been shed onto fabrics.
- Items that cannot be washed: These are usually sealed in a plastic bag for at least 72 hours (off-host survival time is typically <72 hours at room temperature). Leather items, stuffed animals and pillows are commonly bagged and sealed for 1 week.
- Vacuuming: Vacuuming upholstered furniture, car seats, and carpets removes shed mites and skin scales; the vacuum bag is usually thrown away straight afterwards.
- No fumigation required for ordinary scabies; extensive environmental decontamination IS required for Norwegian scabies cases because of massive mite shedding from crusts.
- Institutional outbreaks: The response involves notifying facility management, simultaneous mass treatment of residents, staff, and family members, and environmental decontamination of common areas.
Natural and Supportive Approaches
- Tea tree oil (Melaleuca alternifolia): Laboratory studies show terpinen-4-ol (the active constituent) has in vitro acaricidal and ovicidal activity against Sarcoptes scabiei. A 2004 laboratory study (Walton et al., PubMed PMID: 15148100) tested mites collected from one 20-year-old woman with crusted scabies: 5% tea tree oil and 2.1% terpinen-4-ol reduced mite survival times, and the authors state that in vivo effectiveness was also observed. A 5% tea tree oil body wash is also reported to reduce mite burden in a pig model of scabies. A 2016 review (Thomas et al., PubMed PMID: 26787146) describes tea tree oil as successfully used as an add-on treatment for crusted (Norwegian) scabies, including cases that did not respond to standard treatments, and calls for larger randomized trials. Not a replacement for permethrin or ivermectin; used as adjunct.
- Neem oil (Azadirachta indica): Traditional Ayurvedic remedy; contains azadirachtin, a limonoid with insecticidal properties. Small studies suggest potential; insufficient randomized controlled trial evidence for standalone scabicidal efficacy. Used in combination with turmeric paste in some traditional settings.
- Colloidal oatmeal baths: Anti-inflammatory and anti-pruritic; provides relief from intense itching as adjunct during and after treatment. Does not kill mites.
- Antihistamines for itch relief: Oral cetirizine or loratadine reduce histamine-mediated itch during treatment. First-generation antihistamines (hydroxyzine, diphenhydramine) at night help with sleep disruption.
- Topical corticosteroids (post-treatment): Mild-potency corticosteroids (hydrocortisone 1%) help reduce post-scabetic eczematous dermatitis and nodule inflammation after mites are eradicated. They are described for use once mite eradication has been confirmed.
- Zinc oxide paste: Soothes excoriated skin, provides barrier protection, and has mild antiseptic properties. Useful for secondary skin breakdown from scratching.
Complications
- Secondary bacterial infection (impetigo): Staphylococcus aureus and Streptococcus pyogenes enter through excoriated skin, causing impetiginized scabies — yellow crusted lesions with purulent discharge. Requires topical mupirocin or systemic antibiotics alongside scabicidal treatment.
- Post-streptococcal glomerulonephritis: Group A Streptococcus secondary infection of scabies lesions can trigger post-infectious glomerulonephritis — a serious kidney complication with hematuria, proteinuria, and hypertension. Most prevalent in children in tropical settings with high scabies burden.
- Post-scabetic itch (post-treatment pruritus): Itch can persist for 2–4 weeks after successful mite eradication because dead mite antigens continue to stimulate the immune response. This is NOT treatment failure. Patients need reassurance and symptomatic management.
- Scabetic nodules: Firm, itchy, reddish-brown nodules on the genitalia, axillae, and areolae represent a persistent hypersensitivity reaction. May last 2–12 months post-treatment. Treated with intralesional corticosteroids (triamcinolone acetonide) if distressing.
- Treatment failure: A French cohort paper states that failure occurs in about one-third of cases. In its 210 patients, failure was mainly associated with a single dose of ivermectin rather than two, topical benzyl benzoate alone, and no decontamination of furniture with acaricides. Common reasons include under-treatment (single application of permethrin instead of two), failure to treat all contacts simultaneously, inadequate environmental decontamination, resistant mites (emerging permethrin resistance documented in some populations), and misdiagnosis.
- Psychological impact: Chronic itch, social stigma, and repeated reinfestation cause significant anxiety, embarrassment, and social isolation. Educating patients that scabies is not caused by poor hygiene is an essential part of management.
Prevention and Contagion Control
- Prolonged skin-to-skin contact with an infected person can pass on the mites until that person has completed treatment. Brief handshaking carries very low transmission risk; prolonged holding of hands is a recognized route of transmission.
- Sexual partners: Partners are treated at the same time; scabies is classified as a sexually transmitted infection in adults. Screening for other sexually transmitted infections is commonly offered when scabies is treated in sexually active adults.
- Early diagnosis: The longer scabies goes undiagnosed, the more people are exposed. Scabies belongs on the list of possible causes of an itchy rash — especially when symptoms are bilateral and nocturnal.
- Institutional protocols: Nursing homes, prisons, refugee camps, and day-care centers commonly keep written scabies response protocols including case identification, simultaneous mass treatment, and environmental decontamination procedures.
- Mass drug administration (MDA): World Health Organization-endorsed ivermectin MDA in high-burden communities has reduced scabies prevalence and secondary bacterial infection rates in tropical island populations (studies from Fiji, the Solomon Islands, and northern Australia). In a Fiji trial of three island communities (2,051 people), scabies at 12 months fell from 32.1% to 1.9% with mass ivermectin, from 41.7% to 15.8% with mass permethrin, and from 36.6% to 18.8% with standard care. Impetigo fell from 24.6% to 8.0% with ivermectin. Mild side effects were more frequent with ivermectin than with permethrin (15.6% against 6.8%).
- Post-exposure prophylaxis: Close household contacts exposed to Norwegian scabies usually receive preventive treatment regardless of symptoms given the massive mite burden in crusted disease.
Key Research Papers
- Chosidow O. Clinical practices. Scabies. N Engl J Med. 2006;354(16):1718-1727. — PubMed PMID: 16625010
- Romani L, Steer AC, Whitfeld MJ, Kaldor JM. Prevalence of scabies and impetigo worldwide: a systematic review. Lancet Infect Dis. 2015;15(8):960-967. — PubMed PMID: 26088526
- Strong M, Johnstone P. Interventions for treating scabies. Cochrane Database Syst Rev. 2007;(3):CD000320. — PubMed PMID: 17636630
- Romani L, Whitfeld MJ, Koroivueta J, et al. Mass drug administration for scabies control in a population with endemic disease. N Engl J Med. 2015;373(24):2305-2313. — PubMed PMID: 26650152
- Walton SF, McKinnon M, Pizzutto S, et al. Acaricidal activity of Melaleuca alternifolia (tea tree) oil: in vitro sensitivity of Sarcoptes scabiei var hominis to terpinen-4-ol. Arch Dermatol. 2004;140(5):563-566. — PubMed PMID: 15148100
- Argenziano G, Fabbrocini G, Delfino M. Epiluminescence microscopy. A new approach to in vivo detection of Sarcoptes scabiei. Arch Dermatol. 1997;133(6):751-753. — PubMed PMID: 9197830
- Aussy A, Houivet E, Hébert V, et al. Risk factors for treatment failure in scabies: a cohort study. Br J Dermatol. 2019;180(4):888-893. — PubMed PMID: 30376179
- Johnston G, Sladden M. Scabies: diagnosis and treatment. BMJ. 2005;331(7517):619-622. — PubMed PMID: 16166133
- Hicks MI, Elston DM. Scabies. Dermatol Ther. 2009;22(4):279-292. — PubMed PMID: 19580575
- Engelman D, Yoshizumi J, Hay RJ, et al. The 2020 International Alliance for the Control of Scabies Consensus Criteria for the Diagnosis of Scabies. Br J Dermatol. 2020;183(5):808-820. — PubMed PMID: 32034956
- Sunderkötter C, Aebischer A, Neufeld M, et al. Increase of scabies in Germany and development of resistant mites? Evidence and consequences. J Dtsch Dermatol Ges. 2019;17(1):15-23. — PubMed PMID: 30480868
- Boralevi F, Simon G, Bernigaud C, et al. Oral ivermectin versus 5% permethrin cream to treat children and adults with classic scabies: multicentre, assessor blinded, cluster randomised clinical trial. BMJ. 2026;392:e086277. — PubMed PMID: 41494769
- Bernigaud C, Do-Pham G, Guichard E, et al. Combined oral ivermectin and 5% permethrin cream to treat severe scabies. N Engl J Med. 2026;394(18):1814-1823. — PubMed PMID: 42090793
- Dupuy A, Dehen L, Bourrat E, et al. Accuracy of standard dermoscopy for diagnosing scabies. J Am Acad Dermatol. 2007;56(1):53-62. — PubMed PMID: 17190621
- Walter B, Heukelbach J, Fengler G, et al. Comparison of dermoscopy, skin scraping, and the adhesive tape test for the diagnosis of scabies in a resource-poor setting. Arch Dermatol. 2011;147(4):468-473. — PubMed PMID: 21482897
- Arlian LG, Runyan RA, Achar S, Estes SA. Survival and infectivity of Sarcoptes scabiei var. canis and var. hominis. J Am Acad Dermatol. 1984;11(2 Pt 1):210-215. — PubMed PMID: 6434601
- Thomas J, Carson CF, Peterson GM, et al. Therapeutic potential of tea tree oil for scabies. Am J Trop Med Hyg. 2016;94(2):258-266. — PubMed PMID: 26787146
PubMed Searches
Curated PubMed topic searches of peer-reviewed literature on scabies.
- PubMed: Scabies treatment permethrin vs ivermectin
- PubMed: Sarcoptes scabiei pathogenesis
- PubMed: Norwegian crusted scabies
- PubMed: Scabies mass drug administration
- PubMed: Scabies dermoscopy diagnosis
- PubMed: Scabies secondary bacterial infection
- PubMed: Scabies global epidemiology
- PubMed: Scabies tea tree oil
- PubMed: Permethrin resistance scabies
- PubMed: Scabies institutional outbreak
Connections
- Dermatology
- Eczema
- Psoriasis
- Contact Dermatitis
- Fungal Infections
- Herpes Simplex
- Urticaria (Hives)
- Warts
- Rosacea
- Zinc
- Tea Tree Oil
- Neem
- Gut Healing
- Chronic Kidney Disease
- Acne
- Human Immunodeficiency Virus/Acquired Immunodeficiency Syndrome
- Vitamin D3
- Tea Tree Oil for Head Lice & Scabies
- Topical Ivermectin