Quercetin for Senolytic Activity (Dasatinib + Quercetin)
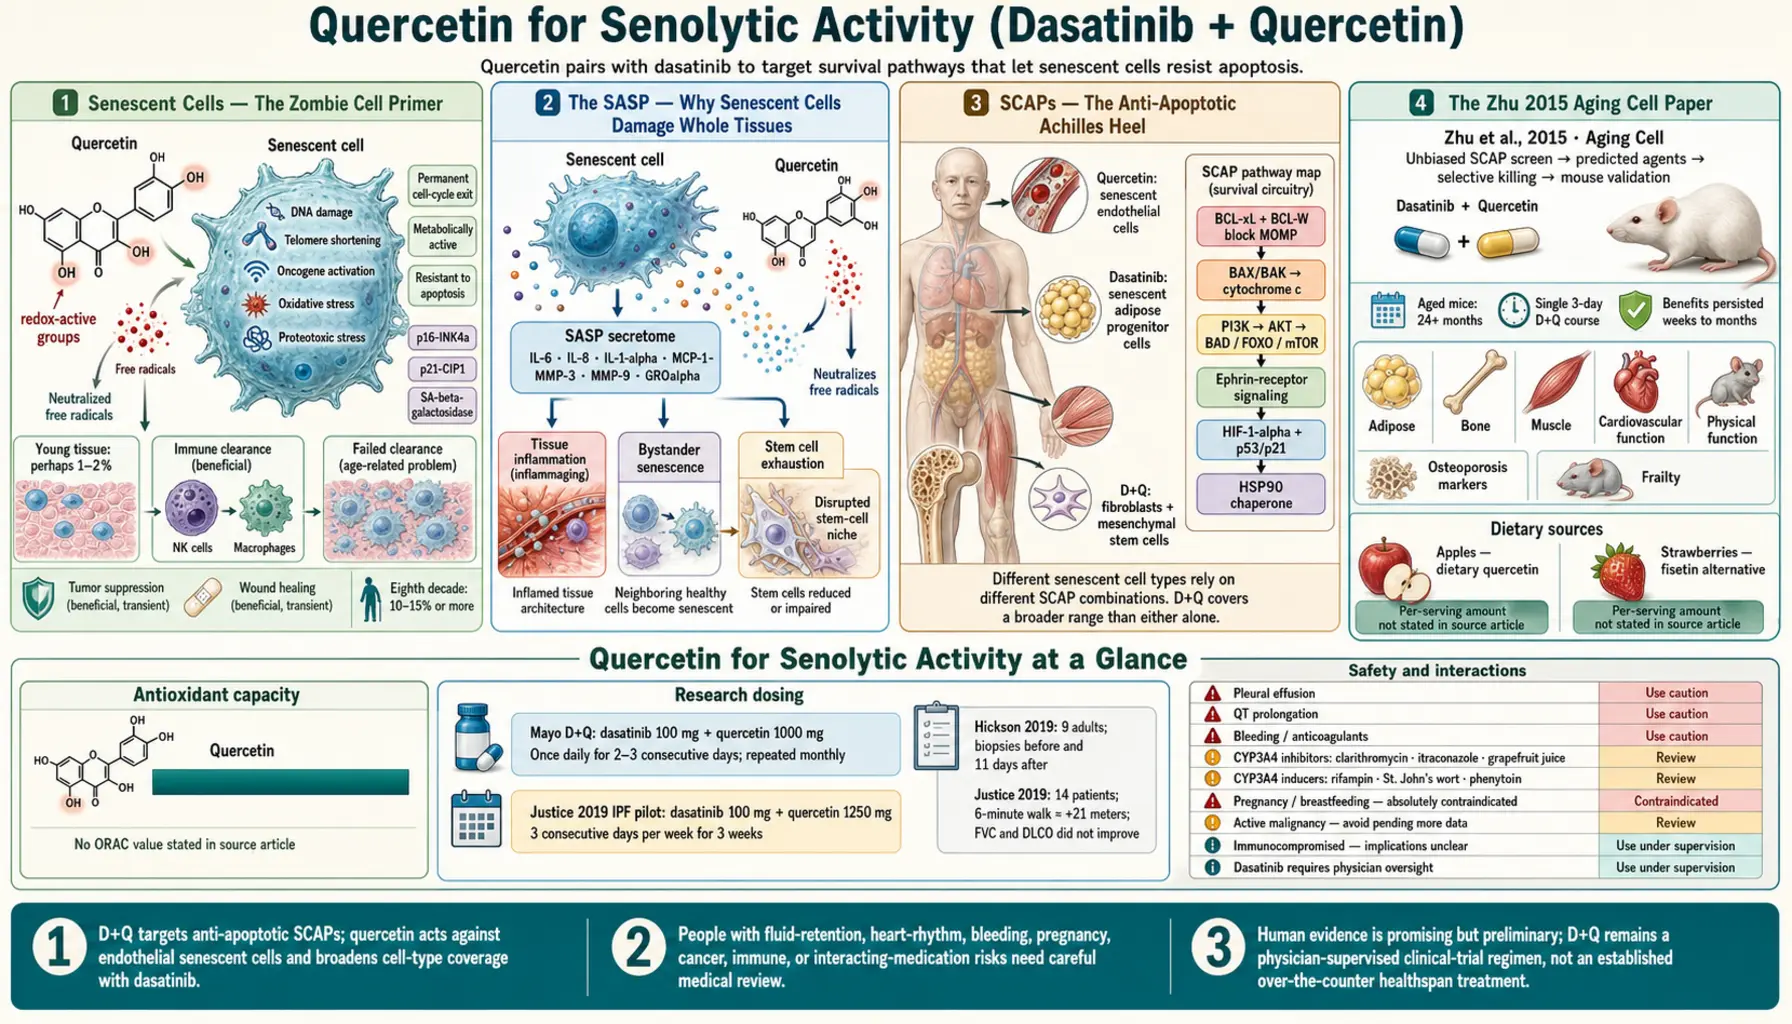
In 2015, a team led by Yi Zhu, Tamar Tchkonia and James Kirkland at the Mayo Clinic, working with Paul Robbins and Laura Niedernhofer at the Scripps Research Institute, published the paper in Aging Cell that introduced a new class of drugs, senolytics, which selectively kill senescent cells. They found that senescent cells switch on pro-survival networks (including ephrins, PI3Kδ, p21, BCL-xL and plasminogen activator inhibitor-2) that help them resist apoptosis, that dasatinib (a prescription cancer drug, a kinase inhibitor approved for certain leukemias) and the dietary flavonoid quercetin each killed some types of senescent cells, and that the combination reduced senescent-cell burden in mice. Dasatinib plus quercetin (D+Q) has since been tested in small human studies: open-label pilots in idiopathic pulmonary fibrosis (Justice 2019, 14 patients) and diabetic kidney disease (Hickson 2019, 9 patients), a pilot in mild Alzheimer's disease (Gonzales 2023, 5 patients), and randomized trials in pulmonary fibrosis, postmenopausal bone health and fibrotic fatty-liver disease. This page reports what those papers found, what the dasatinib label says about the drug's risks, and where the evidence stops.
Table of Contents
- Senescent Cells — The Zombie Cell Primer
- The SASP — Why Senescent Cells Damage Whole Tissues
- SCAPs — The Anti-Apoptotic Achilles Heel
- The Zhu 2015 Aging Cell Paper
- The Dasatinib + Quercetin (D+Q) Combination
- Hickson 2019 — Senescent Cells Measured in Diabetic Kidney Disease
- Justice 2019 — First-in-Human Pilot in Idiopathic Pulmonary Fibrosis
- Randomized and Later Trials, 2023–2026
- D+Q and Fisetin — What Has Been Compared
- Intermittent Dosing in the Trials
- What the Human Evidence Shows
- Dasatinib Label Warnings, Interactions, and Trial Side Effects
- Key Research Papers
- Connections
- Featured Videos
Senescent Cells — The Zombie Cell Primer
Cellular senescence is a cellular response to stress — DNA damage, telomere shortening, oncogene activation, oxidative stress, or proteotoxic stress — in which a cell stops dividing essentially permanently while remaining metabolically active and resistant to apoptosis. Senescent cells are commonly identified by markers such as the cell-cycle inhibitors p16-INK4a and p21-CIP1, senescence-associated beta-galactosidase activity, and a distinctive secretory profile (the senescence-associated secretory phenotype, or SASP, discussed in the next section).
Senescence is not simply harmful. It suppresses cancer by halting the division of damaged cells, and reviews describe further roles in development and tissue repair (van Deursen 2014). Childs and colleagues (2015) point out that these beneficial functions mean that indiscriminately targeting senescent cells, or their secretions, may have negative consequences.
Senescent cells accumulate in various tissues with ageing and at sites of disease in many chronic conditions (Kirkland and Tchkonia 2017). In mice, transplanting relatively small numbers of senescent cells into young animals was enough to cause persistent physical dysfunction and to spread senescence to the host's own tissues (Xu 2018).
Whether senescent cells actually drive age-related decline became testable in 2011, when Darren Baker, Jan van Deursen and colleagues at the Mayo Clinic published a Nature paper using a transgenic mouse (INK-ATTAC) in which p16-INK4a-positive senescent cells could be eliminated on demand with a drug. In progeroid BubR1 mice, life-long removal of these cells delayed age-related pathology in adipose tissue, skeletal muscle and the eye, and late-life clearance slowed the progression of disorders already under way. The authors concluded that cellular senescence is causally implicated in age-related phenotypes in this model. This was a genetic tool in mice, not a drug.
The SASP — Why Senescent Cells Damage Whole Tissues
Senescent cells stop dividing but stay metabolically active, and they secrete a mixture of inflammatory and tissue-remodelling factors — the senescence-associated secretory phenotype (SASP). Coppé and colleagues (2008) measured the factors secreted by human cells made senescent by DNA damage and found myriad factors associated with inflammation and malignancy; in cultured pre-malignant epithelial cells, the SASP's effects depended largely on interleukin-6 (IL-6) and IL-8.
Reviews attribute several downstream effects to the SASP:
- Inflammation — Kirkland and Tchkonia (2017) list senescence-related inflammation, metabolic dysregulation, ageing phenotypes, chronic diseases, geriatric syndromes and loss of resilience among the conditions the SASP can contribute to. Tchkonia and colleagues (2013) describe senescence as a source of chronic inflammation through the SASP.
- Spread to neighbouring cells — in the Xu 2018 mouse transplant experiments, introduced senescent cells spread senescence to the host's tissues.
- Stem cell dysfunction — listed by Kirkland and Tchkonia (2017) among the SASP's possible contributions.
The SASP also explains the dosing idea behind senolytics. Kirkland and Tchkonia (2020) write that because senescent cells take weeks to reaccumulate, senolytics can be given intermittently — a “hit-and-run” approach — rather than continuously.
SCAPs — The Anti-Apoptotic Achilles Heel
Senescent cells carry damage that would ordinarily trigger apoptosis. Kirkland and Tchkonia (2020) describe the most harmful senescent cells as resistant to apoptosis because they up-regulate anti-apoptotic pathways — the “senescent-cell anti-apoptotic pathways,” or SCAPs — which defend them against their own inflammatory SASP. Senolytics transiently disable these pathways.
Zhu and colleagues (2015) found increased expression of pro-survival networks in senescent cells by transcript analysis. Silencing key nodes of this network with siRNA killed senescent cells but not proliferating or quiescent, differentiated cells. The nodes they named were:
- Ephrins (EFNB1 or EFNB3)
- PI3Kδ (the delta isoform of phosphoinositide 3-kinase)
- p21
- BCL-xL, a BCL-2-family protein that blocks the mitochondrial route to apoptosis
- Plasminogen activator inhibitor-2
Drugs targeting the same factors selectively killed senescent cells, and different senescent cell types responded to different drugs. In the Zhu paper, dasatinib eliminated senescent human fat-cell progenitors, quercetin was more effective against senescent human endothelial cells and mouse bone-marrow mesenchymal stem cells, and the combination was effective in eliminating senescent mouse embryonic fibroblasts. This difference between cell types underlies the use of the two drugs together.
The Zhu 2015 Aging Cell Paper
The Zhu, Tchkonia, Pirtskhalava, et al. 2015 paper in Aging Cell introduced the term senolytics. Its approach, as the abstract describes it:
- Compare transcripts of senescent and non-senescent cells to find up-regulated pro-survival networks.
- Silence key nodes of those networks with siRNA and check which knockdowns selectively killed senescent cells.
- Test drugs that act on the same factors for selective killing of senescent versus non-senescent cells.
- Test the most promising combination, dasatinib plus quercetin, in chronologically aged, radiation-exposed, and progeroid Ercc1-deficient mice.
In the mice, D+Q reduced senescent-cell burden. The abstract reports:
- In old mice, cardiac function and carotid vascular reactivity were improved 5 days after a single dose.
- After irradiation of one limb, a single dose led to improved exercise capacity for at least 7 months.
- In progeroid Ercc1-deficient mice, periodic dosing extended healthspan, delaying age-related symptoms and pathology, osteoporosis, and loss of intervertebral disc proteoglycans.
A follow-up mouse study (Xu 2018, Nature Medicine) found that intermittent oral D+Q given to naturally aged mice and to young mice transplanted with senescent cells alleviated physical dysfunction, and in aged mice it increased post-treatment survival by 36% while reducing the mortality hazard to 65%. In explants of human adipose tissue, D+Q decreased the number of naturally occurring senescent cells and their secretion of frailty-related inflammatory cytokines. These are animal and tissue-explant results, not results in living people.
The Dasatinib + Quercetin (D+Q) Combination
Dasatinib is a prescription kinase inhibitor. Its FDA label lists it for Philadelphia chromosome-positive chronic myeloid leukemia and acute lymphoblastic leukemia, at a starting dose of 100 mg once daily for chronic-phase CML in adults and 140 mg once daily for advanced phases, taken continuously. Quercetin is a flavonoid found in foods such as onions and apples and sold as a supplement.
The human senolytic studies on this page gave dasatinib 100 mg together with quercetin 1000 mg or 1250 mg on two or three consecutive days, repeated on a schedule that differed by trial (see Intermittent Dosing in the Trials). Zhu and colleagues chose the pair because the two drugs acted on different senescent cell types, as described above; quercetin's role in the combination comes from its activity against senescent endothelial cells and mouse bone-marrow stem cells in that work.
The short courses in these studies are a far smaller exposure than continuous cancer treatment, but the dasatinib label's warnings come from the drug itself, and the trials recorded side effects of their own; both are listed in the label warnings section. The combination has been studied in clinical trials, not approved for any senolytic or anti-ageing use.
Fisetin, a flavonoid related to quercetin, has been studied as a single-agent senolytic in mice; see the D+Q and fisetin section below and the Fisetin Senolytic Activity page.
Hickson 2019 — Senescent Cells Measured in Diabetic Kidney Disease
Hickson and colleagues (2019, EBioMedicine) ran an open-label phase 1 pilot study with no control group. Nine people with diabetic kidney disease (mean age 68.7 years; 2 women) took oral dasatinib 100 mg and quercetin 1000 mg for 3 days. Adipose tissue, skin biopsies and blood were collected before treatment and 11 days after it ended.
The study's own abstract calls the Justice 2019 IPF study the first clinical trial of senolytics; Hickson's report was the first peer-reviewed study to show directly that a senolytic decreased senescent cells in humans.
Results reported in the abstract:
- Adipose-tissue senescent-cell burden fell within 11 days, with fewer p16-INK4a- and p21-CIP1-expressing cells, fewer cells with senescence-associated beta-galactosidase activity, and fewer adipocyte progenitors with limited replicative potential.
- Adipose tissue macrophages and crown-like structures decreased.
- Skin epidermal p16-INK4a-positive and p21-CIP1-positive cells were reduced.
- Circulating SASP factors decreased, including IL-1α, IL-6, and matrix metalloproteinases 9 and 12.
The abstract does not report clinical outcomes such as kidney function, and with nine participants and no comparison group it cannot separate the drug's effect from other changes over the same 11 days.
Justice 2019 — First-in-Human Pilot in Idiopathic Pulmonary Fibrosis
Idiopathic pulmonary fibrosis (IPF) is a progressive, fatal lung disease that the trial authors describe as associated with cellular senescence. In bleomycin-treated mice, a model of lung fibrosis, D+Q had alleviated IPF-related dysfunction.
Justice, Nambiar, Tchkonia, Kirkland and colleagues (2019, EBioMedicine) ran a two-centre, open-label study with no control group. Fourteen people with stable IPF took dasatinib 100 mg/day and quercetin 1250 mg/day, three days a week for three weeks. The primary endpoints were feasibility — retention and completion of planned clinical assessments; safety and changes in function and reported health were secondary.
Results reported in the abstract:
- Retention was 100% with no discontinuation of D+Q; planned assessments were complete in 13 of 14 participants.
- One serious adverse event was reported. Non-serious events were mainly mild to moderate: respiratory symptoms (16 events), skin irritation or bruising (14) and gastrointestinal discomfort (12).
- 6-minute walk distance, 4-metre gait speed and chair-stand time improved significantly (p < .05).
- Pulmonary function, clinical chemistries, a frailty index and reported health were unchanged.
- Effects on circulating SASP factors were inconclusive, although changes in function correlated with changes in some SASP-related markers.
The authors called the study initial evidence that warranted larger randomized controlled trials. Without a placebo group, the function changes could reflect factors other than the drugs; the randomized follow-up is described in the next section.
Randomized and Later Trials, 2023–2026
- IPF, randomized pilot (Nambiar 2023, EBioMedicine) — a phase 1, single-blind, single-centre, placebo-controlled pilot. Twelve people with IPF aged over 50 were randomized 1:1 to three weeks of D+Q (dasatinib 100 mg/day and quercetin 1250 mg/day, three consecutive days a week) or placebo. All doses and assessments were completed. There were no serious adverse events related to D+Q; the D+Q arm reported 65 non-serious adverse events against 22 with placebo, and sleep disturbance and anxiety occurred in 4 of 6 on D+Q versus 0 of 6 on placebo. Frailty, pulmonary and physical function did not appear to differ meaningfully between groups, though the trial was not powered to test this.
- Mild Alzheimer's disease (Gonzales 2023, Nature Medicine; SToMP-AD) — an open-label phase 1 study in which 5 participants (mean age 76) completed 12 weeks. Dasatinib and quercetin were detected in blood in all participants (dasatinib 12.7–73.5 ng/mL, quercetin 3.29–26.3 ng/mL). Dasatinib was detected in cerebrospinal fluid in four of the five; quercetin was not detected in cerebrospinal fluid. Treatment was well tolerated, cognitive and neuroimaging measures did not change significantly, and cerebrospinal-fluid IL-6 and glial fibrillary acidic protein increased.
- Bone in postmenopausal women (Farr 2024, Nature Medicine) — a phase 2 randomized controlled trial in 60 women. The primary endpoint, change in the bone-resorption marker CTx at 20 weeks, did not differ between groups (P = 0.611). The bone-formation marker P1NP rose by 16% relative to control at 2 and 4 weeks but did not differ at 20 weeks. No serious adverse events were observed. Exploratory analyses suggested larger responses in women with the highest senescent-cell burden; the authors concluded that D+Q did not reduce bone resorption in the overall group.
- Older adults at risk of Alzheimer's disease (Millar 2025, EBioMedicine) — a single-arm pilot in which 12 participants took dasatinib 100 mg and quercetin 1250 mg for two days every two weeks over 12 weeks. No serious adverse events related to the intervention occurred. Montreal Cognitive Assessment (MoCA) scores rose by 1.0 point on average, which was not statistically significant. The authors note the lack of a control group and call the data preliminary.
- Fibrotic fatty-liver disease (Koning 2026, Nature Metabolism) — a phase 2, double-blind, randomized, placebo-controlled trial in 31 people with fibrotic metabolic dysfunction-associated steatohepatitis (MASH), using dasatinib 100 mg/day and quercetin 1,000 mg/day three consecutive days a week over 3 weeks, repeated across three 7-week cycles. On paired liver biopsies, the primary endpoint (at least one stage of fibrosis improvement without MASH worsening) was reached in 47% on D+Q versus 7% on placebo (P = 0.02), and MASH resolution occurred in 53% versus 7%. Adverse events were more frequent with D+Q (82% versus 43%) and were all self-limiting. The authors describe it as a proof-of-principle trial that supports further trials.
The human D+Q studies cited on this page, by design and size. Figures are from each paper's abstract.
D+Q and Fisetin — What Has Been Compared
Fisetin is a flavonoid related to quercetin. Yousefzadeh and colleagues (2018, EBioMedicine), working with the Mayo Clinic group, screened 10 flavonoids against senescent mouse and human fibroblasts and found fisetin the most potent senolytic of those tested. In progeroid and old mice, acute or intermittent fisetin reduced senescence markers in multiple tissues, and given to wild-type mice late in life it extended median and maximum lifespan. In human adipose tissue explants it reduced senescence in a subset of cells. That paper's background describes D+Q as the group's earlier senolytic and states that the goal was to find flavonoids with more potent senolytic activity.
A later lifespan study in genetically heterogeneous mice (Harrison 2024, GeroScience) found that fisetin did not significantly increase lifespan in either sex at the dose and schedule it used. Mouse results for fisetin therefore differ between studies.
No head-to-head human comparison of fisetin and D+Q appears among the papers on this page. The human trials described here all used D+Q, and none of the cited papers reports human senolytic outcomes for fisetin. The differences that can be stated are factual ones: dasatinib is a prescription cancer drug with the label warnings listed below, while fisetin is a dietary flavonoid. Fisetin is covered in detail on the Fisetin Senolytic Activity page.
Intermittent Dosing in the Trials
Kirkland and Tchkonia (2020) explain the intermittent schedules: senescent cells take weeks to reaccumulate, so senolytics can be given in short pulses — a “hit-and-run” approach. Hickson and colleagues (2019) note that dasatinib and quercetin have elimination half-lives under 11 hours, yet their 3-day course was followed by lower senescent-cell counts 11 days later. On quercetin's reach, the Gonzales 2023 study detected quercetin in blood but not in cerebrospinal fluid.
Regimens the trials report:
- Hickson 2019 — dasatinib 100 mg and quercetin 1000 mg for 3 days, once.
- Justice 2019 and Nambiar 2023 — dasatinib 100 mg/day and quercetin 1250 mg/day, three consecutive days a week for three weeks.
- Millar 2025 — dasatinib 100 mg and quercetin 1250 mg for two days every two weeks over 12 weeks.
- Koning 2026 — dasatinib 100 mg/day and quercetin 1,000 mg/day three consecutive days a week over 3 weeks, repeated across three 7-week cycles.
- Farr 2024 and Gonzales 2023 — intermittent D+Q; the abstracts do not give the schedule.
These are research regimens chosen by trial teams. None of the studies was designed to find the best dose, frequency or duration for any clinical outcome.
What the Human Evidence Shows
The senolytic field has consistent mouse data, a clear cellular rationale, and a small number of human studies, most of them uncontrolled pilots with 5 to 14 participants.
What the published human studies report:
- A 3-day D+Q course was followed by fewer senescent cells in adipose tissue and skin in 9 people with diabetic kidney disease (Hickson 2019, no control group).
- Physical-function measures improved in the open-label IPF pilot (Justice 2019), but in the placebo-controlled IPF pilot function did not appear to differ between groups (Nambiar 2023, not powered for efficacy).
- The phase 2 bone trial in 60 postmenopausal women did not meet its primary endpoint (Farr 2024).
- The phase 2 trial in 31 people with fibrotic MASH met its primary liver-biopsy endpoint, with more adverse events on D+Q than placebo (Koning 2026).
- Circulating SASP factors fell in Hickson 2019; in Justice 2019 the effects on SASP factors were inconclusive.
What these studies do not show:
- Any effect on human lifespan
- Reduction in cardiovascular disease, dementia, sarcopenia, or other age-related disease endpoints with long-term use
- An established dose, frequency, or duration for any clinical outcome
- The long-term safety of repeated D+Q courses
In their 2020 review, Kirkland and Tchkonia — who led the original D+Q work — wrote that “until such studies are done, it is too early for senolytics to be used outside of clinical trials.” Decisions about prescription medicines belong with a clinician.
Dasatinib Label Warnings, Interactions, and Trial Side Effects
The warnings below come from the FDA prescribing information for dasatinib tablets (DailyMed: dasatinib labels), which is based on continuous daily treatment of leukemia, not short senolytic courses.
- Myelosuppression and bleeding — severe thrombocytopenia, neutropenia and anemia may occur, and dasatinib can cause serious and fatal bleeding. The label calls for caution when it is used with medicines that inhibit platelet function or with anticoagulants.
- Fluid retention — sometimes severe, including pleural effusion.
- Heart and lung — cardiovascular toxicity; pulmonary arterial hypertension, which may be reversible when the drug is stopped; and QT prolongation, with higher risk in people with low potassium or magnesium, congenital long-QT syndrome, or those taking antiarrhythmic or other QT-prolonging medicines.
- Other warnings — severe mucocutaneous skin reactions including Stevens-Johnson syndrome, tumor lysis syndrome, and hepatotoxicity.
- Pregnancy and breastfeeding — dasatinib can cause fetal harm, and the label advises women not to breastfeed.
- Most common adverse reactions (15% or more of patients on dasatinib alone in cancer trials) — myelosuppression, fluid retention, diarrhea, headache, skin rash, hemorrhage, shortness of breath, fatigue, nausea, and musculoskeletal pain.
- Drug interactions — strong CYP3A4 inhibitors and grapefruit juice can raise dasatinib levels and the risk of toxicity; strong CYP3A4 inducers and St. John's wort can lower them. The label advises against taking H2 blockers or proton pump inhibitors with dasatinib, and against taking antacids at the same time (they are to be separated by at least 2 hours).
- Side effects recorded in the D+Q trials — respiratory symptoms, skin irritation or bruising, and gastrointestinal discomfort, plus one serious adverse event, in Justice 2019; more non-serious adverse events than placebo, and sleep disturbance and anxiety in 4 of 6, in Nambiar 2023; adverse events in 82% on D+Q versus 43% on placebo, all self-limiting, in Koning 2026. These trials were small and short, so rare or delayed effects would not be detected.
- Quercetin-specific cautions — covered on the Allergy & Histamine page and the Cardiovascular Health page; these apply to quercetin with or without dasatinib.
Key Research Papers
- Zhu Y, Tchkonia T, Pirtskhalava T, et al. (2015). The Achilles' heel of senescent cells: from transcriptome to senolytic drugs. Aging Cell 14(4):644-58. — PubMed PMID: 25754370
- Hickson LJ, Langhi Prata LGP, Bobart SA, et al. (2019). Senolytics decrease senescent cells in humans: preliminary report from a clinical trial of Dasatinib plus Quercetin in individuals with diabetic kidney disease. EBioMedicine 47:446-456. — PubMed PMID: 31542391
- Justice JN, Nambiar AM, Tchkonia T, et al. (2019). Senolytics in idiopathic pulmonary fibrosis: results from a first-in-human, open-label, pilot study. EBioMedicine 40:554-563. — PubMed PMID: 30616998
- Baker DJ, Wijshake T, Tchkonia T, et al. (2011). Clearance of p16Ink4a-positive senescent cells delays ageing-associated disorders. Nature 479(7372):232-6. — PubMed PMID: 22048312
- Yousefzadeh MJ, Zhu Y, McGowan SJ, et al. (2018). Fisetin is a senotherapeutic that extends health and lifespan. EBioMedicine 36:18-28. — PubMed PMID: 30279143
- Xu M, Pirtskhalava T, Farr JN, et al. (2018). Senolytics improve physical function and increase lifespan in old age. Nature Medicine 24(8):1246-1256. — PubMed PMID: 29988130
- Kirkland JL, Tchkonia T (2020). Senolytic drugs: from discovery to translation. Journal of Internal Medicine 288(5):518-536. — PubMed PMID: 32686219
- Kirkland JL, Tchkonia T (2017). Cellular senescence: a translational perspective. EBioMedicine 21:21-28. — PubMed PMID: 28416161
- Childs BG, Durik M, Baker DJ, van Deursen JM (2015). Cellular senescence in aging and age-related disease: from mechanisms to therapy. Nature Medicine 21(12):1424-35. — PubMed PMID: 26646499
- Coppé JP, Patil CK, Rodier F, et al. (2008). Senescence-associated secretory phenotypes reveal cell-nonautonomous functions of oncogenic RAS and the p53 tumor suppressor. PLoS Biology 6(12):2853-68. — PubMed PMID: 19053174
- van Deursen JM (2014). The role of senescent cells in ageing. Nature 509(7501):439-46. — PubMed PMID: 24848057
- Tchkonia T, Zhu Y, van Deursen J, Campisi J, Kirkland JL (2013). Cellular senescence and the senescent secretory phenotype: therapeutic opportunities. Journal of Clinical Investigation 123(3):966-72. — PubMed PMID: 23454759
- Nambiar A, Kellogg D 3rd, Justice J, et al. (2023). Senolytics dasatinib and quercetin in idiopathic pulmonary fibrosis: results of a phase I, single-blind, single-center, randomized, placebo-controlled pilot trial on feasibility and tolerability. EBioMedicine 90:104481. — PubMed PMID: 36857968
- Gonzales MM, Garbarino VR, Kautz TF, et al. (2023). Senolytic therapy in mild Alzheimer's disease: a phase 1 feasibility trial. Nature Medicine 29(10):2481-2488. — PubMed PMID: 37679434
- Farr JN, Atkinson EJ, Achenbach SJ, et al. (2024). Effects of intermittent senolytic therapy on bone metabolism in postmenopausal women: a phase 2 randomized controlled trial. Nature Medicine 30(9):2605-2612. — PubMed PMID: 38956196
- Millar CL, Iloputaife I, Baldyga K, et al. (2025). A pilot study of senolytics to improve cognition and mobility in older adults at risk for Alzheimer's disease. EBioMedicine 113:105612. — PubMed PMID: 40010154
- Koning M, Kovynev A, Fondevila MF, et al. (2026). Senolytics dasatinib and quercetin in metabolic dysfunction-associated steatohepatitis: a proof-of-principle randomized, controlled trial. Nature Metabolism. — PubMed PMID: 42823536
- Harrison DE, Strong R, Reifsnyder P, et al. (2024). Astaxanthin and meclizine extend lifespan in UM-HET3 male mice; fisetin, SG1002 (hydrogen sulfide donor), dimethyl fumarate, mycophenolic acid, and 4-phenylbutyrate do not significantly affect lifespan in either sex at the doses and schedules used. GeroScience 46(1):795-816. — PubMed PMID: 38041783
PubMed Topic Searches
Connections
- Quercetin Overview
- Quercetin Benefits Hub
- Quercetin for Allergy & Histamine
- Quercetin for Cardiovascular Health
- Quercetin Zinc Ionophore
- Fisetin (Monotherapy Alternative)
- Fisetin Senolytic Activity
- Spermidine
- Longevity Protocols
- Rapamycin
- NAD+ and NMN
- Oxidative Stress
- Pulmonary Fibrosis
- Chronic Kidney Disease
- Osteoporosis
- Apples (Dietary Quercetin)
- History