Glutamine for Immune Function
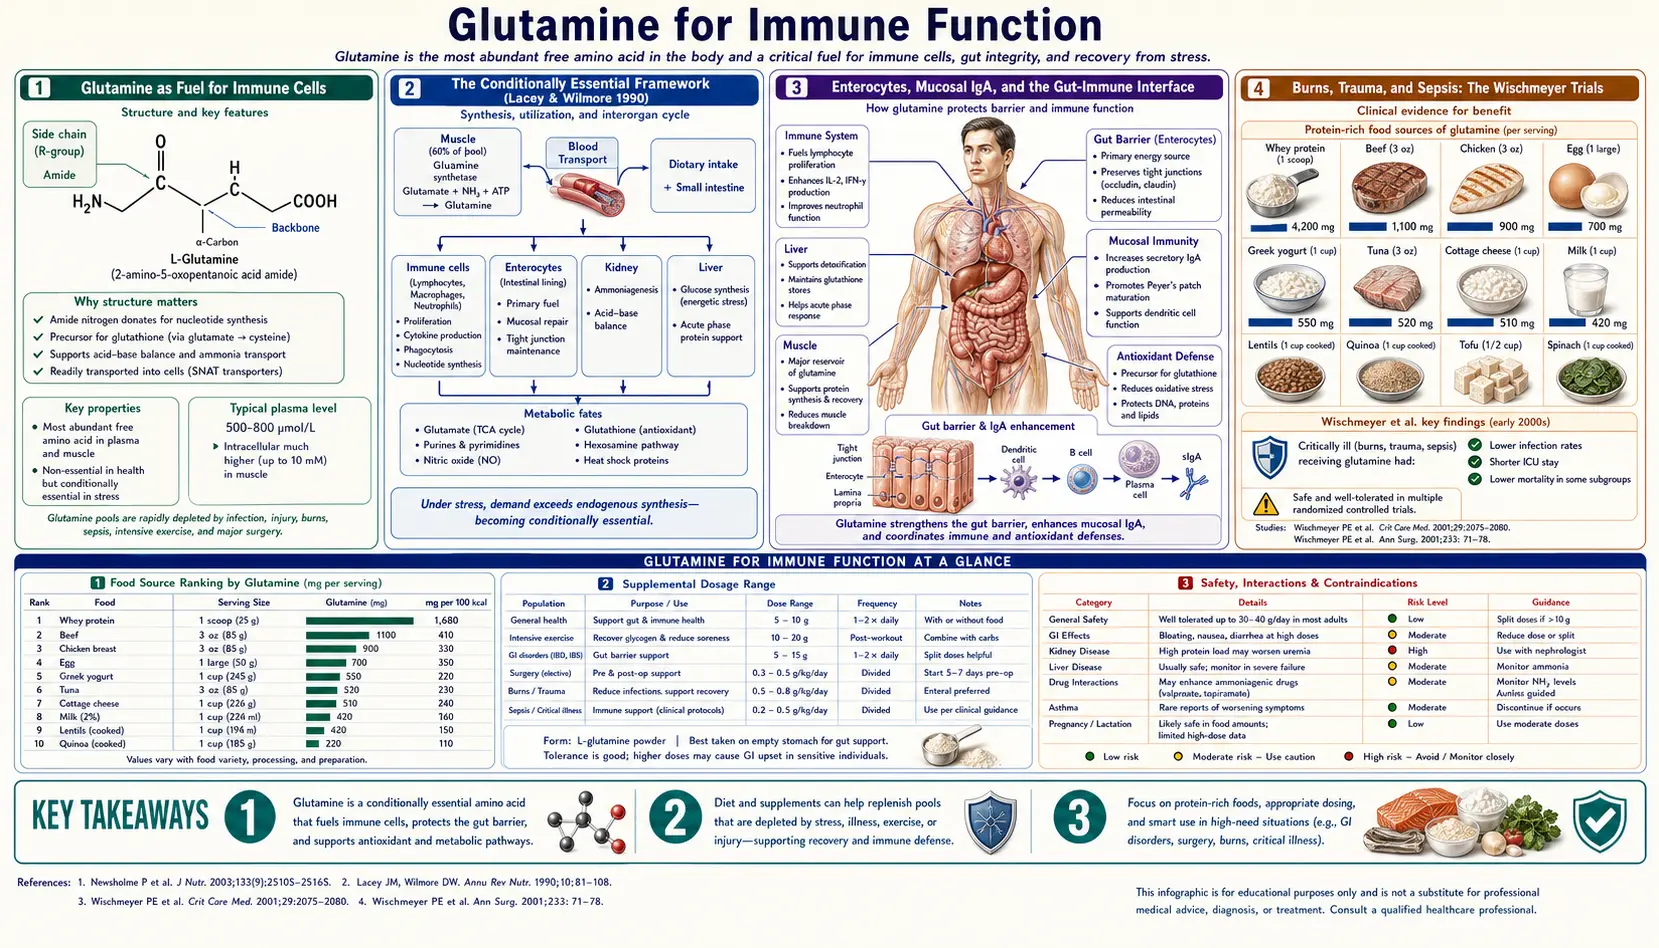
Glutamine is the dominant metabolic fuel for the rapidly dividing cells of the immune system — lymphocytes, neutrophils, and macrophages all consume glutamine at rates that meet or exceed their glucose consumption. Eric Newsholme, the Oxford biochemist who co-authored the first such measurement in rat lymphocytes in 1983, helped open the field, and Philip Newsholme later framed it in the title of a 2001 review as a question of substrate availability: "Why is L-glutamine metabolism important to cells of the immune system in health, postinjury, surgery or infection?" The answer, refined by three decades of follow-up work, is that the immune system shares with the gut and rapidly dividing tumor cells an absolute substrate preference for glutamine over glucose. Under conditions of catabolic stress — trauma, sepsis, severe burns, major surgery, the post-exercise "open window" in athletes — plasma glutamine can fall below the threshold at which immune cells can no longer mount an effective response, and the result is a documented increase in infection-related morbidity and mortality. This deep-dive walks through the cell-biology mechanisms, the pivotal Wischmeyer burn and intensive care unit (ICU) trials, the REDOXS controversy, and the practical clinical applications.
Table of Contents
- Glutamine as Fuel for Immune Cells
- The Conditionally Essential Framework (Lacey & Wilmore 1990)
- Enterocytes, Mucosal Immunoglobulin A, and the Gut-Immune Interface
- Burns, Trauma, and Sepsis: The Wischmeyer Trials
- The REDOXS Controversy
- Major Surgery and Bone Marrow Transplant
- The Post-Exercise "Open Window" of Immune Vulnerability
- Chronic Infection Recovery and Human Immunodeficiency Virus
- Dosing, Routes, and Alanyl-Glutamine Dipeptide
- Cautions (Including the REDOXS-Era Caveats)
- Key Research Papers
- Connections
- Featured Videos
Glutamine as Fuel for Immune Cells
Resting lymphocytes consume glutamine at roughly the same rate as glucose. Activated lymphocytes — cells that have encountered antigen and are clonally expanding to mount a response — consume glutamine at rates that meet or exceed glucose utilization. The same is true for neutrophils (the front-line phagocytes of acute bacterial infection) and macrophages (which carry out both antigen presentation and tissue clean-up). Ardawi and Newsholme's 1983 paper in the Biochemical Journal on glutamine metabolism in rat lymphocytes was the foundational measurement that established this dependency.
The biochemistry is straightforward: glutamine enters the cell, is deaminated to glutamate by glutaminase, and then enters the TCA cycle as alpha-ketoglutarate — a process called glutaminolysis. This generates adenosine triphosphate (ATP), but more importantly, it generates carbon skeletons for nucleotide biosynthesis (essential for DNA replication during cell division) and nitrogen for purine and pyrimidine synthesis. A lymphocyte that has just recognized antigen and is about to divide every 6-12 hours for several days needs nucleotides, and glutamine is the principal source.
This is the reason that under catabolic stress — major surgery, severe burns, sepsis, prolonged endurance exercise — the body breaks down skeletal muscle protein specifically to liberate glutamine for the immune system. Skeletal muscle stores roughly 70-80% of the body's free amino acid pool, and glutamine accounts for roughly 60% of that intramuscular pool. The muscle wasting visible in chronically ill or septic patients is in significant part a glutamine-redistribution phenomenon: muscle protein is being cannibalized to keep the gut and immune system alive.
The Conditionally Essential Framework (Lacey & Wilmore 1990)
The phrase "conditionally essential amino acid" was already in print by 1983, in a paper on taurine in human milk; Joanne Lacey and Douglas Wilmore applied it to glutamine in a 1990 Nutrition Reviews paper that became the conceptual foundation for the modern field of immunonutrition. Their argument: glutamine is non-essential under ordinary conditions because healthy adults synthesize it in adequate quantities. But under specific clinical conditions — major trauma, severe burns, sepsis, the metabolic stress of intensive care — endogenous synthesis cannot keep up with demand, plasma glutamine falls, and at some threshold the deficit becomes clinically significant. In those settings, glutamine must be supplied from outside the body and is functionally essential.
The Lacey-Wilmore framework set off a 30-year research program to map exactly which catabolic stress states reliably deplete plasma glutamine, what threshold of depletion correlates with clinical harm, and which patient populations benefit most from supplementation. The classical observation from intensive care medicine is that plasma glutamine below approximately 420 µmol/L on intensive care unit admission predicts increased mortality, independent of other markers of severity — making it one of the few amino acid measurements with prognostic value at the bedside.
Enterocytes, Mucosal Immunoglobulin A, and the Gut-Immune Interface
Roughly 70% of the body's immune tissue resides in the gut-associated lymphoid tissue (GALT), and the integrity of the gut barrier is itself a major component of immune defense. Glutamine's role here is dual: it fuels the enterocytes that make up the physical barrier (covered in detail in the companion Gut Health & Leaky Gut deep dive), and it supports the secretory immunoglobulin A (IgA) production that constitutes the chemical layer of mucosal immunity.
Studies of critically ill patients on parenteral nutrition without glutamine supplementation have shown progressive villous atrophy, decreased mucosal immunoglobulin A, and increased bacterial translocation across the gut wall — the classical "gut-origin sepsis" of intensive care. The Van der Hulst 1993 Lancet trial in 20 patients found that with glutamine-enriched total parenteral nutrition (TPN) intestinal permeability stayed unchanged and villus height was unaltered, while on standard TPN permeability increased and villus height decreased (bacterial translocation itself was not measured), a finding that helped drive the routine addition of glutamine dipeptide to modern parenteral nutrition formulations.
In ambulatory populations, the connection between gut barrier and systemic immunity is less dramatic but still measurable. Athletes engaged in prolonged endurance training transiently develop increased intestinal permeability, and the subsequent translocation of endotoxin into systemic circulation is one of the mechanisms behind the well-documented post-exercise immune dip discussed below.
Burns, Trauma, and Sepsis: The Wischmeyer Trials
Severe burn injury was long regarded as the clinical setting where the case for glutamine supplementation was strongest. Severely burned patients lose plasma glutamine within hours of the burn (the burn wound itself is metabolically active and consumes large quantities of glutamine), and the resulting deficit correlates with infectious complications, sepsis, and mortality. Paul Wischmeyer's research program at the University of Chicago and later Duke, and other early burn trials, reported that enteral or parenteral glutamine supplementation in burn patients:
- Reduced gram-negative bacteremia (Wischmeyer 2001, Critical Care Medicine)
- Reduced overall infectious morbidity and improved mortality (Garrel 2003, Critical Care Medicine)
- Restored plasma glutamine to physiologic ranges within 24-48 hours of starting supplementation
- Was well-tolerated even at the high doses (0.3-0.5 g/kg/day) used in these trials
The Garrel trial in particular was a milestone: of 45 adults with severe burns randomized to enteral glutamine or an isonitrogenous control mixture, 2 died in the glutamine group and 12 in the control group (intention-to-treat analysis). The American Burn Association and the Society of Critical Care Medicine subsequently incorporated glutamine supplementation into guidelines for severe burn management. Those guidelines predate the much larger RE-ENERGIZE trial (2022, New England Journal of Medicine), in which 1,209 patients with severe burns were randomized to 0.5 g per kilogram of body weight per day of enteral glutamine or placebo: glutamine did not shorten the time to discharge alive (median 40 vs 38 days), and 6-month mortality was 17.2% with glutamine and 16.2% with placebo.
Beyond burns, glutamine has been studied in major trauma, post-surgical patients, and septic shock. The Novak 2002 meta-analysis in Critical Care Medicine pooled the earlier trial data and concluded that glutamine supplementation reduced infectious complications and length of stay in critically ill patients, particularly in surgical and trauma populations.
The REDOXS Controversy
In 2013, Daren Heyland and colleagues published the REDOXS trial in the New England Journal of Medicine: a multi-center randomized trial of 1,223 critically ill intensive care unit patients with multi-organ failure randomized to high-dose glutamine plus antioxidants, glutamine alone, antioxidants alone, or placebo. The result was unexpected and disturbing: in-hospital mortality and 6-month mortality were significantly higher among patients who received glutamine than among those who did not, 28-day mortality showed a trend in the same direction, and glutamine had no effect on organ failure or infectious complications. The authors concluded that glutamine was associated with an increase in mortality.
REDOXS forced a re-evaluation of the field. Subsequent analysis identified several issues that likely explain the discordant result:
- Dosing was at the upper end of historical trials. The combined intravenous (IV) + enteral glutamine load in REDOXS was approximately 0.5 g/kg/day, well above the 0.2-0.3 g/kg/day used in most earlier positive trials.
- Many enrolled patients had multi-organ failure including renal and hepatic dysfunction. Glutamine generates ammonia during metabolism, and in patients with impaired renal or hepatic clearance, supraphysiologic glutamine loading may produce subclinical hyperammonemia that worsens outcomes.
- Baseline plasma glutamine was not measured at enrollment. A subgroup analysis suggested that patients with baseline plasma glutamine in the normal-to-high range did worse with supplementation, while those with low baseline glutamine showed a non-significant trend toward benefit — consistent with the hypothesis that glutamine supplementation helps only when there is a deficit to correct.
After REDOXS, routine high-dose supplementation in unselected intensive care unit patients was no longer recommended, while burn patients, select surgical populations, and patients with documented or strongly suspected glutamine deficiency remained the groups under study; the 2022 RE-ENERGIZE trial then found no benefit in severe burns. The Cruzat 2018 Nutrients review provides an integrated framework that discusses enteral doses of 0.2-0.3 g/kg/day, the risk in multi-organ failure with renal or hepatic dysfunction, and the populations with documented benefit.
Major Surgery and Bone Marrow Transplant
Outside the intensive care unit, the surgical and bone-marrow-transplant literature on glutamine remains generally favorable. Ziegler's 1992 Annals of Internal Medicine trial in patients undergoing allogeneic bone marrow transplantation showed that glutamine-supplemented parenteral nutrition reduced length of stay, infectious morbidity, and improved nitrogen balance — a setting where the catabolic stress of conditioning chemotherapy and the immunosuppression of transplant make glutamine demand particularly high.
In elective major abdominal surgery, perioperative glutamine supplementation (typically 0.3-0.4 g/kg/day) is associated with reduced postoperative infections and shorter hospital stays in multiple smaller trials and at least two meta-analyses. The effect size is modest but consistent. The ESPEN (European Society for Clinical Nutrition and Metabolism) guidelines currently recommend perioperative glutamine in selected high-risk surgical patients, particularly those undergoing major upper gastrointestinal (GI) surgery, pancreatectomy, or esophagectomy.
The Post-Exercise "Open Window" of Immune Vulnerability
Lucy Castell and Eric Newsholme's 1997 paper in Nutrition is often cited for what became known as the "open-window" idea: a period after prolonged exhaustive exercise when the immune system is weakened. They studied middle-distance, marathon and ultra-marathon runners and elite rowers. Infections reported on a questionnaire over the 7 days after exercise were highest in the marathon and ultra-marathon runners and in elite male rowers after intensive training; plasma glutamine fell by approximately 20% one hour after marathon running; white blood cells rose immediately after exhaustive exercise and lymphocyte numbers then fell. Oral glutamine after exercise "appeared to have a beneficial effect" on the level of later infections.
Subsequent work has nuanced this picture. The post-exercise immune dip is real and reliably reproducible, but the contribution of glutamine specifically (versus generalized stress hormones, cytokines, and other catabolic signals) is harder to isolate. Modern sports-nutrition reviews (Coqueiro 2019, Walsh 1998) treat glutamine as one component of post-event recovery rather than a standalone immune intervention — alongside carbohydrate replenishment, vitamin D adequacy, and sleep. The companion Exercise Recovery deep-dive page explores this further.
In practice, endurance athletes preparing for or recovering from events lasting more than two hours are described as taking 5-10 g of L-glutamine per day during the high-training-load period, with an additional 5 g immediately post-event. The evidence is suggestive rather than definitive; glutamine is inexpensive.
Chronic Infection Recovery and Human Immunodeficiency Virus
The Calder & Yaqoob 1999 Amino Acids review surveyed the role of glutamine in chronic infection and human immunodeficiency virus (HIV). Human immunodeficiency virus-positive patients with wasting syndrome typically show low plasma glutamine, and supplementation has been studied as an adjunct to antiretroviral therapy for preserving lean body mass and supporting immune function. Several small trials showed weight gain and trends toward improved CD4 counts in glutamine-supplemented patients, though large definitive trials were never completed before the advent of effective antiretrovirals made human immunodeficiency virus-wasting syndrome much less common.
For chronic infection recovery in immunocompetent patients — the post-Lyme, post-mononucleosis, post-COVID, or general "post-viral fatigue" populations — glutamine is sometimes used as part of immune-support protocols at 5-10 g/day for 4-12 weeks. The evidence base is weak; practitioners who use it point to the biologically plausible mechanism.
Dosing, Routes, and Alanyl-Glutamine Dipeptide
Oral Powder (Most Common Outpatient Form)
- Amounts in trials: the 2022 RE-ENERGIZE burn trial gave 0.5 g per kilogram of body weight per day by the enteral route (no benefit found); the elective-surgery trials described above used about 0.3-0.4 g/kg/day around the time of the operation
- Amounts described in everyday use: 5 g once or twice daily, taken on an empty stomach in room-temperature water, and 10 g two to three times daily for 5-14 days during acute illness or after an endurance event; these are practice figures, not trial-tested regimens
Alanyl-Glutamine Dipeptide (Parenteral / Enteral Tube Feeds)
Free L-glutamine is unstable in solution at neutral pH and degrades to ammonia and pyroglutamic acid when stored in intravenous bags, which is why clinical parenteral glutamine is administered as the more stable L-alanyl-L-glutamine dipeptide, as an intravenous alanyl-glutamine dipeptide solution. This is the form used in most modern intensive care unit and surgical trials, and the form referenced in the ESPEN guidelines for parenteral nutrition. The doses described are typically 0.3-0.4 g/kg/day as the dipeptide.
Timing
Oral glutamine is commonly taken on an empty stomach, because the other amino acids in a high-protein meal compete for the same intestinal transporters. Free glutamine is a single amino acid rather than a protein, so heat does not "denature" it; its slow breakdown in solution, described above, is the relevant chemistry.
Cautions (Including the REDOXS-Era Caveats)
- Multi-organ failure with renal or hepatic dysfunction — the principal lesson of REDOXS, which found significantly higher in-hospital and 6-month mortality with glutamine in critically ill patients with multi-organ failure. Glutamine metabolism generates ammonia, which failing kidneys or liver may not safely clear.
- Hepatic encephalopathy — the same ammonia issue, more acutely: ammonia generated by glutamine metabolism adds to the load a failing liver cannot clear in active encephalopathy.
- Active cancer — "glutamine addiction" of rapidly dividing tumor cells (Wise & Thompson 2010) is a real phenomenon. Some studies suggest benefit from glutamine in reducing chemotherapy-induced mucositis (Sayles 2016); others raise concerns about fueling tumor growth; the question is unresolved.
- Seizure disorders — glutamine is the metabolic precursor to glutamate, the principal excitatory neurotransmitter, which is the basis of the concern raised for seizure disorders.
- Severe renal insufficiency or dialysis — the nitrogen and ammonia load from glutamine metabolism depends on kidney clearance, which is reduced in these settings.
- Routine high-dose supplementation in unselected intensive care unit populations — no longer recommended after REDOXS; the remaining areas of study are trauma, selected surgical patients and documented deficiency, and the 2022 RE-ENERGIZE trial found no benefit in severe burns.
Key Research Papers
- Ardawi MS, Newsholme EA (1983). Glutamine metabolism in lymphocytes of the rat. Biochemical Journal. Foundational measurement establishing glutamine's role in lymphocyte metabolism. — PubMed PMID: 6882397
- Lacey JM, Wilmore DW (1990). Is glutamine a conditionally essential amino acid? Nutrition Reviews. The classic paper applying the conditionally essential concept to glutamine. — PubMed PMID: 2080048
- Newsholme P (2001). Why is L-glutamine metabolism important to cells of the immune system in health, postinjury, surgery or infection? Journal of Nutrition. — PubMed PMID: 11533304
- Calder PC, Yaqoob P (1999). Glutamine and the immune system. Amino Acids. — PubMed PMID: 10582122
- Cruzat V, Macedo Rogero M, Noel Keane K, Curi R, Newsholme P (2018). Glutamine: Metabolism and Immune Function, Supplementation and Clinical Translation. Nutrients 10(11):1564. The modern integrated review. — PubMed PMID: 30360490
- Wischmeyer PE (2003). Clinical applications of L-glutamine: past, present, and future. Nutrition in Clinical Practice. — PubMed PMID: 16215069
- Wischmeyer PE et al. (2001). Glutamine administration reduces gram-negative bacteremia in severely burned patients. Critical Care Medicine. — PubMed PMID: 11700398
- Garrel D et al. (2003). Decreased mortality and infectious morbidity in adult burn patients given enteral glutamine supplements. Critical Care Medicine. — PubMed PMID: 14530749
- Novak F, Heyland DK, Avenell A, Drover JW, Su X (2002). Glutamine supplementation in serious illness: a systematic review of the evidence. Critical Care Medicine 30(9):2022-9. — PubMed PMID: 12352035
- Heyland D, Muscedere J, Wischmeyer PE, Cook D, Jones G, Albert M, Elke G, Berger MM, Day AG; Canadian Critical Care Trials Group (2013). A randomized trial of glutamine and antioxidants in critically ill patients (REDOXS trial). NEJM 368(16):1489-1497. The trial that reshaped ICU glutamine practice. — PubMed PMID: 23594003
- Heyland DK, Wibbenmeyer L, Pollack J, et al.; RE-ENERGIZE Trial Team (2022). A randomized trial of enteral glutamine for treatment of burn injuries. NEJM 387(11):1001-1010. — PubMed PMID: 36082909
- Gaull GE (1983). Taurine in human milk: growth modulator or conditionally essential amino acid? Journal of Pediatric Gastroenterology and Nutrition 2 Suppl 1:S266-71. — PubMed PMID: 6417307
- Ziegler TR et al. (1992). Clinical and metabolic efficacy of glutamine-supplemented parenteral nutrition after bone marrow transplantation. Annals of Internal Medicine. — PubMed PMID: 1567096
- Van der Hulst RR, van Kreel BK, von Meyenfeldt MF et al. (1993). Glutamine and the preservation of gut integrity. The Lancet 341(8857):1363-5. — PubMed PMID: 8098788
- Sayles C et al. (2016). Oral glutamine in preventing treatment-related mucositis in adult patients with cancer. Nutrition in Clinical Practice. — PubMed PMID: 26507188
- Castell LM, Newsholme EA (1997). The effects of oral glutamine supplementation on athletes after prolonged, exhaustive exercise. Nutrition. Often cited as the "open window" paper. — PubMed PMID: 9263279
PubMed Topic Searches
Connections
- All Amino Acids
- Glutamine Overview
- Glutamine Benefits Hub
- Glutamine for Gut Health & Leaky Gut
- Glutamine for Exercise Recovery
- Glutamine for Weight Loss Support
- Arginine
- Cysteine
- Glycine
- N-Acetylcysteine & Glutathione
- Vitamin D3
- Vitamin A for Immune Function
- Vitamin C
- Zinc
- Selenium
- Immune Boosting
- Gut Healing
- Fatigue
- Pneumonia
- Crohn's Disease
- Inflammatory Bowel Disease
- Inflammatory Markers
- Bone Broth
- History
- Sources