Glutamine — Benefits Deep Dive
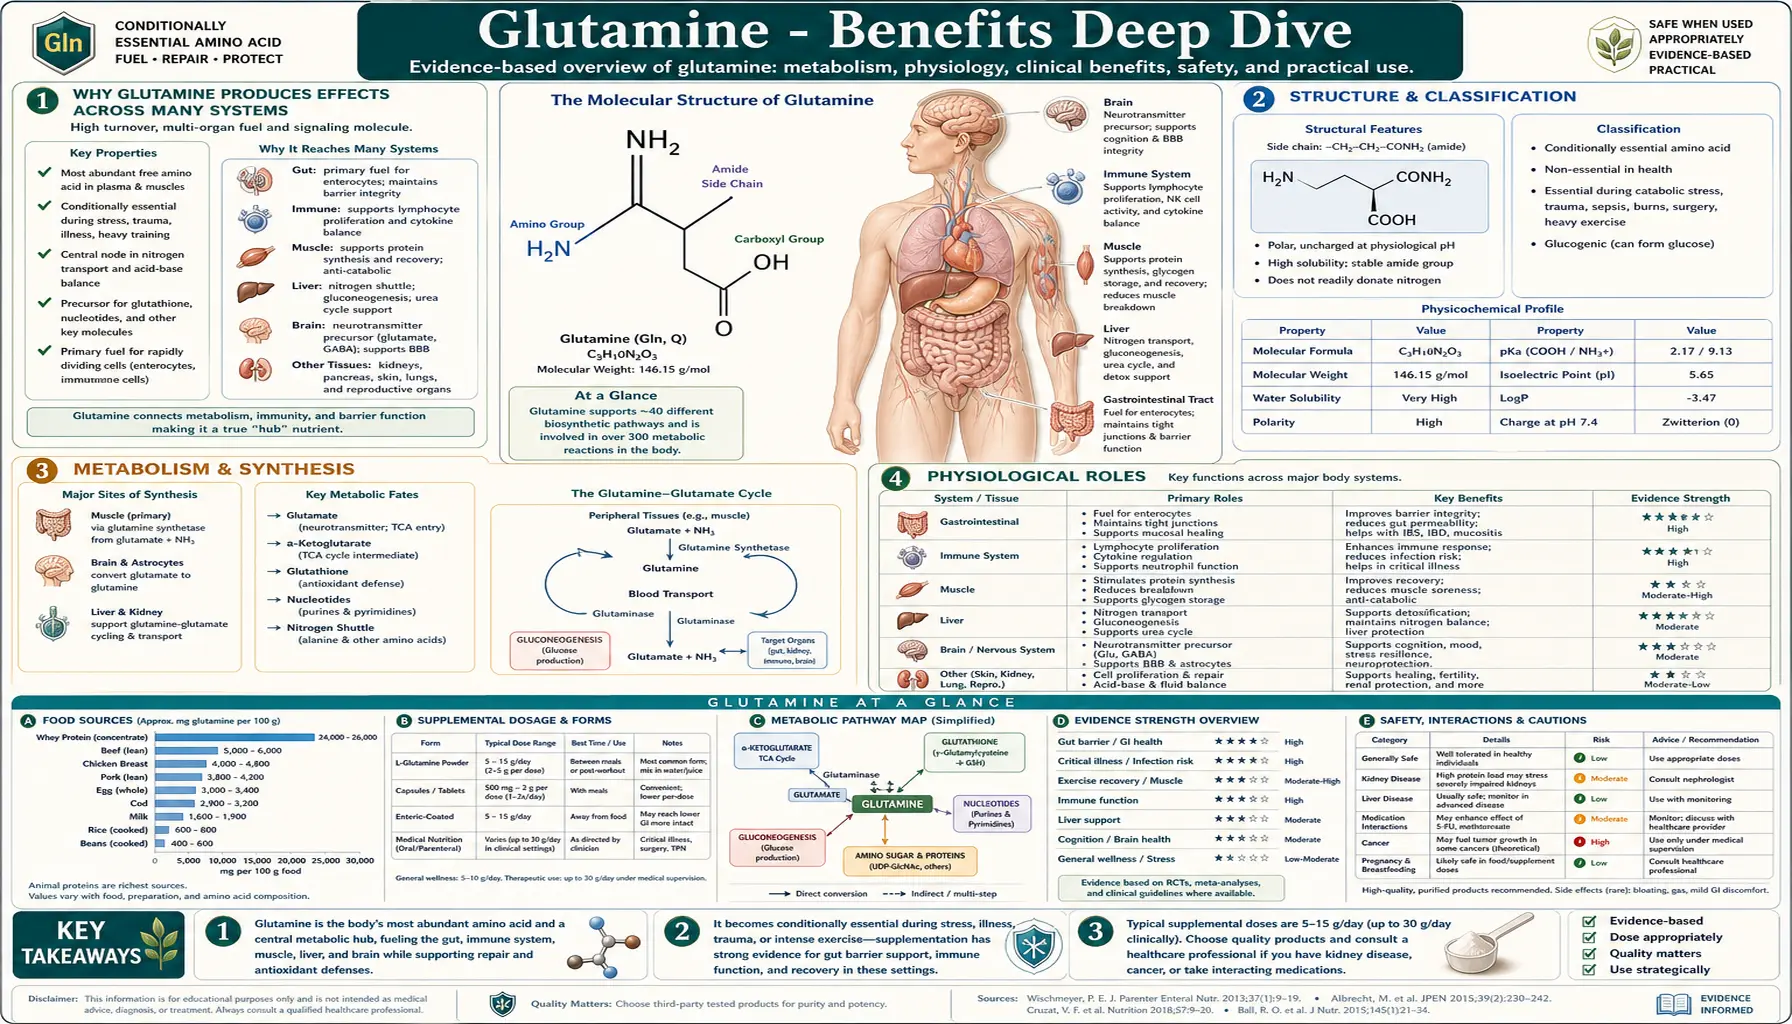
Glutamine is the single most abundant free amino acid in the human body — circulating in plasma at higher concentrations than any other amino acid and stored in skeletal muscle at roughly 60% of the total free amino-acid pool. Although the liver, lungs, and skeletal muscle synthesize it endogenously under ordinary conditions, glutamine becomes conditionally essential during catabolic stress: critical illness, major surgery, severe burns, sepsis, prolonged endurance exercise, and chemotherapy can all drive plasma glutamine below the threshold at which gut enterocytes, lymphocytes, and macrophages can no longer function normally. Five benefit pages below explore where supplemental glutamine has been studied most — gut barrier repair in leaky gut and inflammatory bowel disease (IBD), immune support in trauma and intensive care unit (ICU) populations, recovery from heavy training, weight management through cravings, lean-mass preservation, and microbiome modulation, and recovery after surgery.
Deep-Dive Articles
Gut Health & Leaky Gut
Glutamine as the primary fuel for enterocytes, the upregulation of tight-junction proteins (claudin-1, occludin, ZO-1), heat shock protein induction, mucin synthesis support, and the clinical protocol for repairing increased intestinal permeability driven by nonsteroidal anti-inflammatory drugs (NSAIDs), alcohol, chronic stress, gluten sensitivity, dysbiosis, and intense exercise. Includes Benjamin 2012 Crohn's trial, Zhou 2019 post-infectious irritable bowel syndrome (IBS) trial, and the Achamrah bench-to-bedside framework.
Read the deep dive →Immune Function
Glutamine as the dominant fuel for rapidly dividing lymphocytes, neutrophils, and macrophages — consumed at rates rivaling glucose. The Wischmeyer burn and intensive care unit trials, the REDOXS trial controversy, the conditional-essentiality framework of Lacey and Wilmore, immunonutrition in surgical patients, and why the "anti-fatigue" effect of glutamine in athletes is really an immune-support effect against the post-exercise "open-window" of vulnerability.
Read the deep dive →Exercise Recovery
The Newsholme depletion-in-overtraining hypothesis, plasma glutamine drops of 20-40% after marathon and ultra-endurance events, the branched-chain amino acid-glutamine synergy, post-exercise glycogen resynthesis (Bowtell), muscle soreness attenuation (Legault, Street), and the oral-vs-IV question. Where the evidence is strong (recovery, immune protection, gut barrier in athletes) and where it remains thin (direct hypertrophy, strength gains in trained lifters).
Read the deep dive →Weight Loss Support
The sublingual L-glutamine craving-extinction technique (1-2 g under the tongue, relief in minutes via gluconeogenic glucose support to the brain), preservation of lean muscle mass during calorie restriction, the de Souza 2015 gut-microbiota shift in overweight adults, the Greenfield 2009 glucagon-like peptide-1 (GLP-1) augmentation finding, and the Laviano 2014 pilot trial in obese non-dieting women. Why glutamine is a foundational metabolic-support nutrient, not a fat burner.
Read the deep dive →Surgery & Post-Surgical Recovery
What forty years of surgical trials actually show: the Sandini meta-analysis of 19 elective abdominal randomized controlled trials (RCTs) (hospital stay 2.67 days shorter, complications unchanged), the REDOXS trial where glutamine increased mortality in multi-organ failure, the RE-ENERGIZE null result in severe burns, and the Stehle boundaries — dose, route and organ function — that reconcile them. Why intravenous (IV) alanyl-glutamine dipeptide and oral powder are not the same intervention: the trials in the Sandini meta-analysis all gave glutamine dipeptide into a vein, and its authors judged them “underpowered and of medium or low quality”, so the result says nothing direct about oral powder.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why Glutamine Produces Effects Across Many Systems
- Glutamine as an Approved Medicine for Sickle Cell Disease
- Research Papers: Gut Health & Leaky Gut
- Research Papers: Immune Function & Critical Care
- Research Papers: Exercise Recovery
- Research Papers: Weight Loss, Metabolic Health, Cravings
- Research Papers: Cross-Cutting (Mechanism, Glutathione, Safety)
- External Authoritative Resources
- Connections
- Featured Videos
Why Glutamine Produces Effects Across Many Systems
Most amino acids have one or two principal jobs. Glutamine has at least five, which is why it shows up in nearly every major organ system and why supplementing it can produce measurable effects on gut, immunity, recovery, and metabolism simultaneously. The molecule is unusual because it carries two nitrogen atoms (one in the alpha-amino group, one in the amide side chain), making it the body's preferred nitrogen carrier between tissues. Five distinct roles map to five distinct clinical effect categories.
- Primary fuel for enterocytes (intestinal lining cells) — enterocytes turn over every 3-5 days and prefer glutamine over glucose for adenosine triphosphate (ATP) production. This is the mechanism behind the gut-barrier and leaky-gut effects: without adequate glutamine, the rapidly dividing intestinal epithelium cannot maintain its tight junctions, mucus layer, or rate of turnover, and increased intestinal permeability ensues.
- Primary fuel for rapidly dividing immune cells — lymphocytes, neutrophils, and macrophages consume glutamine at rates comparable to or exceeding glucose, especially during an active immune response. This is the mechanism behind the immune-support effects in burns, trauma, intensive care unit patients, and post-exercise athletes, all of whom show measurable plasma glutamine depletion correlated with infection risk.
- Inter-organ nitrogen carrier — glutamine is the principal vehicle that shuttles nitrogen from peripheral tissues to the liver (for urea synthesis), kidney (for ammonia production and acid-base balance), and gut (for nucleotide synthesis). During catabolic stress, skeletal muscle breaks down its protein stores specifically to liberate glutamine for these other tissues, which is why prolonged stress, sepsis, or starvation produces visible muscle wasting.
- Gluconeogenic substrate — both the liver and the renal cortex can convert glutamine to glucose, making it a non-carbohydrate source of blood sugar between meals and during fasting. This is the explanation practitioners give for the sublingual craving-extinction technique: practitioners describe a small dose dissolved under the tongue as easing the urgency of a sugar or alcohol craving within minutes. This is a reported technique, not a tested mechanism; the classic alcohol experiment behind it (Rogers, Pelton and Williams, 1955) was done in rats.
- Precursor to glutamate (and downstream gamma-aminobutyric acid, GABA) and to glutathione — in the brain, glutamine crosses the blood-brain barrier and feeds the glutamate-glutamine cycle that supplies both the principal excitatory neurotransmitter (glutamate) and, indirectly, the principal inhibitory neurotransmitter (gamma-aminobutyric acid). Throughout the body, glutamine supplies the glutamate backbone of glutathione, the most abundant endogenous antioxidant. Glutamine depletion therefore impairs both neurotransmission and antioxidant defense in addition to its more obvious gut and immune effects.
The therapeutic implication of these five overlapping roles is that under conditions of catabolic stress — burn injury, sepsis, major surgery, intense endurance training, severe inflammatory bowel disease, chemotherapy, prolonged calorie restriction — the demand for glutamine in any one of these roles can starve the others. The often-quoted 420 µmol/L cut-off comes from one study of 80 seriously ill adults admitted to a Dutch intensive care unit (Oudemans-van Straaten 2001): the 25 patients whose blood glutamine was below 420 µmol/L on admission were older, more often in shock, and had a hospital death rate of 60% against 29% for the others. Their illness-severity scores were only slightly (not significantly) higher, and adding low glutamine to a standard severity score improved the prediction of death. What is not known is whether a low level causes the extra deaths or simply marks the sickest patients: when supplements were later given to raise glutamine, they did not lower deaths. In the RE-ENERGIZE trial (1,200 adults with severe burns, 0.5 g per kg of body weight per day of glutamine by tube or mouth), the time to leave hospital alive was a median of 40 days on glutamine against 38 days on placebo, and 6-month mortality was 17.2% against 16.2% (Heyland 2022). A 2023 meta-analysis of 18 randomized trials in 2,552 critically ill adults found that glutamine given by mouth or tube did not change hospital deaths (odds ratio 1.05), intensive care stay or infections, though hospital stay was about 2.85 days shorter; its authors concluded that the data “do not support enteral GLN supplementation used routinely in critical illness patients” (Liang 2024). The Weight Loss Support deep-dive page on this hub explores the metabolic side of this story on this hub explores the metabolic side of this story: how glutamine supplementation can support healthy body composition during caloric restriction by preserving the lean muscle that would otherwise be cannibalized to supply glutamine to gut, immune, and renal systems.
Glutamine as an Approved Medicine for Sickle Cell Disease
Pharmaceutical-grade L-glutamine is also a prescription medicine for sickle cell disease, where it is thought to lower oxidative stress inside sickled red blood cells. In the phase 3 trial (Niihara 2018), 230 children and adults aged 5 to 58 took 0.3 g of L-glutamine per kg of body weight twice a day by mouth, or a placebo, for 48 weeks; about two thirds of both groups also took hydroxyurea. The glutamine group had a median of 3 pain crises against 4 on placebo, and a median of 2 hospital stays against 3. Low-grade nausea, chest pain not coming from the heart, tiredness and muscle or joint pain were more common on glutamine.
Research Papers: Gut Health & Leaky Gut
- Kim MH, Kim H (2017). The Roles of Glutamine in the Intestine and Its Implication in Intestinal Diseases. International Journal of Molecular Sciences. — PubMed
- Rao R, Samak G (2012). Role of Glutamine in Protection of Intestinal Epithelial Tight Junctions. Journal of Epithelial Biology and Pharmacology. — PubMed
- Achamrah N, Déchelotte P, Coëffier M (2017). Glutamine and the regulation of intestinal permeability: from bench to bedside. Current Opinion in Clinical Nutrition and Metabolic Care. — PubMed
- Wang B et al. (2015). Glutamine and intestinal barrier function. Amino Acids. — PubMed
- Van der Hulst RR et al. (1993). Glutamine and the preservation of gut integrity. The Lancet. — PubMed
- Benjamin J et al. (2012). Glutamine and whey protein improve intestinal permeability and morphology in patients with Crohn's disease. Digestive Diseases and Sciences. — PubMed
- Zhou Q et al. (2019). Randomised placebo-controlled trial of dietary glutamine supplements for postinfectious irritable bowel syndrome. Gut. — PubMed
- Rapin JR, Wiernsperger N (2010). Possible links between intestinal permeability and food processing: A potential therapeutic niche for glutamine. Clinics. — PubMed
- Souba WW (1991). Glutamine: a key substrate for the splanchnic bed. Annual Review of Nutrition 11:285-308. — PubMed PMID: 1892702
Research Papers: Immune Function & Critical Care
- Cruzat V, Macedo Rogero M, Noel Keane K, Curi R, Newsholme P (2018). Glutamine: Metabolism and Immune Function, Supplementation and Clinical Translation. Nutrients 10(11):1564. — PubMed
- Newsholme P (2001). Why is L-glutamine metabolism important to cells of the immune system in health, postinjury, surgery or infection? Journal of Nutrition. — PubMed
- Calder PC, Yaqoob P (1999). Glutamine and the immune system. Amino Acids. — PubMed
- Ardawi MS, Newsholme EA (1983). Glutamine metabolism in lymphocytes of the rat. Biochemical Journal. — PubMed
- Wischmeyer PE (2003). Clinical applications of L-glutamine: past, present, and future. Nutrition in Clinical Practice. — PubMed
- Novak F, Heyland DK, Avenell A, Drover JW, Su X (2002). Glutamine supplementation in serious illness: a systematic review of the evidence. Critical Care Medicine 30(9):2022-9. — PubMed
- Heyland D, Muscedere J, Wischmeyer PE et al. (2013). A randomized trial of glutamine and antioxidants in critically ill patients (REDOXS trial). NEJM 368:1489-1497. — PubMed
- Wischmeyer PE et al. (2001). Glutamine administration reduces gram-negative bacteremia in severely burned patients. Critical Care Medicine. — PubMed
- Garrel D et al. (2003). Decreased mortality and infectious morbidity in adult burn patients given enteral glutamine supplements. Critical Care Medicine. — PubMed
- Ziegler TR et al. (1992). Clinical and metabolic efficacy of glutamine-supplemented parenteral nutrition after bone marrow transplantation. Annals of Internal Medicine. — PubMed
- Lacey JM, Wilmore DW (1990). Is glutamine a conditionally essential amino acid? Nutrition Reviews. — PubMed
- Oudemans-van Straaten HM, Bosman RJ, Treskes M, van der Spoel HJ, Zandstra DF (2001). Plasma glutamine depletion and patient outcome in acute ICU admissions. Intensive Care Medicine 27(1):84-90. — PubMed PMID: 11280678
- Sandini M, Nespoli L, Oldani M, Bernasconi DP, Gianotti L (2015). Effect of glutamine dipeptide supplementation on primary outcomes for elective major surgery: systematic review and meta-analysis. Nutrients 7(1):481-99. — PubMed PMID: 25584966
- Heyland DK, Wibbenmeyer L, Pollack J, et al. (2022). A Randomized Trial of Enteral Glutamine for Treatment of Burn Injuries. New England Journal of Medicine 387(11):1001-1010. — PubMed PMID: 36082909
- Liang B, Su J, Chen J, Shao H, Shen L, Xie B (2024). Glutamine enteral therapy for critically ill adult patients: An updated meta-analysis of randomized controlled trials and trial sequential analysis. Clinical Nutrition 43(1):124-133. — PubMed PMID: 38041938
Research Papers: Exercise Recovery
- Castell LM, Newsholme EA (1997). The effects of oral glutamine supplementation on athletes after prolonged, exhaustive exercise. Nutrition. — PubMed
- Legault Z, Bagnall N, Kimmerly DS (2015). The Influence of Oral L-Glutamine Supplementation on Muscle Strength Recovery and Soreness Following Unilateral Knee Extension Eccentric Exercise. International Journal of Sport Nutrition and Exercise Metabolism. — PubMed
- Coqueiro AY, Raizel R, Bonvini A, Tirapegui J, Rogero MM (2019). Glutamine as an Anti-Fatigue Amino Acid in Sports Nutrition. Nutrients. — PubMed
- Street B et al. (2011). Glutamine supplementation in recovery from eccentric exercise attenuates strength loss and muscle soreness. Journal of Exercise Science and Fitness. — PubMed
- Bowtell JL et al. (1999). Effect of oral glutamine on whole body carbohydrate storage during recovery from exhaustive exercise. Journal of Applied Physiology. — PubMed
- Hickson RC et al. (1995). Glutamine prevents downregulation of myosin heavy chain synthesis and muscle atrophy from glucocorticoids. American Journal of Physiology. — PubMed
- Biolo G, Zorat F, Antonione R, Ciocchi B (2005). Muscle glutamine depletion in the intensive care unit. International Journal of Biochemistry and Cell Biology. — PubMed
- Gleeson M (2008). Dosing and efficacy of glutamine supplementation in human exercise and sport training. Journal of Nutrition. — PubMed
- Cordova-Martinez A et al. (2021). Effect of glutamine supplementation on muscular damage biomarkers in professional basketball players. Nutrients. — PubMed
- Walsh NP, Blannin AK, Robson PJ, Gleeson M (1998). Glutamine, exercise and immune function. Links and possible mechanisms. Sports Medicine. — PubMed
Research Papers: Weight Loss, Metabolic Health, Cravings
- Laviano A, Molfino A, Lacaria MT, Canelli A, De Leo S, Preziosa I, Rossi Fanelli F (2014). Glutamine supplementation favors weight loss in nondieting obese female patients: A pilot study. European Journal of Clinical Nutrition. — PubMed
- de Souza AZ, Zambom AZ, Abboud KY et al. (2015). Oral supplementation with L-glutamine alters gut microbiota of obese and overweight adults. Nutrition. — PubMed
- Greenfield JR et al. (2009). Oral glutamine increases circulating glucagon-like peptide 1, glucagon, and insulin concentrations in lean, obese, and type 2 diabetic subjects. American Journal of Clinical Nutrition. — PubMed
- Mansour A et al. (2015). Effect of glutamine supplementation on cardiovascular risk factors in patients with type 2 diabetes. Nutrition. — PubMed
- Samocha-Bonet D, Wong O, Synnott EL et al. (2011). Glutamine reduces postprandial glycemia and augments the glucagon-like peptide-1 response in type 2 diabetes patients. Journal of Nutrition. — PubMed
- Abboud KY et al. (2019). Oral Glutamine Supplementation Reduces Obesity, Pro-Inflammatory Markers, and Improves Insulin Sensitivity in DIO Wistar Rats and Reduces Waist Circumference in Overweight and Obese Humans. Nutrients 11(3):536. — PubMed PMID: 30832230
- Williams RJ (1959). Alcoholism: the nutritional approach. University of Texas Press (classical observation that glutamine reduces voluntary alcohol consumption). — PubMed
- Rogers LL, Pelton RB, Williams RJ (1955). Voluntary alcohol consumption by rats following administration of glutamine. Journal of Biological Chemistry 214(2):503-6. — PubMed PMID: 14381386
- Iwashita S, Mikus C, Baier S, Flakoll PJ (2006). Glutamine supplementation increases postprandial energy expenditure and fat oxidation in humans. JPEN Journal of Parenteral and Enteral Nutrition 30(2):76-80. — PubMed PMID: 16517950
- Reimann F, Tolhurst G, Gribble FM (2012). G-protein-coupled receptors in intestinal chemosensation (relevant to GLP-1 release by glutamine). Cell Metabolism. — PubMed
Research Papers: Cross-Cutting (Mechanism, Glutathione, Safety)
- Curi R et al. (2005). Molecular mechanisms of glutamine action. Journal of Cellular Physiology. — PubMed
- Roth E (2008). Nonnutritive Effects of Glutamine. Journal of Nutrition. — PubMed
- Amores-Sánchez MI, Medina MÁ (1999). Glutamine, as a precursor of glutathione, and oxidative stress. Molecular Genetics and Metabolism. — PubMed
- Flaring UB, Rooyackers OE, Wernerman J, Hammarqvist F (2003). Glutamine attenuates post-traumatic glutathione depletion in human muscle. Clinical Science. — PubMed
- Valencia E et al. (2002). Impact of oral L-glutamine on glutathione, glutamine, and glutamate blood levels in volunteers. Nutrition. — PubMed
- Albrecht J, Sidoryk-Węgrzynowicz M, Zielińska M, Aschner M (2010). Roles of glutamine in neurotransmission. Neuron Glia Biology. — PubMed
- Bak LK, Schousboe A, Waagepetersen HS (2006). The glutamate/GABA-glutamine cycle. Journal of Neurochemistry. — PubMed
- Wise DR, Thompson CB (2010). Glutamine addiction: a new therapeutic target in cancer. Trends in Biochemical Sciences. — PubMed
- Garlick PJ (2001). Assessment of the safety of glutamine and other amino acids. Journal of Nutrition. — PubMed
- Ziegler TR, Benfell K, Smith RJ, et al. (1990). Safety and metabolic effects of L-glutamine administration in humans. JPEN Journal of Parenteral and Enteral Nutrition 14(4 Suppl):137S-146S. — PubMed PMID: 2119459
- Niihara Y, Miller ST, Kanter J, et al. (2018). A Phase 3 Trial of l-Glutamine in Sickle Cell Disease. New England Journal of Medicine 379(3):226-235. — PubMed PMID: 30021096
External Authoritative Resources
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Dietary Supplements for Exercise and Athletic Performance — covers glutamine among the supplements studied for exercise and athletic performance
- U.S. National Institutes of Health Office of Dietary Supplements — Fact Sheets Index — includes amino acid factsheets for clinical reference
- LiverTox (U.S. National Institutes of Health) — L-Glutamine — clinical and research reference on liver-injury reports, dosing, and cautions
- MDPI Nutrients — open-access journal hosting the Cruzat 2018 and Coqueiro 2019 reviews
- PubMed — All research on glutamine (more than 30,000 indexed papers)
- PubMed — Glutamine clinical trials
- PubMed — Glutamine meta-analyses
Connections
- All Amino Acids
- Glutamine (Main Page)
- Glutamine for Gut Health & Leaky Gut
- Glutamine for Immune Function
- Glutamine for Exercise Recovery
- Glutamine for Weight Loss Support
- Glutamine for Surgery & Post-Surgical Recovery
- Glutamic Acid (Glutamate)
- Glycine
- Cysteine (Glutathione Precursor)
- Arginine
- Leucine (Branched-Chain Amino Acid)
- N-Acetylcysteine & Glutathione
- Gut Healing
- Gut-Brain Axis
- Inflammatory Bowel Disease
- Irritable Bowel Syndrome
- Crohn's Disease
- Diabetes
- Obesity
- Bone Broth
- Probiotics
- Collagen
- Zinc
- Blood Sugar
- Fasting
- How the Body Makes Its Own Glutamine
- History
- Sources