⚠ Evidence warning: Clinical trials or other evidence do not support the claims that 600 mg of N-acetylcysteine a day gives general respiratory antioxidant support, that 1800 mg a day helps bronchiectasis, that 400-600 mg a day reduces days of disability, and that its benefit in chronic obstructive pulmonary disease concentrates in the most severe cases. This page keeps it as a report of what people, websites or other media say.
N-acetyl-cysteine and Lung Health (Cysteine Benefits)
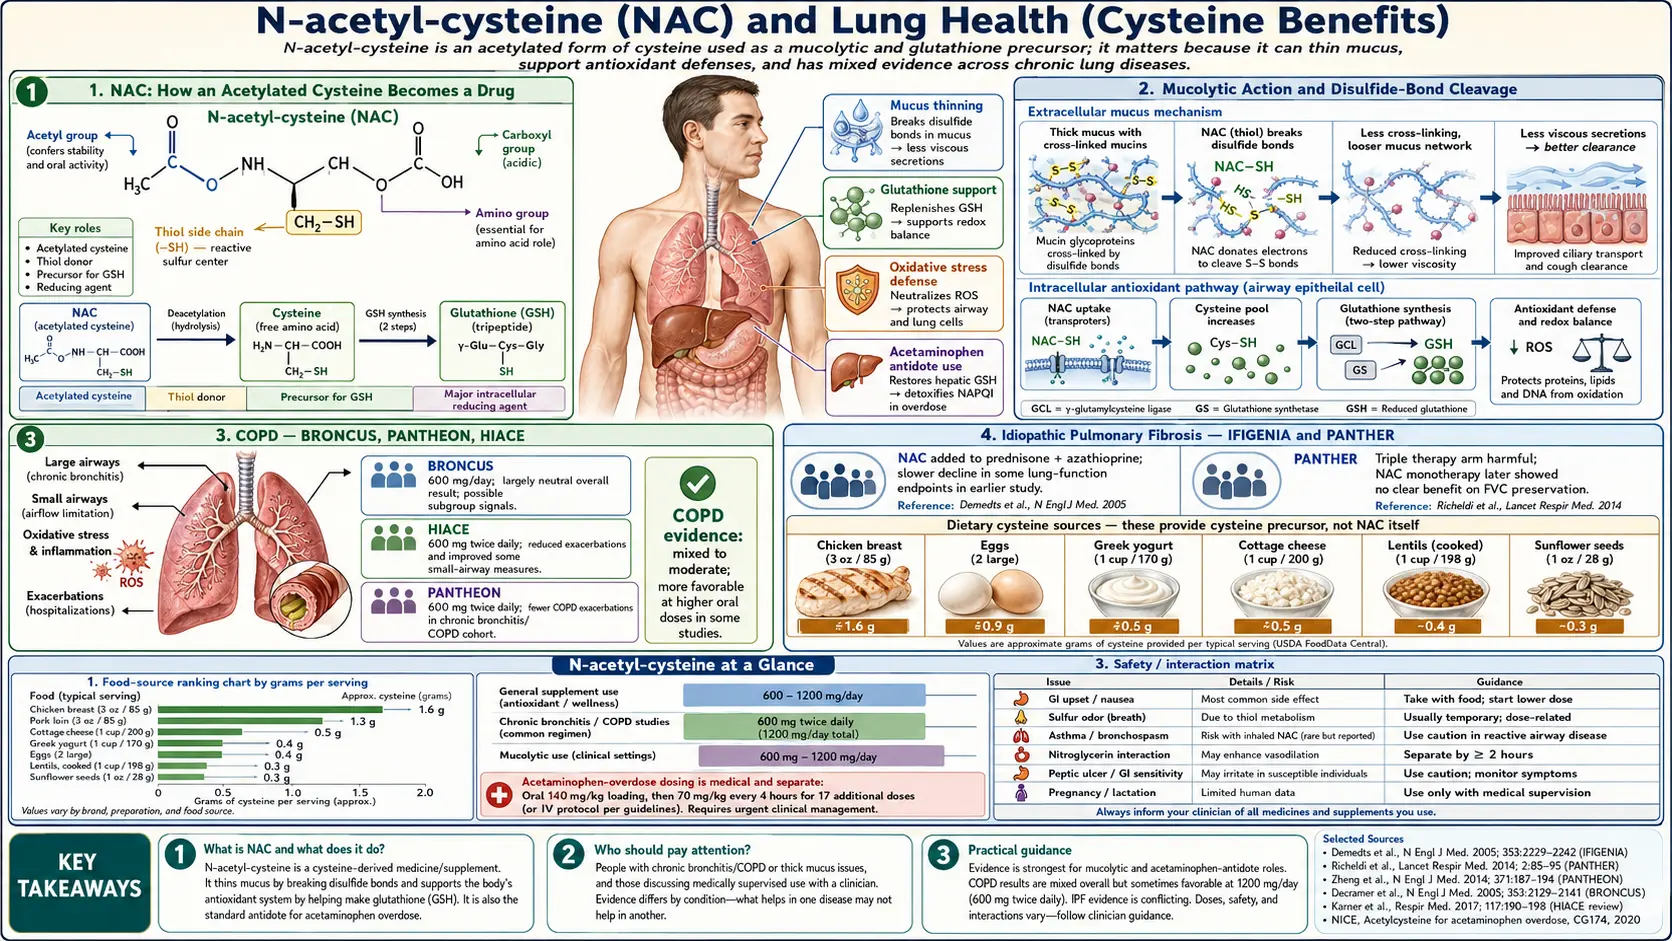
N-acetylcysteine (NAC) was first synthesized in the 1950s as an acetylated prodrug of cysteine, originally developed as a mucolytic agent — an inhaled solution that could break disulfide bonds in airway mucus and thin the secretions of patients with chronic bronchitis and cystic fibrosis. Two unexpected clinical roles followed. In the 1970s oral and intravenous (IV) N-acetylcysteine became the antidote for acetaminophen overdose, with the Rumack-Matthew nomogram (published in 1975) used to decide who needs it, regenerating hepatic glutathione before the toxic metabolite NAPQI can destroy hepatocytes — this single use case made N-acetylcysteine one of the most widely stocked drugs in emergency medicine worldwide. Then in the 2000s the IFIGENIA trial in idiopathic pulmonary fibrosis re-opened the question of whether high-dose oral N-acetylcysteine (1800 mg/day) might slow lung scarring — an early positive signal that the larger PANTHER-IPF trial then complicated by finding no benefit in monotherapy and possible harm in combination with prednisone/azathioprine. This deep-dive walks through each lung-health application of N-acetylcysteine: its mucolytic mechanism, the chronic obstructive pulmonary disease (COPD) exacerbation literature (BRONCUS, PANTHEON), the IPF saga, the acetaminophen antidote protocol, and the more speculative inhaled N-acetylcysteine and bronchiectasis evidence.
Table of Contents
- N-Acetylcysteine: How an Acetylated Cysteine Becomes a Drug
- Mucolytic Action and Disulfide-Bond Cleavage
- Chronic Obstructive Pulmonary Disease — BRONCUS, PANTHEON, HIACE
- Idiopathic Pulmonary Fibrosis — IFIGENIA, PANTHER and PRECISIONS
- Acetaminophen Overdose — Rumack-Matthew Nomogram and Antidote
- Bronchiectasis and Chronic Bronchitis
- Cystic Fibrosis
- Asthma (and the Bronchospasm Caution)
- Contrast-Induced Nephropathy
- Inhaled vs Oral N-Acetylcysteine
- Doses Reported for Lung Conditions
- Key Research Papers
- Connections
- Featured Videos
N-Acetylcysteine: How an Acetylated Cysteine Becomes a Drug
N-acetylcysteine is L-cysteine with an acetyl group (–COCH3) attached to the alpha-amino nitrogen. The molecular weight is 163 Da. The acetyl group is a simple protecting group: it prevents the free cysteine thiol from auto-oxidizing in the bottle, in the upper gastrointestinal tract, and in plasma. Without it, free cysteine has the storage stability of a wet sparkler and the oral bioavailability of a sugar cube in the rain.
Once N-acetylcysteine reaches the intracellular environment (especially hepatocytes and pulmonary epithelial cells, which express high levels of aminoacylase-1 and other deacylating enzymes), the acetyl group is cleaved to release free L-cysteine. This freed cysteine then enters the glutathione synthesis pathway in the cytosol, where it is joined to glutamate by glutamate-cysteine ligase to form gamma-glutamylcysteine, then to glycine by glutathione synthetase to complete the reduced glutathione (GSH) tripeptide. The released acetic acid is harmlessly oxidized in the citric acid cycle. The net effect of an oral N-acetylcysteine dose is therefore equivalent to delivering a pulse of cysteine to the intracellular reduced glutathione-synthesis machinery — with much better stability and absorption than swallowing the same amount of free L-cysteine.
Oral N-acetylcysteine has a complicated pharmacokinetic story. Bioavailability of an oral dose is only about 6-10%, largely because of extensive first-pass hepatic metabolism — the liver grabs and processes most of the absorbed N-acetylcysteine before it reaches systemic circulation. This sounds bad but is actually advantageous for the dominant clinical use of N-acetylcysteine, because the liver is the principal target organ. Intravenous delivery achieves much higher systemic bioavailability when systemic exposure is needed; inhaled N-acetylcysteine acts mainly in the airway, with minimal systemic absorption (see the inhaled versus oral section below). Plasma half-life of free cysteine derived from N-acetylcysteine is about 6 hours, which is why oral N-acetylcysteine dosing is typically twice or three times daily.
Beyond its prodrug-to-cysteine role, N-acetylcysteine has a second direct pharmacological effect: the free thiol on cysteine can directly cleave disulfide bonds in extracellular proteins. This is the basis of N-acetylcysteine's mucolytic action, discussed in the next section, and also of its biofilm-disrupting properties used in chronic infection work.
Mucolytic Action and Disulfide-Bond Cleavage
Airway mucus is not just goo — it is a structured gel built around two enormous glycoproteins called MUC5AC and MUC5B (mucins), which assemble into long polymeric chains held together by intermolecular disulfide bonds between cysteine residues in their C-terminal cysteine-rich domains. This disulfide-bonded mucin gel is what gives healthy airway mucus its elasticity (allowing ciliary beat to transport it) and what becomes pathologically thick and immobile in chronic bronchitis, chronic obstructive pulmonary disease, cystic fibrosis, and severe bronchiectasis.
N-acetylcysteine's free thiol group attacks these mucin disulfide bonds through a thiol-disulfide exchange reaction, breaking the cross-links between mucin polymers and reducing the viscoelasticity of the mucus gel. Thinner, less elastic mucus is more easily cleared by ciliary action and by cough. The mucolytic effect can be demonstrated in vitro within seconds of N-acetylcysteine exposure on sputum samples, and clinically within hours of oral or inhaled administration.
The original inhaled N-acetylcysteine product (a 10% or 20% solution delivered via nebulizer) was approved for this exact purpose — mucolytic adjunct for patients with thick airway secretions. It remains in clinical use, particularly in cystic fibrosis (CF) and in post-surgical patients with mucus plugging, though it has been partially displaced in CF by dornase alfa (recombinant DNase, which cleaves the extracellular DNA from dead neutrophils that accumulates in CF mucus and contributes to its viscosity by a different mechanism). The two drugs are complementary — N-acetylcysteine cleaves the mucin disulfide bonds, dornase alfa cleaves the inflammatory DNA — and both are sometimes used together.
Oral N-acetylcysteine also has mucolytic effect, presumably because the delivered cysteine raises pulmonary epithelial-lining-fluid glutathione concentration, which in turn participates in mucin disulfide-bond cycling. The clinical magnitude of the oral N-acetylcysteine mucolytic effect is smaller than direct inhalation but is still measurable as reductions in sputum viscosity, easier expectoration, and reduced cough scores in chronic bronchitis trials.
Chronic Obstructive Pulmonary Disease — BRONCUS, PANTHEON, HIACE
The clinical question in chronic obstructive pulmonary disease is whether oral N-acetylcysteine reduces exacerbation frequency — the acute symptomatic worsenings that drive hospital admissions, antibiotic use, and steroid courses, and that accelerate the underlying lung-function decline of the disease. Three randomized trials anchor the evidence, the largest with 1006 patients and the smallest with 120 patients at one hospital.
BRONCUS (Bronchitis Randomized on N-acetylcysteine Cost-Utility Study, 2005) randomized 523 European chronic obstructive pulmonary disease patients to 600 mg/day N-acetylcysteine or placebo for 3 years. Neither of its two primary outcomes differed: yearly decline in forced expiratory volume in 1 second (FEV1) was 54 mL versus 47 mL, and exacerbations per year were 1.25 versus 1.29 (hazard ratio 0.99, P=0.85). This was widely interpreted as a negative trial, and Cochrane reviews at the time concluded N-acetylcysteine had no role in chronic obstructive pulmonary disease prevention.
PANTHEON (Effect of N-acetylcysteine on chronic obstructive pulmonary disease Exacerbations in China, 2014) challenged that conclusion. PANTHEON randomized 1006 Chinese moderate-to-severe chronic obstructive pulmonary disease patients to 600 mg twice daily (i.e., 1200 mg/day, double the BRONCUS dose) or placebo for 1 year. The higher-dose group had a 22% reduction in exacerbation rate (1.16 vs 1.49 per patient-year, risk ratio 0.78, P=0.001). Its authors concluded that the drug can prevent exacerbations, "especially in disease of moderate severity", and the trial report lists a pharmaceutical company as its funder. A benefit concentrated in more severe baseline disease and more frequent prior exacerbations has been credited to this trial, but its abstract does not report that. The take-away was that 600 mg/day was likely under-dosed and 1200 mg/day was the meaningful dose for chronic obstructive pulmonary disease exacerbation prevention.
HIACE (The Effect of High Dose N-acetylcysteine on Air Trapping and Airway Resistance of Chronic Obstructive Pulmonary Disease, 2013) separately showed that 600 mg twice daily improved small-airway function (reduced air trapping on lung function testing) compared to placebo in stable chronic obstructive pulmonary disease over 1 year. In this one-hospital trial of 120 patients in Hong Kong, exacerbations were 0.96 versus 1.71 per year (P=0.019). Breathlessness score, quality-of-life score and 6-minute walking distance did not differ significantly between the groups.
A pooled analysis of 13 studies and 4155 patients (Cazzola 2015) found fewer exacerbations on N-acetylcysteine (relative risk 0.75, 95% confidence interval 0.66–0.84), an effect more apparent in people without airway obstruction. High doses were also effective in people whose chronic obstructive pulmonary disease was diagnosed by breathing test (spirometry; relative risk 0.75, 95% confidence interval 0.68–0.82). The risk of side effects did not depend on the dose. The authors state that 1200 mg or more per day is the dose when airway obstruction is documented, and that 600 mg per day seems sufficient for chronic bronchitis without it.
The current GOLD COPD guideline (Global Initiative for Chronic Obstructive Lung Disease) is described as listing N-acetylcysteine as an add-on therapy in selected patients with moderate-severe chronic obstructive pulmonary disease and a history of exacerbations, with the qualifier that benefit is most likely in patients not on inhaled corticosteroids. N-acetylcysteine's safety profile, oral availability, and low cost have made it an add-on in this patient population, particularly for patients on a budget who are still having more than one exacerbation per year despite inhaler therapy.
The mechanistic explanation for N-acetylcysteine's exacerbation-reducing effect is dual: the mucolytic effect improves baseline mucus clearance, reducing bacterial colonization and the trigger for exacerbations; and the reduced glutathione-restoring effect reduces the oxidative stress in airway epithelium that potentiates inflammatory cascade activation when an irritant (viral infection, pollution exposure) triggers an exacerbation.
Idiopathic Pulmonary Fibrosis — IFIGENIA, PANTHER and PRECISIONS
Idiopathic pulmonary fibrosis (IPF) is a progressive, lethal interstitial lung disease in which the alveolar walls fibrose and stiffen, eventually preventing gas exchange. The pathophysiology involves repeated micro-injuries to alveolar epithelium, aberrant repair with fibroblast-myofibroblast activation, and excess collagen deposition. Oxidative stress has been implicated as one of the upstream injury mechanisms, and lung glutathione concentrations in IPF patients are substantially reduced compared to controls — making N-acetylcysteine a mechanistically plausible candidate therapy.
IFIGENIA (2005) was the first large N-acetylcysteine-in-IPF trial. 182 patients were randomized (155 in the main analysis) to high-dose oral N-acetylcysteine (600 mg three times daily, 1800 mg/day) plus standard therapy (prednisone + azathioprine) versus standard therapy plus placebo. After 1 year, the N-acetylcysteine arm showed significantly less decline in vital capacity (VC) and diffusion capacity (DLCO): a difference of 0.18 liter (9%) in vital capacity and 24% in diffusion capacity. The trial was widely interpreted as positive for N-acetylcysteine, and high-dose N-acetylcysteine entered routine IPF care at many centers.
PANTHER-IPF (2012/2014) was the definitive 3-arm follow-up trial: prednisone + azathioprine + N-acetylcysteine (the IFIGENIA combination) vs N-acetylcysteine monotherapy vs placebo. The first arm (the triple combination) was stopped early in 2011 due to increased mortality and hospitalizations — the combination was actively harmful. This effectively retired prednisone + azathioprine from IPF care. The remaining two arms continued for 60 weeks, and the published results in 2014 showed no benefit of N-acetylcysteine monotherapy on lung function decline or any clinical endpoint compared to placebo: forced vital capacity fell 0.18 liters on N-acetylcysteine and 0.19 liters on placebo over 60 weeks (P=0.77).
The current IPF treatment guideline (ATS/ERS/JRS/ALAT) lists N-acetylcysteine monotherapy as a conditional against recommendation — the panel advises against routine use. The U.S. Food and Drug Administration-approved IPF drugs are pirfenidone and nintedanib, both anti-fibrotic agents that slow lung-function decline by 50% or so, and, since October 2025, nerandomilast. Some clinicians still use N-acetylcysteine as adjunct to pirfenidone or nintedanib for patients with rapidly progressive disease or significant oxidative-stress signature, but evidence is weak and the practice is not protocol-recommended.
Nerandomilast is a pill. In its phase 3 trial of 1177 patients, forced vital capacity (lung capacity) fell 114.7 ml on 18 mg twice daily, 138.6 ml on 9 mg twice daily and 183.5 ml on placebo over 52 weeks. Diarrhea was the most frequent side effect (41.3% at 18 mg, 31.1% at 9 mg, 16.0% on placebo).
There is one important caveat in the N-acetylcysteine-IPF story. A later genetic analysis of PANTHER (Oldham 2015) suggested that N-acetylcysteine might benefit patients with a specific TOLLIP rs3750920 genotype, a variant in a gene affecting Toll-like receptor signaling. For the combined outcome of death, transplant, hospitalization or a fall of 10% or more in forced vital capacity, the hazard ratio was 0.14 (95% confidence interval 0.02–0.83) with the TT genotype and 3.23 (0.79–13.16, not statistically significant) with the CC genotype. The authors reported the same pattern in an independent group of patients and asked for a genotype-based trial before any recommendation.
That trial is PRECISIONS, a phase 3 placebo-controlled study of N-acetylcysteine 600 mg three times daily for 24 months, only in people with the TT genotype, which about 25% of people with the disease carry. Its results were reported in a 2026 European Respiratory Society congress abstract: of 201 patients dosed (97 on N-acetylcysteine, 104 on placebo), the probability of remaining free of the combined outcome was 0.36 versus 0.35 (P=0.95), with no difference in patient-reported measures. N-acetylcysteine was well tolerated. A full journal report was not found as of November 2026.
Acetaminophen Overdose — Rumack-Matthew Nomogram and Antidote
Acetaminophen (paracetamol) is one of the most widely used over-the-counter analgesics. At therapeutic doses, it is metabolized in the liver primarily by sulfation and glucuronidation, with a small fraction (about 5-10%) shunted through the cytochrome P450 (mainly cytochrome P450 2E1, CYP2E1) pathway that produces a highly reactive intermediate called N-acetyl-p-benzoquinone imine (NAPQI). Hepatic glutathione rapidly conjugates NAPQI to a harmless mercapturic acid that is excreted in urine.
At an overdose — classically defined as over 7.5 g in adults or 150 mg/kg in a single ingestion, though significant toxicity can occur at lower doses with chronic dosing, malnutrition, or alcoholism — the sulfation and glucuronidation pathways saturate, more drug is shunted through CYP2E1, NAPQI production overwhelms the available hepatic glutathione, and the unconjugated NAPQI binds covalently to hepatocyte proteins, killing cells in zone 3 (centrilobular) of the liver lobule. Without treatment, this produces fulminant hepatic failure within 3-5 days, with mortality of 30-50% in untreated severe cases.
The antidote is N-acetylcysteine. The mechanism is direct cysteine repletion to the depleted hepatic glutathione synthesis pathway, plus some direct NAPQI scavenging by N-acetylcysteine's free thiol. The Rumack-Matthew nomogram, published in 1975, is the clinical decision tool: a plasma acetaminophen level drawn 4 hours after a known acute ingestion is plotted against the nomogram line, and any patient above the treatment line receives a full course of N-acetylcysteine.
The standard treatment protocols are:
- Intravenous N-acetylcysteine (Prescott protocol, used in most countries) — loading dose 150 mg/kg over 60 minutes, then 50 mg/kg over 4 hours, then 100 mg/kg over 16 hours (total 300 mg/kg over 21 hours). Modern hospital protocols increasingly use a 20-hour total infusion. This is the standard for any presentation within the first 24 hours of ingestion.
- Oral N-acetylcysteine (Smilkstein protocol, traditional US protocol) — loading dose 140 mg/kg, then 70 mg/kg every 4 hours for 17 doses (total 1330 mg/kg over 72 hours). The taste is appalling, vomiting is common, and the oral protocol has been largely displaced by intravenous.
A shorter 12-hour intravenous schedule was tested against the standard 20.25-hour one in a UK trial of 222 patients (Bateman 2014). Vomiting, retching or need for rescue anti-vomiting treatment at 2 hours occurred in 39 of 108 patients on the shorter schedule and 71 of 109 on the standard one. Severe allergy-like (anaphylactoid) reactions occurred in 5 versus 31 patients. The authors state that the trial was not powered to show the shorter schedule works as well, and that further research is needed to confirm it.
Outcomes with timely N-acetylcysteine are excellent — mortality drops to under 5% if treatment is started within 8 hours of overdose, and is still substantially improved up to 24 hours post-ingestion. N-acetylcysteine is also given (with less robust evidence but no harm) to patients presenting beyond 24 hours and to patients with chronic acetaminophen exposure complicated by liver injury.
The clinical point for general patients: oral N-acetylcysteine supplementation does not pre-protect against an acetaminophen overdose at the dose levels used for supplementation (600-1800 mg/day). The antidotal effect comes from much higher doses, given by mouth or into a vein: the oral schedule in Smilkstein 1988 starts at 140 mg/kg, and the intravenous schedule at 150 mg/kg. Taking N-acetylcysteine as a supplement does not change the acetaminophen daily limits: a U.S. over-the-counter acetaminophen label warns that severe liver damage may occur above 4,000 mg in 24 hours, and 3 g/day is a lower ceiling some references give.
Bronchiectasis and Chronic Bronchitis
Bronchiectasis is permanent dilation of the bronchi, typically caused by repeated airway infection and resulting in chronic productive cough, recurrent bacterial colonization, and progressive lung function decline. The pathophysiology overlaps significantly with chronic obstructive pulmonary disease and CF — thick, immobile mucus, neutrophilic airway inflammation, and chronic bacterial infection (often Pseudomonas aeruginosa or Haemophilus influenzae) cooperate to perpetuate the disease.
High-dose N-acetylcysteine (1200-1800 mg/day) in non-CF bronchiectasis is reported to reduce exacerbation frequency and 24-hour sputum volume and to improve quality of life on the St. George Respiratory Questionnaire. The BENE trial (Qi 2019) showed that 600 mg twice daily N-acetylcysteine over 1 year reduced exacerbations (1.31 vs 1.98 per patient-year) and sputum volume and improved quality of life in 161 Chinese bronchiectasis patients. It compared the drug with on-demand treatment, without a placebo, and its authors state that the results need checking in a larger trial. Mechanism is the same dual mucolytic + glutathione-restoring effect operating in chronic obstructive pulmonary disease.
Chronic bronchitis without bronchiectasis (the productive-cough phenotype of chronic obstructive pulmonary disease) also shows N-acetylcysteine benefit. The Decramer 2005 BRONCUS report's subgroup analysis suggested that the exacerbation rate might be reduced with N-acetylcysteine in patients not treated with inhaled corticosteroids. The Sutherland 2006 meta-analysis of N-acetylcysteine and exacerbations of chronic obstructive pulmonary disease (8 trials, 2,214 patients, published in the journal COPD) found lower odds of one or more exacerbations (odds ratio 0.49, 95% confidence interval 0.32–0.74). A dose of 400-600 mg/day is also reported to reduce exacerbations and days of disability, a statement not found in that abstract.
In practice, for non-CF bronchiectasis with chronic mucus production and frequent exacerbations, N-acetylcysteine 600 mg twice or three times daily is described as an add-on to airway clearance techniques and standard antibiotics. The drug is well-tolerated and inexpensive, and practitioners describe combining it with macrolide prophylaxis (azithromycin three days a week) and hypertonic saline nebulization with the aim of additive benefit.
Cystic Fibrosis
Cystic fibrosis is a genetic disorder caused by mutations in the CFTR chloride channel, producing thick, dehydrated airway mucus and progressive bronchiectatic lung disease. N-acetylcysteine has two distinct roles in CF care.
The traditional role is inhaled N-acetylcysteine as a mucolytic. Inhaled N-acetylcysteine has been used in CF since the 1960s and is still used in some centers, particularly for patients with thick, sticky secretions that respond poorly to dornase alfa alone. The CFTR-driven mucin abnormality in CF is one of the cleanest examples of disulfide-bond cross-linking pathology in airway disease.
The newer role is oral high-dose N-acetylcysteine for systemic antioxidant restoration. CF patients have significantly lower whole-body glutathione due to chronic neutrophilic airway inflammation, repeated antibiotic courses, and CFTR's underappreciated role as a glutathione transporter (CFTR moves glutathione from the cytosol to the airway lumen, and loss of CFTR function reduces airway-surface glutathione). Trials of high-dose oral N-acetylcysteine in CF have looked at lung function and sputum inflammation, with different results. A 4-week phase 1 study (Tirouvanziam 2006; 0.6 to 1.0 g three times daily) reported lower sputum elastase activity and fewer airway neutrophils, without improved lung function, as expected over so short a time. A 24-week phase 2 trial of 70 people (Conrad 2015) found the reverse: lung function held while it fell on placebo (FEV1 difference 150 mL, P<0.02), with no effect on sputum elastase or other selected markers of neutrophil inflammation. No current CF guideline mandates routine oral N-acetylcysteine.
With the advent of CFTR modulators (ivacaftor, lumacaftor-ivacaftor, elexacaftor-tezacaftor-ivacaftor) that partially restore CFTR function, the clinical landscape of CF has changed dramatically. Modern modulator-treated CF patients have much milder lung disease than their pre-modulator predecessors. The role of N-acetylcysteine in modulator-era CF is being reassessed; it remains useful as adjunct mucolytic therapy and may have residual antioxidant benefit, but it is no longer a centerpiece of CF care.
Asthma (and the Bronchospasm Caution)
N-acetylcysteine's role in asthma is more nuanced. Oral N-acetylcysteine is generally well tolerated in asthmatic patients and may have small antioxidant benefits, but the evidence for clinical benefit in asthma control is weak compared to chronic obstructive pulmonary disease or bronchiectasis. The dominant treatments in asthma are inhaled corticosteroids and bronchodilators, and N-acetylcysteine is not a substitute.
The important caution is with nebulized (inhaled) N-acetylcysteine. Direct delivery of N-acetylcysteine to the airway can trigger paradoxical bronchospasm in some asthmatic patients, presumably through direct irritation of hyperreactive airway epithelium. The bronchospasm can be severe. Standard practice when nebulizing N-acetylcysteine in any patient with asthmatic phenotype is to co-administer a short-acting beta-agonist (albuterol) immediately before the N-acetylcysteine nebulization. Oral N-acetylcysteine does not carry this risk.
The other historical concern was that N-acetylcysteine, by reducing airway mucus, might worsen asthma by removing protective mucus that traps inhaled allergens. This concern has not been borne out in clinical trials of oral N-acetylcysteine.
Contrast-Induced Nephropathy
For two decades, oral and intravenous N-acetylcysteine was widely used as prophylaxis against contrast-induced acute kidney injury in patients undergoing computed tomography (CT) scans and coronary angiography with iodinated contrast. The Tepel 2000 trial and several subsequent small trials suggested that N-acetylcysteine 600 mg twice daily on the day before and the day of contrast administration reduced the rise in serum creatinine after the procedure. The proposed mechanism was free-radical scavenging in the renal medulla, where contrast-induced osmotic stress generates ischemia and reactive oxygen species.
The PRESERVE trial (2018), a 2-by-2 factorial randomized trial of 5177 high-risk patients (4993 in the main analysis) at sites in the United States, Australia, Malaysia and New Zealand, compared intravenous bicarbonate with saline and, separately, oral N-acetylcysteine with placebo. It found no benefit of N-acetylcysteine for contrast nephropathy prevention: the primary end point (death, dialysis or a lasting rise in creatinine at 90 days) occurred in 4.6% on N-acetylcysteine and 4.5% on placebo (odds ratio 1.02). This effectively retired N-acetylcysteine from the contrast-nephropathy prophylaxis indication in most US institutions. Some interventional cardiology and interventional radiology practices still use the protocol because it is harmless and inexpensive, but it is no longer guideline-recommended. The active intervention that does work is volume expansion with isotonic saline before and after contrast administration.
Mentioning this here because it is a useful illustration of the broader truth about N-acetylcysteine research: small early trials sometimes show effects that do not replicate in larger trials, and the literature on N-acetylcysteine is full of both confirmed wins (acetaminophen overdose, chronic obstructive pulmonary disease exacerbations) and confirmed failures (contrast nephropathy, IPF monotherapy). In this literature, large multi-center trials have more than once overturned the results of small early-phase ones.
Inhaled vs Oral N-Acetylcysteine
Inhaled (nebulized) N-acetylcysteine delivers the active drug directly to the airway, achieving high local concentrations for mucolytic action with minimal systemic absorption. Typical regimen is 3-5 mL of 10% solution nebulized 2-4 times daily, often combined with albuterol to prevent bronchospasm. The smell is sulfur-like and unpleasant for patients and their families.
Oral N-acetylcysteine achieves much lower local airway concentrations but provides systemic glutathione restoration that the inhaled route does not. For chronic management of chronic obstructive pulmonary disease, bronchiectasis, and chronic bronchitis, oral N-acetylcysteine is the standard approach. Inhaled N-acetylcysteine is reserved for acute mucus plugging, cystic fibrosis, and specific surgical contexts (e.g., post-thoracotomy retained secretions).
Some integrative-medicine clinics offer nebulized glutathione (rather than nebulized N-acetylcysteine) for various pulmonary indications including asthma, chronic obstructive pulmonary disease, and chronic sinusitis. Evidence is weaker than for N-acetylcysteine, but the underlying logic (direct epithelial glutathione delivery) is similar. Glutathione is more expensive per dose than N-acetylcysteine and is generally not covered by insurance.
Doses Reported for Lung Conditions
- Chronic obstructive pulmonary disease exacerbation prevention — 600 mg twice daily (1200 mg/day total), the dose tested in PANTHEON and HIACE.
- Chronic bronchitis — 600 mg once or twice daily is the amount described; Cazzola 2015 states 600 mg per day without airway obstruction and 1200 mg or more with it.
- Bronchiectasis — 600 mg twice or three times daily (1200-1800 mg/day) is the amount described; the BENE trial tested 600 mg twice daily.
- Cystic fibrosis (adjunct) — 600-1800 mg/day oral plus nebulized 10% N-acetylcysteine as needed is the amount described; the phase 1 study above used 0.6 to 1.0 g three times daily.
- IPF — the guideline panel advises against routine use after PANTHER; some clinicians are reported to still use 600 mg three times daily as adjunct, the dose tested in PRECISIONS.
- Acetaminophen overdose — intravenous under emergency protocol (150 mg/kg loading), a hospital treatment rather than a home one.
- General respiratory antioxidant support — 600 mg once daily is the amount described for this use.
Practitioners describe taking oral N-acetylcysteine on an empty stomach, with vitamin C (which helps maintain cysteine in its reduced active form) and a B-complex for transsulfuration pathway support. Side effects are typically limited to mild gastrointestinal (GI) discomfort, sulfur-tinged taste/burp, and rare rash. Nitroglycerin and anticoagulants (blood thinners) are the two drug groups raised as concerns with N-acetylcysteine. In a trial of severe unstable angina, intravenous N-acetylcysteine (5 g every 6 hours) given with intravenous nitroglycerin was followed by symptomatic low blood pressure in 7 of 24 patients, against 0 of 22 on nitroglycerin alone (Horowitz 1988); that is a far higher dose than oral supplements. No measured figure for oral doses with anticoagulants was found for this page.
Key Research Papers
- Decramer M et al. (2005). Effects of N-acetylcysteine on outcomes in chronic obstructive pulmonary disease (Bronchitis Randomized on NAC Cost-Utility Study, BRONCUS): a randomised placebo-controlled trial. The Lancet. — PubMed PMID: 15866309
- Zheng JP et al. (2014). Twice daily N-acetylcysteine 600 mg for exacerbations of chronic obstructive pulmonary disease (PANTHEON): a randomised, double-blind placebo-controlled trial. Lancet Respiratory Medicine. — PubMed PMID: 24621680
- Tse HN et al. (2013). High-dose N-acetylcysteine in stable COPD: the 1-year, double-blind, randomized, placebo-controlled HIACE study. Chest. — PubMed PMID: 23348146
- Demedts M et al. (2005). High-dose acetylcysteine in idiopathic pulmonary fibrosis (IFIGENIA). NEJM. — PubMed PMID: 16306520
- Idiopathic Pulmonary Fibrosis Clinical Research Network (2014). Randomized trial of acetylcysteine in idiopathic pulmonary fibrosis (PANTHER-IPF). NEJM. — PubMed PMID: 24836309
- Rumack BH, Matthew H (1975). Acetaminophen poisoning and toxicity. Pediatrics. — PubMed PMID: 1134886
- Prescott LF et al. (1979). Intravenous N-acetylcystine: the treatment of choice for paracetamol poisoning. BMJ. — PubMed PMID: 519312
- Smilkstein MJ et al. (1988). Efficacy of oral N-acetylcysteine in the treatment of acetaminophen overdose. NEJM. — PubMed PMID: 3059186
- Qi Q, Ailiyaer Y, Liu R et al. (2019). Effect of N-acetylcysteine on exacerbations of bronchiectasis (BENE): a randomized controlled trial. Respiratory Research. — PubMed PMID: 30975143
- Sutherland ER, Crapo JD, Bowler RP (2006). N-acetylcysteine and exacerbations of chronic obstructive pulmonary disease. COPD. — PubMed PMID: 17361500
- PRESERVE Investigators (2018). Outcomes after angiography with sodium bicarbonate and acetylcysteine. NEJM. — PubMed PMID: 29130810
- Tepel M et al. (2000). Prevention of radiographic-contrast-agent-induced reductions in renal function by acetylcysteine. NEJM. — PubMed PMID: 10900277
- Cazzola M, Calzetta L, Page C, Jardim J et al. (2015). Influence of N-acetylcysteine on chronic bronchitis or COPD exacerbations: a meta-analysis. European Respiratory Review. — PubMed PMID: 26324807
- Oldham JM et al. (2015). TOLLIP, MUC5B, and the response to N-acetylcysteine among individuals with idiopathic pulmonary fibrosis. American Journal of Respiratory and Critical Care Medicine. — PubMed PMID: 26331942
- Podolanczuk AJ et al. (2022). Design and rationale for the prospective treatment efficacy in IPF using genotype for NAC selection (PRECISIONS) clinical trial. BMC Pulmonary Medicine. — PubMed PMID: 36514019
- Noth I et al. (2026). RCT Abstract - A pharmacogenetic trial of N-acetyl-cysteine in idiopathic pulmonary fibrosis. European Respiratory Society congress abstract PA5247. — doi:10.1183/13993003.congress-2026.pa5247
- Richeldi L et al. (2025). Nerandomilast in patients with idiopathic pulmonary fibrosis. New England Journal of Medicine. — PubMed PMID: 40387033
- Bateman DN et al. (2014). Reduction of adverse effects from intravenous acetylcysteine treatment for paracetamol poisoning: a randomised controlled trial. The Lancet. — PubMed PMID: 24290406
- Tirouvanziam R et al. (2006). High-dose oral N-acetylcysteine, a glutathione prodrug, modulates inflammation in cystic fibrosis. Proceedings of the National Academy of Sciences of the USA. — PubMed PMID: 16537378
- Conrad C et al. (2015). Long-term treatment with oral N-acetylcysteine: affects lung function but not sputum inflammation in cystic fibrosis subjects. A phase II randomized placebo-controlled trial. Journal of Cystic Fibrosis. — PubMed PMID: 25228446
- Horowitz JD et al. (1988). Combined use of nitroglycerin and N-acetylcysteine in the management of unstable angina pectoris. Circulation. — PubMed PMID: 3127076
PubMed Topic Searches
Connections
- All Amino Acids
- N-Acetylcysteine and Kidney Health — the renal half of the N-acetylcysteine evidence base — contrast-induced nephropathy from Tepel 2000 through the PRESERVE and ACT trials, chronic kidney disease, hemodialysis, and cystine stone prevention.
- N-Acetylcysteine and Glutathione Precursors — N-acetylcysteine as a glutathione-raising supplement rather than an organ therapy — the hepatocyte synthesis pathway, the psychiatric and polycystic ovary syndrome (PCOS) trials, dosing, and the glycine and selenium cofactors.
- Cysteine Overview
- Cysteine Benefits Hub
- Cysteine for Glutathione Synthesis
- Cysteine for Hair and Nails
- Cysteine for Detoxification
- N-Acetylcysteine
- N-Acetylcysteine and Respiratory Health
- N-Acetylcysteine and Glutathione
- Chronic Obstructive Pulmonary Disease
- Pulmonary Fibrosis
- ARDS
- Pneumonia
- Bronchitis
- All Pulmonology
- Acetaminophen Toxicity
- Acetaminophen Toxin Profile
- Glycine
- Vitamin C
- History
- Sources