⚠ Evidence warning: Clinical trials or other evidence do not support the claim that N-acetylcysteine and dimercaptosuccinic acid enhance urinary mercury excretion in rats. This page keeps it as a report of what people, websites or other media say.
Cysteine for Detoxification
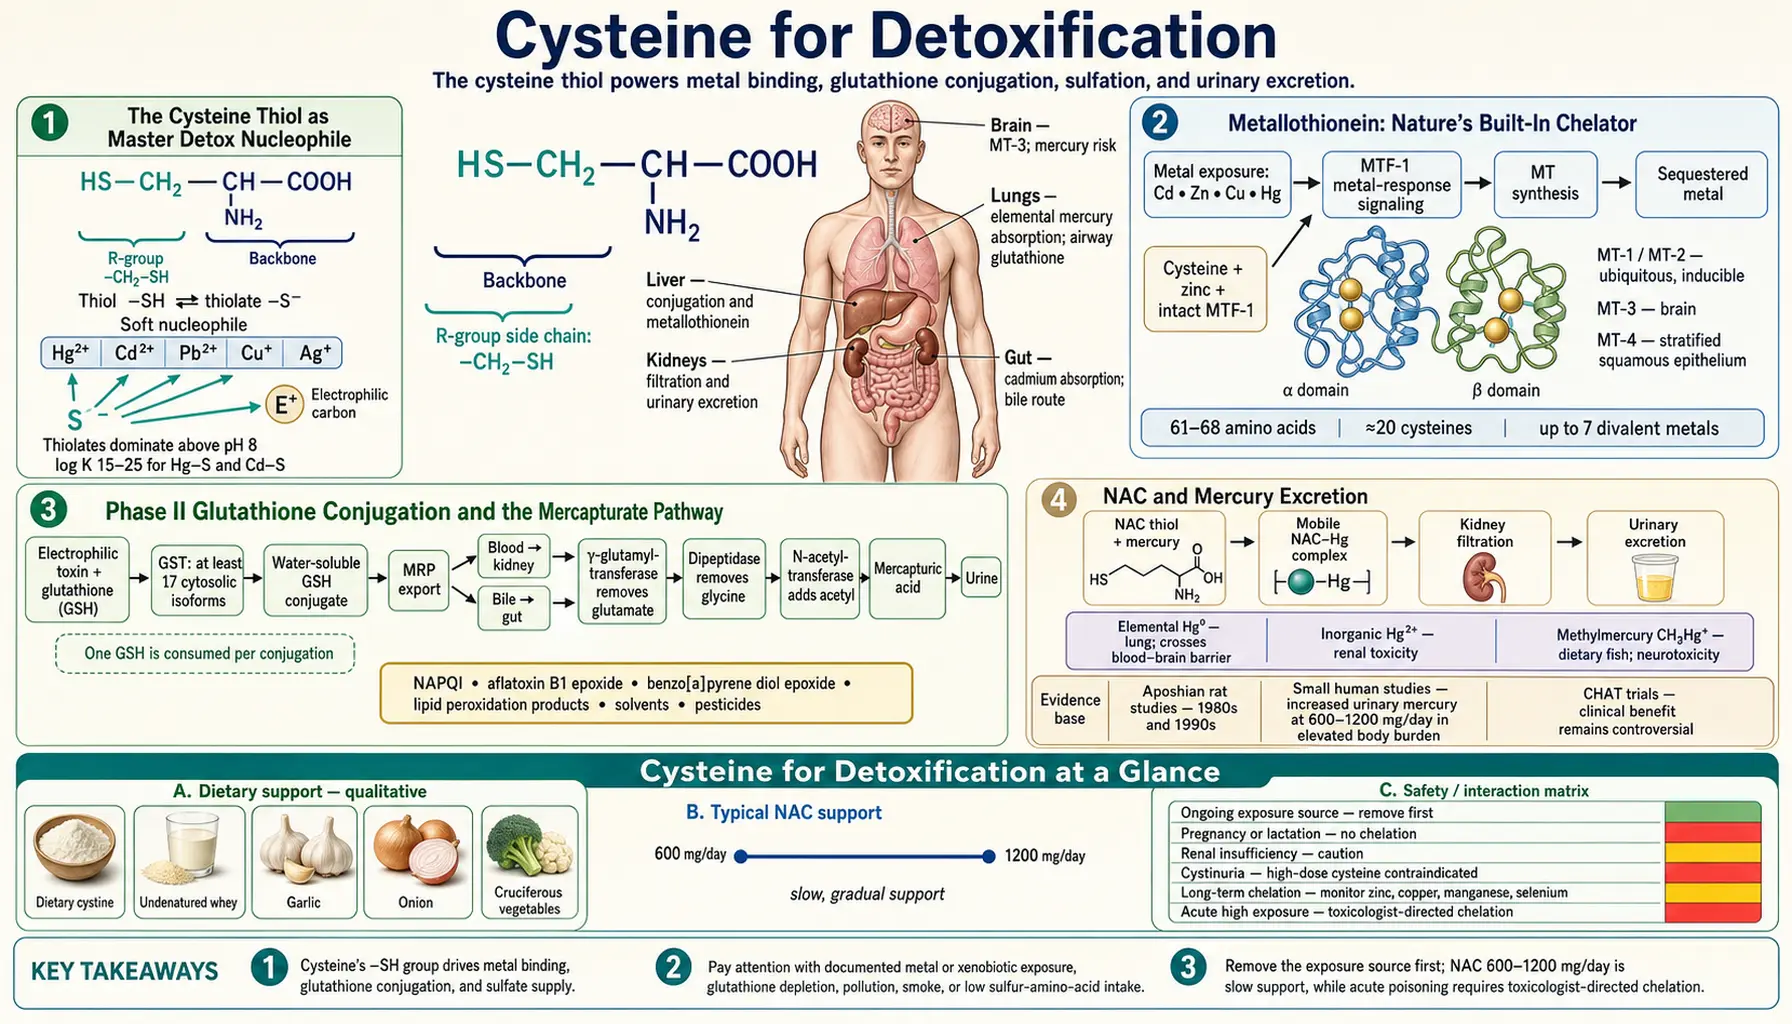
The cysteine thiol (–SH) is the single most important nucleophilic group in human detoxification biochemistry. It is the chelating group on metallothionein, the small cysteine-rich protein that binds and sequesters cadmium, mercury, copper, and zinc with affinities approaching those of dedicated chelation drugs. It is the conjugating group on glutathione, the master Phase II detoxification cofactor that the glutathione-S-transferase (GST) family of enzymes attaches to lipophilic toxins to convert them into water-soluble mercapturic acids for urinary excretion. It is the binding group on the cysteine residues of N-acetylcysteine (NAC) itself when N-acetylcysteine is used clinically as a soft chelator of methylmercury and other organomercurials. This deep-dive walks through each detoxification mechanism in turn — metallothionein and heavy-metal binding, glutathione conjugation and the mercapturate pathway, N-acetylcysteine chelation evidence in mercury and lead exposure, the Andy Cutler chelation protocol controversy, and the practical question of when sulfur-amino-acid supplementation actually helps a real-world detoxification effort versus when it is functioning as biochemical theater.
Table of Contents
- The Cysteine Thiol as Master Detox Nucleophile
- Metallothionein: Nature's Built-In Chelator
- Phase II Glutathione Conjugation and the Mercapturate Pathway
- N-Acetylcysteine and Mercury Excretion
- N-Acetylcysteine and Lead, Cadmium, Arsenic
- The Andy Cutler Protocol Controversy
- DMSA, DMPS, and How N-Acetylcysteine Compares to Drug Chelators
- The Sulfation Pathway (PAPS, Sulfotransferases)
- Pesticides, Solvents, and Cigarette Smoke
- When Cysteine Supplementation Actually Helps
- Cautions in Heavy Metal Chelation
- Key Research Papers
- Connections
- Featured Videos
The Cysteine Thiol as Master Detox Nucleophile
The sulfhydryl group (–SH) on cysteine is unique among the amino acid side chains. It is the only side chain with a free thiol — the only one whose terminal atom is a soft, polarizable, highly nucleophilic sulfur. This single chemical feature is responsible for nearly all of cysteine's detoxification roles, because soft-metal cations (Cd2+, Hg2+, Pb2+, Cu+, Ag+) and electrophilic carbon centers (epoxides, acyl halides, alpha-beta-unsaturated carbonyls from oxidized lipids) preferentially bond to soft, polarizable nucleophiles — and the cysteine thiol is the softest, most polarizable nucleophile a typical cell has available.
In the language of hard-soft acid-base (HSAB) chemistry, the cysteine thiolate (the deprotonated –S− form, which dominates above pH 8 and is present in equilibrium at neutral pH) is a quintessentially soft base. Heavy metals like mercury and lead are quintessentially soft acids. The combination produces extremely strong, kinetically fast bond formation with binding constants (log K) in the range of 15-25 for Hg-S and Cd-S complexes — comparable to the binding strength of dedicated synthetic chelators like EDTA for "hard" metals or DMSA / DMPS for "soft" metals (both DMSA and DMPS are themselves thiol-based, deliberately mimicking the cysteine thiol chemistry).
This is why every detoxification scheme in the body ultimately routes through cysteine in some form. Metallothionein wraps soft metals in a cysteine-thiolate cage. Glutathione conjugates electrophilic xenobiotics through its cysteine thiol. The sulfotransferases load the sulfate group (derived from cysteine catabolism) onto hydroxylated metabolites for excretion. N-acetylcysteine, free cysteine, and dietary cystine all feed this single chemistry. There is no separate detox pathway that does not involve cysteine sulfur somewhere upstream — the human body has consolidated all its soft-metal and soft-electrophile detox functions through this one amino acid.
Metallothionein: Nature's Built-In Chelator
Metallothionein (MT) is a remarkable small protein — only 61-68 amino acids long, with approximately 20 of those residues being cysteine. The cysteines are arranged in two domains (alpha and beta) that fold around metal ions and bind them through their thiolate side chains. A single MT molecule binds up to 7 divalent metal ions (typically zinc and copper at physiological baseline, with the binding sites converting to cadmium and mercury upon exposure).
There are four major isoforms of metallothionein in humans (MT-1, MT-2, MT-3, MT-4). MT-1 and MT-2 are ubiquitously expressed and inducible — their gene expression is upregulated by glucocorticoids, inflammatory cytokines, and most importantly by direct exposure to the metals they bind (cadmium, zinc, copper, and mercury all act as transcription factors via the MTF-1 metal-response element binding pathway). MT-3 is brain-specific and has additional growth-inhibitory functions. MT-4 is found in stratified squamous epithelium.
The functional role of MT in detoxification is to sequester reactive metals away from the active sites of enzymes they would otherwise poison. When the gut absorbs cadmium (e.g., from cigarette smoke or contaminated shellfish), the enterocyte and then the hepatocyte induce MT expression, and the absorbed cadmium binds to newly-synthesized MT inside cells, preventing it from reaching mitochondria, kidney tubule cells, or testicular tissue where it would do damage. Similarly, methylmercury absorbed from dietary fish is partially detoxified by MT binding in liver and kidney before it would otherwise reach the brain.
The clinical implications follow directly from this mechanism. MT synthesis requires three things: adequate cysteine substrate, adequate zinc (which functions as a chronic inducer of MT transcription via the MTF-1 pathway), and intact MTF-1 transcription factor signaling. Marginal cysteine status or marginal zinc status will limit the body's ability to mount an MT response to a new metal exposure. This is one reason why patients with histories of chronic heavy metal exposure (occupational or dietary) frequently benefit from co-supplementation of N-acetylcysteine + zinc rather than either nutrient alone — the combination maximizes both the inducer (zinc) and the structural substrate (cysteine) for MT synthesis.
Phase II Glutathione Conjugation and the Mercapturate Pathway
The other major detoxification role of cysteine is as the functional component of glutathione participating in Phase II detoxification. The glutathione-S-transferase (GST) enzyme superfamily — humans express at least 17 cytosolic GST isoforms encoded by separate genes — catalyzes the conjugation of glutathione's thiol to a wide range of electrophilic xenobiotics.
Important substrates of GST conjugation include:
- NAPQI (the toxic acetaminophen metabolite that destroys hepatocytes in acetaminophen overdose)
- Aflatoxin B1 epoxide (the carcinogenic metabolite of the moldy-peanut toxin)
- Benzo[a]pyrene diol epoxide (the ultimate carcinogen from charred meat and cigarette smoke)
- Lipid peroxidation products (4-hydroxynonenal, malondialdehyde) generated under oxidative stress
- Ethacrynic acid, cisplatin, and many chemotherapy agents
- Industrial solvents like dichloromethane, chloroform, and styrene oxide
- Pesticide residues including organophosphates and many herbicides
The conjugation reaction attaches glutathione's cysteine sulfur to the electrophilic carbon of the toxin, producing a much less reactive water-soluble glutathione conjugate. The conjugate is exported from the cell by the MRP (multidrug resistance protein) transporters, travels via blood to the kidney or via bile to the gut, and undergoes a stepwise enzymatic processing called the mercapturate pathway: gamma-glutamyltransferase removes the glutamate, dipeptidase removes the glycine, and N-acetyltransferase adds an acetyl group to the now-free cysteine, producing the final mercapturic acid (N-acetyl-S-conjugate of cysteine) that is excreted in urine.
Each round of Phase II glutathione conjugation thus consumes one glutathione molecule (which is then catabolized to the mercapturate). High xenobiotic exposure depletes cellular glutathione if cysteine supply for resynthesis is inadequate. This is the mechanism behind acetaminophen overdose — the dose simply outruns the hepatic glutathione synthesis capacity, NAPQI accumulates unconjugated, and binds to hepatocyte proteins instead. N-acetylcysteine repletes the cysteine substrate and restores glutathione synthesis fast enough to prevent the catastrophe.
The clinical translation outside of acute overdose is that anyone with chronic high xenobiotic load — smokers, workers in industrial chemical environments, patients on long-term polypharmacy, patients with significant air-pollution exposure, and patients with chronic infections producing endogenous oxidative load — benefits from maintained high cysteine/reduced glutathione (GSH) status. The standard supplemental approach is N-acetylcysteine 600-1200 mg/day plus the GlyNAC glycine co-supplementation discussed on the Glutathione Synthesis page.
Measurement of urinary mercapturic acids is sometimes used as a research-grade exposure biomarker for specific industrial chemicals (e.g., benzene exposure produces measurable urinary S-phenylmercapturic acid). This is rarely clinically useful in general practice.
N-Acetylcysteine and Mercury Excretion
Mercury is the most toxicologically complex of the common heavy-metal exposures because it exists in three chemically distinct forms with different absorption, distribution, and excretion kinetics: elemental mercury vapor (Hg0, the dental-amalgam and thermometer form, primarily absorbed via lung and crossing the blood-brain barrier), inorganic mercury salts (Hg2+, the older industrial-process form, primarily renal toxicity), and organic methylmercury (CH3Hg+, the dietary-fish form, very lipophilic with strong blood-brain barrier penetration and neurotoxicity). All three forms ultimately bind to the cysteine thiol of various proteins, including critical enzymes and structural elements, producing their toxic effects.
N-acetylcysteine has been studied as a soft chelator for mercury for several decades. The principle is that N-acetylcysteine's cysteine thiol competes with endogenous protein thiols for mercury binding — once mercury is bound to the small, mobile N-acetylcysteine molecule (or to the cysteine derived from N-acetylcysteine, or to glutathione conjugates), the complex can be filtered by the kidney and excreted in urine. This is the reasoning behind its use by integrative practitioners as a mercury “soft chelator”. In rat studies, N-acetylcysteine and dimercaptosuccinic acid (DMSA) both significantly enhanced urinary mercury excretion in metal-exposed animals. Research on chelation in autism is controversial — most reviews have not shown clinical benefit even where mercury elimination is increased.
The setting in which practitioners use N-acetylcysteine for mercury is the person with a known elevated body burden who wants to reduce it slowly, over months to years, with a gentle, oral, well-tolerated agent that is sold without prescription; the doses they describe are 600-1200 mg/day, taken long-term. Practitioners regard the slow pace as an advantage — aggressive chelation with DMSA or DMPS can mobilize tissue mercury faster than the kidney can excrete it, transiently redistributing mercury to brain and producing acute neurological symptoms (the so-called "Hg dump" or "redistribution" phenomenon), and they describe N-acetylcysteine's gentler action as avoiding this.
Mainstream toxicology medicine does not endorse routine "mercury detox" in asymptomatic patients with mildly elevated body burden, because the clinical significance of low-grade chronic mercury exposure is uncertain and randomized intervention trials of mercury removal have not generally shown clear functional benefit. The integrative-medicine community is more willing to act on suggestive evidence of harm at lower exposure levels. Practitioners there argue that N-acetylcysteine at 600-1200 mg/day has a wide enough safety margin, and a plausible enough mechanism, that its use as an ongoing low-grade mercury-detoxification adjunct does not need strong proof.
N-Acetylcysteine and Lead, Cadmium, Arsenic
For lead, the standard chelators are EDTA (calcium disodium EDTA for adults; DMSA for children) and DMSA. N-acetylcysteine's contribution to lead detoxification is more indirect than for mercury — the major mechanism is glutathione restoration in lead-exposed tissues (which protects against oxidative damage from lead) rather than direct lead chelation. Several studies have shown that N-acetylcysteine reduces lead-induced oxidative biomarkers and improves antioxidant enzyme function in lead-exposed subjects, though urinary lead excretion increases are modest compared to DMSA.
For cadmium, the toxic burden of cigarette smoke and certain seafoods (especially aged shellfish and bottom-feeding fish), N-acetylcysteine has been shown to enhance metallothionein induction (the body's primary cadmium-sequestering protein) and to support hepatic detoxification of cadmium. Cadmium has an extraordinarily long biological half-life in human kidney (10-30 years) and cannot be acutely chelated effectively — the approach described is to reduce ongoing exposure (smoking, shellfish from contaminated waters) while the body gradually sequesters stored cadmium in inert metallothionein complexes. Practitioners combine N-acetylcysteine with zinc for this purpose.
For arsenic, the standard chelator is DMSA (which works well for inorganic arsenic, the form found in groundwater and some industrial settings). N-acetylcysteine plays a supporting role by maintaining glutathione status for the methylation-mediated arsenic detoxification pathway, in which arsenic is sequentially methylated to monomethylarsonic acid (MMA) and dimethylarsinic acid (DMA), both of which are less toxic than inorganic arsenic and are excreted in urine. The methylation pathway is glutathione-dependent and is supported by N-acetylcysteine, methionine, B12, folate, and S-adenosylmethionine (SAMe).
The Andy Cutler Protocol Controversy
Andrew Cutler (1957-2017) was an MIT-trained chemist who, after personal mercury toxicity from dental amalgam removal, developed and popularized a chelation protocol using frequent low-dose oral DMSA and alpha-lipoic acid (ALA) along with adjunct nutrients including N-acetylcysteine, vitamin C, vitamin E, magnesium, and zinc. The protocol is built around the half-life arithmetic of the chelators — dosing every 3-4 hours during waking hours (and sometimes overnight) for 3-4 days, then a 3-4 day rest period — with the rationale of maintaining steady chelator blood levels to avoid the redistribution phenomenon.
The Cutler protocol attracted a large following in the integrative-medicine and "mercury-toxic" patient communities, with the books "Amalgam Illness" and "Hair Test Interpretation" being widely circulated. The protocol's N-acetylcysteine role is supportive: maintenance of glutathione status during chelation, support of methylation-pathway function, and possibly some direct mercury binding.
The mainstream-medicine response has been mostly skeptical to critical. Concerns include: (1) the absence of randomized controlled trials demonstrating clinical benefit; (2) the very small evidence base supporting the half-life-based dosing rationale specifically; (3) the financial incentives of practitioners selling the protocol and the chelator supplements; (4) the safety concerns of multi-month chelation in patients without confirmed clinical heavy-metal toxicity; (5) the use of provoked urine challenge testing (which is not a validated diagnostic for body-burden mercury and produces clinically misleading results when interpreted as if it were a passive excretion measurement).
In mainstream practice, people with documented occupational or accidental heavy-metal poisoning that produces symptoms are treated by clinical toxicologists using validated chelation protocols (typically DMSA or DMPS, dosed and monitored according to standard protocols). For vague chronic symptoms attributed to low-level mercury exposure, the diagnostic uncertainty is real, the chelation risks are non-trivial, and the protocol burden is significant. Practitioners who prefer a gentler route use N-acetylcysteine alone, at 600-1200 mg/day, sometimes with zinc, as an ongoing low-intensity approach that does not involve the provocation-and-chelation cycles of the Cutler approach.
DMSA, DMPS, and How N-Acetylcysteine Compares to Drug Chelators
The three drug chelators most commonly used for heavy metal detoxification are dimercaptosuccinic acid (DMSA, also called succimer; oral, U.S. Food and Drug Administration-approved for pediatric lead poisoning, used off-label for mercury), dimercaptopropane sulfonate (DMPS, available in oral and intravenous (IV) forms, more popular in Europe than the US), and calcium disodium ethylenediaminetetraacetate (CaEDTA, intravenous, the standard for acute lead poisoning). All three are stronger and faster chelators than N-acetylcysteine, with measurable urinary metal excretion within hours of administration.
The key chemical similarity: DMSA and DMPS both have two adjacent thiol groups (the "dimercapto" in their name), which form much more stable bidentate complexes with soft metal ions than the single thiol of cysteine or N-acetylcysteine. This is why DMSA and DMPS are more potent — they chemically grip metal ions with two hands rather than one. The structural similarity to the cysteine thiol is what makes them work; they were intentionally designed as bidentate mimetics of the cysteine chelation chemistry.
The trade-offs are familiar. The stronger chelators produce faster mobilization of metal stores, which is desirable in acute high-exposure poisoning but produces redistribution risk in chronic low-exposure detoxification. DMSA and DMPS also chelate essential minerals (zinc, copper, selenium) along with the toxic metals, requiring careful replacement nutrition during use. They produce odorous breath and urine (the sulfur smell). They require physician oversight, lab monitoring, and a defined treatment course.
N-acetylcysteine's comparative advantage is gentleness, oral availability without prescription, well-tolerated long-term use, and the broader range of supportive detoxification effects beyond direct chelation (glutathione synthesis, sulfation pathway support, mercapturate-pathway substrate). N-acetylcysteine's comparative disadvantage is speed and potency — it cannot acutely strip a body burden the way DMSA can in 1-2 months of cycling.
How the two approaches are used in practice: for high-dose recent exposure with symptoms, toxicology practice uses DMSA, DMPS or CaEDTA under a toxicologist's care. For a mild to moderate chronic body burden in a stable person who wants slow reduction without medical supervision, practitioners use N-acetylcysteine 600-1200 mg/day long-term, often with zinc, selenium and general antioxidant support. For ongoing exposure with symptoms, both traditions put identifying and removing the source first, before chelation.
The Sulfation Pathway (PAPS, Sulfotransferases)
Beyond direct chelation and glutathione conjugation, cysteine contributes to detoxification through the sulfation pathway. Cysteine catabolism produces inorganic sulfate (SO42−) via the enzymes cysteine dioxygenase and sulfite oxidase. This sulfate is then activated by the enzyme PAPS synthase to form 3'-phosphoadenosine-5'-phosphosulfate (PAPS), the universal high-energy sulfate donor used by all sulfotransferase enzymes.
Sulfotransferases (SULTs) are a large enzyme family that transfer sulfate onto hydroxyl groups of substrates. Their substrates include:
- Hormones — estrogens, androgens, thyroid hormones, and bile acids are all sulfated to inactive forms for excretion.
- Neurotransmitters — dopamine, serotonin, and their metabolites are sulfated as part of clearance.
- Drugs — acetaminophen, isoproterenol, minoxidil, and many other drugs are partly cleared by sulfation.
- Phenolic dietary compounds — many polyphenols (resveratrol, quercetin, catechins) are conjugated to sulfate metabolites in the liver before circulation.
- Endogenous metabolites — bile acid sulfation, dehydroepiandrosterone sulfate (DHEAS, the most abundant circulating steroid), and many others.
When cysteine is in short supply, sulfate availability for PAPS synthesis is reduced and the entire sulfation arm of Phase II detoxification slows. The clinical manifestation is sometimes called "sulfation insufficiency" — patients (often described in the autism-biomedical and chronic-Lyme communities) with low plasma sulfate, elevated unsulfated/sulfated metabolite ratios, and intolerance of acetaminophen, salicylates, phenolic foods, and other sulfation-demanding substrates.
Sulfation can be supported by ensuring adequate cysteine intake (N-acetylcysteine, dietary cystine, undenatured whey, sulfur-rich foods like garlic/onion/cruciferous vegetables), molybdenum cofactor adequacy (sulfite oxidase is molybdenum-dependent — see Molybdenum and Detoxification), and direct sulfate availability (Epsom salt baths providing magnesium sulfate through transdermal absorption, sodium sulfate or magnesium sulfate oral supplementation in some integrative protocols).
Pesticides, Solvents, and Cigarette Smoke
Beyond heavy metals, cysteine-glutathione detoxification handles a long list of common environmental and occupational xenobiotics:
- Cigarette smoke — contains acrolein, formaldehyde, benzene, polycyclic aromatic hydrocarbons, and dozens of other electrophiles that consume glutathione for detoxification. Smokers have measurably lower plasma and lung-fluid glutathione than non-smokers, and former smokers have ongoing residual oxidative burden for years after quitting. Practitioners use N-acetylcysteine in smokers as a low-risk hedge.
- Organophosphate pesticides (chlorpyrifos, malathion, diazinon) — broken down in part by paraoxonase enzymes, a family of calcium-dependent hydrolases.
- Industrial solvents — benzene, toluene, xylene, ethylene oxide, propylene oxide, dichloromethane all undergo glutathione conjugation. Painters, autobody workers, dry cleaners, and printing-industry workers have elevated baseline glutathione consumption.
- Plasticizers — phthalates and bisphenol A undergo Phase I metabolism to electrophilic intermediates that are then conjugated to glutathione.
- Aflatoxins from moldy peanuts and grains — the epoxide intermediate is detoxified by GST conjugation; populations with high aflatoxin exposure (especially in sub-Saharan Africa) and genetic GST polymorphisms have elevated liver cancer rates.
- Air pollution PM2.5 and ozone — produce lung oxidative stress that consumes airway-lining-fluid glutathione.
Practitioners reason that people with significant chronic environmental or occupational exposure have elevated glutathione turnover, and they use modest ongoing N-acetylcysteine (600 mg/day) as a hedge in such people; for low-exposure adults with intact glutathione synthesis, they describe the marginal benefit as small.
When Cysteine Supplementation Actually Helps
Pulling the threads together, these are the situations in which N-acetylcysteine is used for detoxification — the first on the U.S. drug labels, the rest as practitioners describe them:
- Acute acetaminophen (paracetamol) overdose — a hospital emergency and the one detoxification use on the U.S. Food and Drug Administration labels: intravenous and oral acetylcysteine are both indicated to prevent or lessen liver injury after a potentially liver-toxic amount of acetaminophen. The oral label states that treatment needs to start as soon as possible after the overdose and in any case within 24 hours. The intravenous label warns that the infusion can cause serious allergic reactions, including fatal or life-threatening anaphylaxis, soon after it starts.
- Chronic low-grade heavy metal exposure — smokers, fish-heavy diets, occupational exposure, dental-amalgam-removal patients. Practitioners use N-acetylcysteine at 600-1200 mg/day with the aim of gradually reducing body burden over months.
- High occupational xenobiotic exposure — chemical workers, painters, printers, farmworkers. N-acetylcysteine supports the elevated Phase II conjugation burden.
- Glutathione-depleted disease states — non-alcoholic fatty liver disease (NAFLD), chronic obstructive pulmonary disease (COPD), human immunodeficiency virus (HIV), chronic kidney disease, aging frailty. N-acetylcysteine restores intracellular glutathione and supports all detoxification pathways downstream.
- High air pollution exposure — urban residents in heavily polluted areas, wildfire smoke exposure, firefighters. N-acetylcysteine supports airway-lining-fluid glutathione.
- Vegetarians and vegans with limited sulfur amino acid intake — particularly those eating low-protein diets, the diet-derived methionine and cysteine may be marginal and supplementation modestly raises glutathione status.
- Genetic GST polymorphism carriers — individuals with GSTM1 null or GSTT1 null deletions (common in many populations) have reduced Phase II conjugation capacity and may benefit more from supportive N-acetylcysteine than the general population.
Situations in which cysteine/N-acetylcysteine supplementation is not described as producing meaningful benefit:
- "Cleansing" protocols in healthy adults without specific exposure — the marketing claim that everyone needs to detoxify with N-acetylcysteine, juice cleanses, herbal blends, etc. is not supported by clinical evidence in adults eating normal diets without specific high-exposure factors.
- Mobilization without source removal — if a patient's mercury exposure is from ongoing dental-amalgam fillings, N-acetylcysteine chelation while the source remains in place is not productive; practitioners and toxicologists alike put removing the source first.
- Acute high-exposure poisoning — N-acetylcysteine is too slow and weak; toxicology practice uses DMSA, DMPS, CaEDTA, or BAL, as indicated, under a toxicologist's care.
Cautions in Heavy Metal Chelation
- Source removal comes first. Removing the source of ongoing exposure is described as more important than chelating mobilized burden. Practitioners put stopping smoking before mercury detox, replacing amalgam with composite fillings (with safety measures during removal) before chelating dental-amalgam mercury, and removing environmental lead before lead chelation.
- Provoked urine testing is not body burden testing. A "challenge" urine collected after DMSA or DMPS administration shows mobilized metal, not steady-state burden, and the result cannot be compared to passive-excretion reference ranges. Most mainstream toxicologists consider provoked challenge testing unreliable for diagnosis.
- Essential mineral depletion during chelation. All thiol chelators bind zinc, copper, manganese, and selenium along with the toxic metals. Long-term chelation protocols require monitored replacement of these essential minerals.
- Redistribution risk. Aggressive chelation can mobilize tissue mercury faster than the kidney can excrete it, transiently redistributing to brain. Symptoms include headache, brain fog, fatigue, and mood changes during chelation. N-acetylcysteine's gentler kinetics minimize but do not eliminate this risk.
- Pregnancy and lactation. Chelation during pregnancy or lactation carries the risk that mobilized maternal metals cross to the fetus or infant.
- Renal insufficiency. All chelators rely on renal excretion to clear mobilized metals; significant chronic kidney disease (CKD) slows that clearance, and hemodialysis support is sometimes needed.
- Cystinuria (rare). The inherited cystine-transport disorder is a contraindication to high-dose cysteine supplementation.
Key Research Papers
- Klaassen CD, Liu J, Choudhuri S (1999). Metallothionein: an intracellular protein to protect against cadmium toxicity. Annual Review of Pharmacology and Toxicology. — PubMed PMID: 10331085
- Aposhian HV (1998). Mobilization of mercury and arsenic in humans by sodium 2,3-dimercapto-1-propane sulfonate (DMPS). Environmental Health Perspectives. — PubMed PMID: 9703487
- Ballatori N, Krance SM, Notenboom S et al. (2009). Glutathione dysregulation and the etiology and progression of human diseases. Biological Chemistry. — PubMed PMID: 19166318
- Patrick L (2002). Mercury toxicity and antioxidants: Part 1: role of glutathione and alpha-lipoic acid in the treatment of mercury toxicity. Alternative Medicine Review. — PubMed PMID: 12495372
- Quig D (1998). Cysteine metabolism and metal toxicity. Alternative Medicine Review. — PubMed PMID: 9727078
- Flora SJ, Pachauri V (2010). Chelation in metal intoxication. International Journal of Environmental Research and Public Health. — PubMed PMID: 20717537
- Hayes JD, Pulford DJ (1995). The glutathione S-transferase supergene family: regulation of GST and the contribution of the isoenzymes to cancer chemoprotection. Critical Reviews in Biochemistry and Molecular Biology. — PubMed PMID: 8770536
- Drake J, Sultana R, Aksenova M, Calabrese V, Butterfield DA (2003). Elevation of mitochondrial glutathione by gamma-glutamylcysteine ethyl ester protects mitochondria against peroxynitrite-induced oxidative stress. Journal of Neuroscience Research. — PubMed PMID: 14648597
- Klein AV, Hambley TW (2009). Platinum drug distribution in cancer cells and tumors. Chemical Reviews. (For glutathione-cisplatin interaction context.) — PubMed PMID: 19711978
- Pizzorno J (2014). Glutathione! Integrative Medicine. — PubMed PMID: 26770075
- Hayes JD, Flanagan JU, Jowsey IR (2005). Glutathione transferases. Annual Review of Pharmacology and Toxicology. — PubMed PMID: 15822171
- Bernhoft RA (2012). Mercury toxicity and treatment: a review of the literature. Journal of Environmental and Public Health. — PubMed PMID: 22235210
PubMed Topic Searches
Connections
- All Amino Acids
- Cysteine Overview
- Cysteine Benefits Hub
- Cysteine for Glutathione Synthesis
- N-Acetylcysteine and Lung Health
- Cysteine for Hair and Nails
- N-Acetylcysteine
- N-Acetylcysteine and Glutathione
- Heavy Metals
- Mercury
- Lead
- Cadmium
- Arsenic
- Gerson Therapy Detoxification
- Oxidative Stress
- Sulfur
- Zinc (MT Inducer)
- Selenium (GPX Cofactor)
- Molybdenum and Detoxification
- History
- Sources