N-acetyl-cysteine and Glutathione Precursors
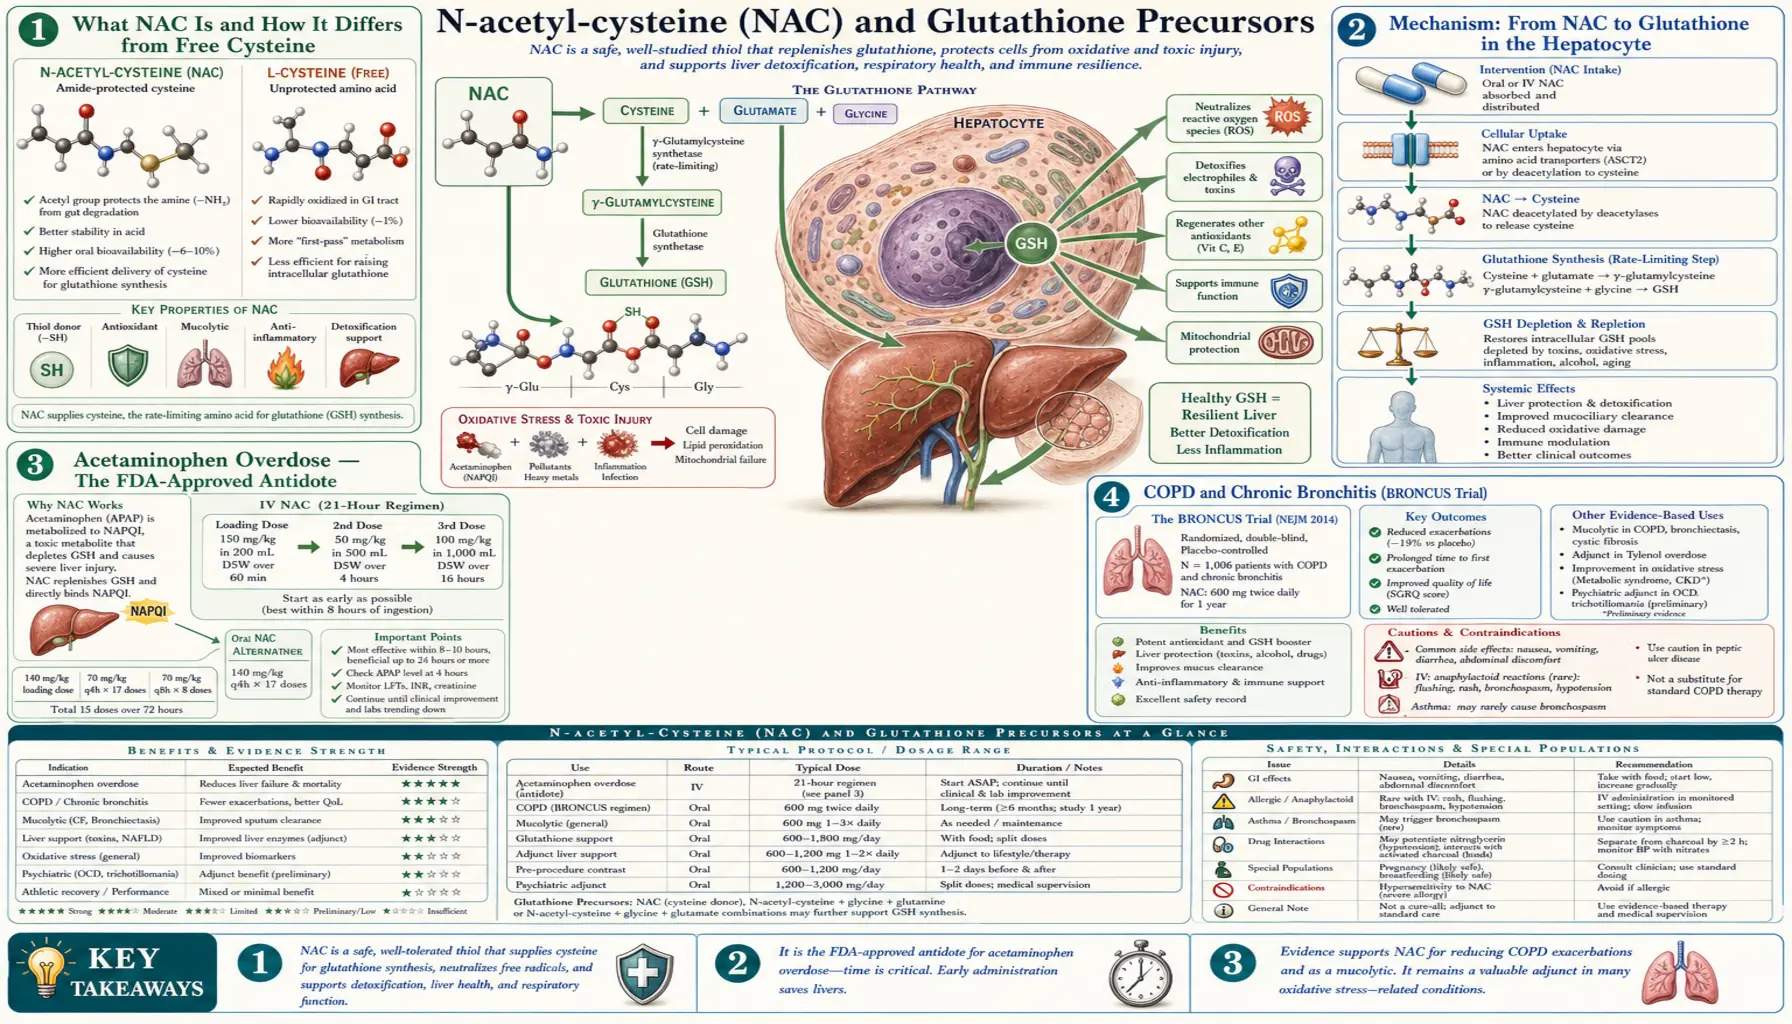
N-acetylcysteine (NAC) is the single most studied supplement for raising tissue glutathione. It supplies the rate-limiting cysteine precursor in an absorbable, oxidation-stable form. As a prescription drug (acetylcysteine) it is U.S. Food and Drug Administration-approved as an antidote for acetaminophen overdose and as a mucolytic for abnormal, thick mucus in lung conditions, including the pulmonary complications of cystic fibrosis. As an over-the-counter supplement it has accumulated clinical trial evidence of varying strength for chronic bronchitis (PANTHEON and HIACE; the earlier BRONCUS trial was null), polycystic ovary syndrome, obsessive-compulsive disorder, trichotillomania, addiction, and bipolar depression. The U.S. Food and Drug Administration-versus-supplement-industry regulatory dispute over N-acetylcysteine's supplement status remains unresolved as of 2026. This deep-dive walks through the mechanism, the established and emerging clinical uses, the dose-response and side-effect profile, and the supporting nutrients (glycine, selenium, B-vitamins) that complete the glutathione synthesis pathway.
Table of Contents
- What N-Acetylcysteine Is and How It Differs from Free Cysteine
- Mechanism: From N-Acetylcysteine to Glutathione in the Hepatocyte
- Acetaminophen Overdose — The U.S. Food and Drug Administration-Approved Antidote
- Chronic Obstructive Pulmonary Disease and Chronic Bronchitis (BRONCUS Trial)
- Contrast-Induced Nephropathy Prophylaxis
- Psychiatric Uses: Obsessive-Compulsive Disorder, Trichotillomania, Addiction, Bipolar
- Polycystic Ovary Syndrome, Fertility, and Metabolic Applications
- Dosing, Timing, and Quality
- Glycine, Selenium, and the Other Synthesis Cofactors
- Cautions, Drug Interactions, and the U.S. Food and Drug Administration Regulatory Dispute
- Key Research Papers
- Connections
- Featured Videos
What N-Acetylcysteine Is and How It Differs from Free Cysteine
N-acetylcysteine is the amino acid cysteine with an acetyl group attached to the amino nitrogen. The chemical modification is simple but functionally critical — it stabilizes cysteine for oral delivery.
Free cysteine is unstable in plasma and oxygenated solutions. Two cysteine thiols readily form a disulfide bond producing the oxidized dimer cystine, which is poorly absorbed, can precipitate (causing the kidney-stone disease cystinuria), and at high concentration is potentially neurotoxic. Cysteine supplements are therefore poorly bioavailable and have an unfavorable safety profile.
N-acetylcysteine's acetyl group prevents this dimerization during digestion and absorption. After absorption, intestinal and hepatic acylases cleave the acetyl group, releasing free cysteine intracellularly where it can immediately enter the glutathione synthesis pathway. N-acetylcysteine is therefore not itself the active molecule — it is a delivery vehicle for cysteine that bypasses the absorption problems of free cysteine.
An additional consideration: N-acetylcysteine retains some intrinsic antioxidant activity itself through its free thiol group, scavenging hydroxyl radicals and hypochlorous acid directly. This is a minor contribution compared to the downstream glutathione-driven effects, but it explains modest acute effects of N-acetylcysteine in some experimental settings before glutathione synthesis ramps up.
Mechanism: From N-Acetylcysteine to Glutathione in the Hepatocyte
The path from a swallowed N-acetylcysteine capsule to elevated tissue glutathione has several steps:
- Absorption — N-acetylcysteine is absorbed through the small intestine with bioavailability of approximately 6-10% for the parent compound. Most N-acetylcysteine is deacetylated in the intestinal mucosa and absorbed as cysteine, raising plasma cysteine within 1-2 hours of dosing.
- First-pass hepatic uptake — the liver extracts a substantial fraction of absorbed cysteine on first pass through portal circulation, where it enters the glutathione synthesis pathway as the rate-limiting substrate for gamma-glutamyl cysteine ligase.
- Hepatic glutathione synthesis — within hours of N-acetylcysteine dosing, hepatic glutathione content increases measurably. This is the basis for the acetaminophen overdose antidote effect, where hepatic glutathione must be restored before NAPQI accumulates to a damaging level.
- Systemic distribution — some cysteine and glutathione cycle out of the liver into systemic circulation as gamma-glutamyl cysteine or cystine, supplying peripheral tissues with substrates for local glutathione synthesis.
- Tissue-specific responses — tissues vary in their responsiveness to N-acetylcysteine. Liver responds robustly. Lungs show measurable effects (relevant to the chronic obstructive pulmonary disease (COPD) evidence). Brain crosses the blood-brain barrier modestly, supporting the psychiatric applications. Kidney concentrates cysteine for renal glutathione synthesis (relevant to contrast nephropathy prophylaxis).
The pharmacokinetic profile favors divided dosing — N-acetylcysteine plasma half-life is approximately 6 hours, so twice-daily dosing maintains more consistent cysteine supply than a single large daily dose. The standard regimens in clinical trials reflect this: 600 mg twice daily for chronic bronchitis, 600-1200 mg twice daily for psychiatric indications.
Acetaminophen Overdose — The U.S. Food and Drug Administration-Approved Antidote
Acetaminophen overdose is the leading cause of acute liver failure in the United States, with approximately 100,000 calls to poison control annually and 500-1,000 deaths despite available antidote. The biochemistry has been precisely mapped:
Therapeutic-dose acetaminophen is cleared 90% by glucuronidation and sulfation. Only 5-10% goes through cytochrome P450 2E1 (CYP2E1), generating the reactive intermediate N-acetyl-p-benzoquinone-imine (NAPQI). NAPQI is immediately quenched by hepatic glutathione, forming a non-toxic conjugate excreted in urine. In overdose (typically >7.5 g acute or >4 g chronic in adults; less in children), the conjugation pathways saturate, more acetaminophen flows through CYP2E1, NAPQI production accelerates, and hepatic glutathione drops. When glutathione falls below approximately 30% of normal, free NAPQI begins arylating hepatocyte proteins, causing centrilobular hepatic necrosis. Without intervention, mortality from severe overdose approaches 25-30%.
N-acetylcysteine is the antidote because it supplies cysteine for accelerated glutathione resynthesis, restoring NAPQI quenching capacity. N-acetylcysteine is most effective if given within 8 hours of ingestion, with progressively reduced efficacy out to 24 hours. The Rumack-Matthew nomogram is used to determine which patients need treatment based on the serum acetaminophen level at 4 hours post-ingestion.
The standard treatment regimens:
- Oral protocol (72-hour Smilkstein) — 140 mg/kg loading dose, then 70 mg/kg every 4 hours for 17 doses (total 1,330 mg/kg over 72 hours). High dose; nausea and vomiting are common.
- Intravenous protocol (21-hour Prescott) — 150 mg/kg loading over 60 minutes, then 50 mg/kg over 4 hours, then 100 mg/kg over 16 hours (total 300 mg/kg over 21 hours). Faster; hypersensitivity (anaphylactoid) reactions occur most commonly during the loading dose (see Cautions).
N-acetylcysteine works. With timely administration mortality drops from 25-30% to under 5%. This is one of the cleanest cause-and-effect pharmacology stories in clinical toxicology — depleted glutathione causes the injury, restoring glutathione precursor reverses the cascade.
Chronic Obstructive Pulmonary Disease and Chronic Bronchitis (BRONCUS Trial)
The lung evidence for N-acetylcysteine has accumulated over four decades. N-acetylcysteine has direct mucolytic properties (its free thiol breaks the disulfide bonds in viscous airway mucus) plus indirect glutathione-mediated antioxidant effects that may reduce the chronic oxidative damage that drives chronic obstructive pulmonary disease progression.
The BRONCUS trial (Bronchitis Randomized On N-acetylcysteine Cost-Utility Study) — Decramer et al., Lancet 2005 — randomized 523 chronic obstructive pulmonary disease patients to N-acetylcysteine 600 mg/day or placebo for 3 years. Results:
- No effect on either primary endpoint: yearly FEV1 decline (the conventional chronic obstructive pulmonary disease progression marker) or exacerbations per year (hazard ratio 0.99, p=0.85)
- A subgroup analysis suggested exacerbations might be reduced in patients not using inhaled corticosteroids
- A secondary analysis was suggestive of an effect on hyperinflation
- The authors concluded that N-acetylcysteine is ineffective at prevention of deterioration in lung function and prevention of exacerbations in chronic obstructive pulmonary disease
The subsequent PANTHEON trial (Zheng et al., Lancet Respiratory Medicine 2014) in 1,006 Chinese chronic obstructive pulmonary disease patients used a higher dose — 600 mg twice daily — for 1 year and found a more definitive 22% reduction in exacerbations across the whole population. The HIACE trial in Hong Kong (Tse et al., Chest 2013; 120 patients, 1 year) also found fewer exacerbations at 600 mg twice daily (0.96 vs 1.71 a year).
The trials that found fewer exacerbations (PANTHEON and HIACE) used N-acetylcysteine 600 mg twice daily (1,200 mg/day total). It is part of the ERS/ATS COPD guidelines as an adjunct option, particularly for patients with chronic bronchitis phenotype and frequent exacerbations. For pulmonology context, see our chronic obstructive pulmonary disease page.
Outside chronic obstructive pulmonary disease, N-acetylcysteine has been studied in idiopathic pulmonary fibrosis with mixed results (the IFIGENIA trial showed benefit, but the more rigorous PANTHER-IPF trial showed no benefit) and in cystic fibrosis where it complements but does not replace standard mucolytic therapy.
Contrast-Induced Nephropathy Prophylaxis
Iodinated contrast media (used in computed tomography (CT) scans and cardiac catheterization) can precipitate acute kidney injury, particularly in patients with pre-existing chronic kidney disease, diabetes, or volume depletion. The mechanism involves direct renal tubular toxicity and oxidative stress at the renal medulla.
N-acetylcysteine was investigated as prophylaxis based on the rationale that boosting renal glutathione should mitigate the oxidative injury. The Tepel 2000 NEJM trial was the original positive study (600 mg twice daily orally for 4 doses bracketing contrast exposure). Many subsequent trials and meta-analyses produced inconsistent results, and the definitive PRESERVE trial (Weisbord 2018 NEJM, 5,000 patients) showed no benefit of N-acetylcysteine over placebo for the primary endpoint of death, dialysis, or sustained renal impairment.
Current professional society guidelines (ACR, KDIGO) no longer routinely recommend N-acetylcysteine for contrast nephropathy prophylaxis. Adequate intravenous (IV) hydration with isotonic saline before and after contrast remains the only well-supported preventive intervention. This is a useful cautionary example — positive small trials do not always replicate in large rigorous trials, and the appropriate humility about N-acetylcysteine's benefits in some indications.
Psychiatric Uses: Obsessive-Compulsive Disorder, Trichotillomania, Addiction, Bipolar
The psychiatric N-acetylcysteine literature is the most actively expanding area. The proposed mechanism centers on N-acetylcysteine's effect on the cystine-glutamate antiporter in the brain — restoring glutamate homeostasis in pathways implicated in compulsive behaviors and reward dysregulation. Notable trials:
Trichotillomania (compulsive hair-pulling) — Grant et al. Archives of General Psychiatry 2009 randomized 50 patients to N-acetylcysteine 1,200-2,400 mg/day or placebo for 12 weeks. The N-acetylcysteine group showed significant reduction in hair-pulling symptoms (56% responder rate vs 16% placebo). This is the strongest psychiatric trial for N-acetylcysteine and led to its adoption as a reasonable evidence-based intervention.
Obsessive-compulsive disorder — small randomized controlled trials (RCTs) have given mixed results. Afshar 2012 (48 patients with treatment-refractory obsessive-compulsive disorder, N-acetylcysteine up to 2,400 mg/day added to serotonin reuptake inhibitor treatment for 12 weeks) found more full responders on N-acetylcysteine than on placebo (52.6% vs 15%). Sarris 2015 (44 participants, 3,000 mg/day for 16 weeks) found no significant difference from placebo in YBOCS total score (p = 0.39); 20% of the N-acetylcysteine group and 27% of the placebo group were responders. N-acetylcysteine is included in some treatment-resistant obsessive-compulsive disorder (OCD) algorithms.
Bipolar depression — Berk et al. Biological Psychiatry 2008 randomized 75 bipolar depression patients to N-acetylcysteine 2,000 mg/day or placebo as adjunct to standard treatment for 24 weeks. The N-acetylcysteine group showed significant improvement in MADRS depression scores. Multiple follow-up trials have generally supported this finding, though a large 2019 trial (CARMS) was negative.
Schizophrenia (negative symptoms) — Berk et al. Biological Psychiatry 2008 (second 2008 paper) randomized 140 schizophrenia patients to N-acetylcysteine 2,000 mg/day or placebo for 24 weeks. The N-acetylcysteine group showed improvement in negative symptoms (PANSS negative subscale).
Cocaine and cannabis dependence — small trials show N-acetylcysteine reduces craving and may help maintain abstinence. The proposed mechanism is the same glutamate-homeostasis pathway. It is not standard of care.
Autism spectrum disorder — small trials (Hardan 2012, Ghanizadeh 2013) of N-acetylcysteine 900-2,700 mg/day in children with autism showed modest reduction in irritability and stereotypy on parent-rated scales.
The aggregate psychiatric evidence is moderate and mixed; N-acetylcysteine is used as an adjunct in functional and integrative psychiatry and is considered in academic psychiatry for treatment-resistant cases.
Polycystic Ovary Syndrome, Fertility, and Metabolic Applications
Polycystic ovary syndrome (PCOS) features insulin resistance, hyperandrogenism, oligo-ovulation, and chronic low-grade oxidative stress. N-acetylcysteine has been studied as an insulin-sensitizing and ovulation-supporting intervention with reasonable evidence base. A 2015 systematic review and meta-analysis (Thakker et al., Obstetrics & Gynecology International) pooled 8 randomized controlled trials with 910 women and found:
- N-acetylcysteine was associated with higher odds of ovulation, pregnancy, and live birth than placebo, but women on N-acetylcysteine were less likely to become pregnant or ovulate than women on metformin
- N-acetylcysteine plus clomiphene increased ovulation and pregnancy rates over clomiphene alone in clomiphene-resistant patients
- No significant improvement in fasting insulin or insulin resistance (homeostatic model assessment of insulin resistance, HOMA-IR) compared with placebo or metformin, although fasting glucose fell
- No significant difference from placebo in adverse events
Regimens described for polycystic ovary syndrome use N-acetylcysteine 1,200-1,800 mg/day, often combined with inositol (myo-inositol 2 g twice daily); practitioners describe the combination especially for patients who do not tolerate metformin.
For broader insulin resistance and metabolic syndrome, N-acetylcysteine has shown reductions in homeostatic model assessment of insulin resistance and improvements in oxidative stress biomarkers. The 2021 GlyNAC pilot trial by Kumar et al. was open-label, with no placebo group, in eight older adults (eight young adults were studied once for comparison). It reported that 24 weeks of glycine plus N-acetylcysteine corrected red-cell glutathione deficiency and mitochondrial dysfunction, and improved insulin resistance, body composition, strength, gait speed, and cognition; the benefits declined after supplementation stopped for 12 weeks.
Dosing, Timing, and Quality
Dose-response data across the indications:
- Acetaminophen overdose — oral 1,330 mg/kg over 72 hours or intravenous 300 mg/kg over 21 hours. These are hospital protocols, given under medical supervision.
- Chronic obstructive pulmonary disease / chronic bronchitis — 600 mg twice daily; the PANTHEON 1,200 mg/day dose performed better than the BRONCUS 600 mg/day dose.
- Polycystic ovary syndrome — 1,200-1,800 mg/day divided into 2-3 doses.
- Obsessive-compulsive disorder / trichotillomania / bipolar depression — the trials above used 1,200-3,000 mg/day, reached by titrating up (starting at 600 mg twice daily in the regimens described).
- Antiaging / general antioxidant — none of the trials above tested this use; the amounts commonly described are 600 mg once daily, or 600 mg twice daily where glutathione deficiency or significant oxidative stress has been documented.
- GlyNAC protocol — the Kumar 2021 pilot gave glycine 1.33 mmol/kg/day and cysteine 0.81 mmol/kg/day (provided as N-acetylcysteine), as capsules, for 24 weeks.
Quality considerations: N-acetylcysteine is one of the most adulterated supplement categories. The pharmaceutical-grade material used in clinical trials is white powder, faintly sulfurous odor. The cheapest internet-sourced N-acetylcysteine may be off-color (yellow tinge from oxidation), strong sulfurous odor, or below labeled potency. Third-party certification programs (USP Verified, NSF Certified) test that a product contains what its label states. Capsules generally tolerate better than powder because the sulfurous taste is masked.
Timing: N-acetylcysteine is moderately better tolerated with food (less gastrointestinal (GI) upset) but can be taken on an empty stomach. The half-life of approximately 6 hours supports twice-daily dosing for clinical indications.
Glycine, Selenium, and the Other Synthesis Cofactors
Cysteine is the rate-limiting substrate for glutathione synthesis in most physiological conditions, but it is not the only substrate or cofactor. The complete pathway requires:
- Glycine — the second amino acid added by glutathione synthetase. Sekhar's work shows glycine is co-rate-limiting in older adults and many chronic disease states. Dietary glycine intake averages 3-5 g/day in Western diets but optimal intake for glutathione synthesis may be 5-15 g/day. Bone broth, gelatin, collagen powder, and pure glycine powder (5-10 g/day) are practical sources. Glycine also has independent benefits for sleep, blood-sugar regulation, and renal function.
- Glutamate — abundant in dietary protein; rarely limiting.
- Selenium — cofactor for glutathione peroxidase activity. The selenium status of US populations is generally adequate; the Recommended Dietary Allowance (RDA) is 55 mcg/day and most adults consume 100-200 mcg from typical diets. Selenium-rich foods include Brazil nuts (1-2 per day provides 100-200 mcg), seafood, organ meats, and selenium-enriched yeast. Supplemental selenium of 100-200 mcg/day is the range described for known deficiency or high-oxidant-load states; chronic intake >400 mcg/day risks selenosis (hair loss, brittle nails, garlicky breath).
- Reduced nicotinamide adenine dinucleotide phosphate (NADPH) — generated by the pentose phosphate pathway (glucose-6-phosphate dehydrogenase (G6PD) enzyme). Not directly supplemented, but supported by adequate niacin status and glucose-6-phosphate availability.
- B-vitamins (especially B2 riboflavin, B6, B12, folate) — required for the transsulfuration pathway (homocysteine to cysteine via cystathionine beta-synthase, which is B6-dependent) and for general one-carbon metabolism. A B-complex with bioavailable forms (methylfolate, methylcobalamin, P5P) supports the upstream pathway.
- Magnesium — cofactor for multiple enzymes in glutathione synthesis and recycling.
Practitioners targeting glutathione therefore describe combining N-acetylcysteine with these cofactors rather than using it alone: N-acetylcysteine 600 mg twice daily, glycine 5-10 g/day, B-complex with methylated forms, selenium 100-200 mcg/day (or 1-2 Brazil nuts), and adequate magnesium. Whole-food sources (whey protein, bone broth, allium vegetables for sulfur amino acids) further support the pathway.
Cautions, Drug Interactions, and the U.S. Food and Drug Administration Regulatory Dispute
- Gastrointestinal upset — the most common side effect (5-10% of users). Nausea, dyspepsia, occasionally diarrhea. Taking it with food and starting at lower doses are the usual ways described to reduce this.
- Sulfurous taste / odor — intrinsic to N-acetylcysteine; capsules minimize the issue compared to powders or effervescent tablets.
- Asthma / bronchospasm — nebulized (inhaled) acetylcysteine can trigger bronchospasm in susceptible patients; its label states that most patients with bronchospasm are quickly relieved by a nebulized bronchodilator, and that the medication is stopped if bronchospasm progresses. Oral N-acetylcysteine does not cause this.
- Anaphylactoid reaction with intravenous N-acetylcysteine — the U.S. label for intravenous acetylcysteine (the acetaminophen antidote) reports hypersensitivity reactions in 8% of adults and 10% of children in a large Canadian safety study, and in 17% of patients in an Australian infusion-rate trial (18% with a 15-minute loading infusion, 14% with a 60-minute infusion); the label states that a two-bag regimen may be associated with fewer reactions than the three-bag regimen. A Danish cohort (Daoud 2020) recorded anaphylactoid reactions needing treatment in 259 of 4,315 admissions (6.0%). Oral N-acetylcysteine has no analogous risk.
- Drug interactions: nitroglycerin — N-acetylcysteine potentiates the hypotensive and headache effects of nitrates, which raises a concern for people taking them.
- Drug interactions: activated charcoal — in acetaminophen overdose, charcoal absorbs N-acetylcysteine and reduces its bioavailability if given simultaneously; a 1-2 hour separation is described.
- Drug interactions: anticoagulants — theoretical potentiation of warfarin through cysteine effects on coagulation; close international normalized ratio (INR) monitoring is the clinical response described when the two are combined at high doses.
- Bipolar I disorder — rare reports of N-acetylcysteine precipitating mania in initial weeks; a question for the treating psychiatrist.
- Pregnancy — N-acetylcysteine is used in pregnancy for acetaminophen overdose without harm; routine high-dose supplementation outside that indication has limited data.
- Chemotherapy — theoretical concern that N-acetylcysteine could blunt oxidant-mediated antitumor effects of cisplatin, doxorubicin; a question for the oncologist during active chemotherapy.
- U.S. Food and Drug Administration (FDA) regulatory dispute — in 2020 the U.S. Food and Drug Administration sent warning letters classifying N-acetylcysteine as a drug (because it was approved as a prescription drug before any DSHEA supplement marketing) and not a legitimate dietary supplement. After industry pushback and litigation, the U.S. Food and Drug Administration in 2022 announced enforcement discretion allowing N-acetylcysteine to remain sold as a supplement pending rulemaking. As of 2026 the supplement status is preserved by enforcement discretion but the formal regulatory question remains unresolved. Some major online retailers briefly pulled N-acetylcysteine, then restored it. Current consumer access is unimpeded but the regulatory backdrop is unstable.
Key Research Papers
- Prescott LF et al. (1979). Intravenous N-acetylcysteine: the treatment of choice for paracetamol poisoning. BMJ. — PubMed PMID: 519312
- Smilkstein MJ et al. (1988). Efficacy of oral N-acetylcysteine in the treatment of acetaminophen overdose. NEJM. — PubMed
- Decramer M et al. (2005). Effects of N-acetylcysteine on outcomes in chronic obstructive pulmonary disease (Bronchitis Randomized on NAC Cost-Utility Study, BRONCUS). Lancet. — PubMed PMID: 15866309
- Zheng JP et al. (2014). Twice daily N-acetylcysteine 600 mg for exacerbations of chronic obstructive pulmonary disease (PANTHEON). Lancet Respiratory Medicine. — PubMed PMID: 24621680
- Tepel M et al. (2000). Prevention of radiographic-contrast-agent-induced reductions in renal function by acetylcysteine. NEJM. — PubMed PMID: 10900277
- Weisbord SD et al. (2018). Outcomes after angiography with sodium bicarbonate and acetylcysteine (PRESERVE). NEJM. — PubMed PMID: 29130810
- Grant JE et al. (2009). N-acetylcysteine, a glutamate modulator, in the treatment of trichotillomania: a double-blind, placebo-controlled study. Archives of General Psychiatry. — PubMed
- Berk M et al. (2008). N-acetyl cysteine as a glutathione precursor for schizophrenia — a double-blind, randomized, placebo-controlled trial. Biological Psychiatry. — PubMed
- Berk M et al. (2008). N-acetyl cysteine for depressive symptoms in bipolar disorder — a double-blind randomized placebo-controlled trial. Biological Psychiatry. — PubMed PMID: 18534556
- Thakker D et al. (2015). N-acetylcysteine for polycystic ovary syndrome: a systematic review and meta-analysis of randomized controlled clinical trials. Obstetrics & Gynecology International. — PubMed PMID: 25653680
- Kumar P et al. (2021). GlyNAC supplementation in older adults improves glutathione deficiency. Clinical and Translational Medicine. — PubMed PMID: 33783984
- Aldini G et al. (2018). N-Acetylcysteine as an antioxidant and disulphide breaking agent: the reasons why. Free Radical Research. — PubMed
PubMed Topic Searches
Connections
- All Remedies
- N-Acetylcysteine and Kidney Health — the renal half of the N-acetylcysteine evidence base — contrast-induced nephropathy from Tepel 2000 through the PRESERVE and ACT trials, chronic kidney disease, hemodialysis, and cystine stone prevention.
- N-Acetylcysteine and Lung Health — the same molecule in the airways instead of the kidney — mucolytic disulfide-bond cleavage, the BRONCUS and PANTHEON COPD trials, IPF, and the Rumack-Matthew acetaminophen protocol.
- Oxidative Stress Hub
- Oxidative Stress Benefits Hub
- Glutathione Master Antioxidant
- Polyphenol Foods
- Mitochondrial Health
- Cysteine
- Glycine
- Selenium
- Vitamin B6
- Vitamin B2 (Riboflavin)
- Chronic Obstructive Pulmonary Disease
- Polycystic Ovary Syndrome
- Hepatology (Liver Disease)
- Psychiatry
- Detoxification