⚠ Evidence warning: Clinical trials or other evidence do not support the claims that nicotinamide riboside and nicotinamide mononucleotide are anti-aging. This page keeps it as a report of what people, websites or other media say.
Vitamin B3 (Niacin) — Benefits Deep Dive
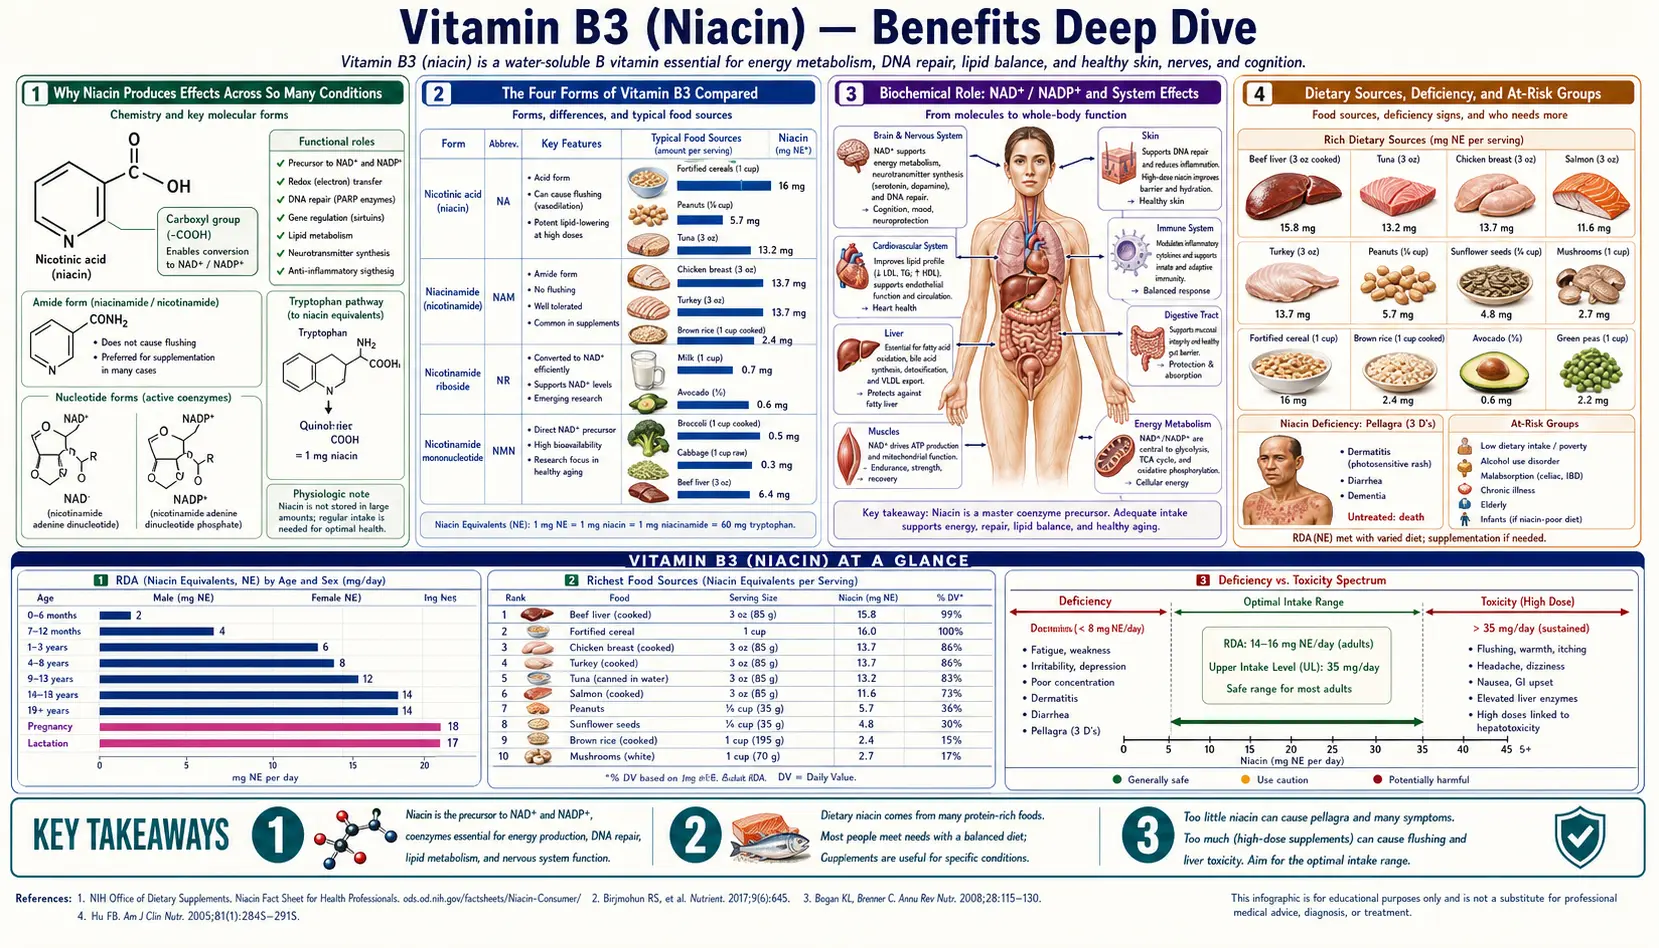
Vitamin B3 is unusual among nutrients because it is the obligate biochemical precursor to nicotinamide adenine dinucleotide (NAD+) and NADP+ — two coenzymes that together participate in more than 500 enzymatic reactions, more than any other vitamin-derived cofactor. That single fact explains why niacin shows up across four utterly different clinical domains: anti-aging nicotinamide adenine dinucleotide restoration, lipid management for cardiovascular prevention, classical deficiency dermatology, and orthomolecular psychiatry. Each benefit page below explores one of those four worlds in clinical-trial depth.
Deep-Dive Articles
Nicotinamide Adenine Dinucleotide Precursor — Why All Roads Lead to Nicotinamide Adenine Dinucleotide
The four niacin family members — nicotinic acid, nicotinamide (NAM), nicotinamide riboside (NR), and nicotinamide mononucleotide (NMN) — all converge on nicotinamide adenine dinucleotide through three distinct biosynthetic routes: the Preiss-Handler pathway (nicotinic acid), the salvage pathway (NAM and nicotinamide riboside via NRK enzymes), and the de novo kynurenine pathway from tryptophan. This page maps every route, compares cost-effectiveness of plain niacin/NAM against expensive nicotinamide riboside/nicotinamide mononucleotide supplements, and tackles the flush-vs-flush-free decision.
Read the deep dive →Cholesterol & Cardiovascular Disease
Niacin has been described as the first lipid-modifying drug shown to reduce all-cause mortality, on the long-term results of the Coronary Drug Project (first reported in 1975): during the trial it did not decrease total mortality, and the 11% lower mortality appeared at a mean of 15 years, nearly 9 years after the trial ended. AIM-HIGH (2011) and HPS2-THRIVE (2014) were negative when niacin was added on top of statins, leading mainstream cardiology to abandon it. This page walks the trial history honestly, explains why niacin still has a real place as monotherapy in statin-intolerant patients with high Lp(a) and ApoB, and gives the 1-3 g/day immediate-release titration protocol that works.
Read the deep dive →Pellagra & Skin Health
The classical deficiency story — the US South pellagra epidemic, Joseph Goldberger's brilliant epidemiology, the "4 Ds" of dermatitis-diarrhea-dementia-death, and why corn-based diets without nixtamalization caused the catastrophe. Then the modern skin chapter: hidden pellagra in chronic alcoholism, Crohn's, and Hartnup disease, plus topical niacinamide for acne, hyperpigmentation, barrier function, and the landmark ONTRAC trial showing 23% reduction in non-melanoma skin cancer.
Read the deep dive →Schizophrenia & Orthomolecular Psychiatry
Abram Hoffer's 1950s niacin trials in schizophrenia inaugurated orthomolecular psychiatry. Linus Pauling gave the field its name and intellectual scaffolding. The niacin flush test (reduced or absent flush response in a subset of schizophrenia patients) remains a fascinating biomarker. This page covers the original positive trials, why later controlled trials disappointed, the genuine pellagra-psychosis link, and the realistic place of high-dose B3 in obsessive-compulsive disorder (OCD), anxiety, and depression today.
Read the deep dive →Niacin and Glioblastoma: The Phase I–II Trial
A single-arm trial of high-dose niacin added to standard glioblastoma treatment, compared with past patients: what it measured, what it found and what it cannot show.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why Niacin Produces Effects Across So Many Conditions
- What Large Trials Found on Niacin and Heart Events
- The Four Forms of Vitamin B3 Compared
- Nicotinamide and Skin Cancer in a Large Veterans Cohort
- How a Niacin Breakdown Product Is Linked to Heart Risk
- Research Papers: Nicotinamide Adenine Dinucleotide Metabolism & Longevity
- Research Papers: Cholesterol & Cardiovascular
- Research Papers: Pellagra, Skin & Dermatology
- Research Papers: Psychiatry & Mental Health
- Research Papers: Cross-Cutting (Forms, Safety, Mechanism)
- External Authoritative Resources
- Connections
- Featured Videos
Why Niacin Produces Effects Across So Many Conditions
Most vitamins are essential cofactors for a small number of specific enzymes — vitamin C for collagen hydroxylase, biotin for the four carboxylases, vitamin K for the gamma-glutamyl carboxylase. Vitamin B3 is different. Its two derived coenzymes — nicotinamide adenine dinucleotide and NADP+ — participate in more than 500 enzymatic reactions, more than any other vitamin-derived molecule. That extraordinary breadth maps to four distinct clinical domains, each addressed in its own deep-dive page:
- Universal energy currency & longevity substrate — nicotinamide adenine dinucleotide accepts electrons in glycolysis, beta-oxidation, the pyruvate dehydrogenase complex, and three of the eight Krebs cycle steps, then delivers them to Complex I of the electron transport chain. Beyond electron carriage, nicotinamide adenine dinucleotide is the obligate substrate for the seven sirtuins (longevity enzymes), 17 PARPs (DNA repair), and CD38 (immune signaling) — all of which consume nicotinamide adenine dinucleotide rather than recycling it. Nicotinamide adenine dinucleotide levels drop roughly 50% between ages 40 and 60 in many tissues, and restoring them is the central premise of the nicotinamide adenine dinucleotide precursor story.
- Pharmacological lipid-modifying drug — at gram-range doses (1-3 g/day), nicotinic acid acts as a true pharmacological agent, not just a vitamin. It is the most effective single agent ever discovered for raising high-density lipoprotein (HDL) (by 15-35%), and uniquely among readily available compounds it meaningfully lowers lipoprotein(a), or Lp(a), by up to 30% (a 2016 meta-analysis of 14 trials and 9,013 people found an average fall of 22.90% with extended-release niacin). This is the basis of the cardiovascular indication, anchored by the 1975 Coronary Drug Project trial.
- The deficiency disease that defined the vitamin — niacin's discovery came from the pellagra epidemic in the US South (1900-1940), an enormous public-health catastrophe driven by corn-based diets lacking nixtamalization. The "4 Ds" of pellagra — dermatitis, diarrhea, dementia, death — remain a teaching paradigm in nutritional medicine, and modern hidden pellagra still appears in alcoholics, Crohn's patients, and Hartnup disease (see Pellagra & Skin).
- Orthomolecular psychiatry — Abram Hoffer and Humphry Osmond's 1950s Saskatchewan niacin trials in schizophrenia were the founding work of what Linus Pauling later named "orthomolecular psychiatry." The niacin flush test (reduced or absent flush response in 58.5% of schizophrenia patients against 11.8% of healthy controls in a 2026 meta-analysis of 32 studies, with the proportion varying between studies) remains a fascinating endophenotype marker. The clinical evidence is mixed but the biochemistry is real — see Schizophrenia & Mental Health.
Beyond these four primary domains, B3 contributes to multiple supporting roles: the reduced nicotinamide adenine dinucleotide phosphate-glutathione recycling axis that powers Phase II detoxification, joint-mobility research dating back to William Kaufman's 1940s nicotinamide protocols for osteoarthritis, GPR109A receptor signaling that links niacin to ketosis and inflammation, and beta-cell protection in early type 1 diabetes (the ENDIT trial). The unifying thread is always nicotinamide adenine dinucleotide availability — whenever a clinical effect of B3 surprises a researcher, the explanation traces back to one of the 500+ NAD/NADP-dependent reactions.
What Large Trials Found on Niacin and Heart Events
The Coronary Drug Project ran from 1966 to 1975 in 8,341 men who had already had a heart attack. Niacin modestly reduced repeat nonfatal heart attacks but did not decrease total mortality during the trial. At a mean of 15 years, nearly 9 years after the trial ended, mortality from all causes was 11% lower than with placebo (52.0% against 58.2%; p = 0.0004).
A 2017 Cochrane review pooled 23 randomised trials and 39,195 people, with niacin given alone or on top of other treatment such as a statin. Niacin did not reduce overall mortality (risk ratio 1.05, 95% confidence interval 0.97 to 1.12), heart deaths, heart attacks or strokes. People on niacin were more likely to stop treatment because of side effects (risk ratio 2.17). The reviewers concluded that "benefits from niacin therapy in the prevention of cardiovascular disease events are unlikely".
The HPS2-THRIVE trial gave 25,673 adults with vascular disease 2 g of extended-release niacin with laropiprant, or placebo, on top of statin-based treatment, for a median of 3.9 years. Major vascular events did not differ significantly (13.2% against 13.7%; rate ratio 0.96; P = 0.29). The niacin group had more serious disturbances of diabetes control (3.7 percentage points more than placebo), new diabetes diagnoses (1.3), serious infections (1.4) and serious bleeding (0.7).
The Four Forms of Vitamin B3 Compared
| Form | Raises nicotinamide adenine dinucleotide | Lipid Effects | Flush | Studied For |
|---|---|---|---|---|
| Nicotinic Acid (Niacin) | Yes (Preiss-Handler) | Yes — high-density lipoprotein, LDL, TG, Lp(a) | Yes | Lipid management; statin intolerance |
| Nicotinamide (NAM) | Yes (salvage) | No | No | Skin cancer prevention; arthritis; pellagra treatment |
| Nicotinamide Riboside (NR) | Yes (NRK salvage) | No | No | Anti-aging; mitochondrial support |
| Nicotinamide Mononucleotide (NMN) | Yes (one step from nicotinamide adenine dinucleotide) | No | No | Anti-aging (mouse studies) |
The cost differential is dramatic. Plain nicotinamide is about $0.05 per gram. Nicotinic acid is about $0.10 per gram. Nicotinamide riboside runs roughly $1-2 per gram — about 20-40x the cost. Nicotinamide mononucleotide is similar or more expensive. For raw nicotinamide adenine dinucleotide raising, plain NAM is the cost-effective option; nicotinamide riboside/nicotinamide mononucleotide gain ground only if the higher-end mitochondrial and tissue-distribution claims for them prove durable in long-term human trials.
Nicotinamide and Skin Cancer in a Large Veterans Cohort
A 2025 study of US Veterans Affairs health records compared 12,287 patients given nicotinamide 500 mg twice daily for more than 30 days with 21,479 matched patients who were not. Skin cancer risk was 14% lower overall and 54% lower when nicotinamide was started after a first skin cancer; that benefit shrank when it was started after later skin cancers. Among solid organ transplant recipients there was no overall significant reduction, although early use was linked with less squamous cell skin cancer. This is an observational records study, not a randomised trial.
How a Niacin Breakdown Product Is Linked to Heart Risk
When the body has more niacin than it needs, it clears the excess as two end products, called 2PY and 4PY. A 2024 study linked blood levels of both to major heart events over three years in two groups of patients, one in the US (2,331 people) and one in Europe (832 people). The adjusted hazard ratios were 1.64 and 2.02 for 2PY and 1.89 and 1.99 for 4PY. In mice, 4PY at physiological levels, but not 2PY, switched on a blood-vessel inflammation signal (VCAM-1) and made white blood cells stick to the vessel lining. In people this is an association: it does not prove that niacin intake causes heart events.
Research Papers: Nicotinamide Adenine Dinucleotide Metabolism & Longevity
- Preiss J, Handler P (1958). Biosynthesis of diphosphopyridine nucleotide from nicotinic acid. J Biol Chem. — PubMed: Preiss-Handler pathway 1958
- Bieganowski P, Brenner C (2004). Discoveries of nicotinamide riboside as a nutrient and conserved NRK genes establish a Preiss-Handler independent route to NAD+. Cell. — PubMed: NR discovery Brenner 2004
- Yoshino J et al. (2018). NAD+ intermediates: the biology and therapeutic potential of NMN and NR. Cell Metabolism. — PubMed: Yoshino NMN/NR review
- Trammell SA et al. (2016). Nicotinamide riboside is uniquely and orally bioavailable in mice and humans. Nature Communications. — PubMed: Trammell NR human PK
- Martens CR et al. (2018). Chronic nicotinamide riboside supplementation is well-tolerated and elevates NAD+ in healthy middle-aged and older adults. Nature Communications. — PubMed: Martens NR human trial
- Mills KF et al. (2016). Long-term administration of nicotinamide mononucleotide mitigates age-associated physiological decline in mice. Cell Metabolism. — PubMed: Mills NMN mice 2016
- Yoshino J, Mills KF, Imai S et al. (2011). Nicotinamide mononucleotide, a key NAD+ intermediate, treats the pathophysiology of diet- and age-induced diabetes in mice. Cell Metabolism. — PubMed: NMN diabetes mice
- Imai S, Guarente L (2014). NAD+ and sirtuins in aging and disease. Trends Cell Biol. — PubMed: Imai-Guarente review
- Camacho-Pereira J et al. (2016). CD38 dictates age-related NAD decline. Cell Metabolism. — PubMed: CD38 NAD decline
- Verdin E (2015). NAD+ in aging, metabolism, and neurodegeneration. Science. — PubMed: Verdin NAD review Science
- Schultz MB, Sinclair DA (2016). Why NAD(+) declines during aging: it's destroyed. Cell Metabolism. 23(6):965-966. — PubMed PMID: 27304496
Research Papers: Cholesterol & Cardiovascular
- Coronary Drug Project Research Group (1975). Clofibrate and niacin in coronary heart disease. JAMA. 231(4):360-381. — PubMed PMID: 1088963
- Canner PL et al. (1986). Fifteen year mortality in Coronary Drug Project patients: long-term benefit with niacin. J Am Coll Cardiol. 8(6):1245-1255. — PubMed PMID: 3782631
- AIM-HIGH Investigators; Boden WE et al. (2011). Niacin in patients with low HDL cholesterol levels receiving intensive statin therapy. N Engl J Med. 365(24):2255-2267. — PubMed PMID: 22085343
- HPS2-THRIVE Collaborative Group; Landray MJ et al. (2014). Effects of extended-release niacin with laropiprant in high-risk patients. N Engl J Med. 371(3):203-212. — PubMed PMID: 25014686
- Carlson LA (2005). Nicotinic acid: the broad-spectrum lipid drug — a 50th anniversary review. J Intern Med. — PubMed: Carlson 50-year niacin review
- Carlson LA, Rosenhamer G (1988). Reduction of mortality in the Stockholm Ischaemic Heart Disease Secondary Prevention Study by combined treatment with clofibrate and nicotinic acid. Acta Med Scand. — PubMed: Stockholm IHD study
- Anderson TJ, Boden WE, Desvigne-Nickens P, Fleg JL, Kashyap ML, McBride R, Probstfield JL; AIM-HIGH Investigators (2014). Safety profile of extended-release niacin in the AIM-HIGH trial. N Engl J Med. 371(3):288-290. — PubMed PMID: 25014706
- Sahebkar A, Reiner Ž, Simental-Mendía LE, Ferretti G, Cicero AF (2016). Effect of extended-release niacin on plasma lipoprotein(a) levels: a systematic review and meta-analysis of randomized placebo-controlled trials. Metabolism. 65(11):1664-1678. — PubMed PMID: 27733255
- Bruckert E et al. (2010). Meta-analysis of the effect of nicotinic acid alone or in combination on cardiovascular events and atherosclerosis. Atherosclerosis. — PubMed: Bruckert niacin meta-analysis
- McKenney JM et al. (1994). A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA. — PubMed: McKenney IR vs SR niacin
- Schandelmaier S et al. (2017). Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 6(6):CD009744. — PubMed PMID: 28616955
- Ferrell M et al. (2024). A terminal metabolite of niacin promotes vascular inflammation and contributes to cardiovascular disease risk. Nat Med. 30(2):424-434. — PubMed PMID: 38374343
Research Papers: Pellagra, Skin & Dermatology
- Goldberger J, Wheeler GA, Sydenstricker E (1920). A study of the relation of diet to pellagra incidence in seven textile-mill communities of South Carolina in 1916. Public Health Reports. 35(12):648. — doi:10.2307/4575517
- Chen AC et al. (2015). A phase 3 randomized trial of nicotinamide for skin-cancer chemoprevention (ONTRAC). NEJM. — PubMed: ONTRAC 2015
- Breglio KF et al. (2025). Nicotinamide for skin cancer chemoprevention. JAMA Dermatol. 161(11):1140-1147. — PubMed PMID: 40960808
- Hegyi J et al. (2004). Pellagra: dermatitis, dementia, and diarrhea. Int J Dermatol. — PubMed: pellagra clinical review
- Hartnup disease and niacin — PubMed: Hartnup disease niacin
- Topical niacinamide for acne — PubMed: topical niacinamide acne
- Niacinamide and skin barrier function — PubMed: niacinamide barrier function
- Niacinamide and hyperpigmentation — PubMed: niacinamide hyperpigmentation
- Crohn's disease and secondary pellagra — PubMed: Crohn's pellagra
- Alcoholism and pellagra — PubMed: alcoholism pellagra
- Carcinoid syndrome and secondary pellagra — PubMed: carcinoid pellagra
Research Papers: Psychiatry & Mental Health
- Hoffer A, Osmond H, Smythies J (1954). Schizophrenia: a new approach. II. Result of a year's research. J Ment Sci. — PubMed: Hoffer-Osmond 1954 schizophrenia
- Hoffer A (1971). Megavitamin B-3 therapy for schizophrenia. Can Psychiatr Assoc J. — PubMed: Hoffer megavitamin B3
- Pauling L (1968). Orthomolecular psychiatry. Science. — PubMed: Pauling orthomolecular 1968
- Niacin flush test in schizophrenia — PubMed: niacin flush schizophrenia
- Wang J et al. (2026). Blunted niacin skin flushing response in schizophrenia: a meta-analysis. Schizophr Bull. 52(4):sbaf069. — PubMed PMID: 40401804
- APA Task Force (1973). Megavitamin and orthomolecular therapy in psychiatry. American Psychiatric Association. — PubMed: APA task force 1973
- Niacin and OCD — PubMed: niacin OCD
- Niacinamide and anxiety / benzodiazepine receptor — PubMed: niacinamide anxiety
- Tryptophan-kynurenine pathway and depression — PubMed: kynurenine depression
- Quinolinic acid and neuropsychiatric disease — PubMed: quinolinic acid psychiatry
- Niacin and Alzheimer's disease (epidemiology) — PubMed: niacin Alzheimer's
Research Papers: Cross-Cutting (Forms, Safety, Mechanism)
- Linus Pauling Institute — Niacin Micronutrient Information Center (current edition) — LPI Niacin MIC
- Knip M et al. (2000). Safety of high-dose nicotinamide: a review (ENDIT trial safety arm). Diabetologia. — PubMed: Knip nicotinamide safety
- Henderson LM (1983). Niacin (review of biochemistry, metabolism, requirements). Annu Rev Nutr. — PubMed: Henderson niacin review
- Sustained-release niacin hepatotoxicity — PubMed: SR niacin hepatotoxicity
- GPR109A receptor and niacin signaling — PubMed: GPR109A receptor
- Kynurenine pathway and quinolinic acid — PubMed: kynurenine pathway
- Inositol hexanicotinate ("no-flush niacin") bioavailability — PubMed: inositol hexanicotinate
- Kaufman W (1949). The common form of joint dysfunction: its incidence and treatment. E.L. Hildreth (book; his earlier book is The common form of niacin amide deficiency disease, Yale University Press, 1943). — doi:10.1001/jama.1949.02910140071039 (JAMA review of the 1949 book)
- Jonas WB, Rapoza CP, Blair WF (1996). The effect of niacinamide on osteoarthritis: a pilot study. Inflamm Res. 45(7):330-334. — PubMed PMID: 8841834
- ENDIT — European Nicotinamide Diabetes Intervention Trial — PubMed: ENDIT trial
- NAD+ measurement and quantification methods — PubMed: NAD+ measurement methods
External Authoritative Resources
- Linus Pauling Institute — Niacin Micronutrient Information Center — the single most authoritative scientific summary of niacin biology and clinical evidence, regularly updated
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Niacin Fact Sheet for Health Professionals
- MedlinePlus — Niacin and Niacinamide
- PubMed — All research on niacin/nicotinamide adenine dinucleotide (NAD) (~100,000+ papers as of 2026)
Connections
- All Vitamins
- Vitamin B3 (Main Page)
- B3 as Nicotinamide Adenine Dinucleotide Precursor
- B3 for Cholesterol & Cardiovascular
- B3 for Pellagra & Skin
- B3 for Schizophrenia & Mental Health
- Pellagra & Niacin Deficiency
- Niacin & Cholesterol
- Niacin in Gerson Therapy
- Nicotinamide Adenine Dinucleotide / Nicotinamide Mononucleotide
- Glutathione
- Tryptophan
- Cardiovascular Disease
- Cholesterol Management
- Schizophrenia
- Obsessive-Compulsive Disorder
- Depression
- Vitamin B2 (Riboflavin)
- Vitamin B6 (Pyridoxine)
- Lipid Panel
- Deficiency
- Toxicity
- History
- Sources