Niacin for Cholesterol and Cardiovascular Disease
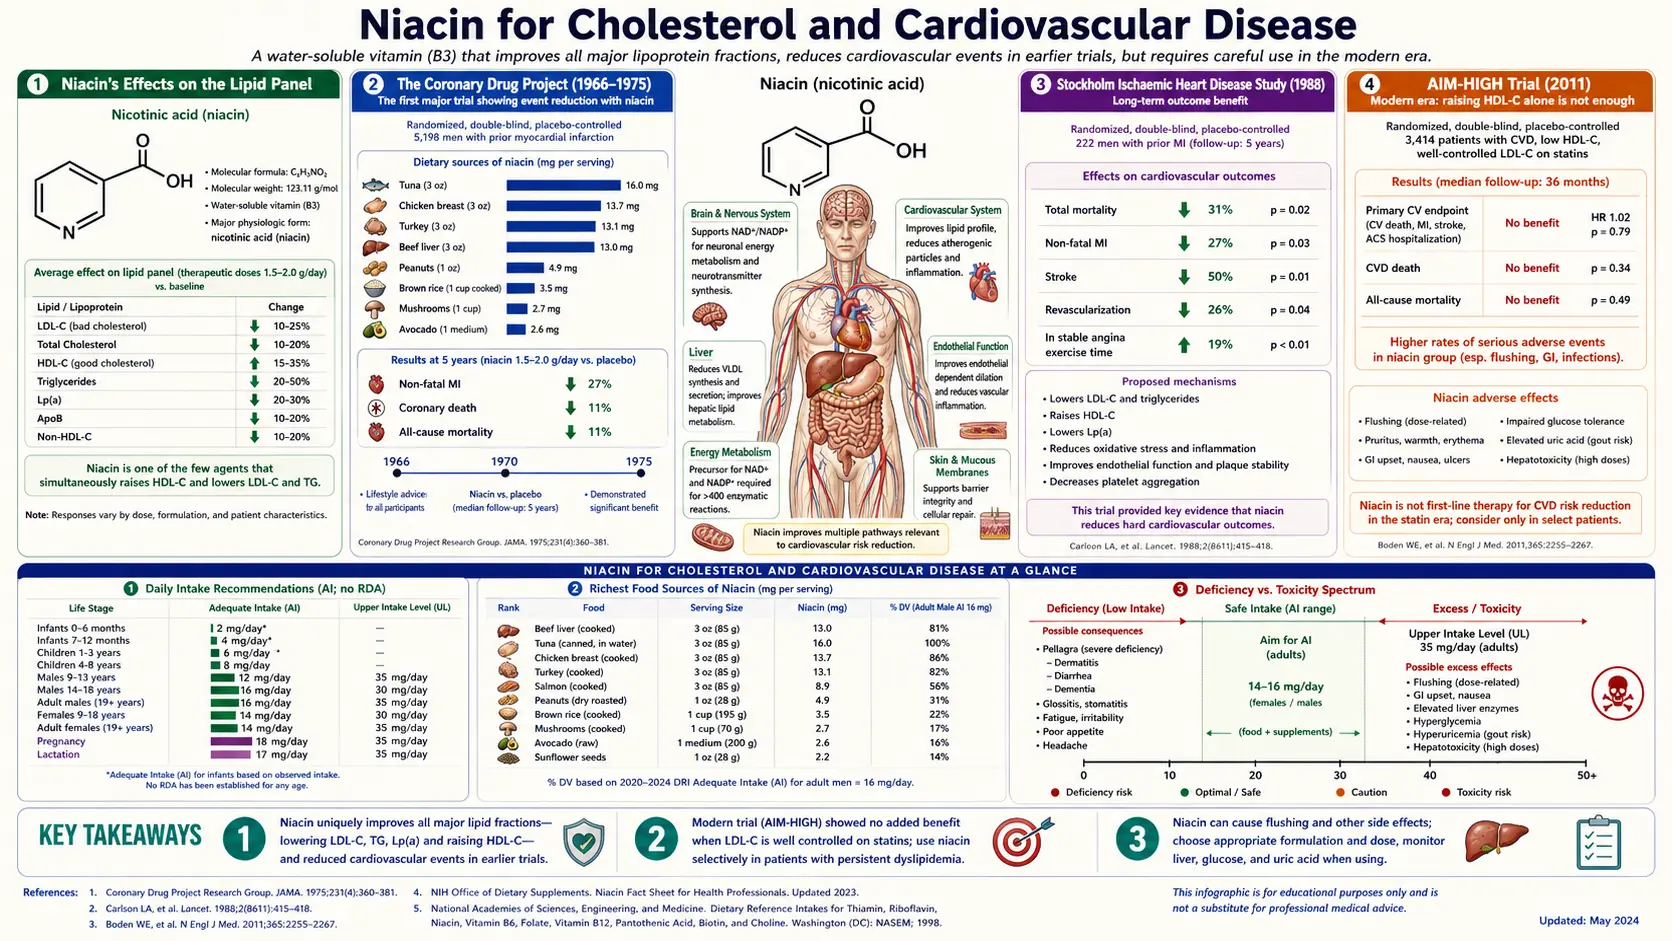
Nicotinic acid (immediate-release niacin) was the first lipid-modifying drug ever shown to reduce all-cause mortality in a randomized trial — the Coronary Drug Project (1966-1975), where niacin did not lower total deaths during the trial itself, but the mortality benefit emerged at the 15-year follow-up published by Canner in 1986. It remains the most potent high-density lipoprotein-raising agent ever discovered and one of the only readily available drugs that meaningfully lowers lipoprotein(a) [Lp(a)]. Two large negative trials in the 2010s — AIM-HIGH and HPS2-THRIVE — correctly led mainstream cardiology to abandon niacin as an add-on to optimized statin therapy, but they did not invalidate its role as monotherapy in statin-intolerant patients or as a targeted intervention for elevated Lp(a) and apolipoprotein B (ApoB). This page walks through the trial history and describes the 1-3 g/day immediate-release titration schedules still used in some lipid practice in 2026.
Table of Contents
- Niacin's Effects on the Lipid Panel
- The Coronary Drug Project (1966-1975)
- Stockholm Ischaemic Heart Disease Study (1988)
- AIM-HIGH (2011)
- HPS2-THRIVE (2014)
- Why the Modern Trials Were Negative
- Where Niacin Is Still Used
- The Lipoprotein(a) Question
- Mechanism of Lipid Modification
- Immediate-Release Titration Schedules Used in Lipid Practice
- Cautions
- Niacin Breakdown Products and Heart Risk
- Key Research Papers
- Connections
- Featured Videos
Niacin's Effects on the Lipid Panel
At pharmacological doses of immediate-release nicotinic acid (1000-3000 mg/day), no single agent matches niacin's spectrum of lipid effects:
| Lipid Marker | Niacin Effect (1-3 g/day immediate-release) | Comparable Agents |
|---|---|---|
| High-density lipoprotein (HDL) cholesterol | +15 to +35% | No drug matches this |
| Low-density lipoprotein (LDL) cholesterol | −5 to −25% | Statins (much stronger); ezetimibe; proprotein convertase subtilisin/kexin type 9 (PCSK9) inhibitors |
| Triglycerides | −20 to −50% | Fibrates; high-dose omega-3 (icosapent ethyl) |
| Lipoprotein(a) [Lp(a)] | −20 to −30% | PCSK9 inhibitors (similar); pelacarsen (investigational); apheresis |
| ApoB | −15 to −25% | Statins; ezetimibe; PCSK9 inhibitors |
| Low-density lipoprotein particle pattern | Shifts small-dense to large-buoyant (less atherogenic) | Fibrates (similar) |
One measured example: in a randomized, placebo-controlled trial published in 2008 (Maccubbin and colleagues), people with high cholesterol or mixed blood-fat problems took extended-release niacin combined with laropiprant (a flush-blocking drug) at 1 g a day for 4 weeks, then 2 g a day for 20 weeks. Compared with placebo, across weeks 12-24 the 2 g dose changed LDL cholesterol by −18.4%, HDL cholesterol by +20.0%, triglycerides by −25.8%, ApoB by −18.8% and Lp(a) by −20.8%. These are extended-release figures; the ranges in the table are given for immediate-release niacin.
The high-density lipoprotein-raising and Lp(a)-lowering effects are essentially unique to niacin among broadly available drugs. PCSK9 inhibitors (alirocumab, evolocumab) lower Lp(a) by similar magnitudes but cost $5000-7000/year — thousands of times more than niacin. The Lp(a) effect, in particular, makes niacin clinically interesting in 2026 because elevated Lp(a) is an underrecognized cardiovascular risk factor with limited therapeutic options.
For the broader picture of niacin's lipid effects in our existing literature, see Niacin & Cholesterol (the long-form article) and Cholesterol Management.
The Coronary Drug Project (1966-1975)
The Coronary Drug Project (CDP) was a landmark National Heart, Lung, and Blood Institute trial of secondary prevention in 8341 men aged 30-64 who had survived at least one myocardial infarction. Participants were randomized to one of five lipid-modifying interventions or placebo and followed for 5-8.5 years.
The five treatment arms
- Niacin (immediate-release nicotinic acid, 3000 mg/day) — 1119 patients
- Clofibrate (1800 mg/day)
- Two estrogen doses (both discontinued early for safety)
- Dextrothyroxine (discontinued early for cardiovascular harm)
- Placebo — 2789 patients
The CDP 1975 publication (JAMA)
- Niacin was the only lipid-modifying treatment to show benefit.
- 14% reduction in nonfatal recurrent myocardial infarction (MI) (p < 0.005)
- 27% reduction in cerebrovascular events (transient ischemic attack (TIA) + stroke)
- Total mortality during the active treatment period showed a trend toward benefit but did not reach significance at the 5-8 year endpoint
- Clofibrate showed no significant benefit on any cardiovascular endpoint
The Canner 1986 follow-up (Journal of the American College of Cardiology) — the mortality benefit emerges
Paul Canner reanalyzed the CDP cohort 15 years after the trial began — 9 years after active treatment had ended. The result is one of the most striking long-term follow-up findings in cardiovascular medicine:
- 11% reduction in all-cause mortality in the niacin arm versus placebo at 15 years (p = 0.0004)
- The benefit had emerged after active treatment ended — a "legacy effect" similar to what was later seen with intensive blood-sugar control in the 10-year follow-up of the UK Prospective Diabetes Study (UKPDS)
- The mortality benefit was driven primarily by reduced cardiovascular deaths but also included reduced non-cardiovascular mortality
- This made nicotinic acid the first lipid-modifying drug ever shown to reduce all-cause mortality in a randomized controlled trial
The CDP/Canner result remained the dominant cardiovascular evidence for niacin for the next 25 years, supporting widespread clinical use of niacin (often combined with bile-acid sequestrants and later with low-dose statins) for cardiovascular prevention.
Stockholm Ischaemic Heart Disease Study (1988)
Lars Carlson and Goran Rosenhamer published the Stockholm Ischaemic Heart Disease Secondary Prevention Study in Acta Medica Scandinavica in 1988. 555 post-MI patients were randomized to standard care or to combination nicotinic acid (3000 mg/day) plus clofibrate (2000 mg/day), and followed for 5 years.
- 26% reduction in all-cause mortality (p < 0.05)
- 36% reduction in ischemic heart disease mortality
- The benefit was largest in patients with the greatest triglyceride reduction
Serum cholesterol fell by 13% and triglycerides by 19% in the treatment group compared with the control group. The benefit appeared only in patients whose triglycerides were above 1.5 mmol/L, and it was most pronounced in the 44% of treated patients whose triglycerides fell by 30% or more — in that subgroup, ischemic heart disease deaths fell by 60%. The trial was open: patients knew they were taking the drugs, and the authors wrote that "caution should be exercised in the interpretation of the results as the trial was not blind."
The Stockholm study was a second positive randomized controlled trial (RCT) in the pre-statin era, reinforcing the CDP findings. Notably, both the CDP and the Stockholm trials used immediate-release nicotinic acid at gram-range doses — not extended-release formulations.
AIM-HIGH (2011)
AIM-HIGH (Atherothrombosis Intervention in Metabolic Syndrome with Low high-density lipoprotein/High Triglycerides: Impact on Global Health Outcomes) randomized 3414 patients with established atherosclerotic cardiovascular disease and atherogenic dyslipidemia (low high-density lipoprotein, high triglycerides) to:
- Extended-release niacin 1500-2000 mg/day plus simvastatin (with ezetimibe added as needed) targeting low-density lipoprotein < 80 mg/dL
- OR placebo plus the same statin regimen
The trial was stopped early at 3 years for futility. Published in the New England Journal of Medicine in 2011:
- No reduction in the primary composite endpoint (coronary heart disease (CHD) death, nonfatal myocardial infarction, ischemic stroke, hospitalization for acute coronary syndrome, or symptom-driven coronary/cerebral revascularization)
- At 2 years, niacin had raised median HDL cholesterol from 35 to 42 mg/dL, lowered triglycerides from 164 to 122 mg/dL and lowered LDL cholesterol from 74 to 62 mg/dL, but this lipid improvement did not translate into clinical events benefit: the primary endpoint occurred in 16.4% of the niacin group and 16.2% of the placebo group (hazard ratio 1.02; P = 0.79)
- A non-significant numerical excess of ischemic stroke in the niacin arm
The trial had design limitations — small placebo dose of niacin (50 mg) was given to mask the flush, which may have created lipid effects in the "placebo" group; the population had already achieved aggressive low-density lipoprotein lowering on statin before randomization, leaving little room for incremental benefit; and the trial was underpowered after early stopping.
HPS2-THRIVE (2014)
HPS2-THRIVE (Heart Protection Study 2 — Treatment of high-density lipoprotein to Reduce the Incidence of Vascular Events) was the larger trial that effectively ended mainstream cardiology's use of niacin. 25,673 patients with vascular disease already taking effective low-density lipoprotein-lowering therapy (mostly simvastatin 40 mg) were randomized to:
- Extended-release niacin 2000 mg/day plus laropiprant 40 mg/day (a prostaglandin D2 receptor antagonist intended to suppress flushing)
- OR placebo
Median follow-up was 3.9 years. Published in the New England Journal of Medicine in 2014:
- No reduction in major vascular events (13.2% on niacin-laropiprant versus 13.7% on placebo; rate ratio 0.96; P = 0.29)
- Significant increase in serious adverse events: new diabetes diagnoses (absolute excess 1.3 percentage points), and serious adverse events of the gastrointestinal (GI) system (1.0 percentage point), musculoskeletal system (0.7), skin (0.3), infection (1.4) and bleeding (0.7 percentage points)
- Serious disturbances of diabetes control: absolute excess of 3.7 percentage points versus placebo
- Increased gout, dyspepsia, diarrhea, and rash
HPS2-THRIVE was definitive that extended-release niacin plus laropiprant adds harm without benefit when given on top of optimized statin therapy. The manufacturer withdrew the extended-release niacin with laropiprant combination from the market globally. The U.S. Food and Drug Administration (FDA) pulled approval for niacin add-on to statins (the extended-release niacin with lovastatin and extended-release niacin with simvastatin combination products were withdrawn in 2016).
Why the Modern Trials Were Negative
The collapse of niacin as add-on to statins did not invalidate the earlier evidence. Several factors explain the divergence:
- Background statin therapy was the difference. CDP (1975) was conducted before statins existed — placebo patients had low-density lipoprotein of ~130-140 mg/dL on average. AIM-HIGH and HPS2-THRIVE patients had low-density lipoprotein already aggressively lowered to ~70 mg/dL by statin therapy. The marginal benefit of additional high-density lipoprotein-raising or further low-density lipoprotein-lowering at these already-low levels appears minimal.
- The "high-density lipoprotein hypothesis" itself was wrong. Mendelian randomization studies (cholesteryl ester transfer protein (CETP) variants and others) have shown that genetically determined high-density lipoprotein levels do not causally protect against coronary heart disease. High-density lipoprotein is a marker of cardiometabolic health, not a causal protective particle. Drugs that raise HDL (CETP inhibitors like dalcetrapib, evacetrapib, anacetrapib; niacin) have mostly failed to translate high-density lipoprotein gains into outcomes. The exception, anacetrapib, cut major coronary events slightly in the REVEAL trial of 30,449 patients (10.8% versus 11.8% on placebo; rate ratio 0.91), while raising HDL cholesterol by 43 mg/dL and also lowering non-HDL cholesterol by 17 mg/dL.
- HPS2-THRIVE was not a test of niacin alone. The flush-blocking drug laropiprant was given with every dose, so the trial could not separate the effects of niacin from those of laropiprant. Major vascular events were not increased (13.2% versus 13.7% on placebo); the excess was in serious non-vascular adverse events such as diabetes, infection and bleeding.
- Extended-release vs immediate-release. Both modern trials used extended-release (ER) niacin. The historical positive trials (CDP, Stockholm) used immediate-release (IR) niacin at higher peak concentrations. Whether IR vs ER pharmacokinetics matter for outcomes is an unresolved question.
- Low-density lipoprotein particle composition matters more than low-density lipoprotein concentration. Niacin's benefit may operate primarily through ApoB and Lp(a) reduction and low-density lipoprotein-particle-size shift, which are not directly captured by standard lipid panels.
The honest reading of the totality of evidence: niacin works when it is the primary lipid-modifying agent in patients who would otherwise have untreated dyslipidemia; it does not add incremental benefit when stacked on top of optimized statin therapy.
Where Niacin Is Still Used
In 2026 cardiology practice, the situations in which some clinicians still use niacin are narrower than they were in 1995:
- Statin intolerance. Patients with statin-associated muscle symptoms, statin-induced liver enzyme elevation, or PCSK9-inhibitor cost barriers are the group for whom an alternative lipid-modifying agent is sought. Immediate-release niacin at 1-3 g/day is used by some clinicians as monotherapy for low-density lipoprotein reduction and high-density lipoprotein raising, with the caveat that low-density lipoprotein reduction is much weaker than with statins.
- Elevated Lp(a). Lp(a) above 50 mg/dL (or 125 nmol/L) is an independent cardiovascular risk factor with limited therapeutic options. Niacin at 1-2 g/day reduces Lp(a) by 20-30%. In the 2026 Lp(a)HORIZON trial, pelacarsen, an injected antisense Lp(a) drug, lowered Lp(a) but did not lower major cardiovascular events (see The Lipoprotein(a) Question below). Niacin remains one of the least expensive Lp(a)-lowering options, but no trial has shown that lowering Lp(a) with niacin prevents heart attacks or strokes.
- Severe hypertriglyceridemia. When triglycerides exceed 500 mg/dL (pancreatitis risk), niacin is one of several agents (along with fibrates, omega-3) that can rapidly bring triglycerides down.
- Atherogenic dyslipidemia in metabolic syndrome WITHOUT existing statin therapy. Patients with low high-density lipoprotein, high triglycerides, small-dense low-density lipoprotein who are not yet on statins (often because of preference or partial intolerance) are another group in whom niacin's spectrum of lipid effects is used.
- Not supported by the trials: Adding niacin on top of optimized high-intensity statin + ezetimibe therapy in patients already at low-density lipoprotein goal. AIM-HIGH and HPS2-THRIVE found no reduction in events in this setting, and HPS2-THRIVE found more serious adverse events.
For the broader cardiovascular workup, see Cardiovascular Disease and Lipid Panel.
The Lipoprotein(a) Question
Lipoprotein(a) is a low-density lipoprotein-like particle with an additional apolipoprotein(a) covalently bound. Lp(a) levels are 80-90% genetically determined — you inherit your Lp(a) at birth and it changes little over a lifetime. Elevated Lp(a) (above 50 mg/dL or 125 nmol/L) is an independent risk factor for atherosclerotic cardiovascular disease and aortic stenosis, with the relative risk roughly equivalent to elevated low-density lipoprotein.
The problem: until recently, almost no drug meaningfully lowered Lp(a):
- Statins: no effect or slight increase
- Ezetimibe: no effect
- Niacin: 20-30% reduction — the strongest of the available oral drugs
- PCSK9 inhibitors: 20-30% reduction, similar to niacin but ~1000x more expensive
- Pelacarsen (antisense oligonucleotide, a monthly injection): 80% reduction in phase 2 trials; in the phase 3 Lp(a)HORIZON outcomes trial (2026), Lp(a) at 12 months was 64.4 nmol/L on pelacarsen versus 233.4 nmol/L on placebo, but major cardiovascular events were not reduced
- Lipoprotein apheresis: dramatic reduction but requires weekly outpatient treatment, expensive, reserved for severe cases
The big test of lowering Lp(a) has now reported. The Lp(a)HORIZON trial, published in the New England Journal of Medicine in November 2026, enrolled 8,350 people who already had cardiovascular disease and an Lp(a) level of at least 70 mg/dL, and gave them a monthly injection of pelacarsen (80 mg) or placebo. At 12 months, Lp(a) was 64.4 nmol/L on pelacarsen and 233.4 nmol/L on placebo. Over a median of 4.7 years, a major adverse cardiovascular event (death from cardiovascular causes, nonfatal heart attack, nonfatal stroke or urgent coronary revascularization) occurred in 12.3% of the pelacarsen group and 12.1% of the placebo group (hazard ratio 1.02; P = 0.76). The result was the same in people whose Lp(a) was at least 90 mg/dL (12.3% in both groups). The authors concluded that "pelacarsen did not result in a lower risk of major adverse cardiovascular events than placebo."
The Lp(a)-lowering effect is one of niacin's most enduring claims to clinical relevance, but lowering Lp(a) by itself has not yet been shown to prevent cardiovascular events with any drug, niacin included.
Mechanism of Lipid Modification
Niacin's lipid-modifying effects derive from multiple convergent mechanisms:
- Inhibition of adipose triglyceride lipase (ATGL) via GPR109A. GPR109A (also called HCA2 or HCAR2) is the niacin receptor expressed on adipocytes. Activation suppresses lipolysis, reducing free fatty acid (FFA) flux to the liver. Lower hepatic FFA delivery reduces very-low-density lipoprotein (VLDL) assembly and secretion, lowering triglycerides and very-low-density lipoprotein-derived low-density lipoprotein.
- Inhibition of DGAT2 (diacylglycerol acyltransferase 2) in hepatocytes, reducing triglyceride synthesis and very-low-density lipoprotein assembly.
- Inhibition of hepatic ApoB synthesis and increased ApoB intracellular degradation, lowering all ApoB-containing particles (VLDL, intermediate-density lipoprotein (IDL), LDL, Lp(a)).
- Increased apolipoprotein A-I (ApoA-I) production in the liver, raising high-density lipoprotein particle number.
- Reduced high-density lipoprotein catabolism through decreased adenosine triphosphate (ATP) synthase beta-chain receptor activity, extending high-density lipoprotein plasma residence time.
- Reduced Lp(a) production through downregulation of apolipoprotein(a) gene expression in hepatocytes.
The flush is a side effect of GPR109A activation on Langerhans cells in the skin, where it triggers prostaglandin D2 release and consequent vasodilation. This is separate from the adipose GPR109A effect that drives lipid modification.
Immediate-Release Titration Schedules Used in Lipid Practice
Clinicians who use immediate-release niacin describe a slow step-up schedule like the one below; it is reported practice, not a tested trial protocol. For comparison, the 1994 McKenney trial raised IR niacin through 500, 1000, 1500, 2000 and 3000 mg/day, each step lasting 6 weeks.
Pre-treatment workup
- Baseline lipid panel including ApoB and Lp(a)
- Baseline alanine aminotransferase (ALT), aspartate aminotransferase (AST), bilirubin
- Baseline fasting glucose and hemoglobin A1c (HbA1c)
- Baseline uric acid
- Patient education on flush expectation and management
Titration schedule
- Weeks 1-2: 100 mg IR nicotinic acid with the largest meal of the day. Some schedules add aspirin 325 mg 30 minutes before the dose during the first 1-2 weeks to lessen flushing.
- Weeks 3-4: 250 mg with the largest meal (or 100 mg twice daily); flush tolerance is reassessed.
- Weeks 5-6: 500 mg once daily with the largest meal, or 250 mg twice daily.
- Weeks 7-8: 500 mg twice daily (1 g/day total).
- Weeks 9-12: Further steps toward 1500-2000 mg/day in 2-3 divided doses with meals when lipid targets have not been reached.
- Maintenance: 1000-2000 mg/day in divided doses for most patients; up to 3000 mg/day in selected cases with rigorous monitoring.
Monitoring schedule
- Baseline, 6 weeks, 12 weeks, then every 6 months: alanine aminotransferase, aspartate aminotransferase, bilirubin, fasting glucose, hemoglobin A1c, uric acid
- Baseline and every 3-6 months: lipid panel (full panel including ApoB, Lp(a))
- Usual stopping points: alanine aminotransferase exceeds 3x upper limit of normal, fasting glucose rises > 30 mg/dL, gout flare occurs, persistent intolerable flushing, or new significant adverse effect
Formulation and liver safety
The schedules above use immediate-release (IR) nicotinic acid. Brand-name preparations have largely disappeared from the US market; generic IR niacin is sold as a supplement. Sustained-release (SR) niacin causes less flushing but carries a much higher risk of liver injury at lipid-modifying doses: in the 1994 McKenney trial in JAMA, which compared the two forms directly, 12 of the 23 patients (52%) taking SR niacin developed liver toxicity and none of the 23 taking IR niacin did, and the authors concluded that the SR form is hepatotoxic and "should be restricted from use." That trial did not test the extended-release (ER) form used at 1.5-2 g/day in AIM-HIGH and HPS2-THRIVE.
Cautions
- HEPATOTOXICITY — sustained-release nicotinic acid at >1 g/day is the single most important contraindication. Sustained-release niacin formulations have caused elevated transaminases, cholestatic jaundice, and fulminant hepatic failure at lipid-modifying doses. The schedules described above use immediate-release niacin, check liver enzymes at set intervals, and stop the drug when alanine aminotransferase rises above 3 times the upper limit of normal (ULN).
- Hyperglycemia. Niacin raises fasting glucose by ~5-10 mg/dL and hemoglobin A1c by ~0.3-0.4 in many patients via increased lipolysis and free fatty acid release driving hepatic gluconeogenesis. In people with diabetes, blood sugar is usually checked more closely after niacin is started, and in HPS2-THRIVE serious disturbances of diabetes control were 3.7 percentage points more common on niacin-laropiprant than on placebo. In well-controlled diabetes, some clinicians judge the trade-off acceptable; in poorly controlled diabetes, other lipid-modifying drugs are usually chosen.
- Gout and hyperuricemia. Niacin competes with uric acid for renal tubular excretion, raising serum uric acid by 0.5-1.5 mg/dL and potentially triggering gout flares. Active gout and symptomatic high uric acid (hyperuricemia) are the settings where this matters most; in people with past gout who currently have no symptoms, some clinicians give a uric-acid-lowering drug (allopurinol or febuxostat) alongside niacin.
- Peptic ulcer activation. Niacin increases gastric acid secretion, which makes active peptic ulcer disease a setting where niacin is generally not used. People with a past peptic ulcer who take a proton pump inhibitor (PPI) or H2 blocker have been given niacin with caution.
- Flush. Universal at gram-range IR doses initially. Slow step-up, aspirin taken beforehand and taking the dose with food are the usual ways it is lessened, and the flush diminishes substantially over 1-2 weeks of consistent dosing.
- Pregnancy. Pharmacological niacin doses are not established as safe in pregnancy.
- Drug interactions: warfarin (niacin may strengthen its effect — the international normalized ratio (INR) is usually checked more often after niacin is started); statin myopathy risk modestly increased; bile-acid sequestrants reduce niacin absorption (doses are usually taken 4 hours apart).
- Lp(a) target ambiguity. While niacin lowers Lp(a) by 20-30%, no randomized trial has yet shown that Lp(a) lowering by any drug translates into hard cardiovascular outcomes. A large outcome trial of a drug made to lower Lp(a), Lp(a)HORIZON with pelacarsen (2026), found no fewer major cardiovascular events despite a large fall in Lp(a). Niacin for Lp(a) remains a mechanistic bet, not a proven outcome.
Niacin Breakdown Products and Heart Risk
When the body has more niacin than it needs, it breaks the excess down into end products (terminal metabolites). Two of these are called 2PY (N1-methyl-2-pyridone-5-carboxamide) and 4PY (N1-methyl-4-pyridone-3-carboxamide). A 2024 study in Nature Medicine (Ferrell and colleagues) measured them in blood samples from several groups of patients:
- In two validation groups, one in the US (2,331 people) and one in Europe (832 people), higher blood levels of 2PY and 4PY went with a higher 3-year risk of major adverse cardiovascular events. The adjusted hazard ratios were 1.64 and 2.02 for 2PY, and 1.89 and 1.99 for 4PY, in the US and European groups respectively.
- A gene variant linked to higher 2PY and 4PY levels was also linked to higher blood levels of a blood-vessel inflammation marker, soluble vascular adhesion molecule 1 (sVCAM-1).
- In mice, 4PY at physiological levels (but not 2PY) switched on VCAM-1 and made white blood cells stick to the blood-vessel lining.
The human findings come from an association study, not a trial, and the inflammation result comes from mice, so the study shows a link between these niacin breakdown products and heart risk rather than proof that they cause heart events in people.
Key Research Papers
- Coronary Drug Project Research Group (1975). Clofibrate and niacin in coronary heart disease. JAMA. 1975;231(4):360-381. — PubMed PMID: 1088963
- Canner PL et al. (1986). Fifteen year mortality in Coronary Drug Project patients: long-term benefit with niacin. JACC. — PubMed PMID: 3782631
- Carlson LA, Rosenhamer G (1988). Reduction of mortality in the Stockholm Ischaemic Heart Disease Secondary Prevention Study by combined treatment with clofibrate and nicotinic acid. Acta Med Scand. — PubMed PMID: 3287837
- AIM-HIGH Investigators / Boden WE et al. (2011). Niacin in patients with low HDL cholesterol levels receiving intensive statin therapy. NEJM. — PubMed PMID: 22085343
- HPS2-THRIVE Collaborative Group (2014). Effects of extended-release niacin with laropiprant in high-risk patients. NEJM. — PubMed PMID: 25014686
- Carlson LA (2005). Nicotinic acid: the broad-spectrum lipid drug — a 50th anniversary review. J Intern Med. — PubMed PMID: 16018787
- Bruckert E et al. (2010). Meta-analysis of the effect of nicotinic acid alone or in combination on cardiovascular events and atherosclerosis. Atherosclerosis. — PubMed PMID: 20079494
- McKenney JM et al. (1994). A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA. — PubMed PMID: 8309029
- Maccubbin D, Bays HE, Olsson AG, et al. (2008). Lipid-modifying efficacy and tolerability of extended-release niacin/laropiprant in patients with primary hypercholesterolaemia or mixed dyslipidaemia. Int J Clin Pract. 2008;62(12):1959-1970. — PubMed PMID: 19166443
- Holman RR, Paul SK, Bethel MA, Matthews DR, Neil HA (2008). 10-year follow-up of intensive glucose control in type 2 diabetes. N Engl J Med. 2008;359(15):1577-1589. — PubMed PMID: 18784090
- HPS3/TIMI55–REVEAL Collaborative Group; Bowman L, Hopewell JC, Chen F, et al. (2017). Effects of anacetrapib in patients with atherosclerotic vascular disease. N Engl J Med. 2017;377(13):1217-1227. — PubMed PMID: 28847206
- Ferrell M, Wang Z, Anderson JT, et al. (2024). A terminal metabolite of niacin promotes vascular inflammation and contributes to cardiovascular disease risk. Nat Med. 2024;30(2):424-434. — PubMed PMID: 38374343
- Cho L, Nicholls SJ, Frndak S, et al.; Lp(a)HORIZON Investigators (2026). Pelacarsen and cardiovascular outcomes in patients with high lipoprotein(a). N Engl J Med. Published online 2026 Nov 7. — PubMed PMID: 43001734
- Niacin and Lp(a) reduction — PubMed
- Niacin and ApoB lowering — PubMed
- GPR109A receptor and niacin lipid mechanism — PubMed
- Niacin in statin-intolerant patients — PubMed
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin B3 Overview
- B3 Benefits Hub
- B3 as Nicotinamide Adenine Dinucleotide Precursor
- B3 for Pellagra & Skin
- B3 for Schizophrenia & Mental Health
- Niacin & Cholesterol (Original Article)
- Cardiovascular Disease
- Cholesterol Management
- Atherosclerosis
- Coronary Artery Disease
- Lipid Panel
- Niacin in Gerson Therapy
- Alpha Lipoic Acid
- Uric Acid
- Deficiency
- Toxicity
- History
- Sources