Niacin for Schizophrenia and Mental Health — Orthomolecular Psychiatry
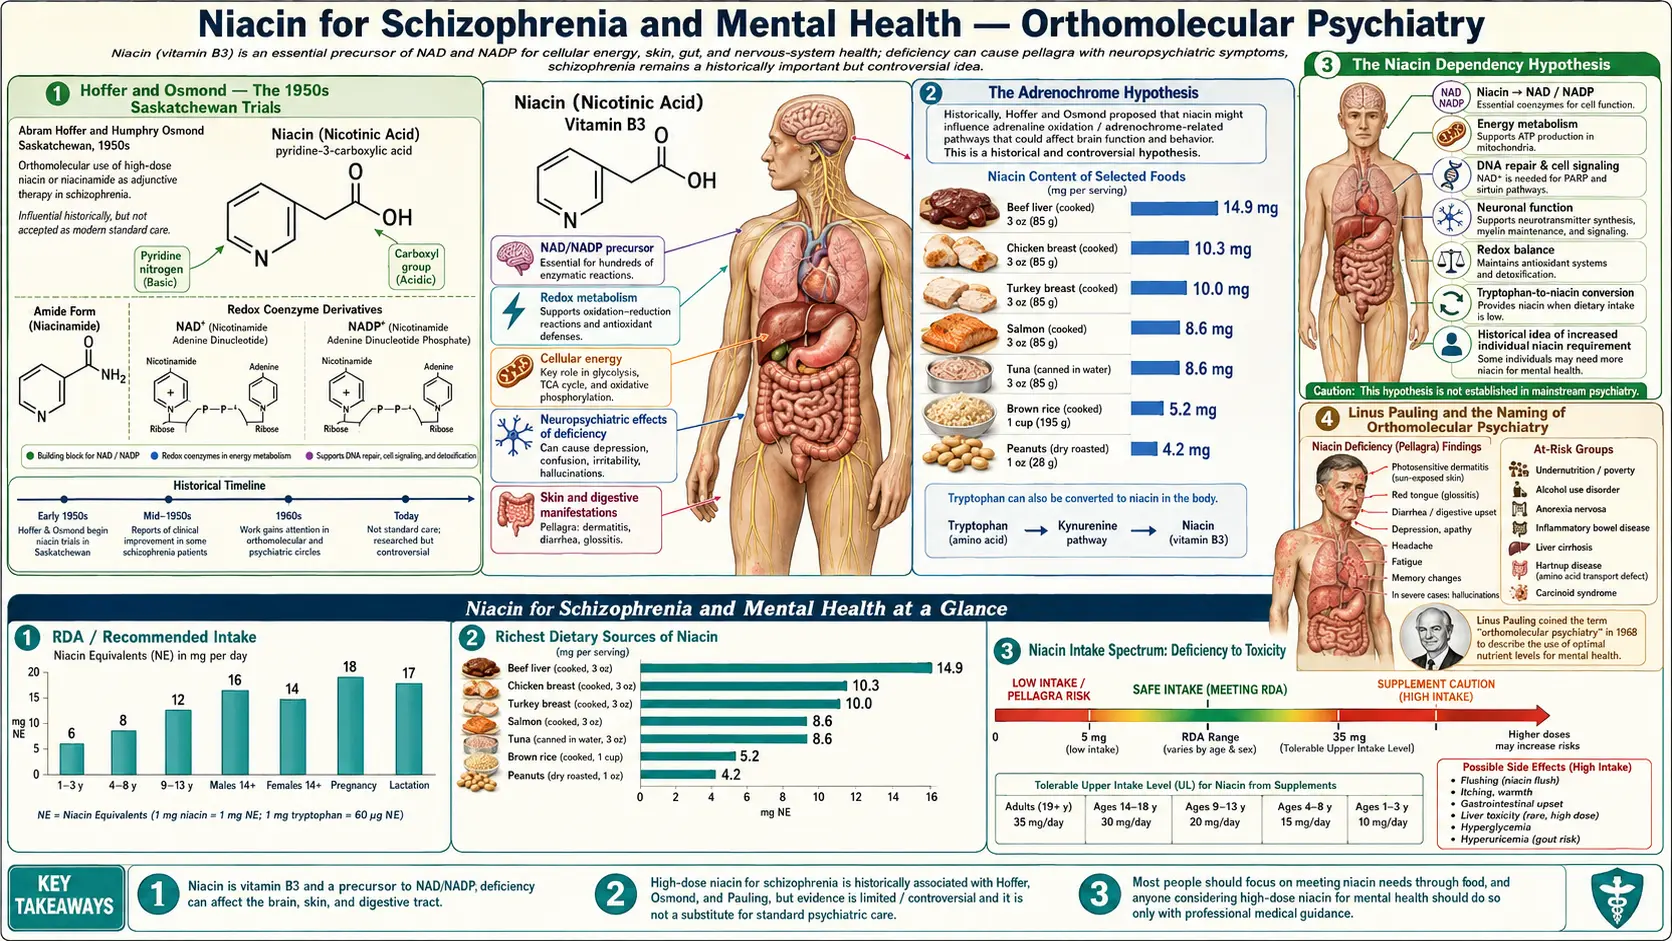
In the 1950s, Saskatchewan psychiatrists Abram Hoffer and Humphry Osmond hypothesized that schizophrenia was a niacin-dependency disorder — an inability to convert tryptophan to nicotinamide adenine dinucleotide (NAD+) at normal rates, leading to accumulation of psychotomimetic metabolites. They ran the first double-blind placebo-controlled trials in the history of psychiatry, and reported improved outcomes with 3-18 g/day niacin. Linus Pauling embraced their work in 1968 and coined the term "orthomolecular psychiatry." Later controlled trials in the 1970s by Wittenborn and others failed to replicate the dramatic effects, and mainstream psychiatry largely abandoned the approach by 1980. But the underlying biochemistry remained interesting: the niacin flush test (a blunted flush in 58.5% of people with schizophrenia versus 11.8% of healthy people, in a 2026 meta-analysis of 32 studies) is a real and replicated endophenotype, frank pellagra causes psychosis that fully reverses with niacin, and the tryptophan-kynurenine-quinolinic acid axis remains an active area of psychiatric research. This page walks the history honestly, separates the documented from the overstated, and locates the realistic modern place of high-dose B3 in psychiatry.
Table of Contents
- Hoffer and Osmond — The 1950s Saskatchewan Trials
- The Adrenochrome Hypothesis
- The Niacin Dependency Hypothesis
- Linus Pauling and the Naming of Orthomolecular Psychiatry
- The Niacin Flush Test — A Real Endophenotype
- Why Later Controlled Trials Disappointed
- The 1973 APA Task Force Verdict
- Pellagra Psychosis — The Genuine Niacin-Psychosis Link
- The Tryptophan-Kynurenine-Quinolinic Acid Axis
- Niacin in Obsessive-Compulsive Disorder, Anxiety, and Depression
- The Realistic Modern Place of High-Dose B3
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Hoffer and Osmond — The 1950s Saskatchewan Trials
Abram Hoffer (a Canadian biochemist and psychiatrist, PhD in biochemistry from the University of Minnesota, MD from the University of Toronto) and Humphry Osmond (a British psychiatrist who coined the word "psychedelic" in correspondence with Aldous Huxley) worked together at the Saskatchewan Hospital in Weyburn starting in 1952. They were responsible for one of the most ambitious clinical research programs in the early history of biological psychiatry.
Their niacin treatment trial, published as “Treatment of schizophrenia with nicotinic acid and nicotinamide” (Hoffer, Osmond, Callbeck, and Kahan, Journal of Clinical and Experimental Psychopathology, 1957), was one of the very first double-blind placebo-controlled trials in psychiatry — predating the modern randomized controlled trial (RCT) era. (An earlier 1954 paper by Hoffer, Osmond, and Smythies in the Journal of Mental Science reported the first year of their research program.) The design:
- 30 newly admitted acutely psychotic schizophrenia patients
- Randomized to nicotinic acid 3 g/day, nicotinamide 3 g/day, or placebo
- Outcomes assessed at 1 month, 1 year, and longer
Hoffer and Osmond reported a roughly doubled recovery rate in the niacin-treated arms compared to placebo at the 1-year mark, with sustained improvement in subsequent follow-up cohorts. They subsequently conducted larger non-randomized series in thousands of patients over the next two decades, consistently reporting that early intervention with high-dose niacin (3-18 g/day, often combined with vitamin C, vitamin B6, and zinc) significantly improved long-term outcomes.
Their work was an explicit challenge to the psychoanalytic establishment of the 1950s — which insisted schizophrenia was a disorder of childhood trauma and mother-blame — and predated the antipsychotic-receptor era by 20 years.
The Adrenochrome Hypothesis
Hoffer and Osmond's mechanistic hypothesis was based on chemistry that was state-of-the-art for the 1950s and remains chemically plausible (though clinically unconfirmed):
- Adrenaline oxidation product. Adrenochrome is the spontaneous oxidation product of adrenaline (epinephrine) — a pink-violet molecule formed when adrenaline encounters oxygen. Hoffer and Osmond proposed that schizophrenia patients had impaired ability to metabolize adrenaline normally, leading to accumulation of psychotomimetic adrenochrome and related quinone derivatives.
- Methylation defect. Normal adrenaline metabolism via catechol-O-methyltransferase (COMT) requires methyl-group donation. Hoffer and Osmond proposed that schizophrenia patients had a methylation defect, with adrenaline shunted into the oxidative pathway producing adrenochrome.
- Niacin as methyl sink. The hypothesis: niacin, being methylated to N1-methylnicotinamide before urinary excretion, acts as a "methyl sink" that draws methyl groups away from the adrenaline-oxidation pathway. This is paradoxical — normally we think of niacin supporting methylation, not depleting it — but the hypothesis was that B3 at gram-range doses competed with adrenaline for the available methylation capacity.
- Adrenochrome experiments. Hoffer, Osmond, and others reported that small doses of synthesized adrenochrome injected into healthy volunteers produced psychotomimetic effects resembling schizophrenia — supporting (though not proving) the hypothesis.
The adrenochrome hypothesis was never decisively confirmed or refuted. Later research showed that adrenochrome is much more chemically reactive than originally appreciated and is unlikely to accumulate in the bloodstream long enough to produce psychotomimetic effects in vivo. But the broader insight — that abnormal one-carbon metabolism might contribute to psychiatric disease — has been validated repeatedly in modern psychiatric biochemistry (folate, B12, methylenetetrahydrofolate reductase (MTHFR), homocysteine).
The Niacin Dependency Hypothesis
Hoffer's second hypothesis was more durable: that a subset of schizophrenia patients suffer from a partial niacin-dependency disorder — analogous to but milder than the inborn errors of B6 dependency or biotin dependency that pediatricians recognized. The argument:
- Pellagra causes psychosis. Severe niacin deficiency reliably produces psychiatric symptoms identical to many schizophrenia presentations — auditory hallucinations, delusions, paranoia, disorganized thinking, catatonia. This is documented across the southern pellagra epidemic.
- Subclinical niacin deficiency might cause subclinical psychosis. If frank pellagra causes frank psychosis, perhaps subclinical niacin insufficiency (or impaired nicotinamide adenine dinucleotide synthesis from tryptophan) causes subclinical psychotic-spectrum symptoms in genetically susceptible individuals.
- Pharmacological-dose niacin might saturate any partial conversion defect by providing massive amounts of substrate, bypassing the rate-limiting enzyme.
- The kynurenine pathway connection. Schizophrenia patients have well-documented abnormalities in tryptophan metabolism — elevated kynurenic acid in cerebrospinal fluid (CSF), altered IDO (indoleamine 2,3-dioxygenase) activity in inflammation. These abnormalities are biochemically connected to nicotinamide adenine dinucleotide synthesis.
The niacin-dependency hypothesis remains compatible with modern findings about kynurenine pathway dysregulation in schizophrenia, even if the original clinical claims of dramatic recovery rates have not been replicated in controlled trials.
Linus Pauling and the Naming of Orthomolecular Psychiatry
Linus Pauling, the only person to win two unshared Nobel Prizes (Chemistry 1954, Peace 1962), encountered Hoffer's work in the 1960s and was sufficiently impressed to publish a programmatic paper in Science in 1968 titled "Orthomolecular Psychiatry." Pauling argued:
- Mental illness frequently involves "abnormal molecular environments of the brain" — abnormal concentrations of substances normally present (vitamins, minerals, amino acids, neurotransmitter precursors)
- Treatment should aim to restore the "right molecules" to the right concentrations — hence "ortho-molecular"
- This is a category of medicine distinct from pharmacological psychiatry (which uses drugs not normally present in the body) and from psychotherapy
- The high-dose niacin work of Hoffer and Osmond was the founding example of this approach
Pauling's intellectual sponsorship gave the orthomolecular movement enormous credibility and institutional momentum through the 1970s, including the founding of the Linus Pauling Institute and an entire alternative-medicine journal infrastructure (Journal of Orthomolecular Medicine). Pauling himself became increasingly associated with high-dose vitamin C megadosing, which somewhat tarnished the broader orthomolecular brand when his cold and cancer claims for vitamin C did not survive rigorous trial replication.
The deeper insight of orthomolecular psychiatry — that nutritional status influences brain chemistry and that some psychiatric patients have correctable nutritional deficiencies — has been substantially validated. Folate deficiency depression, B12 deficiency psychosis, thiamine-related Korsakoff syndrome, pellagra psychosis, and B6-related epilepsy are all clinically recognized. The narrower claim — that gram-range niacin specifically cures schizophrenia — has not been validated in modern controlled trials.
The Niacin Flush Test — A Real Endophenotype
The niacin flush test is one of the most replicated biochemical findings in schizophrenia research. The basic observation:
- Healthy individuals reliably flush when exposed to nicotinic acid (orally or topically as a methyl nicotinate patch) — the prostaglandin D2 vasodilation triggered through the niacin receptor GPR109A (G-protein-coupled receptor 109A), discussed in the cardiovascular-benefits page.
- A 2026 meta-analysis of 32 studies found a blunted flush response in 58.5% of people with schizophrenia, against 11.8% of healthy people, to niacin/methyl-nicotinate challenge. An early 1997 study by Hudson and colleagues found that 12 of 28 people with schizophrenia (42.9%) did not flush after a 200 mg niacin dose, against 1 of 18 with bipolar disorder and none of 28 healthy controls.
- The blunted flush is most pronounced in first-episode psychosis patients and in unaffected first-degree relatives at increased genetic risk — suggesting it is a trait marker (endophenotype), not a state marker or medication artifact.
- The effect has been reported as independent of antipsychotic medication status, smoking, and sex. The 2026 meta-analysis found that the flush was weaker (standardized mean difference -0.90), slower and less sensitive in schizophrenia, and that the test method, the geographical region and age all changed the results — its authors call for one standard way of running the test.
The mechanism is thought to involve abnormalities in arachidonic acid metabolism, prostaglandin D2 synthesis, or GPR109A receptor signaling in Langerhans cells — possibly tied to broader essential fatty acid abnormalities documented in schizophrenia (low membrane arachidonic acid, low docosahexaenoic acid (DHA), altered phospholipase A2 activity).
The clinical implications:
- The niacin flush test is a candidate biomarker for stratifying schizophrenia patients into biological subtypes — the "flush-blunted subgroup" may represent a more biologically distinct population than the broader schizophrenia diagnosis
- It does NOT mean these patients are niacin-deficient or that niacin supplementation will treat their psychosis — the flush abnormality reflects altered prostaglandin signaling, not B3 status per se
- It does support the broader idea that schizophrenia is biochemically heterogeneous and that biological subtypes might respond to different interventions
- An early test of that idea: in a 2026 randomized trial of 99 people with schizophrenia, adding omega-3 fatty acids to standard medicine for 21 days improved the niacin flush response, which did not change with medicine alone. In an exploratory analysis, people who started with a blunted flush showed the largest gain in flush response, with symptom scores moving in a favourable direction. The authors suggest the flush test could help pick out who responds to such add-on treatment.
Why Later Controlled Trials Disappointed
The 1960s and 1970s saw multiple attempts to replicate Hoffer and Osmond's dramatic schizophrenia results in larger and more rigorously controlled trials. Most were negative or marginally positive:
- The Wittenborn trials (1973-1974) — conducted at Rutgers, did not find significant niacin benefit over placebo in well-controlled schizophrenia samples.
- The Ban et al. trials (1971) — multicenter Canadian replication attempts, mixed results overall not supporting Hoffer's original effect sizes.
- The Greenbaum et al. and Petrie et al. studies of the early 1970s — negative or marginally positive.
Several reasons emerged for the divergence between Hoffer/Osmond's original positive results and the later negative trials:
- Selection bias. Hoffer and Osmond's original patient population may have included a higher proportion of patients with acute-onset, treatment-naive presentations — the demographic most likely to remit spontaneously regardless of treatment. Later trials in chronic, treatment-refractory populations had less room for any intervention to show benefit.
- The rise of antipsychotic drugs. By the late 1960s, chlorpromazine and other dopamine receptor antagonists were established as effective treatments. The comparison condition for niacin was no longer "no treatment" but "no treatment plus first-generation antipsychotics" — a much higher bar.
- Dose and form variability. Trials used different doses, different forms (nicotinic acid vs nicotinamide), different cotreatments (B-vitamins, vitamin C, zinc, with vs without).
- Endpoint differences. Hoffer's "recovery" criteria emphasized social functioning, work return, and family relationships rather than symptom rating scales. Later trials used standardized symptom scales (such as the Brief Psychiatric Rating Scale, BPRS) which captured different aspects of outcome.
- Possible biological subtype effect. If only a niacin-dependent subset of schizophrenia patients responds to high-dose niacin — perhaps 20-30% of the population — an unstratified trial may show modest aggregate benefit that doesn't reach significance, even though within-subset benefit could be large. Hoffer himself argued this point repeatedly.
The 1973 APA Task Force Verdict
In 1973 the American Psychiatric Association convened a task force to evaluate megavitamin and orthomolecular therapy in psychiatry. Their report was sharply critical of Hoffer and Osmond's clinical claims, concluding that the rigorous controlled trials did not support the original effect sizes and that orthomolecular psychiatry should not be considered established clinical practice.
Hoffer responded angrily that the task force had cherry-picked negative trials and ignored methodological flaws in those trials, and that the task force chair had pre-existing biases against the orthomolecular approach. The exchange remains a classic episode in the history of clinical-research politics, with arguments on both sides.
The practical effect: by 1980, mainstream academic psychiatry had largely abandoned megadose niacin therapy. The orthomolecular movement continued in alternative medicine and in patient-advocate communities (the International Schizophrenia Foundation, the Journal of Orthomolecular Medicine) but largely disappeared from mainstream psychiatric training and practice. Hoffer continued treating patients with his protocols until his death in 2009 at age 91, maintaining that his original results were real and reproducible in clinical practice even if they had not been replicated in randomized trials.
Modern psychiatric researchers occasionally revisit the orthomolecular hypothesis with newer tools — the niacin flush test endophenotype work, kynurenine pathway imaging, and the recent interest in inflammation-based subtypes of schizophrenia — but no recent randomized trial has supported a return to gram-range niacin as first-line schizophrenia treatment.
Pellagra Psychosis — The Genuine Niacin-Psychosis Link
Setting aside the schizophrenia-treatment debate, one robust fact is established: severe niacin deficiency reliably causes psychosis. The psychiatric manifestations of pellagra (see also Pellagra & Skin) include:
- Irritability and anxiety (early)
- Depression and apathy
- Insomnia and fatigue
- Confusion, disorientation, memory loss
- Hallucinations (auditory and visual)
- Delusions and paranoid ideation
- Disorganized speech and behavior
- Frank dementia in end-stage disease
This is not "schizophrenia-like" — it is clinically indistinguishable from acute psychotic episodes in many cases. Historical southern asylums in the early 20th century were full of pellagra-psychosis patients who would have recovered fully with niacin replacement, had the cause been recognized.
Modern clinical implication: for a person with new-onset psychosis who has risk factors for niacin deficiency — chronic alcoholism, malabsorption, Crohn's disease, carcinoid syndrome, isoniazid therapy, Hartnup disease, severe malnutrition, anorexia nervosa — orthomolecular and integrative practitioners describe an empirical trial of niacin replacement (along with full B-complex) as part of the initial workup. The improvement, if niacin deficiency is the cause, is often dramatic over 24-72 hours and confirms the diagnosis better than any laboratory test.
The Tryptophan-Kynurenine-Quinolinic Acid Axis
One area where orthomolecular intuitions have been substantially validated by modern research is the tryptophan-kynurenine pathway in psychiatry. The basic biochemistry:
- Tryptophan can be metabolized through the serotonin pathway (tryptophan → 5-HTP → serotonin → melatonin) or through the kynurenine pathway (tryptophan → kynurenine → multiple branches including the de novo nicotinamide adenine dinucleotide synthesis route)
- Roughly 95% of tryptophan normally goes through the kynurenine pathway; only ~5% goes through serotonin synthesis
- The first step of the kynurenine pathway is catalyzed by IDO in immune cells and tissues, and by TDO (tryptophan 2,3-dioxygenase) in liver
- IDO is strongly induced by inflammatory cytokines — particularly interferon-gamma and tumor necrosis factor-α
In states of chronic inflammation (autoimmune disease, chronic infection, depression, schizophrenia), IDO induction shunts more tryptophan into the kynurenine pathway, with two consequences:
- Serotonin substrate depletion — less tryptophan available for serotonin synthesis, contributing to depression and sleep disturbance
- Accumulation of quinolinic acid — a downstream kynurenine metabolite that is a potent N-methyl-D-aspartate (NMDA) receptor agonist and neurotoxin, implicated in depression severity, suicidality, human immunodeficiency virus-associated dementia, and possibly schizophrenia symptom severity. The pooled blood studies point to this slide toward quinolinic acid in mood disorders, but not in schizophrenia (see below).
What the pooled studies show. A 2021 meta-analysis of 101 studies (10,912 people) compared these substances in people with major depression, bipolar disorder or schizophrenia against healthy people. Tryptophan and kynurenine were lower in all three conditions, and the kynurenine-to-tryptophan ratio was higher in depression and schizophrenia — a shift of tryptophan away from serotonin and into the kynurenine pathway. The two groups then split: in the mood disorders the pathway leaned toward the potentially nerve-damaging quinolinic acid instead of the protective kynurenic acid, while in schizophrenia kynurenic acid was not altered and that lean toward quinolinic acid was not seen. These are measurements in samples taken from patients; they do not show what happens inside the brain or that changing the pathway changes symptoms.
This is the modern biochemical basis for the "inflammatory hypothesis of depression" that has gained substantial empirical support over the past 20 years. The Hoffer/Pauling orthomolecular intuition — that abnormal tryptophan metabolism contributes to psychiatric disease — was directionally correct, even if the specific adrenochrome mechanism they proposed was not. Niacin supplementation in this context might reduce IDO induction (because adequate nicotinamide adenine dinucleotide provides feedback inhibition on the de novo pathway) and reduce quinolinic acid accumulation — though this is mechanistically plausible rather than rigorously demonstrated.
See Tryptophan for the broader tryptophan biochemistry.
Niacin in Obsessive-Compulsive Disorder, Anxiety, and Depression
Beyond schizophrenia, integrative and orthomolecular practitioners have used high-dose nicotinamide for other psychiatric indications. The evidence is weaker than for schizophrenia (which is itself contested) but the clinical rationale is:
Anxiety
- Benzodiazepine receptor interaction. In laboratory binding studies, nicotinamide binds with low affinity to the benzodiazepine recognition site on the gamma-aminobutyric acid-A receptor; in a 1985 study in mice it showed anticonvulsant activity and impaired coordination, as the benzodiazepine triazolam did. No human anxiety outcome was tested. Orthomolecular practitioners use it for anxiety and describe modest calming effects without the addiction or sedation profile of true benzodiazepines.
- Typical orthomolecular protocols use 500-3000 mg/day of nicotinamide in divided doses for generalized anxiety, panic disorder, and situational anxiety.
- Modern controlled trial evidence is sparse; effect sizes appear modest at best.
Obsessive-Compulsive Disorder
- Some orthomolecular protocols include nicotinamide 1000-3000 mg/day plus inositol and N-acetylcysteine (NAC) for obsessive-compulsive disorder.
- N-acetylcysteine and inositol have more controlled-trial support for obsessive-compulsive disorder than nicotinamide.
- The rationale for nicotinamide is neurotransmitter modulation and possible glutamate/N-methyl-D-aspartate effects.
- See obsessive-compulsive disorder for the broader integrative approach.
Depression
- Tryptophan-substrate preservation. When B3 status is adequate, less tryptophan needs to be diverted toward nicotinamide adenine dinucleotide synthesis, preserving substrate for serotonin production.
- Kynurenine pathway modulation. Adequate nicotinamide adenine dinucleotide feedback inhibits the de novo pathway, potentially reducing quinolinic acid accumulation in inflammatory depression.
- Insomnia component. Nicotinamide 1000-3000 mg at bedtime has been reported anecdotally to improve sleep onset and quality in depressed patients — possibly via benzodiazepine-receptor binding or via supporting melatonin synthesis (which requires serotonin, which requires preserved tryptophan).
- Controlled trial evidence is weak; practitioners who use it describe B3 as an adjunct to standard depression care, not a replacement for it.
Cognitive aging and Alzheimer's disease
- Higher dietary niacin intake has been associated with reduced Alzheimer's disease risk in the Chicago Health and Aging Project cohort and other epidemiological studies. In that Chicago study of residents aged 65 and older (Morris and colleagues, 2004), niacin from food was linked to lower Alzheimer's risk and slower cognitive decline; it was an observational food-questionnaire study, not a trial.
- Nicotinamide adenine dinucleotide decline is implicated in neurodegeneration — see nicotinamide adenine dinucleotide Precursor for the broader story.
- Nicotinamide adenine dinucleotide precursor trials in mild cognitive impairment are ongoing but currently lack definitive outcomes data.
The Realistic Modern Place of High-Dose B3
Synthesizing the historical record with modern evidence:
- Not a replacement for standard psychiatric treatment. Schizophrenia, bipolar disorder, severe depression, and obsessive-compulsive disorder are treated with antipsychotic, mood-stabilizer, antidepressant, or selective serotonin reuptake inhibitor (SSRI) or other serotonin reuptake inhibitor therapy plus psychotherapy. No controlled trial has shown that niacin can replace these treatments, and untreated psychosis can worsen.
- Empirical pellagra workup. Orthomolecular and integrative practitioners describe an empirical niacin trial for any new-onset psychosis in a person with niacin-deficiency risk factors — cheap, generally safe, occasionally curative.
- Adjunctive support in many integrative-medicine protocols, particularly when patients have documented poor diet quality, malabsorption, or biochemical evidence of tryptophan pathway dysregulation. These practitioners regard the risk-benefit at conservative doses (500-1000 mg/day nicotinamide) as favorable.
- A research direction for the flush-blunted schizophrenia subtype — biomarker-guided, not established treatment, and a hypothesis that modern stratified-trial designs could test.
- Multi-gram doses carry known risks — at the doses Hoffer used, and without active monitoring, gram-range nicotinamide carries hepatotoxicity risk and sirtuin product-inhibition concerns; gram-range nicotinic acid carries hepatotoxicity, glucose, gout, and ulcer risks.
For comparison, the 1950s Saskatchewan trial gave 3 g/day of nicotinic acid or nicotinamide, and Hoffer later reported using 3-18 g/day. The lower-dose protocol that orthomolecular practitioners describe today as an adjunct runs along these lines:
- Nicotinamide 500-1000 mg/day (split into 2 doses with meals) alongside standard psychiatric care
- A complete B-complex including B1, B2, B6, B12, folate
- Liver enzyme tests if the dose is raised
- Omega-3 fatty acids (eicosapentaenoic acid (EPA)/docosahexaenoic acid), magnesium glycinate, and zinc as the broader nutritional foundation
- A review of any subjective or objective response after 8-12 weeks
- Stopping if there is no benefit; continuing if benefit is durable
Cautions
- HEPATOTOXICITY — sustained-release nicotinic acid at >1 g/day. The same warning as for cardiovascular use applies in psychiatric protocols. Where gram-range nicotinic acid is used, the protocols use the immediate-release form with liver enzyme tests at baseline, 6 weeks, 3 months, and then every 6 months, and stop it when alanine aminotransferase (ALT) rises above 3 times the upper limit of normal. Sustained-release at gram-range doses has caused fulminant hepatic failure.
- Sirtuin product inhibition — high-dose nicotinamide. Sustained nicotinamide above 3000 mg/day can inhibit sirtuin enzymes (nicotinamide is a product-feedback inhibitor of sirtuin reactions) — the opposite of the desired metabolic-support effect. Practitioners using psychiatric protocols commonly keep long-term nicotinamide at or below 2000 mg/day for this reason.
- Drug interactions in psychiatric patients. Many antipsychotic medications (clozapine in particular) carry hepatotoxicity and metabolic risks of their own. Combining high-dose niacin with clozapine, olanzapine, or valproic acid adds to that liver and metabolic risk.
- Hyperglycemia. Nicotinic acid raises blood glucose; many psychiatric patients are already at metabolic risk from atypical antipsychotic medications. Blood glucose and hemoglobin A1c (HbA1c) are the tests that track this.
- Niacin as a substitute for standard treatment. A psychotic episode or severe depression is treated with standard psychiatric care. Using niacin as primary treatment for an acute psychotic break carries real danger — ineffective treatment may allow patient deterioration to a point requiring more aggressive intervention or hospitalization.
- Methylation concerns. Some integrative practitioners worry about gram-range nicotinamide depleting methyl groups (through N1-methylnicotinamide excretion) and stressing methylation-dependent functions (homocysteine, neurotransmitter synthesis, DNA methylation). At doses up to 1-2 g/day this concern is usually overstated; some practitioners add methylfolate, methylcobalamin, and TMG (trimethylglycine) for people with methylenetetrahydrofolate reductase variants.
- Suicidality screening. Standard care for major depression, obsessive-compulsive disorder, or schizophrenia includes ongoing suicide-risk assessment regardless of niacin status. The orthomolecular community has occasionally minimized this need; modern integrative practice does not.
- Flush in nicotinic acid users. The vasodilatory flush can be alarming in anxious patients. For this reason practitioners use nicotinamide, the non-flushing form, rather than nicotinic acid for psychiatric indications where lipid effects are not needed.
Key Research Papers
- Hoffer A, Osmond H, Smythies J (1954). Schizophrenia: a new approach. II. Result of a year's research. J Ment Sci. — PubMed PMID: 13152519
- Hoffer A, Osmond H, Callbeck MJ, Kahan I (1957). Treatment of schizophrenia with nicotinic acid and nicotinamide. J Clin Exp Psychopathol. — PubMed PMID: 13439009
- Hoffer A (1971). Megavitamin B-3 therapy for schizophrenia. Can Psychiatr Assoc J. — PubMed PMID: 4947171
- Pauling L (1968). Orthomolecular psychiatry. Science. — PubMed PMID: 5641253
- APA Task Force (1973). Megavitamin and orthomolecular therapy in psychiatry. American Psychiatric Association. — PubMed
- Niacin flush test in schizophrenia — PubMed
- Hudson CJ, Lin A, Cogan S, Cashman F, Warsh JJ (1997). The niacin challenge test: clinical manifestation of altered transmembrane signal transduction in schizophrenia? Biol Psychiatry. — PubMed PMID: 9046982
- Wittenborn JR et al. (1973). Niacin in the long-term treatment of schizophrenia. Arch Gen Psychiatry. — PubMed PMID: 4569673
- Marx W, McGuinness AJ, Rocks T, et al. (2021). The kynurenine pathway in major depressive disorder, bipolar disorder, and schizophrenia: a meta-analysis of 101 studies. Mol Psychiatry. — PubMed PMID: 33230205
- Quinolinic acid in schizophrenia and depression — PubMed PMID: 35063739
- Morris MC, Evans DA, Bienias JL, et al. (2004). Dietary niacin and the risk of incident Alzheimer's disease and of cognitive decline. J Neurol Neurosurg Psychiatry. — PubMed PMID: 15258207
- Chweh AY, Swinyard EA, Wolf HH (1985). gamma-Aminobutyric acid modulation of benzodiazepine receptor binding in vitro does not predict the pharmacologic activity of all benzodiazepine receptor ligands. Neurosci Lett. (Laboratory and mouse study of nicotinamide.) — PubMed PMID: 2859562
- Pellagra psychosis case series — PubMed
- Wang J, Wang Q, Wang D, et al. (2026). Blunted Niacin Skin Flushing Response in Schizophrenia: A Meta-analysis. Schizophr Bull. — PubMed PMID: 40401804
- Wang S, Chen Q, Zheng F, et al. (2026). Adjunctive n-3 PUFA supplementation improves niacin skin flush response and shows biomarker-stratified signals in schizophrenia. Schizophr Res. — PubMed PMID: 42691601
- IDO induction by interferon and inflammation in psychiatric disease — PubMed
PubMed Topic Searches
Connections
- All Vitamins
- Dr. Abram Hoffer — the psychiatrist-biochemist whose niacin and vitamin C program founded orthomolecular medicine
- Linus Pauling & Orthomolecular Medicine — the 1968 theory built on these trials
- Vitamin B3 Overview
- B3 Benefits Hub
- B3 as Nicotinamide Adenine Dinucleotide Precursor
- B3 for Cholesterol & Cardiovascular
- B3 for Pellagra & Skin
- Pellagra & Niacin Deficiency
- Schizophrenia
- Obsessive-Compulsive Disorder
- Depression
- Anxiety
- Dementia
- Alzheimer's Disease
- Tryptophan
- Niacin in Gerson Therapy
- Nicotinamide Adenine Dinucleotide / Nicotinamide Mononucleotide
- Vitamin B6 (Pyridoxine)
- Vitamin B12
- Dr. Bryan Ardis: Nicotine and Schizophrenia
- Deficiency
- Toxicity
- History
- Sources