Cholesterol Management
Interactive Visualization Cholesterol & the Artery Wall — watch a plaque form Follow low-density lipoprotein (LDL) particles into the artery wall and see foam cells build plaque — then add a statin and watch the receptors clear them. Launch →
Table of Contents
What is Cholesterol Management?
Cholesterol management is the long-term, risk-based process of lowering atherogenic (artery-clogging) lipoproteins in the blood to prevent heart attacks, strokes, and peripheral artery disease. The goal is not to chase a "normal cholesterol" number on a generic chart — it is to drive the particles that drive plaque as low as your personal risk warrants, and to keep them there for life.
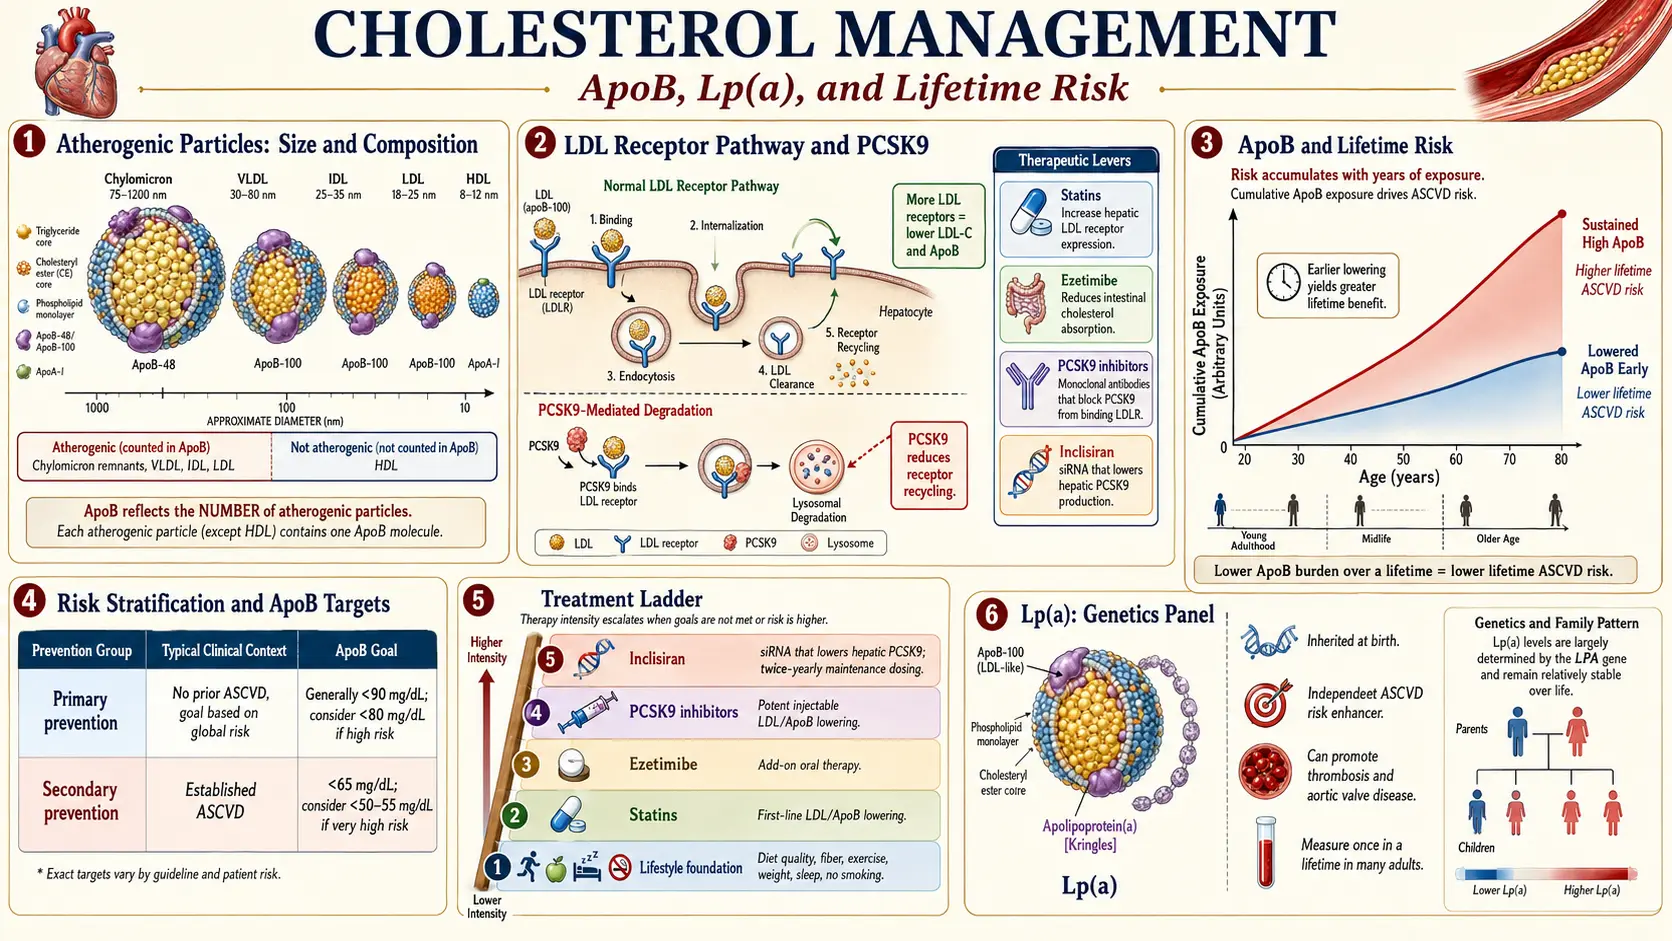
Most people are still told their "total cholesterol" or even just their "low-density lipoprotein cholesterol" (low-density lipoprotein cholesterol, LDL-C). Both numbers matter, but both can mislead. Total cholesterol lumps the bad (low-density lipoprotein, very-low-density lipoprotein (VLDL), Lp(a)) with the good (high-density lipoprotein, HDL). Low-density lipoprotein cholesterol measures the weight of cholesterol inside low-density lipoprotein particles — not the number of particles. Two people can have an identical low-density lipoprotein cholesterol of 100 mg/dL, yet one has half as many low-density lipoprotein particles as the other. The person with more particles has the higher cardiovascular risk. That is why modern lipidology has shifted toward two better markers:
- ApoB — one molecule of apolipoprotein B sits on every atherogenic particle (low-density lipoprotein, VLDL, IDL, Lp(a), chylomicron remnant). One ApoB equals one particle. ApoB is the most direct measure of how many bullets are in the gun.
- Lp(a) — lipoprotein(a) is a genetic variant of low-density lipoprotein that is roughly six times more atherogenic, gram-for-gram, than ordinary low-density lipoprotein. About one in five people has elevated Lp(a) and most have never been tested. Lp(a) is the single biggest source of residual risk — the heart attacks that still happen in people whose low-density lipoprotein cholesterol looks "fine."
Residual risk is the central problem. The major statin trials cut events by roughly 25-35 percent on top of background care. That is excellent — and it means 65-75 percent of events still happen. Closing that gap is what cholesterol management in 2026 is actually about: lower low-density lipoprotein further, find and treat Lp(a), reduce inflammation, and pick up subclinical plaque early with a coronary calcium score.
The framing principle: cholesterol is a lifetime cumulative exposure problem, not a single-decade problem. Plaque builds slowly over decades. Lower numbers earlier — even modestly — bend the lifetime curve dramatically.
Lipid Particles Explained
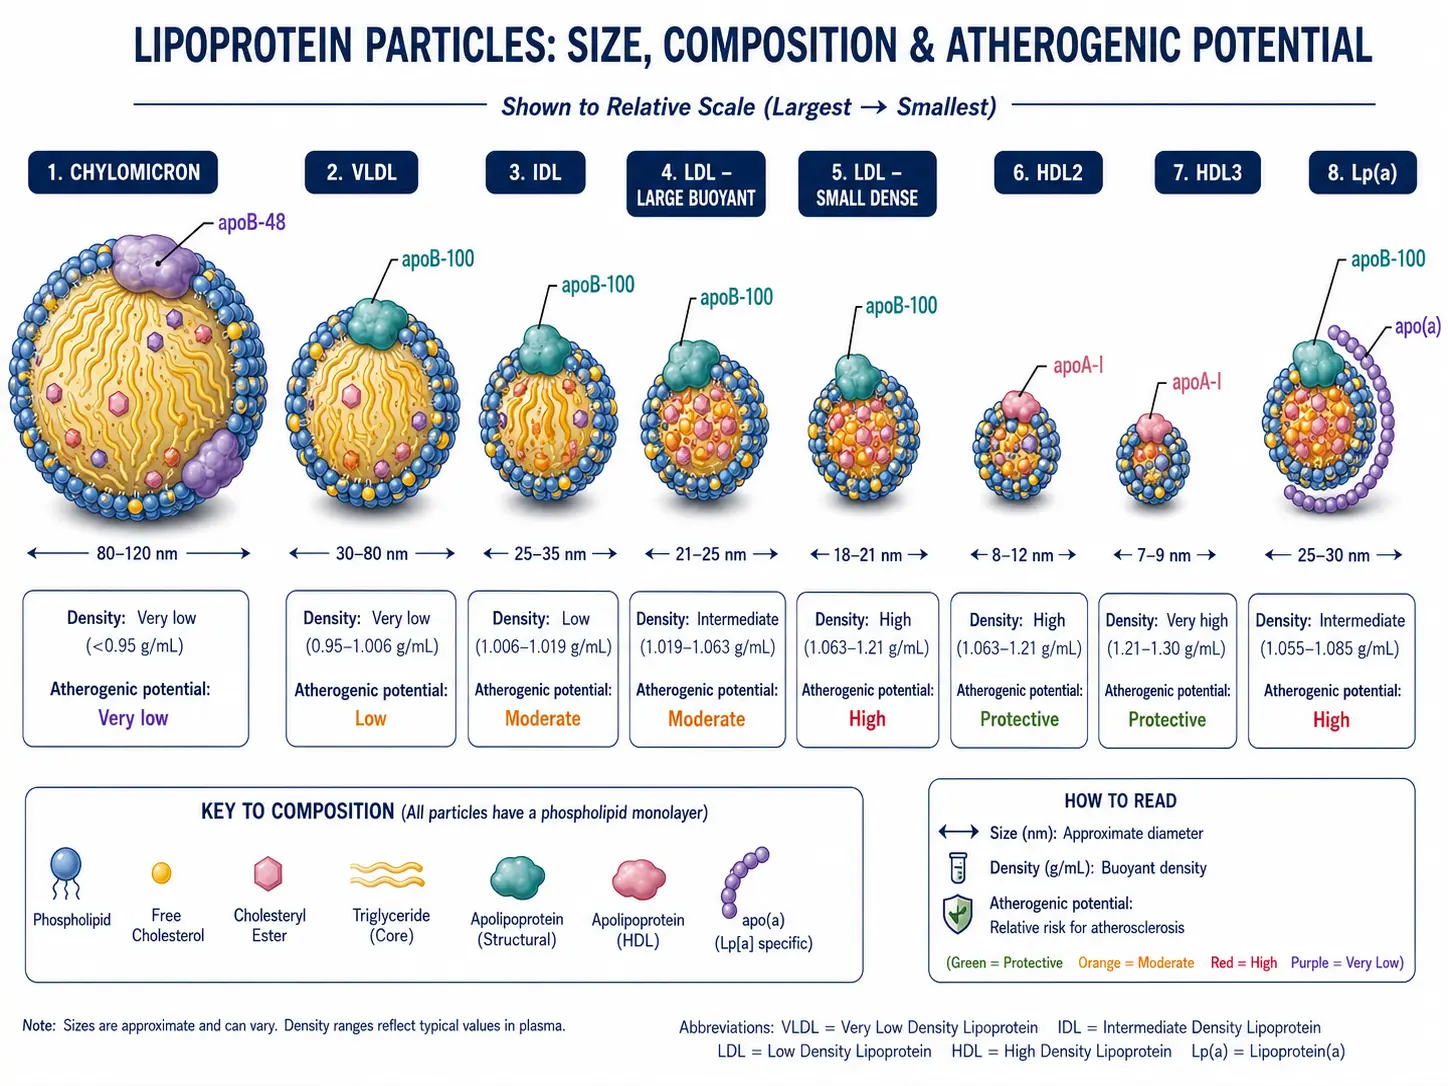
Cholesterol and triglycerides do not float freely in blood — they are wrapped in protein-coated spheres called lipoproteins. Each kind of particle has a different size, density, cargo, and atherogenic potential. The image above shows them roughly to scale.
Chylomicron
- Largest particle (75-1200 nm). Made by the small intestine after a fatty meal.
- Carries dietary triglycerides from the gut to the liver and peripheral tissues.
- Cleared rapidly — usually invisible after a 12-hour fast. Their remnants (after triglyceride drop-off) are atherogenic.
Very-Low-Density Lipoprotein
- Made by the liver to export triglycerides to the body. Roughly 30-80 nm.
- Each very-low-density lipoprotein carries one ApoB-100. As triglycerides are stripped out, very-low-density lipoprotein shrinks into IDL, then into low-density lipoprotein.
- Very-low-density lipoprotein remnants are atherogenic. High triglycerides means high very-low-density lipoprotein means high non-HDL cholesterol — one reason non-HDL outperforms low-density lipoprotein cholesterol alone.
IDL (Intermediate-Density Lipoprotein)
- Short-lived bridge between very-low-density lipoprotein and low-density lipoprotein. Atherogenic when it accumulates (genetic dysbetalipoproteinemia, type 2 diabetes, kidney disease).
Low-Density Lipoprotein — the main villain
- Roughly 18-25 nm. Carries about 70 percent of the cholesterol in the blood. One ApoB-100 per particle.
- Subtypes by size and density:
- Pattern A — large, buoyant low-density lipoprotein: bigger, lighter, less atherogenic. Common in people with low triglycerides and high-density lipoprotein.
- Pattern B — small, dense low-density lipoprotein: smaller, heavier, oxidizes more easily, slips through the artery wall more readily, and stays trapped longer. Strongly linked to insulin resistance, high triglycerides, and metabolic syndrome.
- Same low-density lipoprotein cholesterol number can hide very different particle counts. A high triglyceride / low high-density lipoprotein pattern almost always means more, smaller, denser, more atherogenic low-density lipoprotein particles. Hence ApoB.
High-Density Lipoprotein
- Roughly 5-12 nm — the smallest. Reverse-cholesterol transport: pulls cholesterol out of the artery wall back to the liver.
- HDL2 (larger, more buoyant) is generally considered more cardioprotective than HDL3 (smaller, denser).
- High-density lipoprotein is associated with lower risk — but raising high-density lipoprotein pharmacologically (CETP inhibitors, niacin) has not reliably reduced events. High-density lipoprotein function (efflux capacity) matters more than high-density lipoprotein number.
Lp(a) — lipoprotein(a)
- A low-density lipoprotein particle with a long, kinky apolipoprotein(a) tail covalently bound to ApoB-100. Genetically determined — your level is set at birth and barely moves with diet, exercise, or statins.
- Roughly six times more atherogenic per particle than low-density lipoprotein. Promotes plaque, calcification, thrombosis, and aortic stenosis.
- Affects an estimated 20 percent of the population. Test once in a lifetime. Currently no approved therapy specifically lowers Lp(a) to a target, though several are in late-stage trials (pelacarsen, olpasiran, lepodisiran). PCSK9 inhibitors lower Lp(a) by 20-30 percent as a side benefit.
Lab Targets and Goals
"Optimal" lipid numbers depend on your overall cardiovascular risk. The same low-density lipoprotein cholesterol of 110 mg/dL is reasonable for a 25-year-old with no risk factors and unacceptable for a 60-year-old with diabetes and a prior heart attack. Modern guidelines (ACC/AHA, ESC, NLA) stratify patients into risk tiers, then set lower-is-better targets within each tier.
The Five Numbers That Matter Most
- Low-density lipoprotein cholesterol — still the workhorse marker. Calculated or directly measured.
- ApoB — the particle count. Increasingly preferred when low-density lipoprotein cholesterol and ApoB disagree.
- Lp(a) — one-time genetic test. Reported as nmol/L (preferred) or mg/dL.
- Non-HDL cholesterol — total minus high-density lipoprotein. Captures all atherogenic particles in one number. Free on every standard lipid panel.
- Triglycerides — high triglycerides drive small-dense low-density lipoprotein and reflect insulin resistance.
Goals by Risk Tier (ACC/AHA framework, simplified)
Primary Prevention — Low Risk
- 10-year ASCVD risk under 5 percent, no diabetes, no family history of premature coronary artery disease (CAD).
- Low-density lipoprotein cholesterol goal: < 130 mg/dL (ideally < 100).
- ApoB goal: < 90 mg/dL.
- Non-HDL: < 160 mg/dL.
Primary Prevention — Borderline / Intermediate Risk
- 10-year risk 5-20 percent, or one major risk factor (hypertension, diabetes, smoking, family history, elevated Lp(a), coronary artery calcium (CAC) > 0).
- Low-density lipoprotein cholesterol goal: < 100 mg/dL, ideally < 70.
- ApoB goal: < 80 mg/dL.
- Strong indication for statin if coronary artery calcium > 100 Agatston units or any plaque visible.
Secondary Prevention — Established ASCVD or "Very High Risk"
- Prior heart attack, stroke, peripheral artery disease, coronary stent or bypass, diabetes with target organ damage, familial hypercholesterolemia, coronary artery calcium > 300.
- Low-density lipoprotein cholesterol goal: < 70 mg/dL at minimum; current ESC guidelines push < 55 mg/dL, and very-high-risk recurrent-event patients are often targeted to < 40.
- ApoB goal: < 65 mg/dL (very high risk < 50).
- Non-HDL: < 100 mg/dL (very high risk < 80).
Triglycerides
- < 150 mg/dL: optimal.
- 150-499: borderline-to-high; mostly a lifestyle and metabolic problem.
- > 500: pancreatitis risk — treat aggressively.
High-Density Lipoprotein and the Total/High-Density Lipoprotein Ratio
- High-density lipoprotein > 40 mg/dL men, > 50 women is the conventional bar — but raising high-density lipoprotein pharmacologically does not reduce events. Use high-density lipoprotein as a risk marker, not a treatment target.
- Total cholesterol / high-density lipoprotein ratio < 3.5 is generally favorable; > 5 unfavorable.
Lp(a)
- < 75 nmol/L (~30 mg/dL): low risk.
- 75-125 nmol/L: moderate.
- > 125 nmol/L: elevated — treat low-density lipoprotein/ApoB more aggressively to compensate.
- > 250 nmol/L: very high — consider PCSK9 inhibitor and screen first-degree relatives.
Statins and How They Work
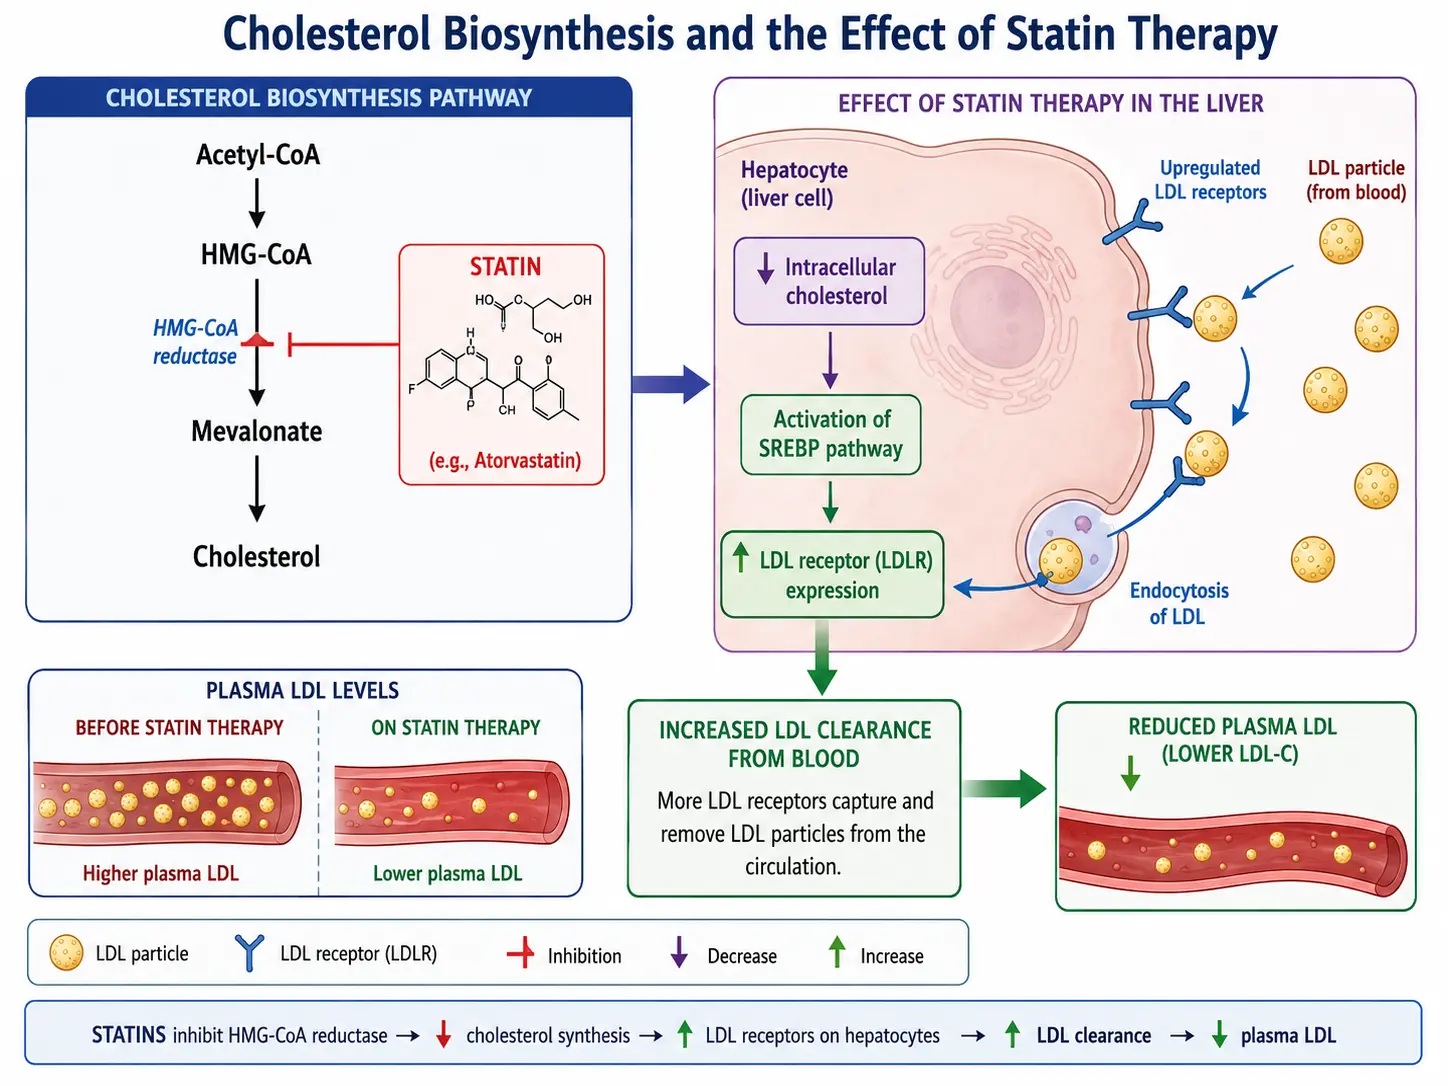
Statins are the most-studied medication class in human history — tens of millions of patient-years across dozens of randomized trials. They are the foundation of low-density lipoprotein lowering and the only lipid drug with both consistent event reduction and proven plaque regression on intravascular ultrasound. The image above shows the molecular mechanism.
The Mechanism in Plain Language
The liver makes most of the body's cholesterol. The rate-limiting step in that synthesis pathway is an enzyme called HMG-CoA reductase. Statins are competitive inhibitors of HMG-CoA reductase — they sit in the enzyme's active site and block it.
Two things happen when liver cells make less cholesterol internally:
- The liver puts more low-density lipoprotein receptors on its surface to grab cholesterol from the blood.
- Those low-density lipoprotein receptors pull low-density lipoprotein particles (and very-low-density lipoprotein remnants and IDL) out of circulation and recycle them.
The net result: blood low-density lipoprotein drops by 20-55 percent, depending on which statin and what dose. ApoB drops in parallel. Triglycerides drop modestly (10-30 percent). High-density lipoprotein nudges up slightly. Plaque often regresses on imaging when low-density lipoprotein stays below ~70 mg/dL for a year or more.
Beyond Low-Density Lipoprotein Lowering — Pleiotropic Effects
Statins do more than lower cholesterol. They reduce vascular inflammation (C-reactive protein (CRP) drops along with low-density lipoprotein), stabilize existing plaque so it is less likely to rupture, improve endothelial function, and have mild anti-thrombotic effects. The "JUPITER" trial showed that even people with normal low-density lipoprotein but elevated C-reactive protein benefited — suggesting some of the event reduction is independent of low-density lipoprotein.
Intensity Tiers (ACC/AHA classification)
High-Intensity Statins (Low-Density Lipoprotein reduction ~50 percent or more)
- Atorvastatin 40-80 mg — first-line for secondary prevention. Used in PROVE-IT, TNT, IDEAL.
- Rosuvastatin 20-40 mg — most potent per milligram; least drug-interaction-prone of the high-potency statins. Used in JUPITER, GISSI-HF.
Moderate-Intensity Statins (Low-Density Lipoprotein reduction ~30-50 percent)
- Atorvastatin 10-20 mg
- Rosuvastatin 5-10 mg
- Simvastatin 20-40 mg (40 only; 80 mg withdrawn for myopathy risk)
- Pravastatin 40-80 mg — least interactions, often used in elderly.
- Lovastatin 40 mg, Fluvastatin 80 mg, Pitavastatin 1-4 mg.
Low-Intensity Statins (Low-Density Lipoprotein reduction < 30 percent)
- Reserved for statin-intolerant patients who can tolerate small doses, or as starter doses.
Landmark Statin Trials
- 4S (1994) — simvastatin in patients with prior myocardial infarction (MI) cut total mortality 30 percent. The trial that changed cardiology.
- WOSCOPS, AFCAPS/TexCAPS — primary prevention works in elevated-LDL patients without prior events.
- PROVE-IT (2004) — intensive (atorvastatin 80) beat moderate (pravastatin 40) post-ACS. Established "lower is better."
- JUPITER (2008) — rosuvastatin in high-CRP patients with normal low-density lipoprotein still cut events 44 percent.
- HOPE-3 (2016) — primary prevention in intermediate-risk patients.
- FOURIER (2017) and ODYSSEY OUTCOMES (2018) — PCSK9 inhibitors on top of maximally tolerated statin further reduced events with no low-density lipoprotein floor seen.
Beyond Statins
If maximally tolerated statin therapy does not reach your low-density lipoprotein cholesterol / ApoB target — or you cannot tolerate statins at all — there are six well-studied add-on or alternative classes.
1. Ezetimibe
- Mechanism: Blocks the NPC1L1 cholesterol transporter in the small intestine, reducing dietary and biliary cholesterol absorption.
- Low-density lipoprotein effect: Additional 18-25 percent on top of statin.
- Evidence: IMPROVE-IT (2015) added ezetimibe to simvastatin in post-ACS patients and cut events 6 percent — the first non-statin low-density lipoprotein drug to prove the lower-is-better hypothesis on outcomes.
- Use case: Cheap, generic, well-tolerated. Almost everyone on a statin who isn't at goal should add ezetimibe before escalating further.
2. PCSK9 Inhibitors (Evolocumab, Alirocumab)
- Mechanism: Monoclonal antibodies that block PCSK9, a protein that destroys low-density lipoprotein receptors. Block PCSK9 and low-density lipoprotein receptors live longer, clearing more low-density lipoprotein.
- Low-density lipoprotein effect: 50-60 percent reduction on top of statin. Lp(a) drops 20-30 percent as a bonus.
- Evidence: FOURIER and ODYSSEY OUTCOMES proved cardiovascular benefit. Driving low-density lipoprotein into the 20s and 30s reduced events further with no safety floor.
- Use case: Familial hypercholesterolemia, secondary prevention not at goal on statin + ezetimibe, statin intolerance, elevated Lp(a). Injection every 2-4 weeks. Expensive but increasingly covered.
3. Bempedoic Acid (Nexletol)
- Mechanism: Inhibits adenosine triphosphate-citrate lyase, an enzyme upstream of HMG-CoA reductase in the cholesterol synthesis pathway. Activated only in the liver, not muscle — so it should not cause myopathy.
- Low-density lipoprotein effect: ~17 percent monotherapy, ~38 percent combined with ezetimibe.
- Evidence: CLEAR Outcomes (2023) showed bempedoic acid reduced major cardiovascular events 13 percent in statin-intolerant patients.
- Use case: Statin-intolerant patients with established ASCVD or familial hypercholesterolemia.
4. Inclisiran (Leqvio)
- Mechanism: Small interfering RNA (siRNA) that silences PCSK9 production in the liver. A "PCSK9 blocker" with twice-yearly dosing.
- Low-density lipoprotein effect: ~50 percent reduction on top of statin, similar to monoclonal PCSK9 inhibitors.
- Evidence: ORION-9, ORION-10, ORION-11 confirmed durable low-density lipoprotein lowering. Outcome trials (ORION-4, VICTORION-2) ongoing.
- Use case: Patients who would benefit from PCSK9 inhibition but prefer two injections a year (administered in clinic) over self-injecting every 2-4 weeks.
5. Niacin (Nicotinic Acid)
- Effect: Lowers low-density lipoprotein ~15 percent, raises high-density lipoprotein 15-35 percent, lowers Lp(a) 20-30 percent, lowers triglycerides 20-50 percent.
- Evidence: AIM-HIGH and HPS2-THRIVE failed to show event reduction when added to statins, despite improving the lipid panel. Side effects (flushing, glucose intolerance, hepatotoxicity) are common.
- Current role: Niche — mainly for severe hypertriglyceridemia or selected Lp(a) cases when nothing else is available. Not a routine add-on.
6. Fibrates (Fenofibrate, Gemfibrozil)
- Mechanism: PPAR-alpha agonists. Lower triglycerides 30-50 percent, raise high-density lipoprotein 10-15 percent. Modest low-density lipoprotein effect.
- Evidence: ACCORD-Lipid suggested benefit only in the high-triglyceride / low-HDL subgroup. PROMINENT (pemafibrate, 2022) was negative.
- Use case: Triglycerides > 500 mg/dL to prevent pancreatitis; selective use in mixed dyslipidemia.
7. Omega-3 Fatty Acids (Eicosapentaenoic Acid / Docosahexaenoic Acid)
- Effect: Lower triglycerides 20-30 percent at high doses (4 g/day). Modest low-density lipoprotein effects.
- Evidence: REDUCE-IT (icosapent ethyl 4 g/day) cut events 25 percent in statin-treated patients with elevated triglycerides. STRENGTH and VITAL (general fish oil) were largely negative.
- Use case: Prescription-grade eicosapentaenoic acid-only (icosapent ethyl) on top of statin for residual risk; high triglycerides.
Lifestyle Cornerstones
Drugs do not replace lifestyle — they layer on top of it. Lifestyle changes alone can lower low-density lipoprotein 15-30 percent, drop triglycerides 30-50 percent, and reduce all-cause mortality independently of any pill. The compounding effect of lifestyle plus medication is much greater than either alone.
1. Mediterranean Diet
- The most-studied dietary pattern for cardiovascular disease. PREDIMED (2013, re-published 2018) randomized 7,400 high-risk adults to Mediterranean diet plus extra-virgin olive oil or mixed nuts vs. low-fat control. The Mediterranean groups had ~30 percent fewer major cardiovascular events.
- Pattern: heavy on vegetables, legumes, whole grains, fruit, nuts, olive oil, fish; moderate dairy and poultry; low red and processed meat; minimal added sugar and refined flour.
- The benefit is most likely a combination of monounsaturated fat replacing saturated fat, polyphenols, fiber, and the displacement of ultra-processed food.
2. Soluble Fiber and Whole Grains
- Soluble fiber binds bile acids in the gut. The liver pulls cholesterol out of the blood to make replacement bile acids — net low-density lipoprotein drops.
- 5-10 g/day of soluble fiber lowers low-density lipoprotein by 5-11 mg/dL. Sources: oats (beta-glucan), psyllium husk, beans, lentils, apples, citrus, brussels sprouts.
- Psyllium 7-10 g/day is the most concentrated, evidence-based form.
3. Plant Sterols and Stanols
- Compete with cholesterol for absorption in the intestine. 2 g/day lowers low-density lipoprotein ~10 percent. Found in fortified spreads, yogurts, and supplements.
- Effect stacks additively with statins, ezetimibe, and fiber.
4. Soy Protein
- 25 g/day of soy protein (in place of animal protein) lowers low-density lipoprotein 4-6 percent. Modest but real, and additive to other measures.
- Soy also has a small blood-pressure-lowering effect.
5. Reduce Saturated Fat, Trans Fat, and Refined Carbohydrate
- Replacing saturated fat (red meat, butter, full-fat dairy) with mono- and polyunsaturated fat (olive oil, nuts, seeds, fish) consistently lowers low-density lipoprotein.
- Trans fats raise low-density lipoprotein and lower high-density lipoprotein — the worst macronutrient ever measured. Largely banned but still lurking in some packaged foods.
- Refined carbs and added sugar drive triglycerides and small-dense low-density lipoprotein through hepatic very-low-density lipoprotein production. Cutting them lowers triglycerides faster than cutting fat does.
6. Exercise
- Aerobic exercise (150 min/week of moderate, or 75 min/week vigorous) raises high-density lipoprotein ~5 mg/dL, lowers triglycerides 10-20 percent, and shifts low-density lipoprotein toward larger, more buoyant subtypes.
- Resistance training adds independent metabolic benefit and improves insulin sensitivity.
- Effect on low-density lipoprotein cholesterol alone is modest, but the cardiovascular event reduction is large — exercise reduces mortality more than most cholesterol drugs.
7. Weight Loss
- Every 10 pounds lost reduces low-density lipoprotein by ~5-8 mg/dL, triglycerides by 20 mg/dL, and raises high-density lipoprotein by 1-2 mg/dL.
- Visceral fat loss is the biggest lever — it drops very-low-density lipoprotein output and reverses the small-dense-LDL pattern.
8. Smoking Cessation
- Smoking lowers high-density lipoprotein, oxidizes low-density lipoprotein, damages endothelium, and roughly doubles cardiovascular risk independent of cholesterol numbers.
- Within one year of quitting, cardiovascular risk drops by half. Within 10-15 years it approaches that of a never-smoker.
9. Alcohol Moderation
- Alcohol raises high-density lipoprotein but also raises triglycerides and blood pressure. The "J-curve" benefit is now considered overstated.
- For lipid management: keep alcohol low; eliminate it entirely if triglycerides are elevated.
Special Populations
Women
- Estrogen is mildly cardioprotective — women's cardiovascular risk lags men by roughly 10 years until menopause, then catches up.
- After menopause, low-density lipoprotein typically rises 10-15 percent. Hormone replacement therapy is not a cholesterol treatment — treat lipids per the same risk-based framework as men.
- Pregnancy: stop statins (Category X). Bile acid sequestrants (cholestyramine, colesevelam) are pregnancy-safe alternatives if needed.
- Women have historically been undertreated for cholesterol — symptoms of heart attack are also more atypical. Treat aggressively.
Elderly (75+)
- Statin benefit persists into the 80s for secondary prevention. Primary prevention in older adults is less clear-cut — weigh against polypharmacy, frailty, and competing causes of death.
- STAREE (in progress) and PREVENTABLE (in progress) are filling the evidence gap.
- Use lower starting doses; renal and hepatic function decline with age.
Type 2 Diabetes
- Diabetes is a "coronary heart disease equivalent" — treat to secondary-prevention targets even without prior events.
- Diabetic dyslipidemia is the small-dense-LDL / high-TG / low-HDL pattern. Statins are foundational; ezetimibe and PCSK9 stack on top.
- Sodium-glucose cotransporter-2 (SGLT2) inhibitors and glucagon-like peptide-1 (GLP-1) agonists (e.g., semaglutide) reduce cardiovascular events independently of low-density lipoprotein — add them when indicated.
Chronic Kidney Disease (CKD)
- Chronic kidney disease accelerates atherosclerosis. Most chronic kidney disease patients qualify as high or very-high risk regardless of other factors.
- Statins and ezetimibe are first-line; SHARP trial (2011) showed 17 percent event reduction.
- Dose-adjust for kidney function (rosuvastatin in particular). Avoid PCSK9 dose changes — renal-cleared metabolism is minimal.
Familial Hypercholesterolemia (FH)
- Genetic disorder — low-density lipoprotein receptor or ApoB or PCSK9 mutation. Heterozygous FH affects ~1 in 250; homozygous ~1 in 250,000-1,000,000.
- Low-density lipoprotein is typically > 190 mg/dL in heterozygous, > 400 in homozygous. Premature ASCVD, often first event in 30s-40s for men, 40s-50s for women.
- Treatment: high-intensity statin + ezetimibe almost always; PCSK9 inhibitor or inclisiran routinely added; low-density lipoprotein apheresis or evinacumab for homozygous FH.
- Cascade-screen first-degree relatives once a proband is identified.
Statin Intolerance
- True statin myopathy (creatine kinase-elevating muscle damage) is rare — well under 1 percent. Statin-associated muscle symptoms (SAMS) without creatine kinase (CK) rise are reported in 5-15 percent of users in observational studies, but blinded crossover trials (SAMSON, StatinWise) show most symptoms are nocebo-driven and resolve on placebo as readily as on statin.
- Practical approach: rechallenge with a different statin; try every-other-day dosing of long-half-life statins (rosuvastatin, atorvastatin); switch to bempedoic acid or PCSK9 inhibitor if symptoms persist on multiple agents.
- Real intolerance is uncommon but real — the goal is to keep low-density lipoprotein down, not to win an argument about which drug.
Elevated Lp(a)
- About 20 percent of the population. Currently no targeted therapy — lower the low-density lipoprotein/ApoB you can control to compensate.
- Aspirin for primary prevention may help in elevated-Lp(a) patients (uncertain — trials ongoing).
- PCSK9 inhibitors lower Lp(a) 20-30 percent as a side benefit. Niacin lowers it ~30 percent.
- Specific Lp(a) lowering drugs (pelacarsen, olpasiran, lepodisiran) are in late-stage outcome trials — potentially transformative if positive.
Key Research Papers
- Anonymous (1994). Randomised trial of cholesterol lowering in 4444 patients with coronary heart disease: the Scandinavian Simvastatin Survival Study (4S). Lancet (London, England) — PubMed PMID: 7968073
- Cannon CP, Braunwald E, McCabe CH, et al. (2004). Intensive versus moderate lipid lowering with statins after acute coronary syndromes. The New England Journal of Medicine — PubMed PMID: 15007110
- Ridker PM, Danielson E, Fonseca FA, et al. (2008). Rosuvastatin to prevent vascular events in men and women with elevated C-reactive protein. The New England Journal of Medicine — PubMed PMID: 18997196
- Cannon CP, Blazing MA, Giugliano RP, et al. (2015). Ezetimibe Added to Statin Therapy after Acute Coronary Syndromes. The New England Journal of Medicine — PubMed PMID: 26039521
- Sabatine MS, Giugliano RP, Keech AC, et al. (2017). Evolocumab and Clinical Outcomes in Patients with Cardiovascular Disease. The New England Journal of Medicine — PubMed PMID: 28304224
- Nissen SE, Lincoff AM, Brennan D, et al. (2023). Bempedoic Acid and Cardiovascular Outcomes in Statin-Intolerant Patients. The New England Journal of Medicine — PubMed PMID: 36876740
- Blumenthal RS, Morris PB, Gaudino M, et al. (2026). 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Journal of the American College of Cardiology — PubMed PMID: 41824590
- Estruch R, Ros E, Salas-Salvadó J, et al. (2018). Primary Prevention of Cardiovascular Disease with a Mediterranean Diet Supplemented with Extra-Virgin Olive Oil or Nuts. The New England Journal of Medicine — PubMed PMID: 29897866
PubMed Topic Searches
The following PubMed topic searches return current peer-reviewed literature relevant to this condition. Each link opens a live PubMed query.
- PubMed: 4S simvastatin survival study
- PubMed: PROVE-IT atorvastatin intensive
- PubMed: FOURIER evolocumab outcomes
- PubMed: PCSK9 inhibitor cardiovascular outcomes
- PubMed: ApoB cardiovascular risk
- PubMed: Lipoprotein(a) management
- PubMed: Ezetimibe IMPROVE-IT
- PubMed: Bempedoic acid CLEAR Outcomes
- PubMed: Niacin HDL cardiovascular
- PubMed: Familial hypercholesterolemia treatment
- PubMed: Statin myopathy intolerance
- PubMed: Mediterranean diet LDL cholesterol
- PubMed: Plant sterols cholesterol lowering
- PubMed: Soluble fiber LDL reduction
Connections
- Cardiology
- Familial Hypercholesterolemia — inherited high low-density lipoprotein cholesterol from birth: genes, diagnosis, screening and treatment
- Cholesterol & the Artery Wall — interactive animation
- Beans for Heart Health & Cholesterol
- Atherosclerosis
- ApoB
- Lipid Panel
- Coronary Calcium Score
- Lipoprotein(a)
- Cardiovascular Disease
- Coronary Artery Disease
- Hypertension
- Stroke
- Diabetes
- Metabolic Syndrome
- Insulin Resistance
- Berberine
- Garlic
- Omega-3 Fatty Acids
- Magnesium
- Anti-Inflammatory Diet
- Olive Oil
- Günter Blobel — trafficking-class low-density lipoprotein-receptor mutations — receptors that never reach the cell surface
- Herbs covered on this site that discuss this condition: Haritaki (Terminalia chebula) · Lemongrass · Plantain (Herb) · Red Clover · Sacred Lotus (Nelumbo nucifera) · Tamarind (Tamarindus indica)