Vitamin E and Immune Function
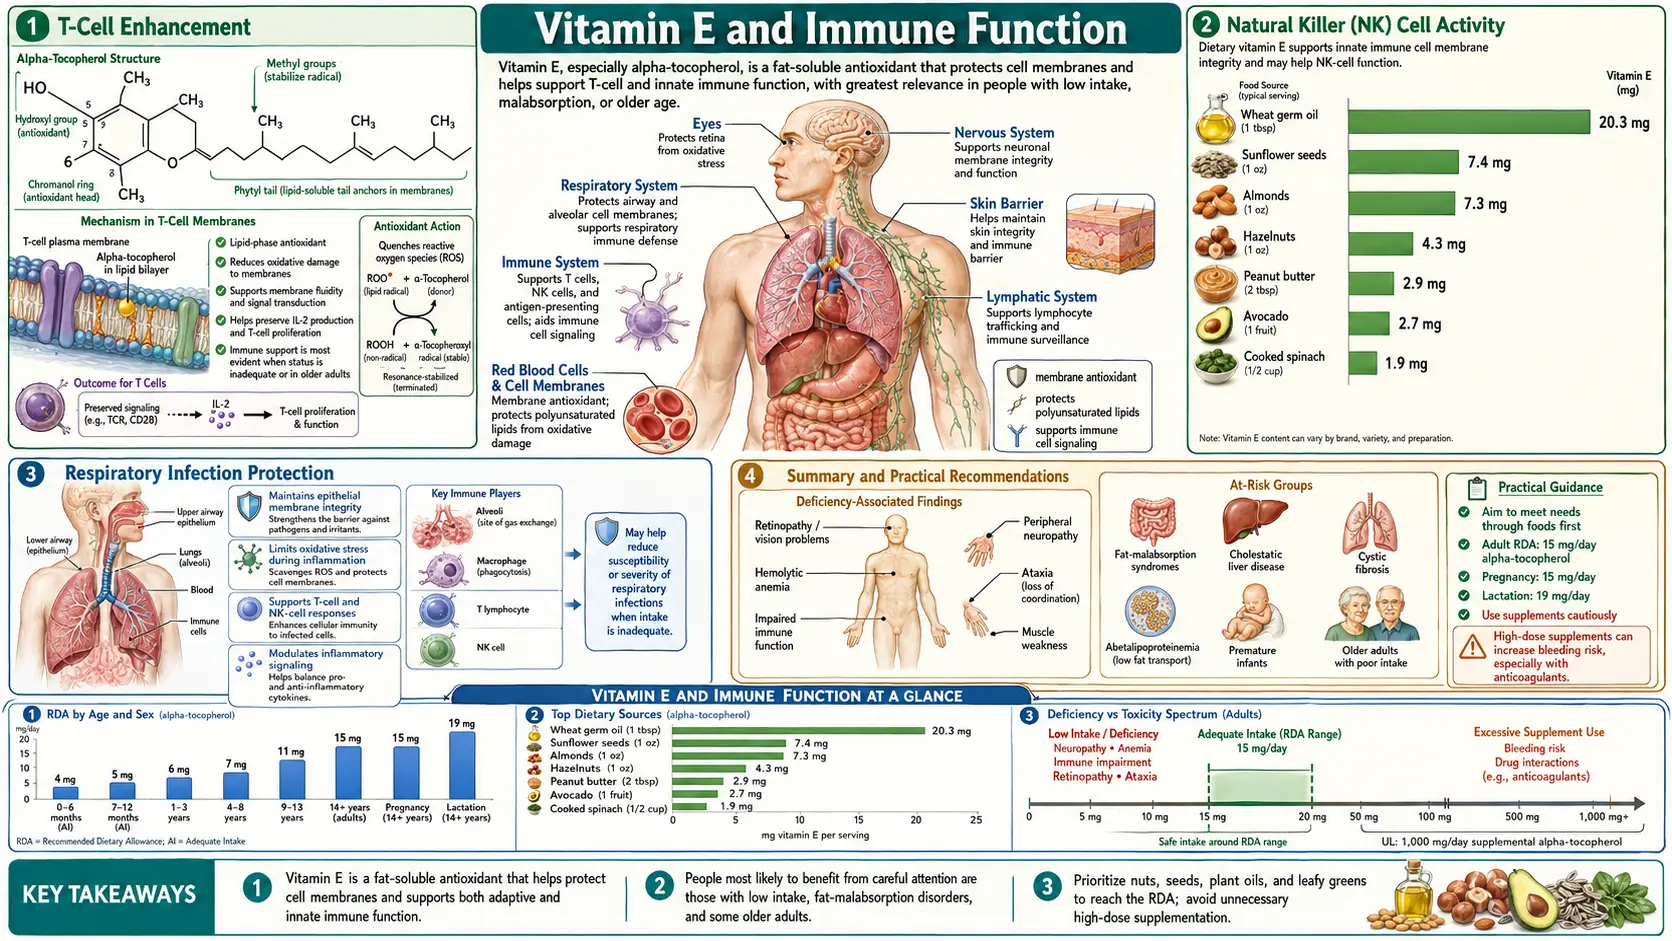
Vitamin E is one of the most potent nutritional modulators of immune function, with effects that are particularly significant in older adults whose immune systems undergo progressive decline through a process known as immunosenescence. The immune system is exceptionally sensitive to oxidative stress — immune cells have high concentrations of polyunsaturated fatty acids in their membranes, they generate reactive oxygen species as part of their antimicrobial arsenal, and they undergo rapid proliferative expansion during immune responses, all of which create enormous demand for antioxidant protection. Vitamin E, as the primary lipid-soluble antioxidant in cell membranes, plays a critical role in maintaining immune cell membrane integrity, modulating intracellular signaling, and regulating the production of immunomodulatory mediators. Decades of research, including landmark studies by Simin Nikbin Meydani and colleagues at Tufts University, have established Vitamin E as a key nutrient for optimal immune function across the lifespan, with the most dramatic benefits observed in the elderly population.
Table of Contents
- T-Cell Enhancement
- Elderly Immune Response and the SENIEUR Protocol Studies
- Natural Killer (NK) Cell Activity
- Prostaglandin E2 (PGE2) Reduction — A Key Mechanism
- Respiratory Infection Protection
- Autoimmune Modulation
- Summary of the Evidence
- Cautions & Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
1. T-Cell Enhancement
T-lymphocytes (T-cells) are central orchestrators of the adaptive immune response, and Vitamin E enhances their function through multiple mechanisms.
- Membrane Protection: T-cells have high concentrations of polyunsaturated fatty acids (PUFAs) in their membranes, making them particularly vulnerable to lipid peroxidation. Vitamin E protects T-cell membranes from oxidative damage, preserving membrane fluidity, receptor function, and signal transduction capacity. Oxidized T-cell membranes have impaired receptor mobility and signaling, leading to reduced responsiveness to antigenic stimulation.
- Immunological Synapse Formation: When a T-cell recognizes an antigen presented by an antigen-presenting cell (APC), it forms an immunological synapse — a structured interface of receptors, signaling molecules, and cytoskeletal elements. Vitamin E supports the membrane reorganization and lipid raft formation required for proper synapse assembly, enhancing the efficiency of antigen recognition and T-cell activation.
- IL-2 Production: Interleukin-2 (IL-2) is the primary T-cell growth factor, essential for T-cell proliferative expansion during immune responses. Vitamin E supplementation increases IL-2 production by T-cells, both by protecting the cells from oxidative suppression and by reducing the inhibitory effects of prostaglandin E2 on IL-2 synthesis.
- T-Cell Proliferation: Multiple clinical studies demonstrate that Vitamin E supplementation significantly enhances T-cell proliferative responses to mitogenic and antigenic stimulation, with the most pronounced effects in elderly individuals whose baseline T-cell proliferation is reduced.
- Th1/Th2 Balance: Aging is associated with a shift from Th1 (cell-mediated) toward Th2 (humoral) immune responses. Vitamin E supplementation may help restore a more balanced Th1/Th2 profile in elderly individuals, supporting cell-mediated immunity against intracellular pathogens and cancer cells.
- CD4+ and CD8+ T-Cell Function: Both helper T-cells (CD4+) and cytotoxic T-cells (CD8+) benefit from Vitamin E supplementation, with improved proliferation, cytokine production, and cytotoxic activity observed in supplemented elderly subjects.
2. Elderly Immune Response and the SENIEUR Protocol Studies
The most compelling evidence for Vitamin E's immune-enhancing effects comes from studies in elderly populations, where immunosenescence creates a measurable window for nutritional intervention.
- Immunosenescence: Aging is associated with progressive decline in immune function characterized by reduced T-cell proliferation, decreased IL-2 production, impaired delayed-type hypersensitivity (DTH) responses, thymic involution, and increased susceptibility to infections. Oxidative stress is a major driver of immunosenescence.
- SENIEUR Protocol: The SENIEUR protocol is a set of rigorous inclusion criteria developed by the European Community's Concerted Action on Aging (EURAGE) to select immunologically healthy elderly individuals for immunogerontological studies. Subjects selected by SENIEUR criteria are free of diseases and medications that affect immune function, allowing researchers to study the effects of aging per se (and nutritional interventions) on immunity without confounding factors.
- Landmark Meydani Study (1997): In a landmark randomized, double-blind, placebo-controlled trial, Simin Meydani and colleagues at Tufts University gave 88 healthy people aged 65 and older placebo or 60, 200 or 800 mg/day of Vitamin E for 235 days. The 200 mg/day group had a 65% increase in DTH responses and a 6-fold rise in hepatitis B vaccine antibodies, against 17% and 3-fold on placebo, 41% and 3-fold on 60 mg/day, and 49% and 2.5-fold on 800 mg/day, so the 200 mg/day dose was the most effective. The 200 mg/day group also had a significant rise in tetanus vaccine antibodies. Vitamin E did not change antibodies to diphtheria vaccine, immunoglobulin levels or the numbers of T and B cells, and the authors observed no adverse effects. The rise in IL-2 production and the fall in PGE2 come from an earlier 1990 trial by the same group (32 older adults, 800 mg/day for 30 days; see the next sections).
- Delayed-Type Hypersensitivity (DTH): DTH responses — skin test reactions to recall antigens such as Candida, tetanus toxoid, and trichophyton — are a clinically meaningful measure of cell-mediated immunity. Vitamin E supplementation at 200 mg/day significantly increased both the number of positive DTH responses and the total diameter of induration, indicating enhanced cell-mediated immune competence.
- Optimal Dose: The finding that 200 mg/day was more effective than 800 mg/day suggests a bell-shaped dose-response curve for Vitamin E's immune effects, with very high doses potentially providing less benefit than moderate doses. This may be related to excessive suppression of reactive oxygen species (ROS) signaling at very high doses, as some reactive oxygen species production is necessary for optimal immune cell activation.
3. Natural Killer (NK) Cell Activity
Natural killer cells are innate immune lymphocytes that provide rapid defense against virally infected cells and cancer cells without requiring prior sensitization.
- Natural killer Cell Cytotoxicity: Vitamin E enhances natural killer cell cytotoxic activity — the ability to recognize and kill target cells through the release of perforin and granzymes. This enhancement is observed in both young and elderly individuals, though the magnitude of improvement is typically greater in the elderly due to their lower baseline natural killer function.
- Membrane-Dependent Recognition: natural killer cell recognition of target cells depends on the interaction between natural killer receptors and ligands on target cell surfaces. Vitamin E's protection of natural killer cell membrane integrity supports proper receptor expression and function, enhancing target cell recognition.
- Cancer Immunosurveillance: Enhanced natural killer cell activity through Vitamin E supplementation may support the immune system's ability to detect and eliminate nascent cancer cells — the process of cancer immunosurveillance — though this hypothesis requires further clinical validation.
- Viral Defense: natural killer cells are critical for early defense against viral infections, particularly herpes viruses, influenza, and other pathogens. Vitamin E's enhancement of natural killer function may contribute to improved antiviral immunity, particularly in elderly individuals whose natural killer cell function is compromised.
4. Prostaglandin E2 (PGE2) Reduction — A Key Mechanism
The reduction of prostaglandin E2 production is considered one of the primary mechanisms by which Vitamin E enhances immune function, particularly in the elderly.
- PGE2 and Immunosuppression: Prostaglandin E2, produced by cyclooxygenase enzymes (primarily cyclooxygenase-2, COX-2) from arachidonic acid, is a potent immunosuppressive mediator. PGE2 inhibits T-cell proliferation, reduces IL-2 and interferon-gamma production, suppresses natural killer cell activity, and shifts immune responses from Th1 toward Th2 predominance.
- Age-Related PGE2 Increase: Aging is associated with increased PGE2 production by macrophages, driven by increased cyclooxygenase-2 expression and elevated arachidonic acid availability. This age-related PGE2 excess is a significant contributor to immunosenescence, creating a suppressory environment that impairs T-cell-mediated immunity.
- Human Evidence: In the 1990 Meydani trial, 32 healthy older adults living in a metabolic research unit took 800 mg of Vitamin E or placebo for 30 days. The Vitamin E group had stronger DTH skin-test responses, more IL-2 production and lower PGE2 production by blood immune cells (peripheral blood mononuclear cells), along with lower lipid peroxides in the blood. The detailed cyclooxygenase mechanism described next, including the role of peroxynitrite (Beharka 2002), comes from studies of macrophages taken from old mice.
- Vitamin E Reduces PGE2: Vitamin E supplementation significantly reduces macrophage PGE2 production through multiple mechanisms: (1) inhibition of cyclooxygenase-2 activity, (2) reduction of arachidonic acid release from membrane phospholipids via phospholipase A2 inhibition, and (3) reduced peroxide tone that activates COX enzymes. By reducing the immunosuppressive PGE2 burden, Vitamin E releases T-cells from PGE2-mediated suppression.
- Cascade Effect: The reduction of PGE2 is not an isolated effect but triggers a cascade of immune improvements: increased IL-2 production, enhanced T-cell proliferation, improved DTH responses, and restored Th1/Th2 balance. This explains why PGE2 reduction is considered the central mechanism of Vitamin E's immune-enhancing effects in the elderly.
- Macrophage Function: While reducing immunosuppressive PGE2 production, Vitamin E does not impair other macrophage functions — phagocytic capacity, antigen presentation, and cytokine production (tumor necrosis factor-alpha and interleukin-1 (IL-1)) are maintained or enhanced, ensuring that the innate immune defense remains intact.
5. Respiratory Infection Protection
Upper and lower respiratory tract infections are leading causes of morbidity and mortality in the elderly, and Vitamin E supplementation may reduce infection risk.
- Nursing Home Studies: A randomized controlled trial by Meydani et al. (2004) in 617 elderly nursing home residents found that Vitamin E supplementation (200 international units (IU)/day for 1 year) had no significant effect on the incidence or number of days of respiratory tract infections — all, upper or lower. Fewer people taking Vitamin E had one or more upper respiratory tract infections (44% against 52%; risk ratio 0.84, P = .05). The authors described a protective effect on upper respiratory tract infections, particularly the common cold, that “merits further investigation.”
- Upper Respiratory Tract Infections: In a post hoc subgroup analysis (one not planned in advance), the Vitamin E group had fewer common colds: 0.67 against 0.81 per person-year (risk ratio 0.83, 95% confidence interval 0.68 to 1.01, P = .06), a borderline result that was not statistically significant for all participants. Among those who completed the study, colds were 20% lower (risk ratio 0.80).
- Dutch Community Trial: A trial of 652 people aged 60 and older living at home in the Netherlands found that 200 mg of Vitamin E a day (median observation 441 days, about 15 months) did not reduce acute respiratory tract infections (incidence rate ratio 1.12). Infections were more severe in the Vitamin E group: illness lasted a median 19 days against 14, fever occurred in 36.7% against 25.2%, and activity was restricted in 52.3% against 41.1%. The authors reported “adverse effects of vitamin E on illness severity.”
- Pneumonia: Some analyses suggest that the effect of Vitamin E on pneumonia risk may depend on baseline characteristics — lighter-weight, less-smoking elderly individuals appeared to benefit more, while heavier smokers did not. The interaction between Vitamin E and smoking in respiratory infection risk remains an area of investigation.
- Immune Mechanism: The respiratory infection protection is likely mediated by Vitamin E's enhancement of mucosal immune defenses, T-cell function, natural killer cell activity, and overall immune competence, enabling more effective pathogen clearance and reduced infection establishment.
- Influenza Protection: In mice infected with influenza, a high-Vitamin E diet lowered the amount of virus in the lungs, with a larger effect in old mice than in young ones (Hayek 1997). This is an animal finding; it suggests that enhanced immune function from Vitamin E may support defense against influenza in the elderly through improved innate immune response and stronger adaptive immunity.
6. Autoimmune Modulation
While Vitamin E is primarily recognized for enhancing immune function, it also possesses immunomodulatory properties that may be relevant to autoimmune conditions.
- Anti-Inflammatory Effects: Vitamin E's anti-inflammatory properties — cyclooxygenase-2 inhibition, PGE2 reduction, NF-kB pathway modulation, and reduction of pro-inflammatory cytokines — may help reduce the chronic inflammatory drive that perpetuates autoimmune tissue damage.
- Oxidative Stress in Autoimmunity: Many autoimmune diseases are characterized by elevated oxidative stress, which can modify self-proteins (creating neo-antigens), activate inflammatory signaling, and amplify tissue damage. Vitamin E's antioxidant protection may reduce these oxidative triggers of autoimmune inflammation.
- Regulatory T-Cell Support: Some research suggests that Vitamin E may support the function of regulatory T-cells (Tregs), which are critical for maintaining immune tolerance and preventing autoimmune responses. Enhanced Treg function could help restrain inappropriate immune activation against self-tissues.
- Rheumatoid Arthritis: Some studies have explored Vitamin E supplementation as an adjunct therapy in rheumatoid arthritis, with mixed results. Vitamin E's anti-inflammatory effects may provide modest symptomatic benefit, but it is not a replacement for disease-modifying therapy.
- Systemic Lupus Erythematosus (SLE): Patients with systemic lupus erythematosus have elevated oxidative stress and often have low Vitamin E levels. Some preliminary studies suggest that Vitamin E supplementation may reduce oxidative stress markers and modestly improve certain disease parameters in systemic lupus erythematosus, though robust clinical trial evidence is limited.
- Balanced Immune Modulation: Vitamin E's value in the context of autoimmunity lies in its ability to modulate rather than simply stimulate immune function — reducing excessive inflammatory responses while preserving antimicrobial defense. This balanced immunomodulatory profile distinguishes Vitamin E from simple immunostimulants.
7. Summary of the Evidence
The evidence supporting Vitamin E's role in immune function is substantial, with the strongest and most clinically relevant data coming from studies in elderly populations.
- Strongest Evidence: Enhancement of T-cell proliferation and IL-2 production, improvement of DTH responses, and reduction of PGE2-mediated immune suppression in elderly individuals are the best-supported immune effects of Vitamin E supplementation.
- Optimal Dose: In the 1997 Meydani trial, 200 mg/day (approximately 200 international units) of alpha-tocopherol gave the largest immune response in the elderly — more than a lower dose (60 mg/day) and more than a very high dose (800 mg/day).
- Target Population: The greatest immune benefit is seen in elderly individuals (65+ years) who are experiencing immunosenescence. Younger, healthy individuals with robust immune function may see less dramatic improvement, as their baseline immune capacity is already high.
- Dietary Sources: A diet rich in nuts (almonds, hazelnuts), seeds (sunflower seeds), avocado, and leafy greens provides Vitamin E along with other immune-supporting nutrients (zinc, selenium, Vitamin C) in a natural food matrix.
- Safety: Moderate-dose Vitamin E supplementation (200-400 international units/day) is generally described as safe for most adults, but the SELECT trial found more prostate cancer in men taking 400 international units/day (see Cautions). The bleeding concern with higher doses is greatest in people on anticoagulant therapy or with bleeding disorders.
Cautions & Drug Interactions
Vitamin E supplementation for immune support is generally well-tolerated, but several clinical considerations apply:
- Dose ceiling for immune benefit — the Meydani 1997 trial found that 200 mg/day produced greater immune enhancement than 800 mg/day, so more was not better in that trial — very high doses (>800 international units/day) may blunt useful reactive-oxygen-species signaling that immune cells need for activation. 200 international units/day is the dose used in the main immune trials.
- Bleeding risk with anticoagulants — even at 200 international units/day, Vitamin E has mild anti-platelet effects, which add to the bleeding risk of warfarin, aspirin, clopidogrel, and fish oil.
- Acute infection — starting high-dose Vitamin E during an active acute infection (e.g. sepsis) raises a theoretical concern. The body's oxidative burst is a critical antimicrobial weapon, and excessive antioxidant suppression could theoretically impair early bacterial clearance. The immune trials gave Vitamin E for months before any infection, not as a treatment for an active one, and their results for infections are mixed: in the Dutch trial of 652 older people, 200 mg a day did not reduce respiratory infections, and the infections lasted longer (median 19 against 14 days) with more fever (36.7% against 25.2%).
- Mixed tocopherols and gamma-tocopherol — gamma-tocopherol contributes to immune effects through reactive-nitrogen-species scavenging and cyclooxygenase-2 and 5-lipoxygenase (5-LOX) inhibition. High-dose alpha-tocopherol monotherapy depletes gamma-tocopherol by 30-50%. Mixed-tocopherol formulations preserve the full immune-relevant tocopherol profile.
- Autoimmune disease patients — Vitamin E's effect in active autoimmune disease is theoretically beneficial (anti-inflammatory) but clinically uncertain. For people with lupus, rheumatoid arthritis, multiple sclerosis, or other autoimmune conditions, Vitamin E is an experimental adjunct, not a replacement for disease-modifying therapy.
- Vaccine timing — in the 1997 Meydani trial, 200 mg/day of Vitamin E for 235 days gave a 6-fold rise in hepatitis B vaccine antibodies (3-fold on placebo) and a significant rise in tetanus antibodies, with no change in diphtheria antibodies. The proposed mechanism is improved T-cell help. Some practitioners describe starting Vitamin E 4-6 weeks before a planned vaccination (e.g. annual flu vaccine) in older adults.
- Smoking and Vitamin E — smokers have higher Vitamin E turnover and lower plasma Vitamin E. Higher dietary Vitamin E intake has been suggested for smokers. The historical signal of more lung cancer in smokers came from high-dose beta-carotene supplements (NOT Vitamin E) (ATBC, CARET). Vitamin E itself did not show this signal.
- Iron co-administration — iron supplements reduce Vitamin E absorption, and some sources describe taking the two supplements at least 8-12 hours apart.
- Prostate cancer in the SELECT trial — in the Selenium and Vitamin E Cancer Prevention Trial (SELECT) of 35,533 men, 400 international units/day of synthetic Vitamin E (all-rac-alpha-tocopheryl acetate) raised prostate cancer risk by 17% compared with placebo (hazard ratio 1.17), an absolute increase of 1.6 cases per 1,000 person-years. The authors concluded that Vitamin E supplementation “significantly increased the risk of prostate cancer among healthy men.”
- Combination regimens described for older adults (65+) — some practitioners describe 200 international units/day mixed-tocopherol Vitamin E with a fat-containing meal, together with zinc (15-30 mg), Vitamin D (1000-2000 international units), Vitamin C (500 mg), and selenium (100-200 mcg), aimed at the most common nutrient-related contributors to immunosenescence.
Key Research Papers
- Meydani SN et al. (1997). Vitamin E supplementation and in vivo immune response in healthy elderly subjects. A randomized controlled trial. JAMA. — PubMed PMID: 9134944
- Meydani SN et al. (2004). Vitamin E and respiratory tract infections in elderly nursing home residents: a randomized controlled trial. JAMA. — PubMed PMID: 15315997
- Meydani SN et al. (1990). Vitamin E supplementation enhances cell-mediated immunity in healthy elderly subjects. American Journal of Clinical Nutrition. — PubMed PMID: 2203257
- Han SN et al. (2000). Vitamin E supplementation increases T helper 1 cytokine production in old mice infected with influenza virus. Immunology. — PubMed PMID: 10929076
- Pae M, Meydani SN, Wu D (2012). The role of nutrition in enhancing immunity in aging. Aging and Disease. — PubMed PMID: 22500273
- Belisle SE et al. (2009). Polymorphisms at cytokine genes may determine the effect of vitamin E on cytokine production in the elderly. Journal of Nutrition. — PubMed PMID: 19710156
- Lewis ED et al. (2019). Regulatory role of vitamin E in the immune system and inflammation. IUBMB Life. — PubMed PMID: 30501009
- Wu D & Meydani SN (2014). Age-associated changes in immune function: impact of vitamin E intervention and the underlying mechanisms. Endocrine, Metabolic & Immune Disorders Drug Targets. — PubMed PMID: 25244230
- Graat JM et al. (2002). Effect of daily vitamin E and multivitamin-mineral supplementation on acute respiratory tract infections in elderly persons: a randomized controlled trial. JAMA. — PubMed PMID: 12169075
- Hayek MG et al. (1997). Vitamin E supplementation decreases lung virus titers in mice infected with influenza. Journal of Infectious Diseases. — PubMed PMID: 9207381
- Beharka AA et al. (2002). Mechanism of vitamin E inhibition of cyclooxygenase activity in macrophages from old mice: role of peroxynitrite. Free Radical Biology and Medicine. — PubMed PMID: 11958951
- Singh U & Devaraj S (2007). Vitamin E: inflammation and atherosclerosis. Vitamins and Hormones. — PubMed PMID: 17628188
- Klein EA et al. (2011). Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. — PubMed PMID: 21990298
PubMed Topic Searches
- PubMed: Vitamin E and immune function
- PubMed: Vitamin E and immunosenescence in the elderly
- PubMed: Meydani — Vitamin E and T-cell function
- PubMed: Vitamin E and natural killer (NK) cells
- PubMed: Vitamin E and prostaglandin E2 (PGE2)
- PubMed: Vitamin E and respiratory infection in the elderly
- PubMed: Alpha-tocopherol and IL-2 production
- PubMed: Vitamin E and delayed-type hypersensitivity (DTH)
- PubMed: Tocotrienols and immune function
- PubMed: Vitamin E and autoimmune disease
- PubMed: Vitamin E and vaccine response
- PubMed: Gamma-tocopherol and inflammation
Connections
- All Vitamins
- Vitamin E (Main Page)
- Vitamin E Benefits Hub
- Vitamin E and Heart Health
- Vitamin E and Skin Health
- Tocotrienols — The Other Vitamin E Family
- Vitamin C
- Vitamin C and Immune Defense
- Vitamin D3
- Vitamin A
- Zinc
- Selenium
- Immune Boosting
- Oxidative Stress
- Cancer
- Influenza
- Arthritis
- Almonds
- Walnuts
- Deficiency
- Toxicity
- History
- Sources