⚠ Evidence warning: Clinical trials or other evidence do not support the claims that mixed tocopherols protect the heart better than alpha-tocopherol alone, or the 200 international units a day mixed-tocopherol protocol described here. This page keeps it as a report of what people, websites or other media say.
Vitamin E and Cardiovascular Health
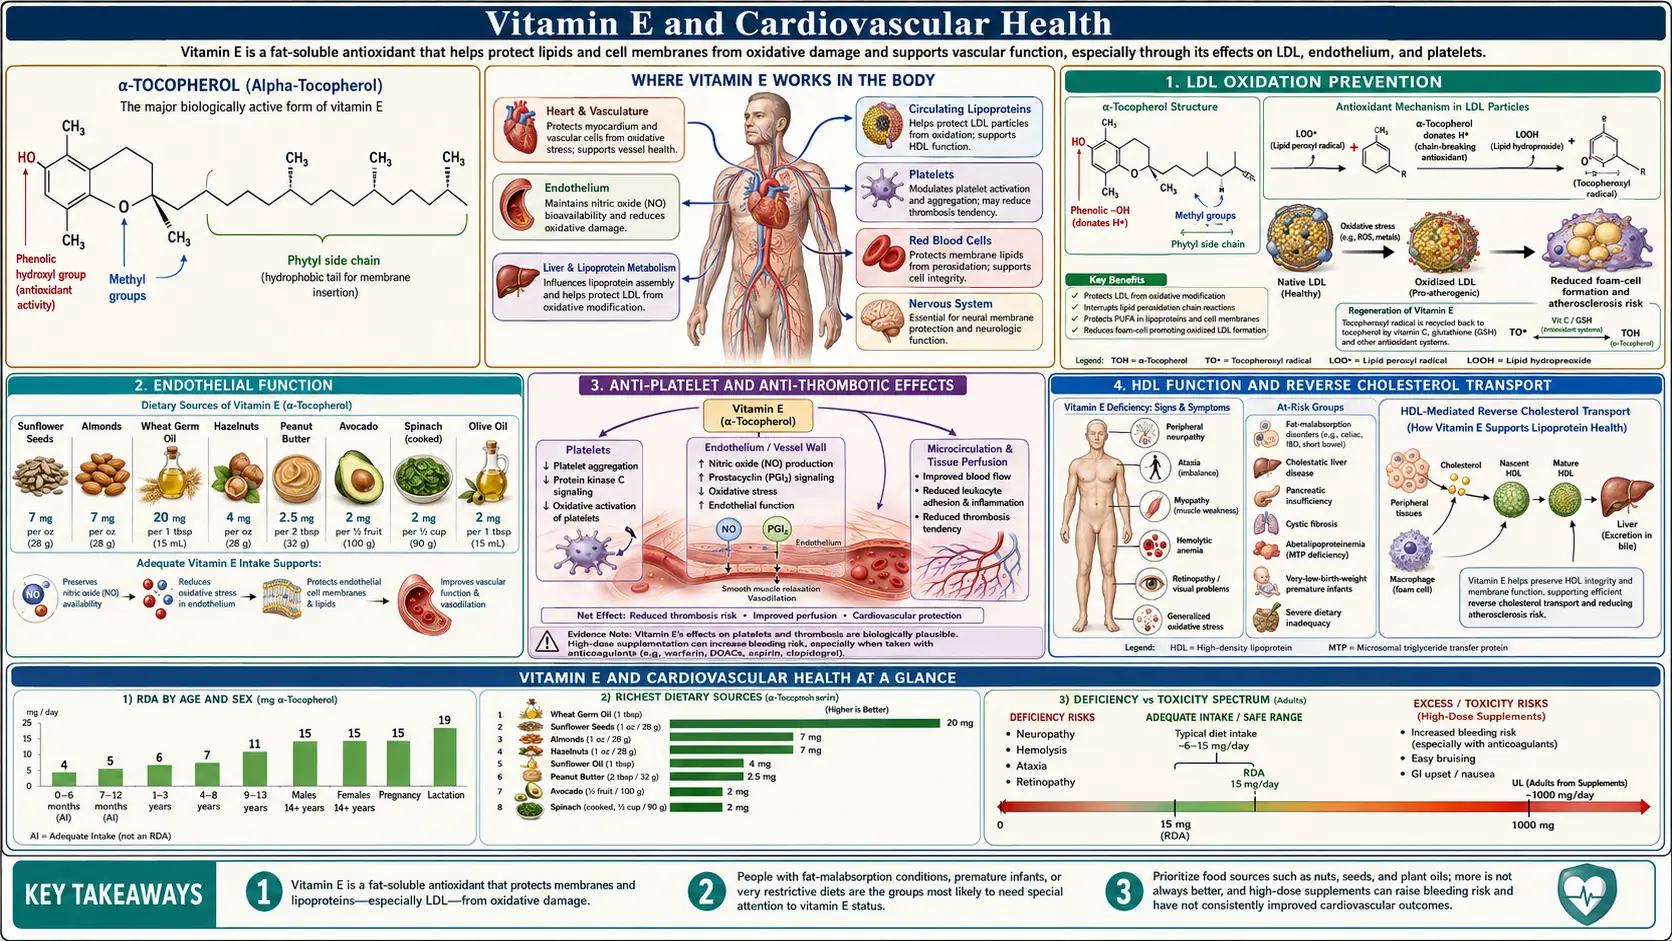
The relationship between Vitamin E and cardiovascular health has been one of the most intensively studied and debated topics in nutritional medicine over the past four decades. The oxidative modification hypothesis of atherosclerosis — which proposes that oxidation of low-density lipoprotein (LDL) cholesterol is a critical early step in the development of atherosclerotic plaques — placed Vitamin E at the center of cardiovascular prevention research, as it is the primary antioxidant within low-density lipoprotein particles. Early epidemiological studies and biological plausibility generated tremendous enthusiasm for Vitamin E supplementation as a cardiovascular protectant. However, large randomized controlled trials produced unexpectedly mixed results, leading to a more nuanced understanding of how Vitamin E interacts with the complex pathophysiology of cardiovascular disease. This page examines the biochemical mechanisms, clinical trial evidence, and current understanding of Vitamin E's role in heart and vascular health.
Table of Contents
- Low-Density Lipoprotein Oxidation Prevention
- Endothelial Function
- Anti-Platelet and Anti-Thrombotic Effects
- High-Density Lipoprotein Function and Reverse Cholesterol Transport
- Vascular Inflammation
- Major Clinical Trials — Evidence and Interpretation
- Gamma-Tocopherol's Cardiovascular Role
- Current Evidence Summary and Guideline Positions
- The 2022 US Preventive Services Task Force Position on Vitamin E
- Vitamin E in Diabetes With the Haptoglobin 2-2 Gene Type
- Cautions & Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
1. Low-Density Lipoprotein Oxidation Prevention
The oxidation of low-density lipoprotein (LDL) cholesterol is a pivotal event in the initiation and progression of atherosclerosis, and Vitamin E's role as the primary low-density lipoprotein antioxidant is its most studied cardiovascular mechanism.
- Low-density lipoprotein Structure and Vulnerability: Each low-density lipoprotein particle contains a core of cholesteryl esters and triglycerides surrounded by a surface monolayer of phospholipids, free cholesterol, and apolipoprotein B-100. The polyunsaturated fatty acids in low-density lipoprotein's lipid core and surface phospholipids are highly susceptible to oxidative attack by reactive oxygen species generated in the arterial wall.
- Vitamin E as low-density lipoprotein Antioxidant: Each low-density lipoprotein particle typically contains 6-12 molecules of alpha-tocopherol, which serve as the first and most important line of antioxidant defense within the particle. Vitamin E intercepts lipid peroxyl radicals, donating a hydrogen atom to terminate chain reactions of lipid peroxidation within the low-density lipoprotein particle.
- Oxidized low-density lipoprotein and Atherosclerosis: Native (unoxidized) low-density lipoprotein is not recognized by scavenger receptors on macrophages in the arterial intima. However, when low-density lipoprotein becomes oxidized, it is avidly taken up by scavenger receptors (CD36, SR-A), leading to unregulated cholesterol accumulation and the formation of lipid-laden foam cells — the defining feature of early atherosclerotic lesions (fatty streaks).
- Monocyte Recruitment: Oxidized low-density lipoprotein stimulates endothelial cells to express adhesion molecules (VCAM-1, ICAM-1) and secrete monocyte chemotactic protein-1 (MCP-1), promoting the recruitment of monocytes into the arterial wall where they differentiate into macrophages and become foam cells.
- Ex Vivo Evidence: Numerous studies demonstrate that Vitamin E supplementation significantly increases the resistance of low-density lipoprotein to oxidation in ex vivo laboratory assays. The lag time before low-density lipoprotein oxidation begins is consistently and dose-dependently prolonged by Vitamin E supplementation.
- Oxidized Phospholipids: Beyond lipid peroxidation, oxidized phospholipids generated during low-density lipoprotein oxidation (such as oxidized phosphatidylcholine) are potent pro-inflammatory mediators that activate endothelial cells and macrophages. Vitamin E reduces the formation of these bioactive oxidized lipids.
2. Endothelial Function
The vascular endothelium plays a critical role in cardiovascular health, and Vitamin E supports endothelial function through multiple mechanisms.
- Nitric Oxide Preservation: Reactive oxygen species, particularly superoxide, rapidly react with nitric oxide (NO) to form peroxynitrite, reducing NO bioavailability. Since NO is the primary endothelium-derived vasodilator and anti-atherogenic molecule, this oxidative destruction of NO impairs vasodilation and promotes vascular disease. Vitamin E reduces superoxide generation and preserves NO bioavailability.
- Endothelial Nitric Oxide Synthase (eNOS): Vitamin E supports the function and coupling of eNOS, the enzyme responsible for producing NO in endothelial cells. Under conditions of oxidative stress, eNOS can become "uncoupled," producing superoxide instead of NO — a process that Vitamin E helps prevent.
- Flow-Mediated Dilation: Several clinical studies have demonstrated that Vitamin E supplementation improves flow-mediated dilation (FMD), a non-invasive measure of endothelial function, particularly in individuals with impaired endothelial function at baseline (diabetics, smokers, patients with coronary artery disease).
- Adhesion Molecule Reduction: Vitamin E reduces endothelial expression of vascular cell adhesion molecule-1 (VCAM-1) and intercellular adhesion molecule-1 (ICAM-1), decreasing the adhesion of monocytes and leukocytes to the endothelium — an early step in atherogenesis.
- Endothelin-1 Modulation: Vitamin E may reduce the production of endothelin-1, a potent vasoconstrictor and pro-inflammatory peptide produced by endothelial cells, contributing to improved vascular tone and reduced vascular inflammation.
3. Anti-Platelet and Anti-Thrombotic Effects
Vitamin E has significant anti-platelet properties that may reduce the risk of thrombotic cardiovascular events.
- Protein Kinase C Inhibition: Alpha-tocopherol directly inhibits protein kinase C (PKC) in platelets, a key signaling enzyme involved in platelet activation and aggregation. This inhibition is independent of Vitamin E's antioxidant activity and represents a direct cell-signaling effect.
- Thromboxane A2 Reduction: Vitamin E inhibits the synthesis of thromboxane A2 (TXA2), a potent platelet aggregator and vasoconstrictor produced by activated platelets. Reduced TXA2 production decreases platelet aggregation tendency.
- Prostacyclin Enhancement: Some studies suggest that Vitamin E may enhance the production of prostacyclin (PGI2) by endothelial cells. Prostacyclin is a vasodilator and platelet aggregation inhibitor, and a favorable balance of prostacyclin over thromboxane promotes vascular health.
- Platelet Adhesion Reduction: Vitamin E reduces platelet adhesion to collagen and other subendothelial matrix components exposed at sites of vascular injury, potentially reducing thrombus formation at atherosclerotic plaque rupture sites.
- Clinical Significance: Vitamin E's anti-platelet effects are clinically relevant — they may contribute to cardiovascular protection but also necessitate caution in patients on anticoagulant or antiplatelet therapy (warfarin, aspirin, clopidogrel) and in pre-surgical settings.
4. High-Density Lipoprotein Function and Reverse Cholesterol Transport
Emerging research suggests that Vitamin E may influence the functionality of high-density lipoprotein (HDL) and the reverse cholesterol transport pathway.
- High-density lipoprotein Antioxidant Capacity: high-density lipoprotein particles carry antioxidant enzymes (paraoxonase-1, platelet-activating factor acetylhydrolase) and contain Vitamin E. The antioxidant capacity of high-density lipoprotein is important for its anti-atherogenic function, as high-density lipoprotein protects low-density lipoprotein from oxidation and removes oxidized lipids from the arterial wall.
- Paraoxonase-1 (PON-1) Activity: Some studies suggest that Vitamin E supplementation may support the activity of paraoxonase-1, a high-density lipoprotein-associated enzyme that hydrolyzes oxidized lipids and protects both high-density lipoprotein and low-density lipoprotein from oxidative modification.
- Reverse Cholesterol Transport: high-density lipoprotein's ability to promote cholesterol efflux from macrophage foam cells in the arterial wall — the first step of reverse cholesterol transport — may be preserved or enhanced by the antioxidant protection provided by Vitamin E, which helps maintain high-density lipoprotein particle integrity and receptor interactions.
5. Vascular Inflammation
Atherosclerosis is now understood as a chronic inflammatory disease of the arterial wall, and Vitamin E's anti-inflammatory effects are relevant to cardiovascular protection.
- NF-kB Inhibition: Vitamin E inhibits the activation of nuclear factor kappa-B (NF-kB) in vascular cells, reducing the transcription of genes encoding pro-inflammatory cytokines (tumor necrosis factor-alpha, interleukin-1 beta, interleukin-6), adhesion molecules (VCAM-1, ICAM-1, E-selectin), and chemokines (MCP-1) that drive vascular inflammation.
- C-Reactive Protein (CRP) Reduction: Some clinical studies have demonstrated that Vitamin E supplementation reduces circulating levels of high-sensitivity C-reactive protein (hs-CRP), a systemic marker of inflammation and an independent predictor of cardiovascular events.
- Monocyte-Endothelial Interaction: Vitamin E reduces monocyte adhesion to endothelial cells by decreasing both adhesion molecule expression on the endothelium and the expression of integrins on monocytes, reducing the inflammatory cell infiltration that drives plaque development.
- Smooth Muscle Cell Proliferation: Alpha-tocopherol inhibits vascular smooth muscle cell proliferation through PKC inhibition. Smooth muscle cell proliferation contributes to plaque growth and arterial remodeling in atherosclerosis, and its inhibition by Vitamin E represents an anti-atherogenic mechanism.
- Gamma-Tocopherol's Unique Role: Gamma-tocopherol possesses anti-inflammatory properties not shared by alpha-tocopherol, including the ability to scavenge reactive nitrogen species (peroxynitrite, NO2) and to inhibit both cyclooxygenase-2 and 5-lipoxygenase. These properties may make gamma-tocopherol an important but underappreciated contributor to cardiovascular protection.
6. Major Clinical Trials — Evidence and Interpretation
The clinical trial evidence for Vitamin E in cardiovascular disease prevention has been the subject of extensive analysis and debate.
- ATBC Study (Alpha-Tocopherol, Beta-Carotene Cancer Prevention Study, 1994): This Finnish trial of 29,133 male smokers found that alpha-tocopherol supplementation (50 mg/day) did not significantly reduce the incidence of major coronary events, though post-hoc analyses suggested a reduction in prostate cancer risk. The relatively low dose of Vitamin E may have limited the study's ability to detect cardiovascular benefit. The participants were male smokers aged 50-69 in a primary-prevention trial aimed at lung and other cancers, not people selected for advanced disease; a separate substudy followed the 1,862 men who had already had a myocardial infarction (heart attack) and found no significant difference in major coronary events on alpha-tocopherol (Rapola 1997).
- CHAOS Study (Cambridge Heart Antioxidant Study, 1996): This trial of 2,002 patients with angiographically proven coronary atherosclerosis showed that Vitamin E supplementation (400-800 international units (IU)/day) significantly reduced non-fatal myocardial infarction by 77%, though there was a non-significant trend toward increased cardiovascular mortality. The dramatic non-fatal myocardial infarction (MI) reduction generated substantial enthusiasm but was not consistently replicated.
- GISSI-Prevenzione (1999): This Italian trial of 11,324 patients who had survived a recent myocardial infarction found no significant benefit of synthetic Vitamin E (300 mg/day) on the combined endpoint of death, non-fatal myocardial infarction, and stroke. The authors wrote that Vitamin E "had no benefit" and that its effects on fatal cardiovascular events "require further exploration". The reductions in cardiovascular death in the trial's abstract (17% and 30%) belong to the n-3 fatty acid groups, not to Vitamin E.
- HOPE Study (Heart Outcomes Prevention Evaluation, 2000): This landmark trial of 9,541 high-risk patients (with vascular disease or diabetes) found that natural Vitamin E (400 international units/day) provided no cardiovascular benefit over 4.5 years. The HOPE-TOO extension found that long-term Vitamin E supplementation was associated with increased risk of heart failure.
- WAVE Study (Women's Angiographic Vitamin and Estrogen, 2002): This trial of 423 postmenopausal women with coronary disease found that Vitamin E (400 international units twice daily) plus Vitamin C (500 mg twice daily) did not slow angiographic coronary progression. There were 16 deaths in the vitamin group and 6 in the placebo group (hazard ratio 2.8; 95% confidence interval 1.1-7.2), and when death or myocardial infarction was counted, the primary outcome suggested increased risk (P=.09). The authors concluded that "a potential for harm was suggested".
- Women's Health Study (2005): This large trial of 39,876 healthy women found that Vitamin E (600 international units every other day) did not reduce the risk of major cardiovascular events overall but showed a significant 24% reduction in cardiovascular mortality, a secondary endpoint.
- Physicians' Health Study II (2008): This trial of 14,641 US male physicians aged 50 or older, followed for a mean of 8 years, found that Vitamin E (400 international units every other day) had no effect on major cardiovascular events (hazard ratio 1.01; 95% confidence interval 0.90-1.13). It was associated with more hemorrhagic (bleeding) strokes (hazard ratio 1.74; 95% confidence interval 1.04-2.91).
- Miller Pooled Analysis (2005): This analysis of 19 trials and 135,967 people found 39 more deaths per 10,000 people in trials using 400 international units/day or more (95% confidence interval 3 to 74), with risk rising at doses above 150 international units/day. The authors note that the high-dose trials were often small and in people with chronic diseases, so how far the finding applies to healthy adults is uncertain.
7. Gamma-Tocopherol's Cardiovascular Role
The focus of most clinical trials on alpha-tocopherol alone has obscured the potentially important cardiovascular contributions of gamma-tocopherol.
- Dietary Predominance: Gamma-tocopherol is the most abundant form of Vitamin E in the typical Western diet (primarily from soybean, corn, and canola oils). Many individuals consuming a Western diet have higher gamma-tocopherol intake than alpha-tocopherol intake.
- Unique Anti-Inflammatory Properties: Gamma-tocopherol traps reactive nitrogen species (peroxynitrite and nitrogen dioxide) that alpha-tocopherol cannot effectively neutralize. These reactive nitrogen species are significant mediators of vascular inflammation and endothelial dysfunction.
- Alpha-Tocopherol Displacement Effect: High-dose alpha-tocopherol supplementation significantly reduces plasma gamma-tocopherol levels by 30-50%, as the alpha-tocopherol transfer protein preferentially binds alpha-tocopherol and accelerates gamma-tocopherol catabolism. This displacement effect means that alpha-tocopherol-only supplementation may inadvertently remove a beneficial cardiovascular nutrient.
- Epidemiological Evidence: Some epidemiological studies have found that plasma gamma-tocopherol levels are inversely associated with cardiovascular disease risk, independent of alpha-tocopherol levels. The highest gamma-tocopherol levels are associated with the lowest cardiovascular risk in several cohort studies.
- Natriuretic Factor: Gamma-tocopherol's metabolite, gamma-CEHC, has natriuretic (sodium-excreting) properties that may contribute to blood pressure regulation — a cardiovascular benefit not provided by alpha-tocopherol.
- Mixed Tocopherol Hypothesis: Some researchers hypothesize that the disappointing results of alpha-tocopherol-only cardiovascular trials may be partly explained by the depletion of gamma-tocopherol. Trials using mixed tocopherols (alpha + gamma + delta) might yield different results, though this hypothesis remains to be tested in large-scale trials.
- What the Gamma-Tocopherol Studies Measured: Jiang 2000 is a cell-culture study: gamma-tocopherol lowered an inflammatory signal (prostaglandin E2) in macrophage cells and human epithelial cells, while alpha-tocopherol lowered it by 25% in macrophages and not at all in epithelial cells. Devaraj 2008 gave 800 mg/day of gamma-tocopherol, alpha-tocopherol, both, or placebo for 6 weeks to 20 people per group with metabolic syndrome and measured blood and urine markers of oxidative stress and inflammation, not heart attacks or strokes. Its authors wrote that the combination needs testing in prospective clinical trials.
8. Current Evidence Summary and Guideline Positions
The totality of evidence regarding Vitamin E and cardiovascular health requires a balanced interpretation that accounts for both the strong biological plausibility and the mixed clinical trial results.
- Dietary Vitamin E: Epidemiological studies consistently show that higher dietary Vitamin E intake from food sources (nuts, seeds, vegetable oils, whole grains) is associated with reduced cardiovascular risk. Dietary Vitamin E provides a natural mixture of tocopherols (alpha, gamma, delta) and tocotrienols, along with other protective nutrients present in Vitamin E-rich foods.
- Supplementation Uncertainty: Large-scale randomized trials have not demonstrated consistent cardiovascular benefit from alpha-tocopherol supplementation, and some studies have raised safety concerns at high doses. The American Heart Association does not currently recommend Vitamin E supplementation for cardiovascular disease prevention.
- Possible Explanations for Trial Failures: Several factors may explain the discrepancy between strong biological mechanisms and disappointing trial results: (1) use of alpha-tocopherol alone (depleting gamma-tocopherol), (2) use of synthetic forms with lower bioactivity, (3) enrollment of patients with advanced disease where oxidative damage is already extensive, (4) inadequate trial duration, (5) failure to select patients based on baseline Vitamin E status or oxidative stress levels, (6) complex interactions with other medications and nutrients.
- Food Sources: Food sources of Vitamin E include nuts (almonds, hazelnuts), seeds (sunflower seeds), healthy oils (olive oil, avocado oil), and leafy green vegetables. A diet rich in these foods provides a natural spectrum of Vitamin E forms along with other cardiovascular-protective nutrients.
- Targeted Supplementation: Some sources describe mixed tocopherol formulations (containing alpha, gamma, and delta tocopherols) as preferable to alpha-tocopherol alone; large-scale trials have not tested this. Moderate doses (200-400 international units/day) have been described as safe for most adults, while the 2005 Miller pooled analysis found more deaths at 400 international units/day or more and rising risk above 150 international units/day (see Major Clinical Trials). Vitamin E above 400 international units/day can raise the international normalized ratio (INR) and bleeding risk in people on warfarin.
- Ongoing Research: Research continues into the cardiovascular effects of tocotrienols, gamma-tocopherol, mixed tocopherol formulations, and the role of Vitamin E in specific cardiovascular conditions. Future trials designed with the lessons of past studies may provide clearer answers about which forms, doses, and populations may benefit from Vitamin E supplementation for cardiovascular protection.
The 2022 US Preventive Services Task Force Position on Vitamin E
The US Preventive Services Task Force reviewed vitamin and mineral supplements in 2022 for community-dwelling, nonpregnant adults. It concluded with moderate certainty that Vitamin E supplements give no net benefit for preventing cardiovascular disease or cancer, and it recommends against them for that purpose (a "D" recommendation).
Vitamin E in Diabetes With the Haptoglobin 2-2 Gene Type
Haptoglobin is a blood protein, and people with diabetes who carry the 2-2 gene type for it are at higher risk of cardiovascular disease. A 2010 analysis went back to people with diabetes in two trials (HOPE and ICARE), tested their gene type, and pooled the results for those with the 2-2 type. On Vitamin E they had fewer strokes, heart attacks and cardiovascular deaths combined (odds ratio 0.58; 95% confidence interval 0.40-0.86). In these trials, testing 69 people with diabetes and treating those with the 2-2 type prevented one such event.
This is a subgroup finding within trials whose overall results are reported above, not a new trial of the gene-test approach.
Cautions & Drug Interactions
Vitamin E supplementation for cardiovascular protection requires awareness of several important interactions and clinical considerations.
- Warfarin and other anticoagulants — Vitamin E at doses above 400 international units/day can potentiate the anticoagulant effect of warfarin, increasing international normalized ratio (INR) and bleeding risk. More frequent international normalized ratio checks are described for at least 4 weeks after starting, stopping, or changing the dose.
- Antiplatelet drugs (aspirin, clopidogrel, ticagrelor) — Vitamin E adds an anti-platelet effect through PKC inhibition and reduced thromboxane A2 synthesis. The combination is not absolutely contraindicated but increases bleeding risk.
- Fish oil (eicosapentaenoic acid (EPA)/docosahexaenoic acid (DHA)) — combination further increases bleeding risk. Many integrative protocols use both at moderate doses; the added bleeding risk matters most before surgery or invasive procedures.
- Pre-surgical discontinuation — most surgeons recommend stopping high-dose Vitamin E supplements 2 weeks before elective surgery, particularly cardiac, neurosurgical, or orthopedic procedures where intraoperative bleeding is a concern.
- Heart failure (HOPE-TOO finding) — long-term high-dose alpha-tocopherol (400 international units/day for >4 years) was associated with a 13% increased risk of heart failure (relative risk 1.13; 95% confidence interval 1.01-1.26) and a 21% increased risk of hospitalization for heart failure (relative risk 1.21; 95% confidence interval 1.00-1.47) in the HOPE and HOPE-TOO report. The research raises a concern for people with established heart failure or high heart-failure risk who take chronic high-dose alpha-tocopherol alone.
- SELECT prostate cancer signal — alpha-tocopherol 400 international units/day alone produced a 17% increase in prostate cancer incidence in the SELECT trial of relatively healthy men, an absolute increase of 1.6 prostate cancers per 1,000 person-years. The research raises a concern for men on chronic high-dose alpha-tocopherol alone, and some sources single out men with a family history of prostate cancer. Mixed-tocopherol formulations are described by some as safer; no large trial has tested that.
- Hemorrhagic stroke — meta-analyses suggest a small (~22%) relative increase in hemorrhagic stroke risk with Vitamin E supplementation, balanced by a small decrease in ischemic stroke. A 2010 pooled analysis (risk ratios 1.22 and 0.90) put this at about one extra bleeding stroke per 1,250 people taking Vitamin E and one clot-type stroke prevented per 476. The research raises a concern for people with prior hemorrhagic stroke or significant hemorrhage risk factors.
- Synthetic vs natural distinction — HOPE used natural-source Vitamin E (the more bioactive form), while SELECT used a synthetic form (all rac-alpha-tocopheryl acetate), both at 400 international units/day. So these negative signals appeared with both forms. Dose reduction and mixed-tocopherol formulations are described as ways to lessen the signal; large trials have not tested mixed tocopherols.
- Statin interaction — some early data suggested antioxidant cocktails (Vitamin E + Vitamin C + selenium + beta-carotene) could blunt the high-density lipoprotein-raising effect of simvastatin + niacin in the HATS trial: over 12 months in 153 people with coronary disease and low high-density lipoprotein, it rose 25% on simvastatin-niacin and 18% with antioxidants added, and its HDL2 fraction rose 42% and 0%. Whether this applies to Vitamin E alone at moderate doses is unclear. Moderate doses (200 international units) are described as an alternative to high doses alongside a statin.
- Iron interaction — Vitamin E and iron supplements are described as being taken at least 8-12 hours apart, because iron oxidizes Vitamin E in the gut, reducing absorption.
- A described cardiovascular protocol — one regimen in circulation for people who choose to supplement: 200 international units/day mixed tocopherols (alpha + gamma + delta) with food, paired with Vitamin C (500-1000 mg) for E-recycling, dietary nut/seed intake, and Mediterranean-pattern diet. The large trials above did not find cardiovascular benefit from high-dose alpha-tocopherol alone (>400 international units/day), in primary or secondary prevention, and the 2022 US Preventive Services Task Force recommends against Vitamin E supplements for prevention.
Key Research Papers
- Stephens NG et al. (1996). Randomised controlled trial of vitamin E in patients with coronary disease: Cambridge Heart Antioxidant Study (CHAOS). Lancet. — PubMed PMID: 8622332
- Yusuf S et al. (2000). Vitamin E supplementation and cardiovascular events in high-risk patients (HOPE trial). New England Journal of Medicine. — PubMed PMID: 10639540
- Lonn E et al. (2005). Effects of long-term vitamin E supplementation on cardiovascular events and cancer: a randomized controlled trial (HOPE-TOO). JAMA. — PubMed PMID: 15769967
- GISSI-Prevenzione Investigators (1999). Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction. Lancet. — PubMed PMID: 10465168
- Rapola JM et al. (1997). Randomised trial of alpha-tocopherol and beta-carotene supplements on incidence of major coronary events in men with previous myocardial infarction (ATBC subgroup). Lancet. — PubMed PMID: 9193380
- Lee IM et al. (2005). Vitamin E in the primary prevention of cardiovascular disease and cancer: the Women's Health Study. JAMA. — PubMed PMID: 15998891
- Sesso HD et al. (2008). Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomized controlled trial. JAMA. — PubMed PMID: 18997197
- Boshtam M et al. (2002). Vitamin E can reduce blood pressure in mild hypertensives. International Journal for Vitamin and Nutrition Research. — PubMed PMID: 12463106
- Devaraj S et al. (2008). Gamma-tocopherol supplementation alone and in combination with alpha-tocopherol alters biomarkers of oxidative stress and inflammation in subjects with metabolic syndrome. Free Radical Biology and Medicine. — PubMed PMID: 18191645
- Jiang Q et al. (2000). gamma-Tocopherol and its major metabolite, in contrast to alpha-tocopherol, inhibit cyclooxygenase activity in macrophages and epithelial cells. PNAS. — PubMed PMID: 11005841
- Boaz M et al. (2000). Secondary prevention with antioxidants of cardiovascular disease in endstage renal disease (SPACE): randomised placebo-controlled trial. Lancet. — PubMed PMID: 11072938
- Schwingshackl L et al. (2017). An umbrella review of nuts intake and risk of cardiovascular disease. Current Pharmaceutical Design. — PubMed PMID: 27748190
- Saremi A & Arora R (2010). Vitamin E and cardiovascular disease. American Journal of Therapeutics. — PubMed PMID: 19451807
- Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group (1994). The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. New England Journal of Medicine. — PubMed PMID: 8127329
- Waters DD et al. (2002). Effects of hormone replacement therapy and antioxidant vitamin supplements on coronary atherosclerosis in postmenopausal women: a randomized controlled trial. JAMA. — PubMed PMID: 12435256
- Miller ER 3rd et al. (2005). Meta-analysis: high-dosage vitamin E supplementation may increase all-cause mortality. Annals of Internal Medicine. — PubMed PMID: 15537682
- Klein EA et al. (2011). Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. — PubMed PMID: 21990298
- Schürks M et al. (2010). Effects of vitamin E on stroke subtypes: meta-analysis of randomised controlled trials. BMJ. — PubMed PMID: 21051774
- Cheung MC et al. (2001). Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arteriosclerosis, Thrombosis, and Vascular Biology. — PubMed PMID: 11498460
- Blum S et al. (2010). Vitamin E reduces cardiovascular disease in individuals with diabetes mellitus and the haptoglobin 2-2 genotype. Pharmacogenomics. — PubMed PMID: 20415560
- US Preventive Services Task Force, Mangione CM et al. (2022). Vitamin, Mineral, and Multivitamin Supplementation to Prevent Cardiovascular Disease and Cancer: US Preventive Services Task Force Recommendation Statement. JAMA. — PubMed PMID: 35727271
PubMed Topic Searches
- PubMed: Vitamin E and cardiovascular disease
- PubMed: Alpha-tocopherol and LDL oxidation
- PubMed: Gamma-tocopherol and cardiovascular risk
- PubMed: Vitamin E and endothelial function
- PubMed: HOPE trial — Vitamin E and cardiovascular outcomes
- PubMed: CHAOS trial — Vitamin E in coronary atherosclerosis
- PubMed: Vitamin E and platelet aggregation
- PubMed: Mixed tocopherols and atherosclerosis
- PubMed: Tocotrienols and cardiovascular health
- PubMed: Vitamin E and C-reactive protein (CRP)
- PubMed: Vitamin E, nitric oxide, and endothelium
- PubMed: GISSI-Prevenzione — Vitamin E post-MI
Connections
- All Vitamins
- Vitamin E (Main Page)
- Vitamin E Benefits Hub
- Vitamin E and Immune Function
- Vitamin E and Skin Health
- Tocotrienols — The Other Vitamin E Family
- Cardiovascular Disease
- Coronary Artery Disease
- Atherosclerosis
- Hypertension
- Stroke
- Vitamin C
- Vitamin K
- Vitamin K2 and Arterial Calcification
- Magnesium
- Magnesium and Heart Health
- Niacin and Cholesterol
- Oxidative Stress
- Almonds
- Deficiency
- Toxicity
- History
- Sources