Vitamin E Toxicity: Symptoms, Causes, and Risks
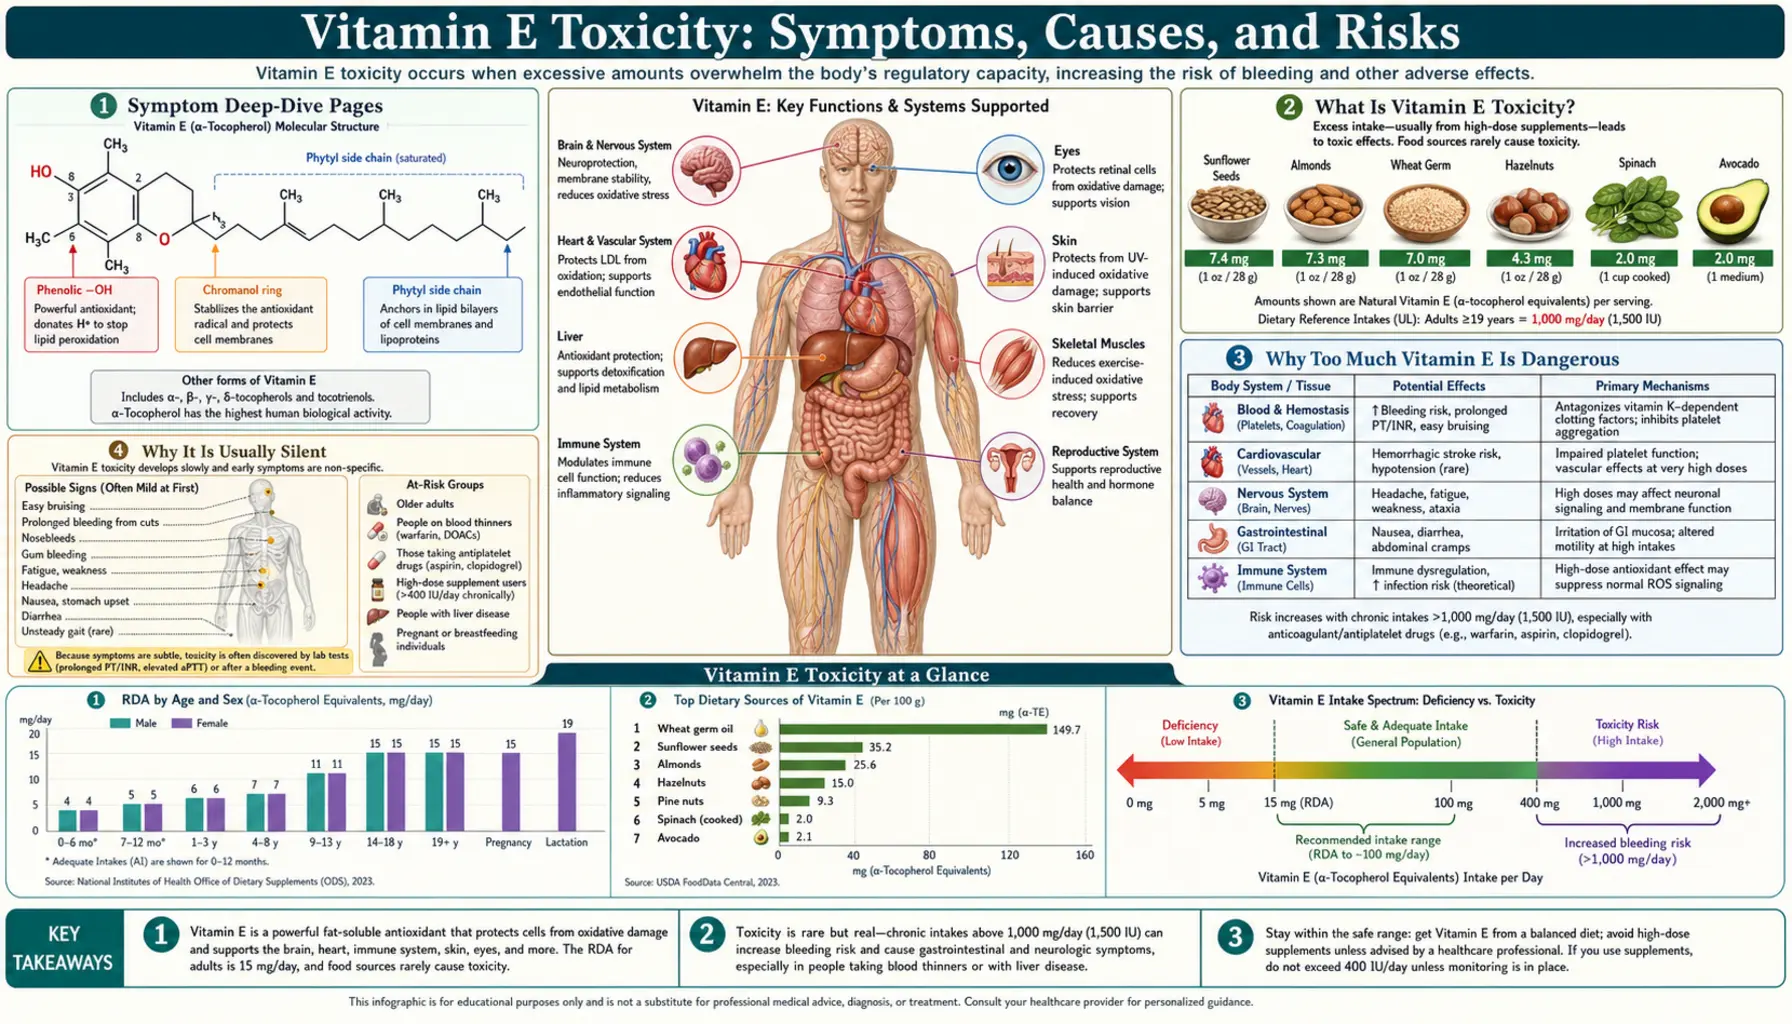
Vitamin E is a fat-soluble antioxidant that the body cannot easily flush away, so unlike the water-soluble vitamins, a large excess can build up — but here is the most important and most reassuring fact: vitamin E toxicity essentially never comes from food. You cannot eat enough almonds, sunflower seeds, or olive oil to harm yourself. The problem comes almost entirely from high-dose supplements — the 400, 800, or 1,000 international units (IU) softgels many people once took daily believing more was better. The danger is also not the classic "poisoning" picture of nausea and collapse. Instead, vitamin E in large amounts gently thins the blood: it interferes with the way platelets clump and with vitamin K–dependent clotting, so the real risks are easy bruising and bleeding, a small but measurable increase in the most dangerous kind of stroke (bleeding into the brain), and a magnified effect when it is taken alongside blood-thinning medicines like warfarin or aspirin. A 2005 pooled analysis of 19 trials (Miller and colleagues) linked high-dose vitamin E (400 international units a day or more) to a slightly higher overall death rate, noting that the high-dose trials were often small and done in people with chronic diseases; a larger 2011 pooled analysis of 57 trials (Abner and colleagues) found no effect on overall deaths at doses up to 5,500 international units a day. None of this means a normal multivitamin or a vitamin-rich diet is dangerous — the harms in the research come from the old "megadose" habit. This hub explains what counts as too much, why the harm centers on bleeding, why it is usually silent until something goes wrong, and how it is managed, with deep-dive pages on each major risk. The official upper limit (U.S. Institute of Medicine) is 1,000 mg a day of supplemental alpha-tocopherol, set because of the increased tendency to bleed; in a 2004 study, 1,000 international units a day for 12 weeks raised PIVKA-II, a blood marker of poor vitamin K status, in adults who were not taking blood thinners.
Symptom Deep-Dive Pages
Bleeding & Bruising
The most common sign of too much vitamin E — how it impairs platelet clumping and clotting, why bruises appear easily or gums and nose bleed, and when this points to your supplement rather than something else.
Read the deep dive →Hemorrhagic Stroke Risk
The most serious concern — what large trials found about high-dose vitamin E and bleeding into the brain, how big the risk really is, and why this stroke signal is the strongest concern about megadoses.
Read the deep dive →Blood-Thinner Interactions
Why vitamin E and medicines like warfarin, aspirin, or clopidogrel are a risky combination, how the effects stack, and what is known for people who take both.
Read the deep dive →Table of Contents
What Is Vitamin E Toxicity?
Vitamin E is the name for a family of eight fat-soluble compounds (four tocopherols and four tocotrienols); the form your body holds onto and the one used in most supplements is alpha-tocopherol. Because it dissolves in fat rather than water, vitamin E is stored in your liver and fatty tissues and is not rapidly excreted in urine the way vitamin C or the B vitamins are. That storage is exactly why a sustained excess is even possible — and why the vitamins most likely to build up to harmful levels are the fat-soluble ones (A, D, E, and K).
That said, the word "toxicity" can be misleading here. Vitamin E does not cause a dramatic acute poisoning. What it causes, at high enough doses over time, is a measurable tendency to bleed — and, in pooled analyses of large trials, a small increase in the risk of suffering a bleeding stroke and, in one of two large analyses, of dying from any cause. So "vitamin E toxicity" really means the harms of chronic high-dose supplementation, not a single dangerous meal.
To make sense of "too much," it helps to know the reference amounts. The numbers below describe alpha-tocopherol, the active form:
- Recommended Dietary Allowance (RDA): about 15 mg/day for adults (roughly 22 international units of natural vitamin E, or 33 international units of the synthetic form). This is the everyday target, easily met by a normal diet.
- Tolerable Upper Intake Level (UL): 1,000 mg/day of supplemental alpha-tocopherol for adults — equal to about 1,500 international units of natural or 1,100 international units of synthetic vitamin E. The Tolerable Upper Intake Level is the ceiling that the U.S. Food and Nutrition Board judged unlikely to cause harm; it was set specifically because of the bleeding risk seen at high intakes.
- The gap is enormous. The Tolerable Upper Intake Level is more than 60 times the Recommended Dietary Allowance. That wide margin is one reason food can never get you into trouble — but it also lulled people into thinking megadose softgels were harmless, which the evidence below challenges.
One nuance worth holding onto: the Tolerable Upper Intake Level is a regulatory ceiling, not a fully reassuring "safe" line. A 2005 pooled analysis of 19 trials (Miller and colleagues) found a small increase in all-cause mortality at supplement doses of 400 international units a day or more — a range that includes doses below the Tolerable Upper Intake Level. The authors describe earlier high-dose trials as showing increases that were not statistically significant on their own, and note that the high-dose trials were often small and done in people with chronic diseases, so how far the finding applies to healthy adults is uncertain; a 2011 pooled analysis of 57 trials (Abner and colleagues) found no effect on all-cause mortality and no link between dose and risk. Taken together, the large trials cited below did not find the hoped-for protection against heart disease or cancer, and they show some signals of harm.
Why Too Much Vitamin E Is Dangerous
If a normal amount of vitamin E is helpful and even a large amount rarely makes you feel sick, why is excess taken seriously? The answer comes down to one theme: bleeding. High-dose vitamin E gently interferes with the body's ability to form clots, and from that single mechanism flow nearly all of its recognized harms.
There are two complementary reasons vitamin E thins the blood, and it helps to picture clotting as a two-part system. The first part is the platelets — tiny cell fragments that rush to a wound and stick together to form the initial plug. The second part is the clotting cascade, a chain of proteins (several of which depend on vitamin K) that reinforces that plug into a stable clot. Vitamin E, in large amounts, dampens both:
- It makes platelets less sticky. Alpha-tocopherol reduces platelet aggregation — the clumping step — so the first plug forms less readily. This is the same kind of effect (though milder) that aspirin produces, which is why the two add together.
- It works against vitamin K. This is the more specific and elegant mechanism. Inside the body, vitamin E can be converted to a compound called tocopheryl quinone, whose shape resembles vitamin K. It can interfere with the vitamin K–dependent enzymes that activate clotting factors II, VII, IX, and X — in effect acting as a mild vitamin K antagonist, the same general lever that the drug warfarin pulls. Laboratory work has shown this quinone has genuine anticlotting activity, and human studies have measured small reductions in vitamin K–dependent clotting markers in people taking high-dose vitamin E.
From this one bleeding tendency, the three concrete dangers follow:
- Easy bruising and bleeding. The most common and visible sign — bruises from minor knocks, bleeding gums, nosebleeds, or bleeding that is slow to stop. This is covered in depth on the Bleeding & Bruising page.
- Hemorrhagic (bleeding) stroke. The most serious concern. A bleeding tendency in the brain's small vessels can, in a small number of people, tip the balance toward a hemorrhagic stroke. A 2010 meta-analysis of nine trials (Schürks and colleagues, about 119,000 people) found that vitamin E raised the risk of this specific (and especially deadly) stroke type by 22% (relative risk 1.22), while it lowered the risk of the more common clot-type (ischemic) stroke by 10% (relative risk 0.90); the vitamin E dose did not explain the differences between trials. In the ATBC trial of male smokers, a modest 50 mg a day of alpha-tocopherol was linked to 50% more bleeding strokes around the brain (subarachnoid hemorrhage, a result just short of statistical significance), 181% more fatal ones, and 14% fewer clot-type strokes (cerebral infarction). The Hemorrhagic Stroke Risk page lays out exactly what the studies found and how large the risk really is.
- Amplified blood thinners. Because vitamin E thins the blood on its own, adding it to a prescribed blood thinner — warfarin, aspirin, clopidogrel, or the newer direct oral anticoagulants — can push the combined effect into dangerous territory, raising the risk of a serious bleed. See Blood-Thinner Interactions.
One honest caveat about scale: for a healthy person taking a normal multivitamin, none of this is a meaningful worry — the bleeding effect is dose-dependent and is mainly seen at high supplemental doses, or at lower doses when combined with another blood thinner, although the ATBC stroke result above came from 50 mg a day. The danger is real, but it is a danger of megadosing, not of vitamin E itself.
Why It Is Usually Silent
Like many vitamin and electrolyte problems, an excess of vitamin E rarely announces itself. There is no number on a routine panel that doctors watch for vitamin E, no characteristic feeling of being "over-dosed," and often no symptom at all until a bleeding event reveals the problem. A person can take 800 international units a day for years and feel completely normal, while their blood is quietly a little slower to clot than it should be.
Why so quiet? Because the body's clotting system has reserve. A mild, vitamin-E–induced reduction in platelet stickiness and clotting-factor activity usually does not matter day to day — small cuts still stop, and life goes on. The effect only becomes visible when it is unmasked: by a fall or surgery that calls on the clotting system, by another blood thinner that pushes the total effect over the edge, or by the rare but catastrophic event of a brain bleed. In other words, the calm is real, but it is not the same as safety — the margin for error has narrowed without any warning sensation.
This silence is why protection against vitamin E excess is preventive rather than symptom-driven: the body gives no signal that vitamin E intake is too high, so what matters is knowing what is taken and why:
- Supplement labels add up. Vitamin E can come from several sources at once — a standalone vitamin E softgel, a multivitamin, and any "antioxidant," "heart," "eye health," or "anti-aging" formula can each contain it. Doses are often listed in international units; the Tolerable Upper Intake Level of 1,000 mg corresponds to roughly 1,500 international units natural / 1,100 international units synthetic.
- Surgery, dental work and blood thinners. High-dose vitamin E changes bleeding risk, which matters to surgeons, dentists, and anyone prescribing a blood thinner. It is commonly stopped before surgery.
- People already on a blood thinner — this is the setting where a "silent" vitamin E effect most often turns into a real bleed.
The take-home is the opposite of reassuring quiet: feeling fine is not evidence that a high-dose habit is safe. With vitamin E, the dose on the bottle tells you more than how you feel.
What Causes Vitamin E Excess
Vitamin E excess has, in practice, essentially one cause: supplements. Unlike many minerals, there is no common medical condition or hormone problem that pushes vitamin E up on its own. Here is what actually drives high intake, from most to least relevant.
- High-dose single-vitamin supplements — the number-one cause. For decades vitamin E was marketed as a heart-protective, anti-aging antioxidant, and softgels of 400, 800, even 1,000 international units were taken daily by millions. A single 1,000 international units capsule already approaches or exceeds the Tolerable Upper Intake Level, and these were often taken on top of other sources. This megadose habit — not diet — is the origin of nearly every documented harm.
- Stacking from multiple products. A surprisingly common, hidden route. Vitamin E turns up in multivitamins, "antioxidant complexes," combined eye-health formulas (such as some macular-degeneration blends), skin and hair supplements, and heart formulas. Someone taking several of these can unknowingly add up to a large daily total even without a dedicated high-dose E capsule.
- The mistaken belief that "more is better." Because vitamin E is an antioxidant and antioxidants sound healthy, people have assumed that large doses must be extra-protective. The large trials summarized below did not support this: vitamin E supplements did not deliver the hoped-for protection against heart disease or cancer; one pooled analysis linked high doses to a small increase in deaths (a larger later analysis did not), and a stroke meta-analysis found more hemorrhagic strokes. Two trials found further harms: in the SELECT trial, 400 international units a day raised the risk of prostate cancer in healthy men by 17% (hazard ratio 1.17), and in the HOPE-TOO trial, 400 international units a day in people with vascular disease or diabetes raised the risk of heart failure by 13% (relative risk 1.13) and of hospital stays for heart failure by 21%.
- Food — essentially never a cause. This is the crucial reassurance. Vitamin E–rich whole foods — almonds, sunflower seeds, hazelnuts, peanuts, wheat germ, spinach and other greens, avocado, and vegetable oils — provide modest amounts (a generous handful of almonds gives only around 7–8 mg, about half a day's Recommended Dietary Allowance). There is no realistic way to eat enough to reach toxic intakes. A diet rich in these foods is healthy and carries none of the supplement risks; see Vitamin E Food Sources, Almonds, and Spinach.
- Topical vitamin E — not a source of internal excess. Vitamin E oil applied to skin (a common skin-care ingredient) is not absorbed in amounts that affect the whole body, so it does not contribute to systemic toxicity. Its main downside is the occasional skin allergy.
The pattern is the opposite of vitamins where diet and disease drive the level: with vitamin E, the question to ask is never "what is my body doing?" but simply "how much am I swallowing, from how many bottles?"
How It Is Diagnosed
There is no routine, widely ordered blood test that screens for vitamin E excess the way a metabolic panel screens for potassium or calcium. A serum alpha-tocopherol level can be measured, but it is a specialized test used mainly to investigate deficiency (or rare fat-absorption disorders), and it correlates poorly with the bleeding risk that actually matters at high intakes. In real life, vitamin E excess is recognized not by a lab number but by putting the pieces together: a high-dose supplement habit plus a bleeding tendency.
The practical diagnostic path looks like this:
- The medication and supplement history is the key step. When someone presents with unexplained bruising, frequent nosebleeds, bleeding gums, or a more serious bleed, a careful clinician asks specifically about all supplements — including the ones people forget to mention because they seem harmless. Discovering 800 or 1,000 international units of vitamin E daily, or several products that each contain it, often explains the picture.
- Coagulation testing measures the effect, not the vitamin. Rather than measuring vitamin E itself, doctors assess how the blood is clotting. A coagulation panel — including prothrombin time (PT) and its standardized version, the international normalized ratio (INR) — can reveal a prolonged clotting time, reflecting the vitamin K–dependent effect. This is especially important in anyone taking warfarin, where vitamin E can push the international normalized ratio higher. See the Coagulation Panel page for what PT/INR mean.
- A confirmatory clue: the problem improves when the supplement stops. Because vitamin E is not a drug with a precise antidote, one of the most telling signs is that an unexplained bleeding tendency resolves over days to weeks after high-dose vitamin E is discontinued (sometimes helped along by vitamin K). A bleeding tendency that clears after stopping the supplement strongly implicates it.
- Ruling out other causes. Bleeding and bruising have many explanations — other medications (aspirin, anticoagulants), liver disease, low platelets, vitamin K deficiency, and inherited clotting disorders among them. Part of diagnosis is making sure vitamin E is the cause and not a coincidence, which is why the full picture (dose, timing, other drugs, and clotting tests) matters more than any single result.
The bottom line: a "vitamin E level" is usually not the answer. The diagnosis is usually clinical — a high-dose habit plus a bleeding problem, supported by clotting tests — and the most useful single action is often simply a careful review of everything a person is taking.
How Vitamin E Excess Is Managed
The good news is that managing vitamin E excess is usually straightforward, because the body slowly clears stored vitamin E once the intake stops, and the bleeding effect is reversible. The cornerstone is simple: stopping the source.
- Stopping the high-dose supplement. This is the central step in managing vitamin E excess — the large trials cited below did not find the hoped-for protection against heart disease or cancer from high-dose vitamin E. It means stopping the dedicated softgel and counting every other product (multivitamins, antioxidant blends, eye-health formulas) so the total intake drops to ordinary dietary levels. Because vitamin E is fat-soluble and stored, the bleeding tendency eases over days to a few weeks rather than instantly, as tissue stores fall.
- Active bleeding. Minor issues (the occasional bruise or nosebleed) usually need nothing more than stopping the supplement and ordinary first aid. A significant or ongoing bleed is treated on its own merits, in a medical setting.
- Vitamin K when clotting is impaired. Because much of vitamin E's effect works against vitamin K, giving vitamin K can help restore normal clotting — particularly when the PT/INR is prolonged or bleeding is significant. It is especially delicate in people taking warfarin, whose entire treatment is built around blocking vitamin K: vitamin K is what is given to reverse warfarin, so it also weakens the drug's protection against clots.
- Blood thinners. For someone on warfarin, aspirin, clopidogrel, or a direct oral anticoagulant, both starting and stopping high-dose vitamin E can shift bleeding risk; in warfarin users the shift shows up in the international normalized ratio (INR, the clotting blood test). The Institute of Medicine notes that its upper limit applies to people who get enough vitamin K, that people who lack vitamin K or are on anticoagulant drugs are at increased risk of clotting problems, and that people on anticoagulant therapy are monitored when they take vitamin E supplements. The Blood-Thinner Interactions page covers this in detail.
- Surgery and dental work. High-dose vitamin E is commonly stopped a couple of weeks before planned procedures to reduce bleeding risk, which is why surgeons, anesthetists, and dentists ask about supplements.
Dramatic intervention is generally not needed: there is no dialysis or chelation for vitamin E. The contrast with the Deficiency side is instructive — there the goal is to raise intake, here it is simply to lower it back to what food provides. For most people, stopping the megadose and eating a normal, vitamin-E–rich diet is the entire treatment.
When to Seek Care / Red Flags
Because vitamin E excess is usually silent, the most useful "red flag" is often a situation rather than a feeling: high-dose vitamin E taken together with a blood thinner is the setting where the bleeding risks above stack, even when a person feels completely well. Beyond that, certain symptoms mean bleeding may be a genuine problem. These are signs of serious or brain bleeding that hospitals treat as emergencies:
- A sudden, severe "thunderclap" headache, the worst of your life — a possible sign of bleeding in or around the brain.
- Sudden weakness or numbness on one side, trouble speaking, vision loss, confusion, or loss of coordination — warning signs of a stroke, including the hemorrhagic (bleeding) type; a stroke is a medical emergency in which every minute counts.
- Bleeding that will not stop, or a large/expanding bruise after a minor injury.
- Blood in the stool (red or black, tarry) or vomit (red or coffee-ground colored), or coughing or vomiting blood — possible internal bleeding.
- Pink, red, or brown urine, or unusually heavy menstrual bleeding.
Less urgent, but still signs that clotting is affected, are easy or unexplained bruising, frequent nosebleeds, or bleeding gums that are new — particularly in someone who takes high-dose vitamin E, is on any blood thinner, or has a procedure coming up. People at higher risk — anyone combining vitamin E with warfarin, aspirin, clopidogrel, or a direct oral anticoagulant, those with liver disease or a known clotting disorder, and anyone scheduled for surgery — are the people in whom a quiet bleeding tendency is most likely to become a real bleed. For the broader stroke picture, see Stroke.
Key Research Papers
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, Riemersma RA, Appel LJ, Guallar E (2005). Meta-Analysis: High-Dosage Vitamin E Supplementation May Increase All-Cause Mortality. Annals of Internal Medicine;142(1):37-46. — DOI: 10.7326/0003-4819-142-1-200501040-00110. — doi:10.7326/0003-4819-142-1-200501040-00110
- Abner EL, Schmitt FA, Mendiondo MS, Marcum JL, Kryscio RJ (2011). Vitamin E and All-Cause Mortality: A Meta-Analysis. Current Aging Science;4(2):158-170. — DOI: 10.2174/1874609811104020158. — doi:10.2174/1874609811104020158
- Bjelakovic G, Nikolova D, Gluud LL, Simonetti RG, Gluud C (2012). Antioxidant supplements for prevention of mortality in healthy participants and patients with various diseases. Cochrane Database of Systematic Reviews;(3):CD007176. — DOI: 10.1002/14651858.CD007176.pub2. — doi:10.1002/14651858.CD007176.pub2
- Sesso HD, Buring JE, Christen WG, et al. (2008). Vitamins E and C in the Prevention of Cardiovascular Disease in Men: The Physicians' Health Study II Randomized Controlled Trial. JAMA;300(18):2123-2133. — DOI: 10.1001/jama.2008.600. — doi:10.1001/jama.2008.600
- Lonn E, Bosch J, Yusuf S, et al. (HOPE and HOPE-TOO Trial Investigators) (2005). Effects of Long-term Vitamin E Supplementation on Cardiovascular Events and Cancer. JAMA;293(11):1338-1347. — DOI: 10.1001/jama.293.11.1338. — doi:10.1001/jama.293.11.1338
- Schürks M, Glynn RJ, Rist PM, Tzourio C, Kurth T (2010). Effects of vitamin E on stroke subtypes: meta-analysis of randomised controlled trials. BMJ;341:c5702. — DOI: 10.1136/bmj.c5702. — doi:10.1136/bmj.c5702
- Leppälä JM, Virtamo J, Fogelholm R, et al. (2000). Controlled Trial of Alpha-Tocopherol and Beta-Carotene Supplements on Stroke Incidence and Mortality in Male Smokers. Arteriosclerosis, Thrombosis, and Vascular Biology;20(1):230-235. — DOI: 10.1161/01.ATV.20.1.230. — doi:10.1161/01.ATV.20.1.230
- Klein EA, Thompson IM Jr, Tangen CM, et al. (2011). Vitamin E and the Risk of Prostate Cancer: The Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA;306(14):1549-1556. — DOI: 10.1001/jama.2011.1437. — doi:10.1001/jama.2011.1437
- Booth SL, Golly I, Sacheck JM, et al. (2004). Effect of vitamin E supplementation on vitamin K status in adults with normal coagulation status. American Journal of Clinical Nutrition;80(1):143-148. — DOI: 10.1093/ajcn/80.1.143. — doi:10.1093/ajcn/80.1.143
- Dowd P, Zheng ZB (1995). On the mechanism of the anticlotting action of vitamin E quinone. Proceedings of the National Academy of Sciences;92(18):8171-8175. — DOI: 10.1073/pnas.92.18.8171. — doi:10.1073/pnas.92.18.8171
- Traber MG (2014). Vitamin E Inadequacy in Humans: Causes and Consequences. Advances in Nutrition;5(5):503-514. — DOI: 10.3945/an.114.006254. — doi:10.3945/an.114.006254
- Corrigan JJ Jr, Marcus FI (1974). Coagulopathy associated with vitamin E ingestion (a classic case of warfarin potentiation by high-dose vitamin E). JAMA;230(9):1300-1301. — PubMed PMID: 4479598
PubMed Topic Searches
- PubMed: High-dose vitamin E supplementation and all-cause mortality
- PubMed: Vitamin E and hemorrhagic stroke risk
- PubMed: Vitamin E, warfarin, and anticoagulant interaction
- PubMed: Vitamin E, platelet aggregation, and vitamin K–dependent clotting
- PubMed: Alpha-tocopherol upper intake level and toxicity
Connections
- All Vitamins
- Vitamin E Toxicity: Bleeding & Bruising
- Vitamin E Toxicity: Hemorrhagic Stroke Risk
- Vitamin E Toxicity: Blood-Thinner Interactions
- Vitamin E Overview
- Vitamin E Deficiency Hub
- Vitamin E Benefits Hub
- Vitamin E Food Sources
- Vitamin K
- Vitamin K2
- Coagulation Panel (PT / INR)
- Stroke
- Almonds
- Spinach
- Olive Oil
- Wheat Germ Oil